Posterior Capsulodesis and Infraspinatus Tenodesis | Engaging Hill-Sachs Lesion | Anterior Instability
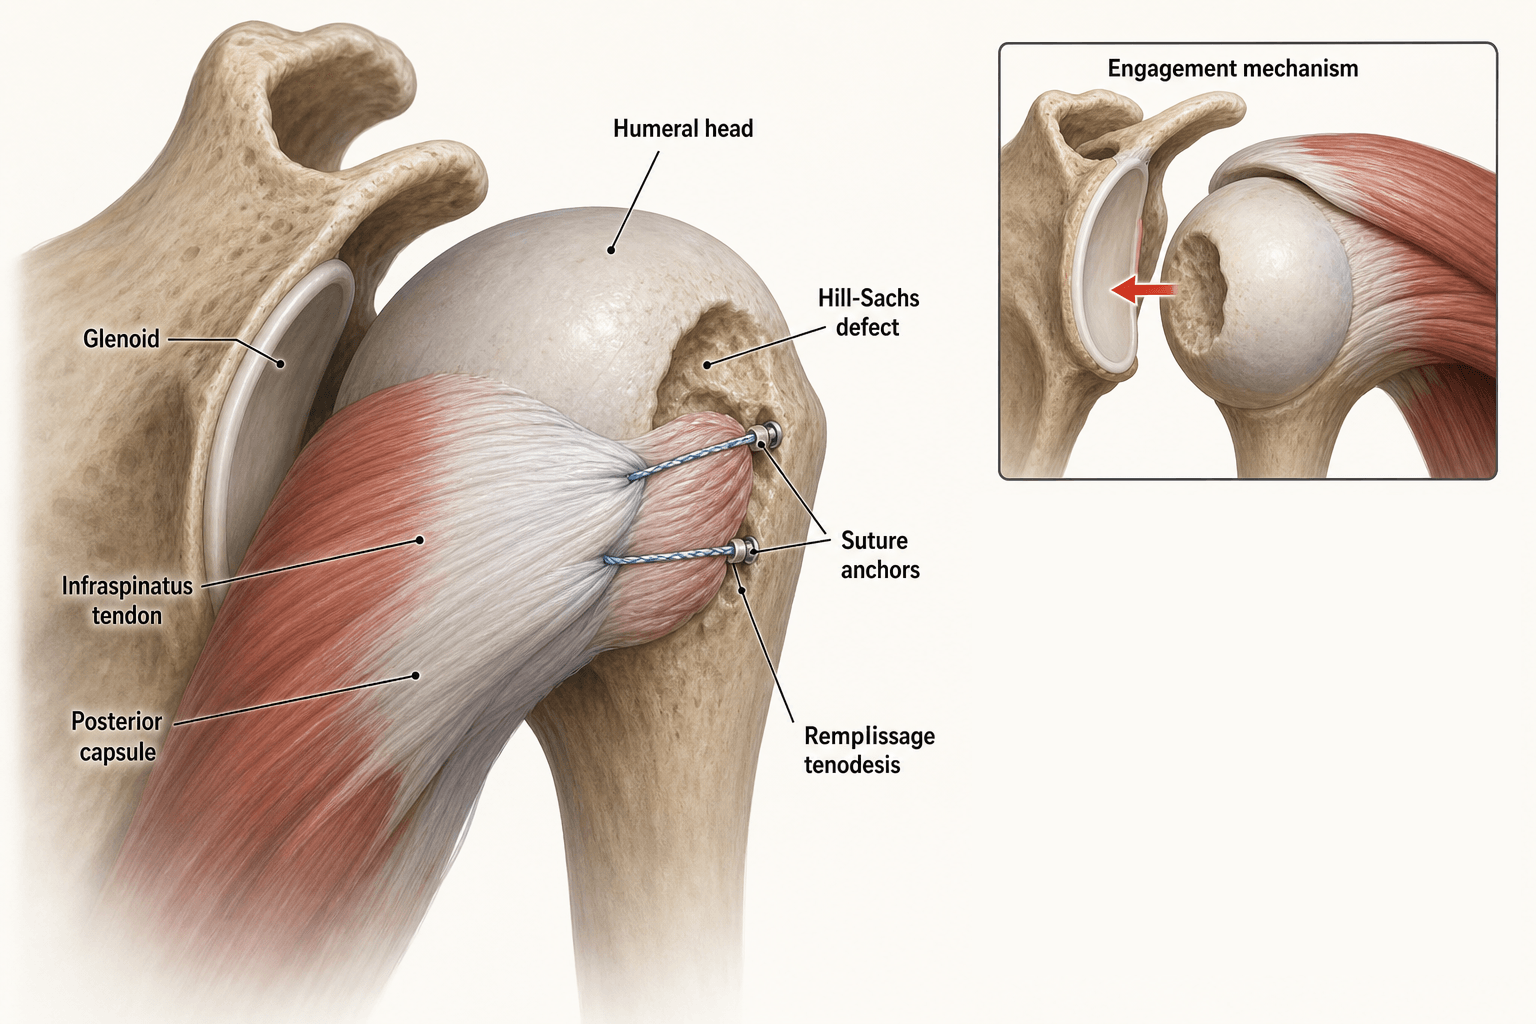
- Remplissage = arthroscopic posterior capsulodesis and infraspinatus tenodesis into Hill-Sachs defect
- Converts engaging intra-articular Hill-Sachs into non-engaging extra-articular lesion
- Indicated when glenoid track width is less than Hill-Sachs interval (off-track lesion)
- Combined with anterior Bankart repair in the same procedure
- Main trade-off: postoperative loss of external rotation (typically 8-14 degrees)
- “Glenoid track = 0.84 multiplied by (glenoid width minus anterior rim bone loss)
- “An engaging Hill-Sachs lesion is one that contacts the anterior glenoid rim in arm abduction and external rotation
- “Remplissage is contraindicated as a stand-alone procedure without Bankart repair
- “Stiffness is the primary complication; counsel patients preoperatively about external rotation loss
Overview and Epidemiology
The operation. Remplissage is an arthroscopic posterior capsulodesis and infraspinatus tenodesis into the Hill-Sachs defect, done with an anterior Bankart repair in the same procedure. It converts an engaging, intra-articular Hill-Sachs lesion into a non-engaging, extra-articular one, and so deals with the humeral side of bipolar bone loss arthroscopically, without open bone grafting.
Why it matters. Off-track, engaging Hill-Sachs lesions are a major cause of recurrent instability after isolated Bankart repair. Until the glenoid track concept arrived, surgeons struggled to decide when a Hill-Sachs lesion was clinically significant. Remplissage, one of the most significant advances in arthroscopic shoulder instability surgery of the past two decades, dramatically reduces recurrence in these shoulders.
How common the lesion is. A Hill-Sachs lesion is present in 40-90% of anterior shoulder dislocations. After a first-time dislocation it is visible on a plain AP in 40-70% and on CT in up to 90%; with recurrent instability the prevalence approaches 100%, and the lesions are larger and more engaging.
Bipolar bone loss. A Hill-Sachs lesion combined with a glenoid defect is present in up to 50% of revision cases.
Pathophysiology
How the lesion forms. When the shoulder dislocates anteriorly, the posterosuperior humeral head impacts the anterior glenoid rim and sustains a compression fracture, the Hill-Sachs lesion. The position of the arm at the moment of impact, typically abduction and external rotation, determines the orientation of the defect.
Engagement. A lesion is engaging when, in abduction and external rotation, the defect aligns with the anterior glenoid rim so that the rim falls within it. The rim then forms a bony barrier to concentric reduction and predisposes to recurrent dislocation. A small, non-engaging lesion is typically irrelevant; a large, engaging one drives recurrence despite labral repair. The glenoid track, described under Classification, quantifies this risk geometrically.
How remplissage works. The posterior capsule and infraspinatus are tenodesed into the defect and fill it, so the articular surface of the head bypasses the anterior rim instead of engaging it. The tethered infraspinatus also acts as a biological bumper, a posterior soft-tissue buttress resisting anterior translation. And the humeral head shifts medially: its effective radius in the remplissage zone decreases, which widens the functional glenoid track. The Bankart repair restores the anterior bumper; the remplissage prevents humeral engagement.
The exact mirror image of the remplissage problem occurs in posterior instability. A reverse Hill-Sachs (McLaughlin lesion) is an impaction fracture of the anteromedial humeral head, produced when the head locks against the posterior glenoid rim in a posterior dislocation; the classic causes are seizure, electric shock or major trauma, the "3 E's". An engaging reverse Hill-Sachs causes recurrent or locked posterior instability.
The classic trap is the locked posterior dislocation, the most commonly missed major joint dislocation. The AP looks deceptively normal ("light-bulb" sign, loss of the half-moon overlap), so get an axillary or CT view.
For a moderate reverse Hill-Sachs, roughly 20-40 percent, the McLaughlin procedure is the "posterior remplissage". The original transfers the subscapularis tendon into the defect; the modified McLaughlin (Neer) transfers the lesser tuberosity with the attached subscapularis. Either fills and extra-articularises the anteromedial defect exactly as the infraspinatus and capsule fill the posterosuperior Hill-Sachs in a remplissage. As on the anterior side, very large (over about 40 percent) reverse Hill-Sachs lesions or chronic locked dislocations need structural reconstruction (allograft, rotational osteotomy) or arthroplasty.
Classification and Types
The glenoid track. Itoi's on-track/off-track classification (2012) replaced the older percentage-based Hill-Sachs size classifications because it accounts for the interaction between humeral and glenoid bone loss rather than measuring the Hill-Sachs in isolation.
Two widths. The glenoid track is 0.84 multiplied by (glenoid width minus anterior rim bone loss). Normally it is 84 percent of glenoid width, approximately 23-25 mm for a 28-30 mm glenoid, and anterior glenoid bone loss narrows it. The Hill-Sachs interval is the Hill-Sachs width plus the bony bridge posterior to it.
On-track or off-track. When the glenoid track is greater than the Hill-Sachs interval the lesion is on-track and non-engaging. When the interval is greater than the track the lesion is off-track and engaging, and it is treated by remplissage with a Bankart repair, or by a Latarjet if the glenoid loss is large.
The older size grades. The percentage-based grading describes how much of the humeral head the defect occupies:
- Characteristics
- Small impression fracture, far from articular margin
- Engagement
- Non-engaging
- Clinical Significance
- No impact on surgical decision; Bankart repair alone
- Characteristics
- Larger defect, may approach articular margin
- Engagement
- May engage depending on glenoid track
- Clinical Significance
- Assess with glenoid track; remplissage if off-track
- Characteristics
- Extensive defect, occupies significant humeral head arc
- Engagement
- Engaging (off-track)
- Clinical Significance
- Remplissage cannot fill a defect this size; structural bone restoration with Latarjet plus humeral head allograft or hemiarthroplasty
Clinical Assessment
History. Establish the pattern of instability and what the patient needs the shoulder to do. Record the number of dislocations, their mechanism and direction, whether each was reduced by the patient or in hospital, and the arm position at the time, typically abduction and external rotation. Ask which positions apprehension makes the patient avoid, such as overhead throwing or reaching back.
Prior surgery and demands. A failed Bankart repair alone suggests significant bone loss. Note the sport and functional demands: overhead athletes, manual workers and contact athletes.
Examination. Test for instability and record a baseline.
- Apprehension test: anterior apprehension in abduction and external rotation
- Relocation test: a posterior force on the humeral head relieves the apprehension
- Sulcus sign: inferior laxity, associated with multidirectional instability
- Range of motion: document external and internal rotation before surgery, as the baseline for postoperative comparison
- Rotator cuff: infraspinatus strength, because remplissage affects this muscle
The glenoid track decides whether the Hill-Sachs needs addressing. The Instability Severity Index Score (Balg and Boileau) is the complementary preoperative tool: it predicts failure of an arthroscopic (Bankart +/- remplissage) repair and flags the patients who should go to a Latarjet or other bone procedure instead. It is a 10-point score from six preoperative factors, taken from the history, examination and plain radiographs:
- Age 20 or younger at surgery
- Participation in competitive sport
- Contact or overhead/forced-overhead sport
- Shoulder hyperlaxity
- A Hill-Sachs visible on an external-rotation AP radiograph
- Loss of the normal glenoid contour (sclerotic line/bone loss) on the AP
A score of more than 6 predicts an unacceptably high recurrence after arthroscopic Bankart repair, and such patients are better served by an open bone-block (Latarjet) procedure; 6 or below supports an arthroscopic approach. Use the two tools together. The track tells you the lesion is off-track and the Hill-Sachs needs filling; the ISIS tells you whether the overall risk profile is still safe for arthroscopic surgery at all, so an off-track lesion with a high ISIS pushes towards Latarjet rather than Bankart plus remplissage. It is the classic answer to "how do you decide arthroscopic versus open for recurrent anterior instability?"
Investigations
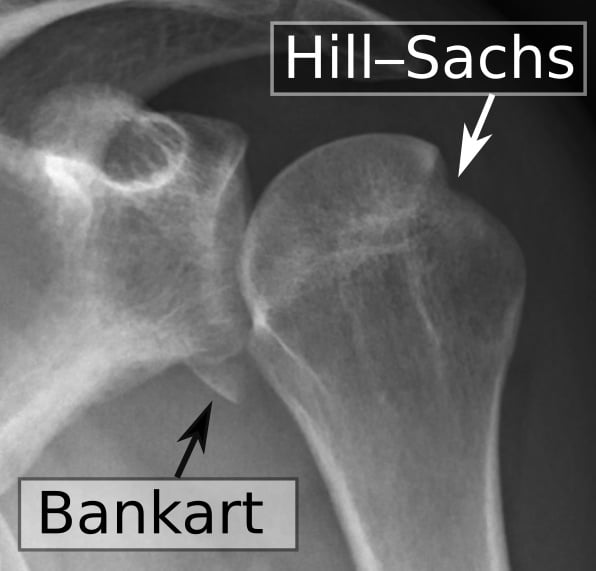
Radiographs. Plain films are the first line and the initial screen, but they underestimate bone loss by 20-50 percent compared with CT. Look for the Hill-Sachs lesion, the glenoid morphology, a bony Bankart fragment and, after a posterior dislocation, a reverse Hill-Sachs.
- True AP (Grashey) and Stryker notch: the Hill-Sachs lesion
- Axillary lateral: glenoid morphology; this view is essential
- Scapular lateral
- West Point axillary: anterior glenoid rim detail, good for anterior glenoid fractures and for assessing an acute bony Bankart
CT with 3D reconstruction. CT is the gold standard for quantifying bone loss and the mandatory investigation for recurrent instability and before deciding on remplissage. The whole decision rests on the glenoid track, and the measurements of glenoid and humeral bone loss it needs are unreliable on plain radiographs alone. Scan both shoulders in thin (1 mm) slices with 3D surface reconstructions in en face and rotated views; comparing the two sides on the same scan accounts for individual variation in glenoid size.
Taking the measurements.
- Glenoid bone loss. On the en face 3D reconstruction, fit a best-fit circle to the inferior glenoid and measure the width of the missing anterior rim; the defect can also be measured on sagittal CT. Bone loss (percent) is the defect width divided by the glenoid diameter, multiplied by 100. A normal inferior glenoid AP diameter is approximately 28-30 mm.
- Hill-Sachs. Measure its width, depth and orientation, and from them the Hill-Sachs interval.
- Glenoid track. Calculate it from the glenoid width and rim loss and compare it with the Hill-Sachs interval. An interval greater than the track is off-track, the threshold for remplissage.
MRI arthrogram. Complementary to CT. It shows the labral tear pattern, capsular laxity and the integrity of the rotator cuff, and earns its place when planning combined procedures or when SLAP, posterior labral or rotator cuff pathology is a concern. It is good for soft tissue and inferior for bone: MRI underestimates bone loss, so do not use it alone to decide on remplissage.
Do not plan surgery for recurrent instability without quantifying bone loss on both sides. At minimum, obtain an axillary lateral X-ray and a CT scan with 3D reconstruction, and calculate the glenoid track. Operating without bone loss assessment risks performing an isolated Bankart repair that fails in the presence of an off-track lesion.
Management Algorithm
The decision. Two measurements drive the choice: whether the Hill-Sachs is on or off the glenoid track, and how much anterior glenoid is missing. An on-track lesion needs a Bankart repair alone. An off-track lesion with glenoid loss under 20-25 percent needs a Bankart repair plus remplissage. Above that threshold large glenoid bone loss dominates the instability, and it needs a bony procedure (Latarjet, Eden-Hybinette or distal tibial allograft), because remplissage alone cannot compensate for the glenoid deficiency.
The grey zone. Between 10 and 25 percent glenoid loss the thresholds shade into each other. At 10-20 percent remplissage is suitable but borderline: it may be sufficient, though Latarjet is more robust once the loss is over 15-20 percent. At 20-25 percent remplissage is only marginally suitable and may be insufficient, and Latarjet may be safer as the loss approaches 25 percent.
- Glenoid Track
- On-track (glenoid track greater than Hill-Sachs interval)
- Procedure
- Bankart repair alone
- Key Decision
- No remplissage needed
- Glenoid Track
- Minimal track narrowing; glenoid loss too small to affect the track significantly
- Procedure
- Bankart + remplissage
- Key Decision
- Remplissage fills the Hill-Sachs; Bankart addresses the labrum
- Glenoid Track
- Moderate track narrowing
- Procedure
- Bankart + remplissage; Latarjet if borderline
- Key Decision
- Remplissage suitable but borderline; counsel on stiffness; Latarjet more robust if glenoid loss over 15-20 percent
- Glenoid Track
- Significant track narrowing
- Procedure
- Strongly consider Latarjet or bone graft
- Key Decision
- Remplissage marginally suitable and may be insufficient; Latarjet may be safer if glenoid loss approaching 25 percent
- Glenoid Track
- Critical: track severely compromised and cannot be calculated reliably
- Procedure
- Latarjet or glenoid bone graft required
- Key Decision
- Remplissage contraindicated as primary solution; Latarjet restores glenoid arc length and provides an anterior bone block
On-track lesions. When the glenoid track is greater than or equal to the Hill-Sachs interval, the lesion is non-engaging and an arthroscopic anterior Bankart repair with suture anchors is the whole operation. Restoring the anterior labral bumper prevents the head from translating far enough anteriorly for the Hill-Sachs to contact the glenoid rim, so no humeral-side procedure is needed.
Off-track lesions. When the track is less than the interval and glenoid bone loss is under 20-25 percent, add a posterior capsulodesis and infraspinatus tenodesis into the Hill-Sachs defect to the arthroscopic Bankart repair. Contraindications:
- Isolated remplissage without Bankart repair (insufficient stability)
- Glenoid bone loss greater than 25 percent (Latarjet preferred)
- Active infection
- Severe shoulder arthritis
Surgical Technique
Setup. Lateral decubitus is preferred for remplissage because it gives superior posterior access; beach chair is also described. Apply lateral traction with 10 degrees of abduction and 20 degrees of forward flexion. Four portals are used: posterior viewing, anterior working, anterosuperior (Wilmington) for the Bankart anchors, and a posterolateral accessory portal for remplissage anchor placement.
Diagnostic arthroscopy. Inspect the labral tear pattern (Bankart, ALPSA, Perthes), the capsular laxity and the size of the Hill-Sachs. Confirm off-track engagement dynamically, bringing the arm into abduction and external rotation to engage the Hill-Sachs against the anterior glenoid under vision, and estimate its dimensions with a probe to correlate with the CT.
The Bankart repair. Debride the labral edge to bleeding bone on the glenoid neck. Place 3-4 suture anchors along the anterior glenoid rim from inferior up to the 4-5 o'clock position, pass the sutures through the labrum with suture shuttles, and shift the labrum medially to restore the bumper effect. Add side-to-side capsular plication stitches if there is capsular laxity, then check that the repair restores anterior stability before moving to the posterior aspect.
Always perform the Bankart repair before the remplissage. If remplissage is done first, it may tether the posterior humeral head and alter the arthroscopic view, making anterior labral repair more difficult. The Bankart is the primary stabiliser; the remplissage augments it for the engaging Hill-Sachs and does not replace it.
The remplissage.
- Prepare the defect. Switch to the posterior or posterolateral portal to view the Hill-Sachs. Remove fibrous tissue and sclerotic bone from its floor with a curette or shaver down to bleeding cancellous bone, across the whole surface that will receive the capsular tethers.
- Insert the anchors. Place 2-3 double-loaded suture anchors (bioabsorbable or metallic, 4.5-5.5 mm) in the floor of the defect at the posteromedial humeral head, spaced along its long axis. They must be intra-defect only: do not penetrate the articular surface outside the Hill-Sachs.
- Pass the sutures. Through the posterolateral portal, use a suture hook or penetrating grasper to retrieve the sutures and pass them through the posterior capsule (including the posterior labrum if present) in a mattress or simple configuration, then through the infraspinatus footprint. The infraspinatus is tenodesed, not detached and repaired: the tendon stays attached at its insertion and is pulled into the defect with the capsule.
- Tie and check. Secure all knots, pulling capsule and infraspinatus into the defect. Viewed from the anterior portal, the defect should be filled with capsule and tendon, confirming extra-articularisation, and with the shoulder in abduction and external rotation the Hill-Sachs should no longer engage the anterior glenoid rim. Finally, make sure the Bankart repair is intact and the remplissage tissue well seated.
FILLRemplissage Surgical Steps
Hook:FILL the defect with capsule and infraspinatus to prevent engagement!
Rehabilitation. A sling is worn for 4-6 weeks, with a small abduction pillow optional, and motion is restored in stages.
- Weeks 0-3: passive forward flexion and internal rotation only; no external rotation beyond neutral, which protects both the Bankart and the remplissage
- Weeks 3-6: active assisted forward flexion and internal rotation; begin gentle passive external rotation to 30 degrees
- Weeks 6-12: progressive active range of motion; restore external rotation gradually, with no forced external rotation beyond a comfortable limit
- Weeks 12-24: strengthening, proprioceptive training and a gradual return to sport
- Contact sport: a minimum of 6-9 months, once full strength and functional stability are confirmed
After an isolated Bankart repair the sling is also worn for 4-6 weeks, with no passive external rotation beyond neutral for 3 weeks. Active assisted motion starts at week 3, avoiding external rotation beyond 30 degrees for 6 weeks; strengthening starts at 6-8 weeks, and return to contact sport is at 6-9 months.
Complications
Loss of external rotation is the expected trade-off of remplissage and the accepted cost of stability. Most patients lose 8-14 degrees, compensate functionally and return to sport, but overhead athletes (throwers, volleyball, racquet sports) may be unable to return to their pre-injury performance level, and anyone requiring full external rotation should be counselled carefully. A thorough preoperative discussion about the stiffness-stability trade-off is mandatory. For patients who cannot accept ER loss, Latarjet may be the better procedure.
- Incidence
- 8-14 degrees mean; up to 20-30 degrees in some series
- Risk Factors
- Large remplissage surface area, aggressive capsular plication
- Management
- Physiotherapy; MUA if refractory at 6-12 months; counsel preoperatively
- Incidence
- 4-17 percent at 2-10 years
- Risk Factors
- Large glenoid bone loss, inadequate remplissage, hyperlaxity, early return to sport
- Management
- Revision with Latarjet or glenoid bone graft; assess bone loss again on CT
- Incidence
- Rare
- Risk Factors
- Malpositioned anchors outside Hill-Sachs defect, anchor loosening
- Management
- Arthroscopic removal if symptomatic; careful anchor placement prevents
- Incidence
- Low incidence but reported
- Risk Factors
- Over-tensioning of infraspinatus tenodesis, aggressive postoperative ER
- Management
- Repair if tendon rupture; rehabilitation for weakness
- Incidence
- Up to 10-20 percent in early recovery
- Risk Factors
- Posterior capsule irritation, remplissage inflammation
- Management
- NSAIDs, physiotherapy; usually resolves by 3-6 months
Outcomes and Prognosis
- Procedure
- Isolated Bankart repair
- Recurrence Rate
- 5-10 percent at 2-5 years
- Functional Outcome
- Good to excellent (Rowe 85-95)
- External Rotation Loss
- Minimal (less than 5 degrees)
- Procedure
- Bankart + remplissage
- Recurrence Rate
- 4-8 percent at 2-5 years
- Functional Outcome
- Good to excellent (Rowe 80-90)
- External Rotation Loss
- 8-14 degrees mean
- Procedure
- Bankart + remplissage or Latarjet
- Recurrence Rate
- 8-17 percent (remplissage); 2-5 percent (Latarjet)
- Functional Outcome
- Moderate to good
- External Rotation Loss
- 8-14 degrees (remplissage); variable (Latarjet)
- Procedure
- Latarjet or glenoid bone graft
- Recurrence Rate
- 2-10 percent at 5-10 years
- Functional Outcome
- Good (Latarjet)
- External Rotation Loss
- Variable; subscapularis function key
What predicts a good result. The best prognosis belongs to an off-track Hill-Sachs with minimal glenoid bone loss (under 10 percent), a first or second dislocation, compliant rehabilitation and avoidance of contact sport during recovery. The prognosis is poorer with multiple recurrences, hyperlaxity, an early return to contact sport, inadequate remplissage coverage, and glenoid bone loss over 15-20 percent treated with remplissage alone. An external rotation loss over 20 degrees may be functionally limiting for overhead athletes.
Guidelines, Registries and Global Practice
- Anterior shoulder instability affects 1-2 percent of the general population
- Hill-Sachs lesions are present in 40-90 percent of first-time dislocations (higher with imaging sensitivity)
- Engaging Hill-Sachs requiring remplissage is estimated in 10-20 percent of operative instability cases
- Bipolar bone loss (combined Hill-Sachs and glenoid defect) is a significant predictor of recurrence after isolated Bankart repair
- High-resource centres: Routine 3D CT for bone loss quantification; arthroscopic remplissage as standard for off-track lesions with small glenoid loss
- Limited-resource settings: CT may not be available; clinical judgement and plain radiographs used; decision to use remplissage may be intraoperative based on arthroscopic engagement testing
- Global trend: Arthroscopic remplissage has largely replaced open humeral plasty or partial humeral head resurfacing for engaging Hill-Sachs
- Remplissage Indication
- Off-track Hill-Sachs with glenoid loss less than 20-25 percent; combined with Bankart
- Bone Loss Assessment
- 3D CT recommended; glenoid track method preferred
- Alternative when Remplissage Insufficient
- Latarjet for glenoid loss over 20-25 percent or large engaging Hill-Sachs with failed remplissage
- Remplissage Indication
- Remplissage is an accepted arthroscopic option for off-track lesions
- Bone Loss Assessment
- CT with 3D reconstruction standard; proportion method or glenoid track method
- Alternative when Remplissage Insufficient
- Latarjet or Eden-Hybinette bone block for significant glenoid deficiency
- Remplissage Indication
- Part of the algorithm for bipolar bone loss; humeral-side bone loss addressed with remplissage when glenoid loss is small
- Bone Loss Assessment
- Precise CT measurement of both sides; 25 percent glenoid loss as key threshold
- Alternative when Remplissage Insufficient
- Coracoid transfer (Latarjet) or iliac crest bone graft for glenoid deficiency
- Remplissage Indication
- Remplissage included in instability guidelines for engaging Hill-Sachs; counsel on stiffness trade-off
- Bone Loss Assessment
- 3D CT where available; proportion method accepted
- Alternative when Remplissage Insufficient
- Latarjet as primary option for large glenoid defects or contact athletes
Shoulder instability registries (such as the Norwegian Shoulder Instability Registry and the Danish Shoulder Arthroscopy Registry) track Bankart and Latarjet procedures but do not yet consistently separate remplissage cases as a distinct category. The evidence base for remplissage is predominantly level 4 (retrospective case series) with no published randomised controlled trials comparing Bankart plus remplissage versus Latarjet for off-track bipolar bone loss. This is a recognised evidence gap.
Controversies and Areas of Uncertainty
No head-to-head randomised trial exists. Latarjet provides a bony block and may have lower recurrence in the setting of significant glenoid loss, but carries higher complication rates (nerve injury, graft problems, subscapularis dysfunction). Remplissage is arthroscopic, lower morbidity, but trades stiffness for stability. Surgeon preference and patient demands often dictate the choice.
Theoretical concern exists that the tenodesed infraspinatus rubbing against the posterior glenoid may accelerate degenerative change. Mid-term series (up to 10 years) have not shown significant arthritis progression, but truly long-term data (over 15-20 years) are not yet available.
Remplissage is almost always combined with Bankart repair. Performing isolated remplissage without restoring the anterior labral bumper is generally considered insufficient for anterior instability. However, rare case reports describe isolated remplissage in revision settings where the anterior labrum is scarred but competent. This is not standard practice.
The external rotation loss (8-14 degrees mean) is functionally significant for throwers and overhead sport athletes. Some authors recommend avoiding remplissage in competitive overhead athletes and favouring Latarjet or humeral osteoplasty instead. Other authors report acceptable return to overhead sport after remplissage with targeted rehabilitation. This remains a clinical judgement call.
MCQ Practice Points
Q: What structures are tenodesed into the Hill-Sachs defect during a remplissage procedure? A: The posterior capsule and the infraspinatus tendon. Suture anchors are placed in the floor of the Hill-Sachs defect, and sutures are passed through the posterior capsule and the infraspinatus footprint. The tendon is pulled into the defect without being detached from its insertion on the greater tuberosity. This creates an extra-articular buttress that prevents the defect from engaging the anterior glenoid rim.
Q: When is remplissage indicated in anterior shoulder instability? A: When the Hill-Sachs lesion is off-track (Hill-Sachs interval greater than glenoid track) and anterior glenoid bone loss is less than 20-25 percent. Remplissage is combined with Bankart repair. It is not indicated for on-track (non-engaging) lesions, which are managed with Bankart repair alone, or for glenoid bone loss exceeding 25 percent, where Latarjet or bone grafting is required.
Q: How is the glenoid track calculated and what does an off-track result mean? A: Glenoid track = 0.84 multiplied by (glenoid width minus anterior rim bone loss width). This is measured on 3D CT. Off-track means the Hill-Sachs interval (Hill-Sachs width plus the bony bridge posterior to it) is greater than the glenoid track width. An off-track lesion engages the anterior glenoid rim during arm abduction and external rotation, predisposing to recurrent dislocation despite labral repair.
Q: What is the most common complication of the remplissage procedure? A: Loss of external rotation (stiffness), with a mean loss of 8-14 degrees. This is the accepted trade-off for achieving stability. Most patients compensate functionally, but overhead athletes may notice the limitation. Patients must be counselled preoperatively about this expected outcome.
Q: When is remplissage contraindicated in the management of anterior shoulder instability? A: When anterior glenoid bone loss exceeds 20-25 percent of the glenoid width. In this setting, the Latarjet procedure or glenoid bone grafting is required because the glenoid deficiency, not the Hill-Sachs, is the dominant driver of instability. Remplissage addresses only the humeral side. Isolated remplissage without Bankart repair is also contraindicated as it does not restore the anterior labral bumper.
Q: Why should the Bankart repair be performed before the remplissage? A: The Bankart is the primary stabiliser and should be completed first. If remplissage is performed first, tethering the posterior humeral head may alter the arthroscopic view and make anterior labral repair technically more difficult. Additionally, the Bankart restores the anterior bumper, and the remplissage is an adjunct to prevent Hill-Sachs engagement. The sequence follows a logical priority: restore the primary stabiliser first, then augment for the secondary pathology.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 24-year-old rugby player presents with his fourth anterior shoulder dislocation. He has had one previous arthroscopic Bankart repair 18 months ago that has failed. CT scan with 3D reconstruction shows an off-track Hill-Sachs lesion (Hill-Sachs interval 22 mm, glenoid track 18 mm) and 12 percent anterior glenoid bone loss. How would you manage him?”
“A 19-year-old competitive volleyball player has had three anterior dislocations. CT shows an off-track Hill-Sachs lesion with a Hill-Sachs interval of 20 mm and a glenoid track of 16 mm. Anterior glenoid bone loss is 8 percent. He is desperate to return to competitive volleyball at the highest level. What are the management options and how would you counsel him?”
Key Anatomy and Concept
- Hill-Sachs = posterosuperior humeral head compression fracture from anterior dislocation
- Engaging Hill-Sachs = defect contacts anterior glenoid rim in abduction/external rotation
- Glenoid track = 0.84 multiplied by (glenoid width minus anterior rim bone loss)
- Off-track = Hill-Sachs interval greater than glenoid track width
Indications and Contra-indications
- Indicated: off-track Hill-Sachs with glenoid bone loss less than 20-25 percent, combined with Bankart repair
- Not indicated: on-track (non-engaging) Hill-Sachs (Bankart alone sufficient)
- Contraindicated: glenoid bone loss greater than 25 percent (Latarjet required)
- Contraindicated: isolated remplissage without Bankart (insufficient stability)
Surgical Technique
- Lateral decubitus position preferred; posterior viewing, posterolateral accessory portal for remplissage
- Complete Bankart repair first, then address Hill-Sachs
- Debride Hill-Sachs floor to bleeding bone; insert 2-3 anchors in defect
- Pass sutures through posterior capsule and infraspinatus; tie knots to fill defect
Outcomes
- Recurrence rate: 4-8 percent at 2-5 years when combined with Bankart
- External rotation loss: mean 8-14 degrees (accepted trade-off)
- Rowe scores: 80-90 percent good to excellent results
- No significant arthritis progression reported at mid-term (up to 10 years)
Complications and Pearls
- Stiffness (ER loss) is primary complication; counsel preoperatively
- Recurrent instability 4-17 percent; consider Latarjet if glenoid loss large
- Overhead athletes: Latarjet may be preferred over remplissage to preserve ER
- Always document bone loss measurements and glenoid track calculation
Evidence Base and Key Trials
Hill-Sachs 'remplissage': an arthroscopic solution for the engaging Hill-Sachs lesion
- First clinical description of arthroscopic remplissage technique combined with Bankart repair for engaging Hill-Sachs lesions
- Low recurrence and acceptable external rotation loss in early series of patients with anterior instability
- Demonstrated feasibility of converting engaging lesions to non-engaging via posterior capsulodesis
Arthroscopic double-pulley remplissage technique for engaging Hill-Sachs lesions in anterior shoulder instability repairs
- Described the double-pulley suture anchor technique for remplissage to achieve secure fixation of infraspinatus and capsule into the defect
- Provided step-by-step technical pearls for anchor placement and suture management in the Hill-Sachs lesion
- Highlighted the importance of addressing both the Hill-Sachs and Bankart components in bipolar bone loss
Midterm outcomes of arthroscopic remplissage for the management of recurrent anterior shoulder instability
- Midterm follow-up of arthroscopic remplissage showed good stability and low recurrence in patients with engaging Hill-Sachs lesions
- Significant improvement in shoulder scores with manageable loss of external rotation
- Confirmed the role of remplissage in converting off-track lesions and reducing revision rates
Bankart repair versus Bankart repair plus remplissage: an in vitro biomechanical comparative study
- Biomechanical study demonstrating that adding remplissage to Bankart repair significantly reduces anterior translation in engaging Hill-Sachs models
- Remplissage provides additional stability by limiting the engaging arc of the humeral head defect
- Quantified the contribution of remplissage to overall joint stability beyond labral repair alone
The biomechanical effect of shoulder remplissage combined with Bankart repair for the treatment of engaging Hill-Sachs lesions
- Demonstrated that remplissage plus Bankart repair restores glenohumeral stability more effectively than Bankart repair alone in engaging Hill-Sachs lesions
- Remplissage reduces the engaging potential by filling the defect and altering humeral head kinematics
- Supports use of remplissage when glenoid track assessment indicates off-track pathology