Skeletal-Muscle Differentiated Sarcoma | Embryonal vs Alveolar | Fusion Status Drives Risk
- Most common soft tissue sarcoma in children, arising from cells committed to skeletal-muscle differentiation
- Two main subtypes: embryonal (better prognosis) and alveolar (worse prognosis)
- PAX3-FOXO1 or PAX7-FOXO1 fusion status, not just histology, now drives risk stratification and outcome
- Risk grouping uses pre-treatment stage (TNM site/size/nodes), surgico-pathological clinical group, histology and fusion status
- Treatment is always multimodal: systemic chemotherapy for every patient, plus local control with surgery and/or radiotherapy
- “Fusion-negative alveolar RMS behaves like embryonal RMS - fusion status outperforms morphology
- “Desmin, myogenin (MYF4) and MyoD1 confirm skeletal-muscle differentiation on immunohistochemistry
- “Parameningeal, extremity and unfavourable-site tumours and any nodal/metastatic disease worsen risk
- “Adult and pleomorphic rhabdomyosarcoma carry a markedly worse prognosis than paediatric disease
Overview and Epidemiology
Rhabdomyosarcoma (RMS) is a malignant soft tissue tumour whose cells are committed to skeletal-muscle differentiation. It is the most common soft tissue sarcoma of childhood and one of the more frequent solid tumours in children overall.
A muscle cancer wherever it arises. RMS does not need pre-existing skeletal muscle to form. It arises from primitive mesenchymal cells that activate the skeletal-muscle differentiation programme (MyoD1, myogenin), which is why it can arise anywhere, including sites that contain no striated muscle, such as the bladder, biliary tree and orbit.
Who. Most cases are under 10 years, with a smaller second peak in adolescence and a slight male predominance overall. The biology is bimodal as well: embryonal tumours dominate in young children, alveolar tumours in older children and teens. Adults are rarely affected and have a substantially poorer prognosis, partly because of more frequent pleomorphic histology, unfavourable sites and later presentation.
Where. Head and neck is the most common region, and extremity disease is the form most relevant to orthopaedic practice.
- Head and neck, including the orbit and parameningeal sites
- Genitourinary: bladder, prostate, paratesticular, vagina
- Extremity: more often alveolar, with a higher rate of nodal involvement
- Trunk, retroperitoneum and other sites
Site carries prognosis. Parameningeal and extremity sites carry the worst outlook, as does any metastatic disease. The parameningeal primaries are the nasopharynx, paranasal sinuses, middle ear and infratemporal fossa, and they carry a worse prognosis because of their proximity to the skull base.
- Examples
- Orbit, non-parameningeal head and neck, genitourinary non-bladder/prostate (e.g. paratesticular, vagina), biliary tract
- Prognostic Significance
- Better outcome; allow treatment de-escalation in low-risk groups
- Examples
- Parameningeal, bladder/prostate, extremity, trunk, retroperitoneum
- Prognostic Significance
- Higher relapse and metastatic risk; require intensified therapy
Pathophysiology and Molecular Biology
The myogenic programme. RMS cells express the master regulators of skeletal-muscle differentiation, MyoD1 and myogenin (MYF4), together with structural muscle proteins such as desmin. This myogenic signature is the basis for diagnosis on immunohistochemistry.
Fusion-positive RMS. These tumours are defined by gene fusions involving FOXO1, which drive an aggressive transcriptional programme. Most morphologically alveolar tumours are fusion-positive.
- PAX3-FOXO1, t(2;13): the most common, with the worst prognosis
- PAX7-FOXO1, t(1;13): less common, with somewhat better behaviour
Fusion-negative RMS. There is no FOXO1 fusion, and the tumour is driven by other mutations, of which RAS pathway mutations are common. The group includes most embryonal tumours and generally has a better prognosis than fusion-positive disease.
Modern risk stratification is increasingly based on FOXO1 fusion status rather than alveolar versus embryonal morphology alone. Large cooperative-group data, from alveolar and embryonal tumours treated with the same intermediate-risk therapy, show that fusion-positive disease, particularly PAX3-FOXO1, has significantly worse event-free and overall survival and behaves aggressively regardless of subtle morphology, while alveolar tumours without a fusion behave like embryonal disease. This is why fusion status is now embedded in risk stratification. Always request molecular fusion testing: it changes risk allocation.
Other recurrent drivers. These alterations recur alongside, or instead of, the fusion.
- Typical Context
- Fusion-negative (mostly embryonal) tumours
- Clinical Relevance
- Found in over half of fusion-negative cases; potential therapeutic target
- Typical Context
- Both fusion-positive and fusion-negative tumours
- Clinical Relevance
- Associated with worse outcome; flags possible Li-Fraumeni predisposition
- Typical Context
- Spindle cell/sclerosing RMS, often older patients
- Clinical Relevance
- Highly aggressive subset despite spindle morphology
- Typical Context
- Congenital/infantile spindle cell RMS
- Clinical Relevance
- Generally favourable behaviour in infants
A minority of rhabdomyosarcomas arise in cancer predisposition syndromes - Li-Fraumeni (TP53), neurofibromatosis type 1, DICER1, Costello and Beckwith-Wiedemann syndromes. Young age, embryonal/anaplastic histology and a relevant family history should prompt consideration of genetic referral.
Classification and Histology
The WHO recognises embryonal, alveolar, pleomorphic and spindle cell/sclerosing subtypes.
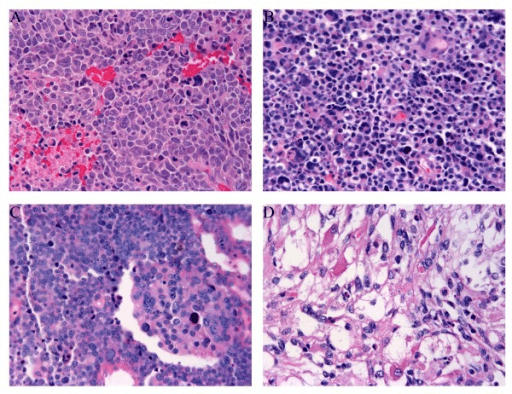
Embryonal (ERMS). The most common subtype, typically in younger children and at head and neck and genitourinary sites. It is usually FOXO1 fusion-negative, with frequent RAS pathway mutations, and generally has a favourable prognosis.
- Primitive small round to spindle cells in a myxoid stroma
- Variable rhabdomyoblasts with eosinophilic cytoplasm (tadpole or strap cells)
- Alternating cellular and loose hypocellular areas
- Botryoid variant: grape-like polypoid growth under mucosa (bladder, vagina), with a cambium layer
The botryoid variant is favourable. Spindle-cell morphology is not reliably so: see spindle cell/sclerosing RMS below.
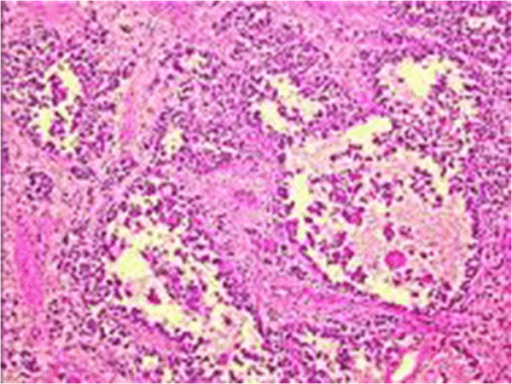
Alveolar (ARMS). More common in older children and adolescents, often at extremity and trunk sites, with frequent nodal involvement. Most are PAX3-FOXO1 or PAX7-FOXO1 fusion-positive, and that is why the subtype has a worse prognosis than embryonal disease.
- Small round cells in nests separated by fibrovascular septa
- Discohesive cells creating the "alveolar" spaces
- A solid variant lacks well-formed alveolar spaces
Every morphologically alveolar tumour must undergo FOXO1 fusion testing. A fusion-negative result reclassifies the patient into the lower-risk, embryonal-like category and can change treatment intensity, so never assign risk on morphology alone; wait for the fusion result.
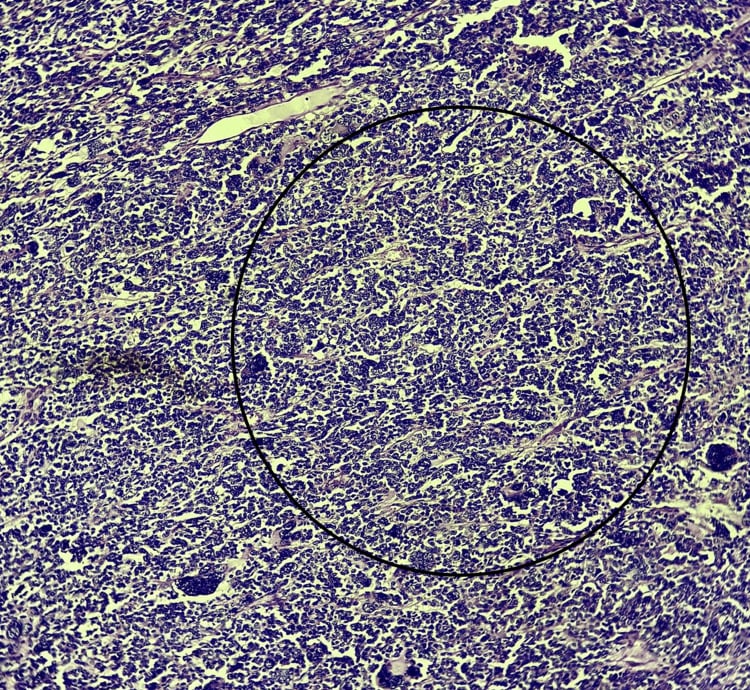
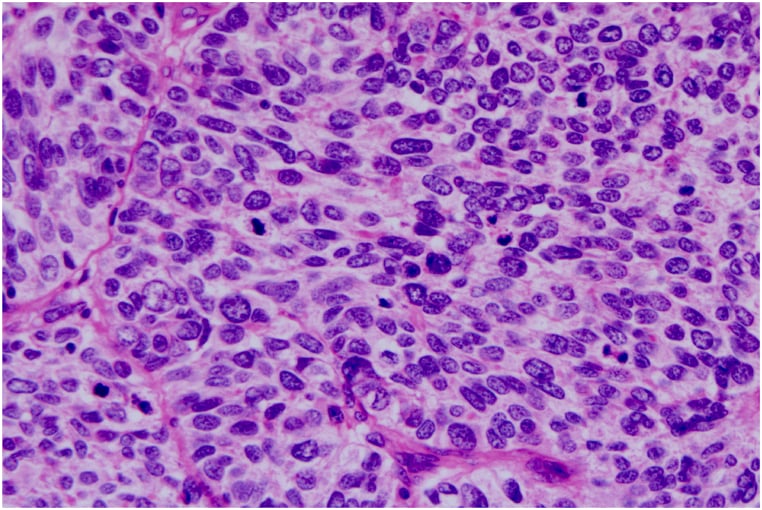
Pleomorphic RMS. Almost exclusively a tumour of adults, in deep extremity soft tissue. It is made of bizarre pleomorphic cells with no FOXO1 fusion, and it is aggressive, often chemoresistant and carries a poor prognosis.
Spindle cell / sclerosing RMS. A sclerosing pattern with dense hyalinised stroma, easily mistaken for other spindle cell tumours. The congenital/infantile form (VGLL2/NCOA2) is favourable; the adult MYOD1-mutant form is highly aggressive.
The MYOD1-mutant spindle cell/sclerosing rhabdomyosarcoma carries a dismal prognosis despite a deceptively bland spindle appearance. Molecular testing is essential to identify this aggressive subset.
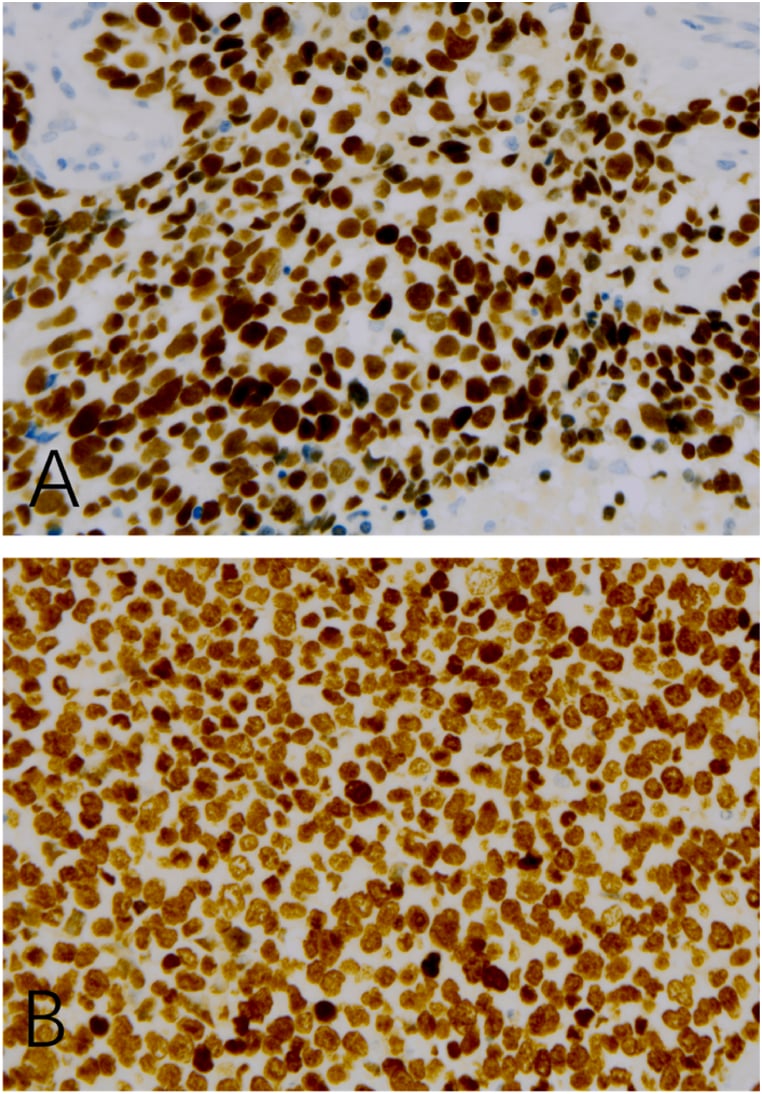
Immunohistochemistry. The diagnosis rests on the nuclear myogenic transcription factors, myogenin and MyoD1, supported by desmin; fusion testing then sets the risk.
- Significance
- Muscle intermediate filament
- Diagnostic Value
- Sensitive but not specific for skeletal muscle
- Significance
- Skeletal-muscle transcription factor
- Diagnostic Value
- Specific; diffuse strong staining favours alveolar subtype
- Significance
- Master myogenic regulator
- Diagnostic Value
- Specific for skeletal-muscle differentiation; key in spindle/sclerosing RMS
- Significance
- Detects PAX-FOXO1 fusion
- Diagnostic Value
- Defines fusion-positive (high-risk) disease
The myogenin pattern is a clue. Diffuse, strong nuclear myogenin is typical of alveolar (often fusion-positive) tumours, whereas embryonal tumours tend to show more patchy staining. Combine immunohistochemistry with molecular fusion testing for definitive classification.
Morphology varies. RMS is a small round blue cell tumour of skeletal-muscle lineage, but an epithelioid variant forms organoid nests rather than the classic spindled or alveolar patterns. Morphology alone is unreliable, which is why immunohistochemistry is mandatory. Beware cross-reactivity as well: this epithelioid variant also expressed TTF-1, a marker normally taken to indicate lung or thyroid origin, and a panel rather than a single stain is what avoids the trap.
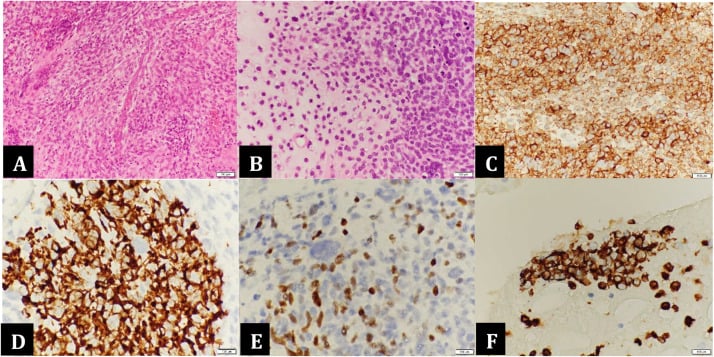
On low power, RMS is a small round blue cell tumour (SRBCT) - densely packed primitive cells with scant cytoplasm - and examiners use it to test the paediatric SRBCT differential, because the management of each member is completely different. A paediatric SRBCT is not a diagnosis: you distinguish them by immunohistochemistry and molecular genetics, not morphology.
- Rhabdomyosarcoma: desmin, myogenin and MyoD1 (nuclear) positive; PAX3/PAX7-FOXO1 fusion in alveolar - the only one with skeletal-muscle markers.
- Ewing sarcoma / PNET: diffuse membranous CD99, NKX2.2; EWSR1-FLI1 (t(11;22)) fusion - muscle markers negative.
- Neuroblastoma: young child, raised urinary catecholamines (VMA/HVA), PHOX2B, NSE, synaptophysin; Homer-Wright rosettes; MYCN amplification.
- Lymphoblastic lymphoma / leukaemia: LCA (CD45), TdT and lineage markers positive.
- Desmoplastic small round cell tumour (DSRCT): abdominal/peritoneal, polyphenotypic (desmin dot-like, keratin, WT1) with EWSR1-WT1 fusion - do not mistake the desmin positivity for RMS.
- Wilms tumour (blastemal), and in bone the mesenchymal chondrosarcoma / small cell osteosarcoma also enter the list.
Clinical Presentation
History. A painless or painful enlarging mass at the primary site, and rapid growth is common. Constitutional symptoms suggest metastatic disease. The rest depends on where the tumour sits:
- Orbit: proptosis
- Parameningeal: nasal obstruction or cranial nerve palsy
- Bladder: haematuria or urinary obstruction
- Paratesticular: a painless scrotal mass
Red flags. Look specifically for:
- Cranial nerve palsy or meningeal symptoms, pointing to parameningeal extension
- A deep, firm, enlarging extremity mass in a child or adolescent
- Regional lymphadenopathy, especially with extremity and paratesticular tumours
- Bone pain or pancytopenia, pointing to marrow involvement
A deep, enlarging or unexplained soft tissue mass in a child or young adult must be imaged and biopsied at a sarcoma centre rather than excised locally. As with all sarcomas, an unplanned excision compromises subsequent margins and contaminates tissue planes.
Examination. Inspect the size and site of the mass, the skin and overlying vascularity, any proptosis or facial asymmetry, and functional impairment of the adjacent joint or organ. Palpate for consistency, fixity and relation to deep structures, for tenderness and the neurovascular relationship, and assess the regional lymph nodes, which is important for extremity and paratesticular tumours.
Regional and systemic examination. Examine the cranial nerves for head and neck tumours and the distal neurovascular status for extremity tumours. Finish with a general examination for hepatosplenomegaly, bone tenderness and signs of marrow failure.
Investigations and Imaging
Local imaging. MRI is the standard for local staging and the imaging of choice for the primary. It defines size, compartment and soft-tissue extent, orbital and intracranial invasion, and the relationship to neurovascular structures, bone and other critical structures. Accurate local imaging underpins both the TNM stage and surgical and radiotherapy planning; measure in three planes, because tumour volume at diagnosis feeds directly into the risk group.
- MRI: T1, fluid-sensitive sequences and post-contrast imaging of the whole compartment
- CT: bony involvement, and head and neck base-of-skull assessment
- Ultrasound: initial assessment of superficial and scrotal masses
An incomplete protocol costs the plan. Extremity soft-tissue sarcoma imaging is frequently incomplete, and the sequences most often omitted are fat-suppressed T2 and post-contrast T1 with subtraction. Both are needed to define margins and viable tumour before biopsy, and an inadequate initial MRI compromises the whole surgical plan.
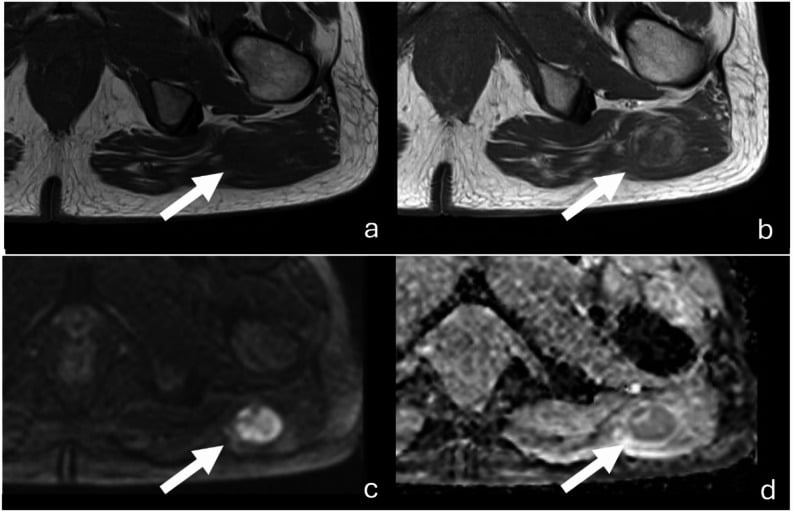
Diffusion imaging. The diffusion-weighted sequence and its ADC map distinguish cellular tumour from oedema, which is useful both at diagnosis and for assessing response. In the orbit, DWI helps detect and delineate extraocular-muscle involvement.
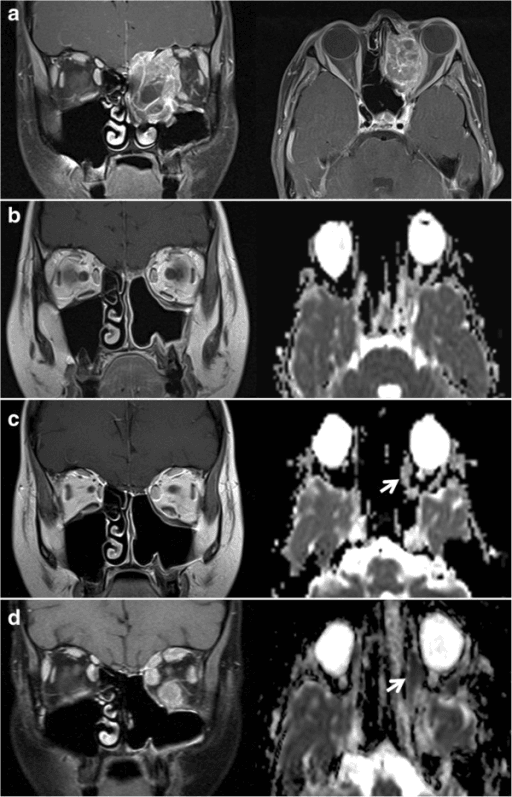
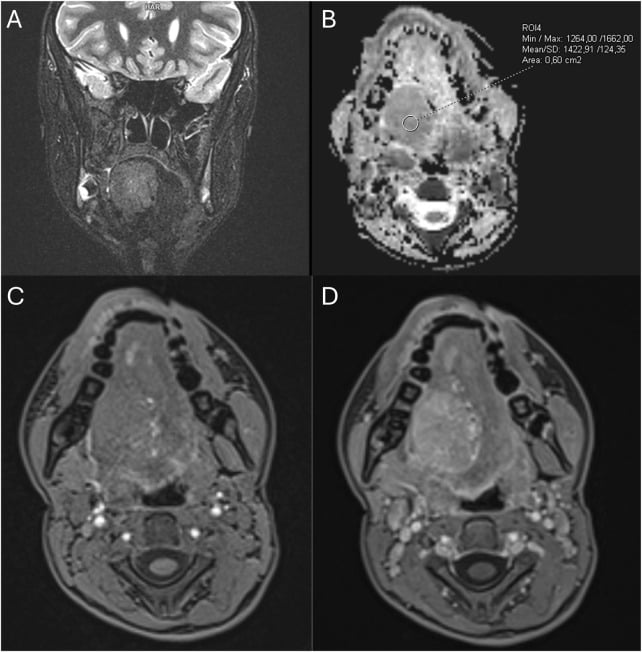
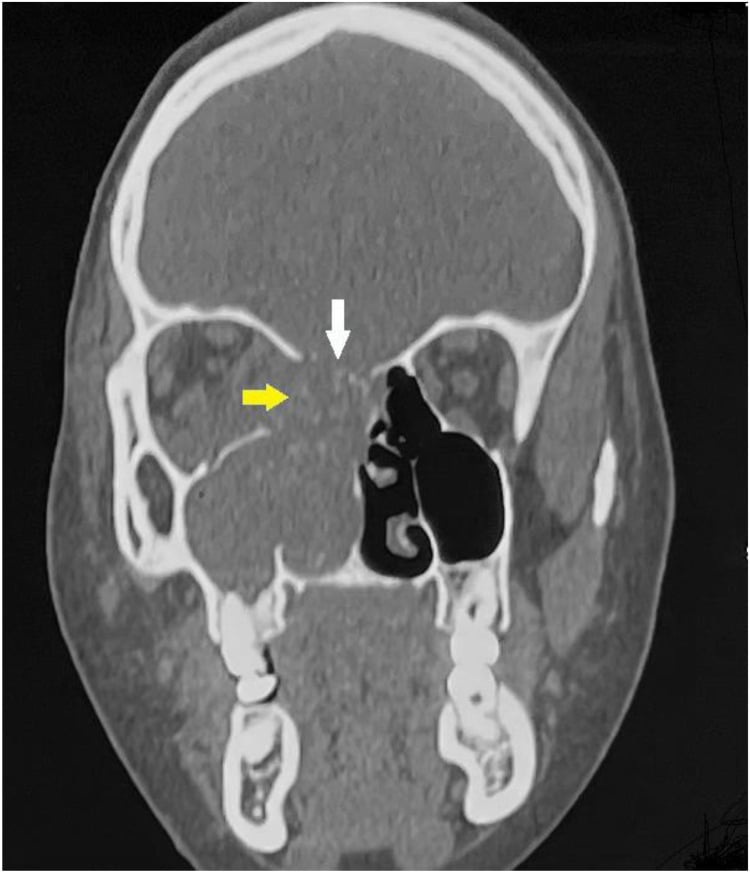
Parameningeal primaries. CT defines the bone erosion, and skull base involvement mandates cerebrospinal fluid examination and directed radiotherapy planning.
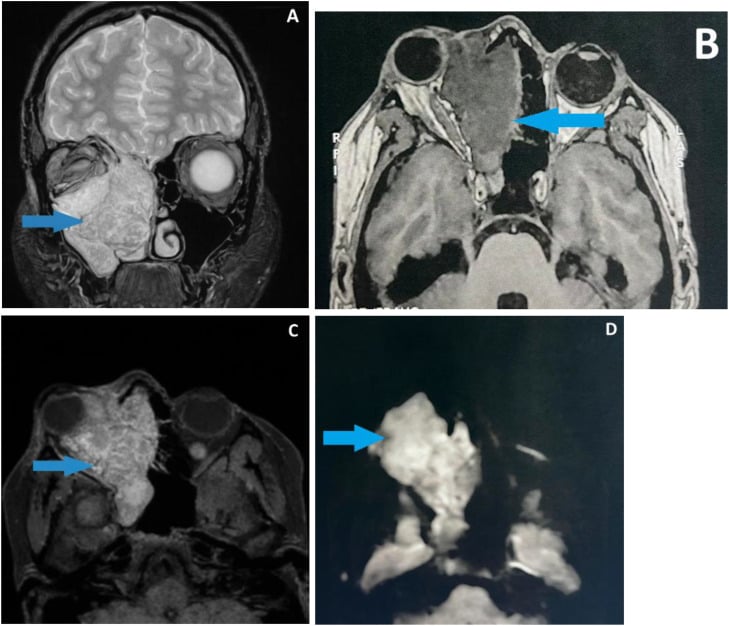
Distant staging. RMS spreads to lung, regional lymph nodes, bone and bone marrow, and complete staging defines the risk group and treatment intensity.
- CT chest: lung metastases, the most common distant site
- Whole-body imaging: FDG-PET-CT is increasingly used to detect nodal and distant disease
- Bone marrow aspirate and trephine: marrow involvement, especially in alveolar and metastatic disease
- Lymph node evaluation: clinical, radiological and, where indicated, sentinel or regional node sampling (extremity and paratesticular tumours)
- Lumbar puncture (CSF cytology): for parameningeal primaries
Tissue diagnosis. Biopsy is core needle or open incisional, at a sarcoma centre, with a planned, excisable tract. An expert pathologist subtypes the tumour (embryonal vs alveolar), immunohistochemistry confirms the lineage (desmin, myogenin, MyoD1), and FOXO1 fusion testing (FISH or RT-PCR) is done on every case, because it is essential for risk grouping and diagnosis is never complete without it. Broader molecular profiling (RAS, TP53, MYOD1) is added where available for prognostic and trial purposes.
Apply standard sarcoma biopsy principles:
- Refer to a sarcoma multidisciplinary centre before biopsy
- Core needle biopsy preferred; plan the tract so it can be excised at definitive surgery
- Use a longitudinal approach for extremity tumours; avoid transverse incisions and contamination of separate compartments
- Obtain adequate tissue for histology, immunohistochemistry and molecular fusion testing
- Never perform an unplanned excisional biopsy of an undiagnosed deep mass
Staging and risk grouping. RMS uses a combination of systems. A pre-treatment TNM stage is based on site, tumour size and invasiveness, nodal status and metastases; a surgico-pathological clinical group records the extent of residual disease after initial surgery. With histology and fusion status these combine into low-, intermediate- and high-risk groups that determine therapy (the factors are tabulated under Prognosis).
- Definition
- Localised tumour, completely resected, negative margins
- Implication
- Lowest local-treatment burden
- Definition
- Gross total resection with microscopic residual and/or resected positive nodes
- Implication
- Local radiotherapy usually added
- Definition
- Gross residual disease after biopsy or incomplete resection
- Implication
- Most common group; needs radiotherapy and chemotherapy
- Definition
- Distant metastatic disease at diagnosis
- Implication
- High-risk; intensified systemic therapy
Management
Every patient with rhabdomyosarcoma receives systemic chemotherapy, combined with local control by surgery and/or radiotherapy; surgery alone is never adequate. The intensity and duration are tailored to the risk group, and management is delivered by a paediatric/sarcoma multidisciplinary team. These principles apply across all sites, including the extremity disease relevant to orthopaedic surgeons.
The modalities. Each has a defined role:
- Chemotherapy: vincristine, actinomycin D (dactinomycin) and cyclophosphamide (VAC) form the backbone; ifosfamide-containing and other regimens are used in different cooperative groups, with intensification for higher risk
- Surgery: complete resection where it can be achieved without unacceptable morbidity; otherwise biopsy followed by chemotherapy and delayed local control
- Radiotherapy: for microscopic or gross residual disease, nodal involvement and most alveolar tumours; its near-universal role is set out below
- Typical Features
- Embryonal/fusion-negative, favourable site, localised, resectable
- Systemic Therapy
- Shorter, lower-intensity VAC-based chemotherapy (cyclophosphamide reduced or omitted in selected lowest-risk patients)
- Local Control
- Surgery; radiotherapy only if residual disease
- Typical Features
- Embryonal at unfavourable site, or non-metastatic fusion-positive/alveolar disease
- Systemic Therapy
- Full multi-agent chemotherapy (VAC and other agents)
- Local Control
- Surgery and/or radiotherapy for local control
- Typical Features
- Metastatic disease (group IV), often fusion-positive
- Systemic Therapy
- Intensified, prolonged systemic therapy; clinical trial enrolment encouraged
- Local Control
- Radiotherapy to primary and metastatic sites; surgery selectively
De-escalation in the lowest-risk patients. Cooperative-group trials have shown that the lowest-risk embryonal patients can be treated with shorter therapy and reduced or omitted cyclophosphamide while maintaining excellent failure-free survival. That reduces long-term toxicity such as infertility and second malignancy, and it is a key example of evidence-driven de-escalation.
Radiotherapy is near-universal. A defining feature of RMS, set against adult soft-tissue sarcoma, is how central radiotherapy is to local control. Because chemotherapy is universal and complete excision is often unachievable without mutilation, almost every RMS patient receives radiotherapy; the principal exception is the patient with completely resected, group I embryonal disease at a favourable site, who may avoid it. Microscopic residual (group II), gross residual (group III), nodal disease and essentially all alveolar/fusion-positive tumours get radiotherapy.
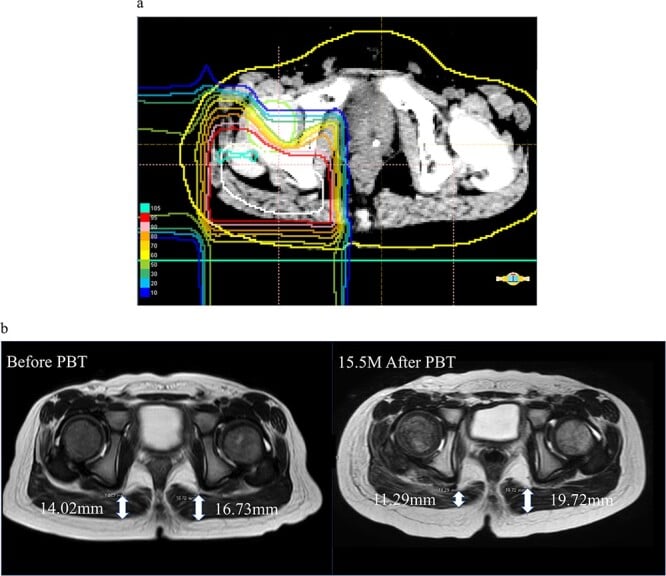
How it is delivered in a growing child. The late effects (growth arrest, asymmetry, organ damage, second malignancy) are lifelong, so the priority is function- and growth-sparing planning rather than dose escalation.
- Proton beam therapy is increasingly used to reduce dose to adjacent growing bone, brain (parameningeal and orbital tumours) and viscera
- Brachytherapy, for example for selected genitourinary/vaginal and small extremity tumours, delivers a high local dose over a small volume, sparing surrounding growth plates and organs
Surgical Considerations
The surgeon's role. In adult extremity soft tissue sarcoma surgery is often the primary treatment. In rhabdomyosarcoma chemotherapy is universal and surgery is integrated into a multimodal plan, in a decision sequence:
- Upfront resection, when feasible. Considered when complete excision with negative margins is achievable without major functional loss or mutilation, which suits small, favourable, resectable tumours (paratesticular, some extremity lesions). It avoids or reduces radiotherapy in selected patients.
- Biopsy then chemotherapy, in most cases. Larger or unfavourable-site tumours have a diagnostic biopsy only, then neoadjuvant chemotherapy to shrink the tumour, and are reassessed for delayed primary resection or definitive radiotherapy.
- Delayed local control, after response. Delayed primary excision can convert a group III tumour to a resected state. Radiotherapy is used when surgery would be mutilating or margins remain positive, and function preservation is prioritised, especially in children.
Extremity tumours. Limb salvage with wide margins is the goal. Amputation is rarely needed and is reserved for tumours not controllable by surgery plus radiotherapy, and reconstruction and rehabilitation planning are essential in growing children.
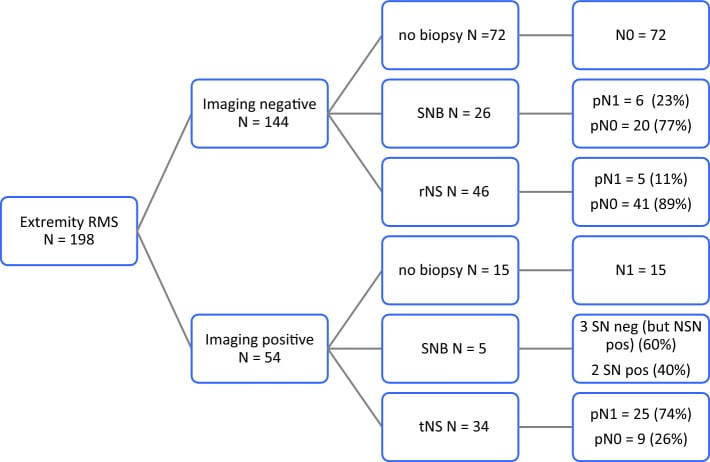
Do not forget the nodes. Extremity and paratesticular rhabdomyosarcomas have a high rate of regional nodal spread, so formal nodal assessment is part of their staging and clinical and radiological evaluation is mandatory. Imaging alone understages the nodes, and these primaries warrant surgical nodal staging: sentinel or regional node sampling guides radiotherapy fields and systemic intensity, and missed nodal disease leads to undertreatment and predicts relapse.
Complications
- Context
- Incomplete margins, gross residual disease, high-risk biology
- Management / Mitigation
- Re-resection if feasible, radiotherapy, systemic therapy
- Context
- Lung, bone, bone marrow; more common in alveolar/fusion-positive disease
- Management / Mitigation
- Intensified systemic therapy, clinical trials, selective metastasis-directed treatment
- Context
- Cyclophosphamide and ifosfamide (gonadotoxicity, haemorrhagic cystitis), anthracycline cardiotoxicity, myelosuppression
- Management / Mitigation
- Dose tailoring, mesna, fertility counselling, cardiac monitoring
- Context
- Growth disturbance, fibrosis, organ-specific damage, second malignancy
- Management / Mitigation
- Modern conformal techniques, minimise dose/field, long-term surveillance
- Context
- Functional loss, nerve injury, wound problems
- Management / Mitigation
- Limb-sparing planning, reconstruction, rehabilitation
The price of local control. Growth impairment, limb length discrepancy and second malignancy are the price of irradiating a growing child, and must be discussed before treatment.
Because many children are cured, the long-term toxicity of treatment (infertility, cardiac dysfunction, growth problems and second cancers) is a central concern. This drives the trend towards risk-adapted de-escalation in low-risk patients and structured long-term survivor follow-up.
Prognosis and Outcomes
Outcome by risk. The spread is wide, from high cure rates to poor survival, and it follows the risk group.
- Low-risk localised disease (favourable site, embryonal/fusion-negative): high cure rates with risk-adapted therapy
- Intermediate-risk disease: intermediate survival; benefits from full multimodal therapy
- Metastatic or high-risk disease: poor survival despite intensified treatment
- Adult and pleomorphic RMS: markedly worse than paediatric disease
Prognostic factors. The same factors feed risk grouping and prognosis.
- Favourable
- Fusion-negative
- Unfavourable
- PAX3-FOXO1 (worst), PAX7-FOXO1
- Favourable
- Embryonal (incl. botryoid variant)
- Unfavourable
- Alveolar; anaplasia in embryonal tumours
- Favourable
- Orbit, non-parameningeal head/neck, favourable GU
- Unfavourable
- Parameningeal, extremity, bladder/prostate, trunk
- Favourable
- Smaller, non-invasive (T1)
- Unfavourable
- Over 5cm, invasive (T2)
- Favourable
- Localised, node-negative
- Unfavourable
- Node-positive or metastatic
- Favourable
- Group I-II
- Unfavourable
- Group III-IV
- Favourable
- 1-9 years
- Unfavourable
- Under 1 or over 10 years; adults much worse
FAILSAdverse Prognostic Factors
Hook:When these factors stack up, treatment more often FAILS.
Clinical Relevance and Controversies
Integrating molecular risk. The shift from histology-based to fusion-based risk stratification, supported by international genomic data, is refining who needs intensification and who can be de-escalated. Incorporating additional drivers (e.g. MYOD1, TP53) into routine risk grouping is an active area of trial design.
De-escalation against cure. Reducing cyclophosphamide and shortening therapy in low-risk patients lowers late toxicity. The balance between minimising harm and maintaining cure rates must be confirmed in each subgroup before it is adopted as standard.
Adult rhabdomyosarcoma. Adults are frequently treated on paediatric-style protocols, and those who receive intensive multimodal therapy fare better than historical adult cohorts, yet outcomes remain inferior to children. Optimal regimens for adults are still debated.
Relapsed and metastatic disease. Outcomes after relapse, and for metastatic disease at presentation, remain poor. New agents (targeted therapy against the RAS pathway, immunotherapy and antibody-based approaches) are under investigation, and trial enrolment is encouraged.
Guidelines, Registries & Global Practice
Global Epidemiology
- Most common soft tissue sarcoma of childhood worldwide
- Majority of cases occur under 10 years, with a second adolescent peak
- Embryonal subtype predominates in young children; alveolar in older children/teens
- Adults are rarely affected and have markedly worse outcomes
- Common metastatic sites are lung, regional nodes, bone and bone marrow
- Outcome ranges from high cure rates in low-risk disease to poor survival when metastatic
- Fusion-positive biology is a key global driver of poor outcome
Cooperative-Group Frameworks
- Risk Stratification
- Stage, clinical group, histology and increasingly fusion status
- Chemotherapy Backbone
- Vincristine, actinomycin D, cyclophosphamide (VAC) and intensified variants
- Emphasis
- De-escalation in low-risk; intensification and trials in high-risk
- Risk Stratification
- Risk-adapted protocols using site, size, nodes, age and fusion status
- Chemotherapy Backbone
- Ifosfamide-, vincristine- and actinomycin-based regimens with maintenance therapy
- Emphasis
- Function-preserving local control and maintenance chemotherapy
- Risk Stratification
- Mandatory specialist multidisciplinary review
- Chemotherapy Backbone
- Protocol-based multi-agent chemotherapy
- Emphasis
- Centralised diagnosis, molecular confirmation and treatment
Regardless of region, all frameworks agree on three points: any suspicious deep or enlarging soft tissue mass should be referred to a specialist sarcoma centre before biopsy, diagnosis should be confirmed histologically and molecularly (including FOXO1 fusion status), and treatment should be multimodal, risk-adapted and delivered by a multidisciplinary team.
High- vs Limited-Resource Practice Variation
- Routine FOXO1 fusion testing and broader molecular profiling
- Centralised paediatric sarcoma multidisciplinary teams
- Modern conformal radiotherapy and limb-sparing surgery
- Structured survivorship and late-effects surveillance
- Diagnosis may rely on morphology and immunohistochemistry where molecular testing is unavailable
- Treatment refusal and abandonment can materially reduce survival
- Later presentation with larger, unfavourable-site tumours
- Regional referral networks and protocol adaptation help bridge gaps
Applicable in any health system:
- Document the investigation pathway for any persistent deep soft tissue mass
- Confirm pre-biopsy staging and that biopsy was planned with the definitive surgeon
- Record that histology, immunohistochemistry and FOXO1 fusion testing were requested
- Evidence of sarcoma multidisciplinary discussion before definitive treatment
- Informed consent covering multimodal therapy, fertility and long-term toxicity
- A written long-term survivorship and surveillance plan
MCQ Practice Points
Q: What is the most common soft tissue sarcoma of childhood? A: Rhabdomyosarcoma. It arises from cells committed to skeletal-muscle differentiation and most often affects children under 10 years, with a smaller second peak in adolescence.
Q: Which gene fusions define high-risk alveolar rhabdomyosarcoma? A: PAX3-FOXO1 (t(2;13)) and PAX7-FOXO1 (t(1;13)). PAX3-FOXO1 carries the worst prognosis. Fusion-negative alveolar tumours behave like embryonal disease.
Q: Which immunohistochemical markers confirm rhabdomyosarcoma? A: Desmin, myogenin (MYF4) and MyoD1. Myogenin and MyoD1 are nuclear skeletal-muscle transcription factors; diffuse strong myogenin staining favours the alveolar subtype.
Q: What is the universal component of rhabdomyosarcoma treatment? A: Systemic chemotherapy - typically a vincristine, actinomycin D and cyclophosphamide (VAC) backbone - given to every patient, combined with local control by surgery and/or radiotherapy and tailored to risk group.
Q: Name key adverse prognostic factors in rhabdomyosarcoma. A: Fusion-positive (especially PAX3-FOXO1) disease, alveolar histology or anaplasia, unfavourable primary site, large/invasive tumour, nodal or metastatic spread, higher clinical group, and adult age.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 14-year-old presents with a firm, deep 6cm mass in the anterior thigh that has grown over two months. There is a palpable inguinal node. How do you investigate and what is your differential?”
“A child's biopsy is reported as alveolar rhabdomyosarcoma. The treating oncologist asks whether molecular testing will change anything. How do you respond?”
“A young child has a completely resected paratesticular embryonal rhabdomyosarcoma that is fusion-negative and node-negative. The parents are worried about chemotherapy toxicity. How do you counsel them and plan treatment?”
Key Epidemiology
- Most common soft tissue sarcoma of childhood
- Majority under 10 years; second adolescent peak
- Common sites: head and neck (incl. orbit, parameningeal), genitourinary, extremity, trunk
- Adult and pleomorphic disease is rare and has a much worse prognosis
Histology and Molecular Biology
- Embryonal (commonest, better prognosis, usually fusion-negative)
- Alveolar (older patients, extremity/trunk, often PAX-FOXO1 fusion-positive, worse prognosis)
- Pleomorphic (adults) and spindle/sclerosing (MYOD1-mutant aggressive) variants
- PAX3-FOXO1 and PAX7-FOXO1 fusions define high-risk biology; fusion status now drives risk
Diagnosis
- Refer to sarcoma centre before biopsy; planned excisable tract
- Immunohistochemistry: desmin, myogenin (MYF4), MyoD1
- FOXO1 fusion testing (FISH/RT-PCR) on every case
- MRI for local staging; CT chest, whole-body imaging and bone marrow for distant staging
Risk Grouping
- Pre-treatment TNM stage (site, size, invasiveness, nodes, metastases)
- Surgico-pathological clinical group I-IV (residual disease)
- Histology and fusion status
- Combine into low-, intermediate- and high-risk groups
Treatment (Always Multimodal)
- Systemic chemotherapy for every patient (VAC backbone and variants)
- Local control with surgery and/or radiotherapy
- Upfront resection only if complete and non-mutilating; otherwise biopsy then chemo then delayed local control
- Low-risk de-escalation: shorter therapy, reduced/omitted cyclophosphamide, lower radiotherapy dose
Adverse Prognostic Factors (FAILS)
- Fusion-positive (PAX3-FOXO1 worst)
- Alveolar histology and anaplasia
- Invasive or large tumour (over 5cm, T2)
- Lymph node or metastatic spread
- Unfavourable Site and age (under 1 or over 10 years; adults much worse)
Complications and Survivorship
- Local recurrence and distant metastases (lung, bone, marrow)
- Chemotherapy toxicity: gonadotoxicity, haemorrhagic cystitis, cardiotoxicity
- Radiotherapy late effects: growth disturbance, fibrosis, second malignancy
- Long-term survivor surveillance is essential, especially in cured children
Evidence Base and Key Studies
PAX-FOXO1 Fusion Status Drives Outcome in Intermediate-Risk RMS
- Children's Oncology Group D9803 cohort; 434 cases with full clinical, molecular and pathology data
- Event-free survival was worse for alveolar PAX3-FOXO1 (54%) and PAX7-FOXO1 (65%) than embryonal RMS (77%)
- Fusion-negative alveolar RMS had outcomes similar to embryonal RMS (90% vs 77% EFS, not significantly different)
- PAX3-FOXO1 tumours had the poorest overall survival (64%) compared with PAX7-FOXO1, fusion-negative alveolar and embryonal disease
Genomic Classification and Clinical Outcome in Rhabdomyosarcoma
- International consortium; custom-capture sequencing of 641 rhabdomyosarcoma tumours from COG and UK trials
- In fusion-negative cases, RAS pathway mutations were present in over half, while about 21% had no identified driver
- TP53 mutations were associated with worse outcome in both fusion-negative and fusion-positive disease
- MYOD1 mutation was linked to older age, head and neck primaries and a dismal survival, and is being incorporated into risk stratification
Anaplasia as a Prognostic Factor in Childhood RMS
- Prospective assessment of anaplasia in 546 children on IRSG/COG trials (1995-1998)
- Anaplasia (focal or diffuse) was present in 13% of samples - more common than previously reported
- In embryonal RMS, anaplasia reduced 5-year failure-free survival (63% vs 77%) and overall survival (68% vs 82%)
- The adverse effect was most pronounced in intermediate-risk embryonal tumours; anaplasia did not affect alveolar tumour outcome