Greater than 5cm | 2+ Tendons | Fatty Infiltration
- Massive tear = greater than 5cm or 2+ tendons completely torn
- Goutallier Grade 3-4 fatty infiltration = poor repair outcomes
- Pseudoparalysis = inability to actively elevate arm
- Repair if possible, otherwise tendon transfer, SCR, or RSA
- Reverse shoulder arthroplasty for CTA (cuff tear arthropathy)
- “Irreparable does not mean inoperable
- “Subscapularis preservation important for function
- “Superior capsular reconstruction emerging option
- “RSA converts deltoid to primary mover
Overview
A massive rotator cuff tear is one greater than 5cm in size, or one involving two or more complete tendon ruptures. These tears present unique challenges for treatment.
Pathophysiology
Tear enlargement. An initial tear increases the stress on the remaining tendon, and the adjacent tendon margins bear the increased load. Propagation is commonly anterior-to-posterior or medial, and tears greater than 3cm have higher progression rates.
Retraction. After rupture the tendon retracts medially. Static retraction indicates a chronic, irreducible tear.
Fatty infiltration (steatosis). It occurs within 3-6 months of a complete tear and is progressive and irreversible. Muscle that has been replaced by fat cannot regenerate contractile function; the Goutallier grading that measures it is set out under Investigations.
Atrophy. Muscle cross-sectional area decreases with disuse, and the tangent sign turns positive when the supraspinatus is atrophied.
Muscle atrophy may partially recover if the tear is repaired early, but fatty infiltration (Goutallier 3-4) is irreversible. This is why timing of repair matters.
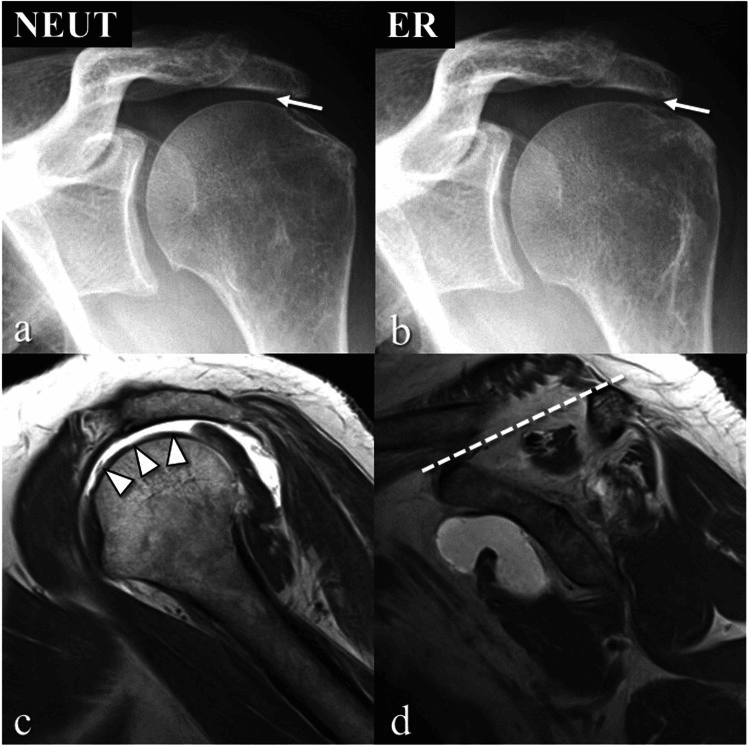
Biomechanical consequences. A torn cuff disrupts the force couple, and with it the balanced compression of the humeral head, so the unopposed deltoid pulls the head upward. In cuff tear arthropathy the undersurface of the acromion develops a concave erosion (acetabularisation) and the humeral head becomes smooth and rounded, losing the greater tuberosity (femoralisation).
Tear Pattern: the Warner Classification
The tear's geometry, not just its size, dictates how, and whether, it can be repaired. Warner describes three patterns:
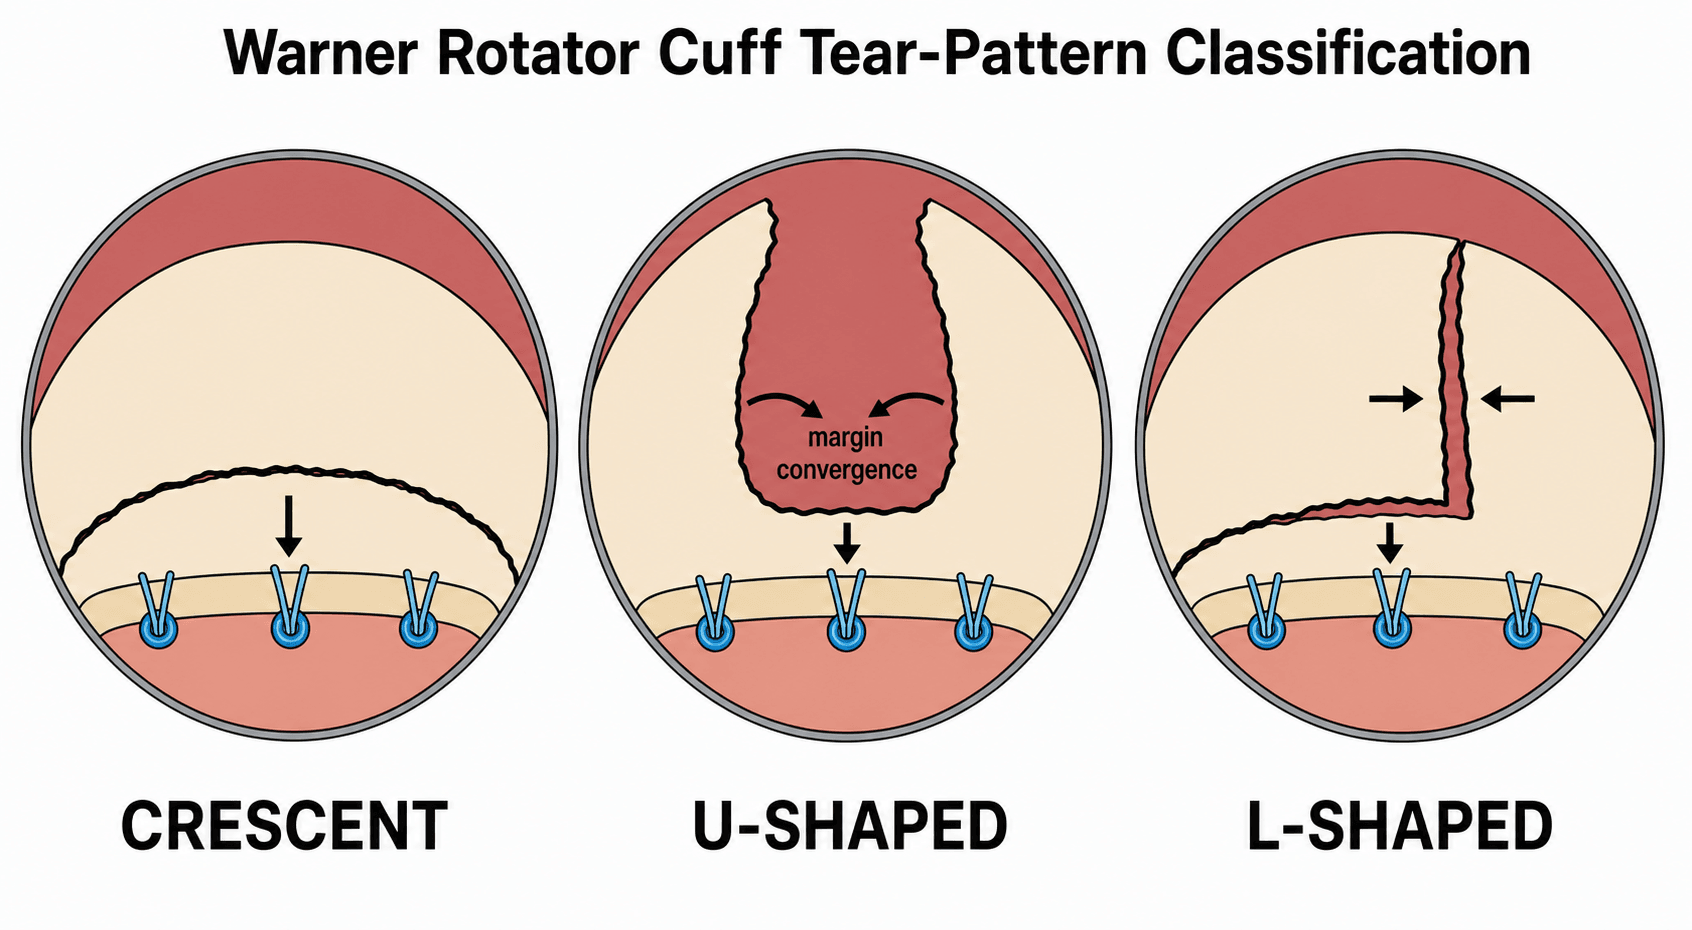
- Crescent. Wide but not deeply retracted, with good medial-to-lateral mobility and a crescent-shaped free margin. It reaches the footprint at low tension and is repaired directly to bone, single- or double-row, without side-to-side sutures.
- U-shaped. The apex retracts far medially, toward or past the glenoid, while the anterior and posterior leaves stay mobile, so the tear looks like a U pointing medially. Pulled straight to bone the apex would be under enormous tension and fail, so the leaves are first brought together by margin convergence to make a small crescent, which is then repaired to bone at low tension.
- L-shaped and reverse-L. One leaf detaches longitudinally, giving the tear a corner: the posterior leaf in an L, the anterior in a reverse-L. The mobile leaf is sutured side-to-side to close the longitudinal limb, then the residual defect is repaired to bone.
Why it matters. The pattern shows the direction of maximum mobility and whether margin convergence is needed before bone fixation. The commonest error, and a classic cause of a high-tension repair and early failure, is to misread a U-shaped tear as a crescent and drag the retracted apex straight to the footprint.
Margin Convergence
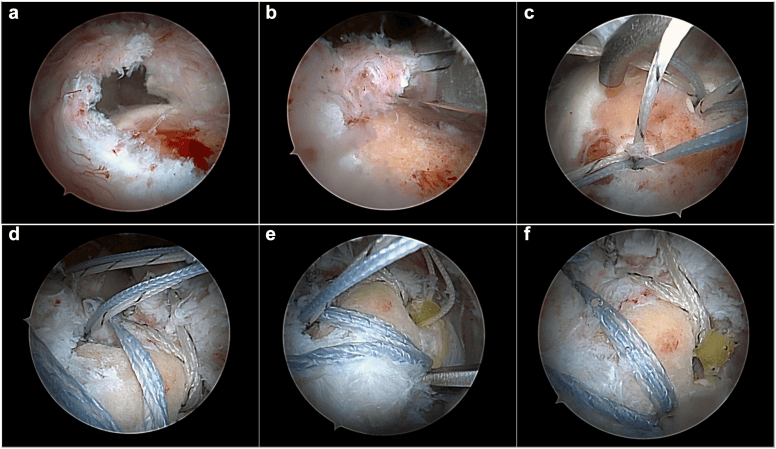
What it is. Side-to-side suturing of the mobile anterior and posterior leaves of a U- or L-shaped tear, starting medially and working laterally. As the leaves are sewn together the free margin converges laterally toward the footprint, turning a large, deeply retracted tear into a small crescent that sits near the bone. It is the technique that makes many massive tears repairable.
Why it works. The apex of a U-shaped tear is the highest-strain point, and pulling it directly to bone concentrates the whole load at the tendon-bone interface, with gap formation and re-tear. Margin convergence shares the load along the side-to-side repair and sharply reduces the strain at the final tendon-to-bone anchors. The tear is closed where it is mobile rather than where it is tethered.
Where it fits. It is done first, before any bone fixation, and the converged margin is then repaired to the footprint, single- or double-row. It also underlies partial repair: even when the margin cannot be brought fully to bone, converging the leaves restores part of the transverse force couple and is biomechanically useful.
The limit. Margin convergence fixes the geometry and tension of a tear, not the quality of its muscle. Where Goutallier 3-4 fatty infiltration has left the muscle unable to generate force, closing the tendon does not restore it.
Clinical Presentation
History. Weakness with overhead activities and a progressive loss of function, and there may be a history of acute-on-chronic pain. Patients have difficulty sleeping on their side.
Pseudoparalysis. The patient cannot actively elevate the arm, often to less than 90°, although passive motion may be preserved. It indicates loss of the force couple, and the need for RSA rather than repair alone.
The tendon-specific signs. Three signs localise the deficit:
- Hornblower's sign - cannot externally rotate in abduction (infraspinatus/teres minor dysfunction)
- External rotation lag sign - cannot maintain the externally rotated position (posterior cuff failure)
- Belly press test - cannot maintain hand pressure on the belly (subscapularis)
Investigations
Radiographs. AP, axillary lateral and scapular Y views. Look for:
- Acromiohumeral interval (AHI) under 7mm - suggests a massive tear with superior migration
- Acetabularisation of the acromion and femoralisation of the humeral head
- Glenohumeral arthritis - suggests cuff tear arthropathy
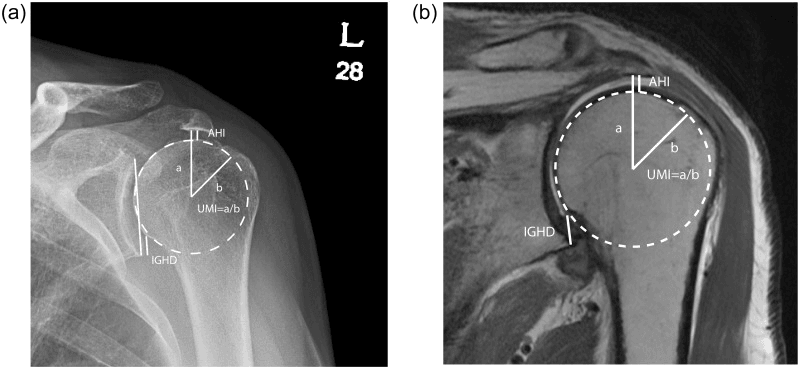
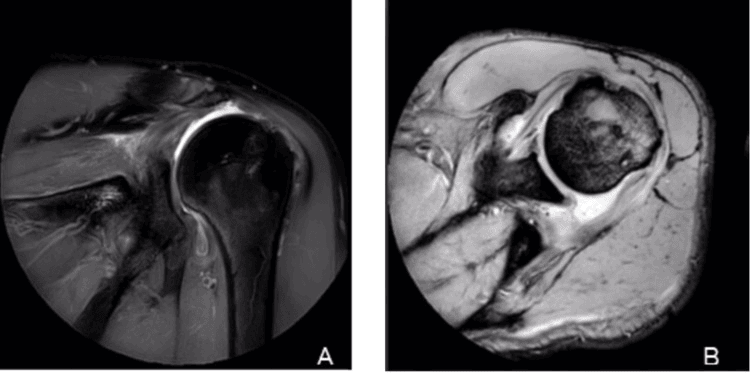
MRI is the gold standard. It measures the size of the tear, the retraction and the tendons involved, and it grades the muscle.
Size. Tear size is measured in two planes. Coronal-oblique images give the medial retraction, from the tendon edge to the greater tuberosity; sagittal-oblique images give the anterior-posterior span across the involved tendons.
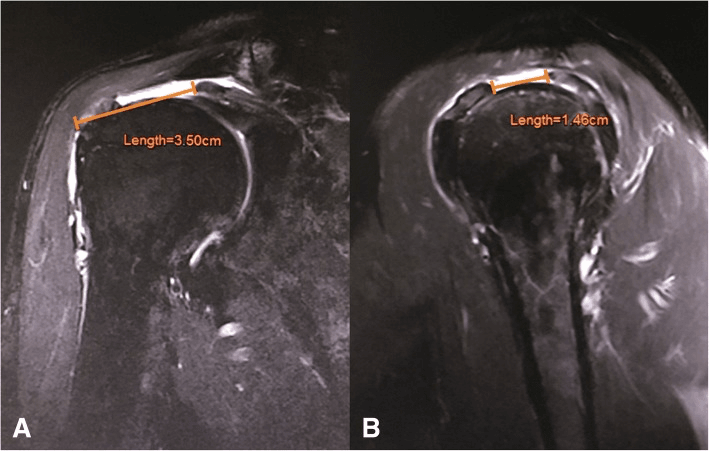
Retraction. Retraction to the glenoid is Patte stage 3 and signals poor reducibility. Tendon retracted beyond the glenoid rim predicts a poor repair outcome.
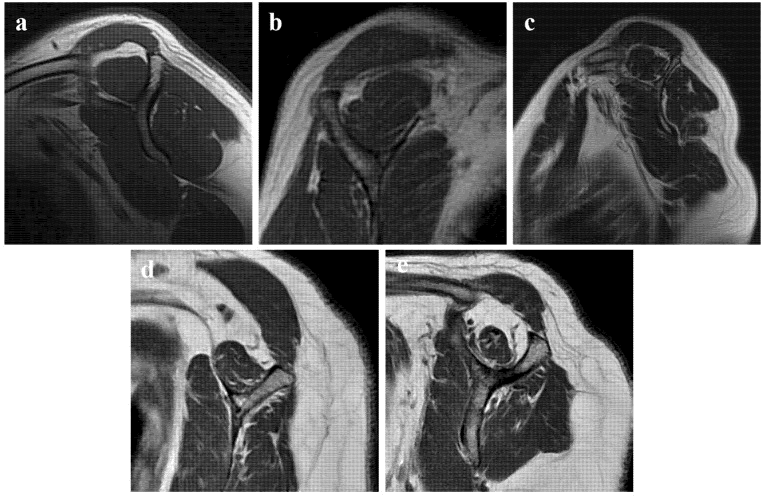
Muscle quality. Fatty infiltration is graded by Goutallier, on CT or MRI.
- Fatty infiltration
- Normal muscle, no fat
- Fatty infiltration
- Some fatty streaks
- Fatty infiltration
- Fat less than muscle (under 50% fat)
- Fatty infiltration
- Fat equals muscle (50% fat)
- Fatty infiltration
- Fat greater than muscle (over 50% fat)
Grades 3-4 predict poor outcomes after repair and may preclude it, because the muscle cannot recover. Grade 4, where fat predominates, is irreparable; grade 3 is borderline.
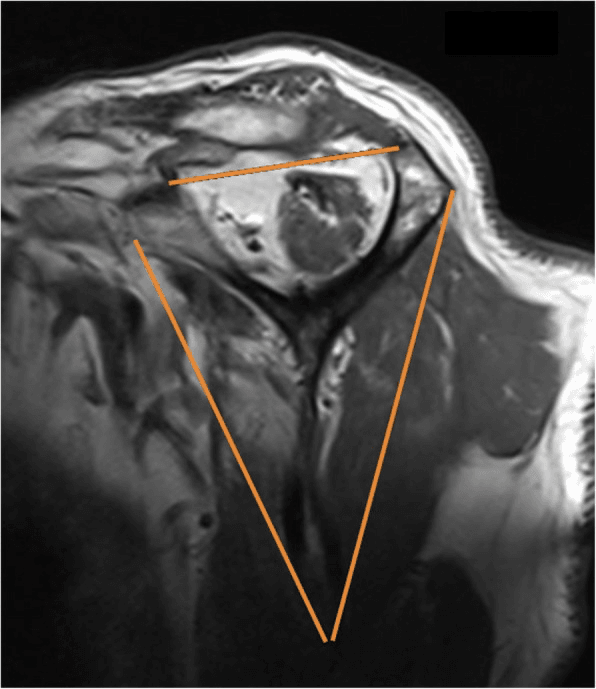
Atrophy. The tangent sign is positive when the supraspinatus does not reach the tangent line on the scapular spine. An occupation ratio under 50% suggests significant atrophy.
CT arthrography. The alternative when MRI is contraindicated. It gives excellent bone detail and can assess fatty infiltration.
Signs of an irreparable tear. Retraction to or beyond the glenoid, atrophy with a positive tangent sign, Goutallier 3-4 fatty infiltration and an AHI under 7mm, the mark of superior migration of the humeral head, are the signs of an irreparable, massive tear.
Classification schemes. Each answers a different question:
- Components
- Stage 1-3
- Clinical Use
- Predicts reducibility
- Components
- Grade 0-4
- Clinical Use
- Repair outcomes
- Components
- Grade 1-5
- Clinical Use
- Arthroplasty planning
- Components
- Crescent, U, L
- Clinical Use
- Repair technique selection
Differential Diagnosis
The patient who cannot actively elevate the arm is the key exam trap. The massive cuff tear has to be distinguished from the causes that mimic it.
- Passive ROM
- Full (passive elevation preserved)
- Discriminator
- Positive lag signs, AHI under 7 mm, intact deltoid
- Passive ROM
- Full
- Discriminator
- Deltoid wasting, regimental-badge sensory loss, EMG abnormal
- Passive ROM
- Full
- Discriminator
- Isolated supra/infraspinatus wasting, intact tendons on MRI, EMG
- Passive ROM
- Full
- Discriminator
- Neck pain, dermatomal sensory change, reflex loss, cervical MRI
- Passive ROM
- Reduced (true global stiffness)
- Discriminator
- Restricted passive AND active motion, OA on radiograph
- Passive ROM
- Blocked external rotation
- Discriminator
- Fixed internal rotation, axillary/CT confirms dislocation
The single most useful bedside test: passive elevation. Preserved passive but lost active elevation points to a cuff/neurological cause; loss of both suggests capsulitis, arthritis or a locked dislocation.
Management
Treatment escalates from debridement up to arthroplasty as muscle quality and arthritis worsen.
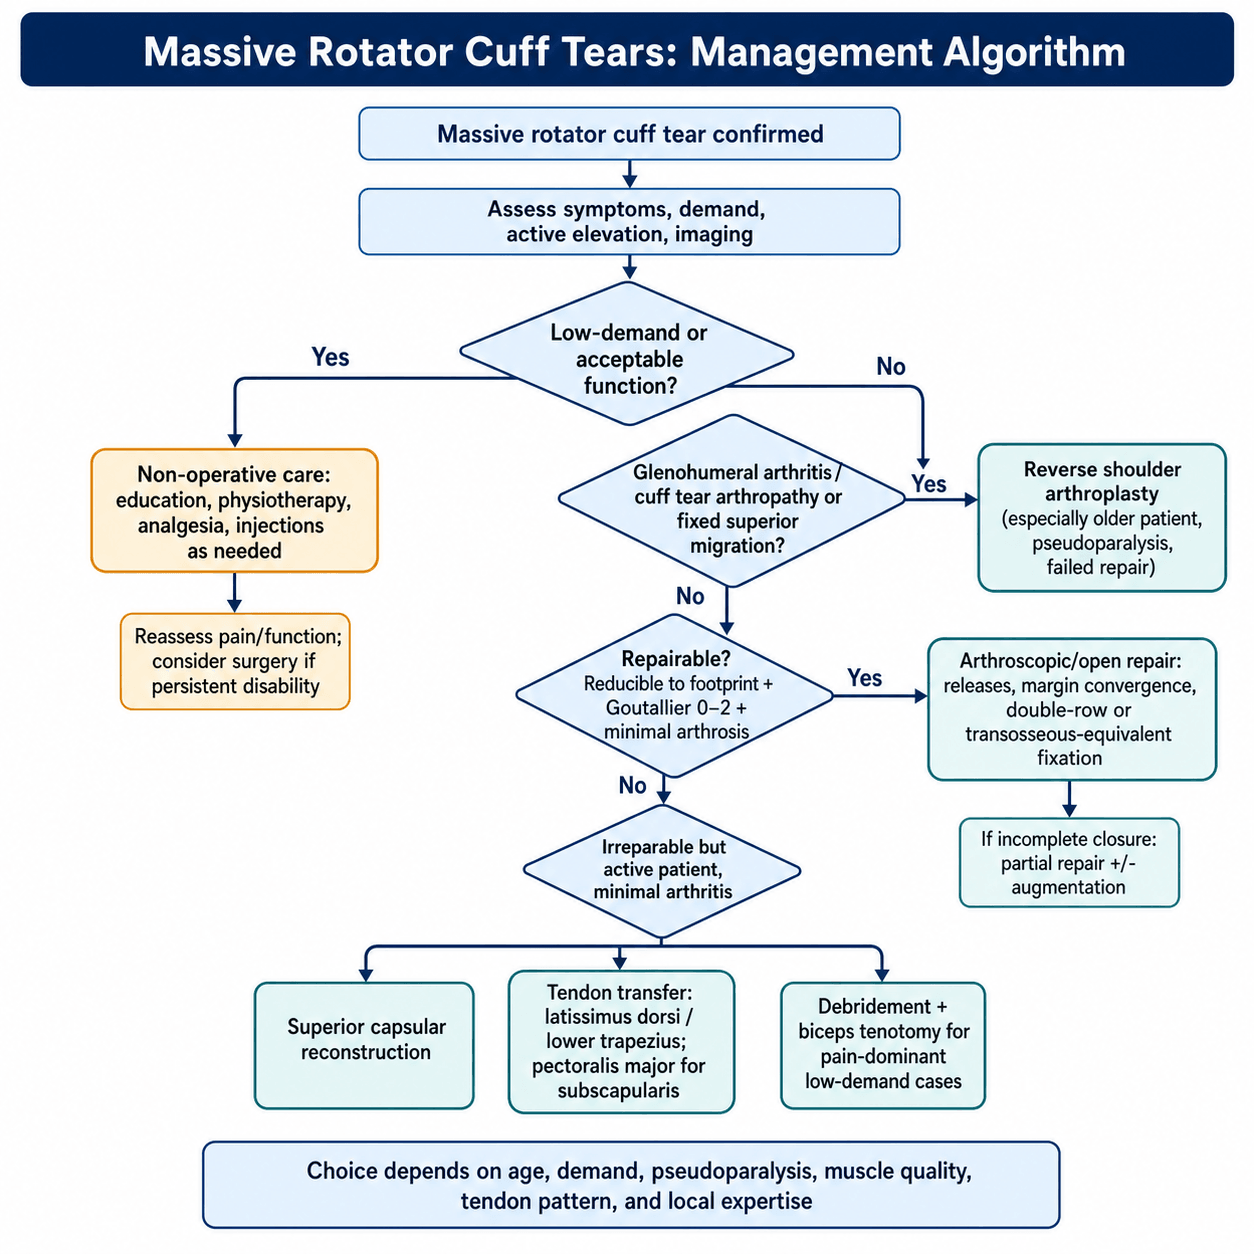
Criteria for repair. All three should be present:
- A tear that can be reduced to the footprint (not statically retracted)
- Acceptable muscle quality (Goutallier 0-2)
- No or minimal arthrosis
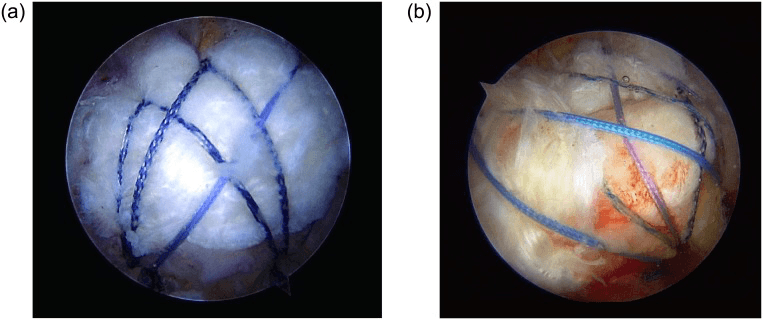
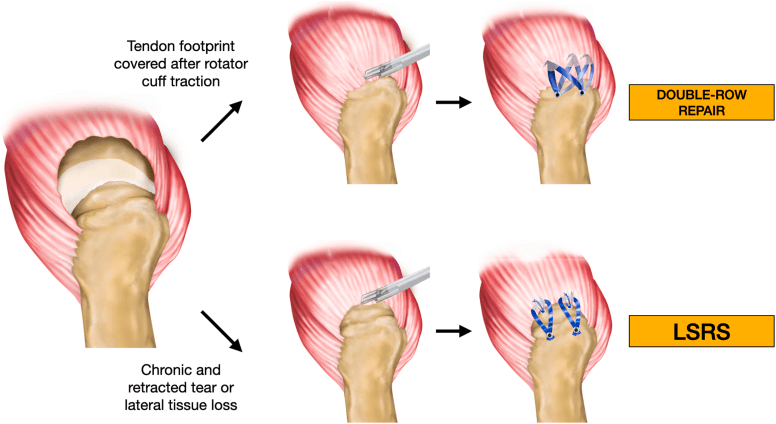
Technique. Arthroscopic or open. Double-row or transosseous-equivalent fixation is stronger, and margin convergence and releases may be needed.
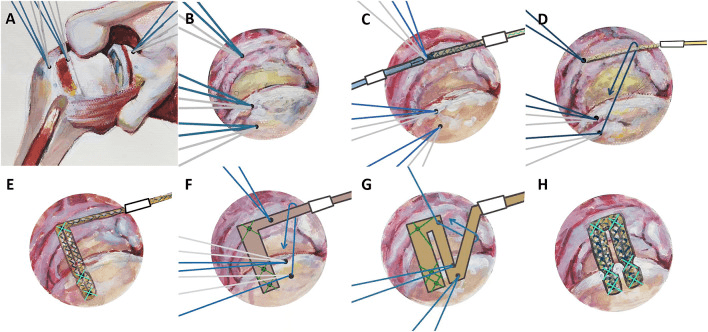
Partial repair. If the tear cannot be fully closed but any tendon is reducible, partial repair with margin convergence is still beneficial because it biomechanically restores the force couples. Synthetic or biologic patches may be used as augmentation.
Complications
After repair
- Incidence
- The rule, not the exception
- Management
- Often still functionally better; consider revision or salvage
- Incidence
- 5-15%
- Management
- Aggressive rehabilitation; may need MUA or lysis
- Incidence
- 1-2%
- Management
- Debridement, antibiotics
- Incidence
- 1-2% (open repair)
- Management
- Repair; may cause significant weakness
- Incidence
- Less than 1%
- Management
- Axillary, suprascapular at risk
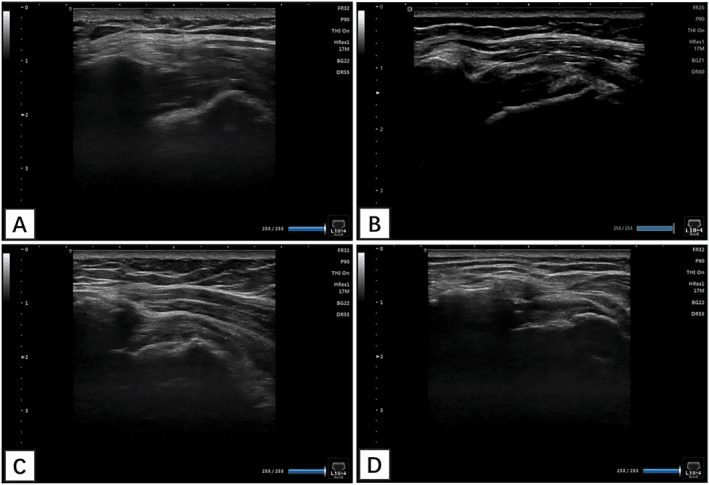
Structural failure after repair of a massive tear is the rule, not the exception. The most-cited series - Galatz et al, JBJS Am 2004 - found recurrent tears in 17 of 18 shoulders (94%), and Paxton's ten-year follow-up of that same cohort confirmed every tear was still present. Patients nonetheless improved in pain and function and stayed improved, because a partial repair restores force couples and scar provides some restraint. Quote the failure rate honestly and then explain why the operation can still be worth doing.
After tendon transfer
Four problems to counsel for:
- Failure of transfer healing - especially latissimus dorsi
- Nerve injury - thoracodorsal (latissimus dorsi), spinal accessory (trapezius)
- Persistent weakness - the transfer may not fully restore function
- Loss of donor function - rarely clinically significant
After reverse shoulder arthroplasty
- Incidence
- 30-50%
- Notes
- Mechanical erosion of scapular neck; usually Grade 1-2
- Incidence
- 2-5%
- Notes
- Especially if prior surgery
- Incidence
- 1-3%
- Notes
- Propionibacterium acnes common
- Incidence
- 3-7%
- Notes
- Due to increased deltoid tension
- Incidence
- 1-5%
- Notes
- More common with osteoporosis
- Incidence
- 2-5%
- Notes
- Dead space in massive RCT
Guidelines, Registries & Global Practice
Global Epidemiology
- Full-thickness cuff tears rise sharply with age; massive tears (greater than 5 cm or 2+ tendons) are a subset concentrated in patients over 60.
- Prevalence of any cuff tear approaches 50% by the eighth decade; many are asymptomatic, so symptomatic massive tears are far less common.
- Male predominance and association with manual/overhead work and smoking are consistent across populations.
- Goutallier 3-4 fatty infiltration on presentation indicates chronic, irreversible muscle change and is the dominant negative prognostic factor worldwide.
Society Guidance, Side by Side
- Position on massive/irreparable tears
- Evidence-based CPG: supports repair where feasible; limited/inconclusive evidence for one technique over another; acknowledges high re-tear rate in large tears
- Position on massive/irreparable tears
- Emphasise structured non-operative care first; reserve RSA for cuff tear arthropathy or true pseudoparalysis; shared decision-making
- Position on massive/irreparable tears
- Algorithmic approach: reparability assessed on retraction, fatty infiltration and subscapularis; SCR and transfer for irreparable non-arthritic, RSA for CTA
- Position on massive/irreparable tears
- Define massive tear, Goutallier, Hamada and Patte classifications as standard exam knowledge
Registry Evidence (Arthroplasty)
- Major joint registries (AOANJRR, NJR-UK, AJRR-US, Nordic registries) all show rapid growth of RSA, now the most common shoulder arthroplasty in many countries, driven largely by cuff tear arthropathy.
- Registry and long-term series report 10-year implant survival of roughly 90%, consistent with the Donoghue 2025 cohort cited above.
- Scapular notching is the most common radiographic finding; symptomatic loosening and instability remain the leading revision reasons.
High- vs Limited-Resource Practice
- In well-resourced settings the full ladder is available: arthroscopic/partial repair, SCR (dermal allograft or fascia lata), tendon transfer, balloon spacer, and RSA.
- Where allograft, implants or arthroscopic expertise are scarce, management shifts toward physiotherapy, biceps tenotomy/debridement, open partial repair, and autograft (fascia lata) rather than dermal allograft for SCR.
- Long waiting times allow tears to progress from Goutallier 2 to 3-4, converting a repairable tear into an irreparable one - an argument for early referral and surgery in active patients.
Controversies & Areas of Uncertainty
- Definition of "massive" and "irreparable": size (greater than 5 cm), tendon number, retraction and fatty infiltration are used inconsistently; irreparability is ultimately an intra-operative judgement, not a fixed MRI threshold.
- Goutallier Grade 3: the borderline grade - some surgeons still attempt repair (often partial), others move directly to transfer/SCR. No consensus.
- SCR graft choice and durability: fascia lata autograft (Mihata) versus dermal allograft, optimal thickness, and long-term durability outside the originating centre remain debated; outcomes are highly operator-dependent.
- Pseudoparalysis terminology: distinction between true pseudoparalysis (loss of active elevation with preserved passive motion) and pseudoparesis is inconsistently applied and affects reported RSA indications.
- RSA in younger patients: lowering the age threshold below 65 is increasingly common but balanced against implant longevity and limited revision options.
- Balloon (subacromial) spacer: short-term symptomatic benefit reported, but high-level evidence for durable benefit over debridement alone is limited.
- Conservative vs surgical for low-demand patients: many massive tears are managed non-operatively with acceptable function; selecting who truly needs surgery is unresolved.
- Tear
- Repairable (reducible, Goutallier 0-2)
- Treatment
- Arthroscopic repair + margin convergence
- Outcome
- Function improves for most; re-tear is the rule not the exception in massive tears
- Tear
- Irreparable (Goutallier 3-4, static retraction)
- Treatment
- SCR or Latissimus dorsi transfer
- Outcome
- Mean shoulder reaches ~66-70% of normal (SSV); pain relief reliable, strength gain small
- Tear
- Irreparable + Cuff tear arthropathy
- Treatment
- Reverse Shoulder Arthroplasty (RSA)
- Outcome
- Excellent pain relief, reliable elevation
- Tear
- Any (large to massive)
- Treatment
- Conservative: physio, injections
- Outcome
- Acceptable for sedentary lifestyle
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 68-year-old man cannot lift his arm. MRI shows complete supraspinatus and infraspinatus tears with Goutallier Grade 4 fatty infiltration. How do you manage him?”
“You are seeing a 52-year-old male carpenter in your shoulder clinic who has been referred by his GP for management of a chronic rotator cuff tear. He initially injured his shoulder 18 months ago when he fell off a ladder at work and has had progressive weakness since then. He has failed 6 months of comprehensive physiotherapy and now has significant functional limitations - he cannot perform overhead work and is at risk of losing his job. On examination, he has weakness of forward elevation (active elevation to 110 degrees only), positive external rotation lag sign, and positive hornblower's sign. He has full passive range of motion. There is no significant glenohumeral arthritis on palpation. You review the MRI report which states: 'Complete full-thickness tear of supraspinatus and infraspinatus tendons. Tear measures 6cm in anteroposterior dimension. Moderate retraction to level of glenoid margin. Subscapularis appears intact. Goutallier grading: Supraspinatus Grade 3 (fat equals muscle), Infraspinatus Grade 2 (fat less than muscle). Tangent sign positive for supraspinatus (atrophy present). No significant glenohumeral arthritis identified.' His plain radiographs show preserved joint space with an acromiohumeral interval of 6mm (borderline). He asks: (1) Can this tear be repaired? (2) What are my options if it can't be repaired? (3) I'm only 52 and still need to work - what would give me the best chance of getting back to work?”
“You are seeing a 58-year-old female administrative manager in your complex shoulder reconstruction clinic for a second opinion. She underwent arthroscopic repair of a massive rotator cuff tear (supraspinatus and infraspinatus) 14 months ago performed by another surgeon. The operative report describes: 'Arthroscopic double-row repair of massive posterosuperior rotator cuff tear. Supraspinatus and infraspinatus mobilized and repaired to footprint with medial row and lateral row anchors. Margin convergence performed to reduce tension. Subscapularis intact.' Post-operatively, she initially improved for about 3-4 months with physiotherapy. However, her symptoms have gradually returned over the past 6 months. She now has significant pain with overhead activities and progressive weakness. She cannot reach overhead to get items from high cupboards and has difficulty washing her hair. On examination today: Active forward elevation 95 degrees (passive 160 degrees), positive external rotation lag sign, positive hornblower's sign, negative belly press test (subscapularis still intact), no significant glenohumeral tenderness. You review her post-operative MRI (performed at 12 months when symptoms returned) which reports: 'Post-surgical changes with anchor artifacts. Complete re-tear of the supraspinatus and infraspinatus repairs with retraction to the level of the glenoid. Marked progression of fatty infiltration since pre-operative imaging - now Goutallier Grade 3-4 in both supraspinatus and infraspinatus. Subscapularis remains intact. No significant glenohumeral joint arthritis. Acromiohumeral interval 7mm (borderline).' Her plain radiographs show: 'Post-surgical changes including subacromial decompression. Humeral head centered with no superior migration. Acromiohumeral interval preserved at 7mm. No glenohumeral arthritis. No hardware complications.' She is very frustrated and asks: (1) Why did my repair fail? (2) What are my options now? (3) Can you redo the repair? (4) I've read about tendon transfers and reverse shoulder replacement - which is right for me?”
Definition
- Greater than 5cm tear
- OR 2+ complete tendon tears
- Assess size, retraction, muscle quality
Goutallier (Fatty Infiltration)
- 0-2: May repair
- 3: Muscle = fat (borderline)
- 4: Fat greater than muscle (irreparable)
Treatment Options
- Repair if reducible, good muscle
- Tendon transfer (lat dorsi, trap)
- SCR (younger, no arthritis)
- RSA (CTA, pseudoparalysis)
Key Concepts
- Pseudoparalysis = loss of force couple
- CTA = irreparable + arthritis
- RSA converts deltoid to mover
Evidence Base
Goutallier Fatty Degeneration Classification - Original Description
- Pre- and post-operative CT in 63 patients graded fatty muscle degeneration in 5 stages (0-4), the foundation of the Goutallier classification
- Infraspinatus fatty degeneration can occur even when its tendon is intact and worsens with time
- After effective repair, moderate supraspinatus degeneration regressed in only 6 of 14 patients; infraspinatus degeneration never regressed and sometimes progressed
- Infraspinatus degeneration had a strongly negative influence on the outcome of supraspinatus repair
Arthroscopic Repair of Large/Massive Tears - High Re-tear, Good Early Function
- 18 completely arthroscopically repaired tears greater than 2 cm, assessed by ultrasound
- Recurrent defects in 17 of 18 shoulders, yet 13 had an ASES score of 90 or more at 12 months
- Forward elevation improved to a mean of 152 degrees despite failed healing
- At minimum 2 years, results deteriorated: mean ASES fell to 79.9 and elevation to 142 degrees
Durability of Clinically Successful but Structurally Failed Repairs - 10-Year Follow-up
- 10-year follow-up of the original Galatz cohort (15 of 18 shoulders) with known structural failure
- Mean ASES 79.4 and pain scores unchanged from 2 years - clinical improvement was durable
- All but one shoulder showed proximal humeral migration or cuff tear arthropathy (Hamada grade 2-4)
- Healing of large tears is not essential for satisfactory long-term clinical results in older patients
Superior Capsule Reconstruction - Biomechanical Rationale
- Cadaveric study of 8 shoulders comparing 3 patch-graft constructs for simulated irreparable tears
- A graft fixed medially to the superior glenoid and laterally to the greater tuberosity (superior capsule reconstruction) fully restored superior translation
- Patch grafting only to the supraspinatus tendon restored superior translation only partially
- All grafts restored subacromial contact pressure but did not alter glenohumeral joint force
Arthroscopic Superior Capsule Reconstruction - Clinical Results
- 24 shoulders (11 large, 13 massive irreparable tears) reconstructed with fascia lata, mean follow-up 34 months
- Mean active elevation improved from 84 to 148 degrees and ASES from 23.5 to 92.9 (both p less than 0.001)
- Acromiohumeral distance increased from 4.6 to 8.7 mm with no progression of osteoarthritis
- 20 of 24 (83%) had no graft tear or retear at final follow-up
Latissimus Dorsi Transfer for Irreparable Tears - Subscapularis Matters
- 69 irreparable tears of at least two complete tendons treated by latissimus dorsi transfer, mean follow-up 53 months
- Subjective Shoulder Value rose from 28% to 66% and relative Constant score from 55% to 73% (both p less than 0.0001)
- Flexion improved from 104 to 123 degrees and abduction strength doubled in shoulders with an intact subscapularis
- In shoulders with poor subscapularis function no improvement occurred - the procedure is of questionable benefit
Latissimus Dorsi Transfer - 10-Year Durability
- 46 shoulders followed a mean of 147 months after latissimus dorsi transfer for irreparable posterosuperior tears
- Subjective Shoulder Value rose from 29% to 70% and relative Constant score from 56% to 80%, with durable pain relief
- Inferior results in shoulders with subscapularis insufficiency or teres minor fatty infiltration
- Better outcomes with a smaller postoperative critical shoulder angle
Reverse Shoulder Arthroplasty - 10-Year Survivorship for Cuff Tear Arthropathy
- 101 primary Grammont-style RSAs in 86 patients (mean age 76), minimum 10-year follow-up
- All-cause implant survivorship 93.2% at 10 years (95% CI 87.8-98.6)
- Most patients died with their primary implant in situ
- Scapular notching present in 79% of implants over 10 years old, but no humeral radiolucency