En bloc resection of primary sacral tumours — margins determine survival
- Chordoma is radioresistant and chemoresistant at conventional doses — wide en bloc resection is the only reliably curative treatment
- Biopsy must be posterior midline transtumoural so the tract can be excised en bloc — NEVER transrectal or transperitoneal
- Neurological deficit is dictated by which roots are sacrificed, not by the bony level per se — and the root that matters is S3, not S2. Preserving both S2 roots while dividing both S3 roots left normal bladder function in only 25 per cent of Todd's patients; preserving at least one S3 raised it to 60 per cent
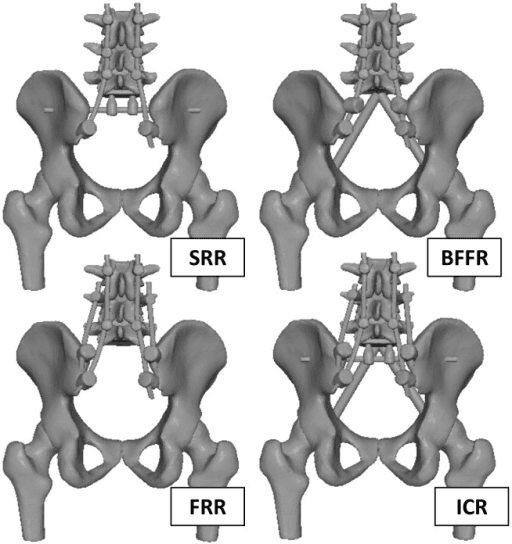
- Total sacrectomy disconnects spine from pelvis: reconstruct with lumbopelvic screw-rod fixation plus anterior column strut (fibula or cage) in a triangulated construct
- Unresectable or high sacral chordoma: definitive carbon-ion or high-dose proton radiotherapy is an established alternative
- “Unilateral root sacrifice at any sacral level generally preserves bladder and bowel through contralateral compensation
- “Bilateral S2-S5 loss produces a flaccid, insensate bladder, incontinent bowel and sexual dysfunction — mandatory pre-operative counselling
- “Silastic sheet placed anterior to the sacrum at the first (anterior) stage protects rectum and vessels during posterior osteotomies
Oncologic Principles and Tumour Biology
Primary sacral tumours amenable to sacrectomy are dominated by three diagnoses.
Chordoma. The commonest primary malignant sacral tumour. It arises from notochordal remnants in the midline, typically in patients in the sixth and seventh decades, and is slow-growing and locally destructive. Histology shows physaliphorous cells, and the tumour is brachyury-positive on immunohistochemistry. It is radioresistant and chemoresistant at conventional doses, so wide en bloc resection is the only reliably curative treatment.
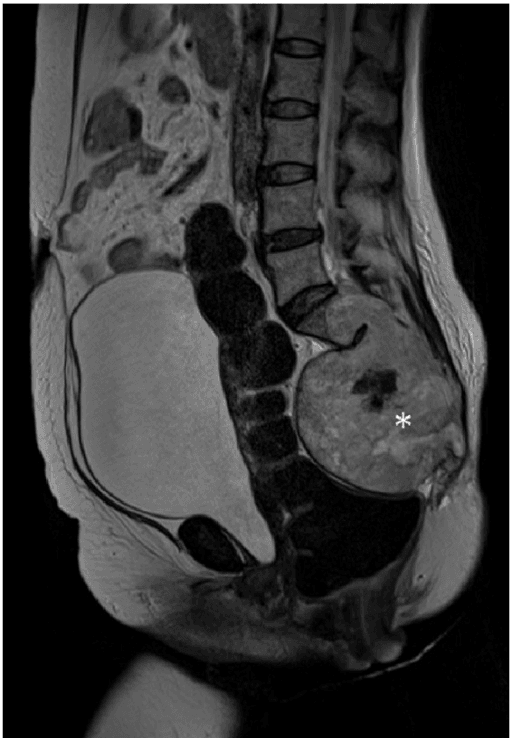
Chondrosarcoma. Eccentric rather than midline, and also radio- and chemoresistant, so the surgical margin is again the decisive variable.
Giant cell tumour (GCT). A tumour of younger patients, in the third and fourth decades, which is eccentric, lytic and expansile. It is benign but locally aggressive, and sacrificing continence for a benign tumour is rarely justified; its management is set out under the decision thresholds below.
Margin is destiny. In sacral chordoma an intralesional or contaminated margin roughly doubles local recurrence against a wide (R0) resection, and local recurrence is the strongest predictor of disease-specific death. Never debulk a resectable chordoma.
Plan backwards from the margin. For chordoma and chondrosarcoma the bony osteotomy level, the roots sacrificed, the amount of gluteus maximus and pelvic floor taken, and whether the rectum must be resected are all dictated by achieving a wide margin, never by the desire to preserve function. Trading margin for function is an oncologic error; trading function without consent is a medicolegal one.
Distant relapse. Local resection does not remove the risk of distant relapse, which mandates surveillance imaging.
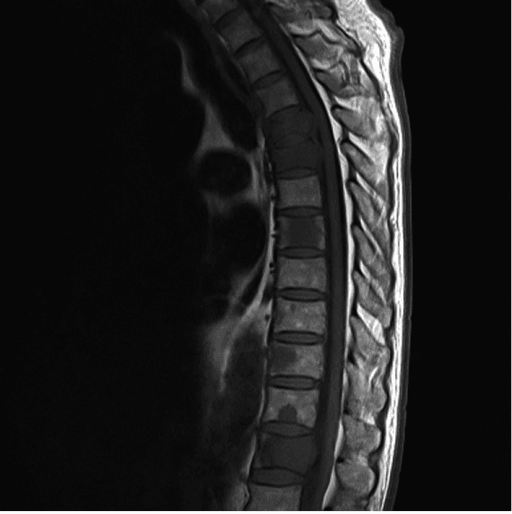
Biopsy
The biopsy is a CT-guided core needle biopsy through a posterior midline transtumoural tract, placed in the line of the future incision, with the tract tattooed or marked. The tract is considered contaminated and is excised en bloc with the specimen.
Contamination of these routes commits the patient to visceral resection or renders the tumour effectively unresectable with margin. Transrectal biopsy contaminates the rectum and may convert a curable tumour into one requiring abdominoperineal resection, or an incurable one. A presacral mass discovered on rectal examination should not be biopsied through the rectum by non-oncology teams; refer it intact to a sarcoma centre.
Anatomy and Neurological Consequences of Root Sacrifice
The roots and what they carry. The sacral roots exit their foramina and merge to form the sacral plexus on the pelvic surface of piriformis. The pelvic splanchnic nerves (S2-S4) carry parasympathetic supply to bladder, rectum and erectile tissue, and the pudendal nerve (S2-S4) supplies the external sphincters and perineal sensation. The level at which the foramina and their exiting roots are divided determines bladder, bowel and sexual function after resection.

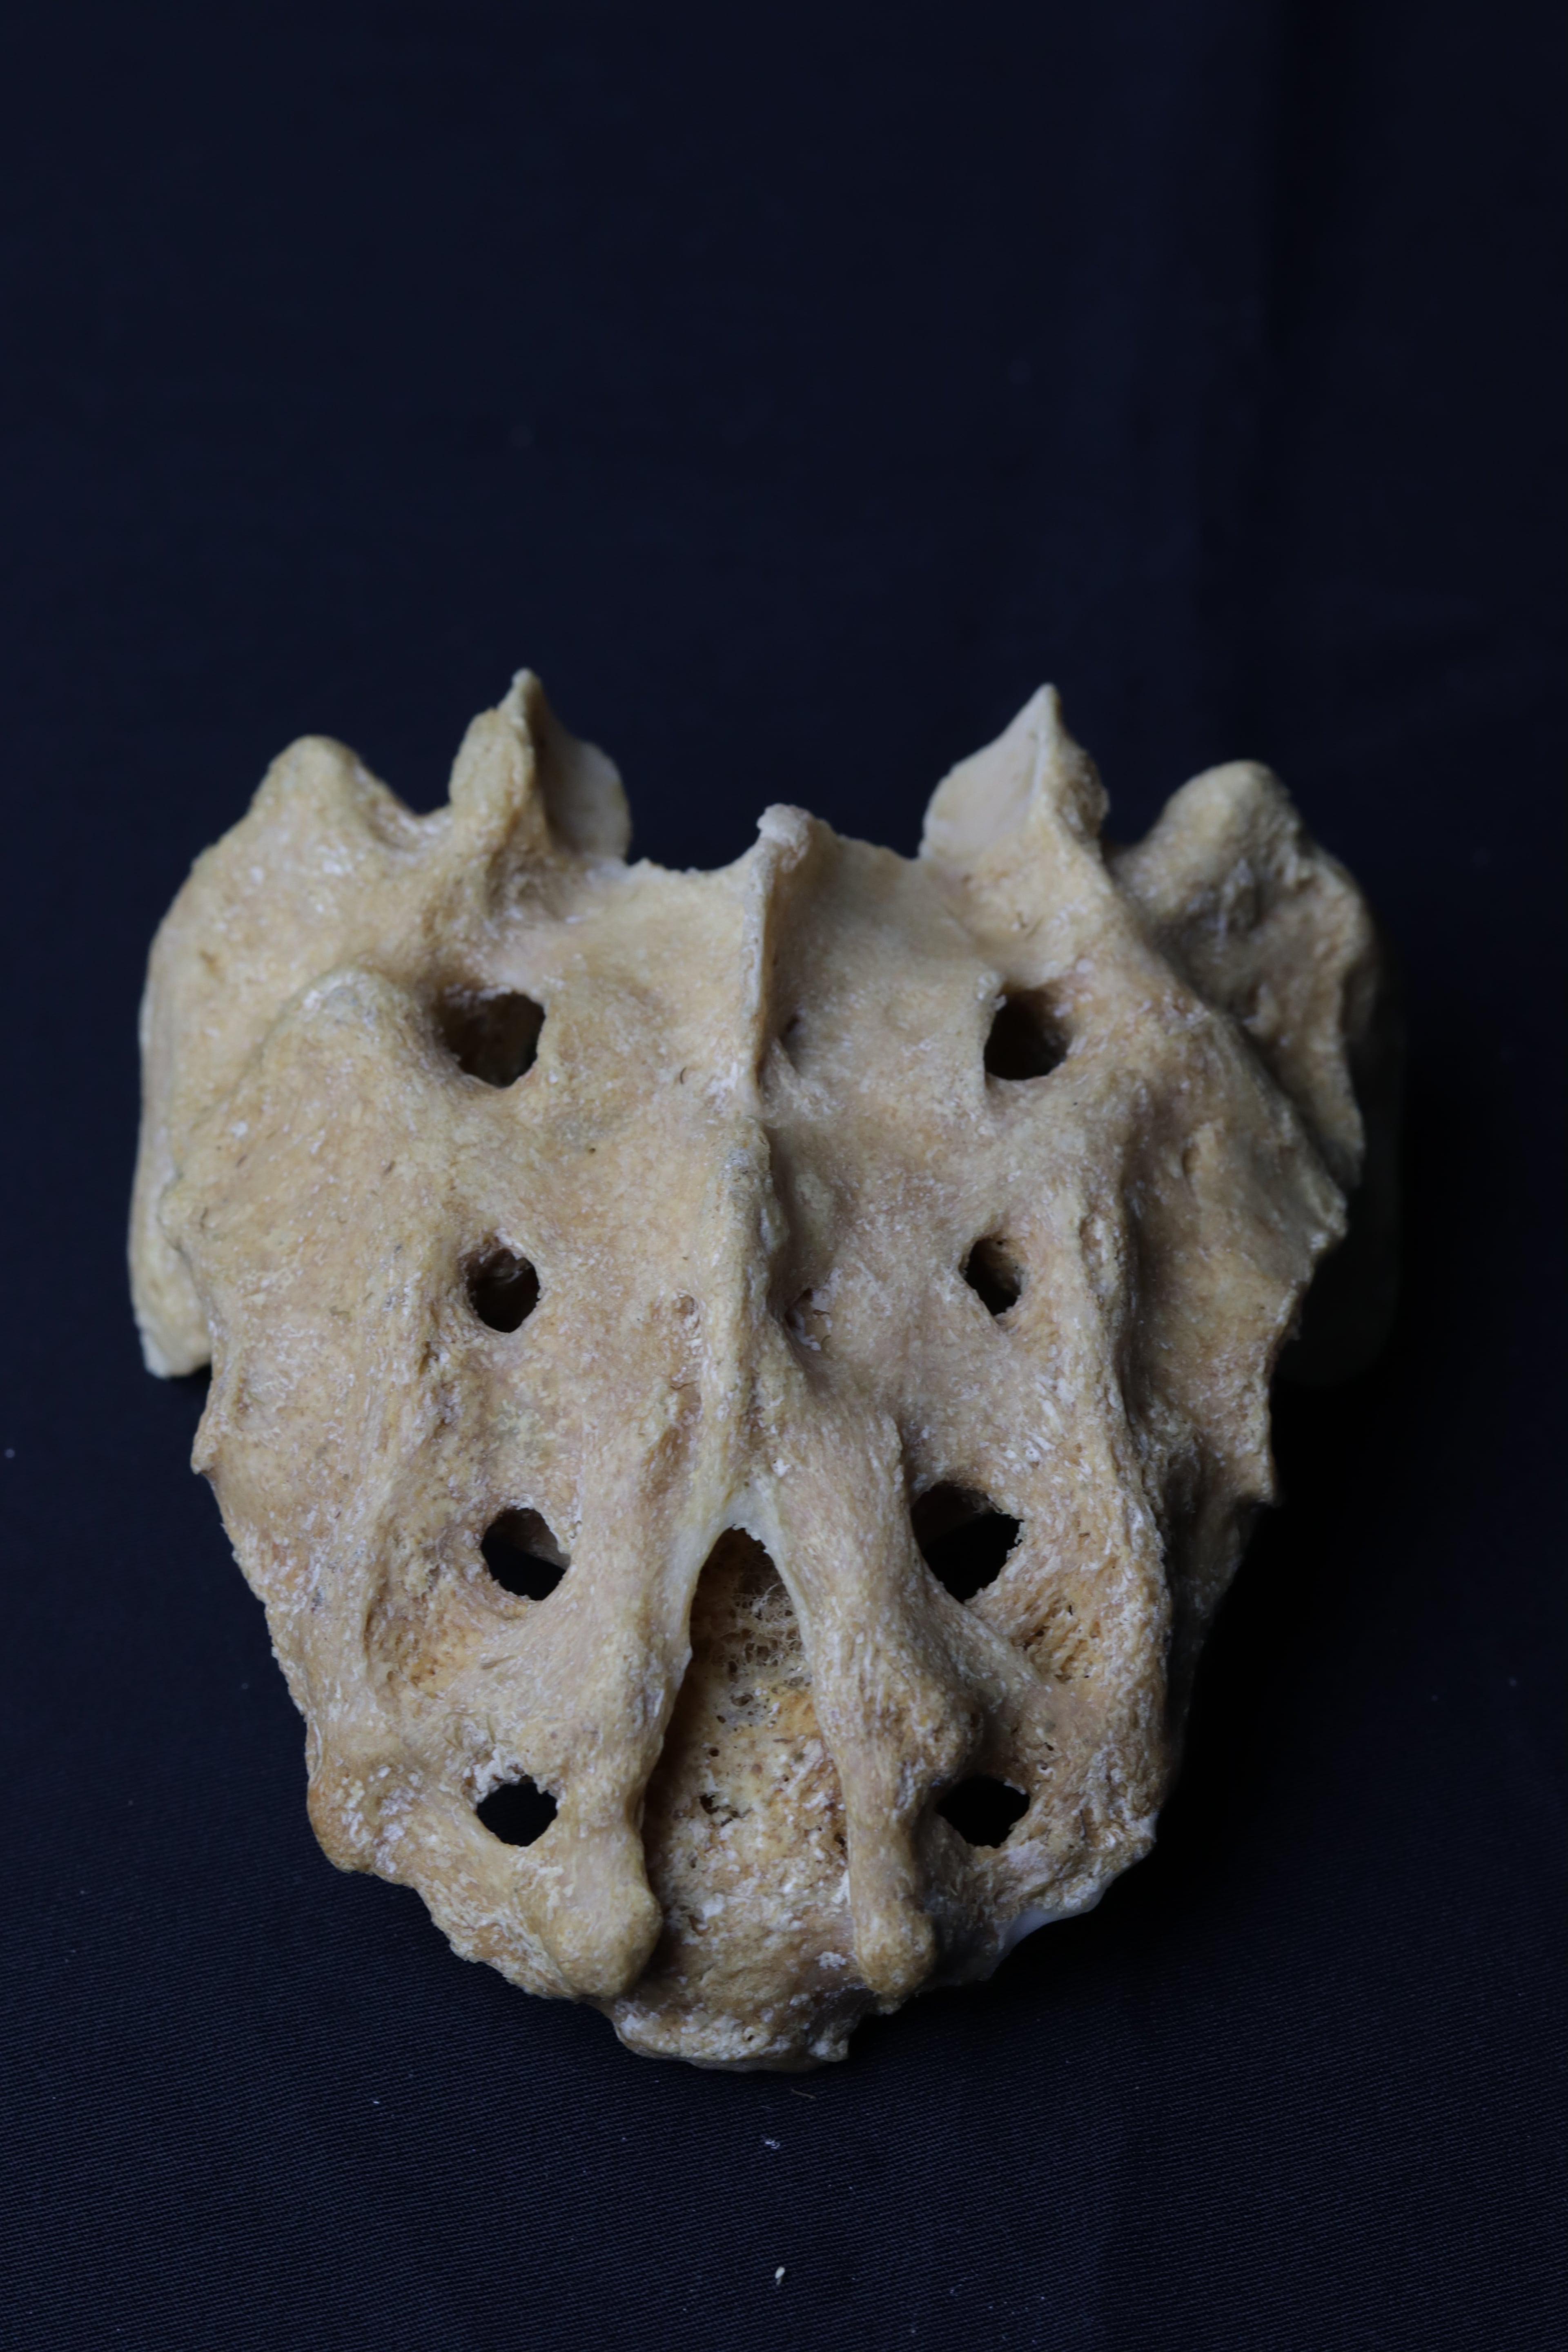
Roots, not bony level. The deficit is dictated by which roots are sacrificed, not by the bony level per se. Unilateral S1-S5 sacrifice (hemisacrectomy) leaves the contralateral pelvic splanchnic and pudendal supply intact, so bladder, bowel and sexual function are usually preserved by contralateral compensation, at the cost of possible ipsilateral motor and sensory loss. Bilateral sacrifice is graded root by root in the table.
- Bladder
- Normal or near-normal; normal in 69 per cent (Todd)
- Bowel
- Normal in 100 per cent (Todd)
- Sexual function / motor
- Preserved
- Overall pattern
- Minimal deficit; no specific continence programme required. S3 is the root that matters
- Bladder
- Usually preserved; normal in 89 per cent after unilateral sacrectomy (Todd)
- Bowel
- Usually preserved; normal in 87 per cent (Todd)
- Sexual function / motor
- Usually preserved; possible ipsilateral motor/sensory loss
- Overall pattern
- Contralateral roots compensate
- Bladder
- Normal in 60 per cent (Todd)
- Bowel
- Normal in 67 per cent (Todd)
- Sexual function / motor
- Largely preserved
- Overall pattern
- Best compromise for mid sacrectomy - the retained S3 is what buys this, not the S2
- Bladder
- Normal in only 25 PER CENT - three-quarters are abnormal
- Bowel
- Normal in only 40 per cent
- Sexual function / motor
- Variable dysfunction
- Overall pattern
- Not a minor deficit. Preserving S2 alone does NOT protect continence; consent accordingly
- Bladder
- Flaccid, areflexic, insensate bladder — intermittent self-catheterisation
- Bowel
- Incontinent, insensate bowel — regimented bowel programme or colostomy
- Sexual function / motor
- Erectile and ejaculatory failure; loss of perineal sensation
- Overall pattern
- Complete sacral deficit; every patient abnormal in Todd's series
- Bladder
- As above
- Bowel
- As above
- Sexual function / motor
- Foot drop, plantarflexion weakness, gait deficit added
- Overall pattern
- Motor deficit superimposed on sphincter loss
Preserve both S2 roots and at least one S3 root and the majority of patients retain socially acceptable bladder and bowel function. The retained S3 is what protects continence: with both S3 roots divided, keeping both S2 roots still left three-quarters of Todd's patients with an abnormal bladder. Bilateral S2-S5 loss leaves every patient abnormal, while unilateral sacrifice at any level is generally well compensated.
Consent follows the roots. Plan the highest root that must be divided, then predict the deficit from that level. Consent must state the expected bladder, bowel and sexual outcome for the planned root sacrifice. The case most often under-warned is bilateral S3 sacrifice with both S2 roots preserved, because "S2 preserved" sounds reassuring.
- Both S3 roots divided, S2 kept: consent explicitly for a high probability of deficit, not a minor one, and arrange bladder retraining, intermittent catheterisation teaching and a bowel regimen in advance
- Bilateral S2-S5 sacrificed: mandatory pre-operative counselling and consent for intermittent self-catheterisation, a regimented bowel programme or colostomy, with stoma and continence nurse review
- Extension to S1 and/or L5: add counselling for an orthosis, gait rehabilitation and lumbopelvic reconstruction
Classification by Level and Approach Selection
- Osteotomy
- Below S3 — distal S3 body or the S3-S4 junction; both S3 roots or lower sacrificed as the margin dictates
- Approach
- Posterior-only, prone, single stage; rectum mobilised bluntly off the anterior sacrum from below through the retrorectal plane after dividing the anococcygeal ligament
- Root sacrifice and function
- Little or no sphincter deficit if S3 is preserved bilaterally or sacrificed on one side only
- Reconstruction and cover
- None — sacroiliac joints intact, pelvic ring uninvolved; primary closure usually sufficient
- Osteotomy
- Through the S2-S3 region; thecal sac ligated below the roots to be preserved
- Approach
- Usually posterior-only in experienced hands; combined approach if there is a large presacral component, prior contamination or previous radiotherapy
- Root sacrifice and function
- Counsel for partial bladder and bowel dysfunction if bilateral S3 is taken
- Reconstruction and cover
- Usually not required — pelvic ring remains in continuity through the upper sacroiliac joints; stress fracture of the residual sacrum can still occur
- Osteotomy
- S1 involvement mandates total sacrectomy — the lumbar spine is disconnected from the pelvis
- Approach
- Staged combined anterior-posterior: typically laparotomy day 1, posterior stage during the same admission
- Root sacrifice and function
- Complete bilateral sacral root sacrifice from S1 or S2 downward with full sphincter deficit; consider planned colostomy
- Reconstruction and cover
- Mandatory spinopelvic reconstruction plus planned soft-tissue flap cover; highest blood loss, longest operating time and greatest complication burden — sarcoma-centre surgery with colorectal, vascular, plastic and spinal collaboration
Posterior-only. Feasible when the anterior tumour extent is modest, the rectal plane is free and vascular control from behind is realistic, which generally means low and mid lesions. Root sacrifice is limited to the planned margin and no anterior stage is needed.
Combined staged anterior-posterior surgery. Chosen for any of the following, with reconstruction and flap cover planned from the outset:
- High or total sacrectomy
- Bulky presacral disease
- Rectal involvement, with en bloc rectal resection and colostomy
- Re-resection after contamination
- Post-radiotherapy tissue
Decision Thresholds in Management
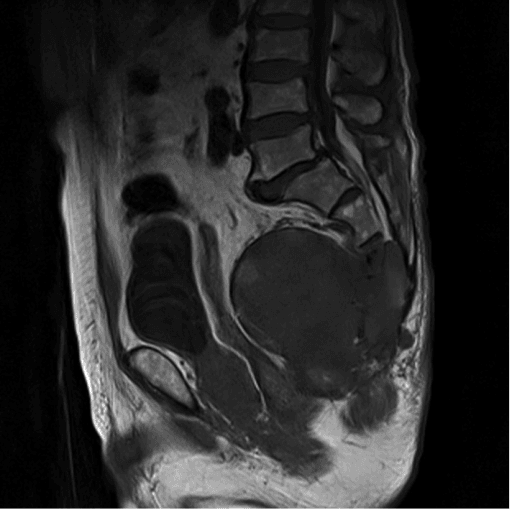
Sacral giant cell tumour. Denosumab and serial embolisation have shifted many sacral GCTs away from sacrectomy toward intralesional surgery or non-operative control. First-line is usually denosumab with or without serial embolisation and, if surgery is needed, nerve-sparing intralesional excision. Sacrectomy with sphincter sacrifice for a benign tumour is reserved for exceptional, refractory, destructive disease.
Resectable chordoma or chondrosarcoma. Where resection carries acceptable morbidity, en bloc wide resection is the standard of care.
Chordoma needing bilateral S2 sacrifice or S1 body resection. Discuss it in a multidisciplinary sarcoma meeting. The options are total sacrectomy accepting a complete deficit, or definitive carbon-ion or high-dose proton radiotherapy, which achieves durable local control in a meaningful proportion of patients and is favoured for surgically unfit patients, patients declining sphincter loss, and some high sacral tumours.
Adjuvant radiotherapy. High-dose photon or proton therapy is commonly added for close margins or after any contamination. Pre-operative radiotherapy protocols exist in some centres but raise wound risk.
Recurrent chordoma. Re-resection is rarely curative once the field is contaminated. Particle therapy and systemic options (brachyury-targeted trials, and imatinib historically, with modest activity) are considered.
Operative Technique
Template the osteotomies. Pre-operative templating of the osteotomies underpins a negative-margin resection.
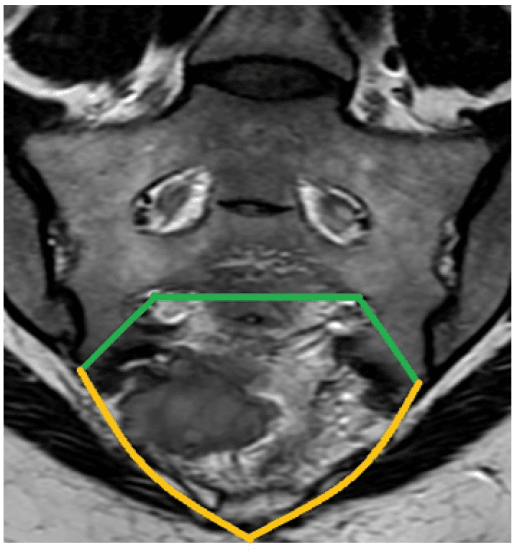
The patient is supine, and the approach is a midline laparotomy, or laparoscopic or robotic in selected centres.
- Mobilise the sigmoid colon and rectum and develop the presacral (retrorectal) plane sharply off the tumour pseudocapsule. If the rectum is adherent or involved, resect it en bloc with the specimen and form a colostomy. Identify and protect both ureters.
- Ligate the median sacral artery. For high resections, ligate or temporarily control both internal iliac arteries and the lateral and median sacral branches, preserving the superior gluteal arteries where possible to protect gluteal flap options. Ligate the internal iliac veins with care: presacral venous plexus injury bleeds torrentially.
- Perform an anterior discectomy or partial corpectomy at the planned proximal level (L5-S1 for total sacrectomy), and score or start the anterior osteotomies and lateral sacroiliac joint cuts so the posterior surgeon works to a defined plane.
- Place a silastic sheet (or mesh or spacer) anterior to the sacrum, separating the rectum and iliac vessels from the posterior osteotomy plane. This is the single most protective manoeuvre for the second stage.
- Consider harvesting a pedicled vertical rectus abdominis myocutaneous (VRAM) flap and tucking it into the pelvis for retrieval at the posterior stage.
- Close, and perform stage two after physiological recovery.
Complications: Rates, Prevention, Management
Haemorrhage. Massive haemorrhage is the leading intraoperative threat. For high resections, anterior-stage ligation of the internal iliac and median sacral vessels, staged surgery and a prepared transfusion protocol are mandatory. The table sets out the mechanism, burden, prevention and salvage of each major hazard.
- Mechanism
- Presacral venous plexus is valveless and diffuse — cannot be suture-ligated; torn during blunt rectal mobilisation
- Typical burden
- Blood loss frequently several litres in total sacrectomy
- Prevention
- Anterior-stage vascular ligation, staged surgery, silastic sheet, hypotensive anaesthesia, correct retrorectal fascial plane, activated transfusion protocol
- If it happens
- Packing, thumbtack occlusion, muscle-fragment welding, rapid completion of resection (bleeding often stops once the specimen is out), interventional radiology
- Mechanism
- Large dead space, thin posterior flaps, irradiated tissue bed
- Typical burden
- 25 to 40 percent, higher after radiotherapy
- Prevention
- VRAM or gluteal flap cover, dead-space obliteration, drains, offloading, nutritional optimisation
- If it happens
- Debridement, negative-pressure therapy, secondary flap
- Mechanism
- Rectal proximity and communication with the wound bed
- Typical burden
- Common, frequently linked to wound failure
- Prevention
- Flap cover, consider diverting colostomy in total sacrectomy, antibiotic protocol
- If it happens
- Debridement, retain hardware early and remove after fusion, prolonged antibiotics
- Mechanism
- Sacral root sacrifice — deficit is planned; unplanned injury to preserved roots also occurs
- Typical burden
- Bladder, bowel and sexual dysfunction proportional to level of root division
- Prevention
- Neuromonitoring, sharp division of intended roots only, preserve roots where oncologically safe
- If it happens
- Intermittent catheterisation, bowel programme, sexual health input, ankle-foot orthosis for L5/S1 loss
- Mechanism
- Thecal sac ligation at the transection level
- Typical burden
- Follows every high transection if closure is imperfect
- Prevention
- Double-ligature or watertight oversew of the sac, fibrin sealant, layered closure
- If it happens
- Lumbar drain; re-exploration and direct repair if persistent
- Mechanism
- Loss of spinopelvic continuity loads the construct until a fusion mass forms
- Typical burden
- Substantial in long-term total sacrectomy survivors
- Prevention
- Triangulated anterior strut plus lumbopelvic rods, generous biological fusion mass
- If it happens
- Observe if fused and asymptomatic; revise if painful instability
Guidelines, Registries & Global Practice
- Epidemiology: chordoma incidence is roughly one per million per year worldwide; sacrococcygeal disease accounts for about half of chordomas, with male predominance and peak in the sixth to seventh decades. Sacral chondrosarcoma and GCT are rarer at this site.
- Society guidance: ESMO/EURACAN and Chordoma Global Consensus Group guidance emphasise referral of presacral masses to sarcoma centres before biopsy, trocar/core biopsy through a resectable posterior tract, en bloc resection with wide margins as standard for chordoma, and high-dose particle therapy (proton or carbon-ion) as definitive treatment where resection is not feasible or declined. NCCN bone tumour guidance mirrors these principles. BOA/BSG sarcoma pathways in the UK mandate management within designated sarcoma networks.
- Registries and multicentre series: there is no arthroplasty-style implant registry for sacrectomy; evidence rests on multicentre collaborations — AOSpine Knowledge Forum Tumour primary spinal tumour cohorts, Rizzoli Institute and Memorial Sloan Kettering chordoma series, and Japanese and Italian carbon-ion cohorts (NIRS/QST Chiba, CNAO Pavia).
- Practice variation by resource setting: carbon-ion facilities exist in only a handful of countries (Japan, Germany, Italy, Austria, China), so surgical resection remains the only curative option in most of the world; in low-resource settings, staged surgery, flap availability and intensive-care capacity constrain total sacrectomy, and non-operative palliation or referral abroad is common for S1-level disease. Denosumab access similarly determines whether sacral GCT is managed medically or surgically.
Controversies & Areas of Uncertainty
- Surgery versus particle therapy for high sacral chordoma: no randomised comparison exists and none is likely, but the field is no longer evidence-free — Yolcu's propensity-matched analysis found no significant difference in overall survival between carbon-ion therapy and en bloc resection (median 68.1 versus 58.6 months, hazard ratio 0.71, p equals 0.53) with markedly less peripheral motor neuropathy after carbon ion (odds ratio 0.13). Read it with its own caveat: the surgical arm was only 54 patients and that confidence interval spans a large benefit either way. Note also that carbon-ion series report ambulation, not continence — Imai's 97 per cent refers to walking, and his paper contains no sphincter data. Long-term insufficiency fracture, late nerve toxicity and the difficulty of salvage after radiotherapy failure remain genuine concerns.
- Rigid spinopelvic reconstruction versus no reconstruction after total sacrectomy: rigid constructs restore load transfer but carry high hardware failure and infection rates; some series report acceptable ambulation without reconstruction.
- Extent of nerve sacrifice for margin: whether a planned marginal (rather than wide) plane over preserved S2/S3 roots is oncologically acceptable in selected chordomas is debated.
- Cell salvage and tumour surgery: traditionally avoided; leucocyte-depletion filters and irradiation of salvaged blood are used in some centres.
- Denosumab in sacral GCT: optimal duration, rebound after cessation, and whether it should replace surgery entirely in the sacrum remain unresolved.
- Prophylactic colostomy in total sacrectomy: reduces perineal wound soiling but adds morbidity; practice varies widely.
MCQ Practice Points
A: Achievement of a wide (R0) surgical margin at the index resection. Contaminated/intralesional resection roughly doubles local recurrence, and local recurrence drives disease-specific mortality.
A: Bilateral S2 preservation with at least one S3 root — the majority retain useful bladder and bowel function, and the retained S3 is what protects continence. Bilateral S2 sacrifice produces a flaccid bladder and incontinent bowel.
A: CT-guided core biopsy through a posterior midline transtumoural tract placed in the line of the planned incision, excised en bloc at resection. Transrectal biopsy is absolutely contraindicated.
A: Total sacrectomy (S1 resection) disconnecting the lumbar spine from the pelvis. Reconstruct with lumbopelvic screw-rod fixation (lumbar pedicle plus iliac screws) triangulated with a fibular or cage anterior strut.
A: Definitive alternative to surgery for unresectable or high sacral chordoma, or where the patient declines sphincter sacrifice — Japanese cohorts show durable local control with sphincter preservation in most patients.
A: Placed anterior to the sacrum after rectal mobilisation and vascular ligation, it protects the rectum and iliac vessels and defines the safe anterior plane for the posterior-stage osteotomies.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 62-year-old man has a firm midline presacral mass palpable on rectal examination and low sacral pain. MRI shows a destructive S3-S5 lesion with a lobulated, T2-hyperintense presacral component. The referring team asks whether to arrange a transrectal biopsy.”
“A 55-year-old woman requires sacrectomy through the S2-S3 junction for chordoma; the plan preserves both S2 roots and one S3 root. She asks exactly what will happen to her bladder, bowel and sexual function.”
“A 48-year-old man has a chordoma involving the S1 body with a large presacral mass abutting but not invading the rectum. He is fit and wishes to pursue curative treatment. Outline your operative strategy.”
“A 26-year-old woman has a large lytic eccentric S1-S2 lesion; biopsy confirms giant cell tumour. A colleague proposes total sacrectomy. What is your view?”
Oncology
- Chordoma: midline, notochordal, brachyury-positive, radioresistant — wide en bloc resection is curative treatment
- R0 margin halves local recurrence versus contaminated resection; recurrence drives mortality
- Biopsy: posterior midline transtumoural core, tract excised en bloc; NEVER transrectal
- Sacral GCT: denosumab and embolisation first; avoid sphincter sacrifice for benign disease
Levels and neurology
- Low (below S3): posterior-only, continence usually preserved if at least one S3 root survives
- Mid (S2-S3): posterior-only usually feasible; keep bilateral S2 plus one S3 for continence in the majority
- High/total (S1): staged anterior-posterior, complete sphincter deficit, reconstruction required
- Unilateral root sacrifice at any level: contralateral compensation preserves function
- Bilateral S2-S5 loss: flaccid bladder, incontinent bowel, sexual dysfunction; add L5/S1 loss = motor deficit
Technique
- Anterior stage: rectal mobilisation, ligate internal iliacs and median sacral, anterior L5-S1 discectomy, silastic sheet, harvest VRAM
- Posterior stage: excise biopsy tract, ligate thecal sac below preserved roots, osteotomies onto silastic sheet, en bloc delivery
- Reconstruction: L3-L5 pedicle screws to double iliac screws, triangulated fibula/cage strut, cross-links, fusion graft
- VRAM flap for total sacrectomy and irradiated fields
Complications and follow-up
- Massive haemorrhage — mitigated by anterior vascular control and staging
- Wound breakdown 25-40 percent; infection, CSF leak, hardware failure in long-term survivors
- Carbon-ion/proton therapy: definitive alternative for unresectable/high sacral chordoma
- Surveillance: MRI of the resection bed plus chest imaging at regular intervals for at least ten years — chordoma recurs late
Evidence Base
Operative Management of Sacral Chordoma
- 52 patients operated for sacrococcygeal chordoma at one institution between 1980 and 2001, followed a mean of 7.8 years
- A wide margin was achieved in only 21 of 52 - fewer than half
- ALL patients with a wide margin survived, significantly better than marginal or intralesional excision (p equals 0.0001)
- Local recurrence occurred in 23 patients (44 per cent); recurrence-free survival was 59 per cent at 5 years and 46 per cent at 10 years; overall survival 74, 52 and 47 per cent at 5, 10 and 15 years
- 17 of the 21 wide margins came from a COMBINED ANTEROPOSTERIOR approach and only 4 from a posterior-only approach
Bowel and Bladder Function After Major Sacral Resection
- 53 patients undergoing major sacral resection at one institution over 10 years, analysed retrospectively for bowel and bladder outcome by the roots divided
- UNILATERAL sacrectomy with contralateral roots preserved: normal bowel in 87 per cent, normal bladder in 89 per cent
- Bilateral S4-S5 division with BOTH S3 roots preserved: normal bowel in 100 per cent, normal bladder in 69 per cent
- Asymmetric resection preserving AT LEAST ONE S3 root: normal bowel in 67 per cent, normal bladder in 60 per cent
- Bilateral S3-S5 resection - that is, both S2 roots preserved but no S3: normal bowel in only 40 per cent and NORMAL BLADDER IN ONLY 25 PER CENT
- Bilateral S2-S5 sacrifice: ALL patients had abnormal bowel and bladder function
- The authors' stated conclusion: unilateral resection, OR preservation of at least one S3 root in a bilateral resection, preserves function in the majority
Carbon Ion Radiation Therapy for Unresectable Sacral Chordoma: An Analysis of 188 Cases
- 188 patients with UNRESECTABLE primary sacral chordoma treated at a single Japanese institute between 1996 and 2013, median age 66, median follow-up 62 months
- Proximal invasion reached above S2 in 137 of the 188 - this is a high-level, surgically difficult population
- Five-year local control 77.2 per cent, overall survival 81.1 per cent, disease-free survival 50.3 per cent
- 41 patients had a local recurrence; sex, tumour volume, level of proximal invasion and dose were all UNRELATED to local control
- Toxicity: grade 3 peripheral nerve in 6 patients and grade 4 skin in 2
- AMBULATION was retained in 97 per cent - note that the paper reports ambulation, NOT sphincter function, which it does not measure
Comparison of Oncologic Outcomes and Treatment-Related Toxicity of Carbon Ion Radiotherapy and En Bloc Resection for Sacral Chordoma
- 911 patients in total: 188 treated with carbon ion radiotherapy, 54 with en bloc resection, and 669 from the National Cancer Database as a survival comparator
- After PROPENSITY SCORE MATCHING there was NO significant difference in overall survival between carbon ion therapy and en bloc resection - median 68.1 versus 58.6 months (hazard ratio 0.71, p equals 0.53)
- The carbon ion cohort had substantially LESS peripheral motor neuropathy (odds ratio 0.13, 95 per cent CI 0.04 to 0.40, p less than 0.001)
- Against matched database cohorts, carbon ion therapy gave better survival than margin-positive surgery without adjuvant radiotherapy (64.7 versus 60.6 months, p equals 0.03) and far better than primary photon radiotherapy alone (64.9 versus 31.8 months, p less than 0.001)
- The authors position carbon ion therapy for older patients with high performance status in whom surgery is not preferred, and after margin-positive resection