A low-grade cartilage tumour with an abrupt transition to a juxtaposed high-grade non-cartilaginous sarcoma — the most lethal chondrosarcoma variant
- Defining histology is an ABRUPT junction between low-grade cartilage and a high-grade non-cartilaginous sarcoma — not a gradual grade transition.
- Both components share clonal genetic changes, including IDH1/IDH2 mutations, supporting a single precursor clone rather than collision of two tumours.
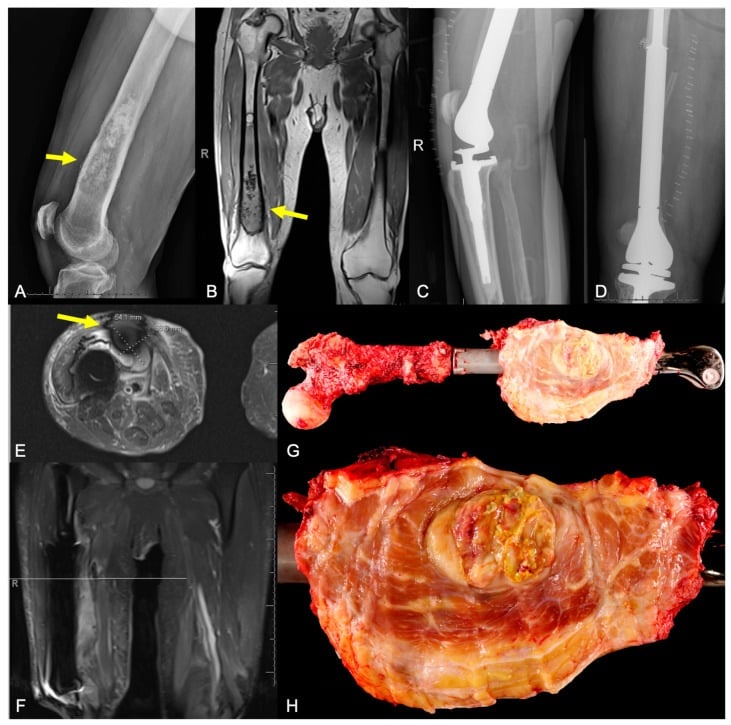
- Imaging is bimorphic: a ring-and-arc mineralised cartilage component adjacent to a purely lytic destructive area with cortical breach and soft-tissue mass.
- The biopsy must sample the LYTIC component. Sampling only the mineralised area yields low-grade cartilage and understages the tumour.
- Prognosis is dismal — early lung metastasis, median survival often under two years; local control alone rarely alters outcome.
- Pathological fracture is common at presentation and complicates limb salvage.
- “Longstanding dull ache for years that suddenly accelerates over weeks in an older patient equals dedifferentiation until proven otherwise.
- “A rising, expanding lytic area within a known atypical cartilaginous tumour on surveillance is the classic dedifferentiation signal.
- “Chemotherapy is often given to fit patients using osteosarcoma-type regimens, but registry and multicentre data show at best modest and inconsistent survival gain.
- “Radiotherapy is used for inoperable pelvic disease and palliation, not as a curative substitute for resection.
- “Amputation may be the only wide-margin option in a large pelvic or proximal femoral tumour with fracture haematoma contamination.
Definition, Biology and Why It Matters
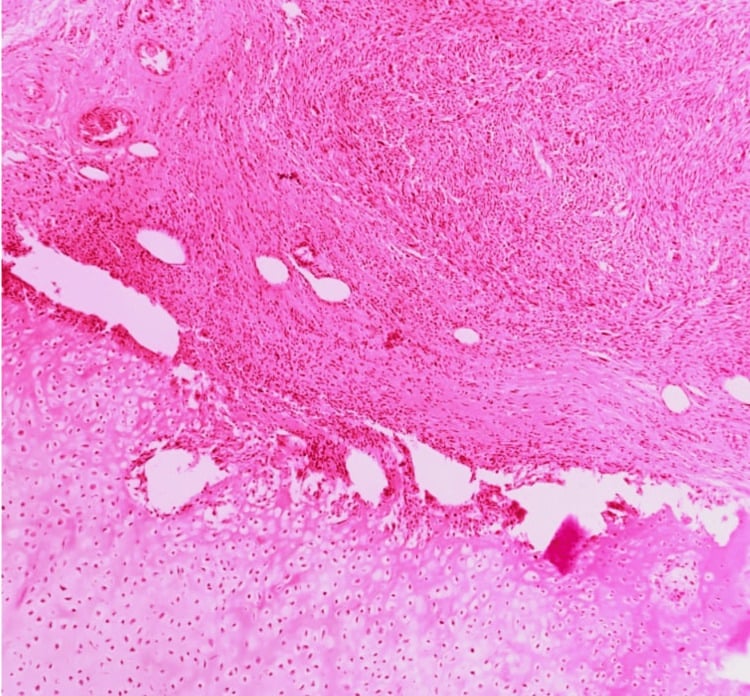
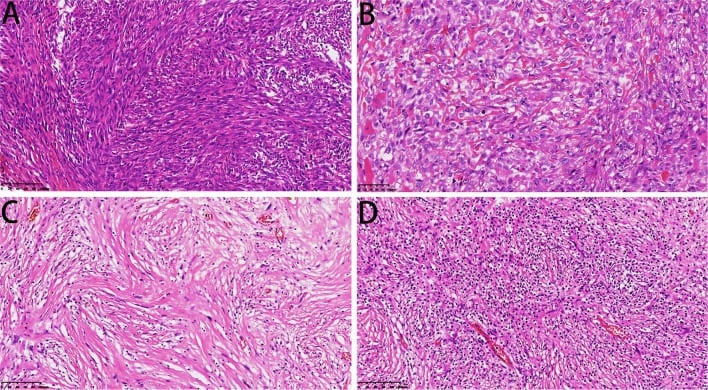
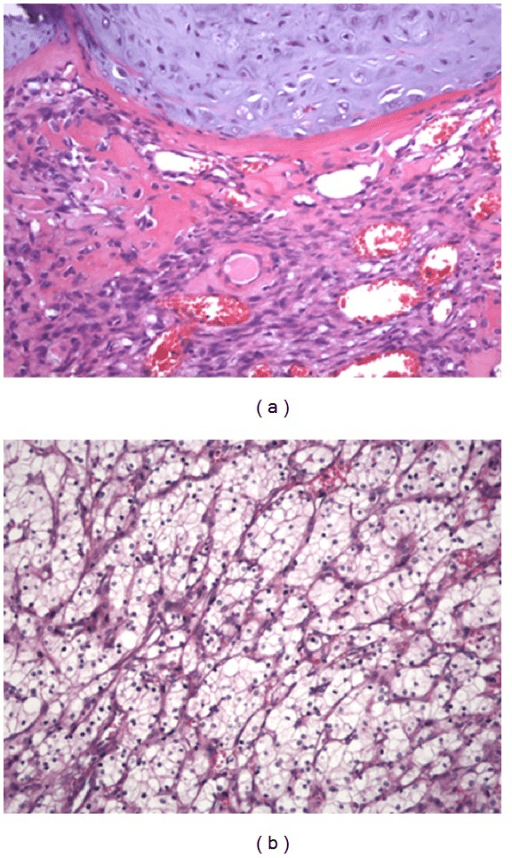
The definition. Dedifferentiated chondrosarcoma is the juxtaposition of a low-grade cartilaginous neoplasm and a high-grade non-cartilaginous sarcoma with an abrupt, sharply demarcated interface. What defines it is the junction. The high-grade component is most often an undifferentiated pleomorphic sarcoma or a fibrosarcoma-like spindle cell sarcoma, but it may be osteosarcomatous, rhabdomyosarcomatous or angiosarcomatous.
This is not grade progression. A grade 1 lesion that becomes grade 3 stays cartilaginous, and the change is gradual. Dedifferentiation means the cartilaginous phenotype is lost altogether, with a knife-edge boundary between the two populations.
One clone, not two tumours. The two components are clonally related. Shared mutations, including the IDH1 and IDH2 hotspot mutations typical of conventional central cartilage tumours, are found in both the cartilage and the dedifferentiated component in the majority of cases, which supports dedifferentiation of one clone rather than a collision of two tumours. Further events accumulate in the high-grade element: TP53 alteration, CDKN2A loss and a complex karyotype.
Where it arises.
- De novo at presentation
- Within a pre-existing central chondrosarcoma or atypical cartilaginous tumour
- In enchondromatosis (Ollier disease, Maffucci syndrome)
- In a secondary peripheral chondrosarcoma arising from an osteochondroma, the rarer route
Why it matters. The biology is that of a high-grade pleomorphic sarcoma of bone in an older adult, superimposed on a chemoresistant cartilage matrix. Survival tracks the high-grade component. The cartilage component is prognostically irrelevant, except that it makes the tumour look deceptively benign.
Epidemiology and Presentation
Who. Roughly 10 to 15 percent of all chondrosarcomas. The peak is in the sixth and seventh decades, it is rare before 40, and most series show a slight male predominance.
Where. In descending frequency: pelvis (especially the periacetabular ilium), proximal femur, femoral diaphysis and distal femur, proximal humerus, scapula, ribs. The hands and feet are almost never involved.
Who is at risk. A known central chondrosarcoma under surveillance; Ollier disease and Maffucci syndrome, where the lifetime risk of malignant transformation is substantial and dedifferentiation is reported; and multiple hereditary exostoses, the rarer route.
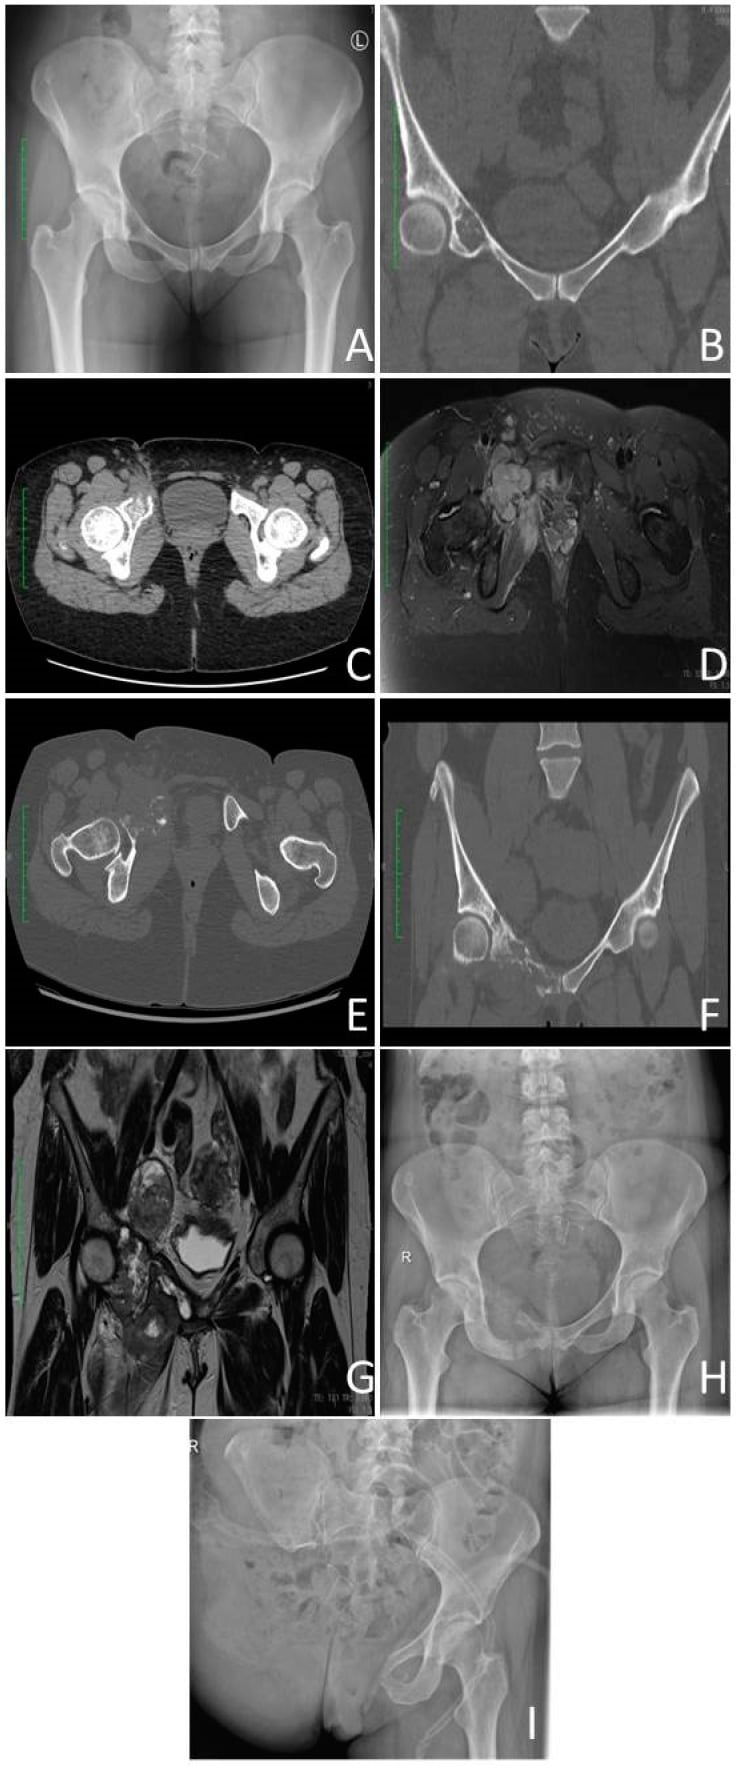
The history is biphasic. Years of low-grade, deep, aching pain, attributed to arthritis, trochanteric bursitis or back pain, correspond to the indolent cartilage tumour. Then, over weeks to a few months, the pain accelerates: severe rest and night pain, a rapidly enlarging mass and loss of function. In an older patient, a longstanding dull ache that suddenly accelerates over weeks is dedifferentiation until proven otherwise.
Pathological fracture is the presenting event in up to a third, typically subtrochanteric or through the femoral neck, or an acetabular insufficiency-type collapse.
Examination. The surgeon's sequence:
- Inspect standing and supine for a visible or palpable mass, limb girth asymmetry, venous distension over the thigh or buttock, and prior biopsy scars.
- Palpate with the patient supine and the limb relaxed, using flat fingers to define the mass, a deep, fixed, non-tender-to-mobile firm swelling. Note whether it moves with muscle contraction; if it does not, it is deep to fascia.
- Move the hip with the pelvis stabilised by the examiner's contralateral hand on the anterior superior iliac spine. In periacetabular disease, expect painful terminal internal rotation with an irritable-hip pattern.
- Rectal and abdominal examination for pelvic tumours: an intrapelvic extension may be palpable, and it changes the approach and the vascular plan.
- Neurovascular examination of sciatic, femoral and obturator function and distal pulses. Sciatic involvement in an ilium or sciatic notch tumour predicts the need for nerve sacrifice, and therefore a flail foot after limb salvage.
- Regional nodes. Nodal spread is rare, but examine them to exclude other diagnoses.
Red flags in a known cartilage lesion. New night pain, pain not related to load, a change in analgesic requirement, a new palpable mass, or a fracture through a previously stable lesion. On surveillance imaging, the classic signal is a rising, expanding lytic area within a known atypical cartilaginous tumour.
Staging and Prognostic Factors
Staging. On the Enneking (MSTS) system essentially every case is stage IIB, high grade and extracompartmental, or III if metastatic. AJCC staging applies but adds little to decision-making beyond metastatic status.
The outlook. Five-year survival is roughly 10 to 25 percent across series; Mercuri's 74 cases gave 13 percent.
What worsens it.
- Effect
- Dominant adverse factor; median survival months
- Effect
- Worse than appendicular, because the margin is harder to get
- Effect
- Contamination, higher amputation rate, worse survival
- Effect
- Higher local recurrence and reduced survival
- Effect
- Associated with poorer outcome in several series
- Effect
- Limit the ability to deliver chemotherapy or major resection
Achieving a wide margin without metastatic disease is the only variable consistently associated with prolonged survival. Local control by itself, in the presence of pulmonary metastases, does not rescue the patient, which is why the metastatic work-up must precede a decision about internal hemipelvectomy or amputation.
Imaging: The Bimorphic Hallmark
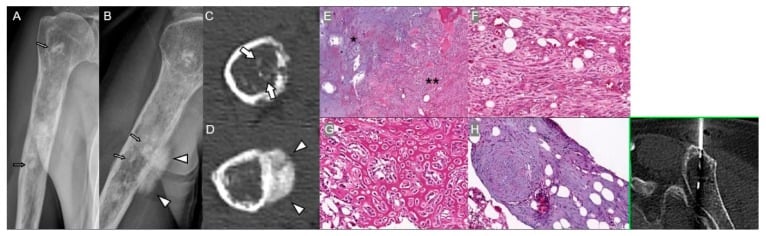
Radiographs. Orthogonal films of the whole involved bone, plus an AP pelvis for pelvic lesions. Look for two adjacent but different territories in the same bone:
- Appearance
- Ring-and-arc, popcorn or stippled chondroid mineralisation, endosteal scalloping, fusiform expansion, relatively defined margins
- Appearance
- Purely lytic, geographic to permeative, no matrix, cortical destruction, periosteal reaction, extraosseous mass
The abrupt change from a mineralised, chronic-looking region to an aggressive lytic region in the same bone is the single most useful radiographic sign. Endosteal scalloping greater than two thirds of cortical thickness, cortical breach and any soft-tissue mass push a cartilage lesion out of the atypical cartilaginous tumour category.
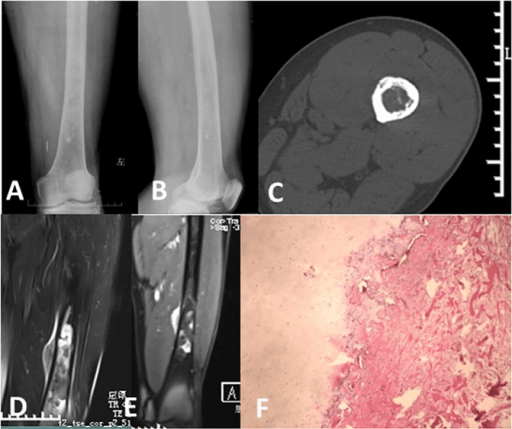
MRI. Whole-bone coverage, axial and coronal T1, fluid-sensitive sequences (STIR or T2 fat-suppressed) and post-gadolinium T1 fat-suppressed, with a dynamic contrast sequence where available. The two components read differently:
- Cartilage: lobulated, very high T2 signal, low-to-intermediate T1, peripheral and septal (ring-and-arc) enhancement with non-enhancing lobule centres, and slow progressive septal filling on the dynamic sequence
- Dedifferentiated: intermediate T2 signal, avid, early, heterogeneous solid enhancement, necrosis, and a soft-tissue mass extending beyond the cortex; on the dynamic sequence the enhancement is early and rapid
MRI also defines what the resection needs: intraosseous extent, measured from a reproducible landmark because it sets the resection level; joint involvement; neurovascular encasement; compartmental spread; and skip lesions.
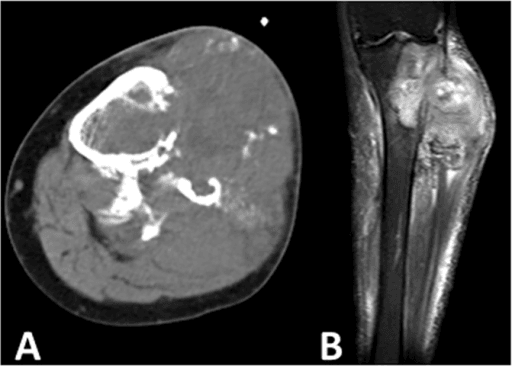
CT of the primary best demonstrates chondroid mineralisation, cortical destruction and the bony geometry of the pelvis for resection planning, 3D navigation and custom cutting guides. Where a pelvic tumour abuts the iliac vessels, add angiography or CT angiography and arrange vascular surgical support before resection.
CT chest is mandatory. Pulmonary metastases are the dominant failure mode, and a significant proportion of patients already have them at diagnosis. Discovering metastatic disease after a morbid internal hemipelvectomy is an avoidable tragedy: staging precedes any resection planning.
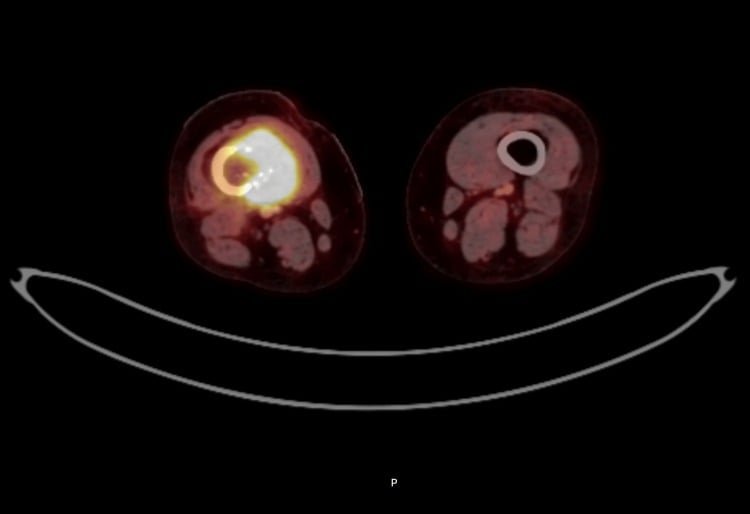
Whole-body bone scan or FDG PET-CT detects distant disease, and PET has a second job. The dedifferentiated component shows a markedly higher SUV than the cartilage component, so the metabolically hottest area is the biopsy target.
When it does not look bimorphic. The bimorphic sign is the teaching point, but it is not universal. Mercuri classified the central lesions in 74 cases into three radiographic patterns, and only the first is the picture described above:
- n
- 36
- What the film shows
- A central chondrosarcoma plus a region of very aggressive change
- Why it is missed
- Rarely missed: this is the classic bimorphic appearance
- n
- 20
- What the film shows
- Looks like a benign enchondroma, but with destructive change and/or a large soft-tissue mass
- Why it is missed
- The cartilage is read first and the destruction is dismissed as incidental
- n
- 8
- What the film shows
- Not distinctive at all: a high-grade destructive lesion of bone with no recognisable cartilage
- Why it is missed
- Nothing on the film suggests a cartilage tumour; diagnosed only after biopsy or resection
Type 2 is the one this page exists for. A lesion reported as an enchondroma does not become safe because the cartilage looks benign. The question is whether anything else on the film is doing something an enchondroma cannot do, and a soft-tissue mass or frank destruction is exactly that.
Type 3 sets the limit of imaging. In roughly one in eight central cases there is no radiographic clue at all, which is why the diagnosis is also a pathologist's responsibility. Because the non-cartilaginous component may be a very small proportion of the tumour, the resection specimen must be sampled throughout rather than at the obvious lesion.
Biopsy: Technique and Rules
Stage first. Complete the imaging of the primary and the chest CT before any biopsy. Biopsy haemorrhage and oedema degrade later MRI and can obscure the true tumour boundary, so the imaging is banked first. If the imaging shows a destructive lytic zone or soft-tissue mass abutting the mineralised cartilage, treat the lesion as dedifferentiated until proven otherwise; if it does not, manage it as a conventional cartilage lesion with interval surveillance.
Who does it. The biopsy is performed by, or in direct consultation with, the surgeon who will resect. Referral to a sarcoma unit before biopsy reduces unplanned excisions and amputations, and the tract is planned to lie within the resection or flap-sacrifice zone.
Where the needle goes. Core needle biopsy under CT or ultrasound guidance, directed at the soft-tissue mass or lytic intraosseous area and away from necrotic centres. The surgeon marks the solid enhancing zone on the images and hands that image to the radiologist performing the biopsy. Take multiple cores; send fresh tissue for cytogenetics and molecular work, and material for culture if infection is a differential. The high-grade component lives in the lytic zone, not in the calcified cartilage: a needle passed through the mineralised area returns bland low-grade cartilage, the tumour is understaged, and the patient is treated as a grade 1 lesion.
Tract discipline. A longitudinal approach, a single tract, the shortest route through one compartment, avoiding neurovascular bundles and joints. Mark the skin entry with a permanent marker or tattoo, or record it precisely, because the tract is excised en bloc at definitive surgery.
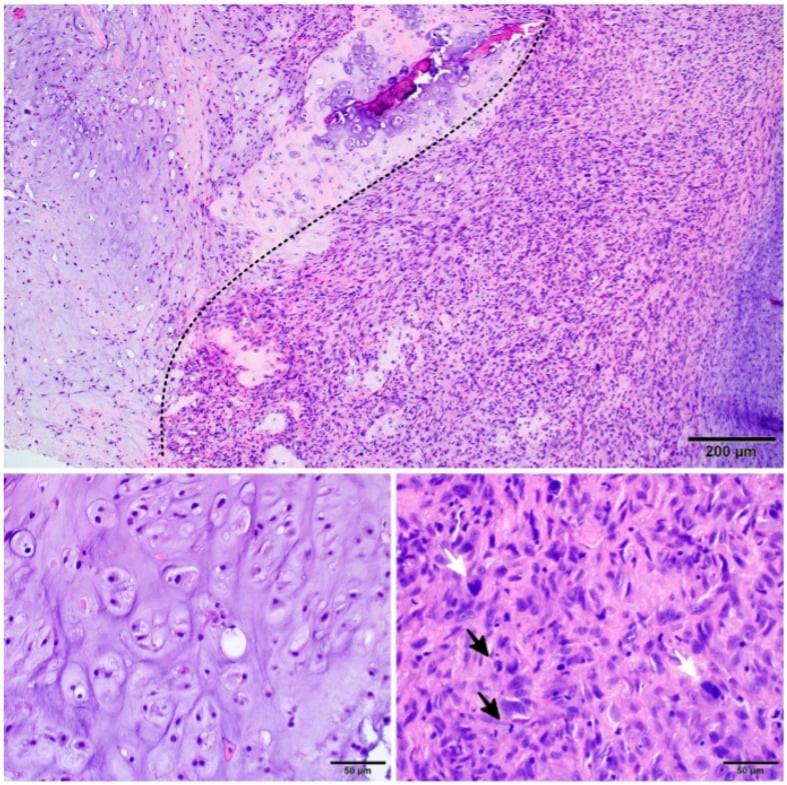
What the pathologist should see. Two populations with an abrupt border. Immunohistochemistry supports the dedifferentiated line: desmin and myogenin if rhabdomyosarcomatous, and S100 absent in the high-grade area whereas the cartilage is S100 positive. IDH1/IDH2 mutation testing supports cartilage lineage and can help separate dedifferentiated chondrosarcoma from primary osteosarcoma or undifferentiated pleomorphic sarcoma of bone. A concordant high-grade result confirms the diagnosis, and the case proceeds to definitive staging and resection planning.
If PET, dynamic MRI or plain films show a discrete lytic or solid area, the biopsy must be steered there. A report of "low-grade cartilage tumour" from a needle placed in the calcified region does not exclude dedifferentiation: in the face of a destructive lytic zone it means the lytic area was missed. When histology and imaging disagree, the imaging wins. Review at the sarcoma MDT with radiology and pathology together, and re-biopsy the lytic zone under image guidance. A discordant benign result triggers re-biopsy, not reassurance.
Differential Diagnosis
- Discriminating features
- Same older-adult, central-skeleton and long-bone setting; cartilaginous throughout with gradual increase in cellularity, nuclear atypia and myxoid change; no abrupt non-cartilaginous component; still lobular high T2 signal
- Consequence of getting it wrong
- Better survival than dedifferentiated; chemotherapy not offered
- Discriminating features
- Younger patient; malignant osteoid produced directly by tumour cells throughout; cartilage is malignant, not low grade; no abrupt interface
- Consequence of getting it wrong
- Chemosensitive: neoadjuvant chemotherapy is standard and outcome far better
- Discriminating features
- Young adults, bone and extraskeletal sites; small round blue cells with haemangiopericytoma-like vessels and islands of well-formed hyaline cartilage, intimately admixed rather than meeting at an abrupt front; chondroid calcification within an aggressive round cell mass on imaging; HEY1-NCOA2 fusion; a distinct entity, not IDH driven
- Consequence of getting it wrong
- Treated as a round cell sarcoma with surgery and multi-agent chemotherapy; carries a better prognosis than dedifferentiated disease
- Discriminating features
- Multiple lesions, known primary, monoclonal protein; no chondroid matrix
- Consequence of getting it wrong
- Radiotherapy and fixation appropriate, but never fix a solitary destructive lesion without a diagnosis
- Discriminating features
- No cartilage component anywhere on imaging or in generous sampling; IDH wild type
- Consequence of getting it wrong
- Similar high-grade management; distinction is prognostic and academic in practice
- Discriminating features
- Serpiginous infarct margins or coarse trabecular Paget bone with lytic destruction
- Consequence of getting it wrong
- Different setting, similarly poor prognosis
Management: Decision Thresholds
Confirm and stage. The diagnosis rests on an adequately targeted core biopsy reviewed at a sarcoma MDT, and the staging on CT chest, cross-sectional imaging of the primary and PET-CT where available. Nothing is planned until both are done.
Localised disease in a fit patient. The question is whether a wide margin can be had, and at what functional cost:
- A wide margin achievable with acceptable function: wide en-bloc resection with reconstruction
- A wide margin only by sacrificing critical structures (sciatic nerve plus iliac vessels, extensive fracture contamination): amputation or external hemipelvectomy may be the only oncologically sound option, discussed frankly against palliative alternatives given the prognosis
- An unresectable primary (extensive intrapelvic, sacral or vascular encasement in a frail patient): palliation with radiotherapy, analgesia, stabilisation of an impending fracture and early palliative care involvement
Metastatic at presentation. The balance shifts sharply towards symptom control. Resection of the primary is justified mainly for pain, fungation or impending fracture, not for cure.
Chemotherapy is considered in fit patients with localised, high-volume dedifferentiated disease, as an MDT decision and ideally within a trial, with honest counselling that the evidence is weak.
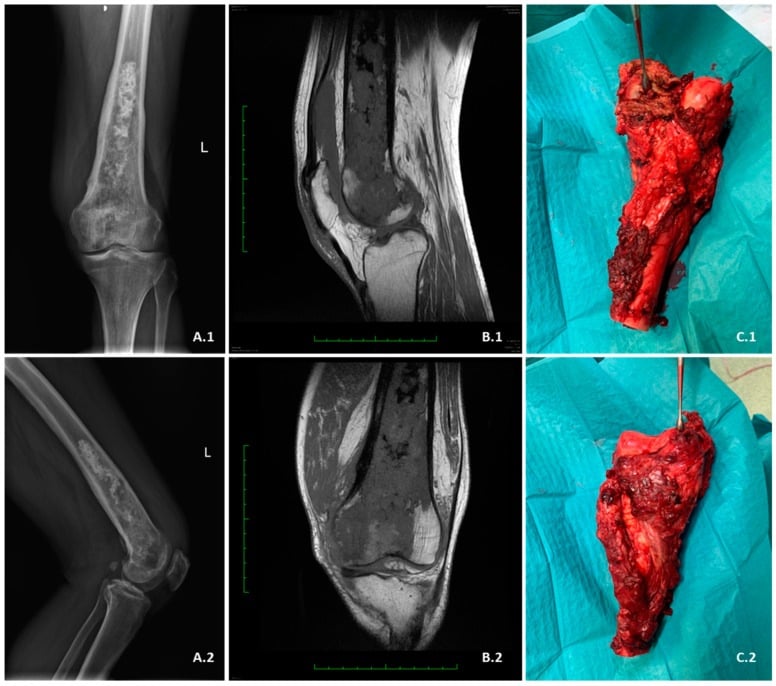
An older patient with a destructive proximal femoral lesion and a fracture is not automatically a metastasis. Intramedullary nailing of an undiagnosed dedifferentiated chondrosarcoma contaminates the entire femoral canal and converts a resectable tumour into a hindquarter or hip disarticulation problem. Investigate, biopsy, then decide.
STOPPre-treatment checklist before any bone lesion surgery in an older adult
Hook:STOP before the saw — the first operation determines whether cure is still possible.
Complications and Follow-Up
Local recurrence is commonest after marginal or intralesional margins and after fracture, and usually heralds systemic disease. Re-resection or amputation is offered only if the recurrence is isolated and the patient has no metastases; in the pelvis, recurrence is usually managed palliatively. An unplanned excision in a non-specialist centre leaves marginal or intralesional margins that contaminate the field, and the answer is wide re-excision of the whole surgical field.
Pulmonary metastasis is the dominant cause of death, typically within 12 to 24 months. Occult nodules present at diagnosis make radical local surgery futile, which is why the staging CT chest precedes any resection. Once metastases appear the intent of treatment is reassessed: metastasectomy is considered only for few, resectable, late nodules with a controlled primary, and otherwise care is palliative and symptom-directed.
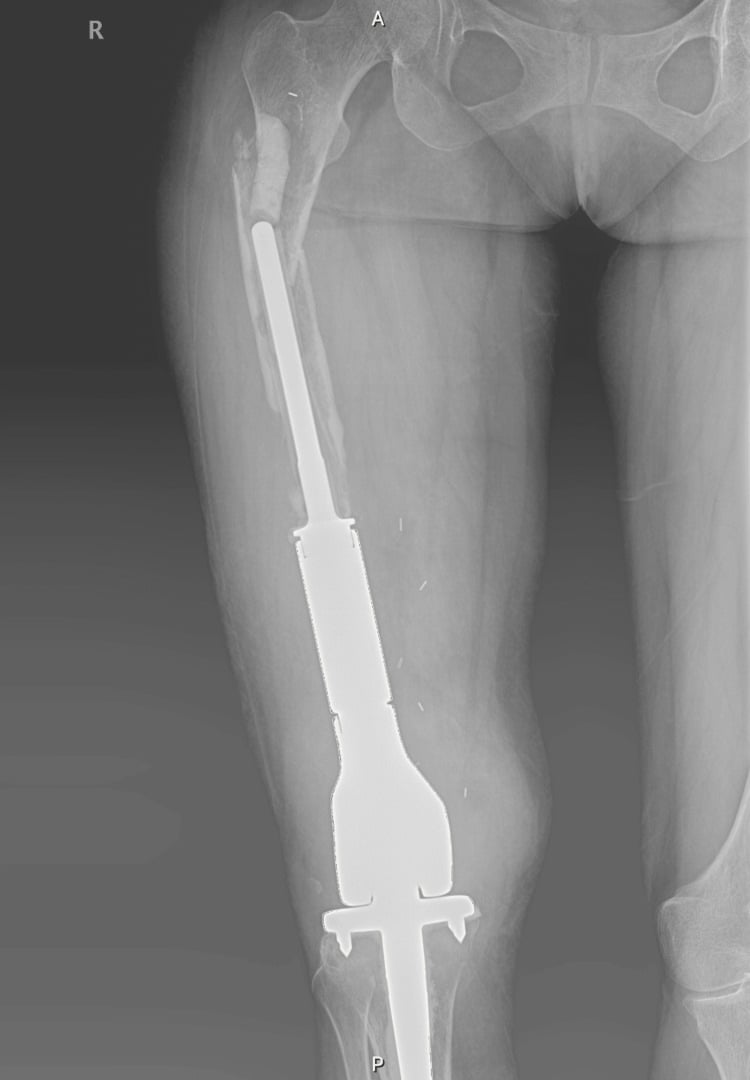
The reconstructed pelvis. Deep infection rates after custom pelvic implants are high, and prior radiotherapy or superior gluteal artery sacrifice adds flap necrosis and wound breakdown, so plastic surgical involvement belongs at the planning stage. Infection is managed with debridement and targeted antibiotics; if uncontrolled, the implant is removed and the hip converted to a flail hip, or the limb to a hindquarter amputation. Instability of a pelvic or proximal femoral endoprosthesis is countered with abduction bracing, constrained or dual-mobility bearings and mesh soft-tissue reconstruction.
Nerve sacrifice. The sciatic or femoral nerve may be encased by tumour or divided to achieve a wide margin. Map the neurovascular relationship on the pre-operative MRI, counsel and consent for the deficit before surgery, and provide an ankle-foot or knee-extension orthosis and gait retraining afterwards. Do not compromise the margin to spare the nerve.
Chemotherapy toxicity. Anthracycline cardiotoxicity, nephrotoxicity and myelosuppression are significant in the seventh decade and are weighed against an unproven benefit.
Surveillance is clinical review with local imaging and CT chest every 3 months for 2 years, then 6-monthly to 5 years, then annually, a schedule that reflects the front-loaded risk. In practice surveillance often shifts to symptom-directed and supportive care once metastases appear.
Guidelines, Registries & Global Practice
Global epidemiology. Chondrosarcoma is the second or third commonest primary bone sarcoma worldwide and is proportionally more important in ageing populations; the dedifferentiated variant, at roughly 10 to 15 percent of chondrosarcomas, is therefore encountered in almost every regional sarcoma unit but rarely in general orthopaedic practice. Incidence appears broadly similar across regions; differences in reported outcome largely reflect stage at presentation and access to specialist surgery.
Society guidance — where it genuinely applies
- What it says relevant to this topic
- Management of bone sarcoma in reference centres; biopsy by the treating team; wide surgical excision is the mainstay for chondrosarcoma; chemotherapy of unproven benefit in conventional and dedifferentiated chondrosarcoma outside trials
- What it says relevant to this topic
- Dedifferentiated chondrosarcoma may be treated along osteosarcoma lines in selected fit patients; wide excision remains primary; radiotherapy for unresectable or close-margin disease
- What it says relevant to this topic
- Any suspicious bone lesion referred to a sarcoma diagnostic service before biopsy; imaging pathway with plain radiograph then MRI; strict prohibition on local biopsy or excision of suspected bone sarcoma
- What it says relevant to this topic
- Defines dedifferentiated chondrosarcoma by the abrupt bimorphic pattern; separates it from grade 3 conventional and mesenchymal chondrosarcoma
- What it says relevant to this topic
- Emphasise centralisation of bone sarcoma surgery and multidisciplinary decision-making
Registry evidence. Bone sarcoma registries and national cancer datasets (for example the Netherlands and Scandinavian bone tumour registries, and large population datasets) consistently show that dedifferentiated chondrosarcoma has the worst survival of all chondrosarcoma subtypes, that pelvic location and metastatic presentation dominate outcome, and that treatment at high-volume centres is associated with better margin rates. Arthroplasty registries (NJR, AJRR, AOANJRR, SHAR, NZJR) contribute mainly by documenting the high revision, infection and dislocation burden of tumour endoprostheses and custom pelvic reconstructions relative to primary arthroplasty — data worth quoting when counselling about reconstruction.
Practice variation by resource setting.
- High-resource centres: navigation and 3D-printed patient-specific guides and implants, particle therapy for unresectable axial disease, molecular profiling and trial access.
- Middle-resource settings: wide resection with off-the-shelf endoprostheses, allografts or hip transposition; radiotherapy for unresectable disease; chemotherapy availability variable.
- Low-resource settings: late presentation with fungating or fractured tumours; amputation or hindquarter amputation is often the only feasible oncological operation, and palliative care provision becomes the central issue. Prognostic honesty and pain control are universal obligations regardless of setting.
Controversies & Areas of Uncertainty
- Does chemotherapy help? The central controversy. Retrospective data conflict; there is no randomised evidence. Some centres treat all fit patients as high-grade osteosarcoma, others reserve chemotherapy for trials only. Selection bias plausibly explains most reported benefit.
- Radical surgery versus palliation in metastatic disease. With a median survival often under a year in metastatic cases, an internal or external hemipelvectomy may consume the patient's remaining functional life. Some units offer it for uncontrolled local symptoms only.
- Reconstruct or not after pelvic resection. Custom implants restore better limb length and function but carry high infection and mechanical failure rates; hip transposition and flail hip are lower-morbidity options that some argue better suit a short prognosis.
- Margin width. No agreed millimetre threshold. Contaminated fields after fracture or prior surgery make "wide" a judgement rather than a measurement.
- Surveillance of atypical cartilaginous tumours. How intensively and for how long to image indolent cartilage lesions to catch dedifferentiation early is unsettled; over-surveillance is costly and anxiety-provoking, under-surveillance misses the treatable window — and it is unproven that earlier detection of dedifferentiation improves survival.
- Role of particle therapy and IDH-directed agents. Promising but with limited access and immature outcome data.
MCQ Practice Points
Q: What single histological feature defines dedifferentiated chondrosarcoma?
A: An abrupt transition between a low-grade cartilaginous tumour and a high-grade non-cartilaginous sarcoma. The criterion is about the interface, not about either component: a gradual increase in cellularity and atypia within cartilage is high-grade conventional chondrosarcoma, not dedifferentiation.
Q: Which area must be biopsied and why?
A: The lytic, non-mineralised, avidly enhancing area. Sampling the calcified cartilage yields low-grade histology and understages the tumour, risking inappropriate intralesional treatment. Mercuri's point sharpens this: the non-cartilaginous component may be a very small fraction of the tumour, so a core through cartilage is a negative test that carries no information.
Q: What is the approximate five-year survival?
A: Grim, and quoted across series as roughly 10 to 25 per cent. The one figure you can attach to a named series is Mercuri's 13 per cent in 74 cases at the Rizzoli Institute. Early pulmonary metastasis is the dominant cause of death. What improved survival in that series was prompt diagnosis and achievement of a wide or radical margin, which is also why pelvic tumours do worse — the margin is harder to get, not the biology different.
Q: What molecular finding supports a common clonal origin of both components?
A: Identical IDH1 or IDH2 hotspot mutations in both the cartilaginous and the dedifferentiated component. Yang's paired-component study adds the more direct evidence: the same X-chromosome inactivation pattern in both halves of the same tumour, which is evidence against a collision tumour rather than merely consistent with a shared origin.
Q: A young adult has a bone tumour with small round cells and islands of hyaline cartilage. What is the diagnosis?
A: Mesenchymal chondrosarcoma, characterised by the HEY1-NCOA2 fusion. It is treated with multi-agent chemotherapy and carries a better prognosis than dedifferentiated disease — but do not call it "chemosensitive" as though a survival benefit were established: Xu's systematic review of 107 patients (PMID 25849226) found anthracycline-based chemotherapy did not improve overall survival, and it was the negative margin that predicted local control and event-free survival. Its biphasic pattern is small round cells beside cartilage — not the abrupt low-grade-cartilage-to-high-grade-sarcoma interface of dedifferentiation. Age separates them too: mesenchymal is a young adult tumour, dedifferentiated is a tumour of the fifth decade onwards.
Q: What is the role of radiotherapy?
A: Non-curative. It is used for unresectable axial or pelvic disease, close or positive margins, and palliation of pain or impending fracture; particle therapy is used for unresectable axial disease in selected centres. Mavrogenis states the same limit plainly — high-dose radiotherapy is confined to inaccessible sites and to palliation.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 68-year-old man has had a dull right hip ache for four years, previously labelled osteoarthritis. Over ten weeks the pain has become severe and wakes him at night. Radiographs show a proximal femoral lesion with ring-and-arc mineralisation in the diaphysis and an adjacent purely lytic area with cortical destruction in the subtrochanteric region. How do you proceed?”
“A CT-guided core biopsy of a large periacetabular lesion in a 62-year-old woman reports 'low-grade cartilage neoplasm, features of atypical cartilaginous tumour'. The MRI, however, shows a 9 cm avidly enhancing solid extraosseous mass beside a lobulated calcified intraosseous component. The referring team proposes curettage and cement. What is your response?”
“A 70-year-old woman presents to the emergency department with a displaced femoral neck fracture after a trivial stumble. Radiographs of the pelvis show chondroid calcification in the femoral neck and a lytic destructive area extending into the intertrochanteric region. She is already scheduled for hemiarthroplasty. What do you do?”
“A fit 58-year-old man with a localised dedifferentiated chondrosarcoma of the ilium asks whether he should have chemotherapy, having read that osteosarcoma patients do well with it. How do you counsel him?”
Definition and biology
- Low-grade cartilage tumour with ABRUPT junction to high-grade non-cartilaginous sarcoma
- High-grade element: undifferentiated pleomorphic sarcoma, fibrosarcoma-like, osteosarcomatous or rhabdomyosarcomatous
- Single clone — shared IDH1/IDH2 mutations in both components
- 10 to 15 percent of all chondrosarcomas; sixth to seventh decade; pelvis and femur
Presentation
- Years of indolent ache then abrupt escalation over weeks
- Rest and night pain, rapidly enlarging deep mass
- Pathological fracture in up to a third at presentation
- Arises de novo, in existing chondrosarcoma, or in Ollier/Maffucci disease
Imaging
- Radiograph: ring-and-arc mineralisation beside a purely lytic destructive area with cortical breach
- MRI: lobulated high T2 cartilage with septal enhancement, adjacent solid avidly enhancing mass
- CT primary for matrix and pelvic geometry; CT chest mandatory
- PET-CT identifies the hottest area as the biopsy target
Biopsy rules
- Stage before biopsy; biopsy by or with the resecting surgeon
- Target the lytic/solid enhancing component
- Single longitudinal tract, excisable en bloc, avoid neurovascular bundles and joints
- Discordant benign result equals re-biopsy, not reassurance
Management
- Wide en-bloc resection is the only curative-intent treatment
- Amputation or hindquarter amputation where wide margin otherwise unachievable
- Chemotherapy: osteosarcoma-type regimens in fit patients, weak and conflicting evidence, prefer trials
- Radiotherapy for unresectable disease, close margins and palliation
- No curettage, no cementing, no nailing of an undiagnosed lesion
Prognosis and pitfalls
- Five-year survival roughly 10 to 25 percent; early lung metastasis
- Adverse: metastasis at diagnosis, pelvic site, fracture, positive margin, large dedifferentiated volume
- Surveillance: clinical review and CT chest 3-monthly for 2 years then tapering
- Key error: treating it as a grade 1 cartilage lesion because the biopsy missed the lytic zone
Evidence Base
Dedifferentiation of Low-Grade Chondrosarcomas
- Named the entity: a low-grade cartilage tumour abutting an anaplastic non-cartilaginous sarcoma, with an abrupt interface rather than a gradual change in grade.
- The indexed sites span the skeleton the page describes - femur, humerus, tibia, scapula, ribs and lumbar spine - and amputation is indexed as a treatment, which is what the outlook was in 1971.
- Framed the lesion as a change in behaviour within a known cartilage tumour, not as a new tumour arising beside one.
Dedifferentiated Chondrosarcoma - 74 Cases with a Radiographic Classification
- 74 cases of central and peripheral dedifferentiated chondrosarcoma reviewed at the Rizzoli Institute.
- Overall five-year survival 13 per cent - not a range, a single figure from the largest early series.
- Three radiographic patterns among the central cases: TYPE 1 (36 cases) looks like a central chondrosarcoma PLUS a region of very aggressive change; TYPE 2 (20) looks like a benign enchondroma PLUS destruction or a large soft-tissue mass; TYPE 3 (8) is not distinctive at all and presents as a high-grade destructive lesion, diagnosed only after biopsy or resection.
- The non-cartilaginous component may make up a very small OR a very large proportion of the tumour, so diagnosis often requires histological evaluation of the entire specimen.
- Survival improved where diagnosis was prompt and a wide or radical margin was achieved. No benefit was found from adjuvant chemotherapy or radiotherapy.
Clonality Analysis and IDH1/IDH2 Mutation Detection in Both Components
- DNA was extracted SEPARATELY from the cartilaginous and the dedifferentiated component of the same tumour in 18 patients.
- X-chromosome inactivation analysis in the 9 female patients showed the same inactivation pattern in both components.
- IDH1 and IDH2 mutation status was consistent between the two components across all 18.
- Concluded that the two components arise from the same primitive cell - dedifferentiated chondrosarcoma is monoclonal in origin, not a collision of two tumours.
Dedifferentiated Chondrosarcoma Revisited
- Wide or radical surgical resection is stated as mandatory - the review offers no alternative curative route.
- High-dose radiotherapy is confined to inaccessible sites and to palliation.
- Chemotherapy is given 'whenever the dedifferentiated component is chemosensitive and the patient is in good general condition' - the decision follows the histology of the high-grade half, not the diagnosis of chondrosarcoma.
- Despite this approach, metastases result in poor survival.
The Hazards of the Biopsy, Revisited
- Errors in diagnosis, technique and complications from biopsy were several times more frequent when the biopsy was performed outside the treating tumour centre.
- In a significant proportion of patients the biopsy adversely altered the treatment plan or outcome, including unnecessary amputation.
- A re-audit of the same society's 1982 study, finding the problem essentially unchanged over more than a decade.