Associated Injuries Critical | Glenoid Fractures Key | Floating Shoulder Concept
- High-energy injury - always look for associated thoracic and shoulder girdle injuries
- Floating shoulder = scapula neck + clavicle fracture disrupts superior shoulder suspensory complex
- Glenoid fractures are the most important - articular involvement determines outcome
- Most body fractures heal well conservatively - surgery for articular/neck displacement
- Ideberg classification for glenoid fossa fractures guides surgical decision-making
- “80-95% have associated injuries - ribs, lung, clavicle, brachial plexus
- “Scapulothoracic dissociation = devastating - high mortality, look for it
- “Glenoid step more than 4mm or fragment more than 25% = surgical indication
- “Lateral border offset 20mm or more, or angulation 45 degrees or more = ORIF neck
Overview and Epidemiology
Scapula fractures are uncommon injuries that typically result from high-energy trauma. The scapula is protected by thick muscle coverage, and significant force is required to fracture it.
Mechanism. Motor vehicle accidents are the most common cause, at 50-70%. Falls from height and direct blows (crush injuries) account for others. Sport causes them uncommonly, and then typically with low energy.
A marker of energy. A scapula fracture indicates massive energy transfer, and the fracture itself is often less important than the injuries that came with it. Maintain a high suspicion for associated injuries and always perform a thorough trauma assessment.
Mortality is 10-15%, primarily from associated thoracic and head injuries rather than from the scapula fracture itself.
How treatment has shifted. Traditionally, scapula fractures were treated almost universally conservatively, with good results. The shift to surgical treatment in selected cases is based on a better understanding of outcomes with significantly displaced glenoid neck and articular fractures.
Anatomy and Biomechanics
The bone. The body is a flat triangular bone, thin at 2-7mm. The named parts:
- Spine - posterior ridge that divides supraspinatus from infraspinatus
- Acromion - lateral extension of the spine, articulating with the clavicle
- Coracoid process - anterior projection carrying muscle and ligament attachments
- Glenoid fossa - articular surface for the humeral head
- Glenoid neck - transition between glenoid and body
The superior shoulder suspensory complex (SSSC). A bone-ligament ring that suspends the upper extremity from the axial skeleton. Its components are the glenoid process, coracoid, coracoclavicular (CC) ligaments, distal clavicle, AC joint and acromion, with the scapular spine forming the ring superiorly. The clavicle is its superior strut, the link to the axial skeleton. A single disruption is stable; a double disruption is the floating shoulder, a potential instability that is judged on residual glenoid displacement.
Muscles. Seventeen muscles attach to the scapula, including:
- Rotator cuff - supraspinatus, infraspinatus, teres minor, subscapularis
- Scapulohumeral - deltoid (partial), coracobrachialis, biceps (long head)
- Axioscapular - trapezius, levator scapulae, rhomboids, serratus anterior
- Scapulothoracic - pectoralis minor, omohyoid
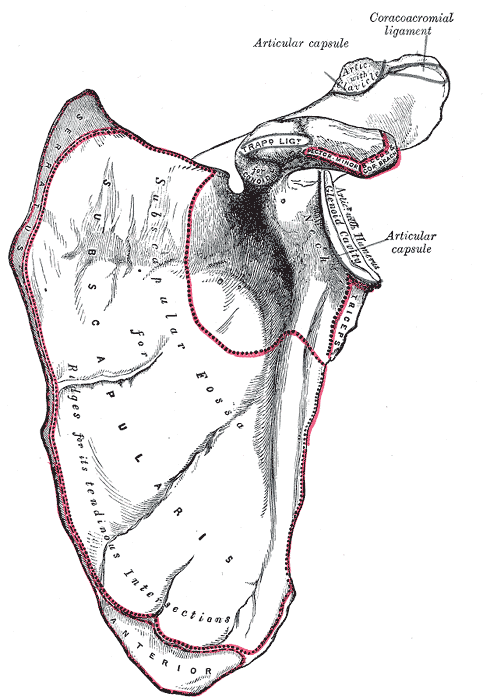
Neurovascular relationships. The structures at risk:
- Suprascapular nerve - in the suprascapular notch; injury in coracoid fractures
- Axillary nerve - quadrangular space
- Subscapular nerves and vessels
- Brachial plexus - runs anterior to the scapula
Classification Systems
Where the fracture lies. The anatomic classification is the most practical, and location carries the prognosis. Glenoid fractures are the most important prognostically because they affect glenohumeral joint function. Glenoid neck fractures matter when significantly displaced or combined with a clavicle injury (the floating shoulder). Body fractures are treated conservatively, the thick muscle coverage aiding healing.
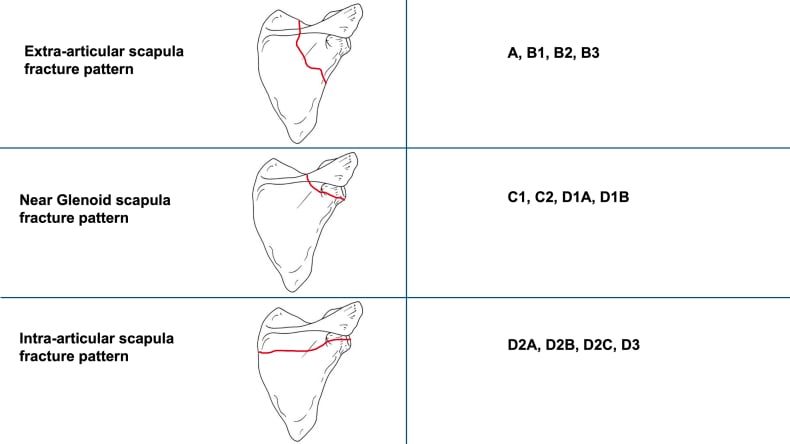
- Frequency
- 50-60%
- Note
- Thick muscle coverage aids healing
- Frequency
- 25%
- Note
- Ada and Miller types
- Frequency
- 10%
- Note
- Ideberg classification
- Frequency
- 8%
- Note
- Distinguish from os acromiale
- Frequency
- 3-7%
- Note
- Ogawa classification
- Frequency
- Rare
- Note
- Usually with body fractures
Coracoid fractures: the Ogawa classification. The coracoid fracture is classified by its relation to the coracoclavicular (CC) ligament attachment, which decides whether the SSSC ring is still intact.
- Type I - posterior (proximal) to the CC ligament attachment. The fracture lies behind the conoid and trapezoid insertions, so the CC ligaments stay attached to the distal fragment and the coracoid strut is detached from the clavicle and SSSC linkage. It behaves like a double disruption, often with an associated AC joint separation or distal clavicle fracture, and it is unstable: this is the type that often needs ORIF.
- Type II - anterior (distal) to the CC ligament attachment, at the coracoid tip. The CC ligaments still bridge clavicle to scapula and the ring is intact, so this is a stable avulsion, usually treated non-operatively.
Suspect a Type I double lesion whenever a coracoid fracture coexists with an AC joint disruption; that is why displacement and an associated AC injury push toward fixation. CT is particularly useful when an apparently isolated coracoid fracture may be part of a double disruption of the SSSC.
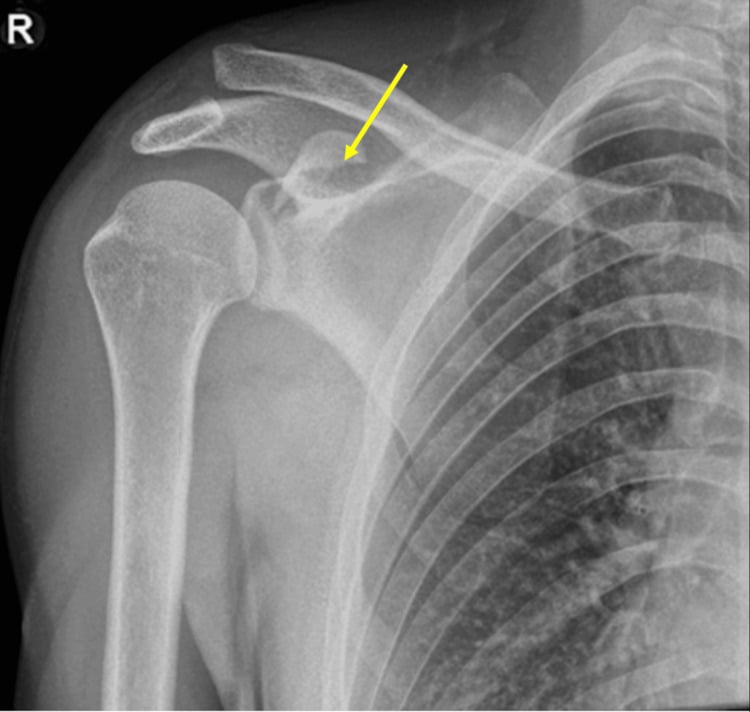
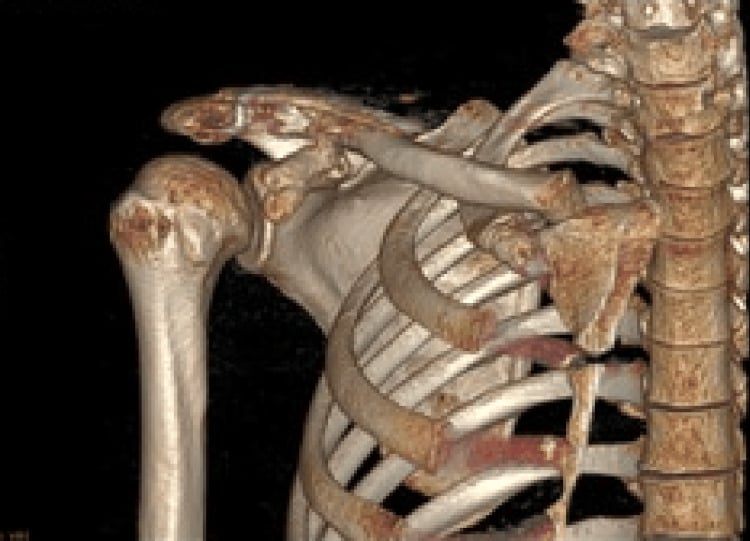
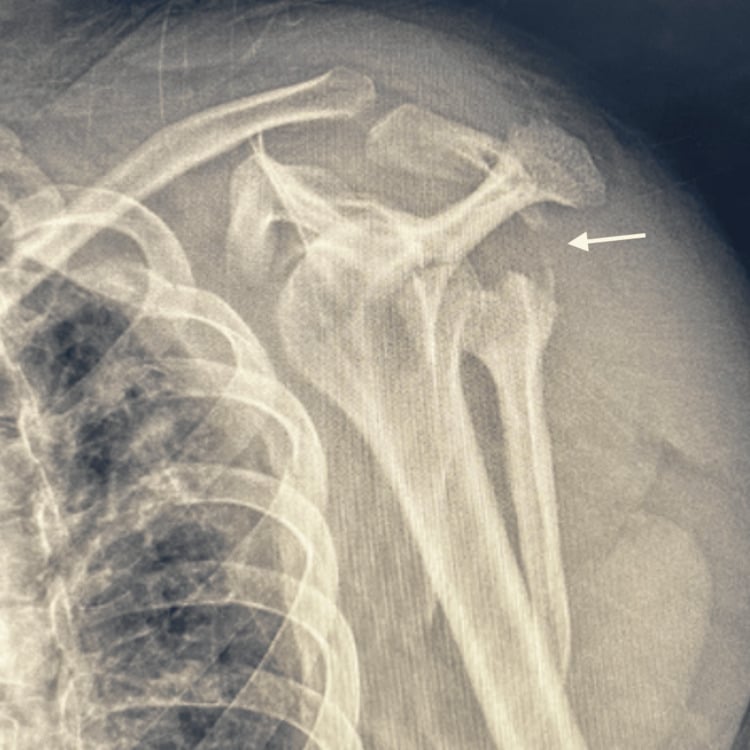
A two-piece acromion on a film of a sore shoulder is a classic viva trap: is it an acute acromial fracture, or an os acromiale, an unfused acromial ossification centre?
The acromion ossifies from up to four centres (from posterior to anterior: basi-acromion, meta-acromion, meso-acromion, pre-acromion), normally fusing by about the mid-twenties. Failure of fusion, most commonly at the meso-meta junction (meso-acromion), leaves a persistent synchondrosis, present in a few percent of people. It is a recognised cause of subacromial impingement and rotator cuff tears, an unstable mobile fragment tilting down on the cuff with deltoid pull, and it is the commonest acromial fracture mimic.
- Os acromiale: smooth, rounded, well-corticated margins at a constant anatomical site (the acromial mid-portion); usually bilateral and symmetrical; best seen on the axillary view
- Acute fracture: sharp, irregular, non-corticated edges; focal tenderness; a high-energy history; unilateral
- Before calling it a fracture: confirm on the axillary view and the contralateral side; marrow oedema on MRI helps if symptomatic
- Management: leave an incidental, asymptomatic os acromiale alone; if symptomatic (painful synchondrosis or impingement), excise a small pre-acromion fragment, or use open reduction and internal fixation with bone graft for a larger mobile meso-acromion
Clinical Presentation and Assessment
Scapula fractures are high-energy injuries and the ATLS protocol is mandatory. Complete the primary survey before focusing on the scapula fracture: life-threatening chest injuries, haemorrhage and neurological injuries take priority.
History. The questions that shape the assessment:
- Mechanism - MVA, fall from height, direct blow
- Associated symptoms - chest pain, dyspnoea, neurological symptoms
- Pre-injury function
- Hand dominance
Associated injuries. Between 80 and 95% of patients have them, and rib fractures are the most common association:
- Rib fractures - 52%
- Pulmonary contusion - 47%
- Pneumothorax - 38%
- Clavicle fractures - 23%; with a neck fracture, the floating shoulder
- Brachial plexus injury - 12%
- Humeral fractures - 11%
- Spine fractures (cervical and thoracic) - 8%
- Acromioclavicular injury - may be concomitant
- Subclavian artery injury - rare but serious; vascular injury in severe cases
- Significance
- Local haematoma
- Associated Condition
- Body/neck fracture
- Significance
- Significant displacement
- Associated Condition
- Displaced glenoid neck
- Significance
- Scapulothoracic dissociation
- Associated Condition
- Life-threatening injury
- Significance
- Pneumothorax
- Associated Condition
- Rib fractures, lung injury
- Significance
- Vascular injury
- Associated Condition
- Subclavian/axillary injury
- Significance
- Brachial plexus injury
- Associated Condition
- High-energy trauma
- Discriminating features
- High-energy mechanism, posterior tenderness, painful but congruent glenohumeral joint
- Confirming investigation
- AP/Y-view radiograph plus CT
- Discriminating features
- Haemarthrosis, articular step, possible subluxation
- Confirming investigation
- CT with 3D reconstruction
- Discriminating features
- Flail arm, absent pulse, gross lateral scapular displacement on CXR
- Confirming investigation
- CXR scapular index plus CT angiography
- Discriminating features
- Locked internal rotation, light-bulb sign, often post-seizure/electrocution
- Confirming investigation
- Axillary lateral or CT - empty glenoid
- Discriminating features
- Anterolateral tenderness, deformity at surgical neck
- Confirming investigation
- AP and scapular-Y radiographs
- Discriminating features
- Point tenderness over AC joint, step deformity, painful cross-body adduction
- Confirming investigation
- AP / Zanca view weighted radiograph
- Discriminating features
- Weakness rather than bony tenderness, lower-energy mechanism
- Confirming investigation
- Ultrasound or MRI
- Discriminating features
- No acute fracture; long thoracic or spinal accessory nerve palsy
- Confirming investigation
- Clinical examination plus EMG if persistent
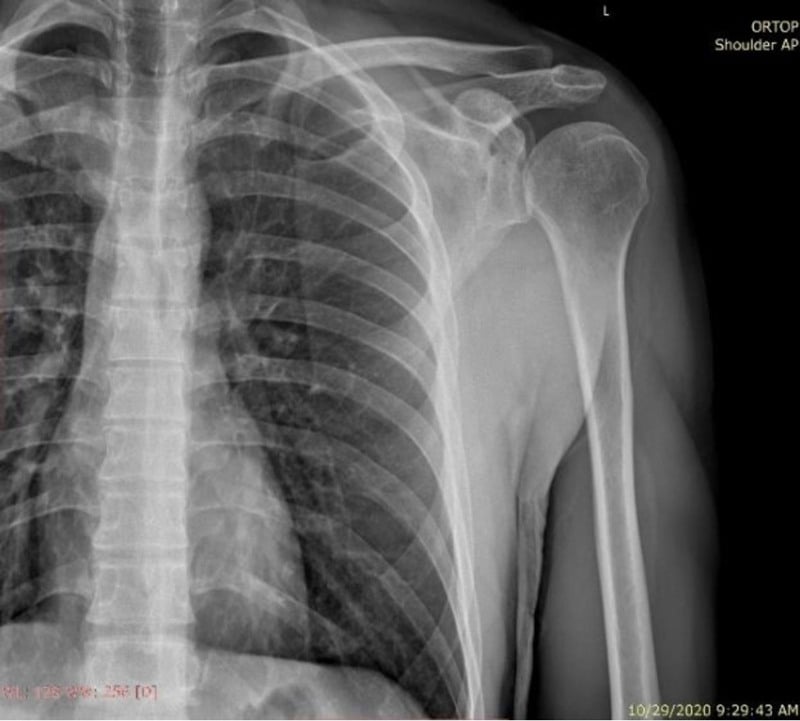
Scapulothoracic dissociation. Look at the chest X-ray for lateral displacement of the scapula compared with the contralateral side. It indicates complete disruption of the scapulothoracic attachments with massive soft-tissue trauma, a high likelihood of subclavian or axillary artery injury, and brachial plexus avulsion. Mortality is high, and forequarter amputation may be required.
The scapula index puts a number on the displacement: the normal average is 1.07, and dissociation is suspected if the ratio exceeds 1.29.
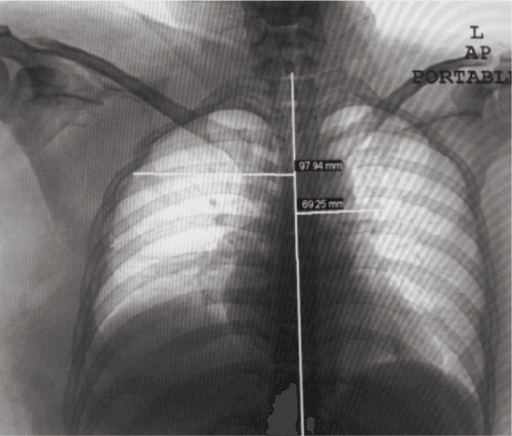
A vascular emergency. A laterally displaced shoulder girdle with a cool, pulseless or neurologically flail limb is a vascular emergency. Document perfusion and brachial plexus function, then obtain urgent vascular imaging without delaying resuscitation.
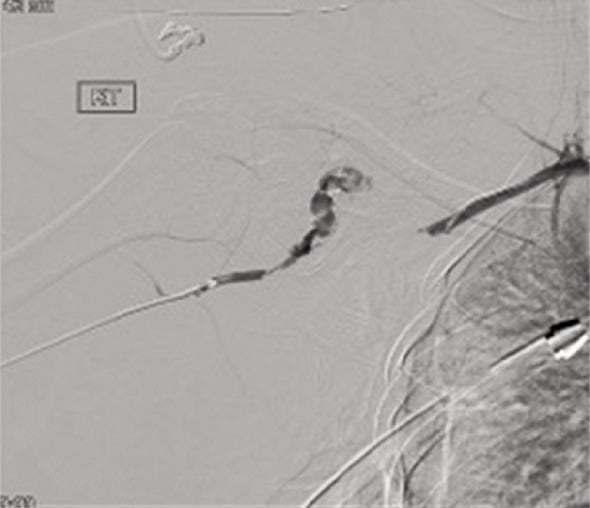
Investigations
Trauma series first. The AP chest, AP pelvis and lateral C-spine series comes first, and the chest X-ray is often the first film to show the scapula fracture. Read it for lateral scapular displacement (scapulothoracic dissociation), rib fractures and pneumothorax.
Dedicated scapula views. Three projections:
- True AP scapula (Grashey view) - 30-40 degree posterior oblique
- Scapula Y-view (lateral) - shows the glenoid neck and body; as a true lateral it complements the AP and axillary projections by showing sagittal angulation and the relationship of the glenoid to the scapular body
- Axillary lateral - glenoid rim fractures
The glenopolar angle (GPA). Measured on the true AP or Y-view, it describes glenoid alignment relative to the scapular body. One line joins the most superior and inferior points of the glenoid; a second runs from the superior glenoid to the inferior angle of the scapula. Normal is 30-45 degrees, and 22 degrees or less indicates significant displacement and is the commonly quoted operative threshold. Interpret it with displacement and clinical context rather than in isolation.
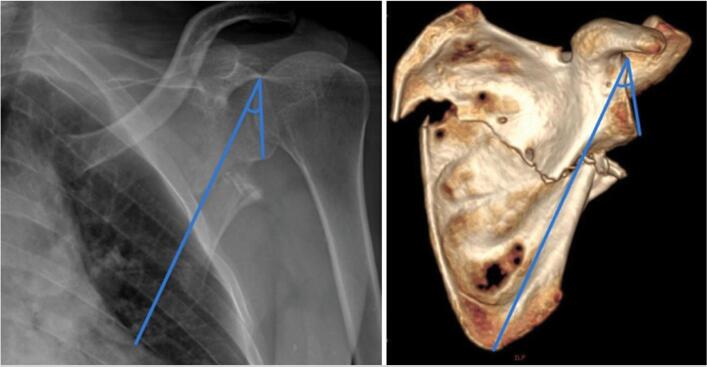
CT. Thin-slice CT with multiplanar reformats and three-dimensional reconstruction characterises body, neck and articular extension, quantifies glenoid step and gap, and reveals fracture components that are frequently occult on plain radiographs. It is essential for:
- All glenoid fractures - articular surface assessment
- Surgical planning for displaced neck fractures
- Complex or comminuted patterns
- Assessment of lateral border offset
The 3D reconstruction is excellent for visualising the fracture pattern and helps plan the surgical approach and fixation strategy.
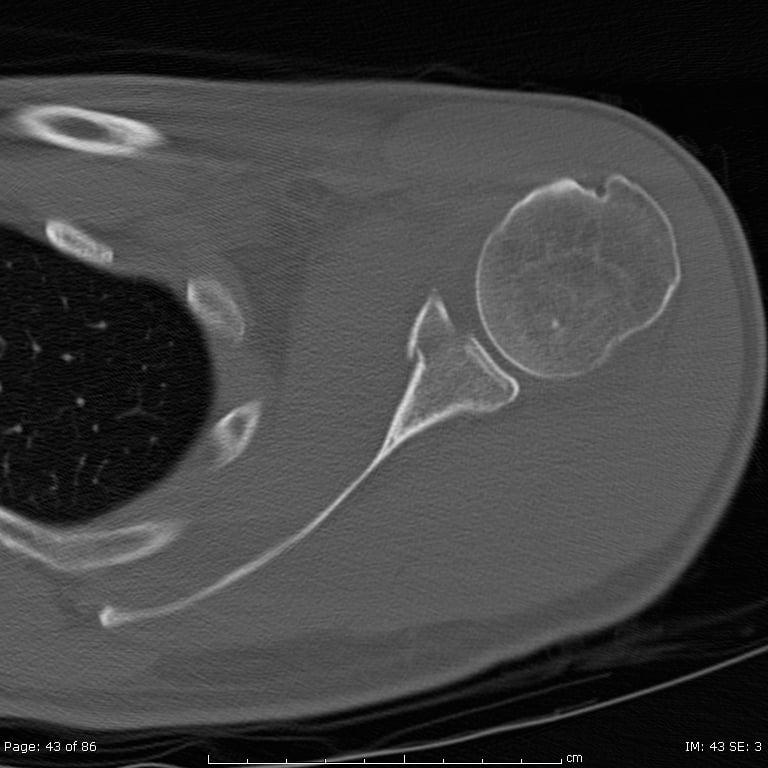
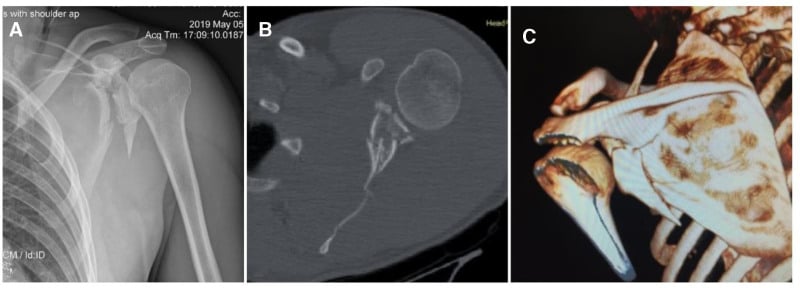
CT angiography. Indicated for:
- Scapulothoracic dissociation
- Expanding haematoma
- Absent or diminished pulses
- Suspected subclavian or axillary injury
Management
Most are treated without surgery. The majority of scapula fractures, 80-90%, are treated conservatively with good outcomes.
- Sling immobilisation for comfort
- Ice, analgesia
- Address associated injuries first
- Gentle pendulum exercises as pain allows
- Wean from sling
- Active assisted ROM
- Progress as pain allows
- Avoid extremes of motion
- Once radiographic callus visible
- Progressive resistance exercises
- Rotator cuff strengthening
- Full ROM and strength expected
- Sport-specific rehabilitation
- Most return to pre-injury function
The decision by pattern. Surgery depends on the fracture's location and how far it has displaced.
- Key Finding
- Less than 1cm displacement
- Treatment
- Sling, early ROM, physio
- Key Finding
- Lateral border more than 20mm displaced
- Treatment
- Rarely surgical - consider surgery
- Key Finding
- Medialisation under 20mm, angulation under 45 degrees, GPA over 22 degrees
- Treatment
- Conservative - sling, early motion
- Key Finding
- Medialisation 20mm or more, OR lateral border offset more than 20mm, OR angulation 45 degrees or more, OR GPA 22 degrees or less, OR humeral head subluxation
- Treatment
- ORIF via posterior approach
- Key Finding
- Step more than 4mm, fragment more than 25% of the surface, or subluxation or instability
- Treatment
- ORIF for articular congruity
- Key Finding
- Clavicle + scapula neck fracture, glenoid NOT caudally dislocated
- Treatment
- Conservative - good outcomes; the double disruption alone is not an indication
- Key Finding
- Glenoid displaced inferiorly despite the clavicle fracture
- Treatment
- Stabilise - this subgroup did badly conservatively
- Key Finding
- Displaced, impinging on the rotator cuff and reducing the subacromial space
- Treatment
- Surgery; conservative unless significantly displaced
- Key Finding
- Displacement more than 1cm, or associated AC joint disruption
- Treatment
- ORIF
- Key Finding
- Lateral scapula displacement on CXR
- Treatment
- Life-threatening - angiography, stabilisation
The glenoid fossa. Articular step, fragment size and instability affect long-term shoulder function, and the Ideberg classification guides treatment.
The neck thresholds are conventions, and you should say so. They are consensus operative indications proposed from expert practice and small retrospective series. No randomised or prospective comparative study has validated any of them, and no trial has shown that operating on a scapula that crosses a cut-off produces a better result than one that does not.
- The glenopolar angle is measured on a true AP that is often imperfect in a polytrauma patient and is sensitive to scapular rotation, so a borderline value should be re-measured on CT rather than acted on
- Medialisation and angulation are read differently on plain films and on 3D CT, with CT generally showing more displacement
Use them to structure the discussion and to justify referral, not as a switch that decides the operation on its own.
4-25-45-204-25-45-20 Rule
Hook:4mm step, 25% fragment, 45 degrees angulation, 20mm offset - four surgical thresholds (plus GPA 22 degrees or less)
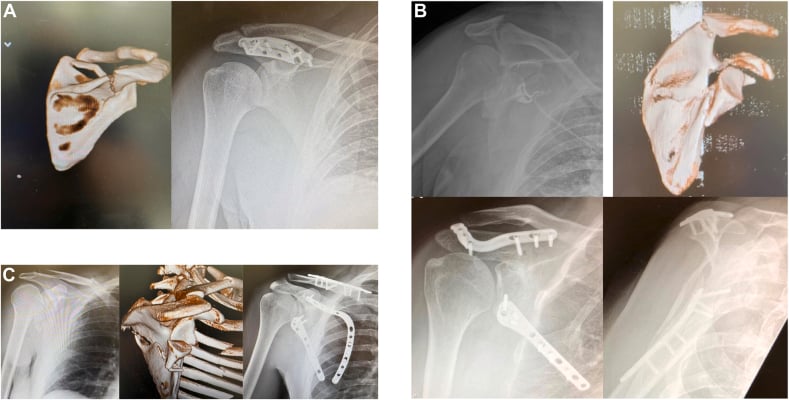
The floating shoulder. Decide from displacement, glenoid alignment, ligamentous integrity, associated injuries and residual instability after clavicular reduction, not from the label. When fixation is chosen, stabilise at least one limb of the ring, usually the clavicle first: it is technically easier to reach and often provides sufficient stability. If residual scapular displacement persists after clavicle fixation, address the scapula neck. Some advocate fixing both primarily, but the evidence suggests clavicle fixation is often sufficient.
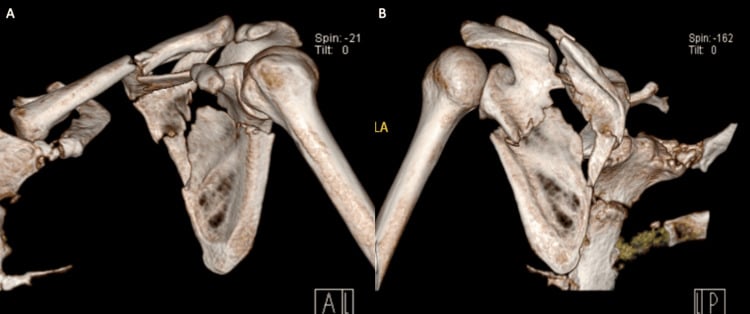
Surgical Technique
Approach selection depends on the fracture pattern and the associated injuries.
The modified Judet approach is the most common. It gives excellent exposure of the glenoid neck, body and spine, and can be extended for the glenoid fossa. The incision runs along the scapular spine and curves distally along the lateral border. The interval between infraspinatus and teres minor opens the lateral border, and superior access toward the scapular spine is gained without detaching the deltoid origin.
The steps.
- Incision along the scapular spine
- Develop the interval below infraspinatus
- Elevate infraspinatus from the fossa
- Expose the fracture and reduce
- Plate fixation along the lateral border
- Closure in layers with rotator cuff repair
Structures to protect. The ones that matter in the posterior exposure:
- Suprascapular nerve and neurovascular bundle - during deep dissection
- Circumflex scapular vessels - during deep dissection
- Infraspinatus and teres minor - preserve their vascularity and the rotator cuff attachments
- Axillary nerve - the inferior limit
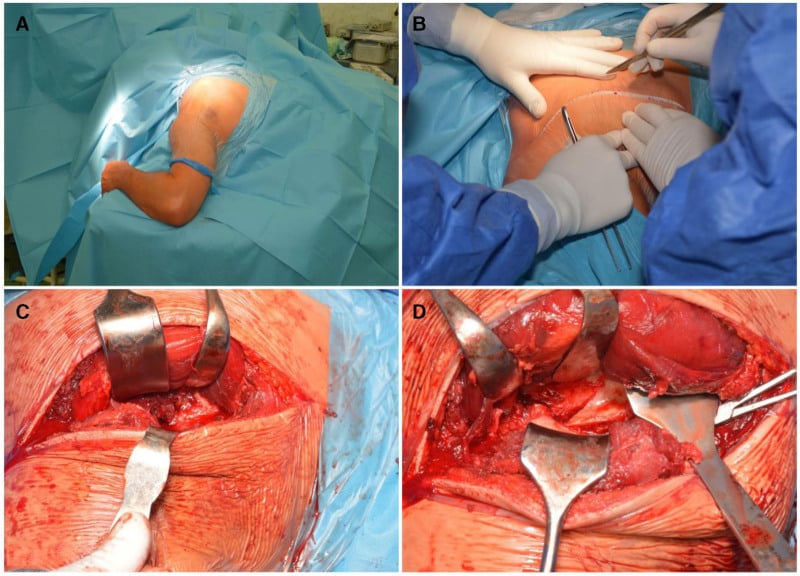
Complications
- Incidence
- 5-15%
- Prevention/Management
- Early motion protocols, physiotherapy
- Incidence
- Variable
- Prevention/Management
- Rarely symptomatic for body; affects glenoid function
- Incidence
- Rare (less than 1%)
- Prevention/Management
- Rich blood supply protects; treat with bone graft if symptomatic
- Incidence
- 5-10% surgical
- Prevention/Management
- Careful retraction, identify nerve
- Incidence
- 10-20% glenoid fx
- Prevention/Management
- Related to articular step-off; minimise displacement
- Incidence
- 1-2%
- Prevention/Management
- Standard precautions, prophylactic antibiotics
Stiffness is the most common complication. It is related to prolonged immobilisation and associated injuries, and the prevention is early motion when it is safe.
Post-traumatic arthritis occurs primarily after glenoid fossa fractures and is related to residual step-off, which is what makes anatomic reduction of articular fractures important.
The suprascapular nerve passes through the suprascapular notch and supplies supraspinatus and infraspinatus. Injury causes external rotation and abduction weakness. Protect it during posterior approaches by staying inferior to the scapular spine.
Postoperative Care and Rehabilitation
- Sling for comfort and protection
- Gentle pendulum exercises
- No active elevation or external rotation
- Wound management
- Wean sling as comfort allows
- Active assisted ROM
- Progress to active ROM
- Avoid loaded activities
- Full active ROM expected
- Progressive strengthening
- Rotator cuff rehabilitation
- Light functional activities
- Confirm radiographic healing
- Sport-specific training
- Return to full activities typically 4-6 months
- High-impact activities may take longer
Protection and early motion. The post-ORIF protocol balances protection of the repair against early motion, and rotator cuff function is critical for the outcome. Serial imaging should confirm that fixation remains stable while rehabilitation advances from protected passive motion to active motion and strengthening, according to fracture union and soft-tissue repair.
The whole patient. Build the associated injuries (rib, clavicle) into the rehabilitation plan, and educate the patient about the expected timeline.
Outcomes and Prognosis
- Outcome
- Excellent
- Notes
- Regardless of treatment; conservative treatment adequate
- Outcome
- Good
- Notes
- Conservative if it meets the displacement criteria
- Outcome
- Good
- Notes
- With surgical stabilisation, or conservatively when the glenoid is not caudally dislocated
- Outcome
- Good-Excellent
- Notes
- Key is anatomic reduction; outcome correlates with reduction quality
- Outcome
- Fair-Poor
- Notes
- Develops arthritis
What decides the result. The associated injuries (head, chest) are the major determinant of mortality, and the quality of articular reduction the major determinant of shoulder function. Patient age, bone quality and rehabilitation compliance also bear on it.
Most patients with scapula body fractures return to full function. The presence of glenohumeral subluxation at presentation is a poor prognostic factor.
Guidelines, Registries & Global Practice
Global epidemiology
- Figure
- ~10 per 100,000 per year
- Source population
- Two Swedish counties, Ideberg 1995
- Figure
- Less than 1%
- Source population
- Pooled case series, Zlowodzki/Cole 2006
- Figure
- 3-5%
- Source population
- Pooled case series, Zlowodzki/Cole 2006
- Figure
- ~30%
- Source population
- Ideberg 1995
- Figure
- ~90% (range 80-95%)
- Source population
- Zlowodzki/Cole 2006
- Figure
- Peak in young men from high-energy trauma; older women from low-energy falls
- Source population
- Ideberg 1995
Scapula fractures are uncommon worldwide and almost always a marker of high-energy transfer; injury patterns therefore track regional trauma epidemiology (road-traffic and motorcycle trauma in much of Asia, Africa and Latin America; falls and vehicle crashes in higher-income settings).
Guidance, side by side
There is no single dedicated international guideline for scapula fractures; management is anchored on the AO Foundation principles plus society trauma-system standards. Recommendations are largely concordant because the evidence base is uniformly low (level IV).
- Position on scapula fractures
- Non-operative for most body/neck fractures; ORIF for displaced intra-articular glenoid, large lateral-border displacement/angulation, low glenopolar angle, or double SSSC disruption; posterior (Judet) approach standard
- Evidence level
- Expert consensus / level IV
- Position on scapula fractures
- No condition-specific clinical practice guideline; managed within polytrauma and shoulder-trauma principles, ATLS-first
- Evidence level
- Consensus
- Position on scapula fractures
- No scapula-specific BOAST; governed by BOAST polytrauma and open-fracture standards and trauma-network triage to a major trauma centre
- Evidence level
- Consensus / standard of care
- Position on scapula fractures
- No scapula-specific guidance; covered by NICE major-trauma pathways (NG39/NG40) emphasising ATLS, imaging and network transfer
- Evidence level
- Consensus
- Position on scapula fractures
- Reflects AO principles; emphasises CT for glenoid and surgical-threshold measurement
- Evidence level
- Expert consensus
Across AO, AAOS, BOA and EFORT the consensus is identical at the level that examiners test: complete ATLS first, image associated injuries, treat most fractures non-operatively, and reserve surgery for displaced articular glenoid fractures, grossly displaced necks (glenopolar angle 22 degrees or less, displacement 20mm or more, angulation 40-45 degrees or more) and unstable double SSSC disruptions.
Registry evidence
Scapula fractures are not implant-survival procedures, so the major arthroplasty registries (NJR, AJRR, AOANJRR, SHAR, Norwegian, NZJR) do not track them directly. Epidemiology instead comes from national trauma databases: a US National Trauma Data Bank analysis of 9,453 scapular fractures (Baldwin et al., J Trauma 2008) showed that, after adjusting for injury severity, upper-extremity, thoracic and pelvic-ring injuries remained significantly associated with scapula fracture, while many other "associations" reflected overall injury severity rather than the scapula fracture itself.
Global practice variation
- High-resource settings: ready CT and 3D reconstruction, sub-specialist shoulder/trauma surgeons, and trauma-network transfer make selective ORIF (Judet or single lateral-column approach) routine for displaced patterns.
- Limited-resource settings: CT may be scarce and most fractures are managed non-operatively with sling and early motion, which is supported by the evidence for the majority of body and minimally displaced neck fractures.
- Scapulothoracic dissociation is a universal surgical emergency requiring immediate vascular assessment regardless of setting; outcomes depend on access to vascular surgery and ICU support.
For any board, be ready to justify management on biomechanical thresholds and evidence level rather than a national pathway. State that the evidence is predominantly level IV, that most fractures heal well non-operatively, and that operative thresholds (glenoid step greater than 4mm or fragment greater than 25%, glenopolar angle 22 degrees or less, lateral-border displacement 20mm or more, double SSSC disruption) are consensus-based and consistent across AO, AAOS, BOA and EFORT.
MCQ Practice Points
Q: What percentage of patients with scapula fractures have associated injuries? A: 80-95%. Scapula fractures are high-energy injuries. Rib fractures are most common (52%), followed by pulmonary contusion (47%) and clavicle fractures (23%).
Q: What is the superior shoulder suspensory complex (SSSC)? A: A bone-ligament ring connecting the upper extremity to the axial skeleton. Components: glenoid, coracoid, CC ligaments, clavicle, AC ligaments, acromion. Two disruptions = floating shoulder = unstable.
Q: What Ideberg type is an anterior glenoid rim fracture? A: Type Ia. Type Ib is posterior rim. These rim fractures are often associated with shoulder instability and may require treatment directed at the instability rather than just the fracture.
Q: What glenoid articular step-off is an indication for ORIF? A: More than 4mm step-off or more than 25% articular surface involvement. These thresholds are based on data showing increased rates of post-traumatic arthritis with larger incongruities.
Q: On chest X-ray, what finding suggests scapulothoracic dissociation? A: Lateral displacement of the scapula compared to the contralateral side. This indicates complete disruption of the scapulothoracic connection with likely vascular injury and brachial plexus avulsion.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 35-year-old motorcyclist is brought to ED after high-speed accident. GCS 15, hemodynamically stable. Chest X-ray shows multiple left rib fractures and a scapula fracture. CT shows a glenoid neck fracture with 15mm medialization. How do you manage this patient?”
“A 42-year-old presents after falling from scaffolding. X-rays show a displaced midshaft clavicle fracture and CT reveals a glenoid neck fracture with 25mm medialization and glenopolar angle of 15 degrees. How do you approach this 'floating shoulder' injury?”
“A 28-year-old is brought in after a motorcycle vs truck collision. There is massive left shoulder swelling, the arm is flail, and there is no radial pulse. Chest X-ray shows the left scapula displaced 4cm lateral to the chest wall. What is your diagnosis and immediate management?”
KEY FACTS
- 1% of all fractures - high-energy mechanism required
- 80-95% have associated injuries - ATLS protocol mandatory
- 10-15% mortality (from associated chest/head injuries)
- Most body fractures (50-60%) treated conservatively
- Peak age 25-40, M:F ratio 2:1
- MVA most common mechanism (50-70%)
CLASSIFICATION
- Anatomic: Body (50-60%), Neck (25%), Glenoid fossa (10%), Processes (8%)
- Ideberg (glenoid): I (rim), II (transverse), III (oblique), IV (horizontal), V (combined), VI (comminuted)
- SSSC: double disruption = floating shoulder = unstable
- Ada-Miller (neck): Type I (anatomic neck), Type II (through body)
- Body fractures: usually heal well with conservative treatment
SURGICAL THRESHOLDS (4-25-45-20 Rule)
- Glenoid fossa: step more than 4mm OR fragment more than 25% of surface
- Glenoid neck: angulation 45 degrees or more OR medialization 20mm or more
- Glenopolar angle 22 degrees or less (normal 30-45 degrees)
- Floating shoulder: not automatically operative - decide on caudal glenoid displacement
- Humeral head subluxation = surgical indication
- GH instability with rim fracture = consider Bankart repair
FLOATING SHOULDER
- Double SSSC disruption (usually clavicle + scapula neck fracture)
- Creates unstable glenoid segment - weight causes medialization
- Treatment: stabilize clavicle FIRST (easier, restores length)
- Reassess scapula after clavicle fixation under fluoroscopy
- Add scapula ORIF if persistent displacement more than 20mm
- Some advocate fixing both primarily - evidence mixed
SCAPULOTHORACIC DISSOCIATION
- Lateral scapula displacement on CXR (compare to contralateral)
- Complete soft tissue disruption - massive energy transfer
- Associated vascular injury (subclavian/axillary), brachial plexus avulsion
- High mortality (10-20%) and amputation rate (20%)
- Immediate CT angiography, vascular surgery consultation
- May need forequarter amputation if limb non-salvageable
ASSOCIATED INJURIES
- Spine fractures (cervical/thoracic) - 8%
- Clavicle fractures - 23% (creates floating shoulder)
- Arterial injury (subclavian) - rare but serious
- Pulmonary contusion - 47% (most common thoracic)
- Upper extremity nerve (brachial plexus) - 12%
- Lateral rib fractures - 52% (most common association)
SURGICAL APPROACHES
- Modified Judet (posterior): along spine/lateral border
- Interval: infraspinatus-teres minor (preserves cuff)
- Protect suprascapular nerve (stay below spine)
- Deltopectoral (anterior): for isolated anterior rim
- Positioning: lateral decubitus 30-45° or prone
- Fixation: 3.5mm recon plates, lag screws, locking plates
TRAPS AND PEARLS
- Always complete ATLS trauma assessment first
- Look for associated chest injuries - ribs, pneumothorax
- Glenoid fractures affect long-term function most
- Body fractures heal well conservatively
- Modified Judet = standard posterior approach
- Glenopolar angle less than 20° = surgical indication
Evidence Base
Zlowodzki, Bhandari, Zelle, Kregor & Cole - Systematic Review of 520 Scapula Fractures
- Pooled 520 fractures from 22 case series: scapula fractures comprise less than 1% of all fractures and 3-5% of shoulder-girdle fractures.
- Approximately 90% of patients had associated injuries.
- Both operatively and non-operatively treated fractures achieved largely good functional results when treated by appropriate indication; operative infection and secondary-surgery rates were low.
Lantry, Roberts & Giannoudis - Operative Treatment of Scapular Fractures: Systematic Review
- Glenoid fossa and scapular neck fractures were the patterns most commonly treated operatively.
- About 25% had a concomitant clavicle or acromioclavicular injury.
- Plate-and-screw fixation through a posterior (Judet) approach was most common; complication rate was low.
- Good to excellent functional results in approximately 85% of operatively treated cases at a mean of 49.9 months.
van Noort, te Slaa, Marti & van der Werken - The Floating Shoulder: A Multicentre Study
- Floating shoulder (ipsilateral scapular neck plus clavicle fracture) is not inherently unstable.
- Mean Constant score 76 for the conservatively treated group versus 71 for the operative group.
- Caudal (inferior) dislocation of the glenoid was the key poor-prognostic finding: Constant 42 with it versus 85 without.
- In the absence of caudal glenoid displacement, conservative treatment gave a good functional outcome.
Herrera, Anavian, Tarkin, Armitage, Schroder & Cole - Delayed Operative Management of Scapular Fractures
- 22 patients had ORIF more than 3 weeks (mean 30 days) after injury for displaced intra-articular fractures, glenohumeral medialisation, angular deformity, or double SSSC lesions.
- Mean DASH score 14 at a mean follow-up of 27 months.
- 13 of 16 followed patients returned to previous work and recreation without restriction.
- No wound complications, infection, or nonunion occurred.
Ideberg, Grevsten & Larsson - Epidemiology of Scapular Fractures (Intra-articular Glenoid)
- Annual incidence of scapular fractures was 10 per 100,000 inhabitants over a 10-year period across two Swedish counties.
- 30% of scapular fractures involved the glenoid cavity.
- The most common intra-articular pattern was the anterior chip (rim) fracture, associated with shoulder dislocation in about two-thirds of cases.
- This series underpins the Ideberg glenoid-fossa classification used to guide surgical planning.
Mannambeth, Kirzner & Moaveni - Direct Lateral-Column Approach for Displaced Extra-articular Scapula Fractures
- Operative thresholds used: medial/lateral displacement of 20mm or more, angulation of 45 degrees or more, double SSSC disruption, or glenopolar angle of 22 degrees or less.
- Scapular neck angulation corrected from a mean 38.7 degrees pre-operatively to 3.6 degrees; mean post-operative glenopolar angle 35.4 degrees.
- Mean DASH score 11.4 and mean Subjective Shoulder Value 88.9; 10 of 11 returned to pre-injury work.
- No infections or neurovascular injuries with a less invasive single-column approach.