Open distal phalanx physeal fracture, nail-bed injury and infection prevention
- Definition: distal phalanx physeal or juxta-epiphyseal fracture with associated nail-bed injury.
- It mimics a mallet finger but behaves like an open fracture.
- The nail plate may lie superficial to the eponychial fold rather than tucked under it.
- Interposed germinal matrix or nail bed prevents stable closed reduction.
- Delayed recognition increases infection, osteomyelitis, non-union, malunion, nail deformity and growth disturbance.
- “Blood at the proximal nail fold in a child with a flexed distal phalanx is the red flag.
- “Request true AP and lateral views of the digit, not only a hand film.
- “Remove or elevate the nail plate to inspect, debride and repair the nail bed.
- “Use K-wire fixation when reduction is unstable after soft-tissue interposition is cleared.
Overview
A Seymour fracture is a paediatric distal phalanx physeal or juxta-epiphyseal fracture with associated nail-bed injury. In practical terms it is an open fracture until proven otherwise: the X-ray may look small, but the open nail-bed wound makes the injury high risk.
The trap. Seymour fractures resemble mallet finger, but the treatment is different. Each finding that suggests a mallet has a different meaning here, and a cost if it is treated as one.
- Seymour fracture implication
- May look like terminal extensor injury but the fracture involves the distal phalanx physis or juxta-epiphyseal region.
- Risk if treated as mallet finger
- Splinting may leave the fracture unreduced.
- Seymour fracture implication
- Suggests nail-bed violation and open fracture communication.
- Risk if treated as mallet finger
- Open fracture may be missed.
- Seymour fracture implication
- Indicates proximal nail-bed disruption.
- Risk if treated as mallet finger
- Germinal matrix may remain interposed.
- Seymour fracture implication
- Soft-tissue block is likely.
- Risk if treated as mallet finger
- Persistent malreduction, infection, non-union and nail deformity.
Four questions. The consultation should answer them in turn:
- Is this a nail-bed wound communicating with bone?
- Is the fracture through or near the open distal phalanx physis?
- Is germinal matrix or nail bed interposed in the fracture?
- Is the reduction stable after the soft-tissue block is cleared?
The great toe. The great toe has an equivalent injury after axial load or stubbing trauma. It is less commonly discussed than the finger injury, but the logic is the same: nail-bed injury plus distal phalangeal physis involvement requires open-fracture thinking.
Where it is missed. In a series of five boys with open physeal fractures of the hallux distal phalanx, 40% were initially missed and 60% arrived as transfers. It is a small series, but the pattern is consistent with how these present: a stubbed toe with a bit of blood at the nail fold does not read as an open fracture to anyone. Treat the recognition step as the hard part.
Once it is recognised. Suture-only stabilisation produced no infections, no reoperations and no physeal bars on follow-up imaging, so the toe does not necessarily demand K-wire fixation once it is recognised and properly cleaned. The evidence level is low: five patients, short median follow-up, and suture-only fixation has not been compared directly against pinning.
Pathophysiology
Mechanism. The usual mechanism is a crush or forced-flexion load to the fingertip. Door-crush injuries are common, but ball sports, falls, machinery, direct blows and toe-stubbing injuries can produce the same pattern. The child often presents with pain, swelling, bleeding at the nail fold and a fingertip that appears flexed at the DIP joint.
The physis. The distal phalanx physis lies near the base of the distal phalanx, close to the nail-bed complex. The load forces the distal phalanx into a flexed posture through the weak physeal or juxta-epiphyseal region, so the fracture passes through or near the growing base of the bone.
The tendons. The terminal extensor tendon is attached dorsally near the epiphysis, which creates the mallet-like posture that misleads the clinician. The FDP insertion is volar and distal; it contributes to the flexion posture and to control of the distal fragment.
The germinal matrix. This is the important soft-tissue structure. It produces most of the nail, sits deep to the proximal nail plate and tears at the same level as the fracture. When the nail plate is avulsed or displaced, the germinal matrix can fold into the fracture gap, which creates two problems:
- It blocks reduction
- It leaves devitalised or contaminated soft tissue inside an open physeal fracture, which increases infection risk
Why it is open. The open physis and the nail-bed laceration connect the outside environment with the growth plate and the distal phalanx. That is why the injury behaves differently from a simple tuft fracture or mallet finger, and why early antibiotics, debridement, reduction and nail-bed repair matter.
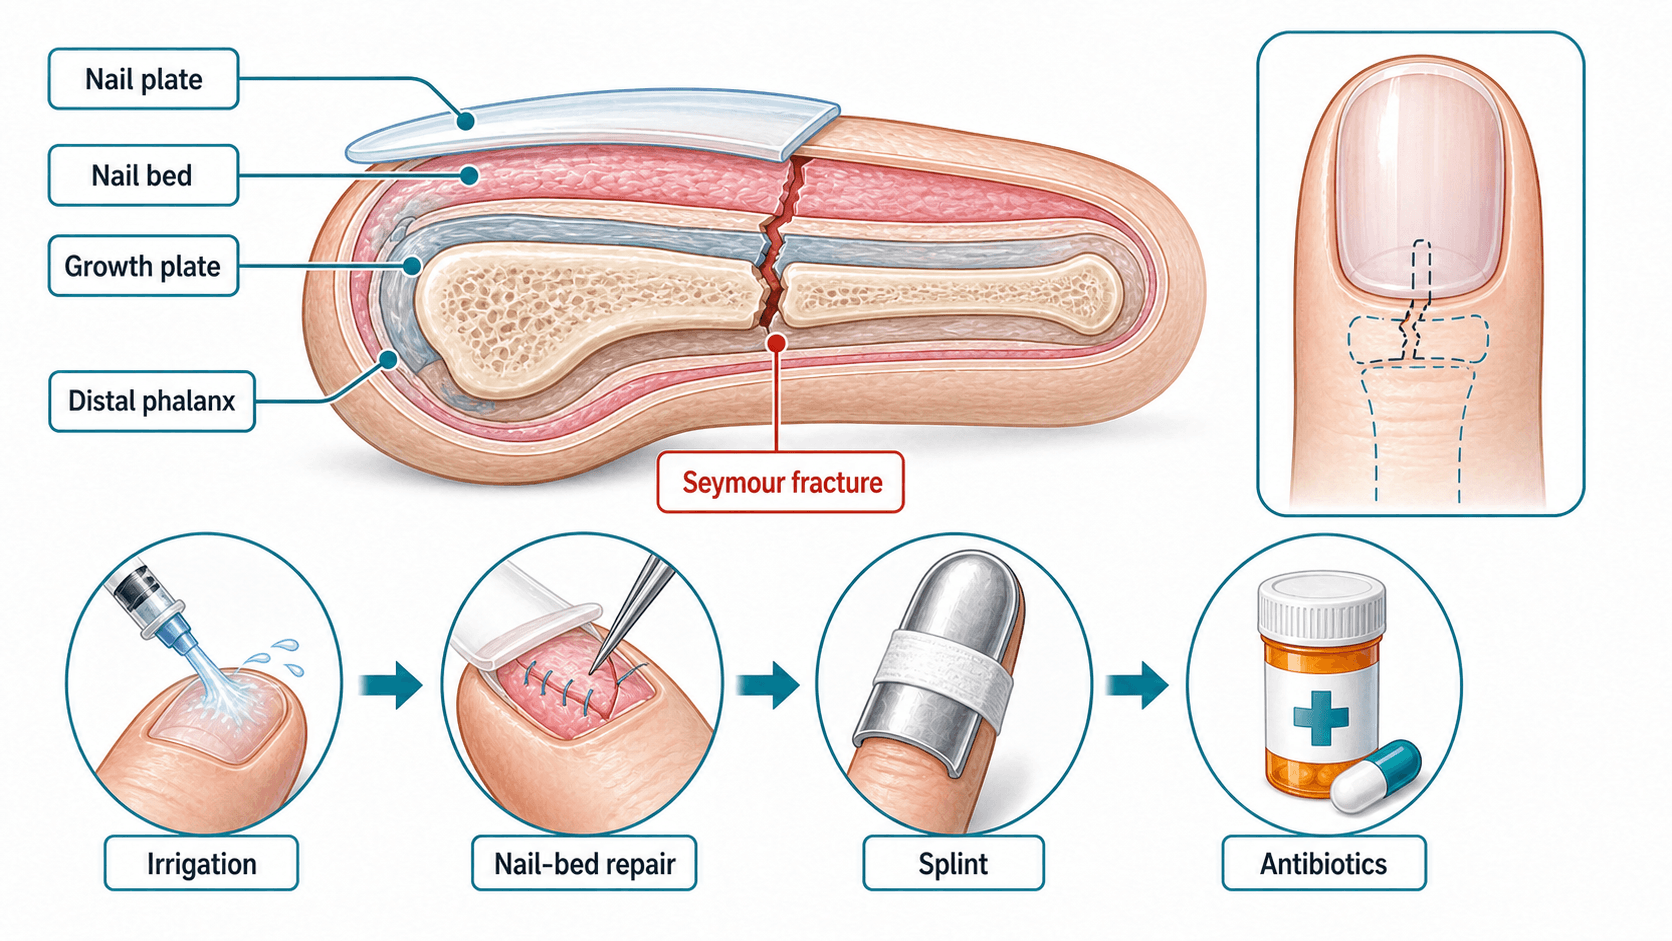
Four injuries in one. Like a mallet finger, the distal phalanx appears flexed. Like an open fracture, there is communication through the nail bed. Like a physeal fracture, growth disturbance is possible if it is missed or infected, and like a nail-bed laceration, the final nail appearance depends on precise soft-tissue repair.
Why it is underestimated. The wound may be tiny, the child may move the finger, and the X-ray may show only subtle physeal widening. The red flag is the combination of distal phalanx posture and proximal nail-fold injury.
Classification
Seymour fractures are commonly described as Salter-Harris I, Salter-Harris II or juxta-epiphyseal distal phalanx injuries. The label confirms that the injury involves the growing distal phalanx base, but it does not by itself decide treatment. That is driven by nail-bed violation, displacement, soft-tissue interposition, contamination, timing and stability.
- Salter-Harris I - through the distal phalanx physis, sometimes seen only as widening on the lateral film
- Salter-Harris II - physeal fracture with a small metaphyseal fragment
- Juxta-epiphyseal - just distal to the physis, and behaving similarly in the clinical setting
Clinical Presentation
History. The history should quickly determine mechanism, contamination, delay and infection risk. Beyond the mechanism, establish:
- Time from injury - delayed presentation changes infection risk and debridement planning
- Nail symptoms - bleeding at the proximal nail fold, nail plate avulsion, a nail plate sitting high, subungual haematoma or a visible nail-bed wound
- Contamination - soil, farm injury, water exposure, bite, dirty sports field or foreign material
- Previous treatment - antibiotics, splinting, trephination, nail removal or attempted reduction
- Infection symptoms - increasing pain, redness, discharge, fever, odour or progressive swelling
- Functional context - digit involved, hand dominance, school or sport needs, and associated fingertip injuries
Examination. Inspection is the most important part. A Seymour fracture may look like a minor nail injury unless the proximal nail fold is examined carefully.
The nail plate sign. A normal nail plate tucks beneath the eponychial fold. In a Seymour fracture its proximal edge may sit on top of the fold, making the nail look too long, and a plate perched there means the germinal matrix is likely disrupted. This subtle sign may be more obvious than the X-ray.
- Look for
- Mallet-like flexion posture of the distal phalanx.
- Why it matters
- Raises suspicion for Seymour fracture in a child.
- Look for
- Blood at proximal nail fold, nail plate superficial to eponychial fold or nail appearing too long proximally.
- Why it matters
- Suggests open nail-bed injury and possible matrix interposition.
- Look for
- Transverse matrix laceration, subungual haematoma, nail avulsion, exposed matrix or open wound.
- Why it matters
- Determines need for washout and nail-bed repair.
- Look for
- Tenderness, swelling, pulp viability, capillary refill and sensation.
- Why it matters
- Documents open fracture severity and neurovascular baseline.
- Look for
- Rotational alignment, finger cascade and associated crush injuries.
- Why it matters
- Avoids missing a second injury.
Motion misleads. A child may still flex through the FDP and may have pain-limited extension. Preserved motion does not exclude an open physeal injury.
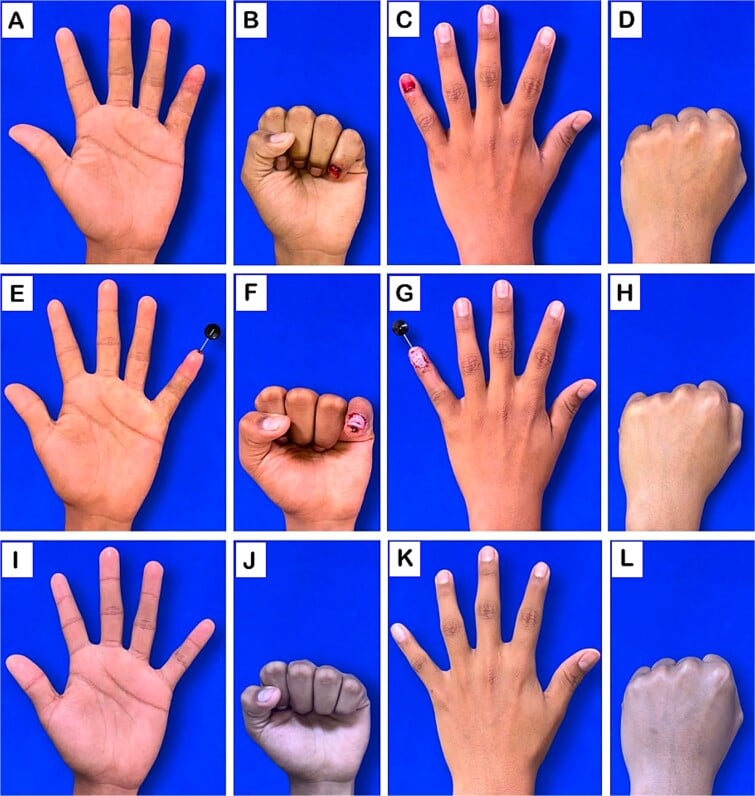
NAILRecognition Clues
Hook:NAIL separates Seymour fracture from a harmless-looking mallet injury.
Investigations
Radiographs. Obtain dedicated true AP and true lateral radiographs of the affected digit, not just a hand X-ray. The AP view helps with alignment and associated fractures, but the true lateral is the key image: it shows the relationship between the distal phalanx epiphysis, physis, metaphysis and nail plate. Look for:
- Widening of the distal phalanx physis
- A Salter-Harris I or II pattern, or a juxta-epiphyseal fracture just distal to the physis
- Flexion deformity or volar angulation of the distal fragment
- Nail plate displacement or soft-tissue swelling
- Subtle physeal asymmetry compared with the contralateral digit, if uncertain
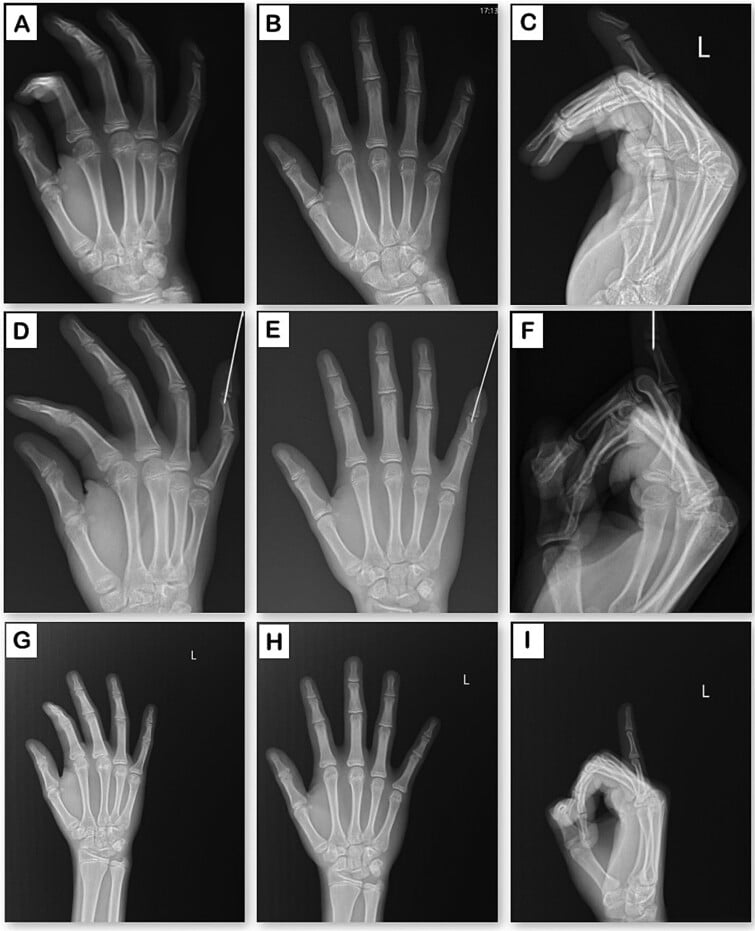
Imaging does not replace the nail fold. A tiny radiographic abnormality with proximal nail-fold bleeding is still clinically important. Conversely, an apparent mallet posture in a skeletally immature patient should not be accepted as a simple tendinous mallet injury until the nail bed and the lateral film are reassuring.
Blood tests and MRI. In a delayed or infected case, FBC, CRP, ESR and cultures (if there is discharge or systemic illness) guide infection severity and the antibiotic plan. When osteomyelitis is suspected, MRI defines marrow involvement and abscess if the extent is uncertain or the symptoms are disproportionate.
Differential Diagnosis
The differential matters because each injury has a different treatment pathway.
- Distinguishing features
- Closed terminal extensor injury, no nail-bed wound, no physeal widening
- Why it matters
- Usually treated with extension splinting rather than open-fracture care
- Distinguishing features
- Dorsal intra-articular avulsion fragment at the distal phalanx base
- Why it matters
- Assess articular fragment size and DIP subluxation
- Distinguishing features
- More distal crush fracture through the tuft rather than basal physis
- Why it matters
- Nail-bed repair and protection may be needed, but it is not the same physeal injury
- Distinguishing features
- Painful nail bleeding; nail plate may be intact
- Why it matters
- Radiographs decide whether fracture management is also required
- Distinguishing features
- Delayed pain, swelling, discharge, redness or systemic symptoms
- Why it matters
- May be the presentation of a missed open Seymour fracture
- Distinguishing features
- No physeal fracture or distal phalanx instability
- Why it matters
- Needs precise soft-tissue repair but not fracture reduction
A painful subungual haematoma without a Seymour fracture is managed differently. Classic teaching was to remove the nail plate and formally repair the bed when the haematoma involved more than 50 percent of the nail, but the better evidence (Seaberg; Roser and Gellman) shows that simple nail-plate trephination (decompression) gives equivalent cosmetic and functional outcomes regardless of haematoma size, even when an underlying distal tuft fracture is present, provided the nail plate and its margins are intact and the bed is not displaced. Remove the nail and repair the bed only when the nail plate or its margins are disrupted, the nail is avulsed, or there is a displaced fracture. This rule does NOT apply to the open Seymour fracture, where the bed must be inspected and repaired and the fracture cleaned regardless of haematoma size.
Management
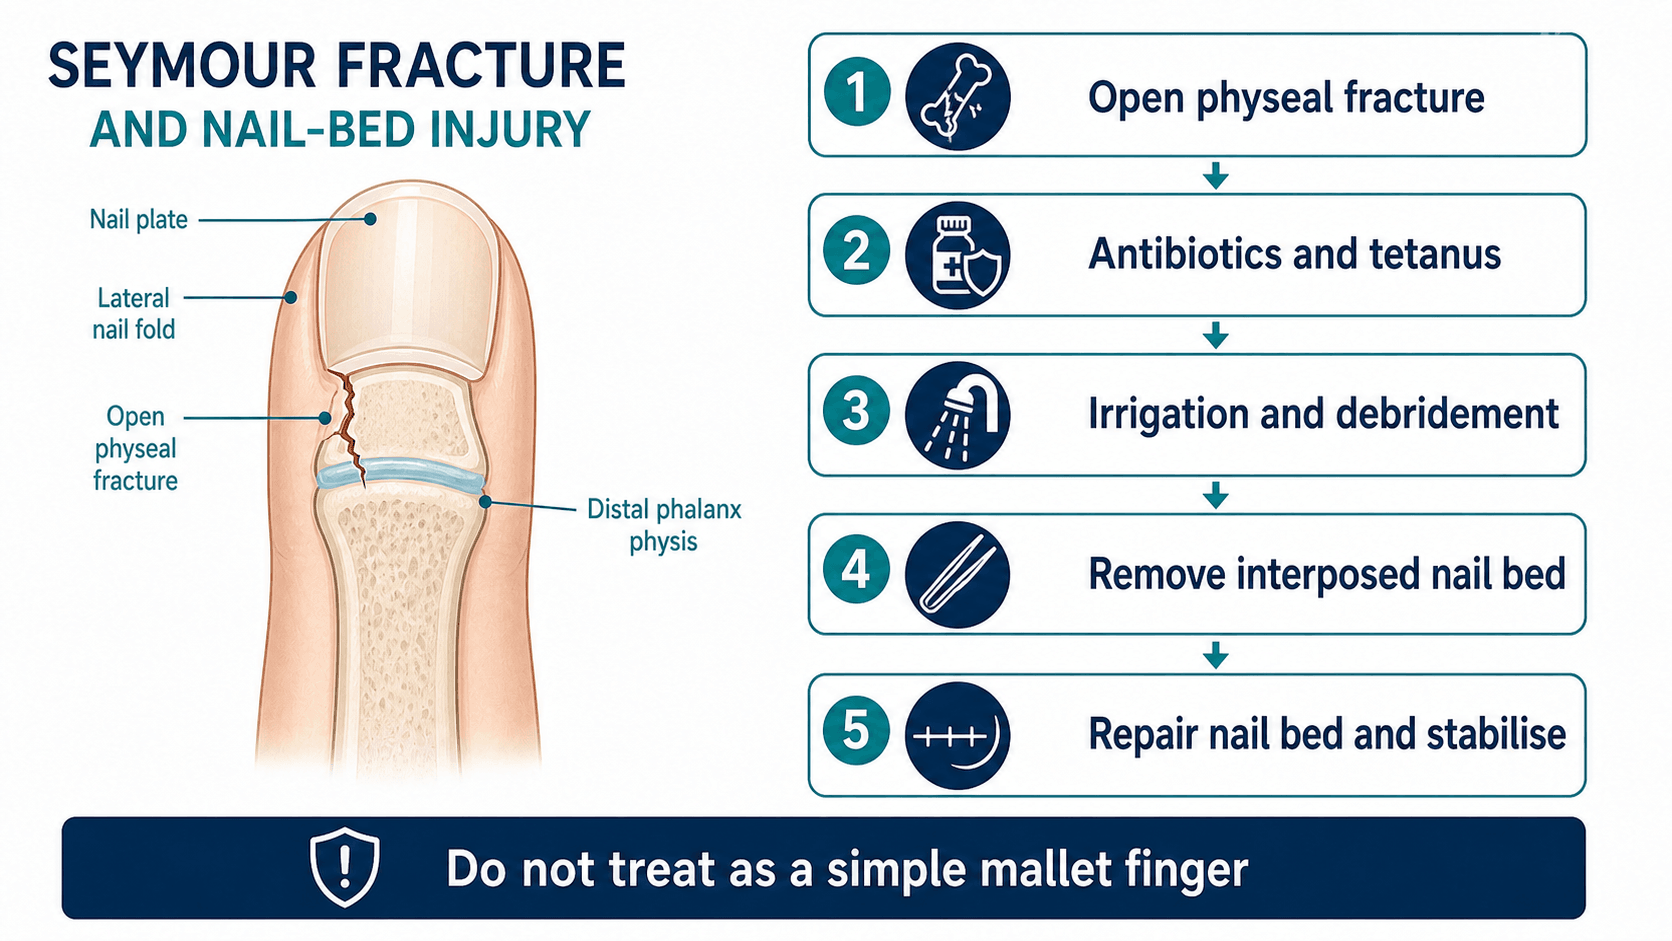
The principle. A Seymour fracture is small in size but high in consequence. If the nail bed is violated and the distal phalanx physis is injured, it is an open fracture, and the aims follow: prevent infection, remove the soft-tissue block, restore distal phalanx alignment, repair the nail bed, protect the reduction until union, and follow the nail and physis.
A child with a mallet-like distal phalanx posture plus blood at the nail fold has a Seymour fracture until proven otherwise. Splinting alone can leave germinal matrix trapped in the fracture and convert a small injury into osteomyelitis, nail deformity or physeal arrest.
Emergency care. Before anything definitive:
- Give analgesia and protect the fingertip with a sterile dressing
- Treat as an open fracture when nail-bed laceration or proximal nail-fold bleeding is present
- Start antibiotics according to local open-fracture and hand-injury protocol
- Check tetanus status
- Obtain dedicated digit X-rays before definitive manipulation, unless vascular compromise demands immediate action
Aftercare. The wound and the reduction both need watching:
- Non-adherent dressing, protective splint and elevation advice
- Early review for the wound, nail fold, pain, discharge and, if wired, the pin site
- Repeat X-ray to confirm maintained reduction and union
- Wire removal according to healing and local practice, commonly around three to four weeks
- Warn parents to return for increasing pain, redness, fever, discharge, foul smell or pin loosening
Operative Technique
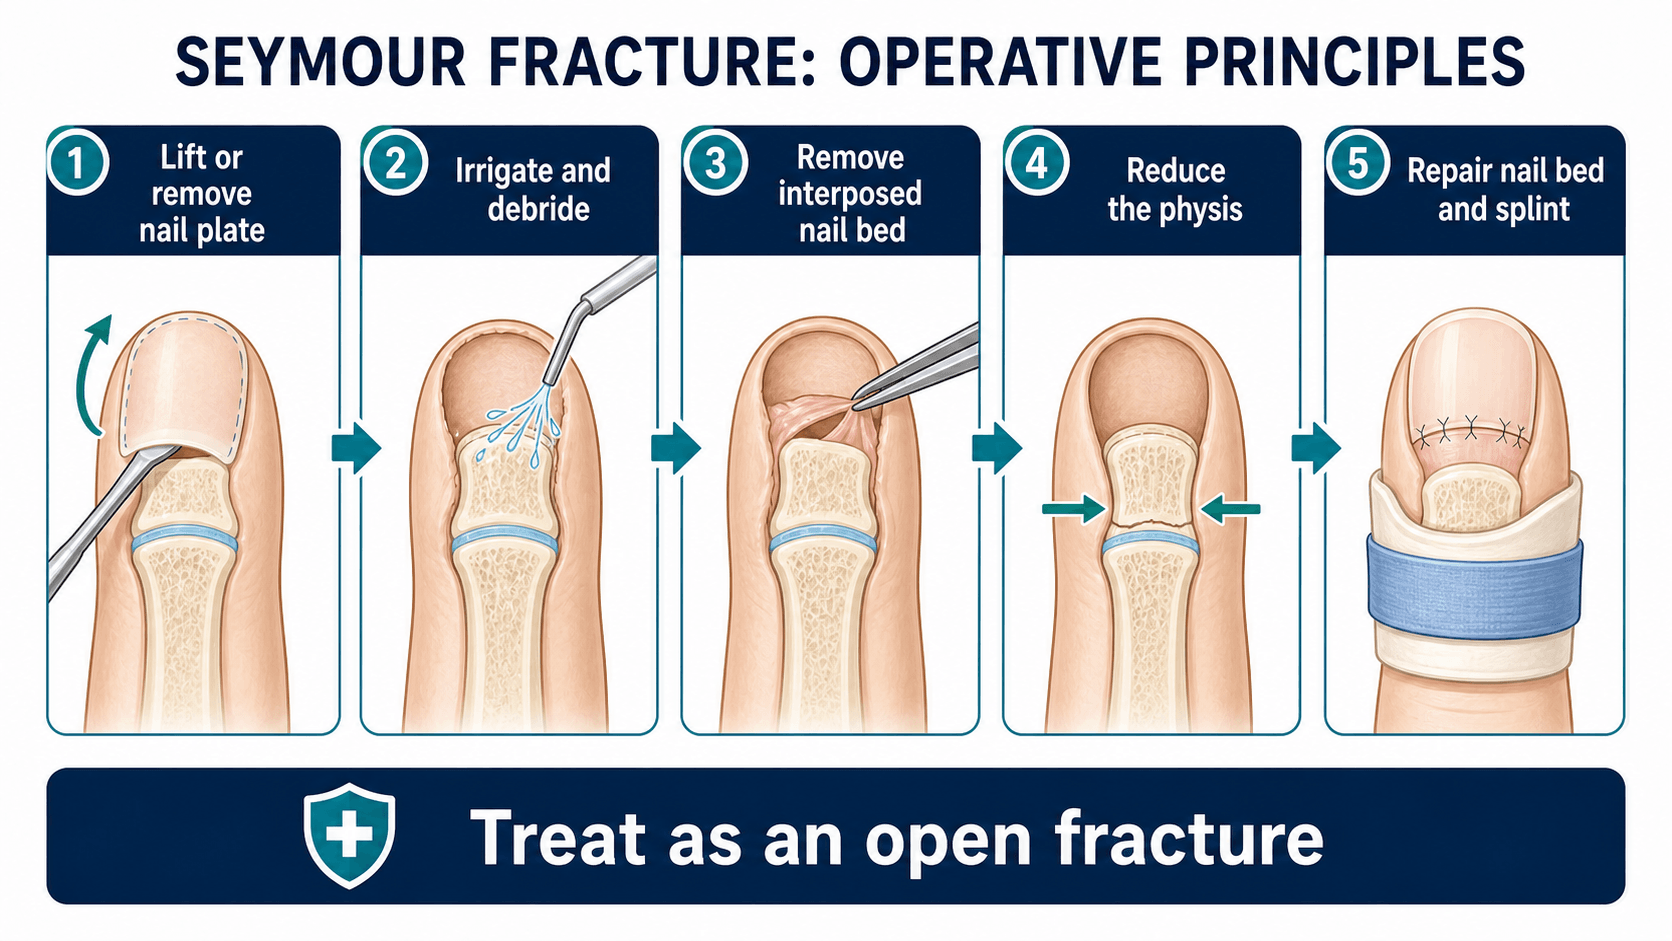
Preparation. Confirm the diagnosis clinically and radiographically, and give antibiotics according to local open-fracture and paediatric hand protocols. Use a digital block, sedation or general anaesthesia depending on age, cooperation and local practice, and prepare and drape the hand so the digit can be assessed and imaged properly.
Consent. Explain the operation as open-fracture care plus nail-bed reconstruction, and cover open fracture care, nail-bed repair, possible K-wire fixation, infection, nail deformity, stiffness, malunion, non-union, physeal disturbance and possible further surgery.
Exposure and debridement. Operative care should be meticulous but not aggressive.
- How to do it
- Use a bloodless field when safe, while confirming fingertip perfusion is not compromised.
- Pitfall
- A tight digital tourniquet left on is unsafe.
- How to do it
- Elevate or remove it if displaced, dirty, trapped or blocking inspection.
- Pitfall
- Leaving the nail plate in place can hide matrix interposition.
- How to do it
- Handle gently and preserve the fold.
- Pitfall
- Scarring here can damage future nail growth.
- How to do it
- Irrigate thoroughly and remove dirt, clot and devitalised tissue.
- Pitfall
- Over-aggressive curettage can injure physis and germinal matrix.
Clearing the reduction block. The germinal matrix or nail bed is often folded into the fracture, which is why closed reduction may repeatedly fail. Extract the interposed tissue gently with fine instruments, and do not keep forcefully manipulating the distal phalanx against a soft-tissue block.
Reduction and fixation. Reduce the distal phalanx anatomically and confirm alignment clinically and on AP and lateral imaging. Whether to wire depends on stability:
- Treatment direction
- Splint protection may be enough.
- Reason
- The soft-tissue block has been cleared and alignment is reliable.
- Treatment direction
- Use K-wire fixation.
- Reason
- Maintains reduction while the open physeal injury heals.
- Treatment direction
- Strongly consider K-wire fixation after debridement.
- Reason
- Higher risk of loss of position and infection-related complications.
- Treatment direction
- Fix if the child cannot protect the digit safely.
- Reason
- Prevents recurrent displacement during healing.
The wire often crosses the DIP joint to hold the distal phalanx, but fixation should follow fracture stability, child factors and local hand-surgery practice. Avoid repeated physeal trauma during wire placement.
Nail-bed repair. Repair the germinal or sterile matrix precisely with fine (6-0 or 7-0) absorbable sutures, under good lighting and magnification where available. The aim is smooth nail-bed continuity without inversion, overlap or excessive tension.
Stenting the fold. Preserve a clean nail plate if it can be reused. Replace it, or a sterile substitute, beneath the eponychial fold as a stent, to prevent fold adhesion (synechiae) and support nail regrowth.
Meticulous matrix apposition is what prevents a split, ridged or non-adherent nail. A randomised trial (Strauss and Miranda) showed 2-octylcyanoacrylate tissue adhesive gives outcomes equivalent to suture for simple nail-bed lacerations and is faster, which is useful in a squirming child. For nail-bed tissue loss, a sterile-matrix defect is resurfaced with a split-thickness nail-bed graft (harvested from the same nail bed or the great toe); germinal matrix loss is the worst scenario for future nail growth and may need a full-thickness germinal-matrix graft from the great toe, or nail-bed ablation if reconstruction is not feasible.
Antibiotics and Delayed Presentation
The infection numbers. Across 35 open Seymour fractures at a level 1 paediatric trauma centre, infection rates fell into three tiers: 0% (0/11) with acute appropriate treatment, 15% (2/13) with acute partial treatment and 45% (5/11) with delayed treatment. There were 7 infections in total, 5 of them osteomyelitis.
The middle tier changes practice. "Appropriate" meant all three of irrigation and debridement, fracture reduction and antibiotics. Children treated acutely but incompletely, reduced without proper debridement or splinted with antibiotics but never formally cleaned, still had a 15% infection rate.
Completeness protects the child. Speed alone does not. Seeing the patient within 24 hours and then doing two of the three things is a substantially worse outcome than doing all three, and that is the single most useful sentence to carry into a viva. It reframes the injury from "a mallet that needs a quick splint" to "an open physeal fracture that needs open-fracture treatment".
The counterweight. Of 65 consecutive children presenting within 24 hours, 58 (89%) were managed successfully in the emergency department with irrigation, debridement, reduction and a first-generation cephalosporin such as cephalexin. Only 7 required primary theatre, usually for unsuccessful closed reduction, and complications were rare, superficial infection the commonest.
Not every Seymour fracture goes to theatre. A stable, adequately reduced, properly debrided acute injury can be definitively treated in the emergency department, and theatre is for unsuccessful or unstable reduction. Four emergency-department children needed unplanned later surgery, usually for redisplacement, so the follow-up appointment is part of the treatment. Both series are retrospective and single-centre, and "stable reduction" is operator-dependent.
Antibiotic choice. Choice and duration should follow local paediatric open-fracture and hand-injury protocols, and a typical clean acute injury is usually covered for skin flora. Gross contamination, a bite, or farm or water exposure changes antibiotic and debridement planning. Broaden the discussion with senior clinicians for these, and for immunocompromise, delayed presentation or established infection.
- Assess
- Pain, nail position, wound status, X-ray alignment and signs of matrix interposition.
- Management implication
- Treat as higher-risk open fracture; debridement and stabilisation may still be required.
- Assess
- Discharge, redness, swelling, odour, worsening pain and pin or wound concerns.
- Management implication
- Cultures when available, debridement, antibiotics and close hand-surgery follow-up.
- Assess
- Fever, persistent pain, radiographic change such as osteolysis, raised inflammatory markers or deep infection concern.
- Management implication
- Senior review, targeted imaging when it changes care and longer antibiotic pathway.
- Assess
- Systemic signs or rapidly worsening infection.
- Management implication
- Do not delay treatment for MRI if urgent debridement and antibiotics are needed.
Complications
Early complications include:
- Missed open fracture and delayed antibiotics
- Pin-site infection when fixation is used
- Loss of reduction from unrecognised matrix interposition or inadequate fixation
- Soft-tissue necrosis from crush injury or tight dressings
- Persistent pain, swelling and stiffness
Late complications include:
- Osteomyelitis, especially after delayed diagnosis
- Non-union or malunion of the distal phalanx
- Persistent mallet deformity or extensor lag
- Nail deformity, including ridging, split nail, hook nail or absent nail growth
- Premature physeal arrest and distal phalanx growth disturbance
- DIP stiffness and a hypersensitive fingertip
How common. In a review of 206 paediatric distal phalanx fractures, Seymour fractures accounted for only 6% of the cohort but carried a 62% complication rate. That is second only to Salter-Harris IV injuries (100%) and clearly above mallet fractures (49%), against an overall rate of 31% across all distal phalanx fractures. The commonest complications were infection (22%), stiffness (15%) and nail deformity (13%).
Small injury, big consequence. A fingertip injury that looks trivial to a parent and to a busy department sits among the highest-risk distal phalanx fractures a child can sustain, which is why the open-fracture discipline above is not over-treatment. Note the design before quoting the figures: a single-centre retrospective review with clinician-recorded rather than independently adjudicated complications.
Follow-up. Structured follow-up is not optional, because nail deformity and stiffness declare late. Review covers union, the pin site, infection, nail growth, mallet posture and the physis. The child is seen until the nail has grown out and the DIP is moving, and nail growth and distal phalanx growth are followed until the complication window has passed.
The feared complication is not the X-ray appearance on day one; it is the open physeal wound that can become infected or scar the germinal matrix if not treated properly.
Clinical Reasoning Notes
The strongest answer starts by naming the injury correctly: an open distal phalanx physeal or juxta-epiphyseal fracture with nail-bed injury. That opening phrase immediately separates it from a simple mallet finger.
The next step is to explain why the clinical appearance is deceptive. The distal phalanx is flexed, but the nail fold is the dangerous clue. If the proximal nail plate sits superficial to the eponychial fold, the germinal matrix has probably been disrupted. If germinal matrix is trapped in the fracture, reduction fails until the tissue is cleared.
Nail-bed repair is not cosmetic trivia. It is part of fracture management because the nail bed and fracture communicate. Poor matrix alignment causes nail deformity. Missed contamination causes infection. Persistent soft-tissue interposition causes malunion, non-union or redisplacement.
A safe family explanation is:
"This is a small bone injury at the end of the finger, but because the nail bed is torn it behaves like an open fracture. We need to clean it properly, put the nail bed and bone back in the right position, give antibiotics, and then watch for infection, healing and nail growth."
Common pitfalls
- Calling it a mallet finger and treating with extension splint alone.
- Ordering only a hand X-ray and missing the true lateral digit view.
- Not looking under or around the proximal nail fold.
- Trying repeated closed reductions despite a soft-tissue block.
- Forgetting antibiotics and tetanus assessment.
- Repairing skin but leaving the nail bed and physis untreated.
Guidelines, Registries & Global Practice
The Seymour fracture is too rare to feature in standalone society guidelines or arthroplasty registries; instead it is governed by general paediatric open-fracture principles, which are broadly concordant across major bodies. The clinically useful comparison is therefore between the open-fracture frameworks that surgeons apply to this injury worldwide.
Global epidemiology
- Seymour fractures account for roughly 6 percent of paediatric distal phalanx fractures in referral series, making them uncommon but clinically high-consequence.
- Peak incidence is in school-age children and early adolescents (mean age around 9 to 10 years across series), reflecting open-physis anatomy and crush mechanisms.
- A boy predominance is consistent across hand and great-toe series. The middle finger and great toe are the most exposed digits.
- Diagnostic delay is common worldwide, with up to a third of cases presenting or being treated late, driving the infection and osteomyelitis burden.
Side-by-side principles from major bodies
- Relevant principle
- Early antibiotics, prompt debridement, combined orthoplastic decision-making, definitive soft-tissue cover.
- Implication for Seymour fracture
- Treat the nail-bed-violating injury as a true open fracture: early antibiotics and timely washout, with nail-bed repair as the soft-tissue component.
- Relevant principle
- Open physeal injuries warrant irrigation, debridement, reduction and antibiotics; most acute, stable injuries can be ED-managed.
- Implication for Seymour fracture
- Supports emergency-department management of stable acute injuries with first-generation cephalosporin cover and theatre for unstable or failed reductions.
- Relevant principle
- Respect the physis, achieve anatomical reduction, use minimal stable fixation (smooth K-wires) and avoid repeated physeal trauma.
- Implication for Seymour fracture
- Use smooth wires only when needed, avoid aggressive curettage across the physis and confirm reduction on a true lateral.
- Relevant principle
- Emphasis on infection prevention and recognition of the hidden open fracture.
- Implication for Seymour fracture
- High index of suspicion for the deceptive mallet-like presentation; nail-fold inspection is mandatory.
High- versus limited-resource practice variation
- High-resource setting
- Dedicated true AP and lateral digit films, occasional MRI for suspected osteomyelitis.
- Limited-resource setting
- Plain films only; rely heavily on clinical nail-fold inspection where imaging is scarce.
- High-resource setting
- Day-case theatre with magnification and fine instruments available.
- Limited-resource setting
- Wound care, debridement and nail-bed repair may be done under digital block in a procedure room; prioritise washout and antibiotics.
- High-resource setting
- Smooth K-wires readily available when unstable.
- Limited-resource setting
- Suture-only stabilisation or careful splinting after reduction is a reasonable alternative when wires are limited.
- High-resource setting
- Structured review for union, nail growth and physeal status.
- Limited-resource setting
- Family education on infection warning signs becomes the critical safety net.
The unifying message across every framework is identical: recognise the hidden open fracture, give early antibiotics, clear the soft-tissue block, repair the nail bed and protect the physis.
Controversies and Areas of Uncertainty
The Seymour fracture is uncommon, so the evidence base is dominated by small retrospective series and a single registered systematic review protocol rather than randomised trials. Several practical questions remain genuinely unsettled, and they are favourite viva discussion points.
- Arguments either way
- Al-Qattan reported uncomplicated healing in all wired cases but mild flexion deformities and one infection among splinted cases; Lin and colleagues managed most acute injuries in the emergency department without theatre, and Cha and colleagues maintained reduction without wires in delayed cases.
- Pragmatic position
- Reserve K-wire fixation for unstable, redisplacing, markedly displaced or unreliable-protection cases rather than treating it as automatic.
- Arguments either way
- Removal allows full inspection and nail-bed repair; some authors elevate rather than excise a clean, adherent plate and reuse it as an eponychial stent.
- Pragmatic position
- Remove or elevate when inspection, debridement or matrix extraction demands it; preserve a clean plate as a stent where possible.
- Arguments either way
- Lin and colleagues found a first-generation cephalosporin (cephalexin) adequate for most acute injuries; contaminated, bite, water or delayed injuries justify broader cover.
- Pragmatic position
- Follow local open-fracture protocol; cephalexin-equivalent cover is reasonable for clean acute injuries, broaden for contamination or delay.
- Arguments either way
- Most series use a 24-hour cut-off; infection risk rises sharply beyond it, but the threshold is pragmatic, not biological.
- Pragmatic position
- Treat within 24 hours where possible and treat all delayed cases as higher-risk open fractures.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A ten-year-old presents after a door crush with a flexed distal phalanx and blood at the proximal nail fold. How do you manage this?”
“Closed reduction of a distal phalanx physeal fracture keeps springing back. What is the likely reason?”
“A child presents five days after a finger crush with swelling, redness and discharge at the nail fold, and the X-ray shows a distal phalanx physeal fracture. How does delay change your management?”
Recognise
- Child or adolescent
- Crush or ball injury
- Mallet-like DIP posture
- Blood at proximal nail fold
- Nail plate above eponychial fold
Image
- Dedicated digit AP
- True lateral is essential
- Physeal widening
- Salter-Harris I or II
- Juxta-epiphyseal fracture
Treat
- Analgesia
- Antibiotics
- Tetanus check
- Washout and debridement
- Remove interposed matrix
- Nail-bed repair
- K-wire if unstable
Do Not Miss
- Open fracture
- Germinal matrix interposition
- Osteomyelitis risk
- Nail deformity
- Physeal arrest
Evidence Signals
Delayed treatment of open Seymour fractures sharply increases infection
- 35 open Seymour fractures over 10 years at a level 1 paediatric trauma centre; 7 infections, including 5 osteomyelitis.
- Infection rate was 0 percent (0/11) with acute appropriate treatment, 15 percent (2/13) with acute partial treatment and 45 percent (5/11) with delayed treatment.
- Appropriate treatment was defined as irrigation and debridement, fracture reduction and antibiotics.
Most acute Seymour fractures can be managed without theatre
- 65 acute Seymour fractures (presenting within 24 hours) in 65 children, mean age 10 years.
- 58 of 65 (89 percent) were managed in the emergency department; 7 had primary irrigation, debridement, open reduction and K-wire fixation, usually for unsuccessful closed reduction.
- Cephalexin gave adequate cover and complications were rare, with superficial infection most common; 4 ED-managed cases needed unplanned surgery, usually for redisplacement.
Evidence Base
Al-Qattan: the defining Seymour fracture series
- 25 extra-articular transverse fractures of the base of the distal phalanx across children, adolescents and adults.
- Before physeal closure the fracture line runs through the metaphysis 1 to 2 mm distal to the growth plate; in adults it lies just distal to the extensor tendon insertion.
- 18 fractures were treated by closed reduction and splinting, with 1 infection and 3 mild residual flexion deformities; all 5 K-wired fractures healed without complication, and 2 late-presenting adults developed malunion.
Seymour fractures carry a high complication rate among distal phalanx injuries
- 206 paediatric distal phalanx fractures reviewed; Seymour fractures made up 6 percent of the cohort.
- Overall complications occurred in 31 percent of children, with the highest rates in Salter-Harris IV (100 percent), Seymour (62 percent) and mallet (49 percent) fractures.
- The commonest complications were infection (22 percent), stiffness (15 percent) and nail deformity (13 percent).
Great-toe (hallux) Seymour fractures follow the same open-fracture logic
- 5 boys (mean age 10.3 years) with open physeal fractures of the hallux distal phalanx and nail-bed injury.
- 40 percent were initially missed and 60 percent were transfers, underlining frequent diagnostic delay in toe injuries.
- Suture-only stabilisation produced no infections, no reoperations and no physeal bars on follow-up imaging.
No consensus on optimal management: systematic review framing
- Confirms there is at present no consensus on the optimal management of Seymour fractures.
- Defines the injury as an open, displaced juxta-epiphyseal distal phalanx fracture with overlying nail-bed laceration in a child with an open physis.
- Sets superficial and deep infection as primary outcomes, with malunion, non-union, reoperation, physeal disturbance and nail dystrophy as secondary outcomes.
Long-Term Outcome at a Mean of Ten Years - What Actually Persists
- 24 skeletally immature patients, mean age 8.5 years, followed for a mean of 10 years (range 1 to 18) - by far the longest follow-up available for this injury.
- 9 treated non-operatively; 9 by debridement, open reduction and fixation; 5 needed an additional K-wire across the distal interphalangeal joint for instability.
- 23 of 24 regained full motion (mean 80 degrees), and there was NO flexion deformity and NO infection in the series.
- Minor growth disturbance of the distal phalanx and nail in 5 patients, plus solitary nail dystrophy in 6 - 11 nail or growth irregularities in 24 children.
- 9 of those 11 irregularities were NOT a relevant cosmetic problem for the patient; mean visual analogue score at 1 year was 0.6.