Progressive Arthritis | Identical Pattern to SLAC | Motion-Preserving Salvage
- Identical arthritis pattern to SLAC wrist - only aetiology differs (nonunion vs SL dissociation)
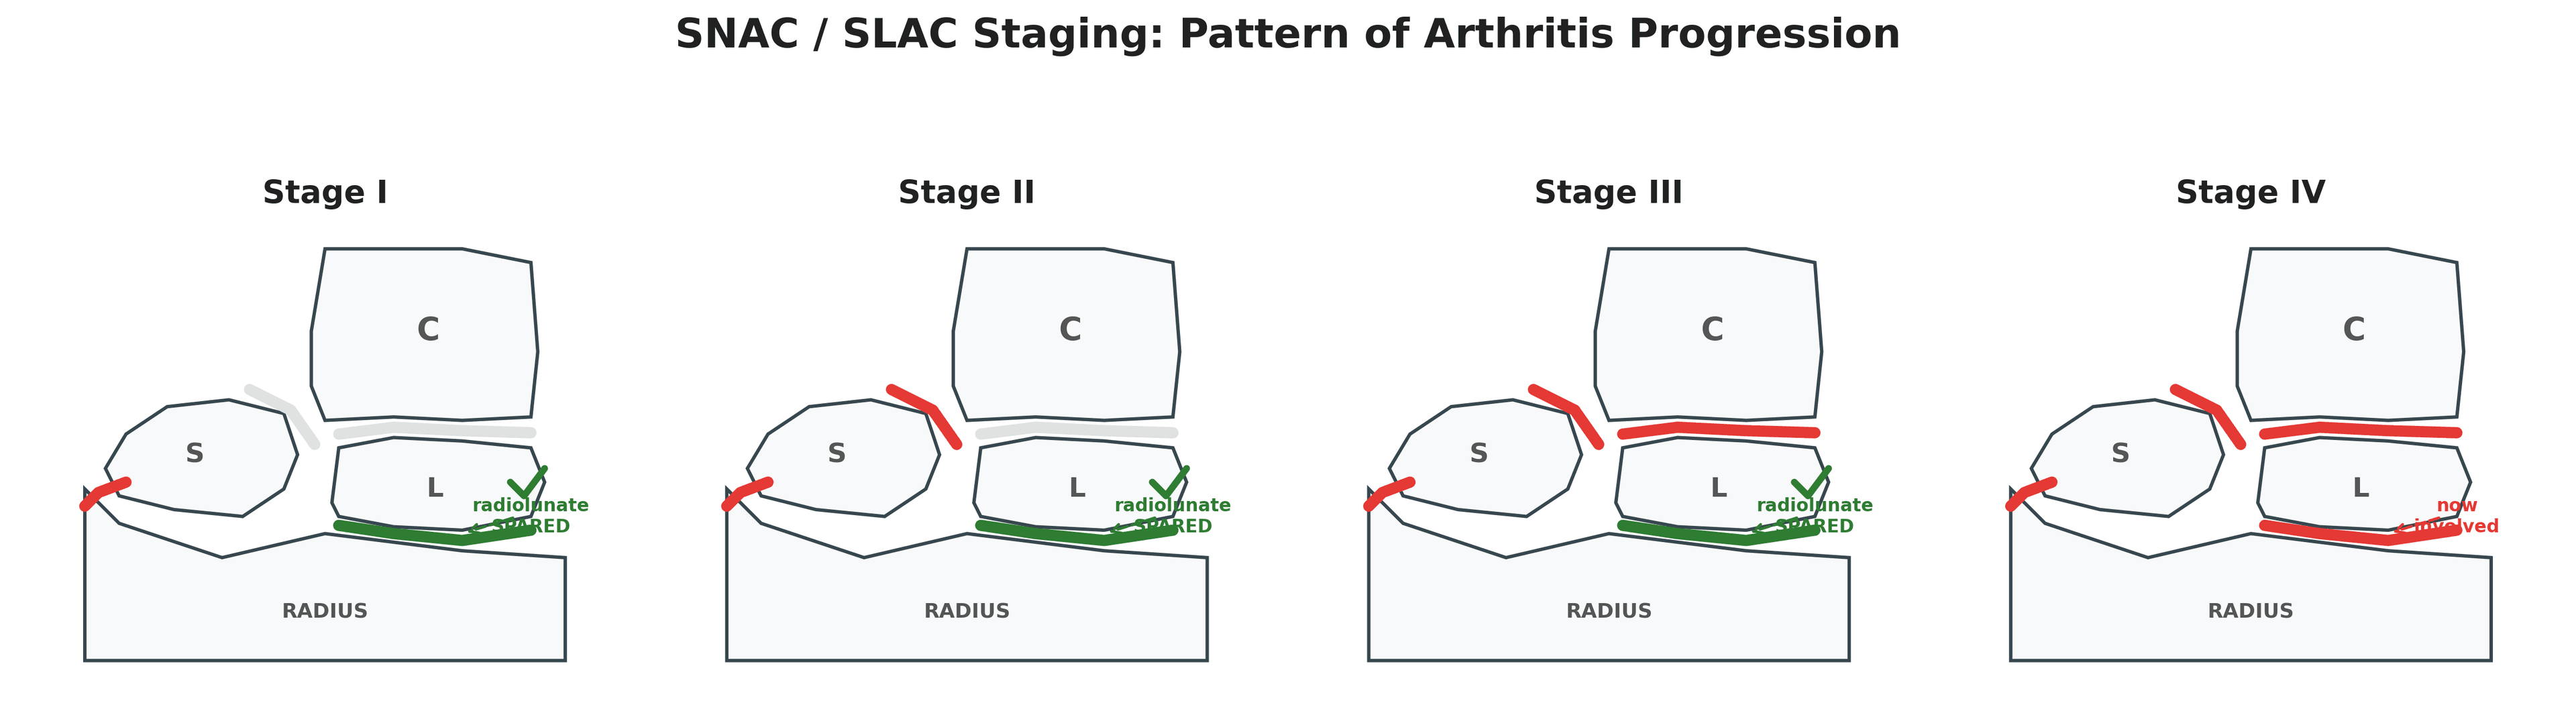
- Radiolunate joint preserved until Stage IV - allows motion-preserving procedures
- Stage I window: May still attempt nonunion repair with styloidectomy
- Attribution: the SNAC staging is Watson's, derived from his SLAC (scapholunate advanced collapse) sequence — the arthritis follows the same radial-styloid-first, capitolunate-last pattern, which is why the salvage options are shared
- Stage II/III treatment: 4-corner fusion or proximal row carpectomy at Stage II (comparable outcomes); 4-corner fusion at Stage III, where the arthritic capitate head contraindicates a standard PRC
- Few nonunions are free of arthritis beyond 10 years (Mack 1984); mean duration to radioscaphoid arthritis approximately 17 years
- “SNAC = SLAC pattern from different aetiology
- “Lunate stays congruent with radius - preserved articulation
- “4CC fuses capitate-lunate-hamate-triquetrum after scaphoid excision
- “PRC removes entire proximal row - capitate articulates with lunate fossa
Overview
What it is. SNAC (scaphoid nonunion advanced collapse) wrist is the predictable pattern of progressive arthritis that develops after a scaphoid nonunion that was never treated, or whose treatment failed. It shares an identical arthritis progression with SLAC (scapholunate advanced collapse) wrist and differs only in aetiology: a nonunion rather than scapholunate dissociation.
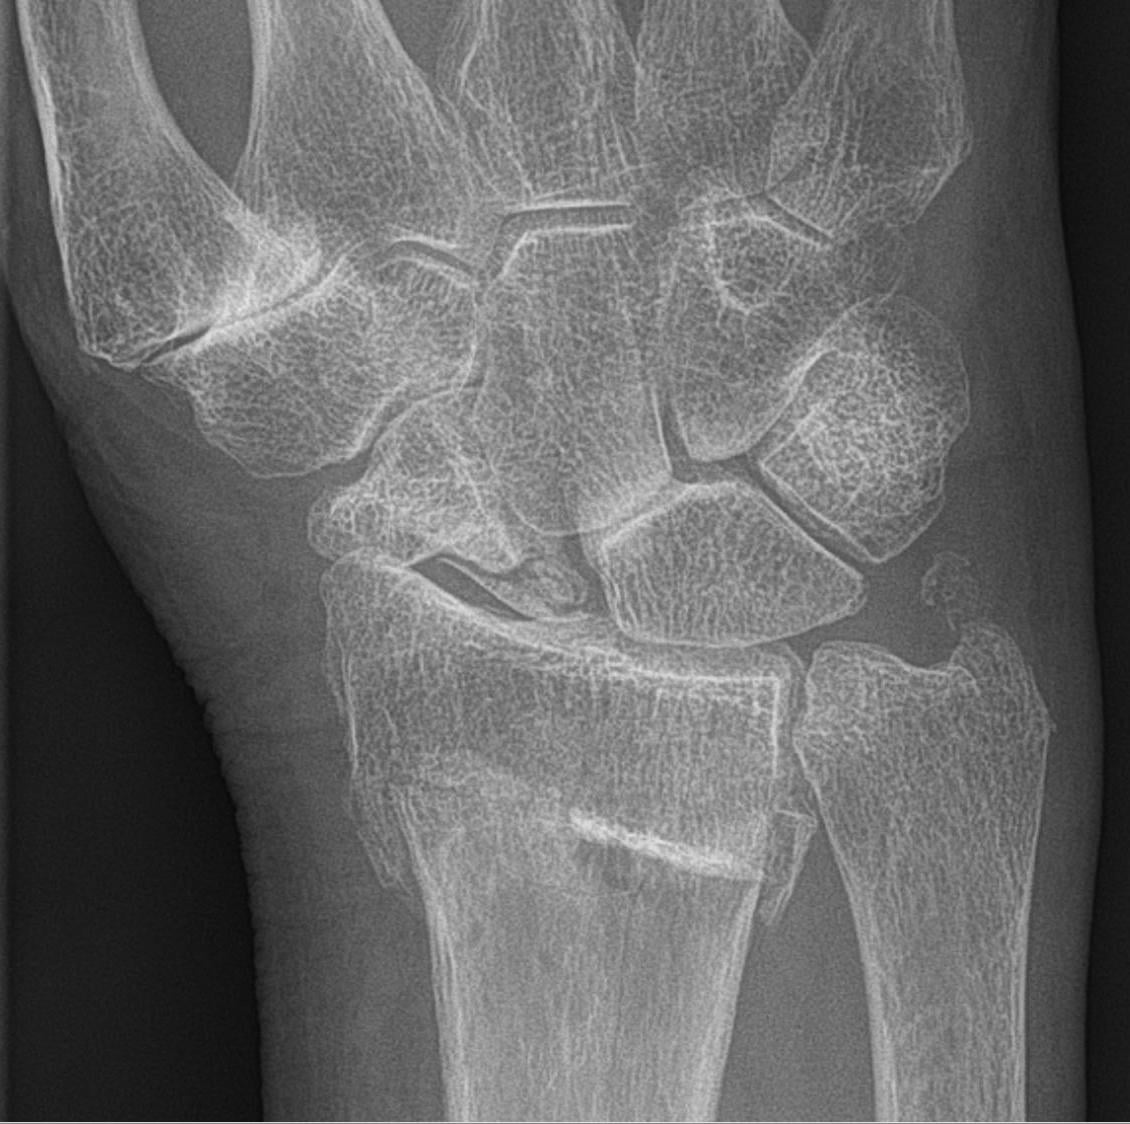
Natural history. Untreated scaphoid nonunion leads to SNAC wrist in the vast majority of cases. In the defining study by Mack et al. (1984), degenerative change followed a predictable, time-dependent sequence: lesions confined to the scaphoid at a mean of 8.2 years, radioscaphoid arthritis at 17.0 years and generalised wrist arthritis at 31.6 years, with few non-unions remaining free of arthritis beyond 10 years.
Why the sequence matters. Understanding it is essential for counselling patients about the importance of treating a scaphoid nonunion, for staging the disease to guide surgery, and for choosing between motion-preserving and motion-eliminating procedures.
The window for nonunion repair closes as arthritis progresses. Early treatment prevents this irreversible cascade.
Anatomy
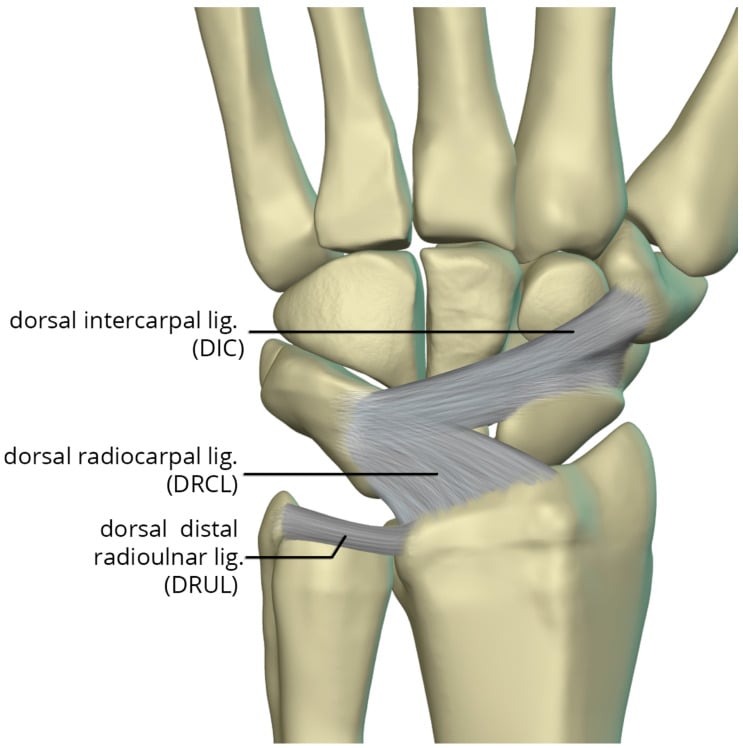
The scaphoid as a link. The scaphoid is the critical link between the proximal and distal carpal rows. It spans the radiocarpal and midcarpal joints, transfers approximately 60% of axial load from the distal row to the radius, and coordinates proximal-row flexion-extension with distal-row motion.
The scaphoid has a retrograde (distal-to-proximal) blood supply: the dorsal carpal branch of the radial artery enters through foramina at the dorsal ridge (distally) and supplies roughly 80% of the bone including the entire proximal pole by running proximally; the volar/distal tubercle branch supplies only the distal ~20-30%. Consequently a proximal pole fracture or nonunion cuts off the proximal fragment's supply, producing a high rate of avascular necrosis and nonunion - which is exactly why proximal-pole viability (MRI T1 signal, punctate bleeding at surgery) drives the Stage-I repair decision and the choice of a vascularised graft.
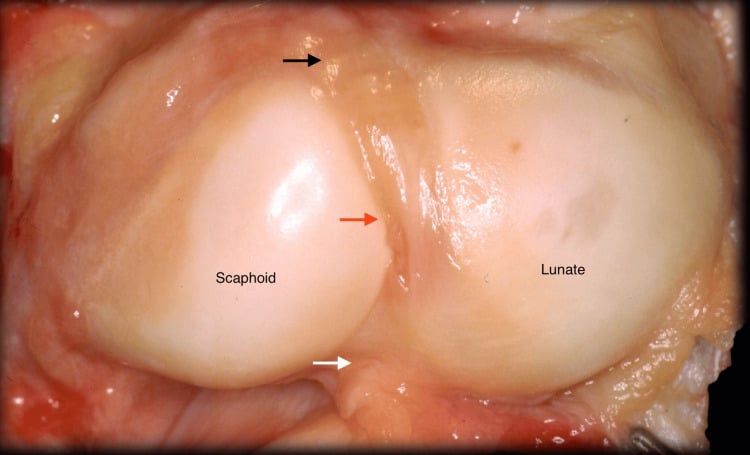
Why the radiolunate joint survives. The lunate keeps its spherical articulation with the lunate fossa of the radius, so the radiolunate joint stays congruent and normally loaded, with no abnormal shear or point loading. It is preserved until very late disease (Stage IV, which is rare). That preservation is the key anatomical feature that allows motion-preserving salvage in most patients.
Pathophysiology
The fragments part company. Once the scaphoid fails to unite, the distal fragment flexes with the distal carpal row, creating a dorsal intercalated segment instability (DISI) pattern. The proximal fragment extends with the lunate, to which it remains linked, and loses its normal articulation with the distal fragment. It may develop AVN, especially after proximal pole fractures.
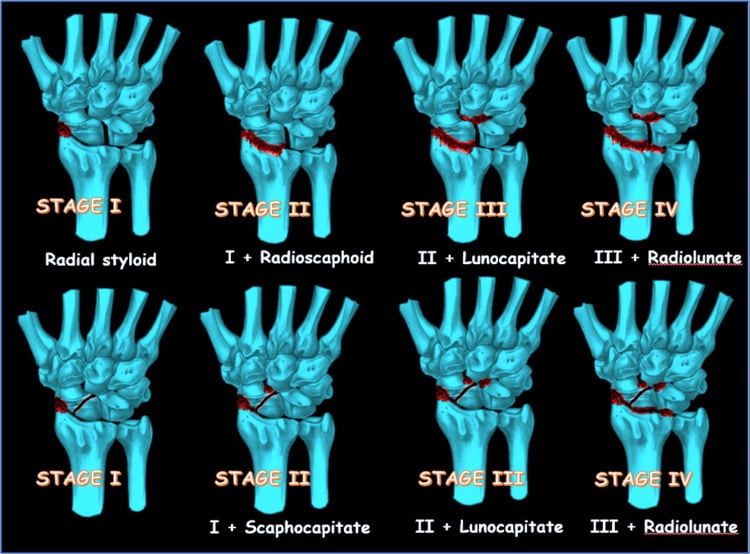
The load goes to the wrong joints. The dorsal lip of the flexed distal fragment comes into abnormal contact with the radial styloid, point loading the styloscaphoid articulation, while stress rises across the scaphocapitate joint. Cartilage then degenerates in a predictable sequence:
- Stage I, styloscaphoid. The cartilage wears and an osteophyte forms at the styloid tip ("beaking").
- Stage II, scaphocapitate. With the scaphoid's span function lost, the capitate migrates proximally and articulates abnormally with the scaphoid fragments, and midcarpal degeneration begins.
- Stage III, capitolunate. Further proximal migration makes the capitate-lunate articulation incongruent and its cartilage is lost. The radiolunate joint is still preserved.
- Stage IV, pancarpal (rare). Only with severe, long-standing disease is the radiolunate articulation finally involved and the spherical lunate-radius relationship lost. No motion-preserving option remains.
SNAC beside SLAC. The two share every stage and differ in the cause and the mechanism of scaphoid malposition, so the treatment algorithm is the same for both at each stage.
- SNAC Wrist
- Scaphoid nonunion
- SLAC Wrist
- Scapholunate dissociation
- SNAC Wrist
- Distal fragment malrotation
- SLAC Wrist
- Scaphoid flexion, lunate extension
- SNAC Wrist
- Radial styloid OA
- SLAC Wrist
- Radial styloid OA
- SNAC Wrist
- Scaphocapitate OA
- SLAC Wrist
- Scaphocapitate OA
- SNAC Wrist
- Capitolunate OA
- SLAC Wrist
- Capitolunate OA
- SNAC Wrist
- Pancarpal (rare)
- SLAC Wrist
- Pancarpal (rare)
- SNAC Wrist
- Identical
- SLAC Wrist
- Identical
Classification Systems
SNAC staging follows the joints in the order they fail, and the stage is what decides the operation.
- Joints involved
- Radial styloid and scaphoid
- Radiographic findings
- Styloid beaking (osteophyte), narrowed styloscaphoid joint space, sclerosis at the styloid tip; scaphocapitate and capitolunate joints preserved. Lateral: DISI pattern
- Significance
- Window for nonunion repair still open - last chance to restore near-normal wrist function
- Joints involved
- Midcarpal (capitate-scaphoid)
- Radiographic findings
- Scaphocapitate narrowing, sclerosis and osteophytes at the midcarpal level; proximal migration of the capitate begins; radiolunate and capitolunate joints preserved
- Significance
- Repair window has closed - motion-preserving salvage indicated
- Joints involved
- Capitate-lunate articulation added
- Radiographic findings
- All Stage II findings plus capitolunate narrowing and more pronounced proximal capitate migration; radiolunate joint still preserved
- Significance
- Motion-preserving salvage still possible despite capitolunate involvement
- Joints involved
- All carpal articulations including radiolunate
- Radiographic findings
- Radiolunate joint space loss, diffuse arthritic change throughout the carpus, severe proximal row collapse. Lateral: complete carpal collapse
- Significance
- Motion-preserving procedures no longer possible. Rare - most patients present or are treated at earlier stages
R-S-C-PSNAC Stage Progression
Hook:RSC-P: Radial Styloid, ScaphoCapitate, CapitoLunate, Pancarpal - same sequence as SLAC!
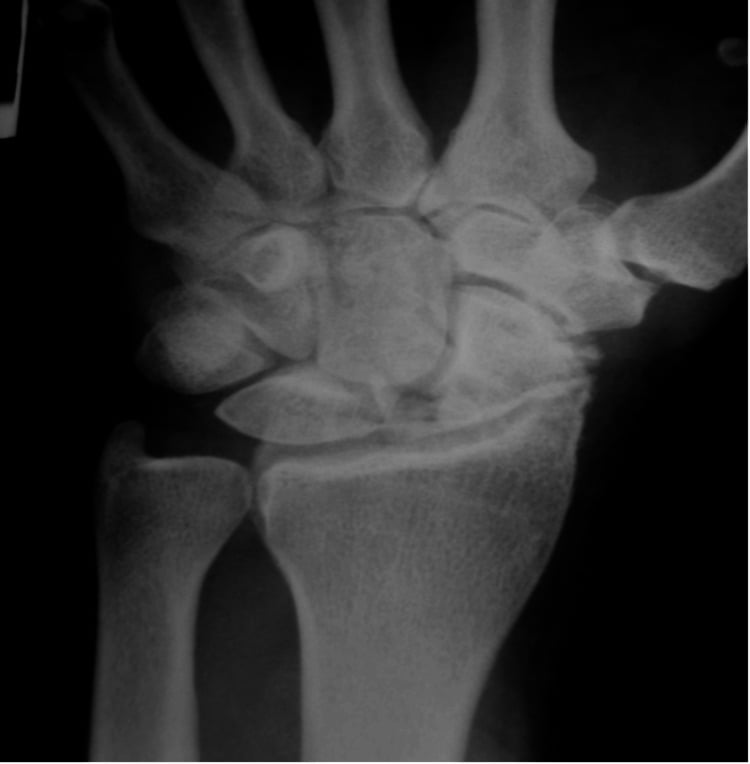
Clinical Assessment
The story. Wrist pain, often long-standing, with decreased grip strength and limited motion. There is a history of prior scaphoid fracture, often remote, and the patient may recall a wrist injury years earlier that was never treated.
The pain. Typically dorsoradial, worse with gripping and loading, and activity-related at first; it may become constant in advanced stages.
What it costs the patient. Push-ups and weight-bearing on the hand become difficult, as do twisting movements such as opening jars. Work capacity falls, especially in manual labourers, and sport is affected.
Examination. Inspection may show dorsal swelling from synovitis, visibly reduced motion and a possible radial deviation deformity. The radial styloid, anatomical snuffbox and scaphoid tubercle are tender, and there may be palpable crepitus with motion. Flexion, extension and radial deviation are reduced, and grip strength is typically reduced; document the preoperative range for later comparison. The Watson scaphoid shift test may be difficult to perform because of the nonunion.
Provocative tests point to the stage:
- Scaphocapitate grind test - axially load the wrist while moving it through flexion-extension. Pain or crepitus at the midcarpal level is positive and suggests Stage II or higher.
- Capitolunate stress test - direct pressure over the capitate with the wrist in neutral. Tenderness suggests Stage III involvement.
- Radiolunate grind test - positive only in Stage IV.
Differential diagnosis. Dorsoradial wrist pain with degenerative change has several mimics. The key discriminator for SNAC is an established scaphoid nonunion driving the styloid-to-pancarpal pattern with a preserved radiolunate joint.
- Key distinguishing feature
- Established scaphoid nonunion; styloid then scaphocapitate then capitolunate arthritis
- Radiolunate joint
- Preserved until Stage IV
- Defining investigation
- Scaphoid-view radiographs / CT showing nonunion
- Key distinguishing feature
- Scapholunate dissociation (widened SL interval), no nonunion
- Radiolunate joint
- Preserved until Stage IV
- Defining investigation
- PA radiograph showing SL gap; identical arthritis pattern
- Key distinguishing feature
- Diffuse change without nonunion or SL gap
- Radiolunate joint
- Often involved early
- Defining investigation
- Radiographs; absence of scaphoid nonunion or SL injury
- Key distinguishing feature
- Symmetrical, periarticular erosions, raised inflammatory markers
- Radiolunate joint
- Involved early/diffusely
- Defining investigation
- Serology (RF/anti-CCP), erosive radiographic pattern
- Key distinguishing feature
- Pain at base of thumb, positive grind, radial-sided
- Radiolunate joint
- Not involved
- Defining investigation
- Trapeziometacarpal radiographs
- Key distinguishing feature
- Tendinous (1st dorsal compartment), positive Finkelstein, no joint-space loss
- Radiolunate joint
- Normal
- Defining investigation
- Clinical; ultrasound if uncertain
- Key distinguishing feature
- Lunate sclerosis/collapse rather than scaphoid pathology
- Radiolunate joint
- Lunate-centred change
- Defining investigation
- Radiographs/MRI of the lunate
Investigations
Radiographs stage the disease (the findings for each stage are in the staging table). Three views:
- PA - overall carpal alignment and joint spaces
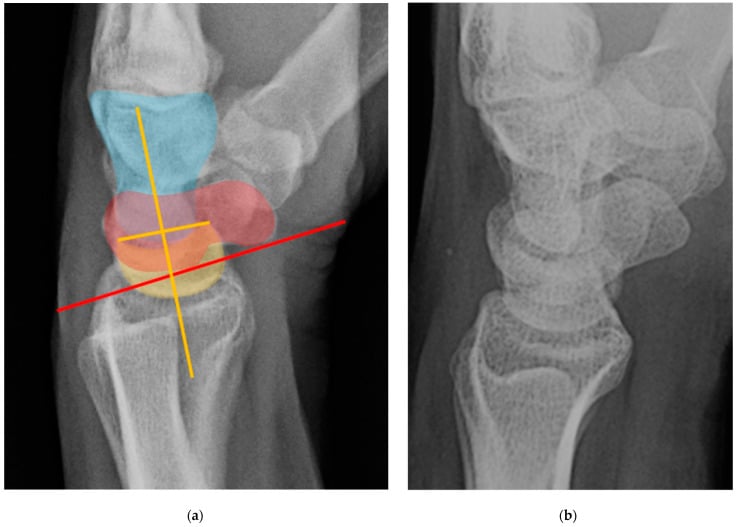
- Lateral - carpal height ratio and the DISI pattern
- Scaphoid views - nonunion characteristics and fragment positions
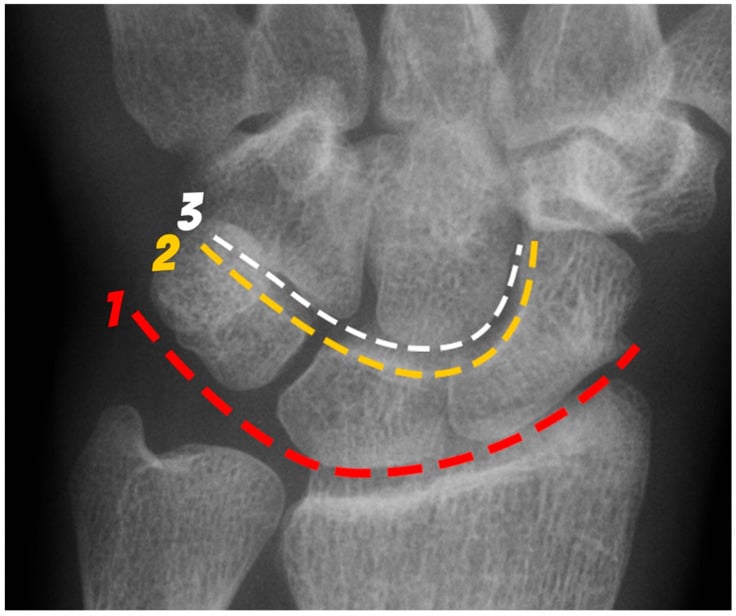
Measurements. The scapholunate angle lies between a line along the volar scaphoid and a line through the lunate axis. It rises toward 90 degrees as the scaphoid flexes and the lunate extends, and an angle greater than 70 degrees indicates DISI. The carpal height ratio falls as the capitate migrates proximally. The radiolunate angle stays normal until Stage IV.
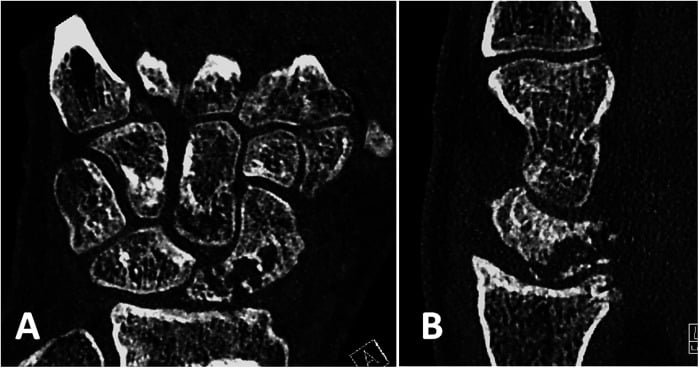
CT is the arbiter of union. Plain films consistently overcall union, so CT along the scaphoid axis is the standard before deciding on salvage. It shows the nonunion site (gap, cystic change, sclerosis), the position and rotation of the fragments, the integrity of the articular surface at each joint and cystic change in the carpal bones. It also gives an indirect assessment of proximal pole vascularity, shows arthritic change better than plain film, and is the planning study for salvage.
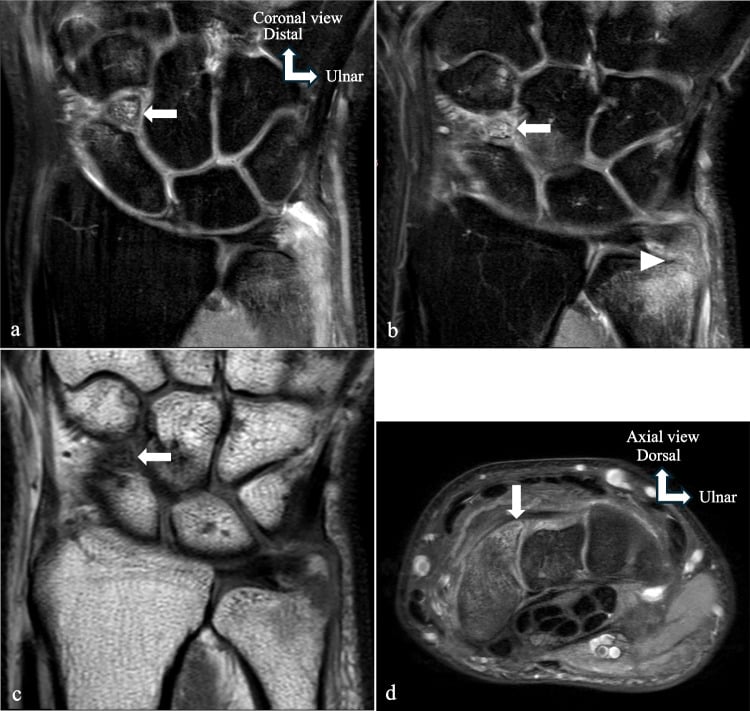
MRI answers the vascularity question when repair is being considered: low T1 signal in the proximal pole suggests AVN. It also answers the occult-injury question, showing the ligaments (the SL ligament is often attenuated or torn), associated bone injury and other pathology, and cartilage damage, including the state of the radioscaphoid joint when the plain film is equivocal.
Management
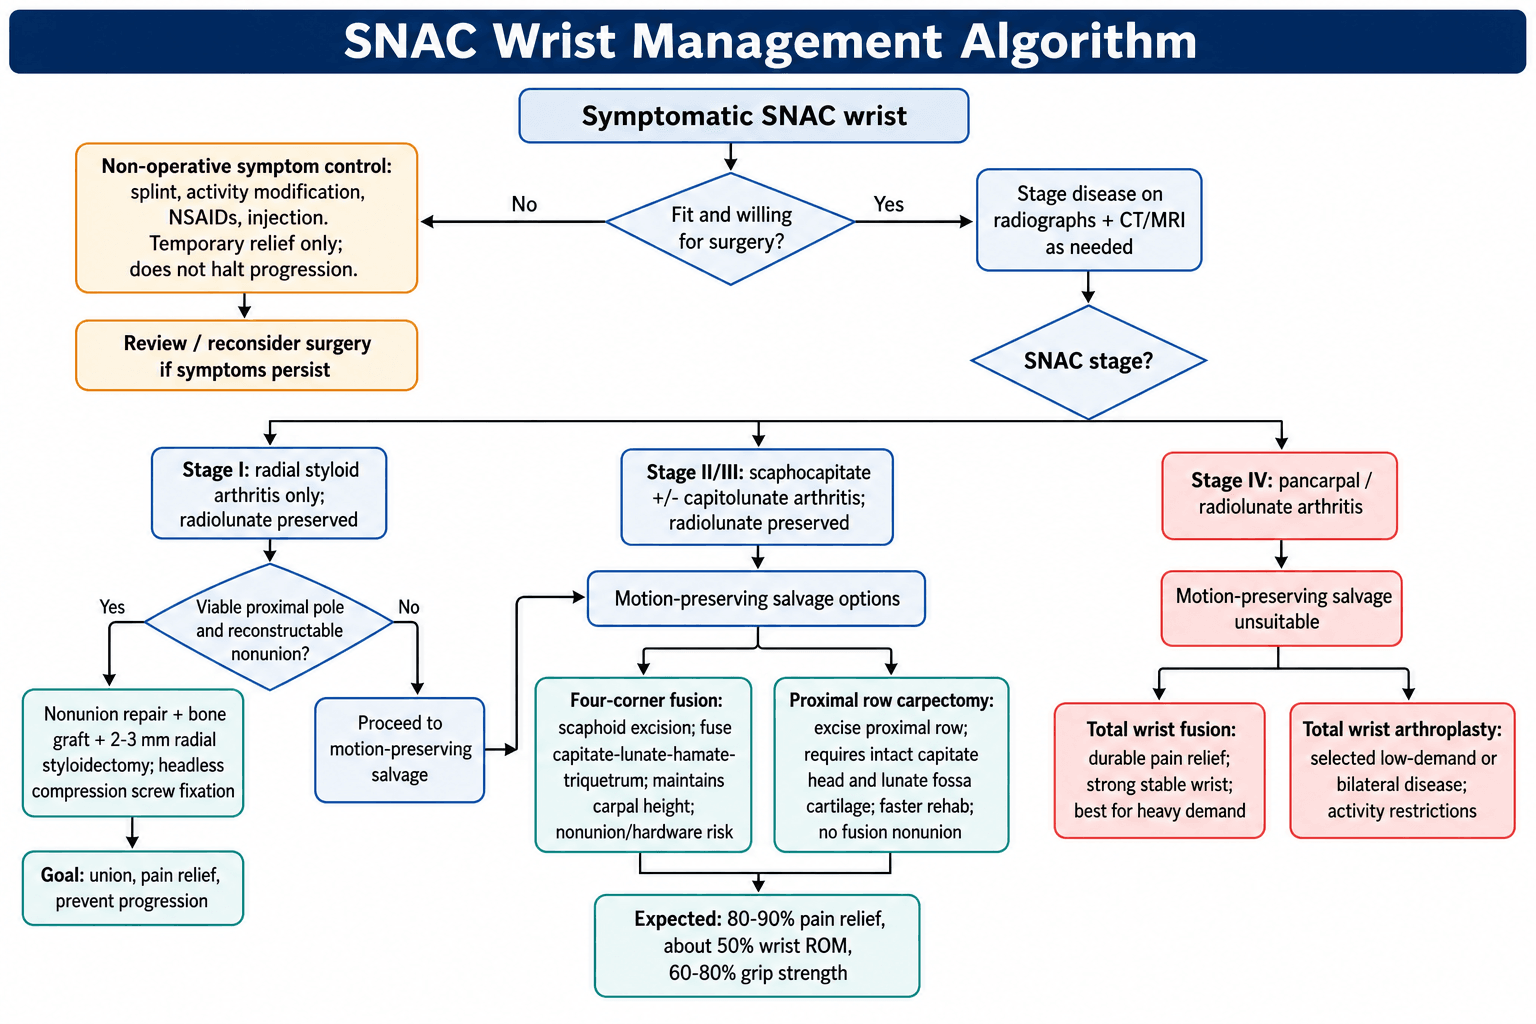
Non-operative treatment has a limited role. It may give temporary symptom relief but does not alter progression: untreated disease continues to advance through the stages. It is generally reserved for patients unfit for surgery, those who decline it, or as a bridge to definitive treatment, using activity modification, splinting or bracing, NSAIDs and intra-articular corticosteroid injection. Surgery is indicated for symptomatic SNAC in appropriate surgical candidates.
Stage I: the repair window
Save the scaphoid if you can. Nonunion repair with radial styloidectomy needs three things:
- A viable proximal pole on MRI
- A repairable nonunion configuration
- A patient willing to accept a prolonged recovery
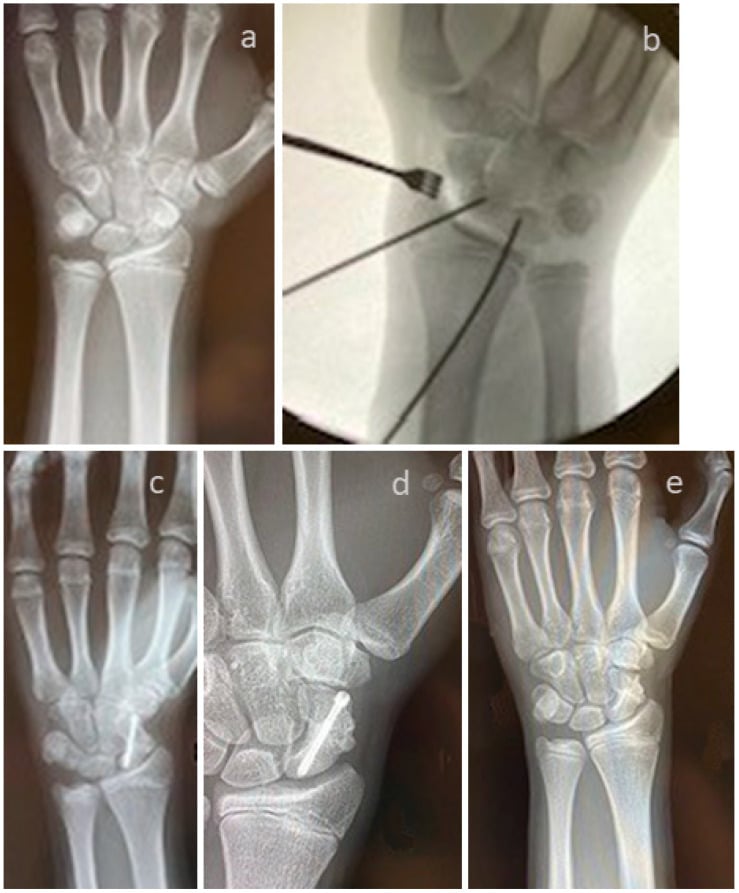
The nonunion is opened and fixed with a headless compression screw, using vascularised or non-vascularised bone graft, and a 2-3 mm radial styloidectomy addresses the styloid arthritis.
The graft is matched to vascularity and deformity: (1) a non-vascularised cancellous/structural graft (distal radius or iliac crest, e.g. a volar interpositional Russe/Fisk-Fernandez wedge to correct a humpback flexion deformity) for a well-vascularised nonunion; (2) a pedicled vascularised graft - the 1,2-intercompartmental supraretinacular artery (1,2-ICSRA) graft from the dorsal distal radius - for proximal-pole nonunion with avascularity; (3) a free vascularised medial femoral condyle (MFC) corticoperiosteal flap (descending genicular artery) for avascular proximal-pole nonunion, failed prior surgery, or significant bone loss/humpback, where it gives the highest union rates in AVN.
Go straight to salvage when the proximal pole has AVN, the nonunion is not reconstructable, or the patient prefers a single definitive procedure. The options are then those of Stage II/III.
Stages II and III: motion-preserving salvage
Both stages keep the radiolunate joint, so both are treated with motion-preserving salvage. What separates them is the capitate head.
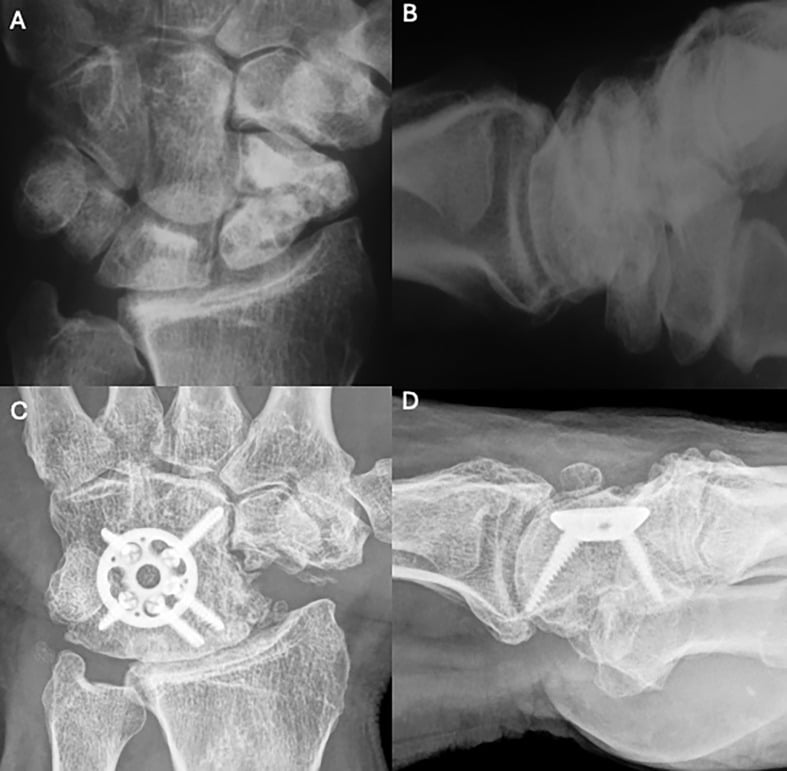
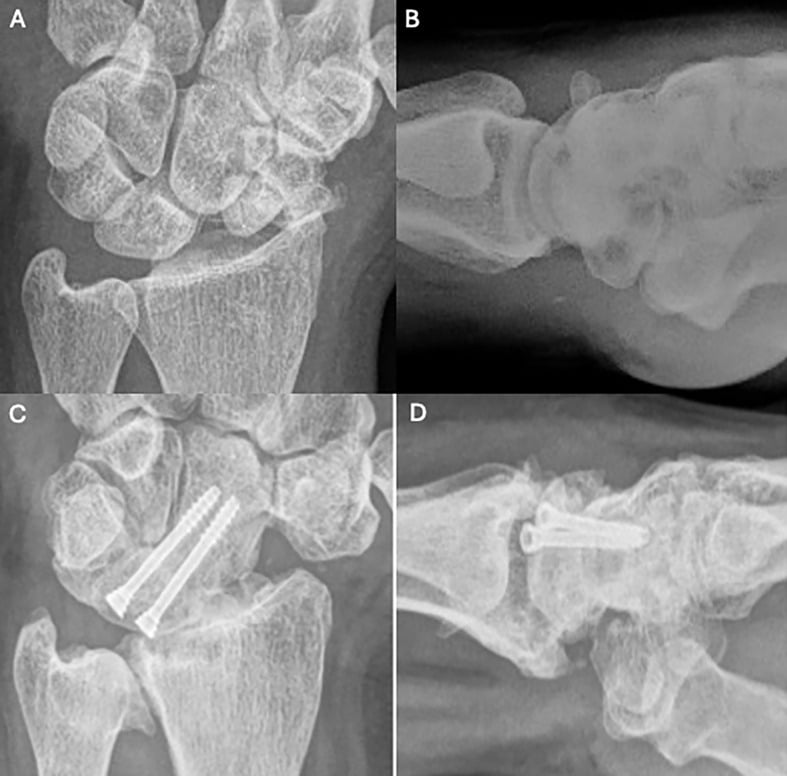
Four-corner fusion (4CC, the SLAC procedure) excises the scaphoid and fuses the capitate, lunate, hamate and triquetrum. The intact radiolunate articulation is its precondition.
Proximal row carpectomy (PRC) excises the entire proximal row so that the capitate articulates with the lunate fossa.
Why the stage decides between them. A PRC creates a new joint between the head of the capitate and the lunate fossa of the radius, so it needs intact cartilage on both; damage to either contraindicates it. Stage III takes that away: capitolunate arthritis is arthritis of the capitate head, so a standard PRC would articulate a worn surface against the radius and fail. Four-corner fusion instead bypasses the diseased capitolunate joint by fusing across it, which is why it remains available at Stage III when PRC is not.
At Stage II both remain on the table, and the choice depends on surgeon and patient factors. Scaphocapitate arthritis involves the capitate's articulation with the scaphoid and may spare the proximal, lunate-facing part of the head, so inspect the capitate head intraoperatively before committing; if it is worn, convert to a four-corner fusion. Capitate resurfacing and dorsal capsular interposition have been described to extend PRC into Stage III, but they are niche solutions rather than the standard answer.
- 4CC
- More demanding
- PRC
- Simpler
- 4CC
- Longer
- PRC
- Shorter
- 4CC
- 5-10%
- PRC
- None
- 4CC
- Possible
- PRC
- None
- 4CC
- Better maintained
- PRC
- Decreased
- 4CC
- Slower (8-12 weeks)
- PRC
- Faster (6-8 weeks)
- 4CC
- Similar (50%)
- PRC
- Similar (50%)
- 4CC
- Similar (80-90%)
- PRC
- Similar (80-90%)
- 4CC
- Similar
- PRC
- Similar
- 4CC
- Convert to TWF
- PRC
- Convert to TWF or TWA
- 4CC
- Radiolunate joint intact
- PRC
- Capitate head + lunate fossa intact
Capitolunate fusion is a smaller alternative to a full four-corner fusion: fewer surfaces to unite and less hardware, at the cost of a narrower correction. The choice between the two is decided by the state of the triquetrohamate joint.
Stage IV: motion-eliminating options
Total wrist fusion is the gold standard. It is a complete radiocarpal fusion that includes the carpometacarpal joints, set in 10-15 degrees of extension and neutral deviation and fixed with a dorsal plate spanning radius to metacarpals. It gives definitive pain relief and a strong, stable wrist, appropriate for heavy labourers, at the price of all wrist motion and compensatory motion at other joints, which may affect function significantly.
Total wrist arthroplasty is the alternative for selected patients: the low-demand, those with bilateral disease, and those who need to preserve motion. It is less durable than fusion, has a higher complication rate, imposes strict activity restrictions and is not suitable for labourers.
Surgical Technique
Four-corner fusion
- Approach. A dorsal longitudinal incision, developing the interval between the 3rd and 4th extensor compartments. Ligate the terminal branch of the posterior interosseous nerve and perform a dorsal capsulotomy.
- Scaphoid excision. Excise the scaphoid completely, taking care to remove every fragment, and preserve the volar radiocarpal ligaments.
- Cartilage preparation. Remove the cartilage from the capitate, lunate, hamate and triquetrum, initially preserving the subchondral bone plate, to create bleeding bone surfaces.
- Bone grafting. Harvest cancellous bone from the distal radius or iliac crest, pack it into the prepared fusion surfaces and fill the scaphoid void.
- Fixation. A circular dorsal plate (most common), spider plate, individual screws or K-wires, with compression across all fusion surfaces.
- Closure. Close the capsule if possible, repair the extensor retinaculum, close the skin and splint in neutral.
The result is a stable construct that preserves the radiolunate articulation.
Proximal row carpectomy
- Approach. The same dorsal approach as for 4CC, which gives good visualisation of the entire proximal row.
- Carpal excision. Excise the scaphoid first (easiest access), then the lunate, then the triquetrum, removing the proximal row completely.
- Cartilage assessment. The critical step: inspect the capitate head and lunate fossa. If the cartilage is damaged, convert to 4CC or consider fusion; if it is intact, proceed.
- Reduction. Let the capitate reduce into the lunate fossa, check for smooth, painless motion and assess stability.
- Closure. Repair the capsule, consider a temporary K-wire if the construct is unstable, and start the early motion protocol.
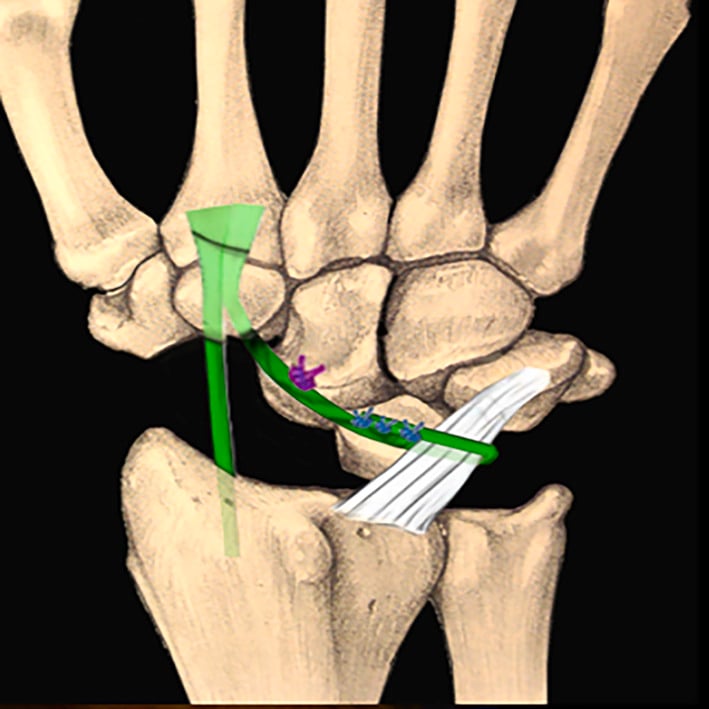
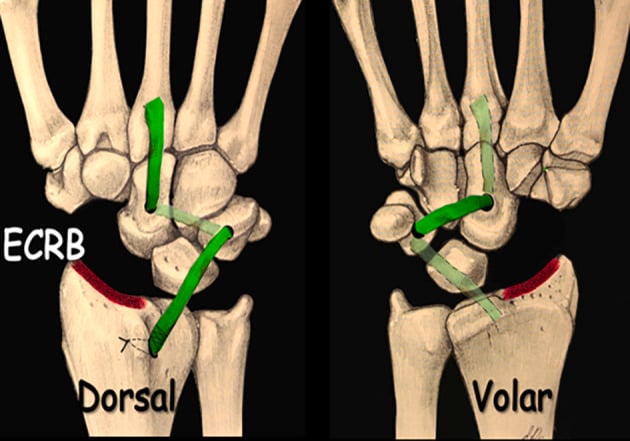
Scaphoidectomy with midcarpal tenodesis
A tendon slip is used in place of a fusion after the scaphoid is removed. The tenodesis substitutes for the excised scaphoid without committing the patient to a fusion; the flexor carpi radialis and extensor carpi radialis brevis variants both aim to hold the capitate in the lunate fossa and prevent ulnar translation once the scaphoid has been removed.
Complications
Four-corner fusion
Nonunion (5-10%) is the most significant complication. Smoking, inadequate fixation and poor bone quality are the risk factors, and it is managed by revision with bone graft and improved fixation. Fixation choice matters: in Vance's series (see the evidence below), first-generation circular dorsal plates had a 26% nonunion rate and a 48% major complication rate, against 6% with traditional wires, staples or screws.
Hardware problems include prominent hardware irritating the extensor tendons, screw loosening and plate failure, and the hardware may need removal after union. A circular plate must sit below the level of the articular surface: if it is proud it impinges on the dorsal rim of the radius, a recognised cause of persistent dorsal pain and hardware removal.
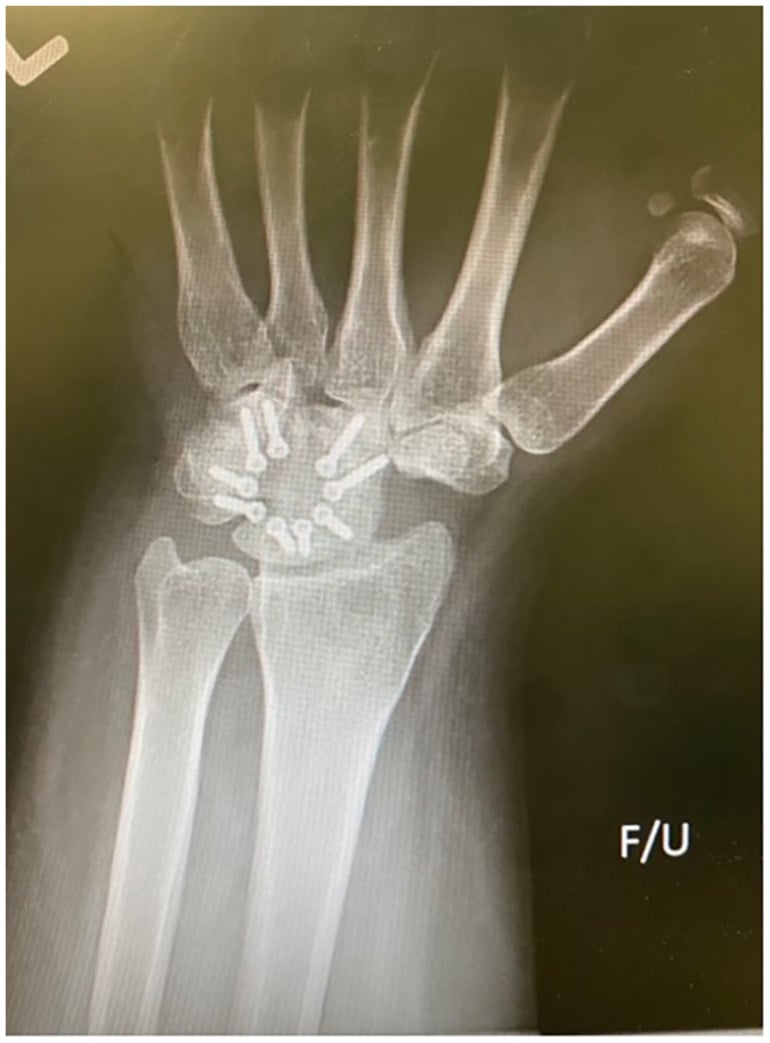
Stiffness. A range of motion less than expected usually follows prolonged immobilisation, and therapy may improve it.
The DRUJ. Pre-existing DRUJ arthritis may become symptomatic; consider a concurrent Darrach or DRUJ fusion.
The preserved joint. The radiolunate joint may develop arthritis in the long term and may require conversion to total wrist fusion. Hardware prominence and progression of the preserved joint are the commonest reasons these wrists come back.
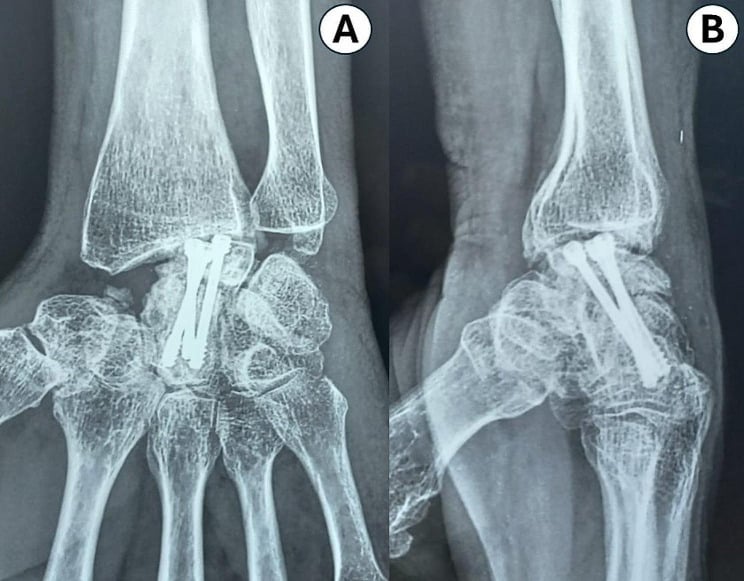
Proximal row carpectomy
Progressive arthritis at the radiocapitate articulation raises concern for long-term durability and may require conversion to fusion. PRC does not "burn bridges": fusion remains available later.
Carpal instability. Capitate subluxation is rare and the construct is usually stable.
Weakness. Some patients are disappointed with their grip strength.
Either operation
- Infection - the standard surgical risk
- Nerve injury - superficial radial nerve, PIN
- Stiffness - expected; counsel patients preoperatively
- Complex regional pain syndrome - rare but devastating
Postoperative Care
After 4CC the wrist is protected until serial radiographs show fusion. After PRC active wrist motion begins from week 2, and recovery is typically faster than after 4CC.
- Four-corner fusion
- Bulky dressing and splint; strict elevation; finger range of motion exercises
- Proximal row carpectomy
- Bulky dressing and splint; elevation; finger motion
- Four-corner fusion
- Short arm cast or removable splint; continue finger motion; no loading
- Proximal row carpectomy
- Begin active wrist ROM; splint for comfort between exercises; no loading
- Four-corner fusion
- Serial radiographs to assess fusion; begin wrist ROM when fusion evident; gradual strengthening
- Proximal row carpectomy
- Progressive strengthening; discontinue splint; gradual return to activities
- Four-corner fusion
- Progressive loading as tolerated; full activities when fully fused (typically 3-4 months); grip strengthening programme
- Proximal row carpectomy
- Full activities as tolerated
Outcomes/Prognosis
Without treatment pain and function decline progressively, grip strength deteriorates, and some wrists eventually reach pancarpal arthritis (the generalised arthritis of Mack's series in the Overview).
After Stage I repair union rates are 70-90% with proper selection. If union is achieved, SNAC progression is prevented and the wrist returns to near-normal function, with good long-term results.
- Pain relief
- 80-90%
- Motion
- 50% of normal (30-40 degrees F/E arc)
- Grip
- 60-80% of normal
- Satisfaction
- 75-85%
- Durability
- Revision rate 5-10% (mostly nonunion)
- Pain relief
- 80-90%
- Motion
- 50% of normal
- Grip
- 60-80% of normal
- Satisfaction
- 75-85%
- Durability
- 10-year survival approximately 80-90% in the two long-term series on this page (Jebson 2003: 90% at mean 13 years; DiDonna 2004: 82% at mean 14 years - every failure was in a patient aged 35 or younger)
- Pain relief
- 90%+
- Motion
- 0 degrees (complete fusion)
- Grip
- Often improves from preoperative
- Satisfaction
- High for appropriate patients
- Durability
- Durable long-term results
Guidelines, Registries & Global Practice
Global Epidemiology
- Scaphoid fracture incidence: A validated Swedish nationwide registry of 34,377 patients reported a true incidence of 22 per 100,000 person-years after correcting a 41% false-positive diagnosis rate (Swärd 2019).
- Nonunion as the substrate for SNAC: In the same registry, nonunion risk was higher in men than women (3% versus 1%), mirroring the male predominance seen in SNAC populations.
- Time course: Mack's natural-history series (1984) remains the reference: radioscaphoid arthritis at a mean of approximately 17 years and pancarpal arthritis at approximately 31 years, with displacement and carpal instability accelerating collapse.
Guidance and Society Positions, Side by Side
There is no high-level prospective randomised trial comparing four-corner fusion (4CC) and proximal row carpectomy (PRC); guidance is therefore consensus- and cohort-based rather than from formal guideline committees. Positions converge internationally:
- Position
- Stage II/III: 4CC or PRC both accepted; PRC favoured in older patients, 4CC where capitate-head or lunate-fossa cartilage is worn
- Evidence level
- Cohort / expert consensus (Level III-IV)
- Position
- Motion-preserving salvage for established midcarpal SNAC; total wrist arthrodesis reserved for pancarpal (Stage IV) or failed salvage
- Evidence level
- Cohort / consensus (Level III-IV)
- Position
- Equivalent functional outcomes for 4CC and PRC; selection by cartilage status, age and demand
- Evidence level
- Systematic review (Level III)
- Position
- Emphasis on preventing SNAC by early fixation/grafting of displaced scaphoid nonunion; low-profile constructs preferred for 4CC
- Evidence level
- Expert consensus (Level V)
Registry and Comparative Evidence
- No dedicated arthroplasty registry captures SNAC salvage, because 4CC and PRC are not implant-arthroplasty procedures (no AOANJRR/NJR/AJRR implant survival data apply). Total wrist arthroplasty for Stage IV is captured in some registries but represents a small, low-demand subset.
- The strongest comparative synthesis is Mulford 2009 (systematic review of 52 studies): comparable grip, pain relief and subjective outcomes; PRC tended to give better motion but more radiographic osteoarthritis (mostly asymptomatic).
- Age is the key practice modifier: DiDonna 2004 showed all PRC failures occurred in patients aged 35 or younger, so many surgeons favour 4CC (or attempted reconstruction) in younger, higher-demand patients.
Practice Variation
- High-resource settings offer the full ladder (vascularised grafting for Stage I, 4CC, PRC, total wrist arthroplasty for selected Stage IV).
- Limited-resource settings more often default to PRC (technically simpler, no implant cost, faster rehabilitation) or total wrist arthrodesis for advanced disease.
- In high-income settings, both 4CC and PRC are routine at hand surgery units; sports- and work-related scaphoid injuries in young men are the dominant feeder population, consistent with the registry epidemiology above.
SNAC and SLAC remain core fellowship topics, examined on pattern recognition, staging and the 4CC-versus-PRC decision.
MCQ Practice Points
Q: What is the relationship between SNAC wrist and SLAC wrist arthritis patterns?
A: They are identical. Both progress in the same sequence: radial styloid to scaphocapitate to capitolunate to pancarpal. The only difference is the underlying etiology (scaphoid nonunion vs scapholunate dissociation).
Q: Which carpal articulation is preserved until late-stage SNAC wrist, and why?
A: The radiolunate joint is preserved until Stage IV because the lunate maintains its normal congruent articulation with the lunate fossa of the radius. There is no abnormal loading across this joint until very late disease.
Q: What is the critical cartilage requirement for proximal row carpectomy?
A: PRC requires intact cartilage on both the capitate head AND the lunate fossa of the radius. If either surface is damaged, PRC is contraindicated - proceed to 4-corner fusion instead.
Q: Why is Stage I SNAC wrist particularly important?
A: Stage I represents the last window for nonunion repair. If the proximal pole is viable and the nonunion is repairable, treatment at Stage I can restore near-normal wrist function and prevent progression. Once Stage II develops, salvage procedures become necessary.
Q: How do outcomes compare between 4-corner fusion and proximal row carpectomy?
A: Similar outcomes for both procedures: 80-90% pain relief, approximately 50% of normal ROM (30-40 degrees flexion-extension arc), 60-80% grip strength, and 75-85% patient satisfaction. The choice is based on surgeon and patient factors, not outcome differences.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 48-year-old mechanic presents with wrist pain. He recalls injuring his wrist playing football 15 years ago but never sought treatment. X-rays show an ununited scaphoid fracture with scaphocapitate joint arthritis but a preserved radiolunate joint.”
Pattern (= SLAC)
- Radial styloid leads to Scaphocapitate leads to Capitolunate leads to Pancarpal
- Radiolunate preserved until Stage IV (rare)
- Few nonunions free of arthritis beyond 10 years if untreated (Mack 1984)
- Etiology differs (nonunion vs SL dissociation) but arthritis pattern identical
- Treatment algorithms same for SNAC and SLAC at each stage
Staging
- Stage I: Radial styloid OA only - repair window
- Stage II: Scaphocapitate OA - salvage indicated
- Stage III: Capitolunate OA added - salvage indicated
- Stage IV: Pancarpal OA (rare) - total fusion
Treatment by Stage
- Stage I: Nonunion repair + styloidectomy (if viable proximal pole)
- Stage II/III: 4CC or PRC (both preserve 50% ROM)
- Stage IV: Total wrist fusion or arthroplasty
- Stage I decision: MRI T1 signal confirms proximal pole viability for repair
- Stage II/III: Choice between 4CC and PRC based on patient factors, not outcomes
4CC vs PRC
- Similar outcomes: 80-90% pain relief, 50% ROM
- 4CC: Better carpal height, 5-10% nonunion risk
- PRC: Simpler, faster rehab, needs intact cartilage
- PRC requirement: Capitate head + lunate fossa cartilage intact
Key Points
- SNAC = SLAC pattern, different etiology
- Stage I = last chance for repair
- Radiolunate preservation enables motion-preserving salvage
- Choose 4CC vs PRC based on patient factors, not outcomes
- Mack 1984: few nonunions free of arthritis beyond 10 years; radioscaphoid OA at mean approximately 17 years
- 4CC/PRC both achieve 80-90% pain relief, 50% ROM preservation
Evidence Base
The Natural History of Scaphoid Non-Union (defining study)
- 47 symptomatic scaphoid non-unions reviewed; degenerative change followed a time-dependent sequence. Lesions confined to the scaphoid had a mean non-union duration of 8.2 years, radioscaphoid arthritis 17.0 years and generalised wrist arthritis 31.6 years.
- Few non-unions remained free of arthritis beyond 10 years; fracture displacement and carpal instability (lunate dorsiflexion of 10 degrees or more) correlated with severity.
Epidemiology of Scaphoid Fractures: Swedish Nationwide Registry
- Nationwide registry of 34,377 patients (2006-2015); validated true scaphoid fracture incidence was 22 per 100,000 person-years after correcting a 41% false-positive rate.
- Men were treated surgically more often than women (6% versus 3%) and had a higher nonunion risk (3% versus 1%).
Proximal Row Carpectomy: Minimum 10-Year Follow-Up
- 20 wrists at mean 13.1-year follow-up; 2 (10%) failed requiring radiocapitate arthrodesis. Survivors retained 63% of contralateral motion and 83% grip strength.
- Radiographic radiocapitate change did not correlate with pain or satisfaction; progressive symptomatic deterioration was not observed.
PRC Long-Term Results: Caution Under Age 35
- 22 wrists, minimum 10-year (mean 14-year) follow-up. 4 failures (18%) required fusion, and ALL occurred in patients aged 35 years or younger at surgery (p = 0.03).
- Wrists that did not fail averaged a 72-degree flexion-extension arc and 91% grip strength; radiocapitate space narrowing did not preclude a good clinical result.
Four-Corner Arthrodesis: Circular Plate vs Traditional Fixation
- 58 four-corner arthrodeses: first-generation circular dorsal plates had a 26% nonunion rate and 48% major complication rate versus 6% with traditional wires/staples/screws.
- Flexion-extension arc was approximately 48-50% of the opposite wrist with either technique; plate patients had lower satisfaction (60% versus 100%).
PRC versus Four-Corner Fusion: Systematic Review (SLAC/SNAC)
- Systematic review of 52 studies of PRC and four-corner fusion for SLAC/SNAC wrists. Grip strength, pain relief and subjective outcomes were similar; PRC tended to give better postoperative range of movement and avoided nonunion, hardware and impingement complications.
- Subsequent radiographic osteoarthritis was significantly more common after PRC, though the majority were asymptomatic at review.