C3-C7 Injuries | SLIC Score Guides Treatment | Anterior vs Posterior Approach
- SLIC score (morphology + DLC + neurology) guides surgical decision-making
- Disco-ligamentous complex (DLC) is the key determinant of instability
- MRI essential to assess DLC integrity and cord compression
- Anterior approach for disc/vertebral body pathology, posterior for facet/lamina
- Combined approach for severe instability or when anterior alone insufficient
- “SLIC 5 or more indicates surgery; a score of exactly 4 is the deliberate grey zone left to surgeon judgement, not an operative indication
- “Indeterminate DLC on MRI = 1 point, disrupted = 2 points
- “Incomplete cord injury with ongoing compression = urgent surgery
- “Facet dislocations often require posterior reduction first
Overview and Epidemiology
Subaxial injuries, those from C3 to C7, account for approximately 50% of all cervical spine fractures. They carry significant morbidity because of the high rate of associated spinal cord injury, present in up to 55%.
Who. The age distribution is bimodal: young patients injured in trauma, and elderly patients who fall. Males outnumber females 3:1, and motor vehicle accidents and falls are the primary mechanisms.
Where. C5-C6 is the most commonly injured level. It is the segment of greatest mobility, and it sits at the transition zone between the more mobile middle cervical spine and the relatively stiffer lower cervical spine; that biomechanical transition creates a stress concentration point.
Mechanism. The loading pattern determines the injury it produces:
- Flexion-compression - burst fractures, teardrop fractures
- Extension-compression - lamina fractures, hangman's variants
- Flexion-distraction - facet dislocations, posterior ligament disruption
- Axial compression - burst fractures
- Lateral flexion - unilateral injuries
Anatomy and Biomechanics
The motion segment. The subaxial spine has consistent anatomy from C3 to C7, and each structure has its own job:
- Vertebral body - the primary load-bearing structure
- Facet joints - a 45-degree orientation that guides motion
- Uncovertebral joints - resist lateral translation
- Intervertebral disc - shock absorption and motion
- Ligamentous structures - stability through the range of motion
The levels differ in motion and clinical significance:
- Primary Motion
- Flexion/extension
- Clinical Significance
- Early degenerative changes
- Primary Motion
- Flexion/extension
- Clinical Significance
- Common stenosis level
- Primary Motion
- Maximum motion; transition zone
- Clinical Significance
- Most common injury level; stress concentration
- Primary Motion
- Cervicothoracic junction
- Clinical Significance
- Mechanically critical
The disco-ligamentous complex. The DLC is the primary determinant of stability. It comprises:
- Intervertebral disc
- Anterior longitudinal ligament (ALL)
- Posterior longitudinal ligament (PLL)
- Ligamentum flavum
- Interspinous and supraspinous ligaments
- Facet capsules
If the DLC is disrupted, the injury is unstable regardless of bony injury severity.
The cord. The cervical cord enlargement runs from C4 to T1, so injury at these levels carries a higher consequence. The space available for the cord is the canal diameter minus the cord diameter: a normal canal is approximately 17mm and the cord approximately 10mm. Stenosis increases the severity of injury for the same energy.
The roots. Cervical nerve roots exit above their numbered vertebra, so the C6 root exits the C5-C6 foramen. C8 is the exception and exits below C7, since there is no C8 vertebra. Root injury is more common than cord injury in unilateral facet injuries, and cord injury is more common with bilateral facet dislocations.
Classification Systems
Subaxial Cervical Spine Injury Classification (SLIC)
The SLIC system is the most widely used classification for guiding treatment decisions. It adds three domains, morphology (0-4), DLC status (0-2) and neurological status (0-4), to a maximum of 10.
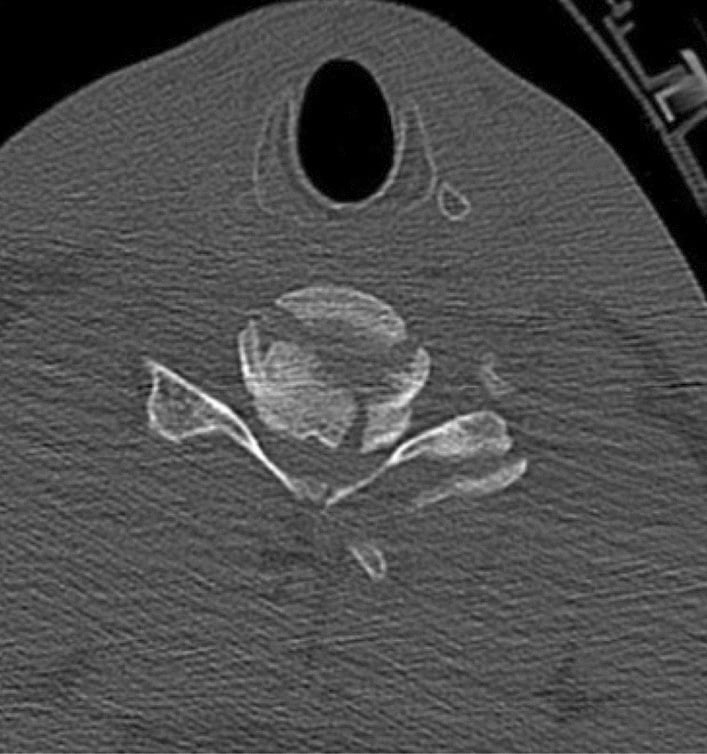
Morphology, 0-4 points.
- Points
- 0
- Description
- Normal alignment and structure
- Points
- 1
- Description
- Loss of anterior height, intact posterior
- Points
- 2
- Description
- Anterior and posterior cortex involved
- Points
- 3
- Description
- Abnormal separation of vertebrae
- Points
- 4
- Description
- Horizontal displacement or rotation
CBDTMorphology Scoring
Hook:C1-B2-D3-T4: Compression 1, Burst 2, Distraction 3, Translation 4.
The DLC, 0-2 points, is scored on MRI.
- Points
- 0
- MRI Findings
- Normal signal, no disruption
- Points
- 1
- MRI Findings
- Isolated interspinous widening, subtle changes
- Points
- 2
- MRI Findings
- High signal in disc, widened facets, ligament rupture
Know its weakness, because it is where the score is decided. In the original validation the interrater ICC was 0.49 for DLC against 0.57 for morphology and 0.87 for neurology. It is the least reliable of the three domains, and the one carrying the 0 / 1 / 2 that most often moves a case across the operative threshold: an indeterminate DLC scored 1 rather than 2 is the difference between a 4 and a 5.
Neurological status, 0-4 points, is 0-3 plus 1 for continuous cord compression with a deficit.
- Points
- 0
- Modifier
- No neurological deficit
- Points
- 1
- Modifier
- Single nerve root deficit
- Points
- 2
- Modifier
- ASIA A
- Points
- 3
- Modifier
- ASIA B, C, or D
- Points
- +1
- Modifier
- Add to the neurological score
- SLIC 0-3: Non-operative
- SLIC 4: Indeterminate (surgeon preference)
- SLIC 5+: Operative treatment recommended
Do not compress that into "4 or more means operate" - it converts the one score the authors left open into a mandate.
Clinical Assessment
History. The questions to ask:
- Mechanism of injury (high vs low energy)
- Time since injury
- Any neurological symptoms (weakness, numbness, bladder/bowel)
- Previous cervical spine problems
- Medical comorbidities affecting the surgical decision
The primary survey. Consider early intubation if unstable, and expect diaphragmatic breathing with a high cord injury. Bradycardia with hypotension is neurogenic shock. Look for associated head, chest and polytrauma injuries.
The spine. Inspect for bruising, deformity and a step-off, and palpate for tenderness and interspinous widening. Do NOT test range of motion if instability is suspected, and log-roll to clear the entire spine.
Neurology. Grade the cord injury on the ASIA Impairment Scale.
- Description
- Complete
- Motor/Sensory
- No motor or sensory below level
- Description
- Sensory incomplete
- Motor/Sensory
- Sensory but no motor below level
- Description
- Motor incomplete
- Motor/Sensory
- Motor below level, less than half key muscles grade 3+
- Description
- Motor incomplete
- Motor/Sensory
- Motor below level, at least half key muscles grade 3+
- Description
- Normal
- Motor/Sensory
- Normal motor and sensory
Complete neurological examination documented at presentation is essential for:
- Baseline for monitoring deterioration
- Surgical decision-making
- Prognostication
- Medicolegal protection
The level of a deficit is read from the sensory landmarks and key muscles:
- Sensory landmark
- Shoulder
- Key muscles
- -
- Sensory landmark
- Lateral arm
- Key muscles
- Deltoid, biceps
- Sensory landmark
- Thumb
- Key muscles
- Wrist extensors, brachioradialis
- Sensory landmark
- Middle finger
- Key muscles
- Triceps, wrist flexors
- Sensory landmark
- Little finger
- Key muscles
- Finger flexors
- Sensory landmark
- Medial arm
- Key muscles
- Finger abduction (intrinsics)
Differential diagnosis. The key reasoning step is separating a genuinely unstable subaxial fracture (operative threshold) from mimics that change urgency or treatment.
- Distinguishing feature
- Cortical break, malalignment, DLC disruption on MRI
- Key discriminator
- CT fracture + SLIC/AO Spine pattern; MRI confirms DLC
- Distinguishing feature
- Neurological deficit with normal CT and X-ray
- Key discriminator
- MRI cord signal change without bony injury
- Distinguishing feature
- Trivial mechanism, rigid spine, transverse 'carrot-stick' fracture
- Key discriminator
- Whole-spine CT; treat as unstable even if subtle
- Distinguishing feature
- Hands worse than legs, hyperextension, frequently no fracture
- Key discriminator
- MRI cord oedema, pre-existing canal stenosis
- Distinguishing feature
- Normal CT but interspinous widening / facet fluid
- Key discriminator
- MRI STIR high signal; flexion-extension only when safe
- Distinguishing feature
- Chronic radiculopathy, no acute trauma
- Key discriminator
- Osteophytes, disc desiccation, no acute oedema
- Distinguishing feature
- Posterior circulation symptoms, transverse foramen fracture
- Key discriminator
- CT angiography
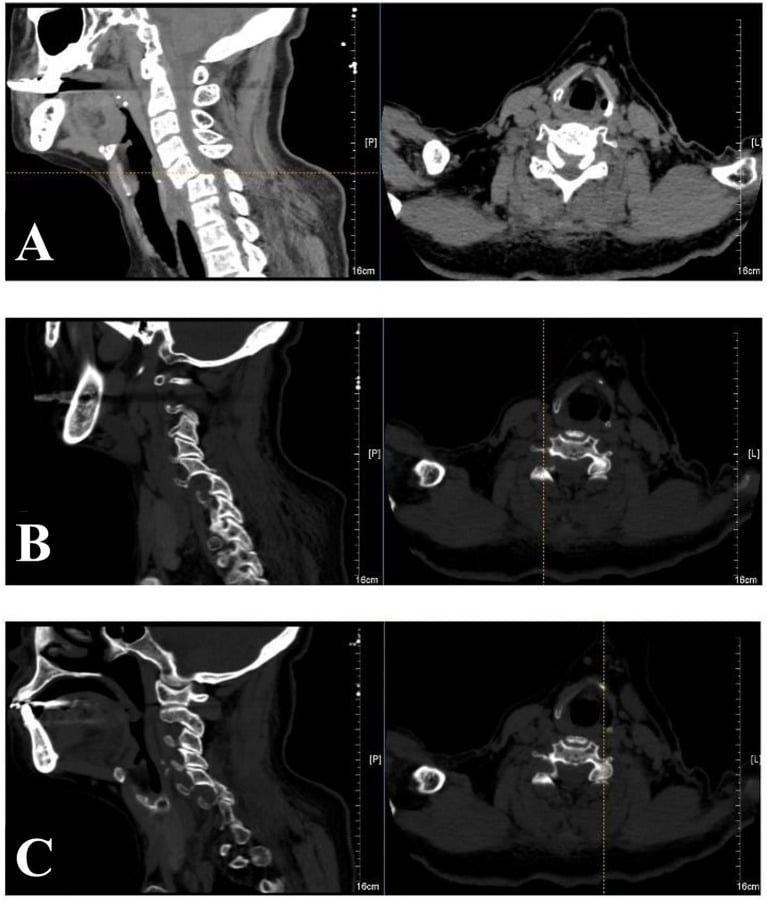
A subaxial fracture in an ankylosed spine (ankylosing spondylitis or DISH) is the highest-stakes pattern, and it is repeatedly examined because it is so often missed and mismanaged.
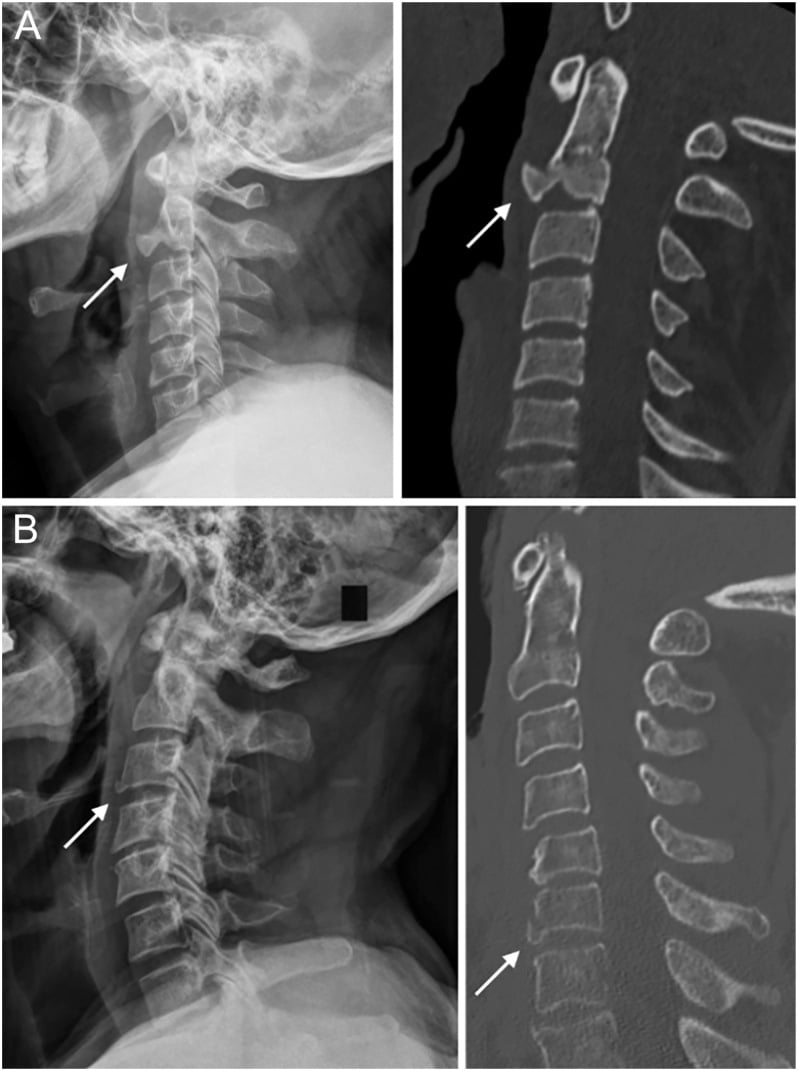
The pattern. The fused, brittle spine behaves like a long bone. Even a trivial low-energy fall produces a transverse, highly unstable three-column "carrot-stick" fracture, often through a fused disc space, with long lever arms above and below.
Why it is missed. The fracture line is subtle against the abnormal fused, ossified spine, plain films are unreliable, and the patient often has a pre-existing kyphotic deformity. Whole-spine CT, with a low threshold for MRI, is therefore mandatory in any ankylosed patient with neck pain after even minor trauma. There is a high rate of epidural haematoma and delayed neurological deterioration.
The positioning trap. Never force the neck into "neutral" or extension: support the patient in their fixed pre-injury deformity with reverse Trendelenburg and padding. Forcing alignment can complete the injury and cause catastrophic cord injury.
Treatment. These fractures are unstable and treated surgically even when subtle, typically with long-segment posterior fixation (often multiple levels above and below) or a combined construct; short anterior-only fixation fails. Mortality and complication rates are high.
Investigations
Imaging Protocol
First-line imaging for trauma. Thin-cut CT from occiput to T1. Sagittal and coronal reconstructions essential. Sensitivity more than 99% for fractures.
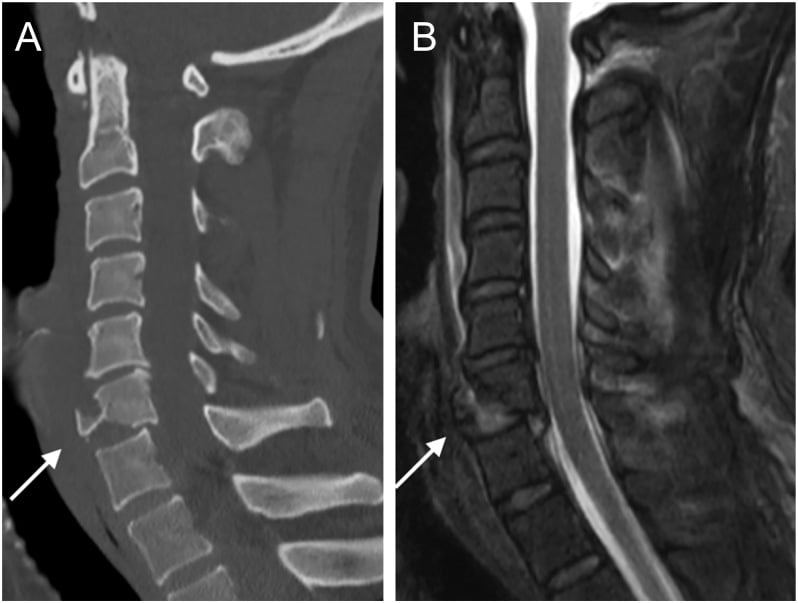
Essential for DLC assessment. Shows disc herniation, ligament rupture, cord contusion, epidural haematoma. STIR sequences best for ligament injury.
Extend imaging to assess cervicothoracic junction. Often obscured on plain films.
Thin-cut CT at 3-6 months to assess fusion. Earlier if concerns about hardware.
Reading the CT. Document five features:
- Vertebral body morphology (compression, burst, translation)
- Facet alignment (subluxation, perched, locked)
- Canal compromise (percentage)
- Fragment retropulsion
- Spinous process widening, which suggests posterior ligament injury
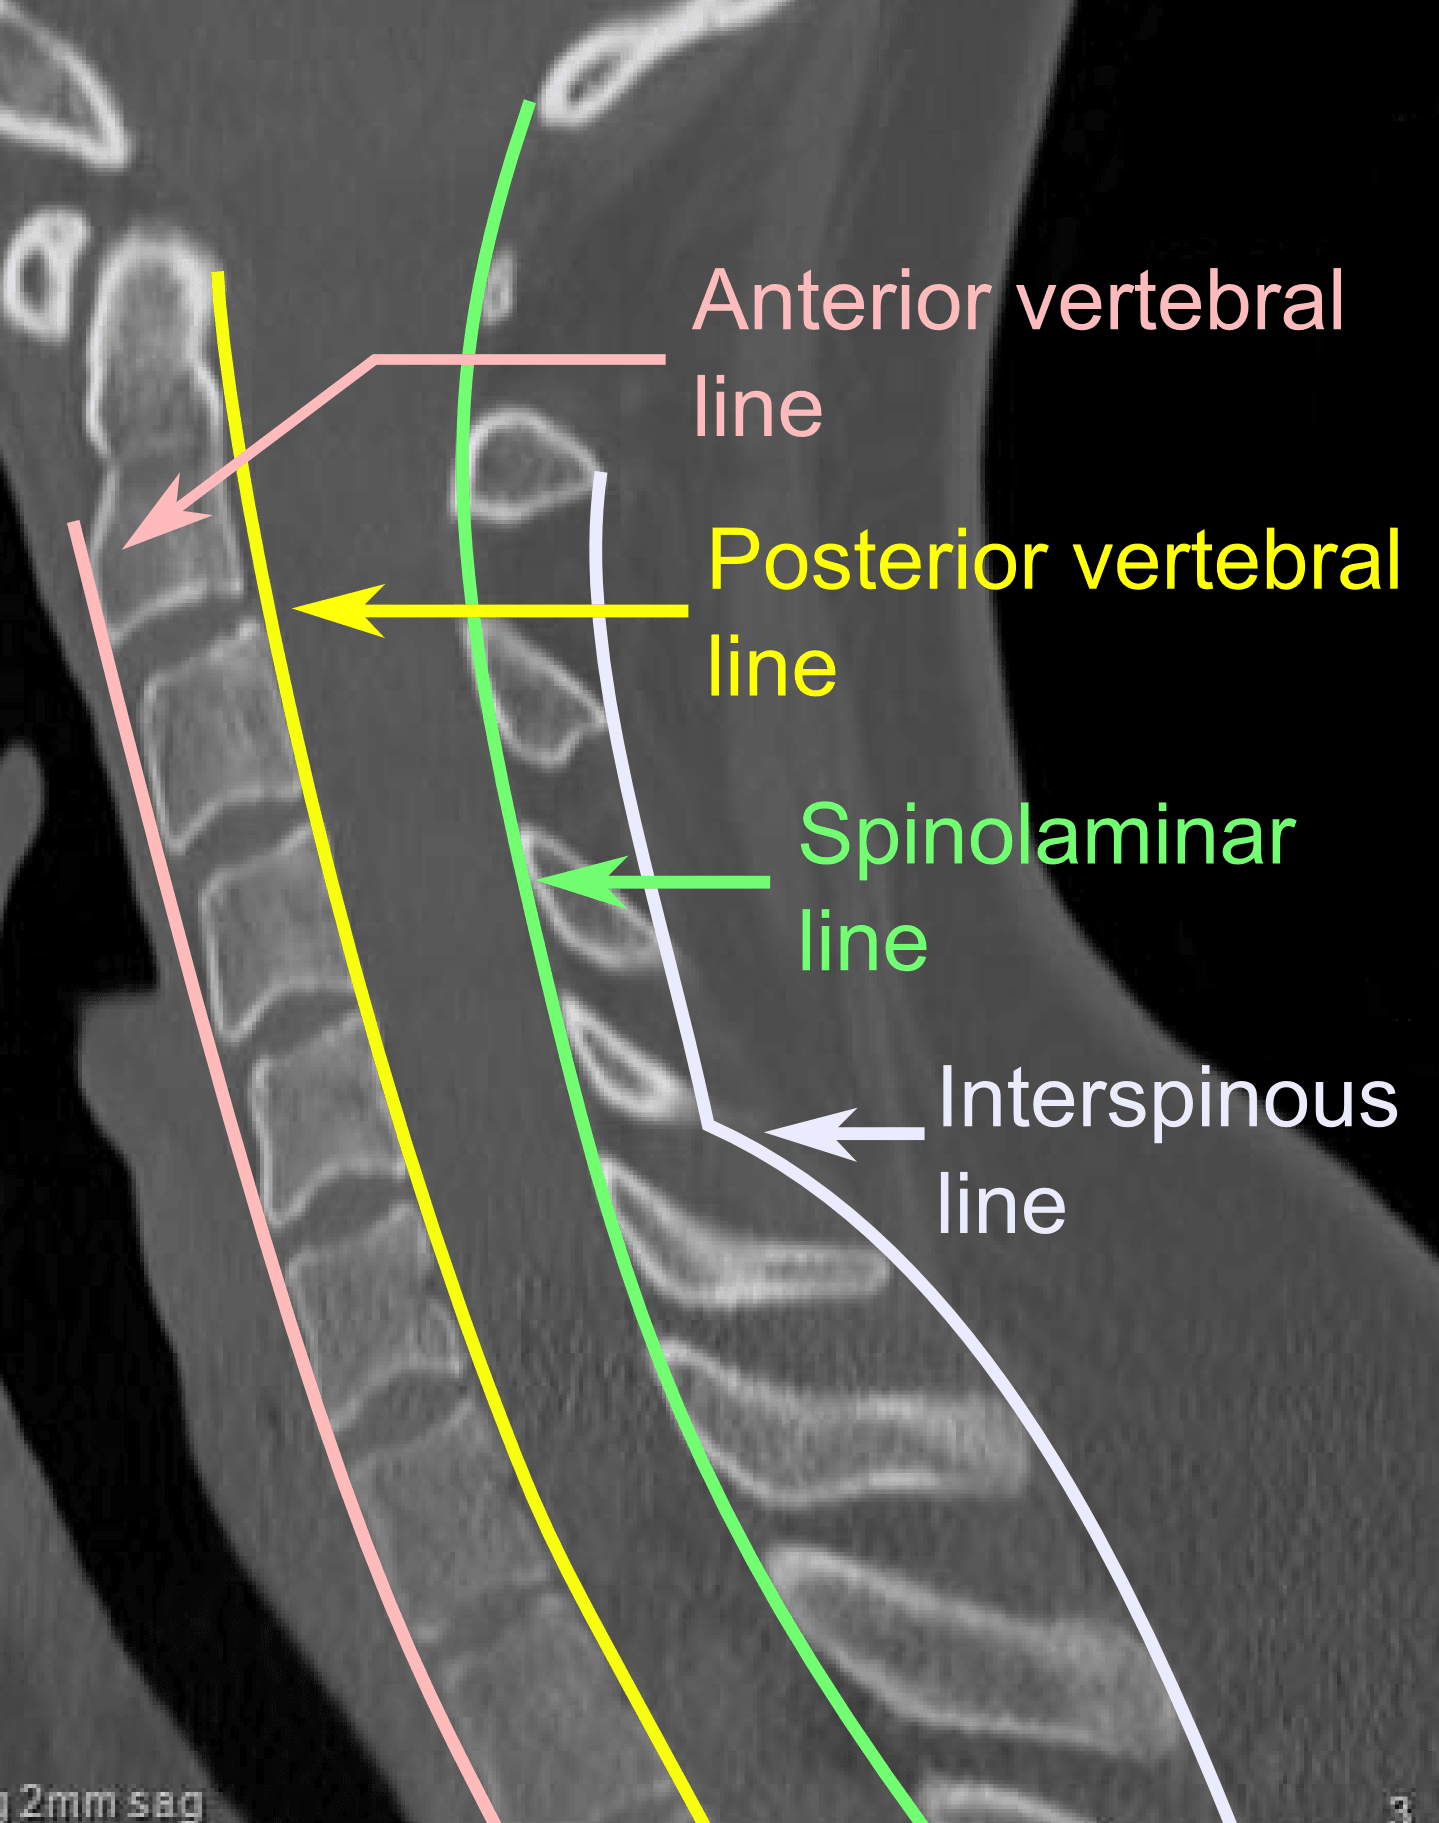
MRI is mandatory for SLIC scoring because DLC status cannot be determined from CT alone. Indeterminate or disrupted DLC significantly changes the score and treatment recommendation.
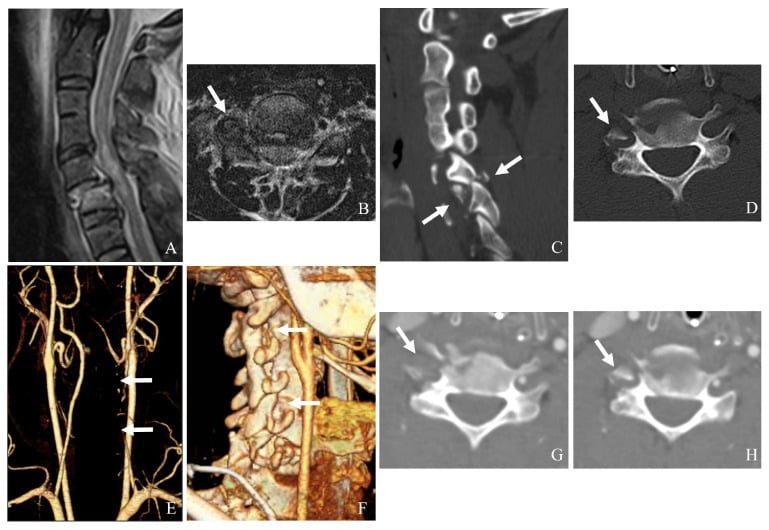
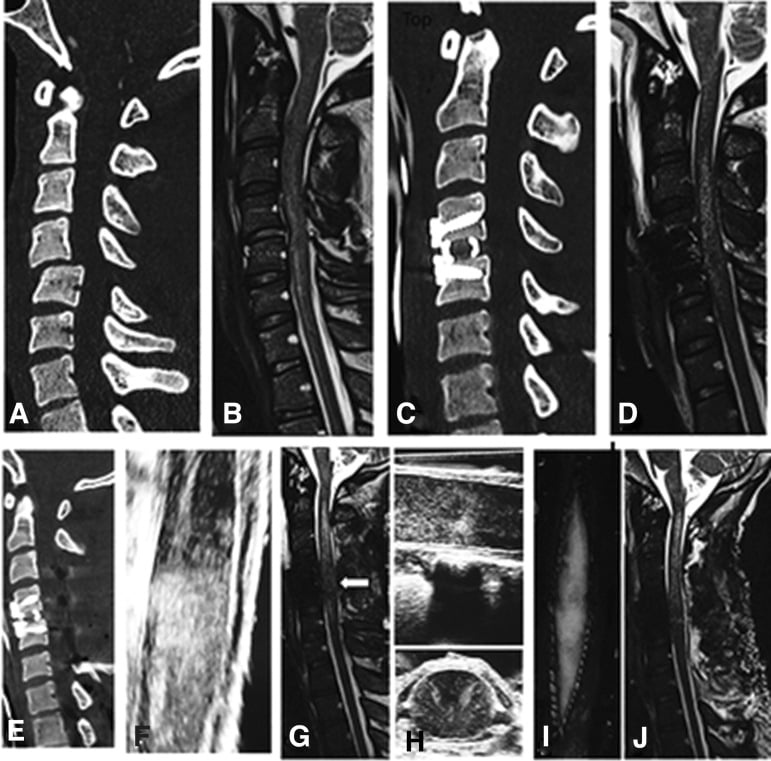
Reading the MRI. What each finding means:
- T2/STIR high signal in the disc - disruption
- Widened interspinous space with oedema - posterior ligament injury
- Facet fluid or widening - capsule disruption
- Cord signal change - contusion or haemorrhage, a poor prognostic sign
- Epidural haematoma - may require urgent decompression
Management Algorithm
All patients with suspected cervical spine injury require:
- Immobilisation with rigid collar
- Log-roll precautions
- Neurological documentation
- MAP optimisation (target 85-90mmHg for incomplete SCI)
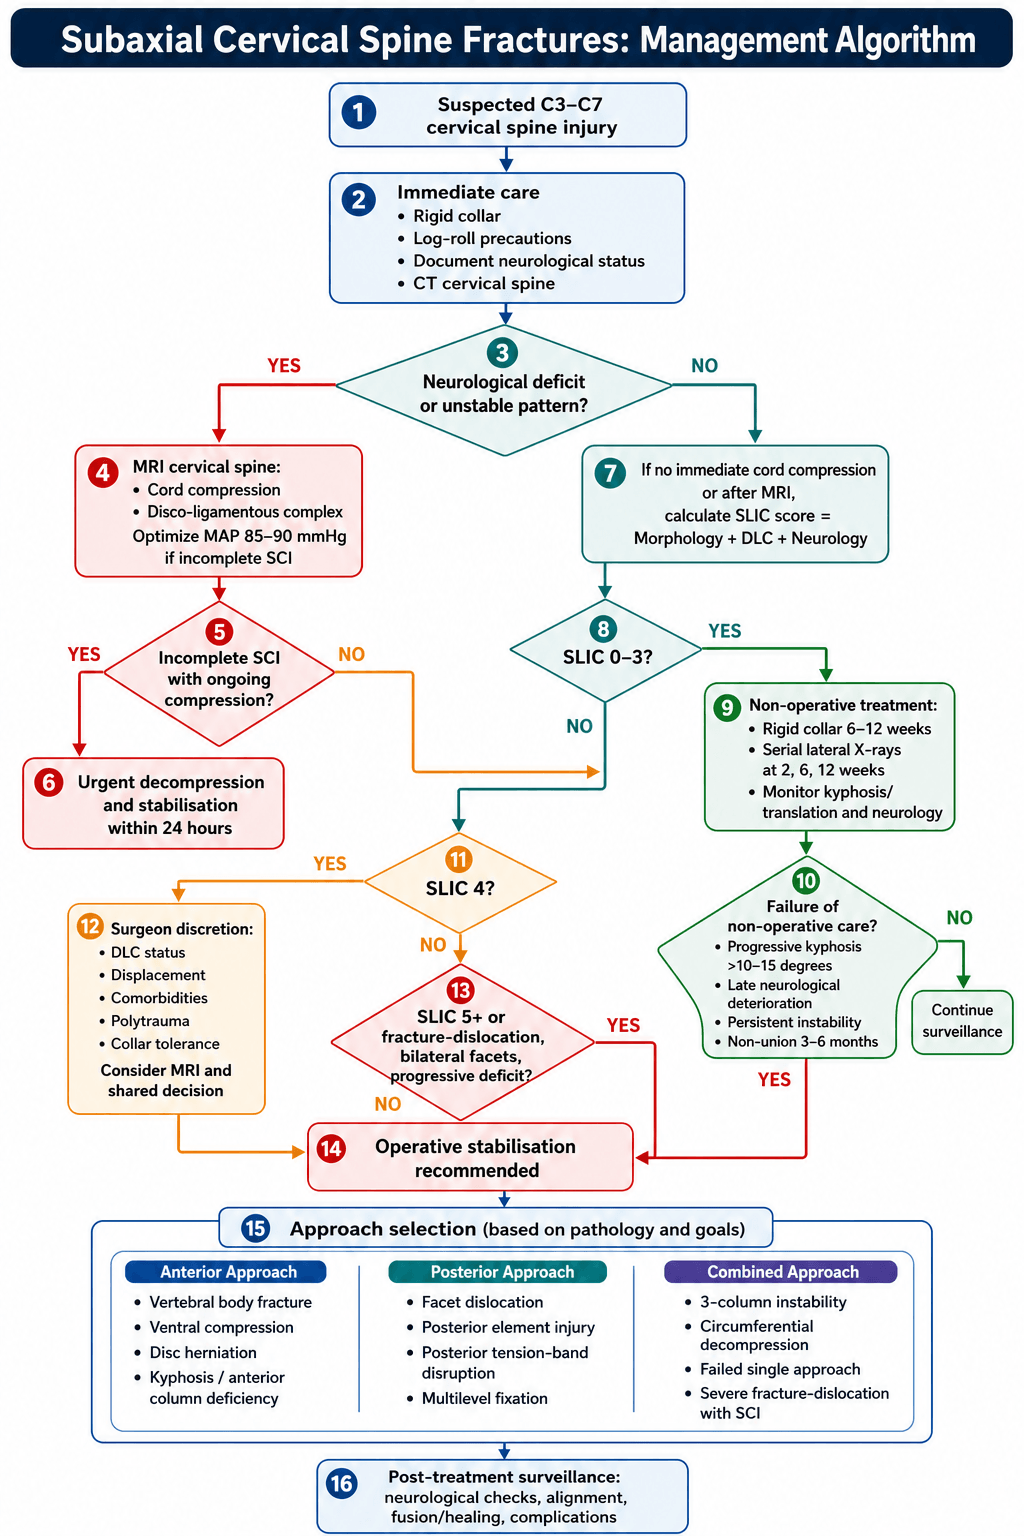
The decision. Once the patient is safe, the SLIC score sets the threshold and the patterns fall into four bands:
- Injury Pattern
- Compression fracture, intact DLC
- Treatment
- Rigid collar 6-12 weeks
- Key Pearl
- Non-op if DLC intact - most common scenario
- Injury Pattern
- Indeterminate stability
- Treatment
- Surgeon preference
- Key Pearl
- MRI critical - DLC status determines treatment
- Injury Pattern
- Burst + DLC disruption + neurological deficit
- Treatment
- Surgical stabilisation
- Key Pearl
- Consider anterior corpectomy with cage
- Injury Pattern
- Fracture-dislocation + incomplete SCI
- Treatment
- Urgent surgical decompression
- Key Pearl
- Within 24h for incomplete SCI with compression
Indications for Non-Operative Treatment
Who. SLIC 0-3 with an intact disco-ligamentous complex, no neurological deficit, minimal displacement and a stable fracture pattern.
The protocol. A hard collar (Miami J or Philadelphia) for 6-12 weeks, with serial lateral X-rays at 2, 6 and 12 weeks to look for progressive kyphosis or translation. Range-of-motion exercises begin once the collar is removed, with physiotherapy for strengthening.
Watching for failure. New neurological symptoms call for an urgent MRI, and failure to heal at 12 weeks means considering surgery.
Conversion to surgery indicated for:
- Progressive kyphosis more than 10-15 degrees
- Late neurological deterioration
- Persistent instability on flexion-extension films
- Non-union at 3-6 months
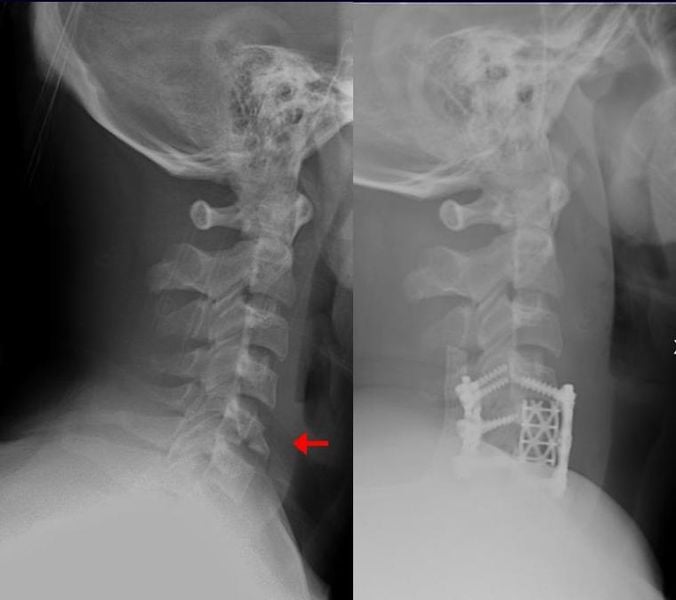
Central Cord Syndrome
Central cord syndrome is the commonest incomplete cord syndrome and a quintessentially subaxial problem. It is distinct from the unstable-fracture algorithm above, and it is examined as the "old person who fell and can't use their hands".
Who. Typically an older patient with a spondylotic, stenotic cervical spine who sustains a hyperextension injury, often a fall onto the face or forehead, frequently with no fracture or only minor injury. The cord is pinched between anterior osteophytes or disc and the inbuckling ligamentum flavum posteriorly.
The deficit. The upper limbs are affected more than the lower limbs, the hands worst of all, with variable sensory loss and sometimes bladder dysfunction, because the centrally located cervical (hand) motor fibres are preferentially injured.
Diagnosis. MRI shows central cord oedema or haemorrhage on a background of stenosis, usually without instability on CT, in contrast with the SLIC fracture pathway.
Management. Many patients recover substantially with supportive care (MAP support, and no fracture to fix), so treatment was historically non-operative. The modern trend favours decompression, often subacute or early, for significant ongoing cord compression, especially if recovery plateaus; timing is debated and individualised. Recovery follows a typical pattern: the legs recover before the hands, with hand intrinsic function the last and least to return.
Surgical Technique
Pre-operative Planning
Consent. Cover neurological worsening, infection (superficial 2-3%, deep less than 1%), dysphagia and recurrent laryngeal nerve injury after anterior surgery, hardware failure, and adjacent segment disease as a long-term risk; the rates are in the Complications table.
Equipment. Check before starting:
- Imaging - fluoroscopy or navigation
- Implants - plates and screws (anterior), lateral mass screws (posterior)
- Cage or graft - structural allograft or cage for corpectomy
- Neuromonitoring - SSEPs and MEPs
- Cell saver - for multilevel procedures
Anterior Cervical Approach (Smith-Robinson)
Step-by-Step Technique
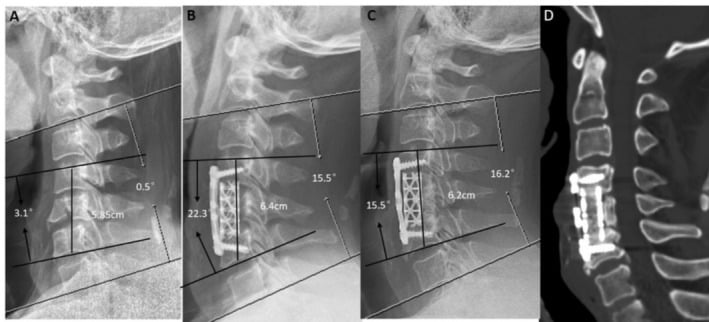
Supine on radiolucent table. Head in neutral with gentle traction (Gardner-Wells if needed). Shoulder roll to extend neck. Arms tucked at sides.
Transverse incision at appropriate level (C5-6 at thyroid cartilage). Develop plane between carotid sheath laterally and trachea/oesophagus medially. Retract longus colli muscles.
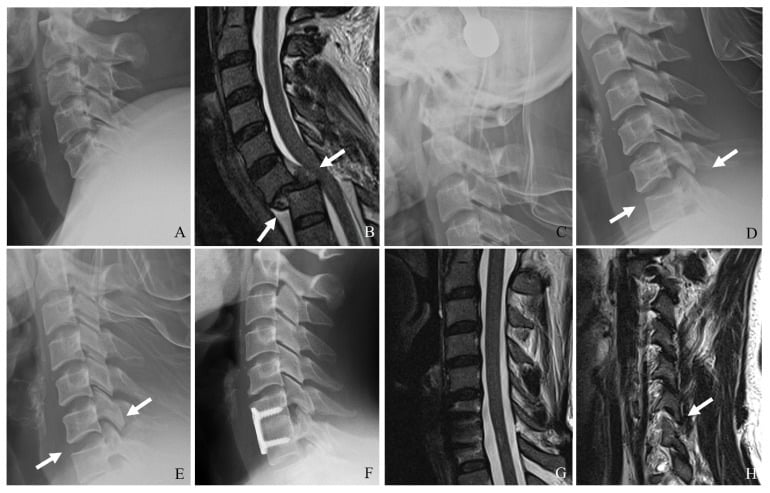
Identify level with fluoroscopy. Mark with needle if uncertain. Expose vertebral bodies and discs. Preserve anterior longitudinal ligament if possible.
Discectomy or corpectomy as indicated. Remove PLL to decompress canal. Visualise dura. Remove retropulsed fragments.
Cage or graft to restore height. Size appropriately (1-2mm larger). Position centrally. Confirm alignment on fluoroscopy.
Anterior plate spanning construct. Bicortical screws (4-5mm engaging posterior cortex). Confirm position with lateral fluoroscopy.
Oesophageal perforation is rare but devastating. The risk rises with previous anterior surgery, prominent osteophytes, excessive retraction and a long operative time. Protect the oesophagus with gentle retractor placement and intermittent release.
Intraoperative Troubleshooting
- Cause
- Locked facet, interposed fragment
- Solution
- Increase distraction, open facet capsule, remove fragment
- Cause
- Screw placed too laterally or angled too medially, dissection too lateral
- Solution
- Pack with haemostatic agent, complete surgery, do NOT attempt repair
- Cause
- Dural tear during decompression
- Solution
- Primary repair if possible, dural sealant, lumbar drain
- Cause
- Cord compression, hypotension, positioning
- Solution
- Stop, check BP, optimise positioning, consider wake-up test
Complications
- Incidence
- 1-3%
- Prevention/Management
- Careful reduction, neuromonitoring, appropriate timing
- Incidence
- Up to 50% early
- Prevention/Management
- Gentle retraction, minimise operative time
- Incidence
- 2-5%
- Prevention/Management
- Left-sided approach traditionally preferred; careful retraction
- Incidence
- 5-10%
- Prevention/Management
- Appropriate construct length, bone quality assessment
- Incidence
- 5-10%
- Prevention/Management
- Adequate graft, smoking cessation, consider BMP
- Incidence
- Up to 25% at 10 years
- Prevention/Management
- Limit fusion length, preserve motion where possible
- Incidence
- 1-3%
- Prevention/Management
- Prophylactic antibiotics, meticulous technique
- Incidence
- Less than 1%
- Prevention/Management
- Preoperative CT angiography, careful screw placement
Neurological deterioration is the most feared complication, and the risk is higher with incomplete SCI. Beyond the measures in the table, avoid over-distraction.
Dysphagia after anterior surgery usually resolves within weeks but persists in 5-10%. Consider thin liquids initially and a speech pathology review.
Left-sided approach is traditionally preferred because the recurrent laryngeal nerve has a more consistent course in the tracheo-oesophageal groove. On the right, it loops around the subclavian artery and has a variable course. However, right-sided revision is preferred if previous left approach.
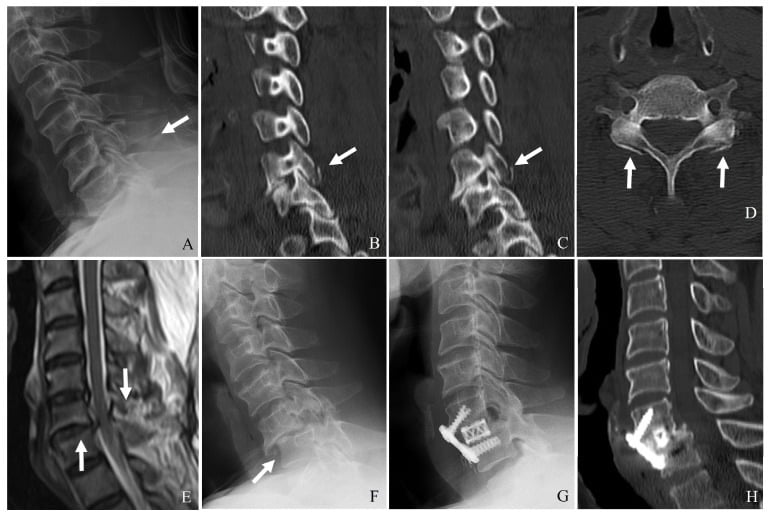
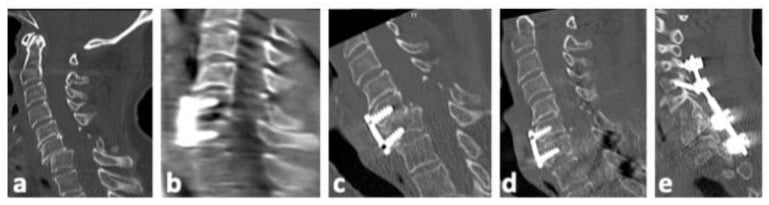
Delayed instability. A small fracture does not make a tension-band injury stable, and a disco-ligamentous injury that is underestimated can declare itself later, even in a brace.
Postoperative Care and Rehabilitation
Rehabilitation Timeline
- ICU monitoring if SCI or high-risk
- Neurological checks every 4 hours
- DVT prophylaxis
- Early mobilisation assessment
- Speech pathology if anterior (nil by mouth initially)
- Transition to ward if stable
- Begin mobilisation with collar
- Physiotherapy assessment
- Diet advancement (anterior)
- Wound check
- Wound review at 2 weeks
- Continue hard collar
- X-ray at 6 weeks
- Progressive mobilisation
- SCI rehabilitation if indicated
- X-ray assessment of fusion
- Consider collar weaning if stable
- Increase activity
- Physio for strengthening
- CT to confirm fusion
- Collar removal if fused
- Return to work assessment
- Long-term follow-up for adjacent segment disease
The collar. Most surgeons use a hard collar for 6-12 weeks after surgery. It comes off earlier with rigid internal fixation and good bone quality, and stays on longer for osteoporosis, a multilevel construct or concern about stability.
Outcomes and Prognosis
Neurological recovery. A complete injury (ASIA A) carries minimal expected recovery, and care focuses on rehabilitation. An incomplete injury has significant potential for recovery, especially with early decompression, and a root injury usually recovers well over 6-12 months.
What drives outcome. Outcome depends on the severity of the initial injury, the timing of decompression for incomplete SCI, the quality of reduction and stabilisation, patient factors (age, comorbidities, smoking) and compliance with rehabilitation.
Early surgery. Early surgery (less than 24 hours) for incomplete SCI results in a shorter ICU stay and faster rehabilitation.
The long term. Hardware removal is rarely needed unless symptomatic, surveillance for late instability is ongoing, and return to contact sports is controversial.
Guidelines, Registries & Global Practice
Global epidemiology. Subaxial injuries account for approximately half of cervical spine fractures, with C5-C6 the most frequently injured level (the mobile-to-stiff transition zone). Across resource settings the demographic is consistent: predominantly young males injured by road traffic accidents, with falls dominating in the elderly. In a meta-analysis of 11,639 patients across 16 African countries, road traffic accidents caused 49.5% of traumatic spine injuries, the cervical spine was the most common level (51.6%), patients were 81% male with a mean age of 34.5 years, and surgery was performed in only 31.9% versus a majority managed conservatively, with 12.1% mortality (Darko et al, J Neurosurg Spine 2025, DOI). This contrasts with high-income systems where most unstable injuries are operated early.
- Region
- International
- Core recommendation
- Decompression within 24h for any-level acute SCI; no recommendation for ultra-early (<12h)
- Evidence basis
- GRADE guideline; RR 2.76 for 2-grade AIS gain at 6 months (PMID 38526922)
- Region
- International
- Core recommendation
- Operate if score 5 or more; 4 indeterminate; 0-3 non-operative
- Evidence basis
- Consensus + validation, 93.3% treatment-algorithm agreement (PMID 17906580)
- Region
- International
- Core recommendation
- Morphology A/B/C + facet (F) + neurology (N) + modifiers (M) for communication and research
- Evidence basis
- Consensus, substantial reliability kappa 0.64-0.75 (PMID 25716661)
- Region
- USA
- Core recommendation
- Closed reduction acceptable in awake, examinable patients; MRI before reduction in obtunded patients
- Evidence basis
- Systematic review, mostly low-level evidence
- Region
- UK
- Core recommendation
- CT first line for adults with suspected significant cervical injury; MRI if neurology or ligamentous concern
- Evidence basis
- Guideline development group review
Registry & systematic-review evidence. Cervical trauma is not captured by arthroplasty joint registries; the comparative evidence base is national trauma databases and pooled reviews rather than a single implant registry. Pooled data in rigid (ankylosing) cervical spines - a high-risk subaxial subgroup - confirm the C6-C7 / C5-C6 predominance and show combined anterior-posterior constructs carry the lowest reoperation rate (1.7%) versus anterior-only fixation (11.1%) (Musa et al, Neurosurg Rev 2025, DOI).
- Variation
- Awake closed reduction (some N. American/European units) vs MRI-first then open reduction
- Driver
- Concern over traumatic disc herniation; obtunded vs examinable patient
- Variation
- Largely abandoned in UK/Australasia; occasional optional use within 8h elsewhere
- Driver
- Net harm signal; weak guideline support
- Variation
- Within 24h standard in high-income systems; often delayed in limited-resource settings
- Driver
- Theatre access, transfer distance, surgical capacity
- Variation
- MAP 85-90 mmHg for ~7 days widely used; duration and target debated
- Driver
- Low-level supportive evidence only
- Baseline neurological examination documented before any intervention or transfer (ASIA/AIS grade, single root vs cord)
- SLIC or AO Spine classification and MRI DLC status recorded with the management rationale and timing decision
- Informed consent covering neurological risk, approach-specific complications and possible revision
- Transfer: notify the receiving spinal unit early, maintain MAP 85-90 mmHg, and avoid secondary insults (hypoxia, hypotension) en route
- Common pitfalls: delayed diagnosis, missed injury on plain films, and neurological deterioration during reduction or transfer
MCQ Practice Points
Q: A patient has a C6 burst fracture (CT), high signal in disc on MRI, and no neurological deficit. What is the SLIC score? A: Morphology (burst) = 2 + DLC (disrupted) = 2 + Neurology (intact) = 0 = SLIC 4 (indeterminate - surgeon discretion)
Q: Which MRI finding indicates disrupted disco-ligamentous complex? A: High signal in disc, widened interspinous space with edema, facet widening with fluid. All three suggest DLC disruption = 2 points on SLIC.
Q: What is the preferred approach for a C5 burst fracture with retropulsed fragment causing cord compression? A: Anterior corpectomy - allows direct decompression of ventral canal compression and restoration of anterior column height.
Q: What does STASCIS show about timing of surgery for incomplete SCI? A: Surgery within 24 hours results in 19.8% improving at least 2 ASIA grades vs 8.8% for late surgery.
Q: What is the trajectory for lateral mass screws in the subaxial cervical spine? A: Entry 1mm medial and caudal to center of lateral mass. Trajectory 30 degrees lateral and 15-20 degrees cephalad (Magerl technique).
Q: A C5-6 disc herniation will compress which nerve root? A: C6 nerve root - cervical nerve roots exit above their numbered vertebra (C6 root exits C5-6 foramen).
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 35-year-old motorcyclist presents after an MVA. CT shows a C5 burst fracture with 50% canal compromise. He has weakness in his right deltoid (4/5) but otherwise intact neurology. MRI shows high signal in the C5-6 disc and widened interspinous space at C5-6. What is your assessment and management?”
“Walk me through your approach selection for a C6-7 fracture-dislocation with bilateral facet dislocation and an associated C6-7 disc herniation causing cord compression. The patient has ASIA C incomplete SCI.”
“You have performed an anterior cervical discectomy and fusion at C5-6 for a trauma patient. Post-operatively, he develops increasing stridor and respiratory distress 6 hours after surgery. How do you manage this?”
SLIC Classification
- Morphology: Compression=1, Burst=2, Distraction=3, Translation=4
- DLC: Intact=0, Indeterminate=1, Disrupted=2
- Neurology: Intact=0, Root=1, Complete SCI=2, Incomplete=3, +1 if ongoing compression
- SLIC 0-3=non-op, 4=indeterminate, 5+=surgical
Key Anatomy
- C5-C6 most common injury level
- DLC = disc + ALL/PLL + posterior ligaments + facet capsules
- Cervical roots exit ABOVE numbered vertebra (C6 at C5-6)
- Vertebral artery at risk with screw placed too laterally or angled too medially
Approach Selection
- Anterior: burst, disc, ventral compression, kyphosis
- Posterior: facet injury, posterior ligaments, multilevel
- Combined: severe instability, 3-column injury
- Facet dislocation + disc herniation: anterior discectomy BEFORE reduction, then posterior fixation
Surgical Pearls
- Lateral mass screws: 1mm medial/caudal, 30deg lateral, 15-20deg cephalad
- Neuromonitoring essential for reduction
- Left approach traditionally preferred (more consistent RLN course); right for revision
- Consider combined if DLC disrupted with corpectomy
Complications
- Dysphagia 50% early, 5-10% persistent
- RLN injury 2-5%
- Hardware failure 5-10%
- Adjacent segment disease 25% at 10 years
Evidence Base
STASCIS: Surgical Timing in Acute Spinal Cord Injury Study
- Multicentre prospective cohort study of 313 adults with acute cervical SCI
- Early surgery (less than 24h, mean 14.2h) vs late (24h or more, mean 48.3h)
- Early surgery: 19.8% improved at least 2 ASIA grades vs 8.8% (OR 2.57, 95% CI 1.11-5.97)
- Adjusted odds of 2-grade AIS improvement 2.8x higher with early surgery; no increase in complications
SLIC: The Subaxial Cervical Spine Injury Classification System
- Derived by the Spine Trauma Study Group from literature review and expert consensus, then tested by 20 surgeons on 11 cases
- Three weighted domains: morphology, disco-ligamentous complex (DLC) and neurological status, summed to a severity score
- Interrater ICC: morphology 0.57, DLC 0.49, neurology 0.87; raters agreed with the algorithm's treatment recommendation in 93.3% of cases
- Reliability compared favourably with the Harris and Allen-Ferguson systems
AO Spine Subaxial Cervical Spine Injury Classification System
- Morphology-based system mirroring the thoracolumbar AO scheme: A (compression), B (tension band) and C (translation), plus facet (F) subtypes
- Adds neurological status (N0-Nx) and case-specific modifiers (M1-M4)
- Intraobserver reliability kappa 0.75, interobserver kappa 0.64 (substantial) in the validation exercise
- Developed by international consensus for both clinical and research communication
AO Spine / GSJ Updated Clinical Practice Guideline: Role and Timing of Decompressive Surgery in Acute SCI
- International multidisciplinary GRADE guideline updating the 2017 recommendations
- Early surgery (24h or less) recommended as the preferred option for adult acute SCI regardless of level
- Patients 2.76x more likely to gain at least 2 AIS grades at 6 months (RR 2.76, 95% CI 1.60-4.98) and 1.95x at 12 months
- Mean additional 4.50-point ASIA Motor Score gain; no recommendation for ultra-early (<12h) surgery on current evidence
Approach Selection in Rigid (Ankylosing) Cervical Spine Fracture: Systematic Review and Meta-analysis
- 66 studies, 1972 patients with cervical fracture in ankylosing spondylitis (a high-risk subaxial subgroup)
- Most fractures at C6-C7 (36.7%) and C5-C6 (27.7%), echoing the subaxial transition-zone pattern
- Posterior fusion most utilised (40.0%); combined anterior-posterior fusion had the lowest reoperation rate (1.7%) vs anterior alone (11.1%)
- Good neurological outcome in 63.4%; overall mortality 2.9%
Global Burden of Traumatic Spine Injury: Systematic Review and Meta-analysis (Africa)
- 105 studies, 11,639 patients across 16 African countries - illustrating practice in limited-resource settings
- Road traffic accidents the leading mechanism (49.5%); cervical the most common level (51.6%); 81% male, mean age 34.5 years
- Mean time injury-to-presentation 60.8 hours and mean 272.6 km to a facility - major access barriers
- Only 31.9% underwent surgery (vs majority conservative); mortality 12.1%, reflecting the high-income vs LMIC outcome gap