Flexion (Burst) vs Extension (Avulsion) | SLIC Classification | Anterior Corpectomy | Spinal Cord Injury
- Two Types: Flexion Teardrop (Unstable, Burst) vs Extension Teardrop (Usually Stable, Avulsion).
- Flexion Teardrop: Catastrophic injury. Kyphosis, retropulsed fragment, ALL ligaments disrupted. Quadriplegia common.
- Extension Teardrop: Elderly/Osteoporotic. Avulsion of anteroinferior vertebral body by ALL. Usually stable.
- Imaging: CT to assess fragment and canal. MRI for discs/ligaments/cord.
- Treatment: Flexion teardrop needs surgical stabilization. Extension teardrop often non-op.
- “The 'Teardrop' fragment is misleading - Flexion type is a BURST injury, not just an avulsion.
- “Flexion Teardrop has ALL THREE column disruption (Unstable).
- “Extension Teardrop is an avulsion at the ALL attachment (Stable unless severe).
- “Check for Sagittal Vertebral Body Fracture (Flexion Teardrop splits the body).
Overview and Epidemiology
A teardrop fracture is a cervical spine injury with a triangular fragment from the anteroinferior corner of the vertebral body. The name covers two distinct injuries with opposite stability profiles, and the fragment looks similar in both. Confusing them is the classic error: the flexion teardrop is a catastrophic three-column injury that often causes quadriplegia, while the extension teardrop is usually stable with an excellent prognosis.
The flexion teardrop. An unstable burst injury of young adults in high-energy trauma, from diving, motor vehicle collisions and sports, and predominantly an injury of young males. It carries a high rate of quadriplegia, often as an anterior cord syndrome or a complete injury, and a poor prognosis. It requires surgical stabilisation with anterior corpectomy.
The extension teardrop. An avulsion injury of elderly, osteoporotic patients after a low-energy fall with hyperextension. It is usually stable, rarely needs surgery and has an excellent prognosis with conservative treatment.
Level. Teardrop fractures most commonly occur at C5 or C6.
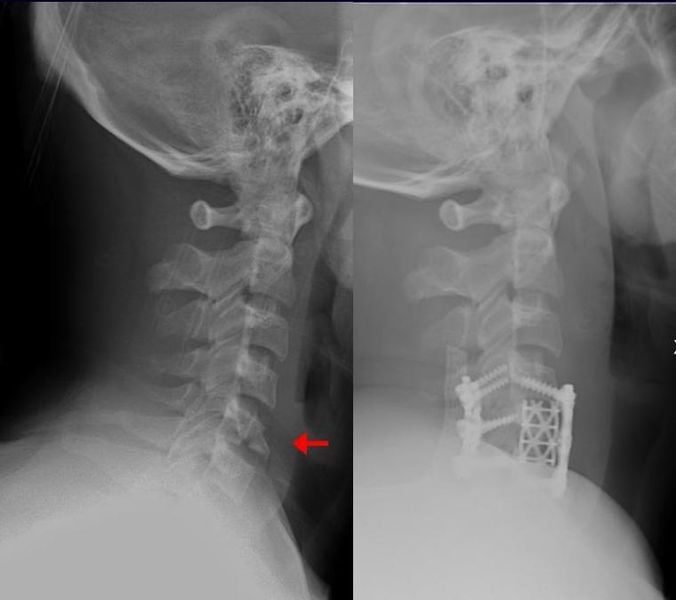
The teardrop fragment of a flexion injury is only the visible part of a burst. Behind it lie posterior ligamentous disruption and retropulsion, so expect a cord injury.
Anatomy and Pathophysiology
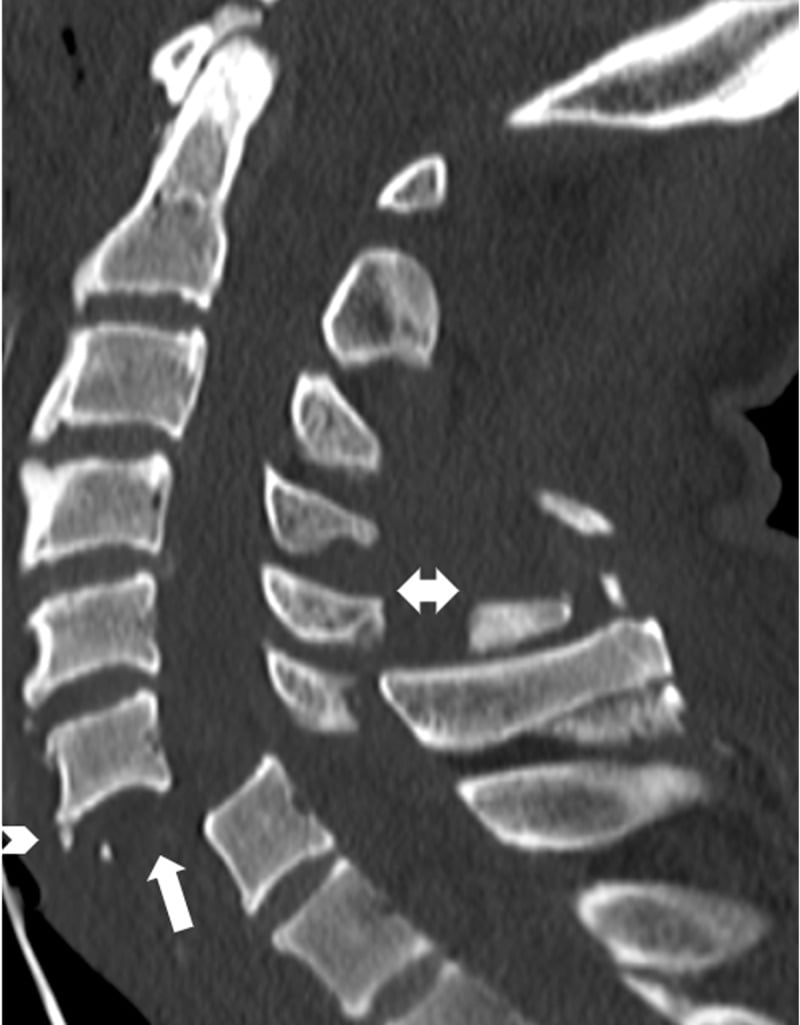
The flexion teardrop is a burst. The classic mechanism is a dive into shallow water: the head strikes the bottom and the axial load passes through the vertex and down the spine, with the neck flexed at the moment of impact. The load compresses the anterior body until a triangular anteroinferior fragment shears off, while the posterior ligaments fail in distraction. The vertebral body comminutes, a sagittal split is common, the posterior ligamentous complex fails in tension and the posterior part of the body retropulses into the canal, while the anteroinferior fragment remains tethered by the anterior longitudinal ligament. The result is a three-column injury, grossly unstable, with cord compression.
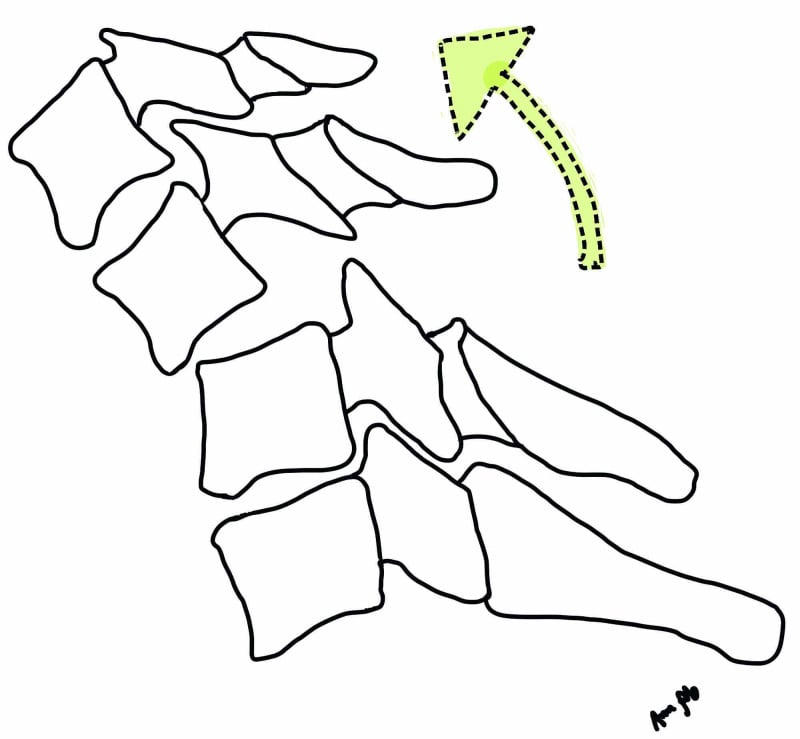
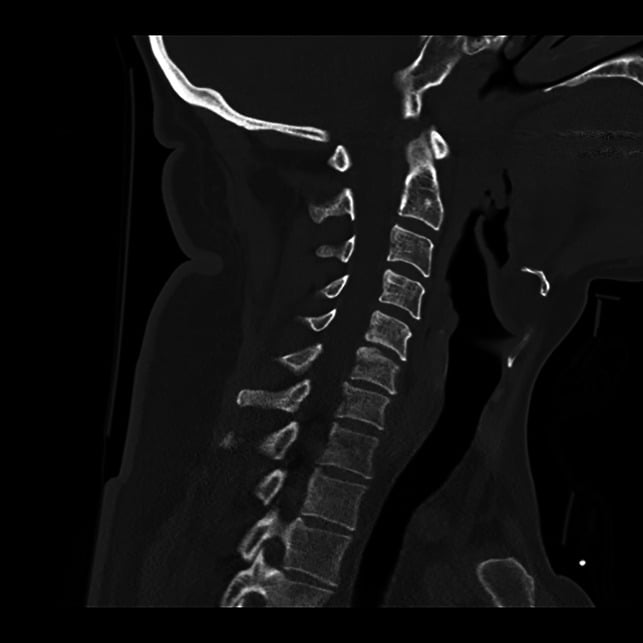
The extension teardrop is an avulsion. The spine hyperextends, with some axial component, and the anterior longitudinal ligament fails in tension, avulsing a small fragment from the anteroinferior body. The body is otherwise intact and not comminuted, and the posterior elements are intact; the injury is confined to the anterior column. Imaging shows prevertebral soft tissue swelling with subtle anterior disc space widening. It is stable unless there is severe disc disruption, and a severe injury may develop delayed instability, which is why it is followed up with imaging.
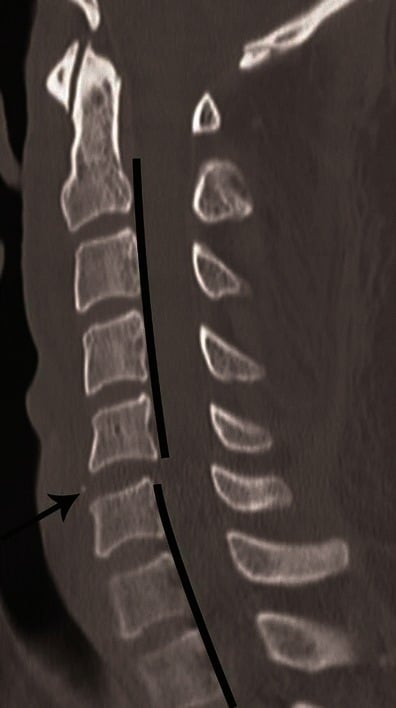
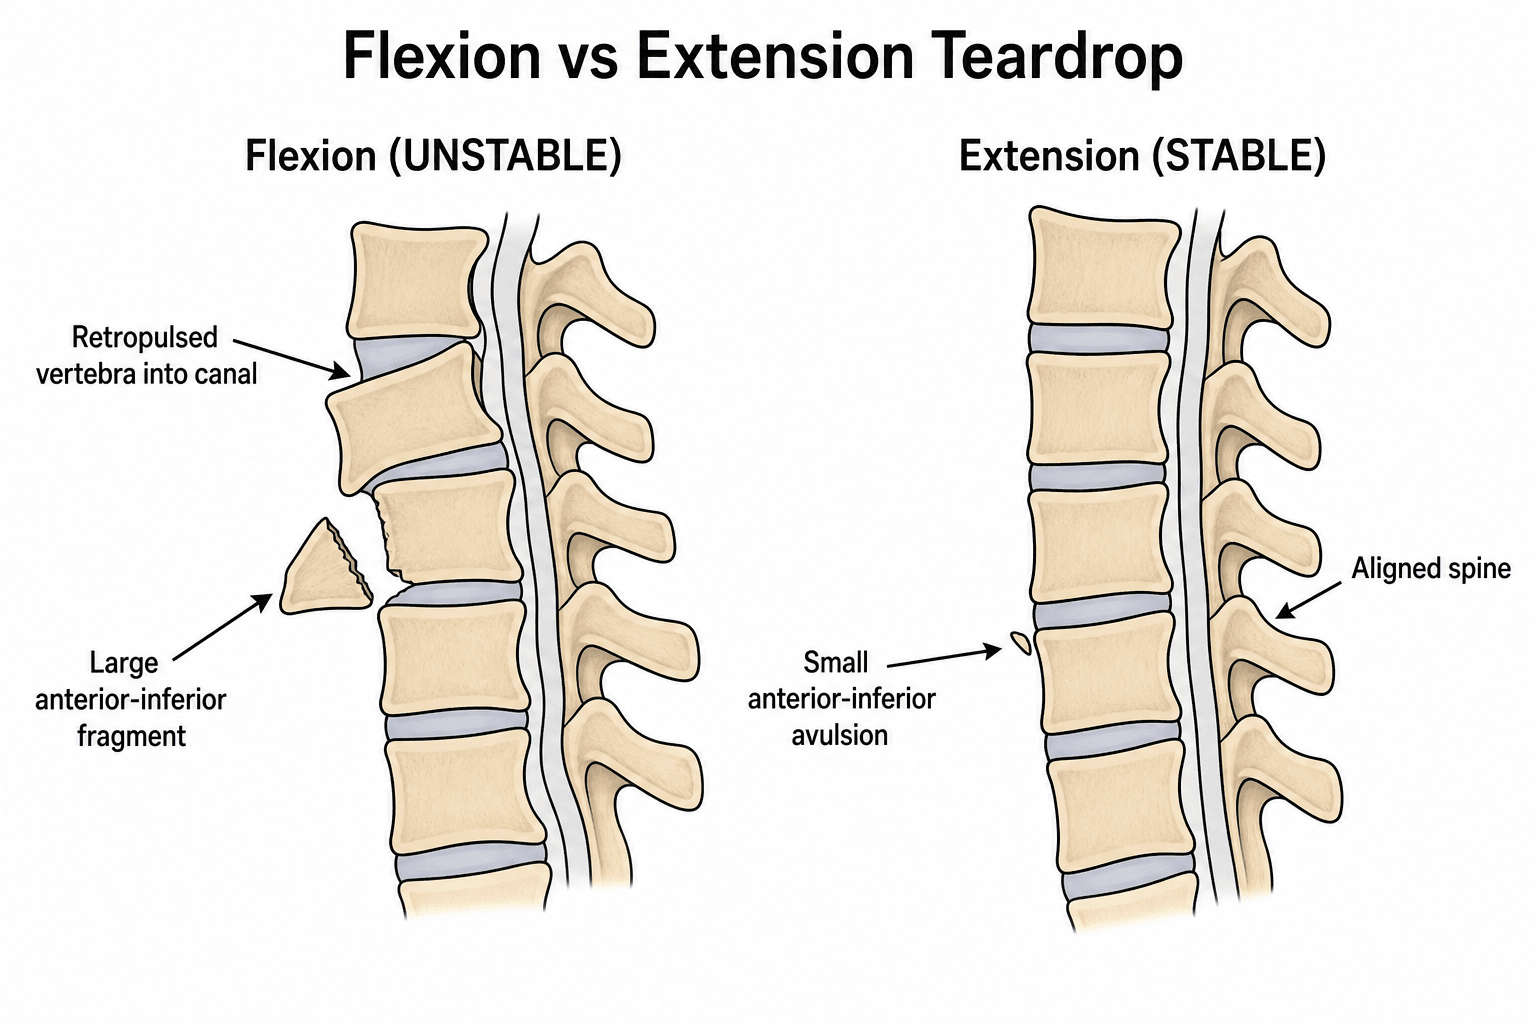
Telling them apart. Fragment size, the alignment of the vertebra behind it and the mechanism separate the two:
- Flexion: sagittal body fracture, posterior ligament injury, kyphosis
- Extension: small fragment from the anteroinferior body, body otherwise intact, no kyphosis
BURSTFlexion Teardrop Features
Hook:Flexion Teardrop is a BURST injury.
Classification Systems
- Flexion Teardrop
- Axial Load + Flexion (Diving)
- Extension Teardrop
- Hyperextension + Axial Load
- Flexion Teardrop
- Young, High Energy
- Extension Teardrop
- Elderly, Osteoporotic
- Flexion Teardrop
- Burst (3-Column)
- Extension Teardrop
- Avulsion (Anterior Column)
- Flexion Teardrop
- UNSTABLE
- Extension Teardrop
- Usually STABLE
- Flexion Teardrop
- Common (Quad/Anterior Cord)
- Extension Teardrop
- Rare
- Flexion Teardrop
- Surgery (ACDF/Corpectomy)
- Extension Teardrop
- Collar / Halo
The floating vertebra. Complete translation of one vertebra on the next means every ligamentous restraint has failed.
Clinical Assessment
History. The mechanism and age point to the type. Diving is classic for the flexion teardrop, which motor vehicle collisions also cause, and a fall with hyperextension points to the extension teardrop. The flexion patient is young, the extension patient elderly. Ask about weakness, numbness and bowel or bladder symptoms, and about neck pain, which may radiate.
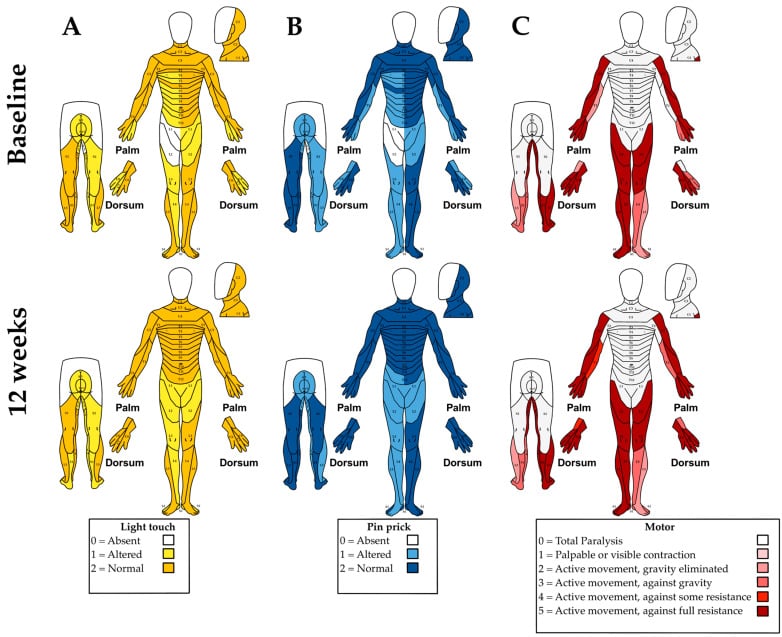
Examination. Maintain cervical spine precautions in a collar and do not test range of motion. The neurological examination is full motor and sensory, including rectal tone and the anal wink. Chart light touch and pinprick by dermatome and motor power by key myotome on the ASIA chart, with the sacral examination for sparing, at presentation and serially: serial charts are what demonstrate recovery or deterioration objectively.
Cord syndromes. A flexion teardrop often causes an anterior cord syndrome, a central cord syndrome or a complete cord injury. An extension teardrop rarely causes neurological injury.
- Motor
- Complete loss below level
- Sensory
- Pain/temp lost, proprioception and vibration preserved
- Prognosis
- Poor - anterior spinal artery
- Motor
- Upper limbs greater than lower
- Sensory
- Variable
- Prognosis
- Better - may recover function
- Motor
- No motor below level
- Sensory
- No sensation below level
- Prognosis
- Poor - unlikely recovery
Spinal shock is neurological. It is the transient loss of all reflex activity below the injury immediately after cord injury, with flaccid paralysis, areflexia and loss of the bulbocavernosus and anal reflexes, and it resolves over hours to days. Return of the bulbocavernosus reflex (S2-S4) marks its end. You cannot accurately classify an injury as ASIA A (complete) while the patient is still in spinal shock, because apparent total loss may partly recover.
Neurogenic shock is haemodynamic. It is seen in cervical and high-thoracic (above T6) cord injury, where loss of sympathetic outflow causes hypotension with bradycardia and warm, vasodilated peripheries. That is the opposite of the tachycardic, vasoconstricted picture of haemorrhagic shock.
In a trauma patient, always exclude haemorrhagic shock before attributing hypotension to neurogenic shock, because the two can coexist. Once haemorrhage is excluded, manage neurogenic shock with judicious fluids, vasopressors (e.g. noradrenaline) and atropine for symptomatic bradycardia, targeting a MAP of ~85-90 mmHg for the first ~7 days to optimise spinal cord perfusion.
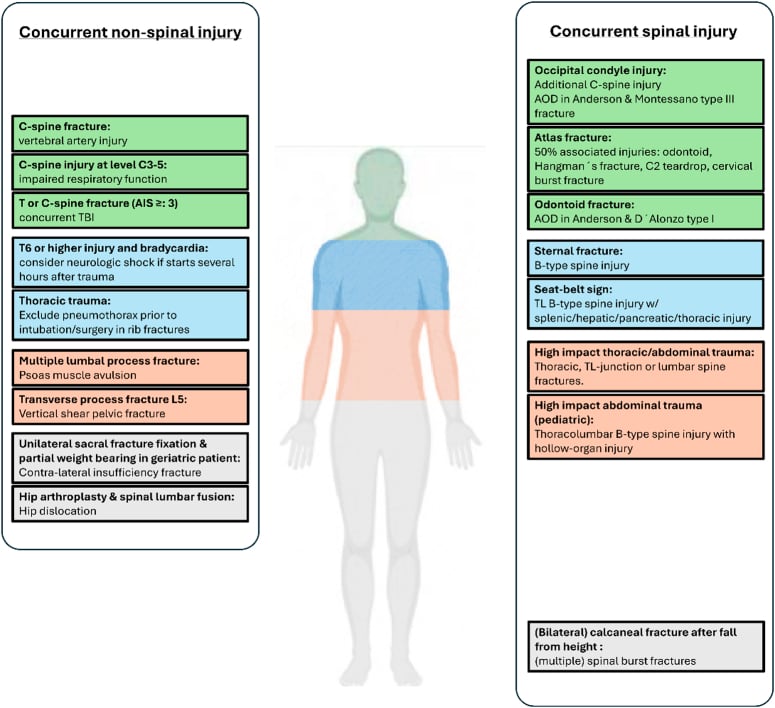
Associated injuries. The flexion teardrop is a high-energy injury and rarely travels alone. Look for a second non-contiguous spinal fracture, vertebral artery injury, and concurrent head, chest and abdominal trauma; an injury at C3 to C5 additionally threatens respiratory function.
Differential diagnosis. Several entities put a fragment at the anteroinferior corner of a cervical body:
- Distinguishing Feature
- Sagittal body split, comminution, retropulsion into the canal, kyphosis, PLC disruption - and the fragment is typically WIDER than it is tall, the converse of the extension pattern below
- Stability / Action
- Unstable - surgery
- Distinguishing Feature
- Small fragment, body intact, no sagittal split, fragment height greater than width
- Stability / Action
- Usually stable - collar
- Distinguishing Feature
- Loss of anterior height without discrete teardrop fragment or retropulsion
- Stability / Action
- Usually stable
- Distinguishing Feature
- Central comminution and retropulsion without the classic anteroinferior triangular fragment
- Stability / Action
- Often unstable
- Distinguishing Feature
- Well-corticated, rounded, smooth margins, no oedema on MRI, incidental
- Stability / Action
- Stable - do not treat as acute
- Distinguishing Feature
- Fused, brittle spine; trivial mechanism; transverse fracture through ankylosed segment
- Stability / Action
- Highly unstable - very low threshold for surgery
A small anteroinferior fragment in a fused, ankylosed spine (ankylosing spondylitis or DISH) is not a benign avulsion. The rigid spine behaves like a long bone, and these are unstable, three-column shear fractures with a high rate of delayed neurological deterioration. CT the whole cervical spine and have a very low threshold for cross-sectional imaging.
Investigations
Radiographs. AP, lateral and odontoid views come first and may show the teardrop fragment at the anteroinferior corner. The findings of a flexion teardrop are:
- Retrolisthesis and kyphosis
- Widening of the interspinous distance
- Loss of vertebral body height
CT. The gold standard and essential for assessment, with 1mm cuts and reconstructions. CT is what differentiates the two types, and the key finding is the sagittal split through the body of a flexion teardrop. Assess:
- Fragment size and location
- Vertebral body comminution (flexion) or an intact body (extension)
- Retropulsed fragment (flexion)
- Facet alignment
- Canal compromise
MRI. Required for soft-tissue assessment, and mandatory before reduction or surgery. A disc extruded behind the vertebral body changes the approach from posterior to anterior. Assess:
- Spinal cord (oedema, contusion, compression)
- Disc herniation
- Posterior ligamentous complex (PLC) integrity
- Anterior longitudinal ligament (ALL)
- Disco-ligamentous complex (DLC) status
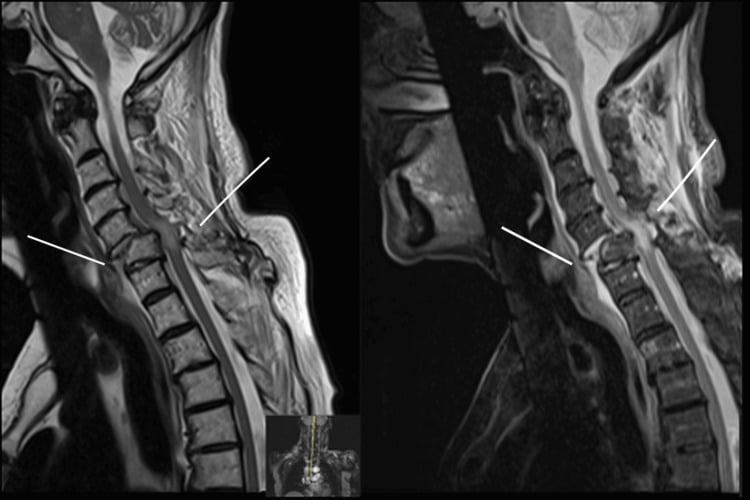
Cervical spine fractures, particularly those with translation, facet subluxation/dislocation, or extension into the foramen transversarium (as a displaced flexion teardrop may have), carry a real risk of blunt cerebrovascular injury (BCVI) to the vertebral (or carotid) artery, which can cause posterior-circulation stroke. Apply screening criteria (e.g. the modified Denver criteria, which include any cervical spine fracture with subluxation, fracture through the transverse foramen, or upper C1-C3 fractures) and obtain CT angiography of the neck. Confirmed BCVI is usually managed with antithrombotic therapy (antiplatelet or anticoagulation), balanced against the patient's bleeding/injury profile, to reduce stroke risk. This is an easy mark to drop in a cervical-trauma viva.
Management Algorithm
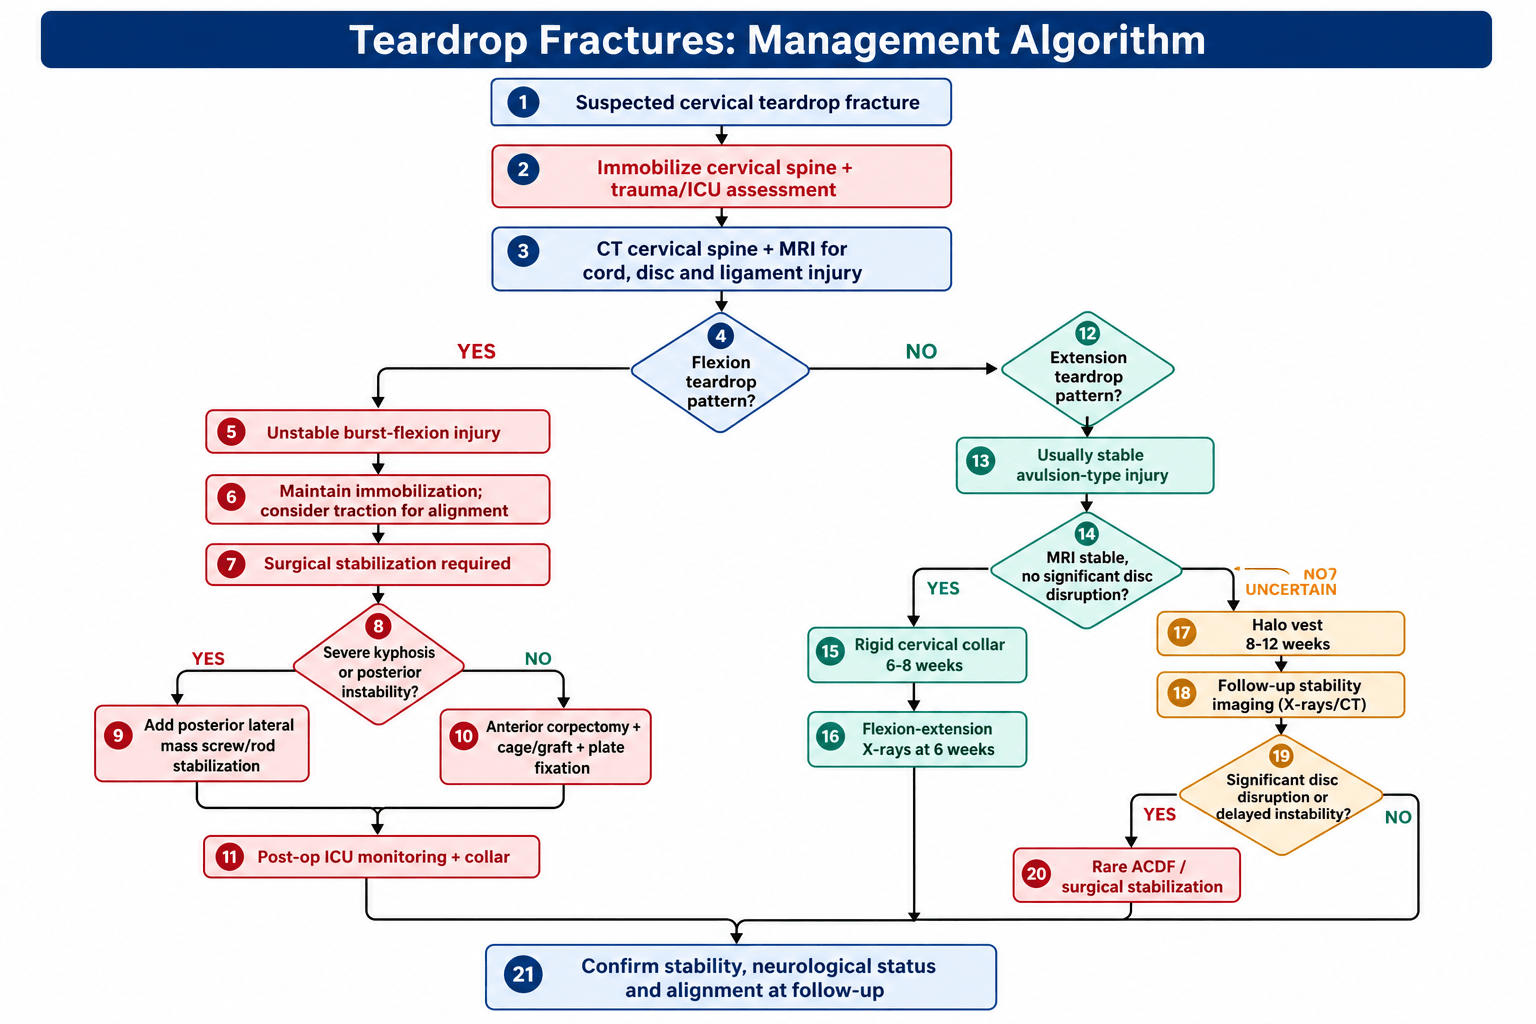
Flexion teardrop: surgical stabilisation. Surgery is required, and the sequence is:
- Immediate cervical spine immobilisation and ICU admission
- Traction may be used for initial alignment (Gardner-Wells tongs)
- Imaging: CT and MRI
- Surgery: anterior corpectomy with cage and plate, or a combined anterior-posterior approach
- Postoperative ICU monitoring and a collar
The exception is the one the SLIC section describes: with an intact neurological examination the composite score may not reach the operative tier, and conservative management can be chosen.
Choosing the approach. The anterior approach addresses the main pathology, the burst body and the disc. The fractured vertebra is removed, which decompresses the retropulsed fragment directly, and a structural graft and plate are placed. Posterior stabilisation with lateral mass screws and rods is added for significant kyphosis or posterior instability, making the fixation circumferential when the posterior ligaments have failed or the anterior construct alone will not hold in a severely kyphotic, three-column injury.
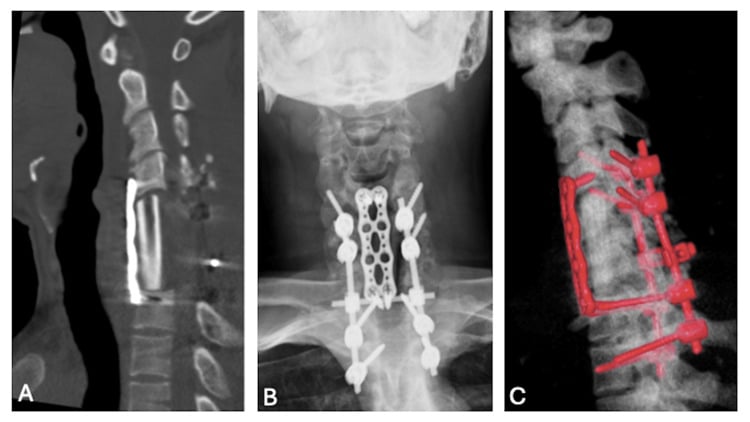
Extension teardrop: usually non-operative. Most extension teardrops heal with immobilisation, and treatment is graded by severity:
- Mild (stable MRI): rigid cervical collar for 6-8 weeks
- Moderate (disc concern): halo vest for 8-12 weeks
- Severe (instability): rarely, ACDF if there is significant disc disruption or delayed instability
Flexion-extension radiographs at 6 weeks confirm stability.
Surgical Technique
Anterior cervical corpectomy and fusion (ACCF). The operation for the flexion teardrop.
- Positioning: supine, head neutral, inline traction
- Approach: standard anterior cervical (left-sided), through platysma, to longus colli
- Discectomy: remove the discs above and below the fractured level
- Corpectomy: remove the fractured vertebral body and decompress the canal
- Graft: structural cage (titanium or PEEK) filled with bone graft
- Plate: anterior cervical plate spanning the levels above and below
- Closure: haemostasis, drain optional, layered closure
Posterior stabilisation may be added if there is severe ligamentous injury.
Complications
- Risk Factor
- Missed instability / Surgical
- Management
- ICU monitoring / Revision
- Risk Factor
- Osteoporosis / Poor fixation
- Management
- Revision surgery
- Risk Factor
- Inadequate correction
- Management
- Extension osteotomy / Revision
- Risk Factor
- Fusion
- Management
- Surveillance / Revision
- Risk Factor
- Anterior approach
- Management
- Usually transient / SLP
Postoperative Care and Rehabilitation
Rehabilitation Timeline
- ICU monitoring, especially if there is a cord injury, with MAP goals
- Rigid cervical collar
- DVT prophylaxis, mechanical and chemical (if no contraindication)
- Early mobilisation if neurologically intact
- Continue the rigid collar
- X-ray at 6 weeks to check for fusion
- Spinal cord rehabilitation if there is a cord injury
- Avoid heavy lifting and contact sports
- If fused, the collar may be removed
- X-ray to confirm fusion
- Gradual return to activities
- Follow-up flexion-extension X-rays
Outcomes and Prognosis
Neurological status at presentation is the strongest predictor of outcome.
Flexion teardrop. The prognosis is guarded, with a high rate of permanent neurological deficit and poor recovery even with surgery; anterior cord syndrome is common. Fusion rates are high, 90%+ with modern instrumentation and anterior corpectomy and fusion.
Extension teardrop. The prognosis is excellent with conservative care: 95%+ heal in a collar, and surgery is rarely needed.
Guidelines, Registries & Global Practice
- Diving/shallow-water injuries: Pooled series report spinal cord injury in over 90% of cases, with roughly two-thirds left with permanent neurological deficit (Griepp 2022)
- Demographics: Flexion teardrop predominantly young males in high-energy trauma; extension teardrop in elderly, often osteoporotic or with cervical spondylosis
- Incidence: Approximately 1 diving-related spinal cord injury per million population per year (Schwarz, 8-institution Austrian series 1991-1998, PMID 11357695)
- Level: C5 and C6 are the most commonly affected segments for both types
- SLIC (Vaccaro 2007): 1-3 non-operative, 4 indeterminate, 5 or more operative; widely adopted globally, and the indeterminate tier is part of the design rather than an oversight
- AOSpine subaxial (2016): A/B/C morphology, facet descriptor and neurology - the common international language alongside SLIC
- C-spine clearance: NEXUS and Canadian C-Spine Rule guide imaging triage; CT is the standard in obtunded or high-risk patients
- MRI: Required to assess DLC, disc and cord before declaring an injury stable
- Position on Subaxial Cervical Trauma
- Morphology-based A/B/C classification; encourages structured severity scoring to guide operative decisions
- Position on Subaxial Cervical Trauma
- Closed reduction and timing guidance for cervical SCI; supports early reduction of malalignment in awake patients
- Position on Subaxial Cervical Trauma
- Suggests decompression within 24 hours for acute traumatic cervical SCI where feasible (informed by STASCIS)
- Position on Subaxial Cervical Trauma
- Spinal injury major-trauma pathway: CT first-line for significant mechanism, MRI for cord/ligament assessment, transfer to spinal-capable centre
- Position on Subaxial Cervical Trauma
- Endorses SLIC and AOSpine for communication and surgical triage of subaxial injuries
- Rapid CT/MRI access, ICU with MAP-targeted cord perfusion
- Early (within 24h) decompression and instrumented anterior/posterior fusion
- Specialist spinal cord rehabilitation pathways
- Imaging may rely on plain films plus limited CT; MRI access constrained
- Traction (Gardner-Wells tongs) and halo/orthosis play a larger role when timely surgery is unavailable
- Emphasis on transfer to a spine-capable centre and prevention of secondary cord injury during handling
Key clinical-governance points (apply globally):
- Document mechanism (diving, fall, MVC) and a full ASIA/ISNCSCI neurological assessment at presentation
- State the teardrop type (flexion vs extension), the SLIC/AOSpine grade, and the rationale
- Counsel on surgical vs conservative options, expected outcomes and the guarded prognosis of cord injury
- Record informed consent including dysphagia, recurrent laryngeal/hypoglossal nerve injury, vascular injury, dural tear, non-union and the small risk of neurological deterioration
Controversies and Areas of Uncertainty
Timing of decompression. STASCIS supports decompression within 24 hours, but it was a non-randomised cohort and the benefit is clearest in incomplete injuries. The practical "ultra-early" (under 12h) target and its benefit in complete injuries remain debated, and logistics often dominate real-world timing.
Anterior or combined approach. A single anterior corpectomy addresses the burst body and retropulsion, but the threshold for adding posterior fixation (degree of kyphosis, facet injury, PLC failure, osteoporosis) is not standardised and varies by surgeon and registry.
Defining a "stable" extension teardrop. There is no validated cut-off separating a benign avulsion from an unstable hyperextension injury. MRI assessment of the disc and ALL is operator-dependent, and delayed instability is occasionally reported, justifying interval flexion-extension films.
Steroids in acute spinal cord injury. High-dose methylprednisolone remains contentious. Several guidelines no longer recommend it routinely because the marginal neurological benefit is outweighed by infective and metabolic complications, and practice varies widely between regions.
MCQ Practice Points
Q: What is the key difference between flexion and extension teardrop fractures? A: Flexion teardrop is a BURST injury (3-column, unstable, surgery needed). Extension teardrop is an AVULSION (anterior column only, usually stable, conservative). The teardrop fragment looks similar but the injuries are vastly different.
Q: What is the classic mechanism for flexion teardrop fracture? A: Diving into shallow water - axial load through the vertex with the neck in flexion. This mechanism causes the burst injury pattern.
Q: What CT finding differentiates flexion from extension teardrop? A: Sagittal split through the vertebral body in flexion teardrop (key finding!). The body is comminuted/burst. In extension, the body is intact with just an avulsion fragment.
Q: What is the typical SLIC score for flexion teardrop fractures? A: 6-10 points (morphology 3-4 + DLC 2 + neurology 2-4) - firmly in the operative tier (5 or more; a score of exactly 4 is the indeterminate zone). Extension teardrop typically scores 1-3 (usually conservative).
Q: What is the surgical treatment for flexion teardrop fractures? A: Anterior cervical corpectomy and fusion (ACCF) - remove fractured vertebra, decompress canal, structural graft, anterior plate. May add posterior stabilization if severe kyphosis or posterior instability.
Q: What cord syndrome is commonly associated with flexion teardrop? A: Anterior cord syndrome - loss of motor, pain, and temperature below the level, preserved proprioception and vibration. Complete cord injury is also common.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 22-year-old male is brought in after diving into shallow water. He is quadriplegic with no motor or sensory function below C5. GCS 15, breathing spontaneously. What is your assessment and management?”
“A 78-year-old female presents after a fall with hyperextension of her neck. She has neck pain but no weakness or numbness. X-ray shows a small teardrop fragment at C5. What is your diagnosis and management?”
“You are shown two lateral C-spine X-rays both showing a teardrop fragment. One is from a 25-year-old diver, the other from a 75-year-old who fell. How do you differentiate flexion from extension teardrop?”
Key Anatomy
- Teardrop fragment = triangular anteroinferior vertebral body fragment
- Flexion = burst injury (3-column), extension = avulsion (anterior column)
- C5-C6 = most common level for both types
- Posterior ligamentous complex (PLC) = determines stability
Classification
- Flexion teardrop = BURST (unstable, surgery), extension = AVULSION (stable, conservative)
- SLIC score: Flexion 6+ (surgery), extension 1-3 (conservative)
- Sagittal split on CT = key finding for flexion teardrop
- Body intact on CT = extension teardrop
Treatment Algorithm
- Flexion teardrop: Anterior corpectomy and fusion (ACCF), may add posterior
- Extension teardrop: Rigid collar 6-8 weeks, excellent prognosis
- SLIC greater than 4 = surgery recommended
- MRI essential to assess DLC and cord
Surgical Pearls
- ACCF: Remove fractured vertebra, decompress canal, structural graft, anterior plate
- May add posterior stabilization if severe kyphosis or posterior instability
- Protect during positioning - Mayfield clamp, neutral alignment
- High fusion rates (90%+) with modern instrumentation
Complications
- Neurological deterioration: Missed instability, surgical complication
- Nonunion: Osteoporosis, poor fixation - revision surgery
- Kyphosis: Inadequate correction - extension osteotomy
- Dysphagia: Anterior approach - usually transient
Evidence Base and Key Trials
SLIC - Original Classification (Spine Trauma Study Group)
- Defined the Subaxial Injury Classification and Severity Scale (SLIC) from three weighted categories: injury morphology, disco-ligamentous complex (DLC), and neurological status
- Multicentre reliability study, 20 spine surgeons scoring 11 trauma cases on two occasions
- Interrater intraclass correlation: morphology 0.57, DLC 0.49, neurology 0.87; raters agreed with the algorithm treatment recommendation in 93.3% of cases
- Reliability compared favourably with the older Harris and Allen-Ferguson mechanistic systems
SLIC-Based Surgical Approach Algorithm
- Evidence-based algorithm linking SLIC injury type to surgical approach (anterior, posterior, or combined)
- Burst/compression and distraction injuries are more often amenable to a single anterior approach
- Severe translation/rotation injuries more commonly require a posterior or combined antero-posterior approach
- Designed to answer the two core questions: should I operate, and which approach do I choose?
SLIC Scored Injuries - Literature Analysis
- Systematic review (2007-2014) mapping specific injury patterns onto SLIC scores and resulting treatment
- SLIC 1-3: neurologically intact spinous-process, laminar, small facet, compression and burst fractures - non-operative
- SLIC 4: indeterminate zone, e.g. central cord syndrome, incomplete deficits, burst with complete deficit
- SLIC 5-10: distraction/rotational injuries, traumatic disc herniation with deficit, burst with incomplete deficit - operative
AOSpine Subaxial Cervical Classification
- Morphology-based system mirroring the thoracolumbar scheme: A (compression), B (tension band), C (translational), plus facet (F) descriptors, patient modifiers and neurology
- Substantial intra- and interobserver reliability (kappa 0.75 intraobserver, 0.64 interobserver)
- A flexion teardrop is typically an A3/A4 compression-burst, often with a tension-band (B) or translational (C) component when posteriorly unstable
- An extension teardrop avulsion is usually a low-grade A0/A1 anterior compression injury