VTE Prevention | DVT and PE | Orthopaedic Perioperative Care
- High Risk Procedures: THA, TKA and hip fracture surgery require extended prophylaxis beyond discharge
- Mechanical: TED stockings + IPC - ALWAYS use with chemical for high-risk procedures
- Chemical Options: LMWH (enoxaparin), DOACs (rivaroxaban, apixaban), aspirin
- Duration: 28-35 days for THA and hip fracture, 14-35 days for TKA - NOT just in-hospital
- Timing: Start LMWH 6-12 hours post-op; rivaroxaban 6-10 hours post-op
- “Extended prophylaxis beyond discharge is MANDATORY after arthroplasty and hip fracture
- “LMWH is gold standard but DOACs are equivalent
- “Aspirin is acceptable after initial anticoagulant
- “Mechanical prophylaxis ALWAYS for high-risk procedures - even if on chemical
Overview and Epidemiology
Why it matters. Venous thromboembolism (VTE) covers deep vein thrombosis (DVT) and pulmonary embolism (PE), and it is the most common preventable cause of in-hospital death. After THA and TKA without prophylaxis, venographic DVT rates are 40-60% and symptomatic PE 1-2%.
What the 40-60% counts. It is the most commonly misquoted number in VTE prophylaxis. It comes from the pre-prophylaxis era, when trials screened every patient with routine ascending venography, and it therefore counts overwhelmingly distal, asymptomatic calf thrombi that would never have declared themselves clinically. It is emphatically not a 40-60% risk of a symptomatic DVT.
How to quote it. Present it as the venographic denominator that established why prophylaxis became mandatory, and pair it with the modern figure: symptomatic VTE after elective THA/TKA is now roughly 1% or less at 90 days with prophylaxis and early mobilisation. Making that distinction is what separates a candidate who has memorised a number from one who understands it.
Risk without prophylaxis, by procedure. These figures are why prophylaxis is mandatory:
- THA - DVT 42-57%, PE 0.9-28%
- TKA - DVT 41-85%, PE 1.5-10%
- Hip fracture - DVT 46-60%, fatal PE 3-12%
- Major trauma - DVT 40-80%
Pathophysiology and Mechanisms
Virchow's triad. All three components are present in orthopaedic surgery:
- Stasis - immobility, surgery, prolonged recumbency
- Endothelial injury - surgical trauma, inflammation
- Hypercoagulability - surgery-induced, thrombophilia
Where the thrombus forms. Most clinically significant DVTs originate in the deep calf veins, the posterior tibial and peroneal veins and the soleal sinuses, and propagate proximally. Proximal DVT, in the popliteal, femoral and iliac veins, carries the highest PE risk. Upper limb DVT, in the subclavian and axillary veins, is uncommon in orthopaedics.
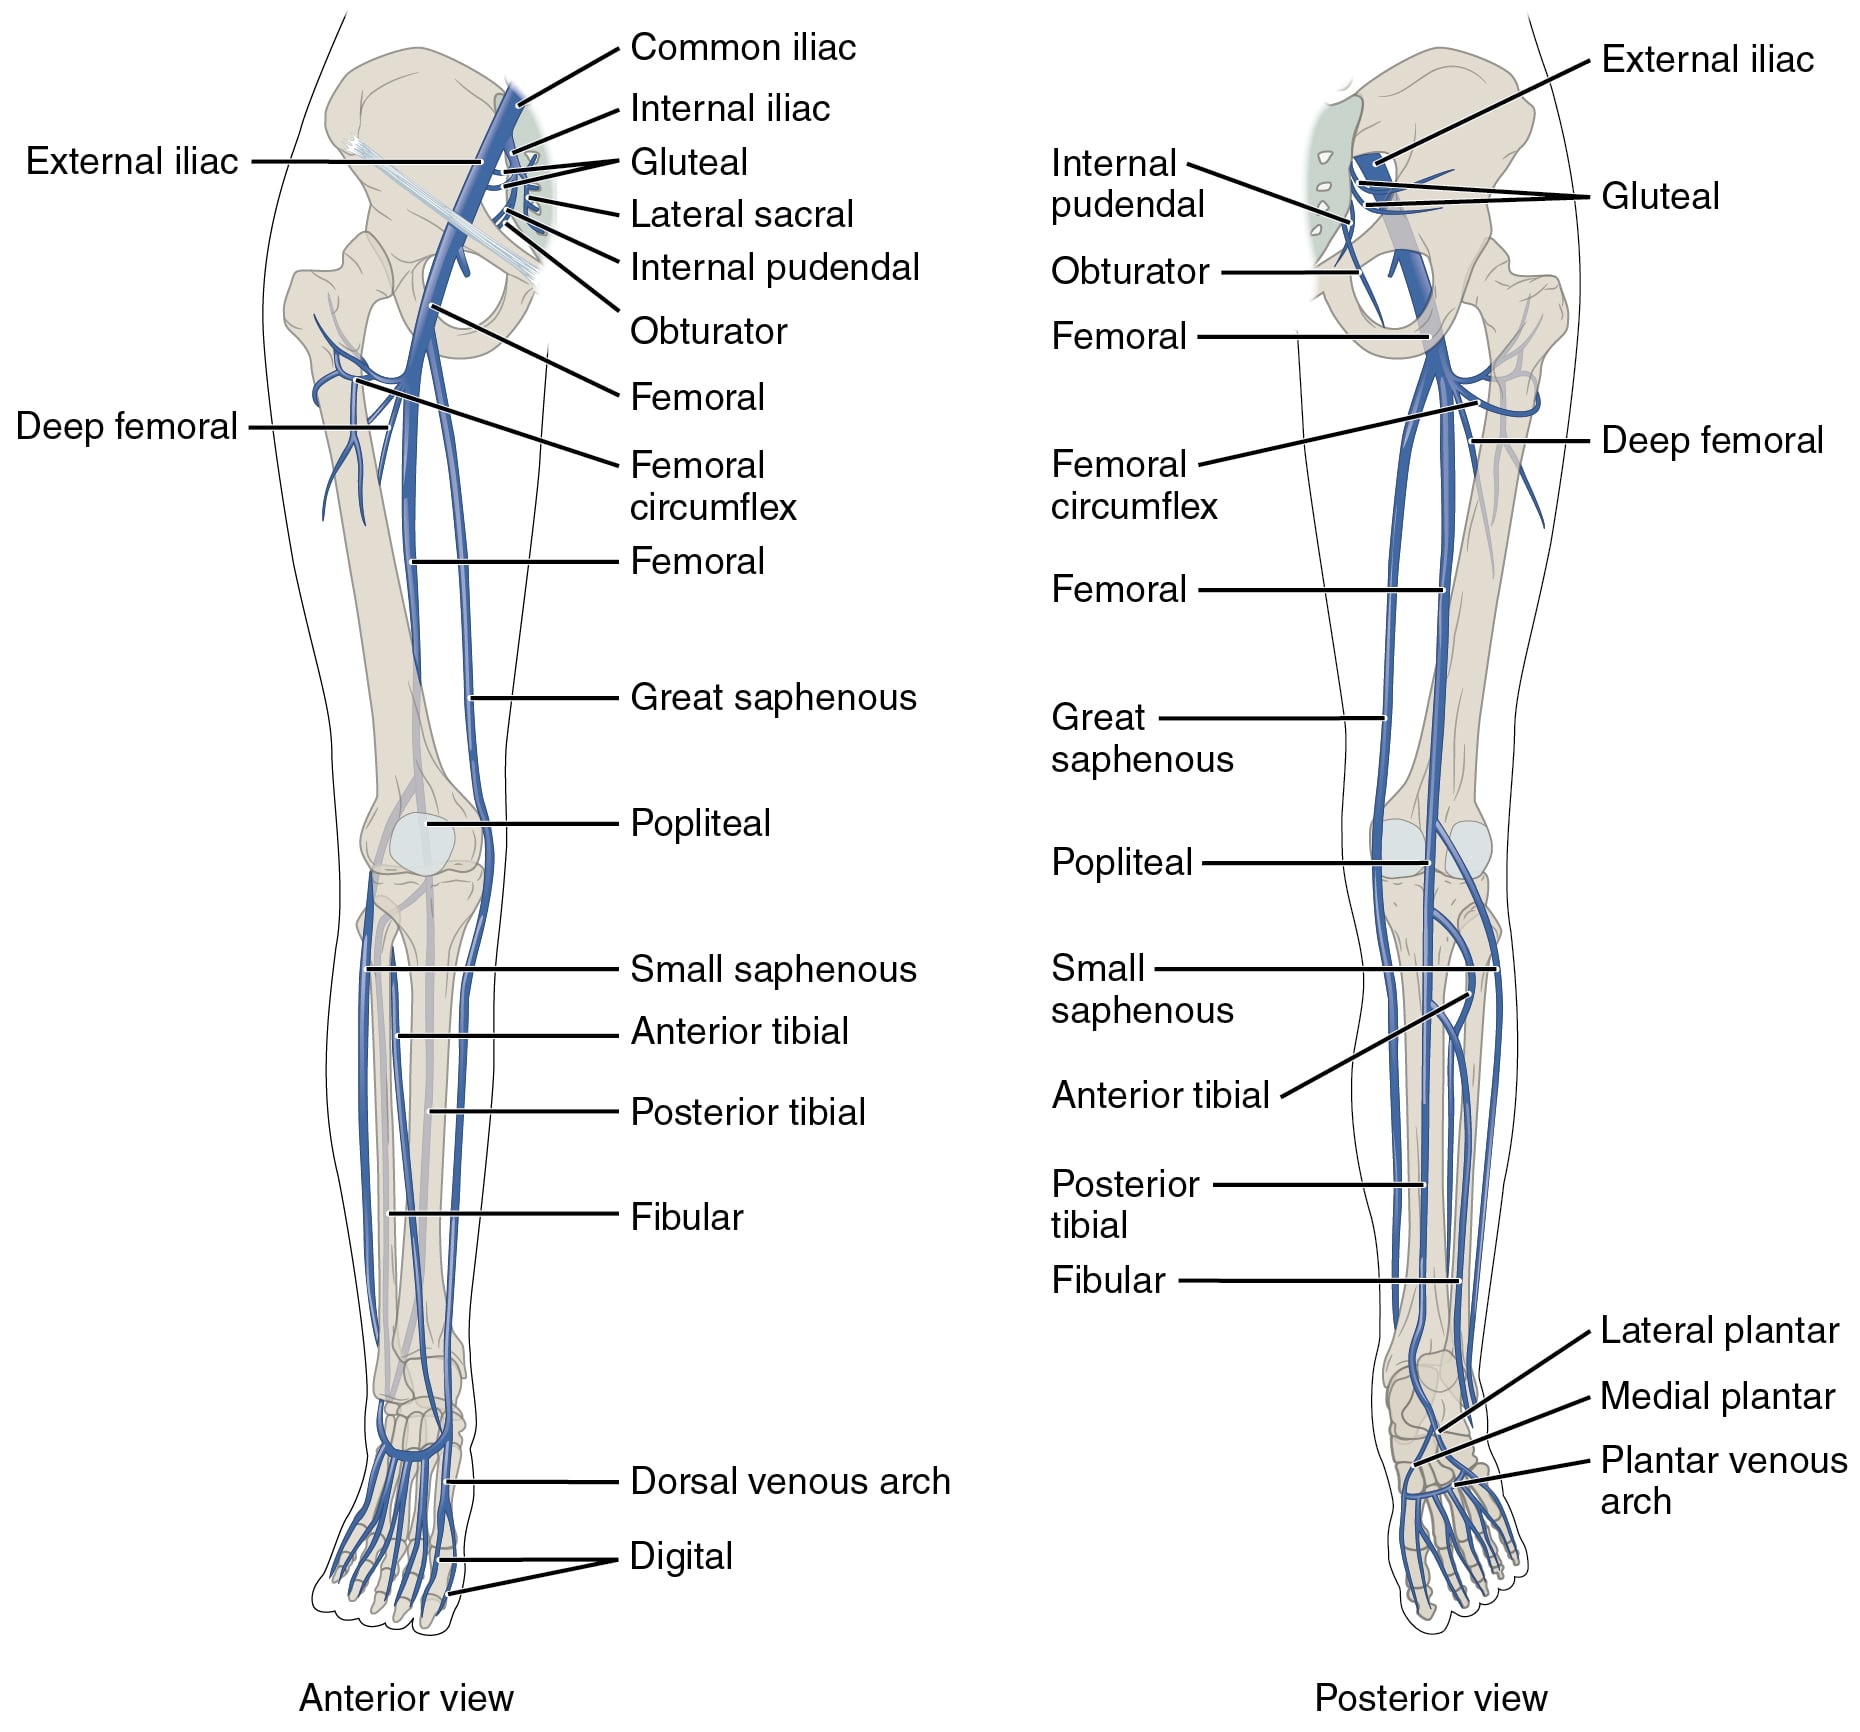
Natural history. Thrombus forms in the calf veins during or after surgery and may propagate proximally, in 20-30% if untreated. Proximal DVT can embolise to the pulmonary circulation, and the mortality of the resulting PE depends on clot burden and cardiopulmonary reserve.
Classification Systems
Procedure sets the baseline. Risk stratification by procedure guides the intensity and duration of prophylaxis.
- Procedures
- THA, TKA, hip fracture, pelvic trauma
- Prophylaxis
- Mechanical + LMWH/DOAC (mechanical + LMWH after hip fracture)
- Duration
- 28-35 days (TKA 14-35 days)
- Procedures
- Major trauma, spine fusion, cancer surgery
- Prophylaxis
- Mechanical + LMWH
- Duration
- Until ambulatory or 14 days
- Procedures
- Foot/ankle, upper limb, arthroscopy
- Prophylaxis
- Mechanical ± aspirin
- Duration
- Until ambulatory
- Procedures
- Minor procedures, outpatient
- Prophylaxis
- Early mobilisation
- Duration
- None required
Patient factors add to procedural risk. Each carries its own relative risk and implication for prophylaxis:
- Relative Risk
- 5-10x
- Implication
- Extended prophylaxis mandatory; consider continuing beyond 35 days
- Relative Risk
- 3-5x
- Implication
- LMWH preferred over aspirin
- Relative Risk
- 2-5x
- Implication
- Screen if prior VTE or family history; haematology input
- Relative Risk
- 2x
- Implication
- Higher dose or longer duration
- Relative Risk
- 2x
- Implication
- Weight-based LMWH dosing
- Relative Risk
- 2x
- Implication
- Aggressive mobilisation
- Relative Risk
- 1.5x
- Implication
- Balance bleeding risk
- Relative Risk
- 1.5x
- Implication
- Adequate prophylaxis
The Caprini Risk-Assessment Model
The model. The Caprini score is the most widely used weighted, cumulative VTE risk-assessment model. Each risk factor is assigned 1, 2, 3 or 5 points by severity, and the points are summed.
- Representative factors
- Age 41-60, minor surgery, BMI over 25, swollen legs/varicose veins, oestrogen therapy, pregnancy/postpartum, sepsis
- Theme
- Minor / additive
- Representative factors
- Age 61-74, major open or arthroscopic surgery, malignancy, confined to bed more than 72 hours, central venous line
- Theme
- Moderate
- Representative factors
- Age 75 or older, prior VTE, family history of VTE, thrombophilia (factor V Leiden, prothrombin gene, lupus anticoagulant), heparin-induced thrombocytopenia
- Theme
- Strong / heritable
- Representative factors
- Elective arthroplasty, hip/pelvis/leg fracture, stroke or acute spinal cord injury within a month, multiple trauma
- Theme
- Dominant
Score bands. The total maps to a prophylaxis recommendation:
- 0 - very low risk: early ambulation
- 1-2 - low: mechanical
- 3-4 - moderate: chemical or mechanical
- 5 or more - high: chemical plus mechanical, extended duration
The ceiling in orthopaedics. An elective arthroplasty and a hip, pelvis or leg fracture each score 5 on their own, so essentially every major orthopaedic patient is already "high risk" before a single individual factor is added. That ceiling is why the score has only modest discrimination within the arthroplasty population: it cannot separate the high-risk arthroplasty patient from the very-high-risk one.
Where it earns its place. Its value here runs the other way. Use it to surface the extra factors (prior VTE, active cancer, thrombophilia) that justify longer or higher-intensity prophylaxis rather than to decide whether to give it, and to risk-assess the lower-risk and mixed surgical patients for whom it was derived.
Clinical Assessment
Signs are unreliable. Half of DVTs are asymptomatic and clinical signs miss 50%. Screening is not recommended: the focus is prevention with appropriate prophylaxis rather than detection.
DVT. The signs, when present:
- Calf pain, worse with dorsiflexion (Homans' sign)
- Asymmetric leg swelling
- Warmth of the affected limb
- Subtle erythema
- A palpable cord, the thrombosed vein
PE. A clinical emergency: act immediately if it is suspected.
- Dyspnoea, the most common symptom
- Pleuritic chest pain, sharp and worse on inspiration
- Tachycardia, heart rate over 100
- Hypoxia, SpO2 under 92%
- Syncope in massive PE
Investigations
Pre-test probability. The Wells score estimates the probability of DVT or PE and guides further investigation.
D-dimer. Sensitive but not specific, so a negative result is useful to rule VTE out. It is always elevated after surgery, which makes it useless post-operatively: rely on clinical suspicion and imaging instead.
Compression ultrasound is the gold standard for DVT. A non-compressible vein is thrombus, and sensitivity exceeds 95% for proximal DVT.
CTPA (CT pulmonary angiography) is the gold standard for PE. Use a V/Q scan if contrast is contraindicated.
Differential Diagnosis
Mimics. The swollen, painful post-operative limb and the breathless post-operative patient both have important mimics. Anchoring on VTE risks missing a treatable alternative, and treating a mimic as VTE exposes a fresh surgical wound to unnecessary anticoagulation.
- Distinguishing features
- Unilateral whole-leg swelling, warmth, calf tenderness
- Key test
- Compression ultrasound (non-compressible vein)
- Why it matters
- Therapeutic anticoagulation needed
- Distinguishing features
- Pleuritic pain, dyspnoea, tachycardia, hypoxia
- Key test
- CTPA
- Why it matters
- Life-threatening; treat empirically if unstable
- Distinguishing features
- Tense swelling, bruising, falling haemoglobin
- Key test
- Clinical, ultrasound, FBC
- Why it matters
- Anticoagulation would worsen it — opposite treatment
- Distinguishing features
- Erythema with defined border, fever, raised CRP
- Key test
- Clinical, inflammatory markers
- Why it matters
- Needs antibiotics, not anticoagulation
- Distinguishing features
- Sudden calf pain, crescent bruise at ankle
- Key test
- Ultrasound
- Why it matters
- Mimics DVT closely; conservative management
- Distinguishing features
- Bilateral or chronic, painless, pitting
- Key test
- Clinical
- Why it matters
- No acute intervention
- Distinguishing features
- Hypoxia, petechiae, confusion 24–72h post long-bone fracture
- Key test
- Clinical (Gurd criteria), CXR
- Why it matters
- Supportive care, not anticoagulation
Management Algorithm
The principle. For high-risk procedures, combine mechanical and chemical prophylaxis and extend it beyond discharge. Mechanical prophylaxis reduces VTE on its own and adding a chemical agent reduces it further. For high-risk procedures mechanical prophylaxis is always indicated, even when a drug is given. The AAOS guideline is less prescriptive for elective arthroplasty, asking for pharmacological and/or mechanical prophylaxis without mandating an agent.
Mechanical methods. Three devices are used:
- Graduated compression (TED) stockings - below-knee or thigh-high; reduce DVT by 50% alone; proper fit is essential
- Intermittent pneumatic compression (IPC) - sequential calf compression, applied in theatre and continued post-operatively; more effective than stockings alone, and best combined with them
- Venous foot pumps - an alternative to IPC, which may be used if calf access is limited
Drugs. Enoxaparin is the gold standard, DOACs are convenient oral alternatives, and aspirin is acceptable to complete an extended course. Edoxaban and dabigatran are further DOAC options.
- Dose
- 40mg SC daily
- Timing
- 6-12 hrs post-op
- Monitoring
- None routinely (anti-Xa if renal impaired)
- Dose
- 10mg PO daily
- Timing
- 6-10 hrs post-op
- Monitoring
- None required
- Dose
- 2.5mg PO BD
- Timing
- 12-24 hrs post-op
- Monitoring
- None required
- Dose
- 81mg PO daily in EPCAT II; 81mg PO BD in PREVENT CLOT - regimens vary, so quote the trial
- Timing
- Immediate
- Monitoring
- None required
- Dose
- 2.5mg SC daily
- Timing
- 6-8 hrs post-op
- Monitoring
- None (avoid if CrCl less than 30)
Timing is a trade. A first dose given too early increases bleeding; one given too late may allow thrombus to form.
Gold standard against the trials. Calling LMWH the gold standard sits alongside RECORD1 and RECORD4, in which rivaroxaban was more effective than enoxaparin on a composite driven by asymptomatic venographic DVT (see the Evidence Base). Aspirin's place rests on EPCAT II: it was non-inferior when used to complete extended prophylaxis after an initial anticoagulant, a five-day rivaroxaban lead-in in that trial, so it can finish a course begun with LMWH or a DOAC.
Duration. VTE risk persists beyond discharge, so extended prophylaxis is mandatory after arthroplasty and hip fracture and in-hospital prophylaxis alone is inadequate. The durations below follow the ACCP; the AAOS leaves duration to surgeon discretion.
- Minimum Duration
- 10-14 days
- Recommended
- 35 days
- Minimum Duration
- 10-14 days
- Recommended
- 14-35 days
- Minimum Duration
- 28 days
- Recommended
- 35 days
- Minimum Duration
- Until ambulatory
- Recommended
- Until ambulatory
- Minimum Duration
- 7-10 days
- Recommended
- Until ambulatory
MCEVTE Prophylaxis Approach
Hook:MCE = Mechanical, Chemical, Extended - the three pillars of VTE prophylaxis in orthopaedics.
Surgical Technique
In theatre. These measures complement mechanical and chemical prophylaxis:
- Minimise tourniquet time: the longer the tourniquet, the higher the risk
- Handle tissue gently to reduce endothelial injury
- Regional anaesthesia may reduce VTE compared with general
- Start IPC before induction
- Keep the patient adequately hydrated and avoid hypovolaemia
- Avoid hypotension and maintain perfusion
Complications
Anticoagulation has its own price. Every regimen balances VTE risk against bleeding risk.
- Incidence
- 1-3%
- Management
- Hold anticoagulant, reverse if severe, mechanical only
- Incidence
- 2-5%
- Management
- May require washout, balance VTE and bleeding risk
- Incidence
- 0.5-1%
- Management
- Stop heparin, use fondaparinux or argatroban
- Incidence
- Rare
- Management
- Neurological emergency - decompress urgently
- Incidence
- 1-2%
- Management
- PPI cover, balance benefits vs risks
Heparin-Induced Thrombocytopenia and the 4T Score
Why it is examined. HIT is a serious complication of heparin products and the one prophylaxis complication where the intuitive response is wrong. Check platelets on days 5-10 when using LMWH.
The paradox. Immune (type II) HIT is caused by IgG antibodies against complexes of heparin and platelet factor 4 (PF4). The antibody-PF4-heparin complex activates platelets, so despite a falling platelet count the patient becomes intensely prothrombotic, with venous and arterial "white clots" rather than bleeding. Type I is a mild, early, non-immune, self-limiting dip and is benign.
Who and when. HIT is commoner with unfractionated heparin than LMWH, and commoner after surgery. The platelet fall is classically on days 5-14, or within a day if heparin was given in the preceding 100 days or so (rapid-onset HIT).
The 4T score estimates pre-test probability, each item scoring 0, 1 or 2:
- 2 points
- Fall over 50% AND nadir 20 or higher
- 1 point
- Fall 30-50% or nadir 10-19
- 0 points
- Fall under 30% or nadir under 10
- 2 points
- Clear onset days 5-10 (or day 1 if heparin within 30 days)
- 1 point
- Onset after day 10, unclear, or day 1 with heparin 30-100 days ago
- 0 points
- Fall before day 4 with no recent heparin
- 2 points
- New confirmed thrombosis, skin necrosis, or systemic reaction post IV bolus
- 1 point
- Progressive/recurrent or silent thrombosis, erythematous skin lesions
- 0 points
- None
- 2 points
- None apparent
- 1 point
- Possible
- 0 points
- Definite
Reading the score. A total of 0-3 is low probability and effectively excludes HIT clinically; 4-5 is intermediate and 6-8 high. An intermediate or high score triggers treatment and laboratory confirmation.
Management runs against instinct. The patient is clotting, not bleeding:
- Stop all heparin immediately, including LMWH, heparin flushes and heparin-bonded lines
- Start a non-heparin anticoagulant at therapeutic dose: a direct thrombin inhibitor such as argatroban, or danaparoid or fondaparinux
- Do not transfuse platelets prophylactically, which fuels the thrombosis
- Do not start warfarin until the platelet count recovers (over 150): early warfarin precipitates venous limb gangrene and skin necrosis through protein C depletion, so overlap and bridge instead
- Confirm the diagnosis with an anti-PF4/heparin immunoassay (ELISA), which is sensitive but not specific, plus the serotonin-release assay (SRA), the specific functional gold standard
- Document a heparin allergy and avoid heparin thereafter
Postoperative Care
On the ward. Of these measures, early mobilisation is one of the most effective:
- Mobilise early, weight-bearing on day 0-1 when possible
- Continue IPC until ambulatory
- Begin bilateral TED stockings immediately
- Encourage oral fluids
- Elevate the legs when in bed
- Active ankle exercises hourly when awake
After discharge. The course continues at home:
- At discharge - educate on the symptoms of VTE (calf pain, swelling, shortness of breath) and to seek immediate help if they occur
- Days 1-14 - continue LMWH or DOAC as prescribed, make sure the patient understands the regimen, and teach self-injection for LMWH
- Days 14-35 - the patient may switch to aspirin to complete the course, on the EPCAT II evidence, continuing until 35 days in total
- Follow-up - stop prophylaxis at 35 days if fully mobile; continue longer if high-risk or immobile
Compliance. Patient compliance with home prophylaxis is essential, so simplify regimens where possible.
Outcomes and Prognosis
With prophylaxis. DVT falls to 2-5%, symptomatic PE to less than 0.5% and fatal PE to less than 0.2%. Appropriate prophylaxis makes VTE a rare event after modern arthroplasty. The patient factors that raise risk are tabulated under Classification.
Guidelines, Registries & Global Practice
Global epidemiology: Without prophylaxis, venographic DVT occurs in roughly 40–60% after major lower-limb arthroplasty or hip fracture. Modern prophylaxis plus early mobilisation has driven symptomatic VTE after elective THA/TKA to roughly 1% or less at 90 days, with fatal PE now well under 0.5%. The greatest residual burden of fatal PE is in hip-fracture and polytrauma patients.
Side-by-side major guidelines:
- Stance on agent
- No single agent mandated; pharmacological and/or mechanical
- Duration (THA / TKA)
- Surgeon discretion
- Distinctive feature
- Discourages duplex screening of asymptomatic patients
- Stance on agent
- LMWH, DOAC, fondaparinux, VKA, UFH or aspirin all acceptable
- Duration (THA / TKA)
- Min 10–14 days, extend to 35
- Distinctive feature
- Suggests adding IPC to drug prophylaxis
- Stance on agent
- Explicitly endorses aspirin protocols and DOACs
- Duration (THA / TKA)
- THA up to 28–35 days / TKA 14 days
- Distinctive feature
- LMWH-then-aspirin sequence written into guideline
- Stance on agent
- LMWH or DOAC for major lower-limb surgery
- Duration (THA / TKA)
- Extended after THA, shorter after TKA
- Distinctive feature
- Emphasises early mobilisation and individualised bleeding-risk assessment
Joint registries (NJR, AJRR, AOANJRR, SHAR) report symptomatic VTE and 90-day mortality as quality metrics rather than mandating one agent. Pragmatic trials embedded in trauma networks (PREVENT CLOT) and arthroplasty cohorts (EPCAT II) have shifted high-resource practice toward aspirin-based regimens after an initial anticoagulant.
- High-resource: ready access to DOACs, LMWH, mechanical IPC devices and outpatient anticoagulation clinics; cost and patient-satisfaction data increasingly favour aspirin where appropriate.
- Limited-resource: LMWH and DOACs may be unaffordable or cold-chain–limited; aspirin plus aggressive early mobilisation and, where available, graduated compression stockings is a pragmatic, evidence-supported strategy. Mechanical IPC pumps are often scarce, raising the relative importance of chemical prophylaxis and mobilisation.
every surgical patient should have a documented VTE and bleeding-risk assessment, mechanical prophylaxis where pharmacological agents are contraindicated, and a clear discharge plan for extended prophylaxis. Failure to risk-assess and to prescribe extended prophylaxis is a recurrent medicolegal theme worldwide.
Controversies & Areas of Uncertainty
Aspirin versus anticoagulants. EPCAT II and PREVENT CLOT show aspirin is non-inferior for clinically important outcomes, yet PREVENT CLOT found a small excess of mostly distal, often asymptomatic DVT with aspirin. Whether this matters clinically, and in which patients, remains debated.
How long after TKA. Guidelines diverge from 10-14 days (NICE for TKA, and some ACCP options) up to 35 days. The thrombotic burden after TKA is lower than after THA, so the marginal benefit of prolonged prophylaxis after knee replacement is uncertain.
Mechanical-only prophylaxis. For low-risk arthroplasty with rapid mobilisation, some advocate mechanical methods plus aspirin alone. Robust trials isolating the independent contribution of stockings, IPC and chemical agents are lacking.
Risk tools. Caprini and other scores are widely used but were not derived for arthroplasty and have modest discrimination. No universally validated tool exists to individualise agent and duration in elective joint replacement.
Screening. AAOS recommends against duplex screening of asymptomatic patients, yet some units still screen high-risk groups. Treating asymptomatic distal DVT of uncertain significance risks over-anticoagulation.
Distal versus proximal DVT. Isolated distal (calf) DVT detected on surveillance has a low embolic risk. Whether to anticoagulate it, surveil it or ignore it is unresolved and varies by guideline and bleeding risk.
MCQ Practice Points
Q: How long should VTE prophylaxis continue after THA? A: 28-35 days. VTE risk persists beyond hospital discharge. In-hospital only prophylaxis is inadequate.
Q: When should enoxaparin be started after THA? A: 6-12 hours post-operatively. Too early increases bleeding risk. Too late may allow thrombus formation.
Q: What trial supports aspirin for VTE prophylaxis after arthroplasty? A: EPCAT II (NEJM 2018) showed aspirin is non-inferior to rivaroxaban when used to complete extended prophylaxis after initial anticoagulant.
Q: What is the DVT rate after THA without prophylaxis? A: 40-60% VENOGRAPHIC DVT, 1-2% symptomatic PE. Say the word venographic - those were routine-screening studies from the pre-prophylaxis era counting mostly distal, asymptomatic calf thrombi, not a 40-60% risk of symptomatic DVT. With modern prophylaxis, symptomatic VTE after elective THA/TKA is around 1% or less at 90 days.
Q: What is the role of mechanical prophylaxis in VTE prevention? A: Always use mechanical prophylaxis (TED + IPC) as adjunct. Essential for patients with bleeding contraindications. Start IPC intraoperatively.
Q: How do you manage suspected HIT in a post-arthroplasty patient? A: Stop all heparin immediately. Use non-heparin anticoagulant (fondaparinux, argatroban). Check platelet count and 4T score.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are planning a primary THA on a 65-year-old man with no prior VTE history. What is your VTE prophylaxis protocol?”
“A 70-year-old woman is undergoing TKA. She has a history of GI bleeding and is on aspirin for coronary artery disease. How do you manage VTE prophylaxis?”
“Post-operative day 3 after TKA, the patient develops sudden dyspnea and pleuritic chest pain. HR 120, SpO2 88% on room air. What is your approach?”
VTE Risk
- THA/TKA/Hip fracture = very high
- 40-60% VENOGRAPHIC DVT without prophylaxis (mostly distal and asymptomatic, pre-prophylaxis era) - not a 40-60% symptomatic rate
- 1-2% symptomatic PE
- Risk persists 35 days post-op
Prophylaxis Approach
- MCE: Mechanical + Chemical + Extended
- TED + IPC for ALL high-risk
- LMWH is gold standard
- DOACs are equivalent alternatives
Duration
- THA: 35 days
- TKA: 14-35 days
- Hip Fracture: 35 days
- NOT just in-hospital
Timing
- LMWH: 6-12 hrs post-op
- Rivaroxaban: 6-10 hrs post-op
- Start IPC in OR
- TED immediately post-op
Complications
- HIT: Stop heparin, use alternative
- Major bleeding: 1-3%
- Balance VTE vs bleeding risk
- Spinal epidural haematoma with neuraxial anaesthesia
Evidence Base
RECORD1 (Eriksson et al)
- 4541 elective THA patients; rivaroxaban 10mg OD vs enoxaparin 40mg SC OD for 36 days
- Primary composite (DVT, non-fatal PE, all-cause death): 1.1% rivaroxaban vs 3.7% enoxaparin (ARR 2.6%, P less than 0.001)
- Major VTE: 0.2% vs 2.0% (P less than 0.001)
- Major bleeding similar: 0.3% vs 0.1% (P=0.18)
RECORD4 (Turpie et al)
- 3148 TKA patients; rivaroxaban 10mg OD vs enoxaparin 30mg BD for 10–14 days
- Primary composite VTE/death: 6.9% rivaroxaban vs 10.1% enoxaparin (ARR 3.19%, P=0.012)
- Major bleeding 0.7% vs 0.3% (P=0.11, not significant)
- Companion knee-arthroplasty trial to RECORD1
EPCAT I (Anderson et al)
- 778 THA patients; all received dalteparin for 10 days, then randomised to aspirin or dalteparin for a further 28 days
- Symptomatic VTE: 0.3% aspirin vs 1.3% dalteparin — aspirin non-inferior (P less than 0.001)
- Clinically significant bleeding 0.5% aspirin vs 1.3% dalteparin
- Stopped early for slow recruitment but established the lead-in-then-aspirin concept
EPCAT II (Anderson et al)
- 3424 THA/TKA patients; all received rivaroxaban for 5 days, then randomised to aspirin 81mg OD or continued rivaroxaban (30 days THA, 9 days TKA)
- Symptomatic VTE: 0.64% aspirin vs 0.70% rivaroxaban (P less than 0.001 for non-inferiority)
- Major bleeding: 0.47% vs 0.29% (NS); clinically important bleeding 1.29% vs 0.99% (NS)
- Aspirin is a cheap, oral, well-tolerated agent to complete extended prophylaxis
PREVENT CLOT (O'Toole et al)
- 12211 patients with operative extremity fractures or any pelvic/acetabular fracture
- Aspirin 81mg BD vs enoxaparin 30mg BD; primary outcome 90-day all-cause death
- Death 0.78% aspirin vs 0.73% LMWH — aspirin non-inferior
- DVT slightly higher with aspirin (2.51% vs 1.71%); PE identical (1.49% each)
ACCP / CHEST Guidelines (Falck-Ytter et al)
- Extended prophylaxis (minimum 10–14 days, up to 35 days) recommended after THA/TKA/hip fracture
- LMWH, fondaparinux, DOACs, adjusted-dose VKA, low-dose UFH or aspirin all acceptable agents
- Add intermittent pneumatic compression to pharmacological prophylaxis where feasible
- Mechanical-only prophylaxis if high bleeding risk; switch to drug once risk falls
AAOS Clinical Practice Guideline
- All elective THA/TKA patients should receive pharmacological and/or mechanical prophylaxis
- No single agent mandated — surgeon discretion balancing VTE and bleeding risk
- Routine post-operative duplex screening of asymptomatic patients NOT recommended
- Assess for prior VTE which increases risk