Hemimelic epiphyseal osteochondromas | Children, lower limb | Usually one side of one limb
- DEFINITION: a rare, non-hereditary developmental disorder of childhood with osteocartilaginous overgrowth (osteochondroma-like masses) arising from one or more epiphyses, almost always confined to ONE SIDE OF ONE LIMB
- HEMIMELIC MEANS ONE HALF: the medial or lateral half of the epiphysis is affected (medial more often than lateral), and the lesion respects the midline of the limb
- IT IS NOT AN OSTEOCHONDROMA: it shares histology with osteochondroma but is NOT linked to the EXT genes and is NOT part of hereditary multiple exostoses; it is intra-articular and epiphyseal rather than metaphyseal
- MRI IS THE KEY INVESTIGATION: it shows the cartilage cap continuous with epiphyseal cartilage, defines the lesion before the bony nidus ossifies, and plans surgery
- MAIN RISKS IF UNTREATED: progressive deformity, joint incongruity, mechanical block, limb-length discrepancy and early secondary osteoarthritis - marginal excision of symptomatic lesions is the mainstay of treatment
- “Hemimelic = affects medial OR lateral half of an epiphysis, one limb only
- “Most common around the ankle (talus) and knee (distal femur)
- “NOT EXT-related, NOT hereditary multiple exostoses
- “MRI defines the unossified cartilage cap and guides excision
- “Recurrence and secondary OA are the principal long-term concerns
Overview and Epidemiology
Dysplasia epiphysealis hemimelica (DEH), eponymously Trevor disease or Trevor-Fairbank disease, is a rare developmental skeletal disorder defined by asymmetric osteocartilaginous overgrowth of one or more epiphyses in a growing child. The masses behave like osteochondromas but arise from the epiphysis, or from an epiphyseal equivalent such as a carpal or tarsal bone, rather than the metaphysis.
What "hemimelic" means. The word means "half a limb", and the whole pattern follows from it. Picture a line along the long axis of the limb dividing it into medial and lateral halves: the lesion affects the medial or lateral half of an epiphysis, medial more often than lateral, and involvement is almost always limited to one side of one limb, respecting the midline. The lower limb is far more often affected than the upper.
The name. Mouchet and Belot described it in 1926 as "tarsomegalie", a description of the tarsus. Trevor characterised it in the English literature in 1950, and Fairbank, in 1956, coined "dysplasia epiphysealis hemimelica".
Who gets it. It is very rare, with an estimated prevalence of about 1 per 1,000,000, and boys outnumber girls roughly 3:1. It presents in childhood, most often between about 2 and 14 years and often between 2 and 8. The diagnosis frequently follows the appearance of the bony nidus, which can lag behind the cartilage by months to years. No racial or strong geographic predilection has been established, given the rarity.
Where. The lower limb dominates:
- Ankle and hindfoot: the talus is the single most frequently reported site, especially in foot-and-ankle series
- Knee: the distal femoral and proximal tibial epiphyses are very commonly involved
- Others: the tarsals (navicular, cuneiforms), distal tibia and patella are also reported
- Upper limb and spine: rare but recognised
A systematic review of foot-and-ankle DEH by Artioli and colleagues pooled 70 patients (mean age 9.6 years, predominantly male) and found the talus the most common location, with a mass and pain the typical presentation (DOI).
Aetiology. The cause is unknown. DEH is a sporadic, non-hereditary developmental disorder of localised cartilage regulation, in which a focus of epiphyseal cartilage escapes normal growth control and forms an osteochondroma-like mass. Three negatives are what examiners test, and it is not "multiple hereditary exostoses":
- Not familial: there is no Mendelian inheritance pattern and no established family clustering
- Not EXT-related: unlike solitary osteochondroma and hereditary multiple exostoses, DEH is not associated with mutations in the EXT1/EXT2 genes
- Not a true neoplasm of the metaphysis: the lesion is epiphyseal and intra-articular
Degnan and Ho-Fung's contemporary imaging review stresses that, although DEH was once conceptualised as "epiphyseal osteochondromatosis", its lesions differ from osteochondromas (DOI).
Pathophysiology and Anatomy
The lesion. DEH is best understood as a disorder of localised epiphyseal cartilage proliferation. A focus of chondrocytes within the epiphysis loses normal growth restraint and proliferates, producing a cartilage-capped mass that undergoes enchondral ossification from within. That is the mechanism of an osteochondroma, originating in the epiphysis.
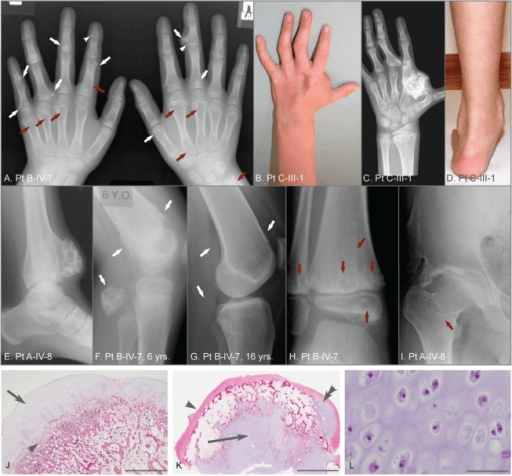
Histology. The lesion is histologically indistinguishable from an osteochondroma: a cartilage cap of disorganised but cytologically benign chondrocytes over a bony stalk or nidus, with a zone of enchondral ossification at the base. Because the histology is benign and non-specific, the diagnosis is clinical and radiological, not histological.
Behaviour. Like an osteochondroma, the lesion grows with the child and tends to stop enlarging at skeletal maturity. As it grows it can distort the joint surface, create a mechanical block, stretch the capsule and ligaments, and cause angular deformity or limb-length discrepancy. Long-standing joint incongruity predisposes to secondary osteoarthritis in adult life.
Why these sites. The talus, distal femur and proximal tibia carry large, actively growing epiphyses around the knee and ankle, where most reported lesions occur. An intra-articular, epiphyseal location means the mass projects toward the joint, hence the early presentation with a hard juxta-articular swelling, restricted movement and joint-line catching.
Surgical anatomy. The neighbours of the mass are the structures at risk during excision:
- Ankle, medial: close to the deltoid ligament, the posterior tibial tendon and the neurovascular bundle
- Ankle, lateral: threatens the lateral ligament complex and the talar dome articular cartilage
- Knee: femoral condyle and tibial plateau lesions sit beneath the menisci and collateral ligaments and may abut the cruciates
Classification
The most widely cited classification is by Azouz et al (1985). It grades DEH by the extent of skeletal involvement and correlates loosely with prognosis:
- Localised: a single epiphysis or one ossification centre, for example one tarsal bone or one femoral condyle. Best prognosis.
- Classical: more than one epiphysis within a single lower limb, for example distal femur plus talus on the same side. The typical, most common pattern.
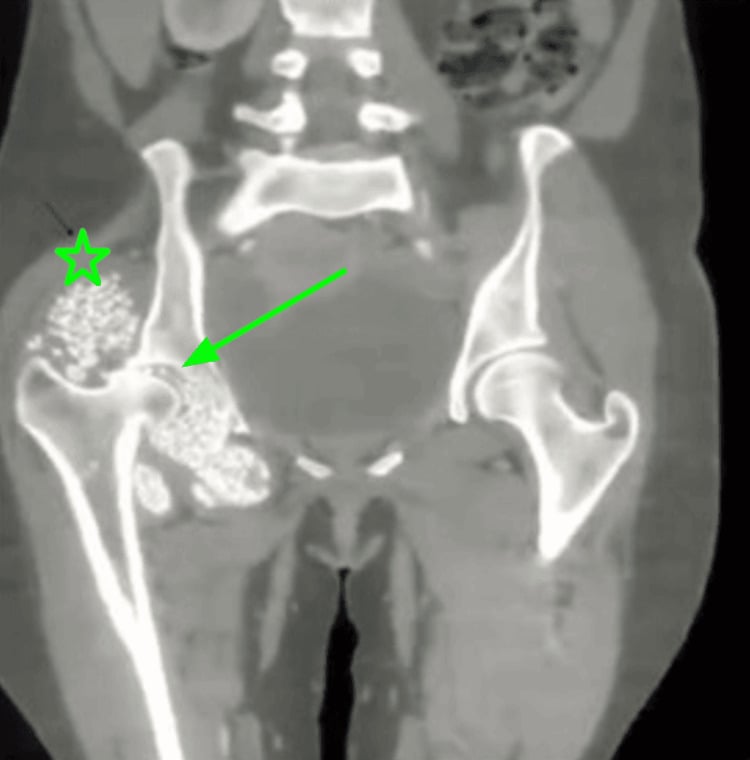
- Generalised: the entire lower limb from the pelvis to the foot, sometimes with megaepiphyses (enlargement of a whole epiphyseal centre). Worst prognosis, with the greatest deformity and functional burden.
Azouz and colleagues studied 24 patients, adding 15 new cases, and also described advanced bone age and metaphyseal or growth-plate involvement in some cases (DOI).
Clinical Presentation
History. The classic patient is a young child with a painless or mildly painful hard lump near a joint of one limb, usually noticed by a parent. Artioli's review found a mass and pain were the presenting features in 54% of cases (DOI). The history fills in the rest:
- A firm swelling around the ankle or knee, often present for months to years
- Pain in roughly half of patients, often mechanical and worse with activity
- A limp, angular or rotational deformity, or a leg-length difference noticed over time
- Restricted or catching movement, or a feeling of the joint "locking" when the mass blocks motion
- One limb only: bilateral or midline-crossing involvement should make you doubt the diagnosis
Examination. The mass is hard, bony, and non-tender or mildly tender, fixed to the epiphyseal region, typically on the medial or lateral side rather than circumferential. It is continuous with bone and does not move independently. Look for angular deformity (valgus or varus at the ankle or knee), limb-length discrepancy, and muscle wasting if the joint has been painful or stiff for some time.
Movement and stability. Range of motion is reduced, and there may be a hard mechanical block or catching at the extreme of movement. Test joint stability, because a large lesion can stretch or deform the collateral ligaments.
Always. Examine the whole limb and the opposite side, to confirm the unilateral pattern and screen for additional sites. Document a baseline neurovascular examination, especially at the ankle, where a medial mass lies near the tarsal-tunnel structures.
Investigations
Imaging is central to the diagnosis and to distinguishing DEH from more sinister lesions, as the review by Tyler and colleagues emphasises (DOI).
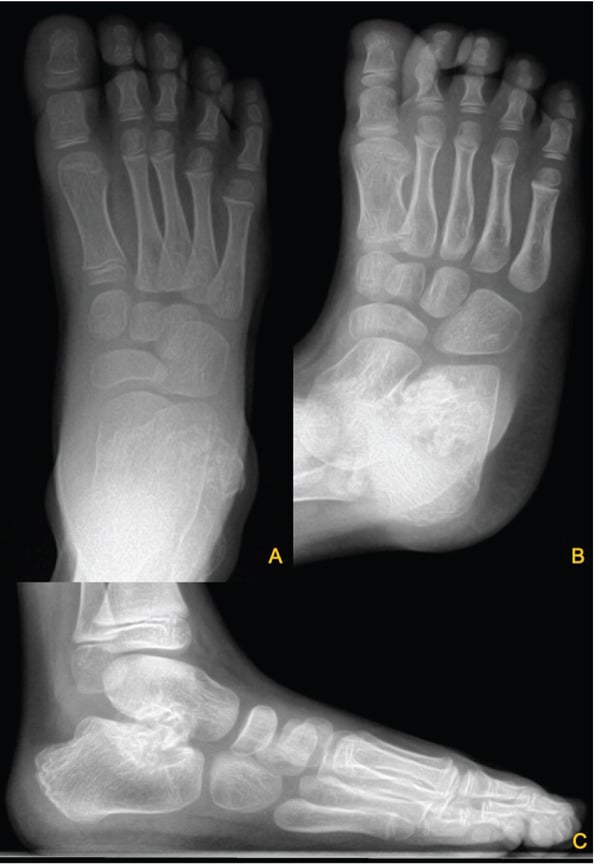
Radiographs. AP and lateral films are the first-line investigation and are often diagnostic once the lesion ossifies. They show an irregular, lobulated ossified mass arising from the epiphysis on one side of the joint, continuous with the epiphysis and sometimes containing multiple ossific foci that coalesce with time. Joint-surface distortion, angular deformity and sometimes an advanced bone age in the affected epiphysis complete the picture.
Early in the disease the cartilaginous lesion may be radiographically occult until the ossific nidus appears, so a normal radiograph does not exclude DEH in a young child.
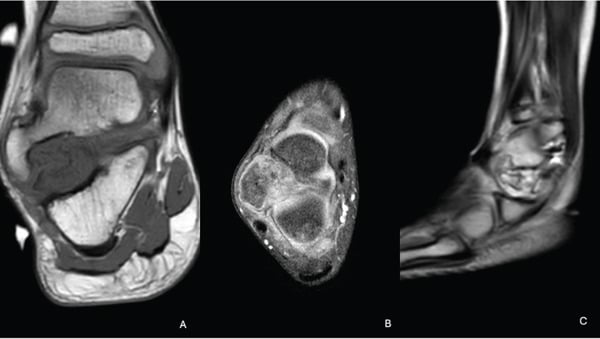
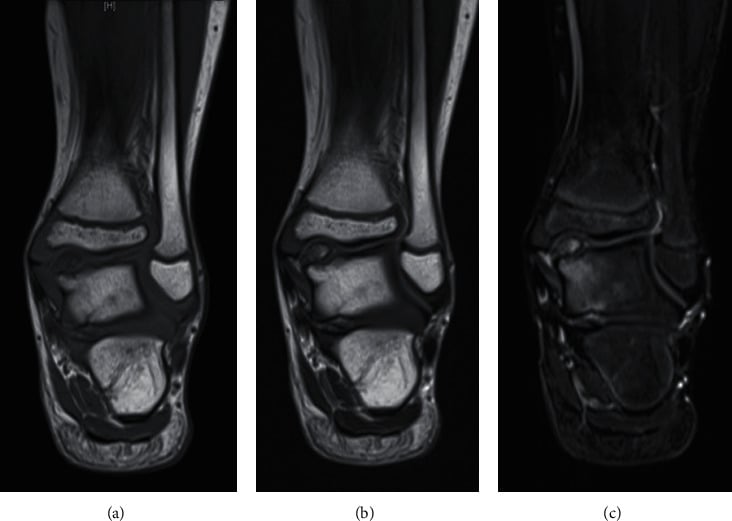
MRI. The single most useful investigation, favoured over CT in children to avoid radiation. It does four things:
- Shows the cartilage cap continuous with the epiphyseal cartilage, the diagnostic feature
- Detects the lesion before the bony nidus ossifies, when radiographs are normal
- Maps the lesion's relationship to the articular surface, physis, ligaments and neurovascular structures for surgical planning
- Helps distinguish DEH from sinister lesions and from synovial chondromatosis
The imaging reviews by Tyler et al and by Degnan and Ho-Fung both place MRI at the centre of characterising the cartilage cap, defining unossified disease and planning management (DOI; DOI).
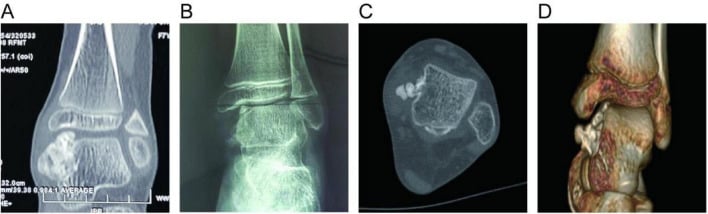
CT. Useful for bony anatomy and operative planning in complex tarsal or articular lesions, and for showing the ossified nidus in three dimensions. Weigh the radiation dose in a child.
Whole-body bone scintigraphy or skeletal survey. Screens for additional, clinically silent epiphyseal sites, including upper-limb or axial lesions. Additional sites change the Azouz or Arealis type and therefore the prognosis, which is why Arealis recommended a whole-body bone scan once DEH is confirmed.
Biopsy. Not routinely required. The histology is identical to an osteochondroma, so biopsy is reserved for atypical presentations in which a more aggressive lesion must be excluded.
Differential Diagnosis
The mimics are synovial chondromatosis, intra-articular chondroma and, rarely, a chondral or parosteal lesion. MRI together with the typical age and the hemimelic epiphyseal pattern usually settles it; atypical features, such as cortical destruction, a soft-tissue mass or rapid growth, prompt MRI and, if doubt remains, biopsy.
- Key differences from DEH
- Key differences from DEH: arises from the METAPHYSIS with cortex and medulla continuous with the parent bone; EXT1/EXT2-related; the multiple form is hereditary
- Clue that settles it
- Clue that settles it: DEH is epiphyseal and intra-articular, hemimelic, confined to one limb, non-EXT and non-hereditary
- Key differences from DEH
- Key differences from DEH: multiple similarly-sized cartilaginous bodies within the synovium and joint, not arising from the epiphyseal bone; typically older patients
- Clue that settles it
- Clue that settles it: DEH is a mass continuous with the epiphysis - a child with one hemimelic epiphyseal mass, not scattered loose bodies
- Key differences from DEH
- Key differences from DEH: a surface or juxtacortical CARTILAGE tumour without the hemimelic epiphyseal pattern
- Clue that settles it
- Clue that settles it: the DEH cartilage cap is CONTINUOUS WITH EPIPHYSEAL CARTILAGE on MRI and respects a limb half
- Key differences from DEH
- Key differences from DEH: a parosteal, surface-based osteocartilaginous mass of the hands or feet with NO cortico-medullary continuity and 'blue bone' histology
- Clue that settles it
- Clue that settles it: DEH is EPIPHYSEAL, confined to one limb, and continuous with the epiphysis - not a surface lesion of a tubular bone
- Key differences from DEH
- Key differences from DEH: Older patients, cortical destruction, an ill-defined soft-tissue mass or rapid growth
- Clue that settles it
- Clue that settles it: atypical features prompt MRI and, if needed, biopsy - DEH is benign, slow-growing and histologically bland
Uncommon Sites: Upper Limb, Carpal/Tarsal and Spine
These are the presentations in which the diagnosis is missed.
Epiphyseal equivalents. The carpal and tarsal bones ossify from a single centre, so each behaves as an epiphyseal equivalent and can host a DEH lesion. That is why the talus and tarsals are such classic sites, and why tarsomegaly, an enlarged and deformed tarsal bone, is a recognised presentation.
Upper limb (Arealis types 3-4). Lesions of the distal radial or ulnar epiphysis or of the carpus produce a hard juxta-articular wrist mass, a radial or ulnar deviation deformity and reduced forearm and wrist motion; at the elbow or shoulder they restrict movement. They are easily mistaken for osteochondroma, and the hemimelic, one-limb, epiphyseal pattern and MRI settle it.
Spine (Arealis type 6). Exceptionally rare. Epiphyseal-equivalent overgrowth from a vertebral element can encroach on the canal or a neural foramen, compressing the cord or a root, or drive a deformity or scoliosis. MRI is essential to map the cartilage and any neural compromise, and the symptomatic lesion is treated by excision or decompression.
Management Algorithm
Principles. Because the condition is so rare there is no high-level evidence and no standardised protocol, and management is symptom-driven and individualised. Small, quiet lesions are watched; symptomatic ones are excised. In Artioli's review surgery was chosen in 92% of patients, 95% of whom underwent mass excision, which reflects that most reported cases are symptomatic enough to operate on (DOI).
Observation. For incidental or small lesions with minimal symptoms, no deformity or mechanical block, and a well-aligned, stable, congruent joint:
- Clinical and radiographic surveillance at intervals, for example 6-12 monthly, until skeletal maturity
- Physiotherapy to maintain range of motion and strength; analgesia for mild mechanical pain
- Activity modification and footwear or orthotic adjustment for foot-and-ankle lesions
The counselling point. Observation is reasonable, but vigilance is essential. A lesion left to enlarge can damage the joint surface and make eventual excision and reconstruction far more difficult, and the systematic review cautions that unchecked mass growth complicates later surgical intervention (DOI).
Indications for surgery.
- Significant or progressive pain
- Mechanical block or locking
- Angular deformity or joint incongruity
- Instability
- Limb-length problems
- Cosmetic or functional concern
- Progressive growth threatening the articular surface
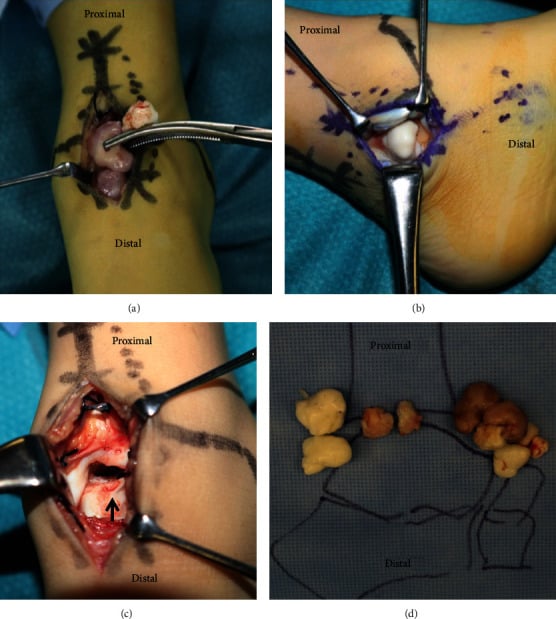
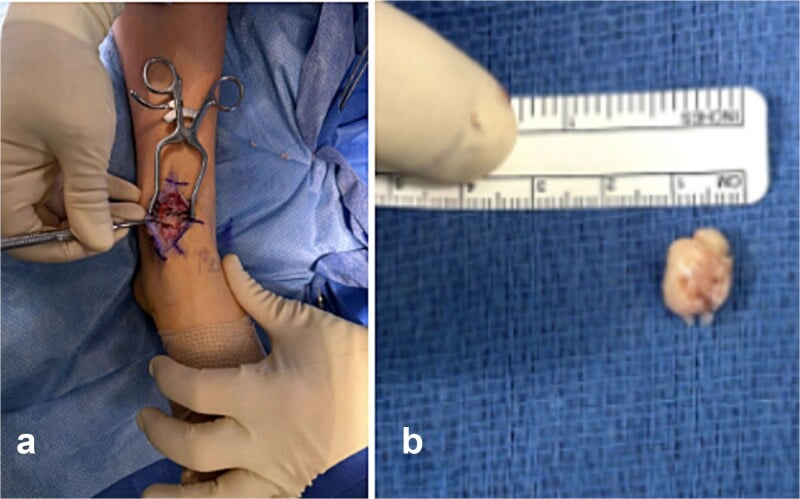
Goals. Marginal excision of the osteocartilaginous mass, including the cartilage cap, relieves symptoms and reduces recurrence. The operation also aims to restore a congruent, smooth articular surface, correct deformity by osteotomy, address any limb-length discrepancy, and preserve the physis and articular cartilage.
Timing. Excision is feasible even in young children and may be done early when a lesion is enlarging or causing deformity. The systematic review adds that it requires precision to avoid recurrence or secondary arthritis (DOI).
Surgical Technique
Marginal excision. Intralesional-to-marginal excision is the workhorse procedure:
- Use a direct approach centred on the lesion, for example a medial approach for a medial talar or distal tibial lesion, protecting the nearby tendons, ligaments and neurovascular bundle
- Expose the mass at its base and excise it flush with the parent epiphysis, removing the cartilage cap as completely as is safely possible; residual cap is the main source of recurrence
- Protect the articular cartilage and physis: do not violate the growth plate, whose damage risks iatrogenic arrest and deformity, and preserve as much joint surface as possible
- Smooth the remaining contour to restore joint congruity, and remove any intra-articular loose fragments
- Address ligament instability
When complete excision is unsafe. It is not always achievable when the lesion is intimately related to the joint surface or physis. The systematic review and Arealis et al both note that even partial excision can be a successful, symptom-relieving treatment (DOI).
Deformity. Once the symptomatic mass has been addressed, established angular deformity is treated by corrective osteotomy, for example supramalleolar or distal femoral. Guided growth (hemiepiphysiodesis or tension-band plating) can be used for progressive angular deformity in a child with substantial growth remaining.
Limb-length discrepancy. Managed along standard lines: a shoe raise for small differences, and contralateral epiphysiodesis or lengthening for larger ones near maturity.
Salvage. A severely incongruent, arthritic joint in an older patient may need realignment osteotomy, and rarely arthrodesis for a painful, destroyed joint. Large or complex articular and tarsal lesions benefit from CT-based planning and, where available, intra-articular techniques to preserve cartilage.
Complications
Natural history. Left untreated, or growing unchecked, the lesion produces:
- Progressive angular (valgus or varus) and rotational deformity
- Joint incongruity and mechanical block, with stiffness and locking
- Limb-length discrepancy from asymmetric epiphyseal growth
- Joint instability as the mass deforms or stretches the collateral ligaments, especially at the ankle
- Secondary early osteoarthritis in adolescence or adult life, the most important long-term consequence
Degnan and Ho-Fung emphasise that DEH may result in pain, growth disturbance and early osteoarthritis, which is why timely treatment of symptomatic lesions matters (DOI).
Recurrence. The most frequent surgical complication, driven by incomplete excision of the cartilage cap, especially in the still-growing child. Artioli's review reported it in about 9% of cases (DOI).
Other surgical complications.
- Iatrogenic growth-plate injury, with arrest and progressive deformity, if the physis is violated
- Articular cartilage damage and accelerated joint degeneration
- Neurovascular or tendon injury during exposure, for example around the medial ankle
- Residual deformity or instability if alignment and ligaments are not addressed
- Infection, wound problems and stiffness
Surgery here is technically demanding and not without morbidity: the paediatric series by Oberc and colleagues observed late complications in two of four operated patients (50%) ([DOI not available]; PMID 24941028).
Postoperative Care and Rehabilitation
Early. Protect the joint with a period of splint or cast immobilisation or protected weight-bearing, chosen by the site, the extent of excision and any osteotomy. Check the neurovascular status after ankle and knee procedures, and provide wound care and standard infection surveillance.
Rehabilitation. Progressive range-of-motion work begins once the soft tissues have settled, to prevent stiffness in a joint that was often already stiff before surgery. Strengthening and gait re-education follow, particularly after deformity correction or osteotomy, and osteotomy and guided-growth cases follow standard bony-healing and alignment protocols before unrestricted activity.
Surveillance to maturity. This is the most important part of aftercare. The lesion can recur while the child is still growing and new deformity can develop, so follow-up continues until skeletal maturity:
- Periodic clinical and radiographic review, confirming that any deformity correction is maintained as the child grows
- Tracking of range of motion, strength, gait and limb length
- Prompt imaging of any new pain, swelling or deformity
- Counselling the family that recurrence and the late risk of osteoarthritis make this a long-term relationship, not a one-off
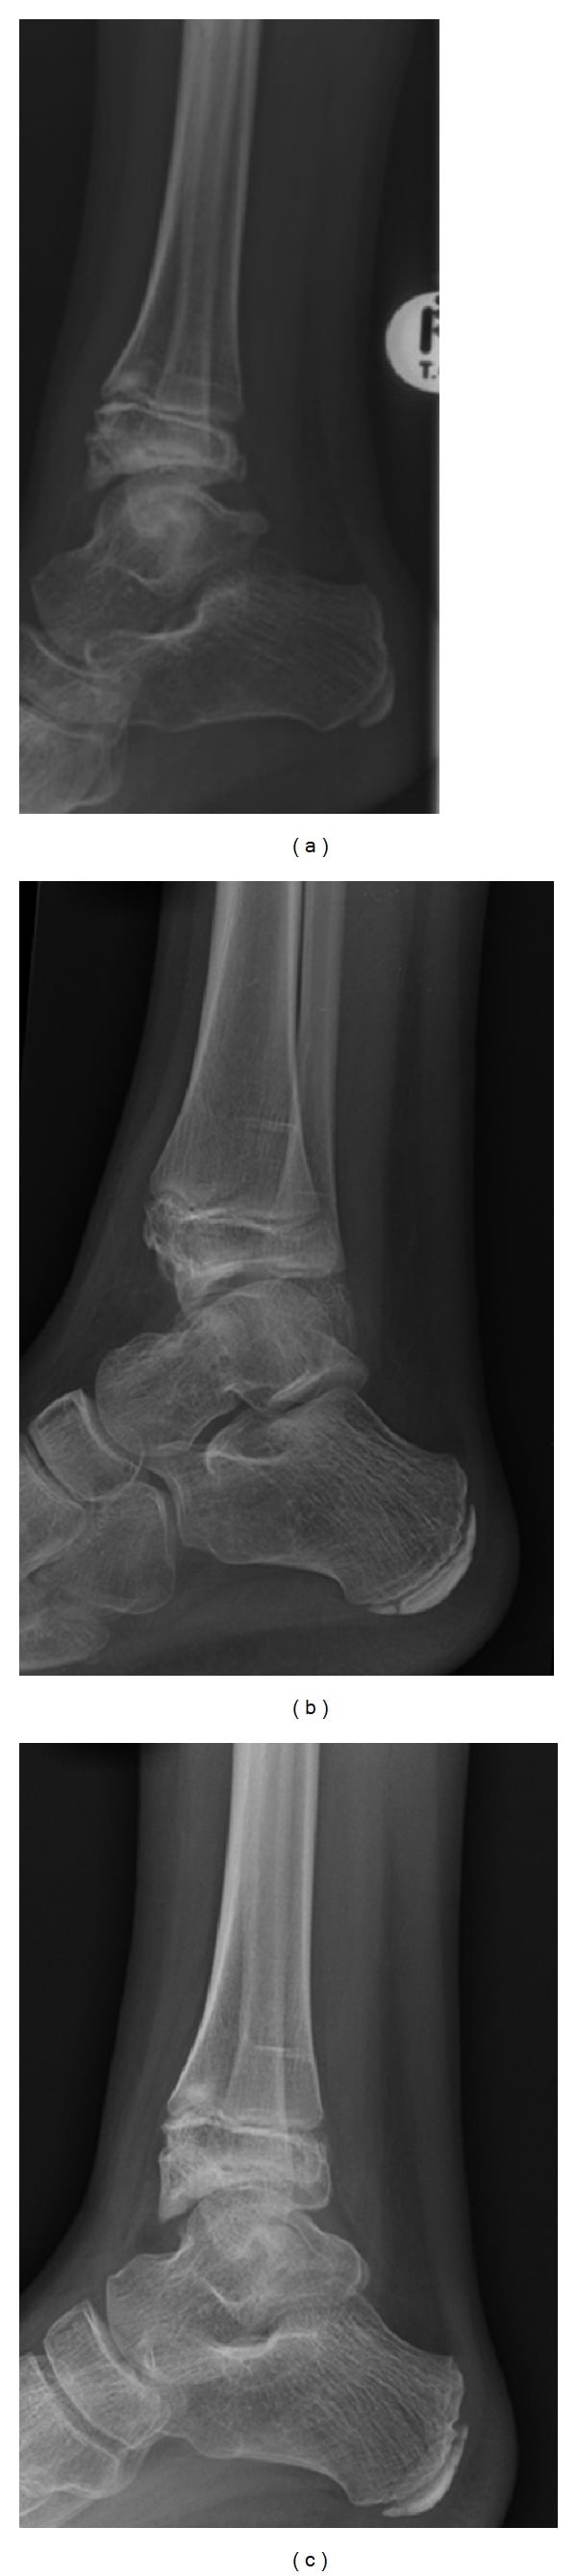
Outcomes and Prognosis
Extent sets the prognosis. The general prognosis is good for localised, single-limb disease treated appropriately, and it worsens with the extent of involvement:
- Localised (Azouz) or type 1 (Arealis): best outcome, with the lowest risk of osteoarthritis even without resection
- Classical, multi-epiphysis disease: more deformity, and a higher likelihood of needing surgery and developing secondary osteoarthritis
- Generalised disease: the greatest functional burden, more staged procedures and the highest osteoarthritis risk
After surgery. Resection, even partial, is usually successful in relieving symptoms; complete excision is ideal but not always possible near the joint surface or physis. Recurrence is common during growth and falls after skeletal maturity.
The long view. The dominant long-term concern is secondary osteoarthritis from joint incongruity. That is why restoring a congruent, well-aligned joint matters more than simply removing a lump.
Guidelines, Registries & Global Practice
Global epidemiology:
- A very rare developmental disorder (about 1 per 1,000,000), with a male predominance (~3:1) and presentation in childhood
- Lower-limb predominance, with the talus and knee epiphyses most often affected; upper limb and spine are uncommon
- No strong racial or geographic predilection has been established given the rarity
Side-by-side principles (consistent across the literature):
- There is no formal national guideline for Trevor disease because of its rarity; practice is driven by case series and systematic reviews (Azouz; Arealis; Artioli; imaging reviews by Tyler and by Degnan/Ho-Fung)
- Diagnosis: clinical pattern plus radiographs and MRI; MRI is universally favoured for the cartilage cap and unossified disease, and to avoid radiation in children
- Classification: the Azouz localised/classical/generalised scheme is the standard reference, with the Arealis six-type system offered as a prognostic refinement
- Treatment: observation for small asymptomatic lesions and marginal excision for symptomatic disease are the globally accepted approaches, with deformity correction (osteotomy or guided growth) as needed
Registry note: Trevor disease is a rare paediatric developmental dysplasia and is not captured by arthroplasty/implant registries (NJR, AJRR, AOANJRR, SHAR, NZJR). The evidence base is single-centre series and pooled literature reviews, not registry data.
High- vs limited-resource variation:
- In well-resourced settings, MRI and CT-based planning, guided-growth implants and intra-articular techniques allow earlier, joint-preserving treatment
- In limited-resource or remote settings, late presentation with larger lesions and established deformity is more common, and treatment relies on excision with simpler imaging and fixation
- Because the condition is rare, referral to a paediatric orthopaedic centre improves diagnosis and outcomes everywhere
MCQ Practice Points
The following points are frequently tested in Orthopaedic exams on Trevor disease.
Q: What does the term "hemimelic" describe in dysplasia epiphysealis hemimelica?
A: It means half a limb - the lesion affects the medial or lateral half of an epiphysis (medial more often than lateral) and is essentially confined to one side of one limb, respecting the midline. Bilateral or midline-crossing disease should prompt you to question the diagnosis.
Q: How does Trevor disease differ from a solitary osteochondroma?
A: The histology is identical (a cartilage-capped bony mass), but DEH is epiphyseal/intra-articular (osteochondroma is metaphyseal), is unilateral within one limb, is sporadic and non-hereditary, and is not associated with EXT1/EXT2 mutations or hereditary multiple exostoses.
Q: Which sites are most commonly affected?
A: The lower limb dominates - the talus (most common single site, especially in foot-and-ankle series) and the distal femur / proximal tibia around the knee. Tarsals, distal tibia and the patella are also reported; upper limb and spine are rare.
Q: What is the single most useful investigation and why?
A: MRI. It shows the cartilage cap continuous with epiphyseal cartilage (the diagnostic feature), detects the lesion before the bony nidus ossifies when radiographs are normal, and maps the lesion to the joint surface, physis and neurovascular structures for surgery.
Q: What is the Azouz classification?
A: Localised (one epiphysis), classical (more than one epiphysis in a single lower limb - the typical pattern), and generalised (whole limb pelvis-to-foot, sometimes with megaepiphyses). Prognosis worsens from localised to generalised.
Q: What is the mainstay of treatment for a symptomatic lesion?
A: Marginal excision of the osteocartilaginous mass, including the cartilage cap, while protecting the physis and articular cartilage. Small asymptomatic lesions can be observed. Deformity is corrected with osteotomy or guided growth, and limb-length discrepancy managed along standard lines.
Q: What is the most common complication after surgery, and what is the key long-term concern?
A: Recurrence (about 9% in foot-and-ankle disease, from incomplete removal of the cartilage cap during growth) is the most common surgical complication. The key long-term concern is secondary (early) osteoarthritis from joint incongruity.
Summary
Trevor disease (dysplasia epiphysealis hemimelica) is a rare, sporadic developmental disorder in which osteochondroma-like cartilage-capped masses grow from one or more epiphyses on one side of one limb in a child. It is hemimelic (medial or lateral half), epiphyseal/intra-articular, and crucially not EXT-related and not hereditary - this is how it differs from osteochondroma and hereditary multiple exostoses.
Key diagnostic points:
- Young child (male predominance) with a hard, fixed juxta-articular mass on one limb, most often the talus or knee
- MRI is the key investigation, showing the cartilage cap continuous with epiphyseal cartilage and detecting unossified disease
Classification:
- Azouz: localised, classical, generalised (prognosis worsens with extent)
- Arealis: a six-type, prognosis-correlated scheme (type 1 single lower-limb lesion does best)
Management:
- Observe small, asymptomatic lesions with surveillance
- Marginal excision (including the cartilage cap, protecting physis and joint surface) for symptomatic disease, with osteotomy or guided growth for deformity; even partial excision can succeed
Critical exam points: name the hemimelic, one-limb, epiphyseal pattern; distinguish it firmly from osteochondroma/EXT disease; use MRI; treat symptomatic lesions by marginal excision; and counsel about recurrence during growth (~9%) and the long-term risk of secondary osteoarthritis, following the child until skeletal maturity.
Exam Day Cheat Sheet
Must-Know Definition
- Dysplasia epiphysealis hemimelica (Trevor disease): a rare, sporadic developmental disorder with osteochondroma-like masses arising from one or more EPIPHYSES
- Hemimelic means the medial OR lateral half of an epiphysis - essentially one side of one limb
- Not EXT-related, not hereditary, not metaphyseal - this is how it differs from osteochondroma
- Childhood onset, male predominance of about 3:1, lower-limb dominant
Sites & Classification
- Most common sites: the talus (ankle) and the distal femur or proximal tibia (knee)
- Azouz classification: localised (one epiphysis), classical (more than one epiphysis in one limb), generalised (whole limb, megaepiphyses)
- Prognosis worsens from localised to generalised
- Arealis six-type scheme: type 1 (single lower limb) has the best prognosis
Investigations
- Radiographs: a lobulated ossified epiphyseal mass on one side of the joint, with deformity
- MRI is the key test: it shows the cartilage cap continuous with epiphyseal cartilage, detects unossified disease, and plans surgery
- CT for complex bony or tarsal planning; bone scan or skeletal survey to find clinically silent sites
- Biopsy is not routine - the histology mirrors osteochondroma, so reserve it for atypical cases
Management Principles
- Observe small, asymptomatic lesions, with vigilant surveillance
- Marginal excision for pain, deformity, mechanical block, instability or progressive growth
- Remove the cartilage cap while protecting the physis and the articular cartilage
- Correct deformity by osteotomy or guided growth, and address limb-length discrepancy
- Even partial excision can succeed when complete removal is unsafe near the joint
Complications (High Yield)
- Recurrence (about 9% in foot-and-ankle disease), from residual cartilage cap during growth
- Secondary early osteoarthritis - the key long-term concern, arising from joint incongruity
- Angular deformity and limb-length discrepancy from asymmetric epiphyseal growth
- Iatrogenic physeal injury or arrest if the growth plate is violated
- Neurovascular, tendon or articular cartilage injury at surgery
Viva Scenario Approach
- State the hemimelic, one-limb, epiphyseal pattern up front
- Separate it from osteochondroma and hereditary multiple exostoses - it is not EXT-related
- Order MRI to show the cartilage cap and plan surgery
- Choose between observation and marginal excision based on symptoms and deformity
- Counsel about recurrence during growth and the long-term osteoarthritis risk
- Commit to follow-up until skeletal maturity
Quick Exam Tips
- Hemimelic = one half of an epiphysis, one limb only
- Talus and knee epiphyses are the commonest sites
- MRI shows the cartilage cap continuous with epiphyseal cartilage
- Azouz = localised / classical / generalised
- Marginal excision for symptomatic lesions; observe the quiet ones
- Recurrence ~9%; early OA is the main long-term risk
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 6-year-old boy is brought in with a hard lump on the inner side of his right ankle, present for over a year and now mildly painful with sport. The left ankle is normal. On examination there is a firm, non-mobile, bony mass over the medial distal tibia/talus with slightly reduced ankle dorsiflexion. How would you approach this?”
“An 8-year-old girl has confirmed Trevor disease of the distal femoral epiphysis. Over 12 months she has developed a 10-degree valgus deformity at the knee, increasing pain, and catching on deep flexion. What factors guide your decision, and what would you do?”
“A 5-year-old boy had marginal excision of a medial talar Trevor lesion 18 months ago. He now returns with a recurrent medial ankle swelling and early valgus. Radiographs confirm a recurrent ossified epiphyseal mass. How do you manage this?”
Evidence Base
Unveiling dysplasia epiphysealis hemimelica in the foot and ankle: a systematic review
- 25 publications, 70 patients (53 male, 16 female), mean age 9.6 years
- Talus was the most common location; mass and pain were the presentation in 54%
- Surgery in 92% of patients, mass excision in 95% of those operated
- Recurrence was the most frequent complication, about 9% of cases
The variable manifestations of dysplasia epiphysealis hemimelica
- Series of 24 patients with 15 new cases added to the literature
- Proposed the localised, classical and generalised subdivision still used today
- Generalised disease may show megaepiphyses (enlargement of a whole epiphyseal centre)
- Described advanced bone age and metaphyseal/growth-plate involvement in some cases