The Musician's Nerve (Fine Motor Control)
- Originates from Medial Cord (C8-T1)
- Passes POSTERIOR to Medial Epicondyle
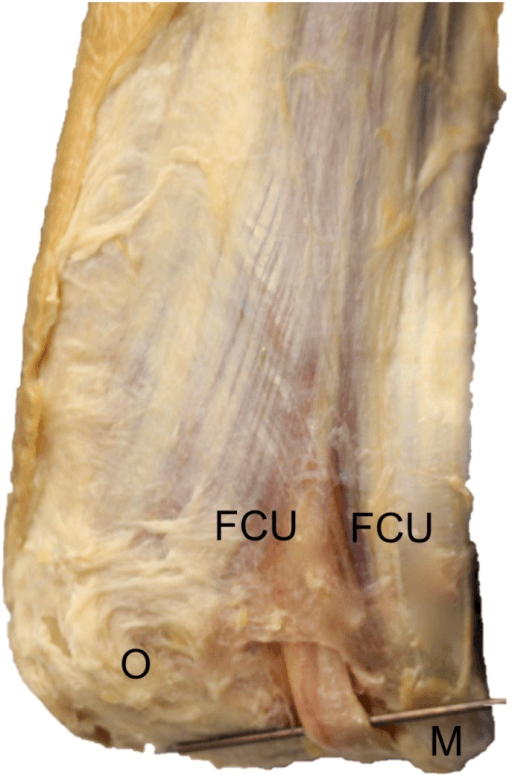
- Enters forearm between two heads of FCU
- Supplies all intrinsics EXCEPT LOAF (Lumb 1/2, Opponens, AbdPB, FlexPB)
- Sensory to medial 1.5 fingers
- “Ulnar Paradox: High lesions claw LESS than low lesions (FDP paralysis)
- “Froment's Sign tests Adductor Pollicis (Ulnar), compensation by FPL (Median/AIN)
- “Struthers Arcade is in the ARM (Ulnar), Struthers Ligament is Supracondylar (Median)
- “Martin-Gruber Anastomosis: Median → Ulnar communication in forearm
Overview and Function
The ulnar nerve is the nerve of fine manipulation. It powers the intrinsic muscles behind grip strength, pinch and complex finger movements, and power grip relies heavily on ulnar-innervated intrinsic function to stabilise the MCP joints. The profound impact of this innervation is seen in the intrinsic-minus hand.
Where it is caught. The cubital tunnel at the elbow is the commonest site of compression, and Guyon's canal at the wrist is the second.
Motor supply. In the forearm the nerve supplies flexor carpi ulnaris and the ring and little finger portions of FDP, one and a half muscles between them, which flex the wrist and digits 4 and 5. In the hand it supplies most of the intrinsics:
- Hypothenar muscles - abductor, flexor and opponens digiti minimi
- Interossei - the palmar interossei (3), which adduct, and the dorsal interossei (4), which abduct
- Lumbricals 3 and 4, the medial two
- Adductor pollicis, the muscle Froment's sign tests
- Deep head of flexor pollicis brevis
LOAFExceptions (Median Supplied)
Hook:Median nerve supplies the LOAF, Ulnar supplies the rest.
Sensory supply comes through three branches:
- Palmar cutaneous branch - arises proximal to the wrist and supplies the hypothenar eminence
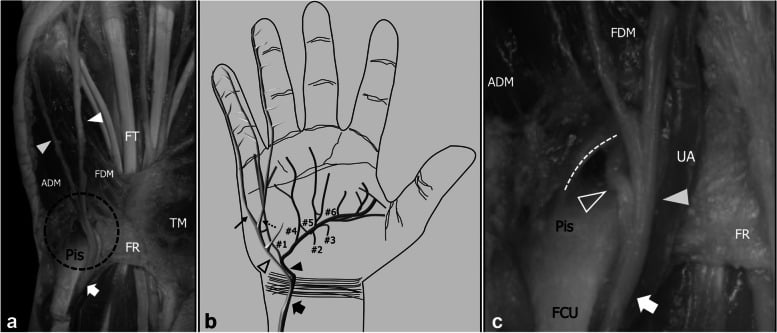
- Dorsal cutaneous branch - arises about 5 cm proximal to the wrist, passes dorsal to FCU and supplies the dorsal medial hand
- Superficial (terminal) branch - supplies the volar little finger and the ulnar half of the ring finger
Course and Relations
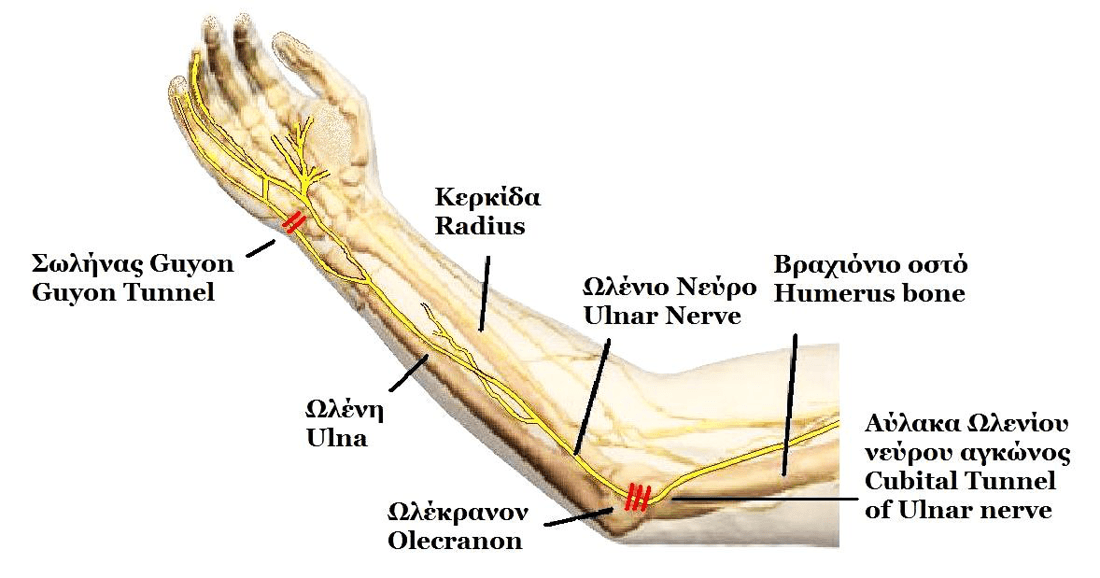
Axilla and arm. The ulnar nerve is a terminal branch of the medial cord (C8, T1) and often receives C7 fibres from the lateral cord. It lies medial to the axillary and brachial arteries and runs at first in the anterior compartment. At mid-arm it pierces the medial intermuscular septum into the posterior compartment and runs distally towards the groove behind the medial epicondyle. This proximal course is relatively safe from compression.
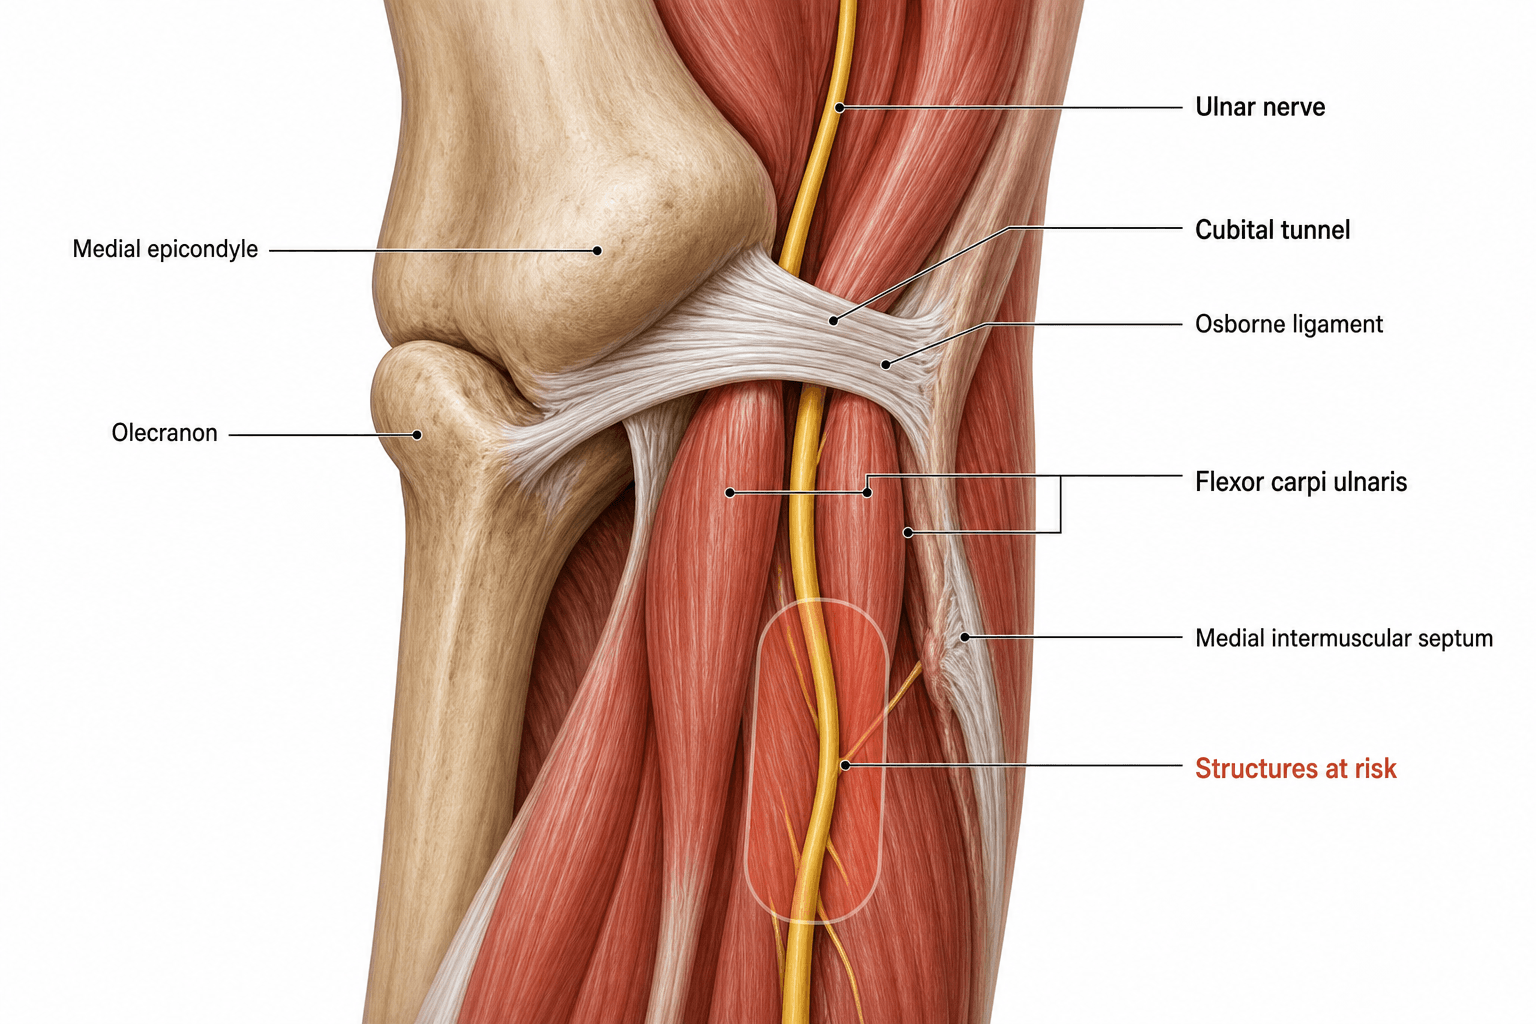
The elbow. The nerve passes posterior to the medial epicondyle in the retrocondylar groove and enters the cubital tunnel, a fibro-osseous tunnel, which it leaves to enter the forearm between the humeral and ulnar heads of flexor carpi ulnaris.
The boundaries of the cubital tunnel:
- Roof - the cubital tunnel retinaculum (Osborne's, or arcuate, ligament), taut in flexion
- Floor - the MCL (ulnar collateral ligament), its posterior bundle, and the capsule
- Anterior - medial epicondyle
- Posterior - medial head of triceps
- Lateral - olecranon
Why flexion matters. Elbow flexion increases intraneural pressure, elongates the nerve by 4-7 mm and reduces the volume of the tunnel by 50%. Hence splinting in extension is effective, and this dynamic compression explains why symptoms are worse at night.
Five sites of compression. From proximal to distal, these are the layers a complete decompression releases:
- Arcade of Struthers - a band of fascia about 8 cm proximal to the medial epicondyle; a potential compression site, especially after transposition
- Medial intermuscular septum, where the nerve passes through it
- Cubital tunnel retinaculum (Osborne's ligament)
- Aponeurosis of FCU, as the nerve enters between the two heads
- Deep flexor-pronator aponeurosis, as the nerve exits
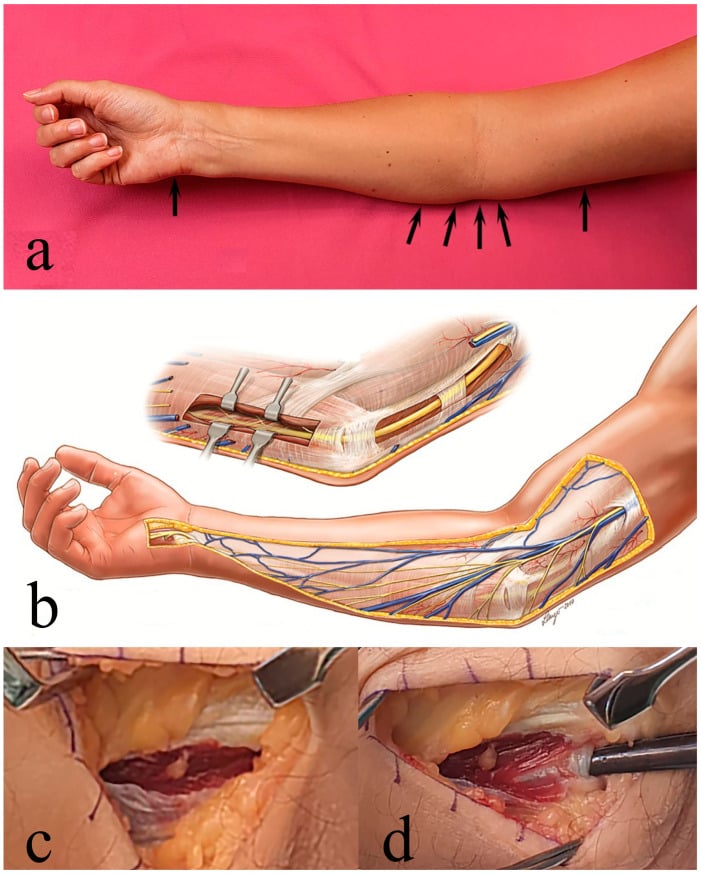
The forearm. Beyond FCU the nerve lies on FDP and is joined by the ulnar artery in the distal two-thirds, then gives off the dorsal cutaneous branch.
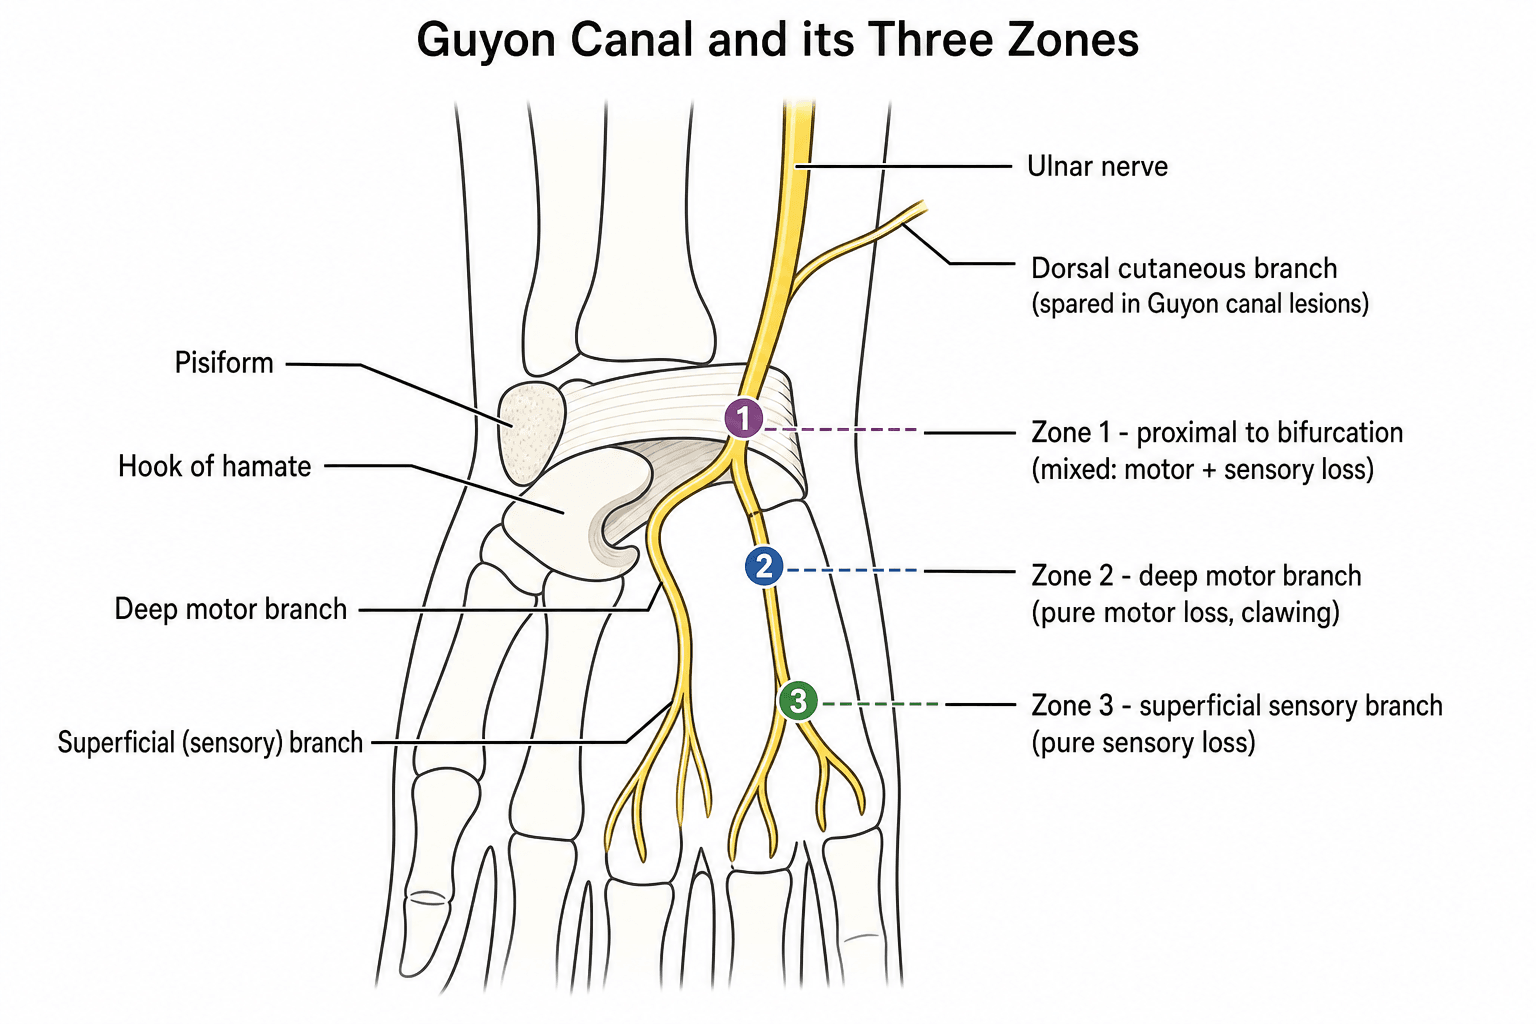
Guyon's canal. A fibro-osseous tunnel at the wrist containing the ulnar nerve and ulnar artery, the nerve lying on the ulnar (medial) side of the artery:
- Roof - volar carpal ligament
- Floor - transverse carpal ligament (flexor retinaculum) and pisohamate ligament
- Medial wall - pisiform
- Lateral wall - hook of hamate
Within the canal the nerve divides into a superficial sensory branch and a deep motor branch. The deep branch turns around the hook of hamate, which explains its vulnerability to a hook fracture, a ganglion and repetitive handlebar pressure. The level of a lesion relative to this bifurcation defines the three zones of the Akahori classification.
Martin-Gruber, Riche-Cannieu and Anomalous Innervation
Martin-Gruber anastomosis. Crossover fibres run from the median to the ulnar nerve in the forearm in 15% of the population, so the ulnar intrinsics are innervated by median fibres. In a high ulnar lesion hand function may be surprisingly preserved (pseudo-preservation), and in median lesions ulnar signs appear. The anomaly can confuse clinical and EMG findings.
Riche-Cannieu anastomosis. Its hand-level counterpart is a communication in the palm between the recurrent (motor) branch of the median nerve and the deep (motor) branch of the ulnar nerve. It is common in anatomical studies and, when extensive, can produce an all-ulnar hand, in which the ulnar nerve effectively supplies all the intrinsic muscles, including the thenar group.
- Location
- Forearm
- Direction
- Median (or AIN) to ulnar
- Clinical effect
- High ulnar lesions may spare hand intrinsics (pseudo-preservation); confounds nerve conduction studies
- Location
- Palm / hand
- Direction
- Median recurrent branch to ulnar deep branch
- Clinical effect
- Can produce an 'all-ulnar hand'; confounds median/ulnar localisation and conduction studies
- Location
- Forearm
- Direction
- Ulnar to median (reverse of Martin-Gruber)
- Clinical effect
- Rare; produces atypical median-territory findings
Classification Systems
The original three-grade clinical staging system for ulnar nerve compression at the elbow, used to guide management and predict outcome.
- Clinical Findings
- Mild: intermittent paraesthesia in ulnar digits, subjective weakness, no measurable motor loss or wasting
- Prognosis
- Good with conservative or surgical treatment
- Clinical Findings
- Moderate: measurable intrinsic weakness, persistent paraesthesia, wasting may be early/absent
- Prognosis
- Good outcome likely if treated before fixed atrophy
- Clinical Findings
- Severe: marked weakness, established intrinsic atrophy and clawing, often constant numbness
- Prognosis
- Guarded; permanent deficit common despite surgery
Clinical Assessment
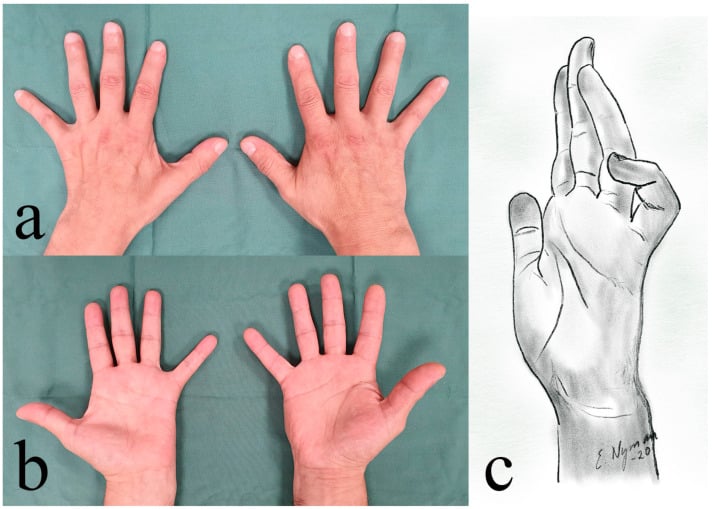
Inspection. Look for wasting of the hypothenar eminence and of the first dorsal interosseous on the dorsum of the first web space. Then look at the ring and little fingers for clawing, which is hyperextension of the MCP joints with flexion of the IP joints.
The ulnar paradox. A high lesion claws less than a low one. In a low lesion (wrist) FDP is intact, and its unopposed flexion of the IP joints produces severe clawing. In a high lesion (elbow) the FDP to the ring and little fingers is paralysed as well, so the IP joints do not flex and the claw deformity is masked.
Wartenberg's sign. The little finger sits abducted, from weakness of the palmar interossei (adduction) and the unopposed action of EDM (radial nerve) and abductor digiti minimi, which is ulnar-supplied but often spared or less affected relative to mechanics.
Wartenberg's sign is ulnar and motor; Wartenberg's syndrome is radial and sensory.
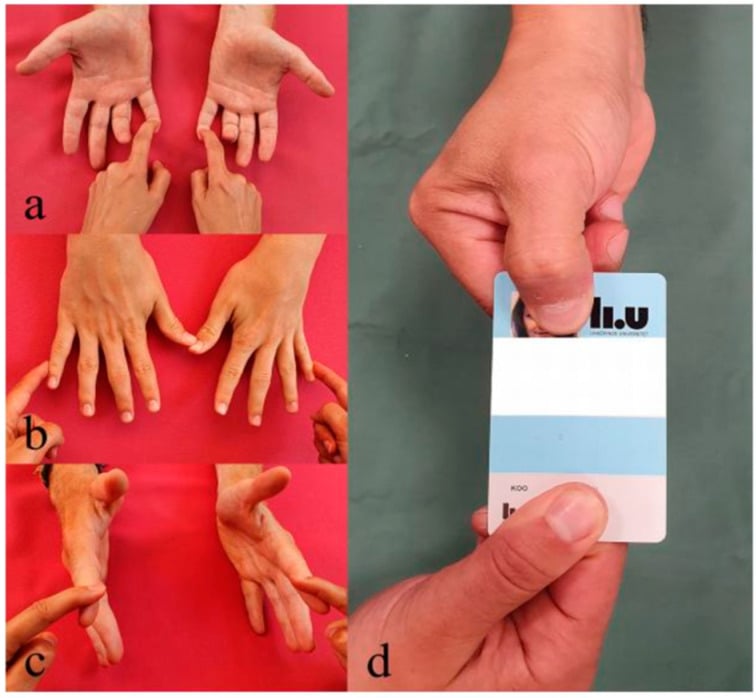
Froment's and Jeanne's signs. Froment's sign tests adductor pollicis. The patient grips a sheet of paper between the thumbs; if adductor pollicis is weak, the patient flexes the thumb IP joint with FPL (median nerve) to compensate, and that flexion is the positive sign. Jeanne's sign is hyperextension of the thumb MCP joint during pinch (instability).
Provocation tests.
- Tinel's sign - tap over the cubital tunnel and Guyon's canal
- Elbow flexion test - the patient flexes the elbow fully with the wrist extended and holds it for 60 seconds; reproduction of symptoms is positive
- Scratch collapse test - its sensitivity is controversial
Localising the level. The dorsal cutaneous branch leaves before Guyon's canal, so dorsal ulnar sensation is lost in cubital tunnel and other high lesions and often spared in Guyon's canal and wrist lesions.
Differential diagnosis. A lower trunk plexopathy can mimic an ulnar nerve lesion.
- Differentiating Features
- Neck pain, All medial hand muscles affected (incl Median)
- Key Test
- Spurling's Test / MRI Neck
- Differentiating Features
- T1 fibres affected (AP loss), Horner's Syndrome (sometimes)
- Key Test
- Chest X-Ray (Pancoast)
- Differentiating Features
- Vascular signs, Positional provocation
- Key Test
- Adson's Test / Doppler
- Differentiating Features
- Painless wasting, Fasciculations, Hyperreflexia
- Key Test
- EMG (Widespread denervation)
Other causes of clawing. Ulnar nerve palsy is the classic cause of a claw hand, but the differential also includes leprosy (a thickened nerve), neuritis (viral or autoimmune), amyotrophy (diabetic or neuralgic) and C8/T1 radiculopathy.
Investigations
Radiographs. Look for bone spurs, a cubitus valgus deformity, a supracondylar spur (rare) or, at the wrist, a hook of hamate fracture.
Ultrasound. A cross-sectional area over 10 mm² suggests compression, and the scan can show nerve instability (subluxation) in real time. Its sensitivity is only modest (Pompe and Beekman), so a normal scan cannot exclude disease.
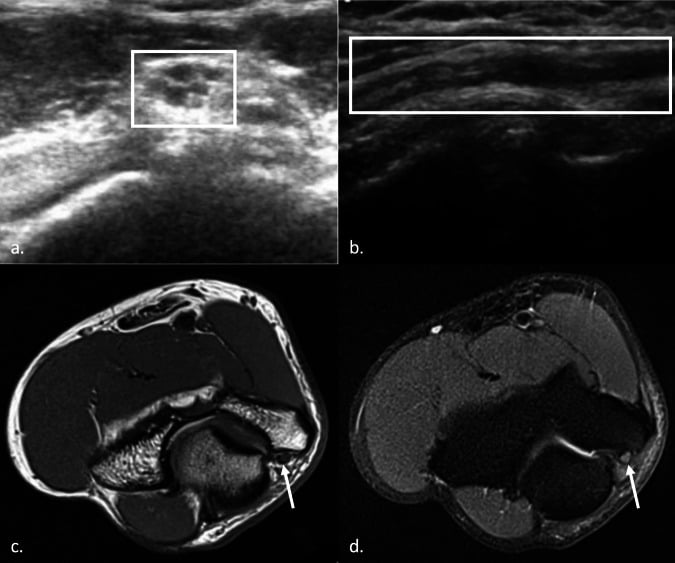
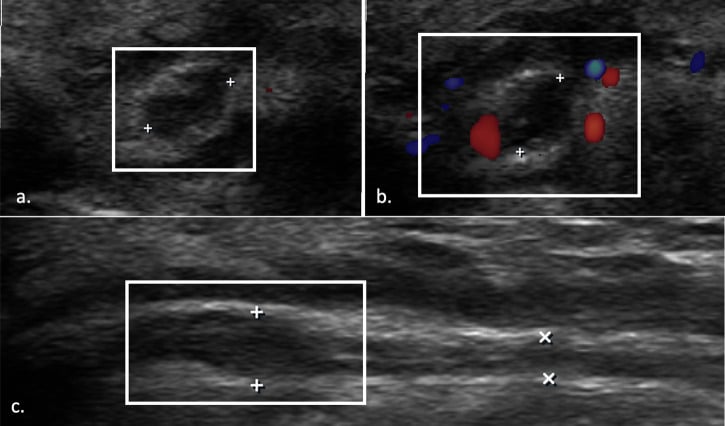
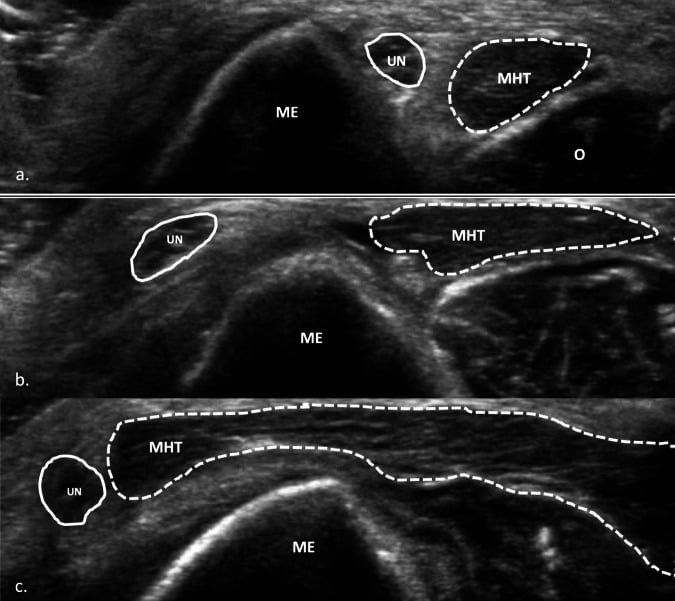
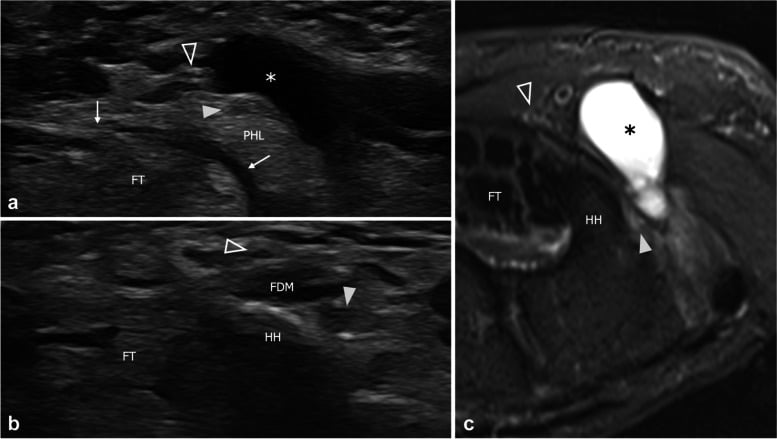
MRI. Shows space-occupying lesions, such as a ganglion cyst in Guyon's canal.
Nerve conduction studies and EMG. Neurophysiology is the gold standard for grading severity.
- Conduction velocity - slowing across the elbow to under 50 m/s, or an absolute drop of over 10 m/s compared with the forearm
- EMG of FCU - denervation suggests the lesion is at or above the elbow; a normal FCU suggests a distal lesion, or a very mild one
- Guyon's canal - prolonged distal latency
Management Strategy
Conservative care is for mild symptoms (McGowan I) and intermittent paraesthesia:
- Night splinting that prevents elbow flexion over 45 degrees
- Activity modification - avoid resting the elbows on tables, and headset use
- NSAIDs as an adjunct
It is about 50% effective in mild cases, and patient compliance is key. The Cochrane review puts the splint in its place: in mild disease, advice on avoiding provocative positions improved symptoms, and adding splinting or nerve gliding gave no further benefit. The advice is therefore the core of conservative care.
When to operate. There is no agreed cut-off for how long to persist with conservative care, and no precise electrodiagnostic threshold that mandates surgery. The pragmatic consensus is to operate for:
- Failure of 3-6 months of conservative nerve-protection measures
- Motor weakness (McGowan II/III), progressive motor loss or wasting
- Persistent constant numbness
The operations.
- In situ decompression - simple release of Osborne's ligament; success 80-90%
- Anterior subcutaneous transposition - the nerve is moved anterior to the epicondyle and secured with a fascial sling
- Anterior submuscular transposition - the nerve is placed under the flexor mass; good for revision or very thin patients
- Medial epicondylectomy - removes the bony prominence, with a risk of MCL injury and instability
Choosing. For primary compression, multiple meta-analyses show no difference in outcome between decompression and transposition, and for idiopathic disease the RCTs and the Cochrane review agree, with fewer complications after decompression. Decompression is also faster, less invasive and preserves vascularity, so it is standard for primary simple cases. Transposition is indicated for a subluxating nerve, valgus deformity, stricture or scarring, and revision cases, and is often indicated when the bed is irregular (arthritic osteophytes). Beyond that, the choice depends on surgeon preference and pathology, and whether subluxation alone justifies transposition is disputed (see Controversies).
Surgical Technique
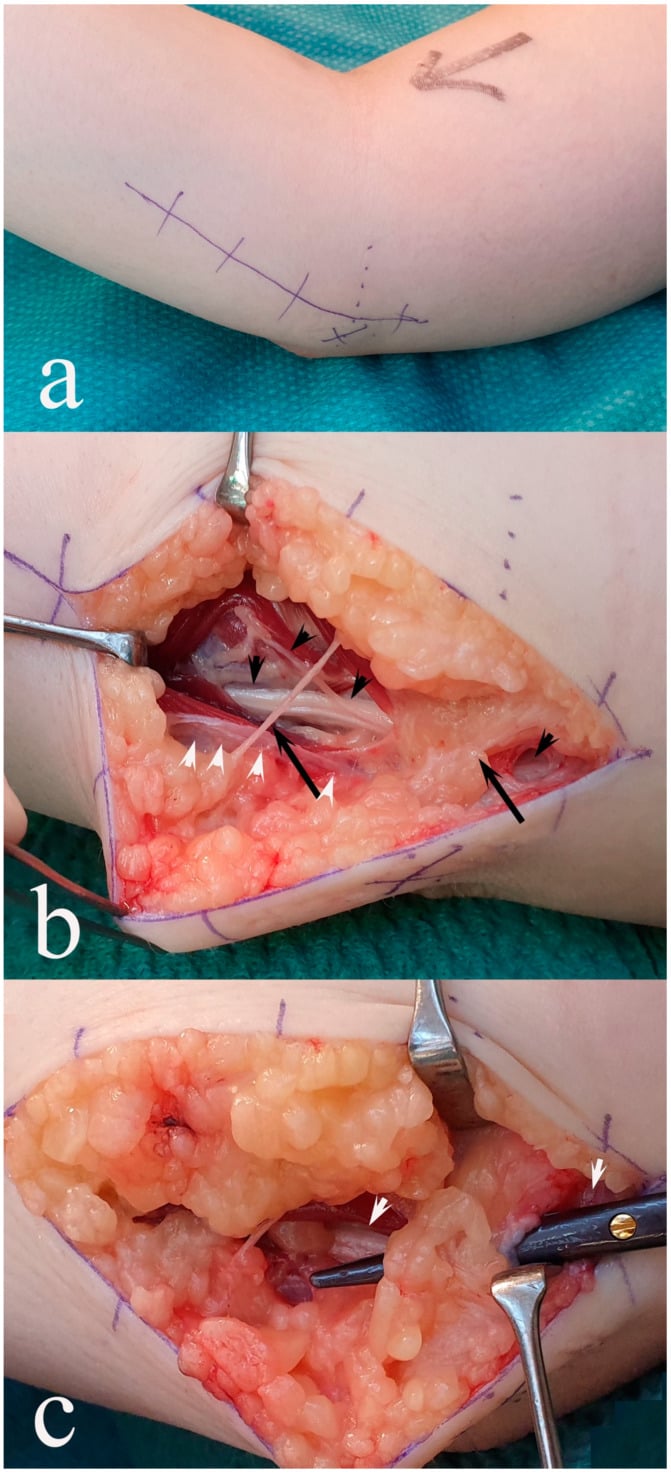
Set-up. Mark the incision and confirm the symptomatic side before starting, to avoid wrong-site surgery.
- Position - supine on an arm board, tourniquet high on the arm
- Anaesthesia - general or regional (block)
- Equipment - loupes or microscope (optional but recommended) and a nerve stimulator
- Instruments - basic plastic set, tenotomy scissors, vessel loops
In situ decompression.
- Incision - a short curvilinear posteromedial incision over the cubital tunnel, centred on the medial epicondyle. Identify and protect the MABCN (medial antebrachial cutaneous nerve) branches.
- Release - expose the nerve without circumferential devascularisation and release every constricting layer proximally and distally: all five sites, from the FCU aponeurosis between the two heads and the deep flexor-pronator aponeurosis distally, through Osborne's ligament over the tunnel, to the arcade of Struthers and medial intermuscular septum proximally.
- Stability check - flex the elbow after release. If the nerve subluxes, transpose; if not, close.
The MABCN branches cross the surgical field. Injury causes painful neuroma and numbness over the olecranon/posterior proximal forearm.
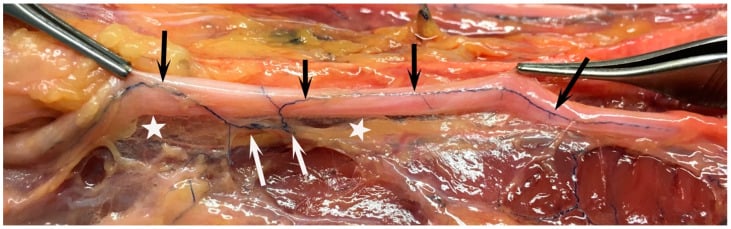
Anterior submuscular transposition. The technique is robust for recurrent cases.
- Extended exposure - extend the incision proximally and distally.
- Mobilise the nerve - release proximally to the arcade of Struthers and distally deep into the forearm, and excise the medial intermuscular septum completely.
- Prepare the bed - elevate the flexor-pronator mass from the medial epicondyle.
- Transpose - place the nerve anterior to the epicondyle, deep to the muscle mass.
- Reattach - repair the flexor origin.
Complications
- Cause
- Surgical trauma
- Management
- Excision / Burying
- Cause
- Incomplete release (septum/FCU)
- Management
- Revision Decompression
- Cause
- Excessive release anteriorly
- Management
- Transposition
- Cause
- Destabilised origin
- Management
- Physio / Repair
Rehabilitation
After decompression, move early in a soft dressing to prevent stiffness, and avoid direct pressure. After transposition, immobilise for 1-2 weeks to allow the nerve's new position to stabilise, then begin range of motion.
- Timeframe
- 0-2 Weeks
- Goals
- Wound healing, Oedema control, Nerve gliding
- Precautions
- Avoid resisted flexion
- Timeframe
- 2-6 Weeks
- Goals
- Full ROM, Scar management, Isometrics
- Precautions
- No heavy lifting
- Timeframe
- 6-12 Weeks
- Goals
- Progressive strengthening, Work hardening
- Precautions
- Monitor for recurrence
Outcomes
The order of recovery. Sensory recovery typically precedes motor: paraesthesia resolves first, then strength returns, and sensation may take months.
Severity decides. Severity at presentation is the single most important determinant of recovery. Motor recovery is unpredictable in severe cases (McGowan III): "time is muscle". Established (pre-operative) intrinsic atrophy is a poor prognostic sign and rarely reverses fully. Other factors:
- Age - patients over 50 have poorer outcomes
- Duration - symptoms for over 1 year correlate with incomplete recovery, and intrinsic function may not fully return in elderly or long-standing cases
- Site - distal (wrist) lesions reinnervate faster than proximal (elbow) ones, but intrinsic demand is high
Guidelines, Registries & Global Practice
Global Epidemiology
- Cubital tunnel syndrome is the second most common compressive (entrapment) neuropathy of the upper limb, after carpal tunnel syndrome.
- Reported population incidence is approximately 20-30 per 100,000 person-years, with a male predominance and a peak in the 5th-6th decades.
- Strong associations: prolonged or repetitive elbow flexion, prolonged direct pressure on the elbow, diabetes, smoking, manual/vibrating-tool occupations and prior elbow trauma (tardy ulnar palsy after cubitus valgus).
- Guyon's canal (ulnar tunnel) syndrome is far less common; ganglion cyst is the single most frequent space-occupying cause, followed by hook-of-hamate pathology and ulnar artery aneurysm/thrombosis (hypothenar hammer syndrome).
Side-by-Side Guideline Comparison
- Position on Conservative Care
- First-line for mild/intermittent disease: activity modification, night extension splinting
- Position on Surgery
- Surgery for failed conservative care or motor involvement; in-situ release first-line for idiopathic disease
- Position on Conservative Care
- Trial of nerve-protection advice and splinting in mild cases
- Position on Surgery
- Simple decompression preferred for primary idiopathic CuTS; transposition reserved for instability/deformity
- Position on Conservative Care
- Advice on avoiding provocative positions improves mild symptoms; added splinting/gliding no extra benefit
- Position on Surgery
- Decompression and transposition equivalent in efficacy; decompression has fewer wound complications
- Position on Conservative Care
- Limited role once structural deformity present
- Position on Surgery
- Transposition favoured when nerve sits in a scarred or deformed (valgus) bed or after distal humerus fixation
Across AAOS/ASSH, BOA/BSSH, the Cochrane review and European consensus, the core message is identical: for primary idiopathic cubital tunnel syndrome, simple in-situ decompression is first-line surgery. Transposition (subcutaneous or submuscular) is reserved for a subluxating nerve, cubitus valgus / post-traumatic deformity, a scarred bed, or revision.
Registry & High-Volume Evidence
- There is no large dedicated international registry for peripheral nerve decompression equivalent to the joint-replacement registries (NJR, AJRR, AOANJRR), so practice rests on RCTs and systematic reviews rather than registry survivorship data.
- Large administrative and insurance datasets consistently show cubital tunnel surgery is among the most frequently performed elective hand operations worldwide, with low but non-trivial revision rates (incomplete release and persistent symptoms being the leading reasons for reoperation).
High- vs Limited-Resource Practice Variation
- High-resource settings: ready access to nerve conduction studies/EMG and high-resolution ultrasound for diagnosis and lesion localisation; endoscopic in-situ release available in selected centres; day-case surgery under regional or local anaesthesia.
- Limited-resource settings: diagnosis is predominantly clinical (Tinel's, elbow flexion test, Froment's, pattern of wasting) with selective or no electrodiagnostics; open simple decompression under local anaesthesia is the pragmatic default — low-cost, effective, and avoids dependence on imaging or specialised endoscopic equipment.
- Globally, the threshold to operate is driven by motor involvement and failure of conservative measures, not by access to advanced imaging.
Special Scenarios
Ulnar tunnel syndrome. Compression in Guyon's canal is localised by Akahori's zones (under Classification). The causes:
- Ganglion cyst - the most common, at 50%
- Hook of hamate breakdown (the golfer)
- Ulnar artery aneurysm (hammer syndrome)
- Cyclist's palsy
Treatment is decompression of the tunnel and treatment of the pathology, removing a cyst where one is found.
The Bouvier test. It determines whether a claw hand is simple or complex, and so whether an intrinsic transfer is needed. The examiner blocks MCP hyperextension, mimicking the intrinsics.
- Positive (simple claw) - the patient can extend the IP joints using EDC, so EDC and the extensor mechanism are intact. Treatment prevents MCP hyperextension (Zancolli, capsulodesis).
- Negative (complex claw) - the patient cannot extend the IP joints despite the MCP block, indicating a fixed flexion contracture or an incompetent extensor mechanism. It needs more than a simple static block, for example a dynamic transfer.
Tardy Ulnar Nerve Palsy
The cause. Tardy ulnar nerve palsy is a delayed ulnar neuropathy at the elbow that develops months to years after an old elbow injury. The classic cause is a childhood lateral condyle fracture that goes to nonunion or malunion and produces a progressive cubitus valgus deformity; the increased carrying angle stretches and tethers the ulnar nerve over the medial epicondyle, causing a slow traction and friction neuropathy. Supracondylar malunion, old distal humeral fractures and chronic elbow osteoarthritis can do the same.
The presentation is a gradual ulnar neuropathy, with paraesthesia in the ulnar digits, intrinsic weakness and wasting, and clawing, appearing long after an injury the patient may have forgotten. The key examination clue is a valgus elbow with a positive Tinel's sign over a nerve that is often palpably subluxing or thickened.
Treatment. Because the nerve sits in a deformed and often scarred bed, anterior transposition (subcutaneous or submuscular) is generally preferred over simple in situ decompression, sometimes alongside correction of the underlying deformity.
Controversies & Areas of Uncertainty
The subluxating nerve. This is where the decompression-versus-transposition debate is still genuine. Bartels found decompression effective even with subluxation, yet many surgeons still transpose an unstable nerve to avoid a mobile, vulnerable target.
Endoscopic or open release. Systematic-review data favour endoscopic release on outcomes and complications, but the evidence is non-randomised and learning-curve sensitive. Open in situ release remains the global default, and endoscopy is centre- and surgeon-dependent.
Routine imaging. Whether ultrasound or MRI should be routine rather than selective is unsettled. Many advocate reserving imaging for atypical, recurrent or mass-suspicious cases.
MCQ Practice Points
Q: What is the most common anomaly of upper limb innervation? A: Martin-Gruber Anastomosis. (Median to Ulnar in forearm). Occurs in 15-20% of people.
Q: Which nerve innervates the First Dorsal Interosseous (1st DI)? A: Ulnar Nerve (deep motor branch). The 1st DI abducts the index finger and is a key contributor to pinch strength. Its bulk in the first web space is one of the earliest sites of visible wasting in ulnar neuropathy. (Do not confuse with Wartenberg's sign, which reflects unopposed little-finger abduction.)
Q: Which muscle is tested by Froment's Sign? A: Adductor Pollicis. It is the only hypothenar/thumb muscle supplied by the Ulnar nerve (besides deep head of FPB).
Q: What distinguishes Zone I from Zone II injury at Guyon's Canal? A: Zone I (proximal to bifurcation) causes mixed motor and sensory loss. Zone II (deep branch only) causes pure motor weakness of interossei with sparing of hypothenar sensation.
Q: What is the positive finding in the elbow flexion test for cubital tunnel syndrome? A: Paresthesias in the ring/small fingers within 60 seconds of holding the elbow maximally flexed with the wrist extended.
Ulnar Nerve Vivas
Practise clinical reasoning and management decisions out loud
“A patient presents with clawing of the ring and little fingers. Explain the mechanism and the 'Ulnar Paradox'.”
“You are performing a cubital tunnel decompression. What are the key sites of compression you must release?”
“A cyclist complains of numbness in the little finger but has normal grip strength. Localization?”
“Post-operatively, your patient complains of numbness over the medial proximal forearm and pain when resting the elbow on a table. What has happened?”
Key Anatomy
- C8-T1 Origin
- Arcade of Struthers (8cm proximal)
- Osborne's Ligament (Cubital Tunnel)
- FCU Heads (Entry to forearm)
- Guyon's Canal (Pisohamate ligament)
Branches
- No branches in Arm
- Muscular: FCU, FDP (Medial 1/2)
- Dorsal Cutaneous: 5cm proximal to wrist (Spared in wrist lesions)
- Deep Branch: Motor to intrinsics
- Superficial Branch: Sensory to digits
Clinical Signs
- Froment's Sign (Thumb IP flexion)
- Wartenberg's Sign (Pinky abduction)
- Jeanne's Sign (Thumb MCP hyperextension)
- Duchenne's Sign (Clawing of ring/little)
Surgical Pearls
- Protect MABCN
- Release 5-8cm proximal (septum)
- Release FCU fascia distal
- Check for subluxation
Evidence Base
Bartels RCT: Simple Decompression vs Anterior Subcutaneous Transposition
- Single-blind RCT, 152 patients (75 simple decompression, 77 anterior subcutaneous transposition), 1-year follow-up
- Good/excellent outcome equivalent: 49/75 (SD) vs 54/77 (AST), not statistically different
- Complication rate significantly lower with simple decompression (9.6% vs 31.1%; risk ratio 0.32, 95% CI 0.14-0.69)
- Outcome was equivalent even in the presence of nerve subluxation
Zlowodzki Meta-analysis of RCTs
- Meta-analysis of 4 randomized controlled trials (2 submuscular, 2 subcutaneous transposition)
- No difference in clinical scores (standardised mean difference -0.04, 95% CI -0.36 to 0.28) across 261 patients
- No difference in postoperative motor nerve-conduction velocity (100 patients)
- Narrow confidence intervals exclude any clinically meaningful difference
Cochrane Review: Treatment for Ulnar Neuropathy at the Elbow
- Six RCTs, 430 participants, moderate-quality evidence
- No difference between simple decompression and transposition for clinical improvement (RR 0.93, 95% CI 0.80-1.08) or nerve conduction - in raw terms 91 of 131 improved after simple decompression against 97 of 130 after transposition
- Transposition associated with more wound infections (RR 0.32, 95% CI 0.12-0.85)
- In mild disease, advice on avoiding provocative positions improved symptoms; added splinting/nerve gliding gave no further benefit
Open vs Endoscopic In-Situ Decompression
- Systematic review of outcomes from 8 articles (494 patients: 344 endoscopic, 150 open) and complications from 18 articles (1,108 patients: 691 endoscopic, 417 open)
- Pooled good/excellent outcome 92.0% (88.8-95.2) endoscopic against 82.7% (76.2-89.2) open in-situ - but these are pooled across DIFFERENT studies rather than compared within them, and the endoscopic arm is more than twice the size
- THE ODDS RATIO DOES NOT COME FROM THOSE 1,108 PATIENTS: the pooled odds ratio of 0.280 (95% CI 0.125-0.625) favouring endoscopic release was computed from only the FOUR articles that reported complication rates for both techniques, so the comparison rests on a small subset of the review
- Evidence base limited to small, mostly non-randomised case series
Ultrasonographic Diagnosis: CSA, Diameter and Swelling Ratio
- Prospective cohort of 191 patients in whom the diagnosis was CONSIDERED - 137 had ulnar neuropathy or probable ulnar neuropathy and 54 proved to have another condition - plus 73 healthy volunteers for reference values
- That design is a strength worth naming: specificity was tested partly against 54 PATIENT controls with other diagnoses, not only against healthy volunteers, so it reflects the discrimination actually required in clinic
- Enlarged ulnar nerve diameter, cross-sectional area and swelling ratio all distinguished cases (p less than 0.01)
- Specificity 78-87%, sensitivity 42-61%, area under ROC curve 0.75-0.77 — comparable across the three measures
- The number that matters clinically is the negative predictive value: only 37-44%. A normal ultrasound leaves the majority of these patients still having the disease
- Real-world diagnostic accuracy lower than earlier optimistic reports - and note this is the same senior author revising his own 2011 review, which had called the accuracy good while flagging methodological flaws in the studies then available
Critical Review of Ultrasonography in UNE
- Systematic review of ultrasonography clinical trials in ulnar neuropathy at the elbow
- Increased cross-sectional area at the elbow is the most consistently reported abnormality
- Diagnostic accuracy appears good but several studies had methodological flaws and differing CSA cut-offs
- Role of ultrasound is promising but not yet firmly established