Real-Time Dynamic Soft Tissue Assessment
Hyperechoic (bright): Fat, fibrous tissue, cortical bone surface, tendons (perpendicular beam)
Isoechoic (grey): Muscle at rest, peripheral nerves
Hypoechoic (dark): Fluid-filled structures (bursae), cartilage, some tumours
Anechoic (black): Simple fluid (effusion, cyst), blood vessels
Key: The echogenicity of a structure depends on its acoustic impedance relative to surrounding tissues — large impedance differences create strong reflections
- Ultrasound uses high-frequency sound waves (no ionising radiation) reflected by tissue interfaces to create real-time images.
- Higher frequency (12-18MHz) gives better resolution but less penetration. Lower frequency (5-8MHz) penetrates deeper but with lower resolution.
- Ultrasound is the only modality offering dynamic, real-time assessment — invaluable for impingement testing, snapping tendons, and subluxation.
- Ultrasound sensitivity for full-thickness rotator cuff tears (89-95%) approaches MRI, but is operator-dependent.
- Ultrasound guidance raises injection accuracy for the AC joint (93.6% vs 68.2% landmark), glenohumeral joint (92.5% vs 72.5%) and biceps sheath (86.7% vs 26.7%), but not for the subacromial space (65% vs 70%).
- “A linear transducer (12-18MHz) is used for superficial structures (tendons, ligaments, nerves). A curvilinear transducer (5-8MHz) is used for deeper structures (hip joint, spine).
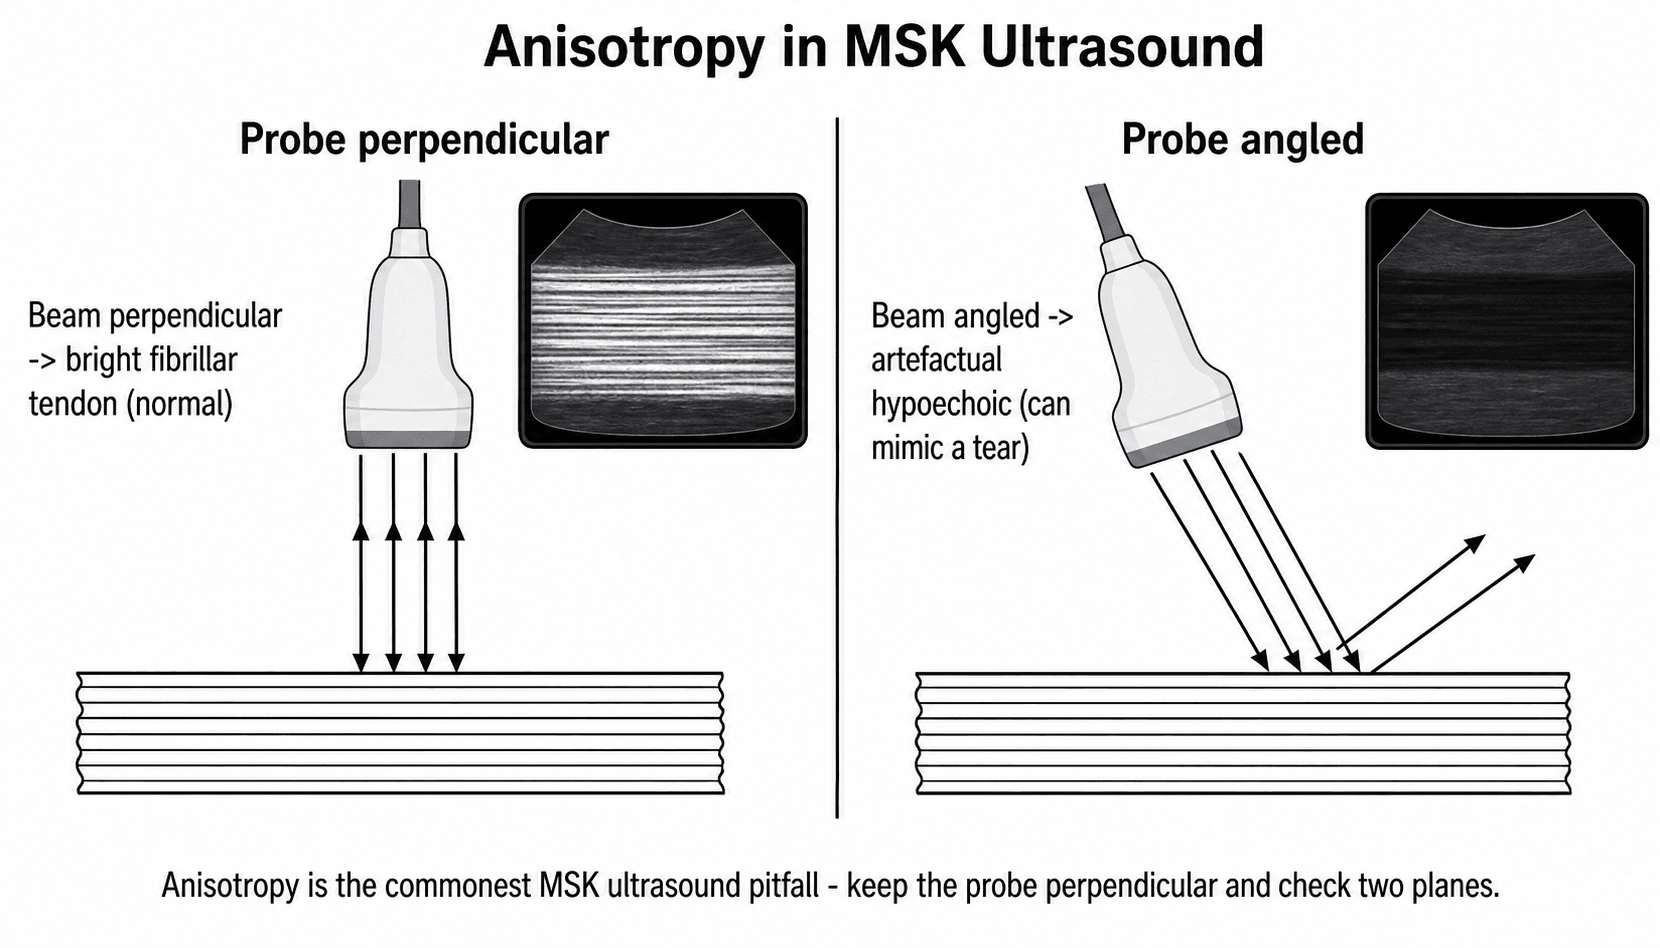
- “Tendons appear hyperechoic (bright) and FIBRILLAR on long axis. Loss of this fibrillar pattern indicates pathology.
- “Anisotropy artefact: tendons appear falsely dark when the ultrasound beam is not perpendicular — the most common pitfall in MSK ultrasound.
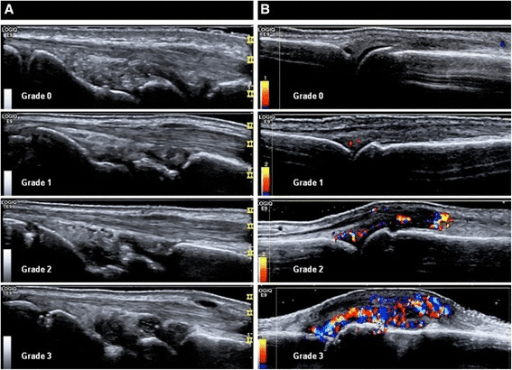
- “Power Doppler detects neovascularisation in tendinopathy — increased Doppler signal correlates with active disease.
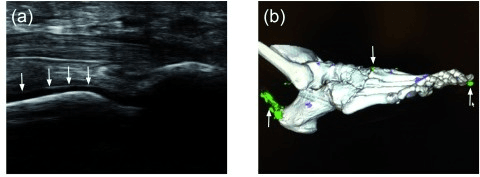
- “Ultrasound cannot penetrate cortical bone — it sees the bone surface only, not internal bone pathology.
Overview
Musculoskeletal (MSK) ultrasound has evolved from a niche technique into an essential tool in modern orthopaedic and sports medicine practice. It images in real time, so the examiner can watch structures during movement, provoke pathology with dynamic tests and guide diagnostic and therapeutic interventions, all without ionising radiation and at the point of care.
Advantages over MRI. Ultrasound offers real-time dynamic assessment, portability, lower cost, the absence of contraindications and the ability to guide interventional procedures. RAPID gathers them.
RAPIDUltrasound Advantages
Hook:RAPID sums up why ultrasound is becoming indispensable in modern orthopaedic practice.
Operator dependence. This is the single greatest limitation. Image quality and diagnostic accuracy depend heavily on the operator's training and experience, the learning curve to competence is steep, and the published studies showing high accuracy come from expert centres and may not reflect general practice.
What it cannot see. Sound does not pass through cortical bone, so marrow, intraosseous pathology and deep structures behind bone are out of reach, and the field of view is limited. Unlike MRI, which produces a complete dataset for review, ultrasound keeps only the images the operator selects, so pathology can be missed if it was not scanned.
Musculoskeletal ultrasound is examined in both clinical and viva settings. A common viva trap is not mentioning the operator-dependent nature of ultrasound as a limitation.
Choosing between ultrasound and MRI. Ultrasound is preferred for dynamic assessment of tendon subluxation or impingement, guided injections and aspirations, and rotator cuff assessment (comparable to MRI in experienced hands). It is also the choice for superficial soft-tissue masses, the neonatal hip (DDH screening), foreign body localisation, muscle injuries (haematoma, tears) with dynamic contraction, and monitoring of tendon healing.
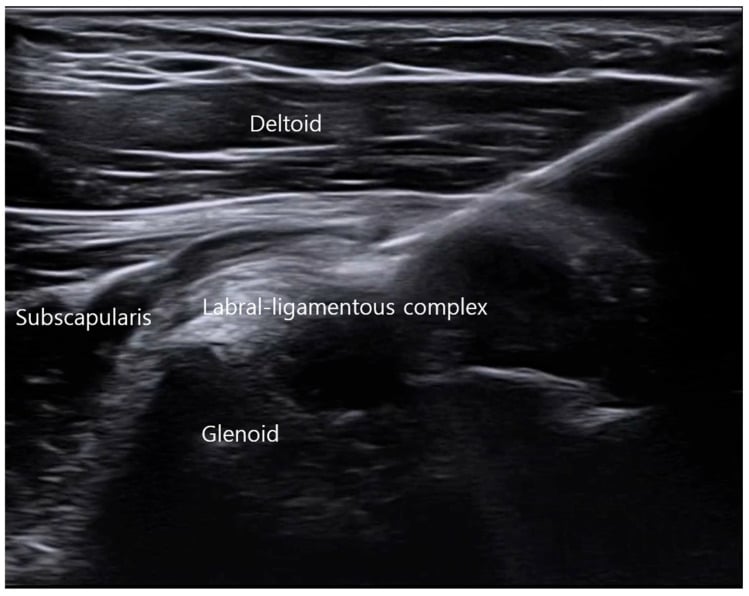
MRI is preferred for bone marrow pathology (oedema, AVN, tumour), intra-articular structures (menisci, labrum, cruciate ligaments), deep structures behind bone, and comprehensive joint assessment, since ultrasound cannot see all areas. It is also preferred for preoperative tumour staging, spinal cord and nerve root assessment, and whenever a permanent, reviewer-independent dataset is required.
Ultrasound Physics
How the image forms. Ultrasound uses sound above the audible range (more than 20kHz), and MSK imaging uses 5-18MHz. Piezoelectric crystals in the transducer generate the waves, which are transmitted into tissue, reflected at tissue interfaces and received by the same transducer to construct the image.
Resolution against penetration. Higher frequency gives better axial resolution, the ability to distinguish structures along the beam axis: about 0.1mm at 15MHz. Higher-frequency waves are also absorbed more rapidly, so useful penetration at 15MHz is about 3-4cm, whereas 5MHz reaches 15-20cm.
This trade-off is the fundamental physics concept. You cannot have maximum resolution and maximum depth at the same time.
Acoustic impedance. Each tissue has a characteristic acoustic impedance (Z = density × speed of sound), and sound is reflected at interfaces between tissues of different impedance. The greater the mismatch, the stronger the reflection, which is why cortical bone, with its very high impedance, produces an extremely bright surface reflection.
Coupling gel. Air's acoustic impedance is very different from tissue's, so without gel nearly all the energy is reflected at the skin-air interface. Gel eliminates that interface and lets the sound enter the tissue efficiently.
Systematic Approach
A systematic MSK ultrasound examination runs through the following steps.
- Assessment
- Choose appropriate probe for depth and resolution requirements
- Key Principles
- Linear 12-18MHz for superficial (tendons, nerves). Curvilinear 5-8MHz for deep (hip joint, deep muscles)
- Assessment
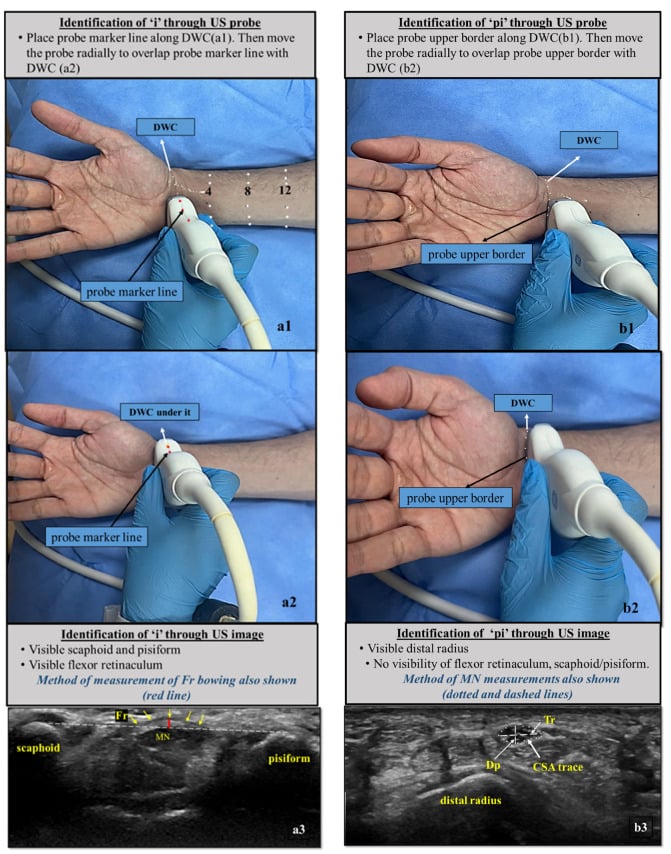
- Follow established scanning protocols for the region
- Key Principles
- Always scan in BOTH long axis and short axis
- Assessment
- Evaluate echogenicity, echotexture, size, vascularity (Doppler)
- Key Principles
- Document measurements
- Assessment
- Perform specific dynamic tests for the region
- Key Principles
- Movement during scanning reveals snapping, subluxation, impingement that are invisible on static imaging
- Assessment
- Apply colour and power Doppler to assess vascularity
- Key Principles
- Increased Doppler signal indicates active inflammation, neovascularisation, or tumour vascularity
- Assessment
- Compare findings to the normal contralateral side, and scan it when findings are equivocal
- Key Principles
- Bilateral scanning helps distinguish normal variants from pathology and quantifies asymmetry
Differential Diagnosis & Controversies
Hypoechoic Tendon: Differential Diagnosis
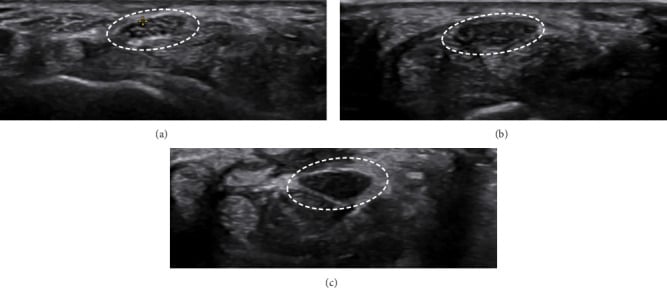
A focal dark (hypoechoic) area within a tendon is one of the commonest decision points in MSK ultrasound. Distinguishing artefact from true pathology, and grading true pathology, is examined frequently.
- Echotexture & Behaviour
- Falsely dark area, tendon thickness normal
- Doppler / Dynamic
- No Doppler signal; resolves on tilting
- Key Discriminator
- Disappears when beam made perpendicular — NOT seen on both axes
- Echotexture & Behaviour
- Thickened tendon, disrupted fibrillar pattern, surfaces intact
- Doppler / Dynamic
- Neovascular power Doppler signal often present
- Key Discriminator
- Persists on tilting; visible on both long and short axis
- Echotexture & Behaviour
- Focal anechoic/hypoechoic defect reaching one surface only
- Doppler / Dynamic
- Variable; may track fluid
- Key Discriminator
- Defect involves bursal OR articular surface but not full depth
- Echotexture & Behaviour
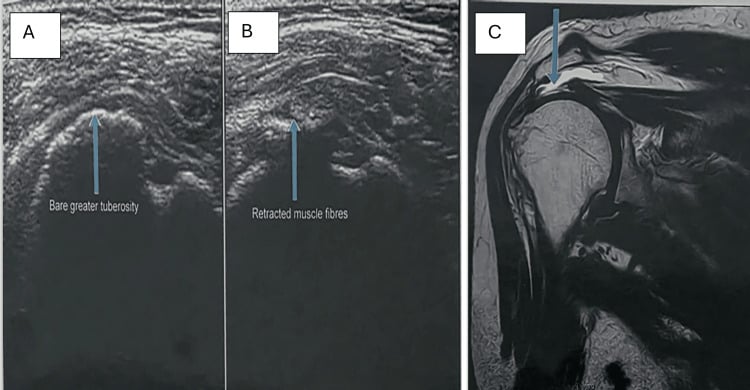
- Defect through entire tendon; deltoid may abut humeral head
- Doppler / Dynamic
- Fluid may fill the gap
- Key Discriminator
- Naked tuberosity sign; tendon retraction
- Echotexture & Behaviour
- Hypoechoic or iso-echoic focus, may lack shadow
- Doppler / Dynamic
- No internal Doppler
- Key Discriminator
- Often shadows when dense; clinical calcific tendinitis
Areas of Uncertainty & Controversy
Universal or selective DDH screening. Countries using the Graf method universally (e.g. Austria, Germany) report fewer late-presenting dislocations but treat more physiologically immature hips. Selective, risk-based screening (UK, US, Australasia) reduces overtreatment but risks late diagnosis. No global consensus exists, and cost-effectiveness drives policy.
Power Doppler in tendinopathy. Neovascular Doppler signal correlates with symptomatic tendinopathy. Its prognostic value, and whether targeting neovessels (e.g. with sclerosant or high-volume injection) improves outcomes, remain uncertain.
Narrowing the operator gap. Standardised protocols, accreditation and emerging deep-learning assistance aim to narrow the gap between expert-centre accuracy and general practice. AI tools are not yet validated for routine independent reporting.
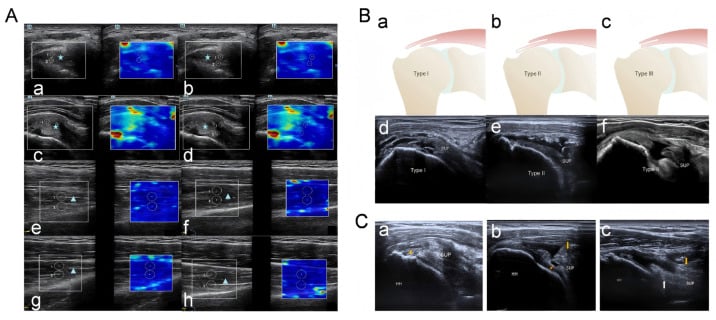
Elastography. Supraspinatus shear-wave elastography is a promising quantitative adjunct, but measured wave velocity changes with region of interest, tendon tension and arm position. Until acquisition and thresholds are standardised, use elastography as supportive information rather than a stand-alone diagnosis.
Clinical Applications
Ultrasound is the primary imaging modality for rotator cuff assessment in many centres, with sensitivity for full-thickness tears of 89-95% in experienced hands, comparable to MRI.
How it compares with MRI. Pooling 65 studies that used a surgical reference standard, there was no significant difference in sensitivity or specificity between ultrasound and MRI for either partial- or full-thickness tears. On summary ROC area, MR arthrography was most accurate at 0.935, with ultrasound 0.889 and MRI 0.878.
Ultrasound therefore sits numerically above plain MRI rather than trailing it, although the pairwise comparison of those curves found no significant difference. The meaningful step up is intra-articular contrast, rather than the switch from sound to magnetic resonance.
What that means in practice. Ordering an MRI purely because ultrasound "isn't good enough" for a cuff tear is not evidence-based; ultrasound is a valid first-line investigation. MRI earns its place for what it shows besides the cuff: muscle quality and Goutallier grade, labrum, bone marrow and occult fracture.
The caveat belongs in the same breath. These pooled figures come largely from expert centres, ultrasound performance is operator-dependent in a way MRI is not, and a service without trained MSK sonographers should not assume the numbers apply to it.
The standard shoulder protocol runs as follows:
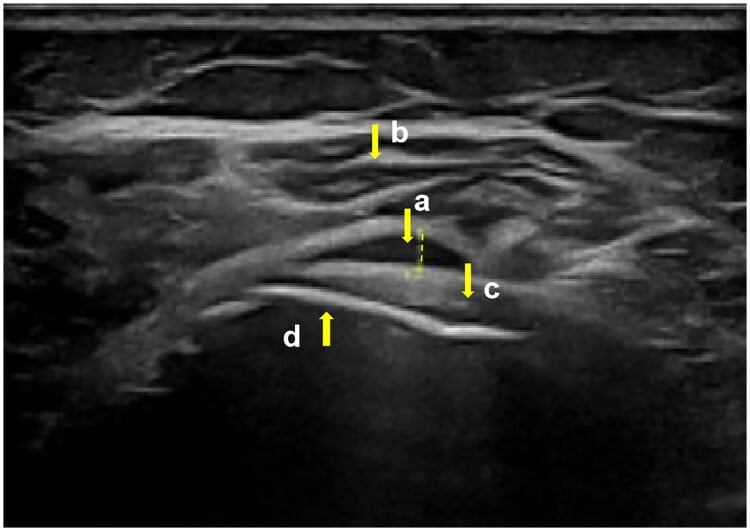
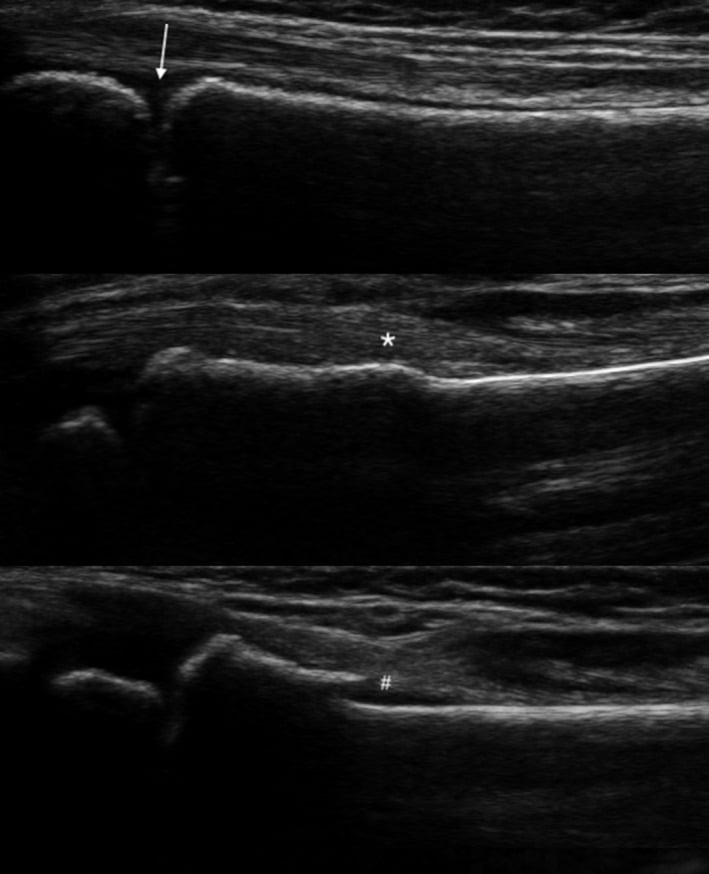
- Biceps tendon (long head): transverse and longitudinal views in the bicipital groove, looking for tenosynovitis (fluid around the tendon), subluxation, dislocation and tears.
- Subscapularis: internal rotation brings the tendon to the anterior scanning window. Assess for partial- and full-thickness tears; dynamic external rotation shows the tendon rolling over the lesser tuberosity.
- Supraspinatus: modified Crass position (hand on back pocket), in long and short axis. The appearances of partial- and full-thickness tears are set out in the hypoechoic tendon table below.
- Infraspinatus and teres minor: external rotation with the arm adducted. They are less commonly torn but are assessed as part of the complete protocol.
- AC joint: superior assessment for osteophytes, effusion and instability.
Dynamic impingement testing. Under real-time ultrasound the examiner sees subacromial bursal thickening and cuff compression during abduction. This is unique to ultrasound and impossible with MRI.
Guidelines, Registries & Global Practice
Musculoskeletal ultrasound is performed worldwide by radiologists, sonographers, sports and rehabilitation physicians, rheumatologists, and increasingly by orthopaedic surgeons and emergency physicians. Reflecting its operator-dependence, every major society anchors practice in accreditation, standardised protocols, and supervised training rather than in any single national pathway.
- Focus
- Technical standards
- Key Position
- Publishes anatomy-specific scanning protocols and graded clinical-indication recommendations; ultrasound first-line for many tendon, nerve and superficial soft-tissue problems
- Focus
- Inflammatory disease & training
- Key Position
- Endorses ultrasound (greyscale plus power Doppler) for synovitis, enthesitis and guided injection; defines structured competency and certification
- Focus
- Practice parameters
- Key Position
- Joint practice parameters for the performance of MSK and interventional ultrasound; accreditation of laboratories and personnel
- Focus
- Accreditation & scope
- Key Position
- Define sonographer/practitioner competence and supervised logbooks; support extended scope MSK ultrasound
- Focus
- Point-of-care use
- Key Position
- Recognise POCUS as an adjunct for fracture detection and reduction monitoring, especially paediatric and resource-limited settings
Global epidemiology and access. MSK ultrasound use has grown faster than any other imaging modality in many health systems because it is inexpensive, portable and radiation-free. There is no implant registry for ultrasound itself; the closest equivalent is national DDH screening data. Approaches diverge: several countries (e.g. Austria, Germany — the home of the Graf method) operate universal newborn hip ultrasound screening, whereas the UK, US and Australasia use selective/targeted screening based on risk factors (breech presentation, family history, clinical instability). The debate centres on cost-effectiveness and overtreatment of physiologically immature hips versus missed late-presenting dysplasia.
High- vs limited-resource practice. In well-resourced centres ultrasound complements MRI and CT and underpins almost all image-guided joint and periarticular injection. In limited-resource and remote settings, portable and handheld ultrasound is often the only available cross-sectional imaging — used for fracture triage, effusion detection, foreign-body localisation, abscess drainage and guided aspiration. The principal global limiting factor is not equipment cost but trained operators, which is why every society pairs guidance with structured accreditation.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“An examiner asks you about the role of ultrasound in assessing rotator cuff tears, including the advantages and limitations compared to MRI.”
“You are performing an ultrasound of the supraspinatus tendon and notice a dark area in the tendon on the long-axis view.”
“You are asked to perform an ultrasound-guided aspiration and injection of a large knee effusion. Describe your technique and the principles of ultrasound-guided intervention.”
Physics Basics
- Higher frequency = better resolution but less penetration
- 12-18MHz (linear) for superficial structures; 5-8MHz (curvilinear) for deep
- Acoustic impedance differences create reflections — basis of image formation
- Coupling gel eliminates air interface that blocks sound transmission
Advantages (RAPID)
- Real-time dynamic imaging (impingement, subluxation, snapping)
- Accessible, portable — clinic, bedside, theatre
- Procedure guidance (AC and glenohumeral injections more than 90% accurate)
- Inexpensive, no radiation, no contraindications
- Doppler for vascularity (neovascularisation, synovitis)
Key Artefacts
- Anisotropy: tendon appears falsely dark when beam not perpendicular (MOST COMMON pitfall)
- Acoustic shadowing: behind bone, calcification (blocks deeper structures)
- Posterior enhancement: bright signal behind fluid-filled structures (confirms fluid)
- Always tilt probe to check for anisotropy before diagnosing pathology
Rotator Cuff Ultrasound
- Sensitivity 89-95% for full-thickness tears (comparable to MRI)
- Modified Crass position for supraspinatus (hand on back pocket)
- Dynamic impingement testing is unique to ultrasound
- LIMITATION: operator-dependent, cannot assess labrum or fatty infiltration
DDH (Graf Classification)
- Type I: Normal, alpha greater than 60 degrees
- Type II: Immature/Dysplastic, alpha 50-60 degrees
- Type III: Subluxated, alpha less than 43 degrees
- Type IV: Dislocated — labrum displaced inferiorly
Evidence Base
Ultrasound vs MRI vs MR Arthrography for Rotator Cuff Tears
- Pooled analysis of 65 studies using a surgical reference standard (open or arthroscopic).
- No significant difference in sensitivity or specificity between ultrasound and MRI for partial- or full-thickness tears (p greater than 0.05).
- Area under the summary ROC curve: MR arthrography 0.935, ultrasound 0.889, MRI 0.878 — MR arthrography most accurate; ultrasound and MRI comparable.
Ultrasound-Guided vs Landmark-Guided Shoulder Injections
- Systematic review and meta-analysis of 4 cadaveric studies (300 shoulders) and 9 human studies (514 patients).
- Ultrasound-guided injection was significantly more accurate for the AC joint (93.6% vs 68.2%), glenohumeral joint (92.5% vs 72.5%) and biceps tendon sheath (86.7% vs 26.7%).
- For the subacromial space ultrasound was NOT more accurate - 65% versus 70% for landmark guidance, numerically worse and not significant - yet it still produced significantly greater reduction in pain (MD 1.47, 95% CI 1.0 to 1.93) and improvement in function (SMD 0.70, 95% CI 0.39 to 1.01) at 6 weeks.
Strong evidence supports ultrasound for rotator cuff assessment and guided interventions.