Adhesive | Abrasive | Fatigue | Third-Body
- Polyethylene wear debris causes particle-induced osteolysis via macrophage activation
- Cross-linking reduces polyethylene wear by 80-90% but may reduce mechanical properties
- Ceramic-on-ceramic has lowest volumetric wear but risk of fracture and squeaking
- Third-body wear from cement, bone, or metal particles accelerates bearing damage
- Wear threshold: the often-quoted 0.1 mm/year linear-wear association comes from conventional-polyethylene THA cohorts; it is not a universal implant or revision threshold
- “Adhesive = cold welding, material transfer
- “Abrasive = harder scratches softer (two-body or three-body)
- “Fatigue (delamination) = subsurface crack propagation
- “Submicron debris drives osteolysis: 0.1-1μm is phagocytosable, 0.2-0.8μm most reliably activates macrophages
Overview
Wear is the progressive loss of material from articulating surfaces due to mechanical action. In joint replacement it generates debris that can cause adverse biological reactions (osteolysis), leading to implant loosening and revision surgery.
Why it matters. Wear is a major cause of late arthroplasty failure, alongside infection, instability, fracture and corrosion. Polyethylene wear debris triggers osteolysis, and the problem has driven the development of bearing surface materials; highly cross-linked polyethylene (HXLPE) has dramatically improved outcomes.
Debris by material. Polyethylene wear is the most common concern. Metal ions are released from metal-on-metal bearings and from the trunnion, and ceramic particles come from fracture.
Mechanisms and Types
Four mechanisms act at the bearing surface: adhesive, abrasive, fatigue and third-body wear.
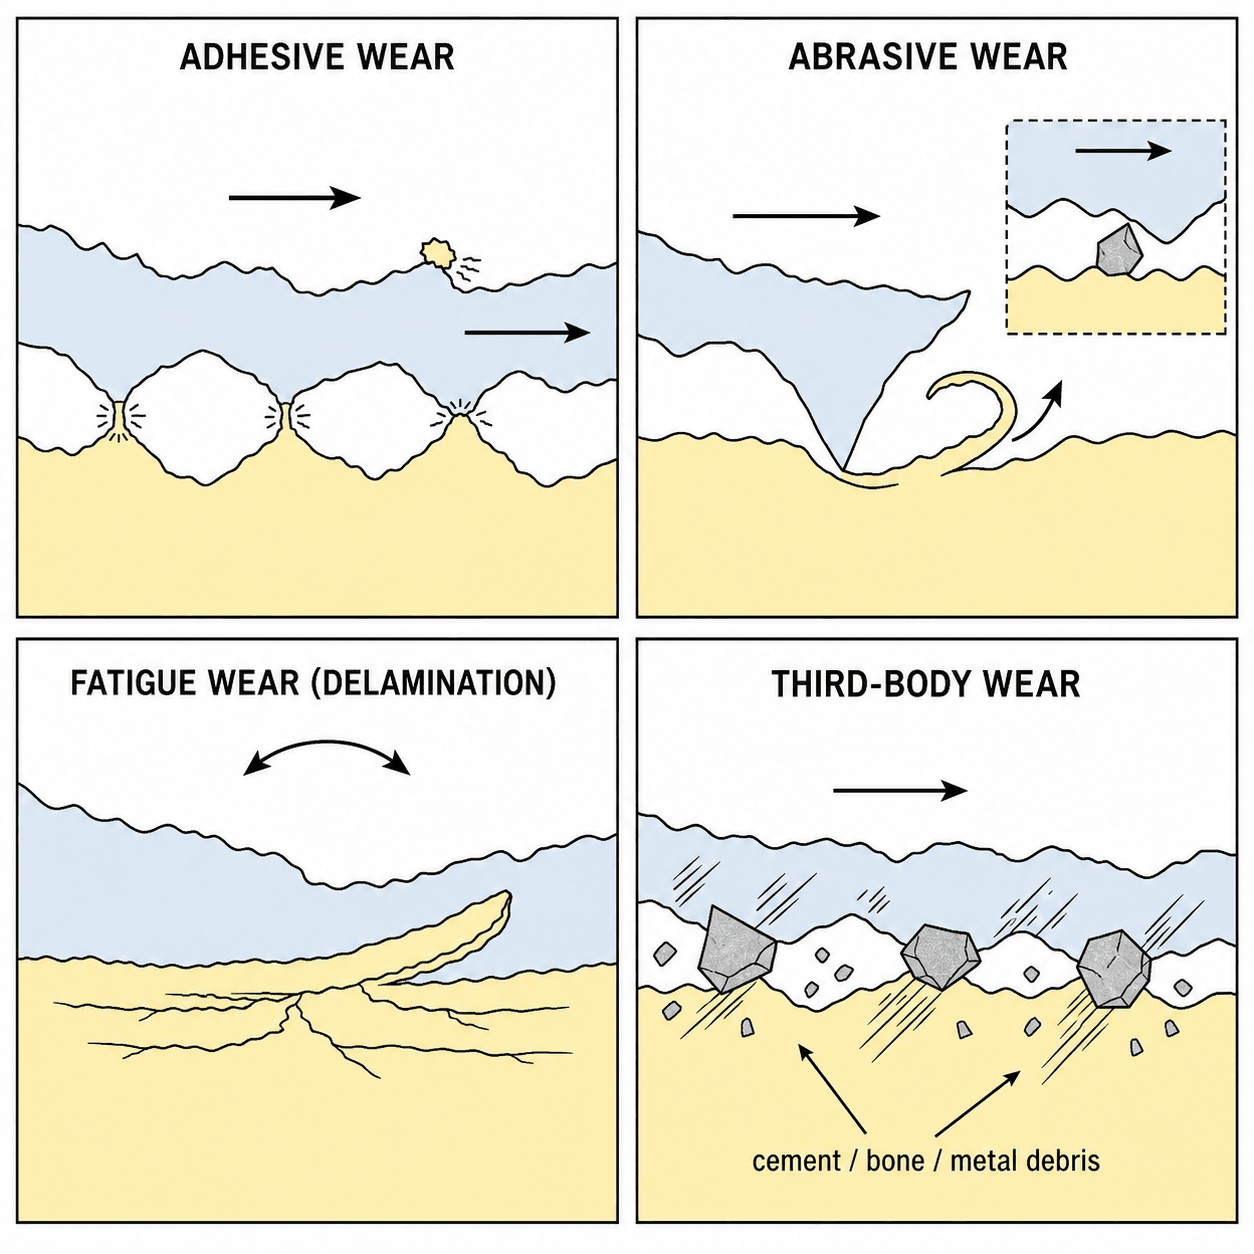
What it is. Adhesive wear results from adhesion, or cold welding, between the asperities of two surfaces, followed by material transfer. High local pressure at the points of asperity contact produces local micro-welding between the surfaces. Relative motion then shears the junction, material transfers from the weaker to the stronger surface, and the transferred material may detach as debris.
What governs it. Surface finish quality, lubrication by synovial fluid, the mismatch in material hardness and contact pressure. The clinical examples are metal-on-metal bearings (historic), poorly lubricated interfaces and the run-in wear of new implants.
Prevention. A good surface finish, adequate lubrication and material selection, with CoCr or ceramic heads.
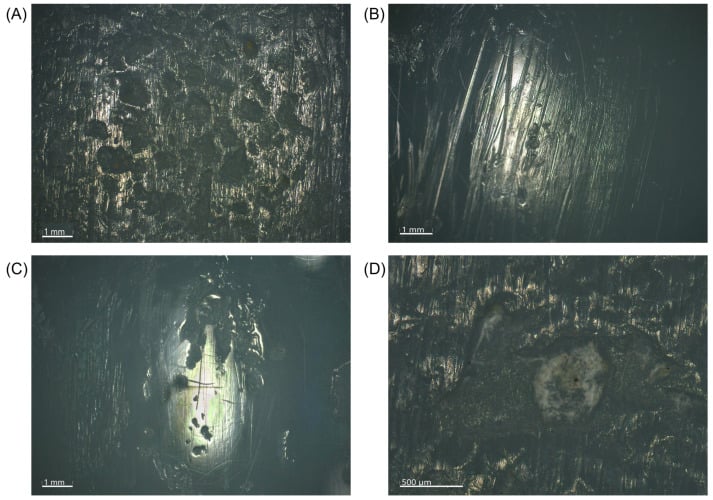
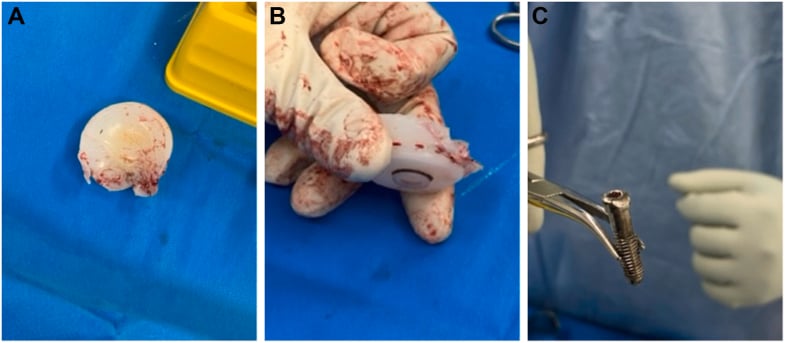
AAFTWear Types
Hook:AAFT = Adhesive, Abrasive, Fatigue, Third-body - the four wear mechanisms!
Volumetric vs Linear Wear (and the Head-Size Paradox)
Two ways to measure wear. Linear wear is the penetration depth of the head into the liner, in mm/year, measured radiographically: the clinical number, and the one the 0.1 mm/year osteolysis threshold refers to. Volumetric wear is the actual volume of material removed (mm³/year), which determines the number of particles and hence the biological burden.
The head-size paradox. A larger femoral head gives better stability, but for a polyethylene bearing volumetric wear rises with head diameter. The bigger head sweeps a greater sliding distance, so more material is removed per year, even though linear penetration may be similar or lower. This is why very large-head metal-on-metal and large-diameter bearings, despite low linear wear, generated a large volumetric (and ionic) debris burden.
Why it matters biologically. Osteolysis is driven by the number of submicron particles, so volumetric wear, not linear penetration alone, best predicts osteolytic potential. HXLPE reduces both, which is why it cut osteolysis so dramatically.
How the paradox was resolved in practice. The multiplier is real but it acts on the linear rate, and crosslinking drove that rate towards zero: 0.03 mm/year in the randomised ten-year data, and below the resolution of radiostereometric analysis at seven years in the vitamin E trial. A geometric penalty applied to an unmeasurably small number stays unmeasurably small, which is why 36 mm heads on crosslinked polyethylene became standard while 36 mm heads on conventional polyethylene never were. The paradox is a statement about conventional polyethylene and about metal-on-metal, not a general prohibition on large heads.
Run-in and steady state. Wear is typically higher in the first year or so (run-in, as surface asperities bed in), then settles to a lower steady-state rate. This matters when interpreting early radiographic wear measurements.
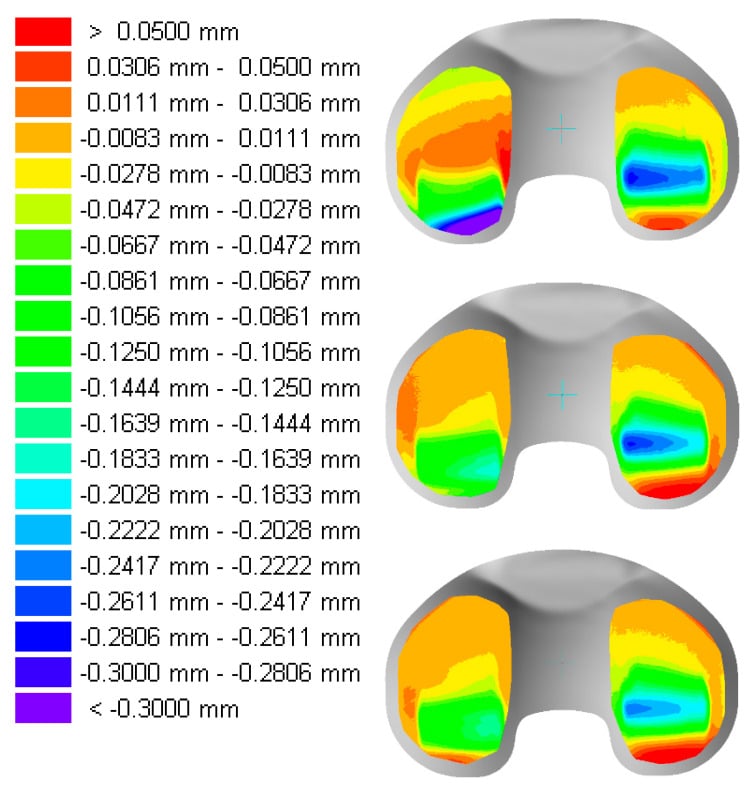
Bearing Surface Anatomy
The hip. A femoral head of CoCr, ceramic or oxinium articulates with an acetabular liner of polyethylene, ceramic or metal. The head joins the neck at a modular junction, the head-neck trunnion.
The knee. A CoCr femoral component articulates with a polyethylene tibial insert, and there is a patellofemoral articulation.
- Head
- CoCr or ceramic
- Cup/Insert
- Polyethylene
- Head
- Ceramic
- Cup/Insert
- Ceramic
- Head
- Ceramic
- Cup/Insert
- Polyethylene
- Head
- CoCr
- Cup/Insert
- CoCr (abandoned)
Surface properties. The relevant surface characteristics are roughness (the Ra value), hardness, the harder surface scratching the softer, and wettability, which affects lubrication.
The trunnion. The head-neck junction is a site of fretting corrosion and a potential source of third-body debris, and taper design affects its stability.
Trunnion corrosion can generate metal debris:
- Independent of bearing surface
- More common with large heads
- Can cause ALVAL even with MoP

Investigations
Radiographs. Polyethylene wear is measured on serial radiographs, from the femoral head centre to the acetabular rim, and compared with the baseline post-operative films. They show the linear wear rate (mm/year), an eccentric head position and osteolytic lesions as radiolucent areas.
The threshold is a rate. Osteolysis is rare below 0.1 mm/year of linear penetration and its incidence climbs steeply above that, which is why cumulative wear on a radiograph must be divided by the years in situ before it is interpreted. The association was derived from conventional-polyethylene hip arthroplasty cohorts and describes increased osteolysis risk. It is not a universal implant threshold or an automatic revision cut-off.
Reading modern polyethylene. HXLPE often has far lower measurable penetration. Compare serial calibrated images, separate true wear from bedding-in and measurement error, and interpret linear and volumetric wear in the context of implant type, head size, time in situ and the trajectory of any osteolysis.
- Purpose
- Wear measurement
- Findings
- Linear wear, osteolysis
- Purpose
- Osteolysis quantification
- Findings
- 3D bone loss assessment
- Purpose
- Soft tissue assessment
- Findings
- ALVAL, pseudotumour
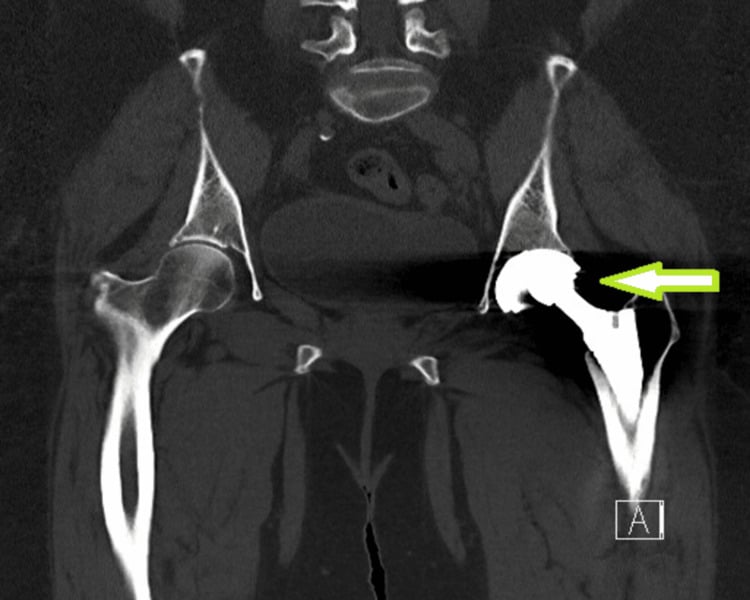
CT quantifies the volume of bone loss. It helps surgical planning and guides the choice between liner exchange and cup revision.
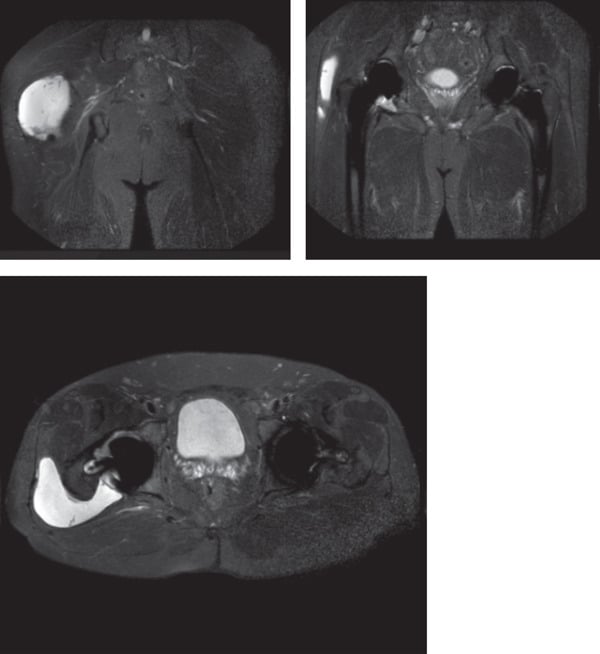
Metal ions. Cobalt and chromium testing supports assessment of metal-on-metal bearings or suspected taper corrosion. No single concentration diagnoses adverse local tissue reaction: thresholds are implant- and regulator-specific, and trends, symptoms, imaging and renal function matter. Cross-sectional imaging is required when clinical concern persists despite a non-diagnostic ion result.
Differential Diagnosis: Causes of Late Arthroplasty Failure
Wear-driven osteolysis is one of several causes of a painful or failing joint replacement. Distinguishing them governs management.
- Typical Features
- Slow, often asymptomatic; eccentric head; lytic lesions
- Key Investigation
- Serial X-ray, CT volume
- Discriminator
- High PE wear rate, scalloped periprosthetic lysis
- Typical Features
- Start-up pain, progressive radiolucent lines
- Key Investigation
- Serial X-ray
- Discriminator
- Migration/subsidence over time
- Typical Features
- Rest pain, early failure, effusion, raised CRP/ESR
- Key Investigation
- Aspiration, alpha-defensin, cultures
- Discriminator
- Positive aspirate, raised inflammatory markers
- Typical Features
- MoM or corroded trunnion; effusion, mass
- Key Investigation
- Cobalt/chromium ions, MARS-MRI
- Discriminator
- Pseudotumour, elevated metal ions
- Typical Features
- Squeak or sudden noise; CoC bearing
- Key Investigation
- X-ray, CT
- Discriminator
- Audible squeak, fracture line, stripe wear
Management
Surveillance. Tailor the interval to symptoms, implant, wear trajectory, osteolysis location and risk of structural compromise; do not assign every stable asymptomatic implant a universal annual or biennial schedule. Use CT when the extent of a lesion will change planning.
When to consider intervention. The reasons to consider it are:
- Symptoms attributable to the bearing or loosening
- Progressive wear or osteolysis, especially where bone stock or fixation is threatened
- Mechanical liner failure, component malposition, instability, corrosion or adverse tissue reaction
- Approach
- Observe, serial X-rays
- Rationale
- May stabilise
- Approach
- Plan revision
- Rationale
- Prevent bone loss
- Approach
- Revision arthroplasty
- Rationale
- Address failure
When to revise. Base the decision on symptoms, progression, lesion location and volume, component fixation, mechanical failure and remaining bone stock. No universal 2 cm lytic-lesion threshold applies across acetabular, femoral and knee defects. The principle is to revise before massive bone loss, because revision is easier with preserved bone.
The bearing at revision. Correct the failure mechanism, then use a compatible modern low-wear bearing, commonly HXLPE with an appropriate head. Ceramic-on-ceramic, ceramic-on-polyethylene and other combinations are construct- and patient-specific rather than age rules. Inspect the taper and retain it only if it is mechanically sound and compatible with the planned head or sleeve strategy.
Revision Surgical Technique
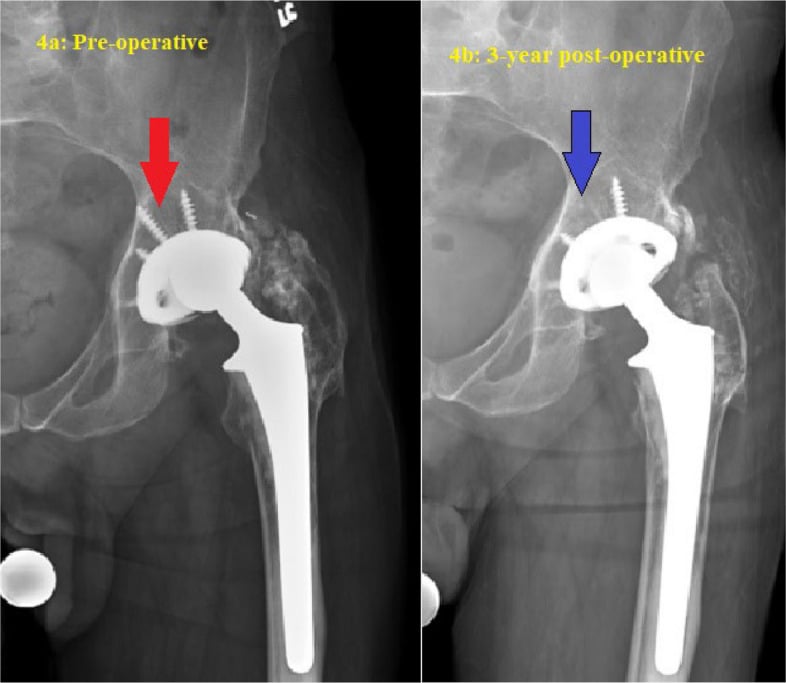
Choosing the operation. Isolated liner exchange suits a well-fixed cup with adequate bone. The cup is revised when it is loose or bone is insufficient. The stem is revised if it is loose, and stem revision is considered if its trunnion is corroded.
- Indication
- Well-fixed cup, good bone
- Complexity
- Moderate
- Indication
- Loose or poor bone stock
- Complexity
- Major
- Indication
- Both components involved
- Complexity
- Complex
Key steps. The liner exchange runs in four steps:
- Remove the worn bearing
- Debride the inflammatory membrane, curetting all of it
- Bone graft the osteolytic lesions: graft contained defects, and augment with structural graft if needed
- Implant a new HXLPE liner
The trunnion. Titanium sleeve adapters are available, and the new head is matched to a clean trunnion.
Complications
Biological. Particle-induced osteolysis, aseptic loosening and periprosthetic fracture.
By material. Polyethylene brings osteolysis and loosening; metal brings ALVAL, pseudotumour and metallosis; ceramic brings fracture and squeaking.
- Complication
- Osteolysis
- Incidence
- 10-20% at 10 years
- Complication
- Osteolysis
- Incidence
- Less than 5% at 10 years
- Complication
- Fracture
- Incidence
- Less than 0.1%
- Complication
- ALVAL
- Incidence
- 5-10% (abandoned)
These are summary figures. Devane's ten-year randomised trial found higher osteolysis prevalence in both arms, 38% with conventional polyethylene and 8% with cross-linked, but it compared one pair of liners in one hip, so its absolute rates should not be transferred to other cross-linked polyethylenes.
Prevention. The surgical measures are proper component positioning, avoiding intraoperative scratching and thorough lavage before closure. In material selection, HXLPE is standard for most patients, ceramic is a consideration in young patients, and metal-on-metal and large metal heads are avoided.

Postoperative Care
After revision. Standard THA precautions and VTE prophylaxis, with protected weight-bearing if bone graft was used.
- Weight-Bearing
- Protected if bone graft
- Activity
- Hip precautions
- Weight-Bearing
- Progress to full
- Activity
- Rehabilitation
- Weight-Bearing
- Full activities
- Activity
- Long-term monitoring
Follow-up. Serial radiographs assess bone healing and monitor resolution of the osteolysis. Surveillance is then long-term, with radiographs for new osteolysis and clinical assessment for symptoms, at an interval set as for any wear surveillance. Its purpose is early detection of wear or osteolysis, so that intervention comes before bone loss.
Registries. Submitting data to the national joint registries (NJR, AJRR, AOANJRR and others) tracks outcomes and gives early warning of implant issues, and registry data guide implant selection.
Outcomes
HXLPE. Survivorship is 95-98% at 10-15 years, with a dramatic reduction in osteolysis and lower revision rates than conventional polyethylene. Data beyond 15 years are now available and show sustained low wear rates and no late mechanical failures.
Ceramic-on-ceramic. Survivorship is 97-99% at 10 years, with the lowest wear rates; fracture and squeaking are rare.
- 10-Year Survival
- 95-98%
- Key Advantage
- Low wear, proven
- 10-Year Survival
- 97-99%
- Key Advantage
- Lowest wear
- 10-Year Survival
- 96-98%
- Key Advantage
- Low wear, no squeak
- 10-Year Survival
- 85-90%
- Key Advantage
- Abandoned for HXLPE
Registry data. In the AOANJRR, HXLPE has lower revision rates than conventional polyethylene, ceramic has the lowest revision for wear, and metal-on-metal has the highest revision rate; it was abandoned because of metal ions and ALVAL.
Clinical Relevance - Particle Disease
The pathway. Particle-induced osteolysis runs in sequence:
- Wear particles are generated at the bearing surfaces
- Macrophages attempt to phagocytose the particles
- Particles resistant to digestion cause frustrated phagocytosis, which activates the macrophages
- The macrophages release pro-inflammatory cytokines (IL-1, TNF-α, IL-6)
- The cytokines stimulate osteoclast differentiation (RANK-RANKL)
- Osteoclasts resorb bone around the implant
- Progressive osteolysis leads to loosening
Particle size matters. The phagocytosable range is 0.1-1 μm, and 0.2-0.8 μm is the fraction that most reliably activates macrophages. Larger particles cannot be phagocytosed and are less inflammatory; smaller particles are generated in billions and act cumulatively. By volume of debris, polyethylene exceeds metal, which exceeds ceramic.
How it presents. Osteolysis is often asymptomatic until advanced. It shows as radiolucent lesions on radiographs, then as progressive loosening or a pathological periprosthetic fracture.
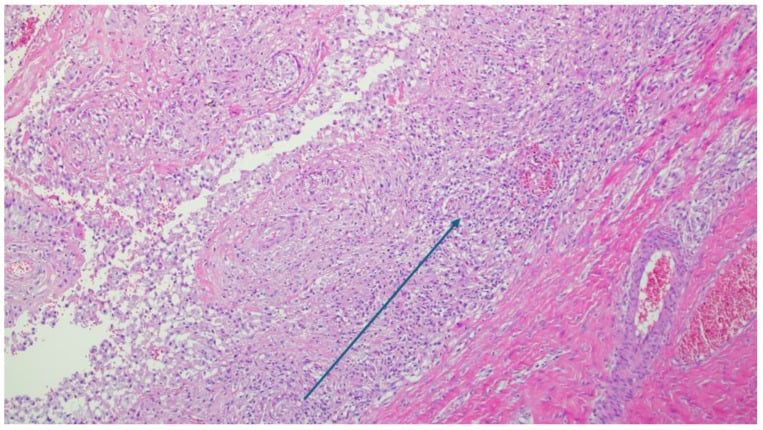
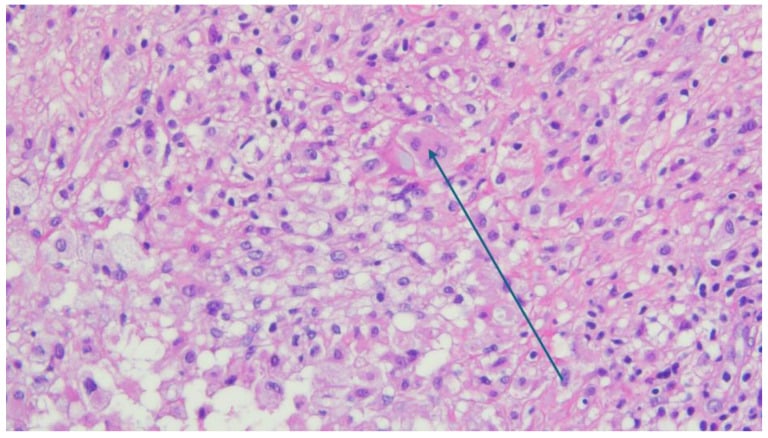
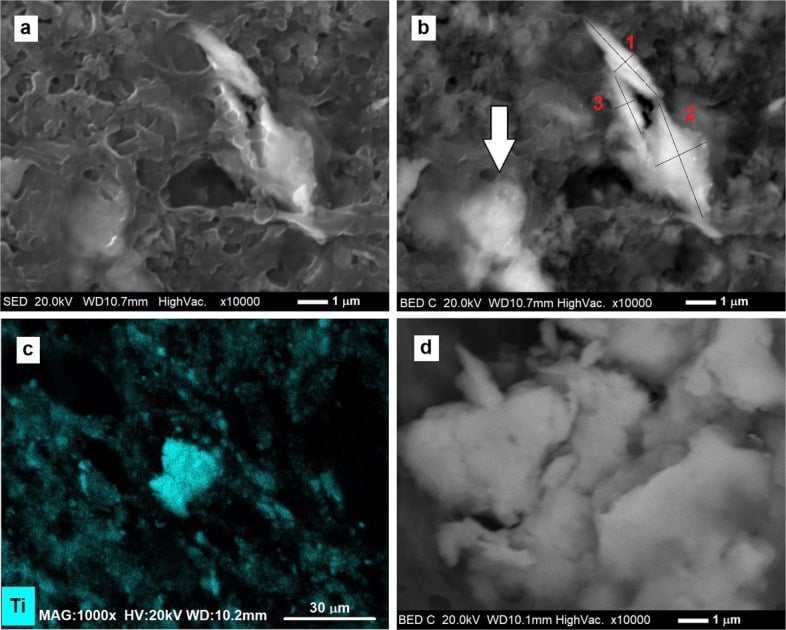
The Effective Joint Space: Why Osteolysis Occurs at a Distance
The Evidence Base notes that solid fixation limits particle migration. The unifying concept is the effective joint space.
The concept (Schmalzried). The effective joint space is the entire region that a prosthetic joint's fluid, and therefore its wear debris, can reach, which is far larger than the articulation itself. Pressurised joint fluid pumps submicron particles along any accessible interface.
Why lysis appears remote from the bearing. Debris tracks down the bone-implant (or bone-cement) interface, along the stem and, classically, through empty acetabular screw holes and around screws. The result is focal, scalloped osteolytic lesions remote from the bearing surface, which is why periacetabular or peri-stem lysis can appear where the bearing itself is not.
Fixation controls migration. A well-bonded, circumferentially porous-coated or fully cemented interface limits the effective joint space and confines debris. Hence solid fixation reduces particle migration and osteolysis, and practice has moved away from non-circumferential coatings and unnecessary screw holes.
The clinical corollary. Osteolysis is often silent and periprosthetic rather than at the joint line, so surveillance radiographs (and CT) must be read along the whole length of the implant, not just at the bearing.
Guidelines, Registries & Global Practice
Global epidemiology: Particle-induced osteolysis and aseptic loosening were historically the leading causes of late revision in metal-on-conventional-polyethylene hips. The widespread shift to HXLPE has substantially reduced wear-related revision worldwide, while metal-on-metal bearings were largely abandoned after 2010 following adverse-reaction-to-metal-debris signals.
- Position on bearings & wear
- Supports HXLPE as standard bearing; evidence-based work-up for painful MoM hips
- Position on bearings & wear
- Bearing selection guidance with registry-informed implant benchmarks (ODEP ratings)
- Position on bearings & wear
- Emphasises tribology principles, component positioning to limit edge loading
- Position on bearings & wear
- Endorse HXLPE and ceramic bearings; structured MoM surveillance
- Position on bearings & wear
- Issued alerts mandating surveillance of metal-on-metal hips (ion levels, MARS-MRI)
Registry evidence: National joint registries (NJR England/Wales, AJRR US, AOANJRR Australia, Swedish SHAR, Norwegian, NZJR) consistently show lower revision rates for HXLPE versus conventional polyethylene and the highest revision rates for large-head metal-on-metal bearings, driving global practice change. Registries also underpin implant benchmarking schemes (e.g. ODEP) used internationally.
High- vs limited-resource practice: In high-resource settings HXLPE and ceramic bearings are routine, with CT and MARS-MRI available for surveillance. In limited-resource settings conventional polyethylene and metal-on-poly remain common due to cost, and surveillance relies mainly on serial plain radiographs; metal ion assays and metal-artefact-reduction MRI may be unavailable.
Related pages: Tribology and Wear is the parent subject and holds the half this page does not - friction, the lubrication regimes and the Stribeck curve that determine whether the surfaces touch at all; read it first if the question is why a bearing wears, and this page if the question is how. Polyethylene: UHMWPE and XLPE carries the polymer chemistry behind crosslinking, remelting and annealing, and Highly Crosslinked Vitamin E Polyethylene the antioxidant route that the Galea trial tested; Ceramics covers the material whose fracture risk the ceramic-on-ceramic decision turns on, and THA Bearing Surfaces is where the bearing choice is actually made. THA Wear and Osteolysis applies all of this to the hip clinically, including surveillance and the bedding-in versus true-wear distinction that makes early radiographic rates unreliable. THA Aseptic Loosening and TKA Aseptic Loosening are the endpoint particles produce, Acetabular Bone Loss (Paprosky) grades the defect they leave, and Revision THA with Femoral Impaction Bone Grafting covers reconstructing it; Periprosthetic Joint Infection is the diagnosis that must be excluded before any lysis is called aseptic. Metal-on-Metal Complications, Trunnionosis and Taper Corrosion and Corrosion Mechanisms cover debris generated by processes other than articular wear - including at a taper in a hip with no metal-on-metal bearing at all; and Implant Fracture Biomechanics with Viscoelasticity explain the material behaviours - fatigue crack propagation and creep - that must be separated from wear when a retrieval is examined.
Controversies & Areas of Uncertainty
Remelting (above the melt transition) eliminates free radicals most completely but lowers crystallinity and mechanical strength. Annealing (below melt) preserves mechanical properties but leaves residual free radicals and a residual oxidation risk. The optimal trade-off remains debated; vitamin E stabilisation is an attempt to sidestep it.
HXLPE is the clear standard at the hip, but the knee sees higher contact stress, multidirectional motion and thinner inserts where reduced toughness could matter. Registry signals are favourable but long-term superiority over conventional PE in TKA is not yet definitively proven.
The commonly cited ~7 ppb cobalt/chromium action level is a guide, not a hard cut-off. Symptoms, imaging and trends matter more than a single value, and authorities differ on exact thresholds and surveillance intervals.
CoC offers the lowest wear and is attractive in young, active patients, but fracture risk (rare with fourth-generation delta ceramic), squeaking and cost temper enthusiasm versus ceramic-on-HXLPE. Best bearing for the young patient is unresolved.
MCQ Practice Points
Q: What are the four main types of wear in orthopaedic implants? A: Adhesive (cold welding), Abrasive (scratching), Fatigue (delamination), and Third-body (trapped particles). Remember AAFT.
Q: What is the mechanism of particle-induced osteolysis? A: Wear particles are phagocytosed by macrophages → activated macrophages release cytokines (IL-1, TNF-α) → cytokines stimulate RANK-RANKL pathway → osteoclast activation → bone resorption.
Q: How does highly cross-linked polyethylene reduce wear? A: Cross-linking by irradiation creates bonds between polymer chains, reducing plastic deformation and adhesive/abrasive wear by 50-90%. Post-irradiation treatment (remelting/annealing/vit E) removes free radicals to prevent oxidation.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 65-year-old man presents with progressive periacetabular osteolysis 12 years after primary cemented THA. PE wear measures 3mm. He is minimally symptomatic. How do you manage him?”
“A retrieved polyethylene liner shows sheet-like surface delamination with a subsurface white band. The examiner asks you to classify the wear mechanisms acting on a bearing surface and explain what this retrieval demonstrates.”
“A 58-year-old woman has groin pain three years after a large-head metal-on-metal THA. Radiographs show well-fixed components. How do you investigate and manage her?”
Wear Types (AAFT)
- Adhesive: Cold welding and transfer
- Abrasive: Scratching (two-body or three-body)
- Fatigue: Subsurface cracks, delamination
- Third-body: Trapped particles accelerate wear
Osteolysis Pathway
- Particles → Macrophage phagocytosis
- Cytokine release (IL-1, TNF-α)
- RANK-RANKL → Osteoclast activation
- 0.1-1μm phagocytosable, 0.2-0.8μm most activating
HXLPE
- Cross-linking by irradiation
- Remelting/annealing removes free radicals
- Wear reduction 50-90%
- Standard for hip, increasing in knee
Bearing Selection
- MoP with HXLPE: Standard, proven
- CoC: Lowest wear, fracture/squeak risk
- CoP: Low wear, ceramic benefits
- MoM: Abandoned (metal ions, ALVAL)
Evidence Base
Devane et al — XLPE vs UHMWPE RCT
- Double-blinded RCT, 122 patients, minimum 10-year follow-up
- 3-D wear rate 0.03 mm/yr (XLPE) versus 0.27 mm/yr (conventional UHMWPE), p less than 0.001
- Osteolysis prevalence 8% (XLPE) versus 38% (conventional), p less than 0.005
- Revision rate 1.9% (XLPE) versus 14.6% (conventional), p = 0.012
Ingham & Fisher — Biological reactions to wear debris
- It is the concentration of particles in the critical size range, not total wear volume, that drives the biological response
- Critical size range for macrophage activation is 0.2-0.8 micron
- Pre-clinical testing of any bearing must characterise particle size and reactivity, not just wear volume
- Predicted nanometre-scale metal-on-metal debris would raise new biological concerns
Kadoya et al — Wear and osteolysis in TJR
- Polyethylene particle NUMBER (not size) differed between osteolysis-positive and -negative cases
- Critical threshold around 1 x 10^10 particles per gram of tissue for osteolysis
- Macrophages identified as the cells primarily responsible for bone loss
- Solid bone-implant fixation limits particle migration and osteolysis
Dumbleton, Manley & Edidin — Wear rate threshold for osteolysis
- Systematic literature review establishing that osteolysis incidence rises as the polyethylene wear rate rises
- Osteolysis is RARELY observed at a wear rate below 0.1 mm per year - the origin of the threshold used clinically
- A practical threshold of 0.05 mm per year is proposed as the rate that would eliminate osteolysis altogether
- Predicted that crosslinked polyethylenes would reduce osteolysis if in-vivo rates matched in-vitro rates - which they since have
Galea/Bragdon et al — Vitamin E-diffused HXLPE RCT
- First RCT reporting 7-year RSA results for vitamin E-diffused HXLPE (VEPE)
- Mean 7-year proximal head penetration -0.07 mm (VEPE) versus 0.00 mm (moderately XLPE), not significant
- All wear rates below the 0.1 mm/yr osteolysis threshold
- No implants revised for aseptic loosening; acetabular radiolucency linked to greater shell migration
Alshammari et al — Ceramic-on-ceramic at 10+ years
- 235 fourth-generation (BIOLOX delta) CoC THAs, mean 12-year follow-up
- All-cause survivorship 96.7% at 12 years
- Squeaking reported in 9 hips; only 1 required revision for squeaking
- No ceramic liner or head fractures in the cohort
Dion et al — Durability of HXLPE in THA and TKA
- Reviews development and clinical results of HXLPE in hip and knee arthroplasty
- Polyethylene wear and osteolysis identified as principal long-term failure modes
- Second-generation (vitamin E) HXLPE introduced to address oxidative degradation
- Ongoing retrieval and clinical studies needed for longest-term durability