X-Linked Hypophosphataemia (XLH) and Tumour-Induced Osteomalacia (TIO)
- FGF23 is a phosphaturic hormone made by osteocytes; its EXCESS causes RENAL PHOSPHATE WASTING (it downregulates the proximal-tubule sodium-phosphate cotransporters) AND suppresses 1-alpha-hydroxylase, giving an inappropriately LOW (or normal) 1,25-dihydroxyvitamin D - the combination produces HYPOPHOSPHATAEMIA and impaired mineralisation (RICKETS in children, OSTEOMALACIA in adults).
- X-LINKED HYPOPHOSPHATAEMIA (XLH) is the commonest heritable form: an X-linked dominant PHEX gene mutation leads to excess FGF23. Children present with RICKETS, lower-limb BOWING (genu varum/valgum), short stature, bone pain, dental abscesses and enthesopathy; adults have osteomalacia, pseudofractures, enthesopathy and early osteoarthritis.
- TUMOUR-INDUCED (ONCOGENIC) OSTEOMALACIA (TIO) is an ACQUIRED paraneoplastic syndrome in which a usually small, benign PHOSPHATURIC MESENCHYMAL TUMOUR secretes FGF23, causing adult-onset osteomalacia with bone pain, muscle weakness and fractures; the great challenge is LOCALISING the small tumour (functional imaging such as 68Ga-DOTATATE PET/CT, octreotide scintigraphy, and selective venous sampling).
- The BIOCHEMISTRY is distinctive: LOW serum PHOSPHATE with renal phosphate wasting (low TmP/GFR, high fractional phosphate excretion), inappropriately LOW or normal 1,25-vitamin D, NORMAL calcium, NORMAL or HIGH alkaline phosphatase (osteomalacia), normal/mildly raised PTH, and elevated FGF23 - importantly the ALP is NOT low (contrast with hypophosphatasia, where ALP is LOW).
- CONVENTIONAL treatment is oral PHOSPHATE supplements plus ACTIVE vitamin D (calcitriol/alfacalcidol), but this is burdensome and risks GI upset, secondary/tertiary hyperparathyroidism and nephrocalcinosis; the targeted therapy BUROSUMAB, a monoclonal antibody against FGF23, addresses the underlying mechanism and is first-line for XLH (children and adults) and for inoperable/metastatic TIO.
- For TIO, complete SURGICAL RESECTION of the FGF23-secreting tumour is the DEFINITIVE, curative treatment (FGF23, phosphate and symptoms normalise); when the tumour cannot be found or resected, burosumab or conventional phosphate/active-vitamin-D therapy is used. Orthopaedic care addresses pseudofractures, deformity (osteotomy timed around medical optimisation) and enthesopathy.
- “XLH (PHEX, inherited) and TIO (FGF23 tumour, acquired) both = EXCESS FGF23 → renal phosphate wasting + low/normal 1,25-vitD → rickets/osteomalacia.
- “Biochemistry: LOW phosphate + phosphate wasting + low/normal 1,25-vitD + NORMAL calcium + NORMAL/high ALP + high FGF23 (ALP NOT low - unlike hypophosphatasia).
- “TIO: localise the tumour (68Ga-DOTATATE PET) → resection is curative. Burosumab (anti-FGF23) is first-line for XLH and inoperable TIO.
Mechanism: Too Much FGF23
What FGF23 does. FGF23 is a phosphaturic hormone secreted by osteocytes, and normally it keeps phosphate in check. In excess it does two things that cause disease:
- It downregulates the sodium-phosphate cotransporters in the proximal renal tubule, causing renal phosphate wasting and a low serum phosphate
- It suppresses 1-alpha-hydroxylase, so 1,25-dihydroxyvitamin D is inappropriately low or normal when it should rise in response to the low phosphate
The result. Chronic hypophosphataemia and a failure of bone mineralisation: rickets in the growing child and osteomalacia in the adult.
Where the excess comes from. In X-linked hypophosphataemia (XLH), the commonest heritable rickets, an inherited PHEX mutation with X-linked dominant inheritance drives it. In tumour-induced (oncogenic) osteomalacia (TIO), an acquired paraneoplastic syndrome, a tumour secretes it.
XLH vs TIO & Workup
Delay is the defining clinical problem in this pair: both are missed for years, and at different steps. Knowing which kind of delay you are up against tells you what to do about it.
XLH is missed at the diagnosis. Suspect it in a child with rickets, lower-limb bowing (genu varum or valgum), short stature, delayed walking, a waddling gait, bone pain, dental abscesses or a family history. The presentation is non-specific and looks like nutritional rickets, which is far commoner. Confirm with the phosphate-wasting biochemistry and genetics; adults with XLH have osteomalacia, pseudofractures, enthesopathy and early osteoarthritis.
The separator is biochemical and cheap. In nutritional rickets calcium is low or borderline and PTH is high; in XLH calcium is normal, PTH is normal or only mildly raised, and phosphate is low. The test that makes the diagnosis is therefore the one most easily left off the request, and a normal calcium is falsely reassuring. Ask for phosphate explicitly, and confirm renal wasting rather than poor intake with a TmP/GFR.
TIO is missed at the localisation. Suspect it in an adult with new, unexplained osteomalacia, severe hypophosphataemia, bone pain, muscle weakness and fractures, and no family history. Here the biochemistry is usually recognised. The problem is the tumour: usually a small, benign phosphaturic mesenchymal tumour, slow-growing, in bone or soft tissue and able to sit anywhere, commonly in bone of the extremities or in the head and neck.
Finding the tumour. Anatomical imaging alone will not find it, so functional imaging comes first and a negative CT or MRI does not end the search.
- 68Ga-DOTATATE PET/CT
- Octreotide scintigraphy
- Selective venous sampling for FGF23
Why the delay matters. A missed XLH child accrues deformity that later needs correcting. A missed TIO adult is living with an unresected, potentially curable tumour while being treated symptomatically, and that is the stronger reason to keep looking.
The biochemistry of both. The same profile appears in XLH and TIO:
- Low phosphate with renal phosphate wasting: low TmP/GFR and high fractional phosphate excretion
- Inappropriately low or normal 1,25-vitamin D
- Normal calcium
- Normal or high alkaline phosphatase
- Normal or mildly raised PTH
- Elevated FGF23
The alkaline phosphatase is the one to be precise about. Hypophosphatasia shares the "hypophosphat-" name but has a low ALP, is treated with asfotase alfa, and bisphosphonates are contraindicated in it: two very different diseases with opposite treatments. (See our Hypophosphatasia topic.)
Radiographs. Children show rickets, with physeal widening, cupping and bowing. Adults show osteomalacia with Looser-zone pseudofractures, thin linear lucent bands running perpendicular to the cortex. The Looser zone is the classic radiographic sign of osteomalacia from any cause of chronic hypomineralisation, including the FGF23-mediated disorders.
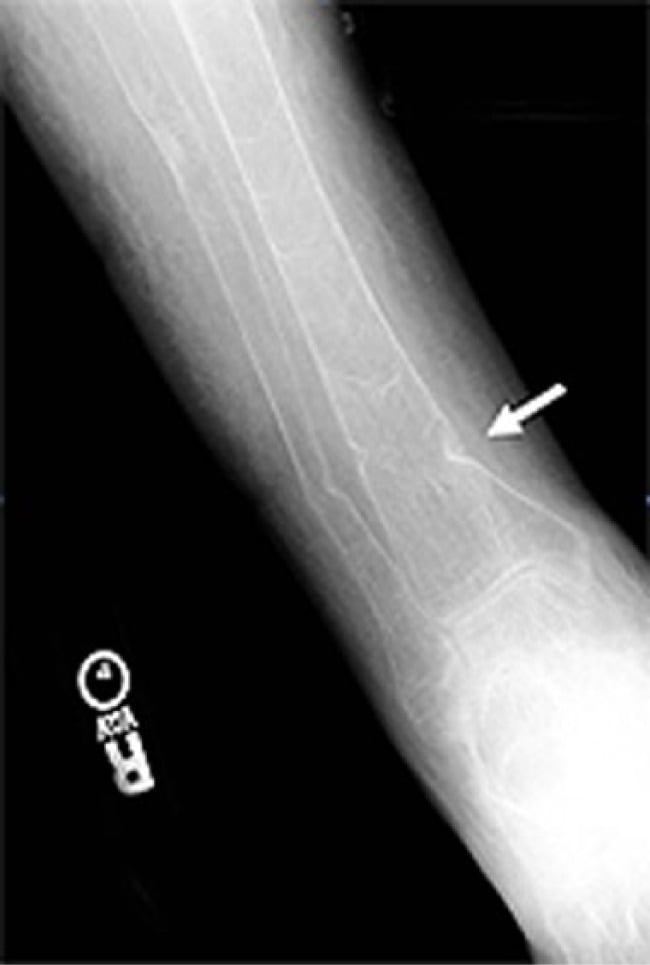
In an adult, keep looking for the tumour until the hunt has genuinely been exhausted, using functional imaging and venous sampling rather than giving up after negative cross-sectional scans. Resection is curative and the disease otherwise persists. Long-term FGF23 blockade controls the biochemistry well enough to remove the pressure to keep searching, which is precisely when a curable disease becomes a permanent one.
The Hypophosphataemic-Rickets Differential
Let PTH, calcium and 1,25-vitamin D sort the causes. Check PTH, calcium, 25- and 1,25-vitamin D, FGF23 and a urine screen. The pattern separates:
- FGF23-mediated (XLH, TIO, and also fibrous dysplasia / McCune-Albright and the autosomal hypophosphataemic rickets): renal phosphate wasting, inappropriately low or normal 1,25-vitamin D, high FGF23, normal calcium
- Nutritional / vitamin-D-deficient rickets or osteomalacia: a different mechanism, with low 25-vitamin D, low or low-normal calcium, and secondary hyperparathyroidism (high PTH) that itself drives the phosphaturia; responds to vitamin D and calcium
- Hereditary hypophosphataemic rickets with hypercalciuria (HHRH, SLC34A3): FGF23-independent renal phosphate wasting with an appropriately high 1,25-vitamin D and hypercalciuria; treated with phosphate alone, since active vitamin D is not needed and would worsen the hypercalciuria
- Fanconi syndrome / proximal tubulopathy: phosphate wasting plus glycosuria, aminoaciduria and bicarbonate loss, a generalised proximal-tubule defect
- Hypophosphatasia: the low-ALP mimic
General rickets, osteomalacia and vitamin-D deficiency are covered in our Rickets, Osteomalacia and Vitamin D Deficiency topics.
Management
Conventional medical therapy. Oral phosphate supplements in divided doses plus active vitamin D (calcitriol or alfacalcidol). It is effective but burdensome, with risks of GI upset, secondary or tertiary hyperparathyroidism and nephrocalcinosis, so calcium, PTH and the renal tract are monitored.
Burosumab. An anti-FGF23 monoclonal antibody that targets the underlying excess FGF23. It is first-line for XLH in children and adults, healing rickets and osteomalacia and improving symptoms, and it is also used for inoperable or metastatic TIO.
Resection for TIO. Complete resection of the FGF23-secreting tumour is definitive and curative: FGF23, phosphate and symptoms normalise. When the tumour cannot be localised or resected, burosumab or conventional therapy is used.
The Orthopaedic Burden & Deformity Surgery
Optimise the biochemistry before you operate. Correct deformity only after medical optimisation with phosphate and active vitamin D or burosumab, and optimise phosphate and vitamin D peri-operatively to support healing. Operating on poorly mineralised, biochemically uncontrolled bone risks delayed union or nonunion, hardware failure and rapid deformity recurrence.
Lower-limb deformity. Genu varum or valgum, with tibial and femoral bowing and torsion. The choice of procedure follows growth and severity:
- Growing child: guided growth (hemiepiphysiodesis) can correct angular deformity while growth remains
- Adult, or severe or multi-apical deformity: corrective osteotomy, for example tibial or femoral
Pseudofractures. Looser zones largely heal with medical control. An impending or displaced one may need fixation.
Enthesopathy. Progressive ossification or calcification of tendon and ligament insertions is characteristic of adult XLH and causes pain and stiffness. In the spine, together with facet hypertrophy and ligament ossification, it can cause spinal canal stenosis with cord or cauda equina compression, a recognised XLH complication to watch for.
The rest of the burden. Early and secondary osteoarthritis, dental abscesses, and the iatrogenic nephrocalcinosis and hyperparathyroidism of conventional therapy.
Guided-growth and osteotomy technique are covered in our Guided Growth and Osteotomy topics, and general spinal stenosis in our Lumbar Spinal Stenosis topic; the point here is the XLH-specific burden and the timing rule.
Mnemonics & Memory Aids
FGF23
Hook:FGF23 excess wastes phosphate and lowers active vitamin D.
ALP TELLS
Hook:Let the ALP tell you: normal/high = FGF23 (XLH/TIO); low = hypophosphatasia.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“An adult presents with osteomalacia, bone pain and severe hypophosphataemia with renal phosphate wasting. What is the likely mechanism, what would you look for, and how is it treated?”
“How does X-linked hypophosphataemia present and how is it managed, and how does the biochemistry differ from hypophosphatasia?”
Mechanism
- Excess FGF23 → renal phosphate wasting + suppressed 1,25-vitamin D
- → hypophosphataemia → rickets (children) / osteomalacia (adults)
- XLH = PHEX (inherited); TIO = FGF23-secreting tumour (acquired)
Biochemistry
- LOW phosphate + renal phosphate wasting (low TmP/GFR)
- Inappropriately low/normal 1,25-vitD; normal calcium; NORMAL/high ALP; high FGF23
- ALP NOT low (contrast with hypophosphatasia)
Diagnosis
- XLH: childhood rickets/bowing + family history (PHEX) + genetics
- TIO: adult osteomalacia, no family history; localise tumour (68Ga-DOTATATE PET, venous sampling)
- Radiographs: rickets (child) / Looser-zone pseudofractures (adult)
Management
- Conventional: oral phosphate + active vitamin D (monitor PTH/nephrocalcinosis)
- Burosumab (anti-FGF23): first-line for XLH; inoperable TIO
- TIO: tumour resection is curative; osteotomy for deformity (optimise phosphate first)
Evidence & Key Studies
X-linked hypophosphatemia and tumour-induced osteomalacia in the era of burosumab: a narrative review
- XLH and TIO are both caused by persistent excess FGF23 leading to renal phosphate wasting and reduced phosphate availability.
- Traditional oral phosphate and active vitamin D have limitations; burosumab directly targets FGF23 and is recommended first-line for XLH (1-17 years and adults).
- For TIO, tumour resection is the definitive treatment (success depends on localisation and surgical expertise), with burosumab or conventional therapy when surgery is not feasible.
Burosumab for FGF23-associated hypophosphatemia in fibrous dysplasia/McCune-Albright syndrome
- FGF23 overproduction can cause hypophosphataemia beyond XLH/TIO - here in fibrous dysplasia/McCune-Albright syndrome.
- Burosumab (anti-FGF23) normalised calcium-phosphate metabolism and markedly reduced alkaline phosphatase, with no further fractures over 24 months.
- Demonstrates the central role of FGF23 and the efficacy of targeting it, while noting more data are needed in non-XLH settings.
The shared FGF23 mechanism of XLH and TIO, the first-line role of burosumab for XLH and the curative role of tumour resection for TIO come from the cited Brandi review, and the central role of FGF23 and the response to burosumab from the cited Stelmachowska-Banas case. The phosphate-wasting biochemistry, the contrast with hypophosphatasia's low ALP, and the rickets/osteomalacia radiology are standard, well-established teaching. (See also our Hypophosphatasia, Rickets/Osteomalacia and Calcium/Metabolic Bone topics.)