Pivot Shift | Graft Selection | Tunnel Placement | Return to Sport
- ACL is PRIMARY restraint to anterior tibial translation
- Pivot shift is the most specific test UNDER ANAESTHESIA (0.98); awake its sensitivity is only ~0.28, so a negative one in clinic excludes nothing
- Wait 3+ weeks post-injury to reduce arthrofibrosis risk
- Anatomic tunnel placement critical - avoid high noon position
- BTB autograft remains gold standard for young athletes
- “Segond fracture = pathognomonic for ACL tear
- “Associated meniscal tears in 50%+ of acute injuries
- “Allograft failure 4x higher in patients under 25
- “STABILITY trial: LET reduces graft failure in high-risk
Overview and Epidemiology
Who. ACL reconstruction runs at about 46 per 100,000 per year in German registry data, with a peak age of 15-25 years. In the same sport, females have a 2-8x higher injury rate than males; the factors are a narrower notch, hormonal influences and neuromuscular patterns, and prevention programmes reduce the risk by 50%. The high-risk sports are soccer, basketball and skiing.
What goes with it. Meniscal tears accompany 50% or more of acute injuries, MCL injury goes with a contact mechanism, and lateral meniscus root tears also occur. The Segond fracture on the radiograph and the bone-bruise pattern on MRI are described under Investigations.
Pathophysiology and Mechanisms
Anatomy. The ACL arises from the posteromedial aspect of the lateral femoral condyle within the intercondylar notch and inserts on the anterior intercondylar area of the tibia, anterolateral to the medial tibial spine. It is 30-35mm long and 10-12mm wide. Its blood supply is the middle genicular artery, and that poor vascularity limits healing.
The two bundles. The anteromedial (AM) bundle is tight in flexion and is the main restraint to anterior translation; the posterolateral (PL) bundle is tight in extension and is the main restraint to rotation. The two work together, and losing the ligament leads to rotational instability, the pivot shift phenomenon.
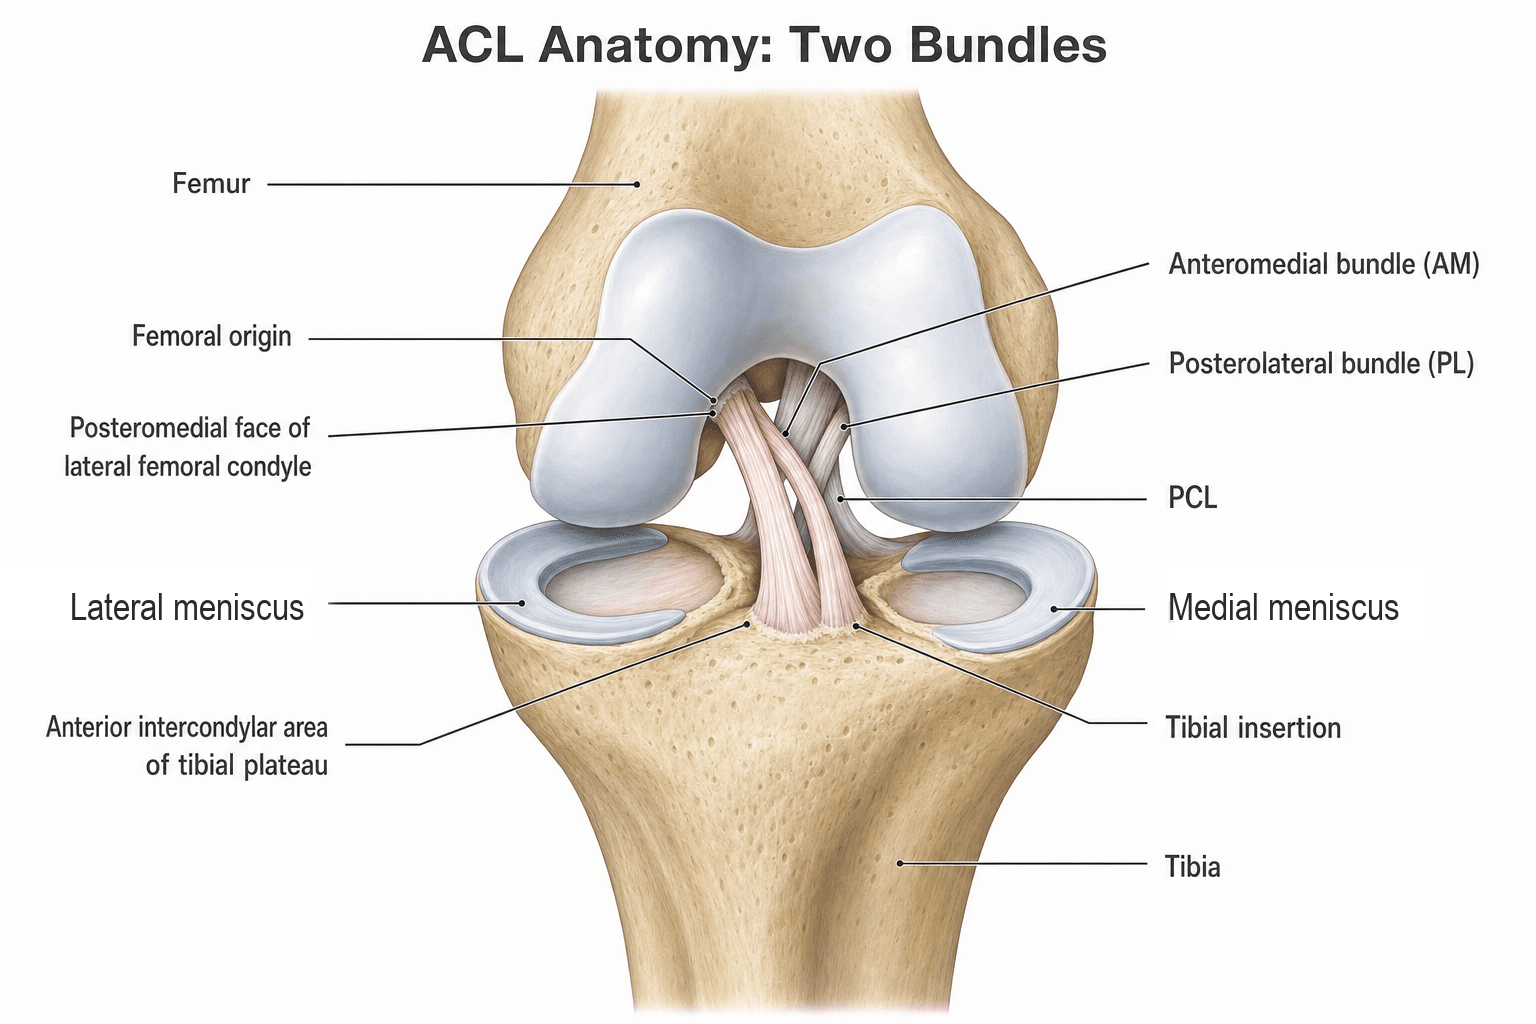
Function. The ACL is the primary restraint to anterior tibial translation, providing 85% of that restraint at 30 degrees of flexion. It also resists internal rotation and hyperextension.
Mechanism. 70% of injuries are non-contact: cutting or pivoting on a planted foot with the knee near extension and a valgus collapse. The other 30% are contact injuries, a direct blow producing valgus or hyperextension. Peak strain on the ligament comes near full extension with valgus and internal rotation, and it takes more than 2000N to fail it.
Anatomic reconstruction aims to recreate the centre of the native footprint. Double-bundle reconstruction has not shown superiority in most studies.
Classification Systems
Injury grade. Most presentations are Grade III, a complete tear.
- Pathology
- Microscopic tears
- Clinical Finding
- Firm endpoint
- Treatment
- Conservative
- Pathology
- Partial macroscopic
- Clinical Finding
- Endpoint present
- Treatment
- Variable
- Pathology
- Complete rupture
- Clinical Finding
- No endpoint, positive pivot
- Treatment
- Reconstruction
Pivot shift grade. The higher the grade, the greater the instability and the worse the functional outcome without surgery.
- Grade 0: negative, no subluxation
- Grade 1 (glide): subtle sliding
- Grade 2 (clunk): obvious subluxation and reduction
- Grade 3 (gross): transient locking with gross subluxation
Chronicity. An acute injury is within 3 weeks, with a haemarthrosis and limited range of motion. Subacute is 3 weeks to 3 months, when examination is better. Chronic is beyond 3 months, with functional instability and possible meniscal damage.
Clinical Assessment
History. The story is a non-contact pivot, a pop, and immediate swelling from a haemarthrosis, followed by giving way with pivoting. Ask about the level of sport, which determines treatment, and about previous injuries, including the contralateral ACL.
Examination. The Lachman test is the most sensitive (85-95%); the anterior drawer is less sensitive; the pivot shift is the most specific. Look for an effusion, a haemarthrosis in the acute knee, and always examine for the associated injuries: the MCL, the menisci and the posterolateral corner.
Flex the knee to 20-30 degrees, stabilise the femur and translate the tibia anteriorly. The test is positive when translation is increased AND the endpoint is soft or absent. Compare with the contralateral side.
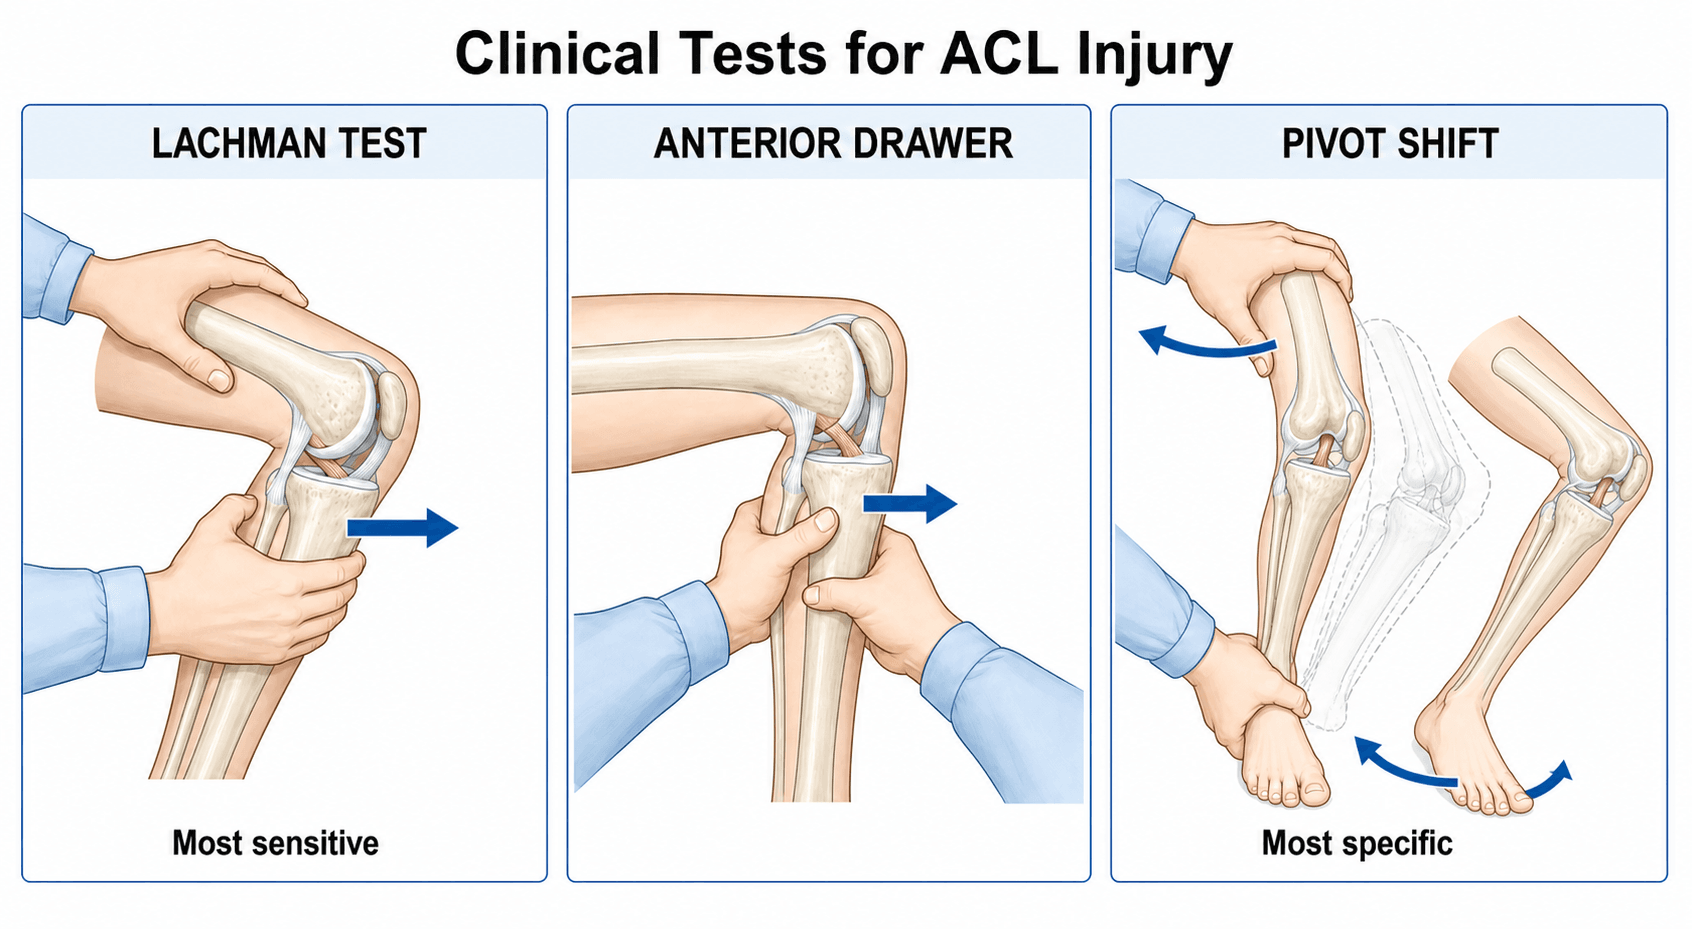
The pivot shift. It is best elicited with the patient relaxed, under anaesthesia, and it demonstrates the functional rotational instability that causes giving way.
The shorthand that Lachman is the most sensitive test and the pivot shift the most specific is true, but incomplete in a way that matters at the bedside — the pivot shift's reputation rests on figures obtained under anaesthesia.
A meta-analysis of 20 studies comparing the same tests in the office and under anaesthesia (DOI, level II) reported:
- Pivot shift: office sensitivity 0.28, specificity 0.81 — under anaesthesia sensitivity 0.73, specificity 0.98
- Lachman: office 0.81 / 0.81 — under anaesthesia 0.91 / 0.78
- Anterior drawer: office 0.38 / 0.81 — under anaesthesia 0.63 / 0.91
Two consequences follow. First, in the awake patient all three tests had comparable specificity (~0.81), so the famous 0.98 belongs to the anaesthetised examination, not the clinic. Second, an office pivot shift at 0.28 sensitivity misses roughly three of every four acute complete ruptures — guarding and hamstring spasm abolish the glide. A negative pivot shift in clinic is therefore close to meaningless and must never be used to reassure; the error direction is under-diagnosis.
An earlier meta-analysis of 28 studies gives similar office-setting figures — Lachman pooled sensitivity 85% (95% CI 83-87) and specificity 94% (92-95), pivot shift sensitivity 24% (21-27) with specificity 98% (96-99) (PMID 16715828). The two analyses differ on how specific the pivot shift is when the patient is awake, so quote the sensitivity confidently and treat the specificity as setting-dependent.
What survives, and it is a lot. Lachman remains the workhorse in clinic. The pivot shift remains the test that captures ROTATIONAL instability, the grade correlates with functional giving-way, and under anaesthesia it becomes near-definitive at 0.98 — which is exactly why it is performed at examination under anaesthesia before reconstruction, and why a persistent pivot shift after reconstruction signals a failed or malpositioned graft.
Differential Diagnosis of the Acute Haemarthrotic Knee
- Distinguishing Feature
- Non-contact pivot, pop, rapid effusion, positive Lachman/pivot shift
- Confirming Test
- MRI; EUA
- Distinguishing Feature
- Lateral patellar apprehension, medial tenderness (MPFL)
- Confirming Test
- MRI - MPFL tear, lateral femoral/medial patellar bone bruise
- Distinguishing Feature
- True locking, joint-line tenderness, slower effusion
- Confirming Test
- MRI
- Distinguishing Feature
- Dashboard/hyperflexion mechanism, positive posterior drawer/sag
- Confirming Test
- Posterior drawer, MRI
- Distinguishing Feature
- Haemarthrosis with fat globules on aspiration
- Confirming Test
- Radiograph/CT
- Distinguishing Feature
- Gross instability in multiple planes, vascular concern
- Confirming Test
- Vascular assessment, MRI
A tense haemarthrosis after a twisting injury is ACL rupture until proven otherwise, but patellar dislocation and peripheral meniscal tears are the commonest mimics. Always exclude a spontaneously reduced knee dislocation when more than one ligament is involved.
Investigations
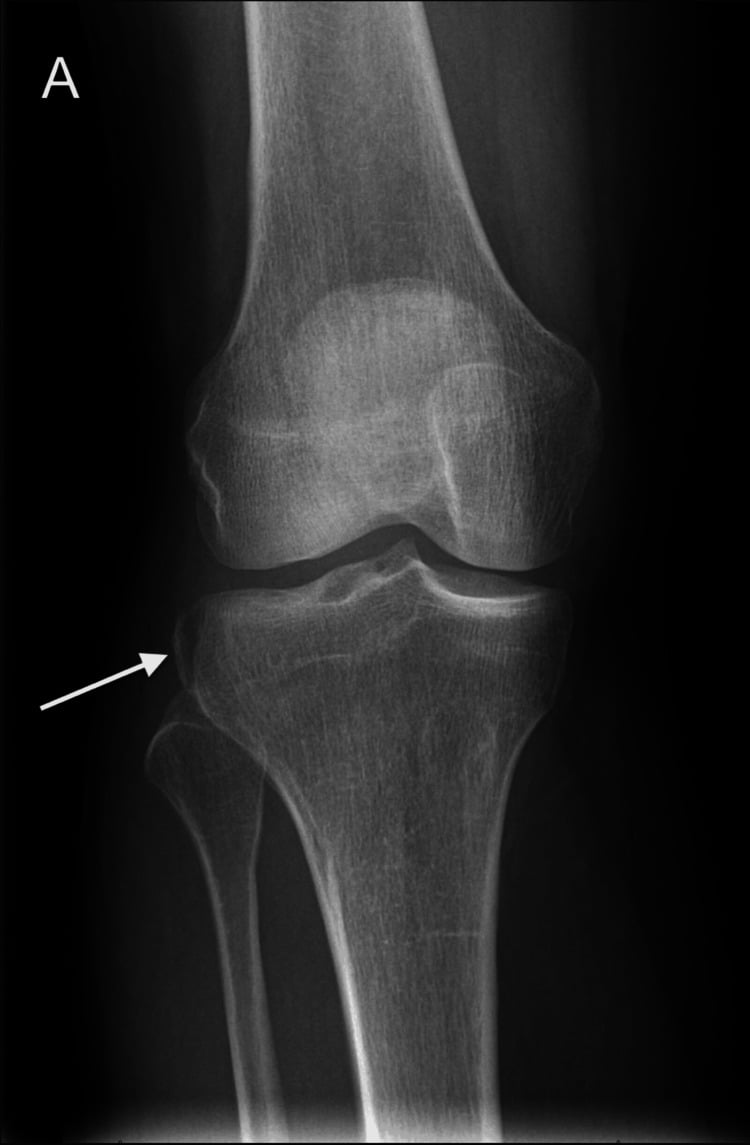
Radiographs. A weight-bearing AP for alignment and fractures, and a lateral for the tibial plateau. Three findings should prompt further evaluation with MRI:
- A Segond fracture
- A tibial spine fracture, common in children
- A deep lateral notch sign, greater than 1.5mm
A Segond fracture is a small avulsion off the lateral tibial plateau, the bony avulsion of the anterolateral ligament. It is pathognomonic for ACL injury and is associated with a high-grade pivot shift.
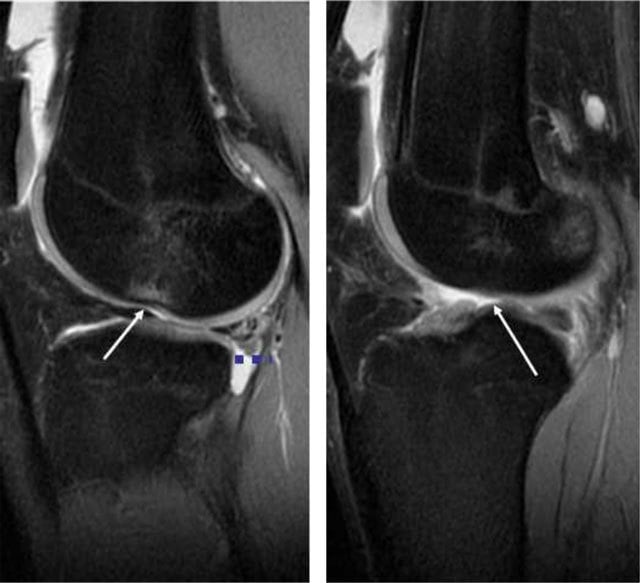
MRI. The direct signs are ACL fibre discontinuity, abnormal signal and an empty notch. The indirect sign is the bone-bruise pattern on the posterolateral tibial plateau and the lateral femoral condyle, the kissing contusion. MRI also shows the associated injuries: meniscal tears and the MCL.
Instrumented laxity. The KT-1000 arthrometer quantifies anterior translation side to side and is useful for research and outcomes:
- Less than 3mm difference: normal
- 3-5mm: suggestive
- Greater than 5mm: highly suggestive of a complete tear
Management Algorithm
Initial management. RICE, aspiration for comfort, a brace, and physiotherapy for range of motion.
The decision. Surgery versus non-operative treatment turns on age, activity, sporting demands, instability and associated injuries. Non-operative rehabilitation suits the low-demand, older patient who is willing to avoid pivoting and has no giving way. Reconstruction is for the young active patient, pivoting sports, recurrent instability, or a repairable meniscus.
What KANON adds. In selected acute tears, structured rehabilitation with optional delayed reconstruction is a valid alternative to immediate surgery: there was no difference in 2-year KOOS, and 61% of the optional-delayed group avoided surgery.
Graft selection. BTB autograft is the gold standard for the young athlete under 25 in contact or pivoting sports, and integrates fastest. Hamstring suits non-contact sports and the patient with a kneeling pain concern. Allograft is for the low-demand patient and is avoided under 25, where its failure rate is 4x higher. Patient factors and activity level guide the final choice; the table sets out the trade-offs.
- Advantages
- Fastest integration
- Disadvantages
- Anterior knee pain
- Best For
- Young athletes, contact sports
- Advantages
- Less knee pain
- Disadvantages
- Slower integration
- Best For
- Non-contact sports
- Advantages
- Strong graft
- Disadvantages
- Quad weakness
- Best For
- Revision surgery
- Advantages
- No donor morbidity
- Disadvantages
- Higher failure in young
- Best For
- Low-demand older than 35
Timing. Wait for full range of motion, extension above all, for the swelling to reduce and for good quadriceps control, and a minimum of 3 weeks from injury; early surgery risks arthrofibrosis. The optimal window is 4-12 weeks, once motion is restored. Bottoni's RCT of hamstring reconstruction found no difference in motion lost between surgery within 21 days and surgery beyond 6 weeks when both arms followed an extension-focused rehabilitation, which challenges a rigid mandatory delay, though it does not exclude arthrofibrosis when motion has not first been restored.
Surgical Technique
Femoral tunnel. Place it at the centre of the native ACL footprint: low and deep on the wall of the lateral femoral condyle, behind the resident ridge, which is the landmark, at about 10:30 in a right knee and 1:30 in a left. The anteromedial portal technique reaches this point. Anatomic placement is essential for restoring rotational stability.
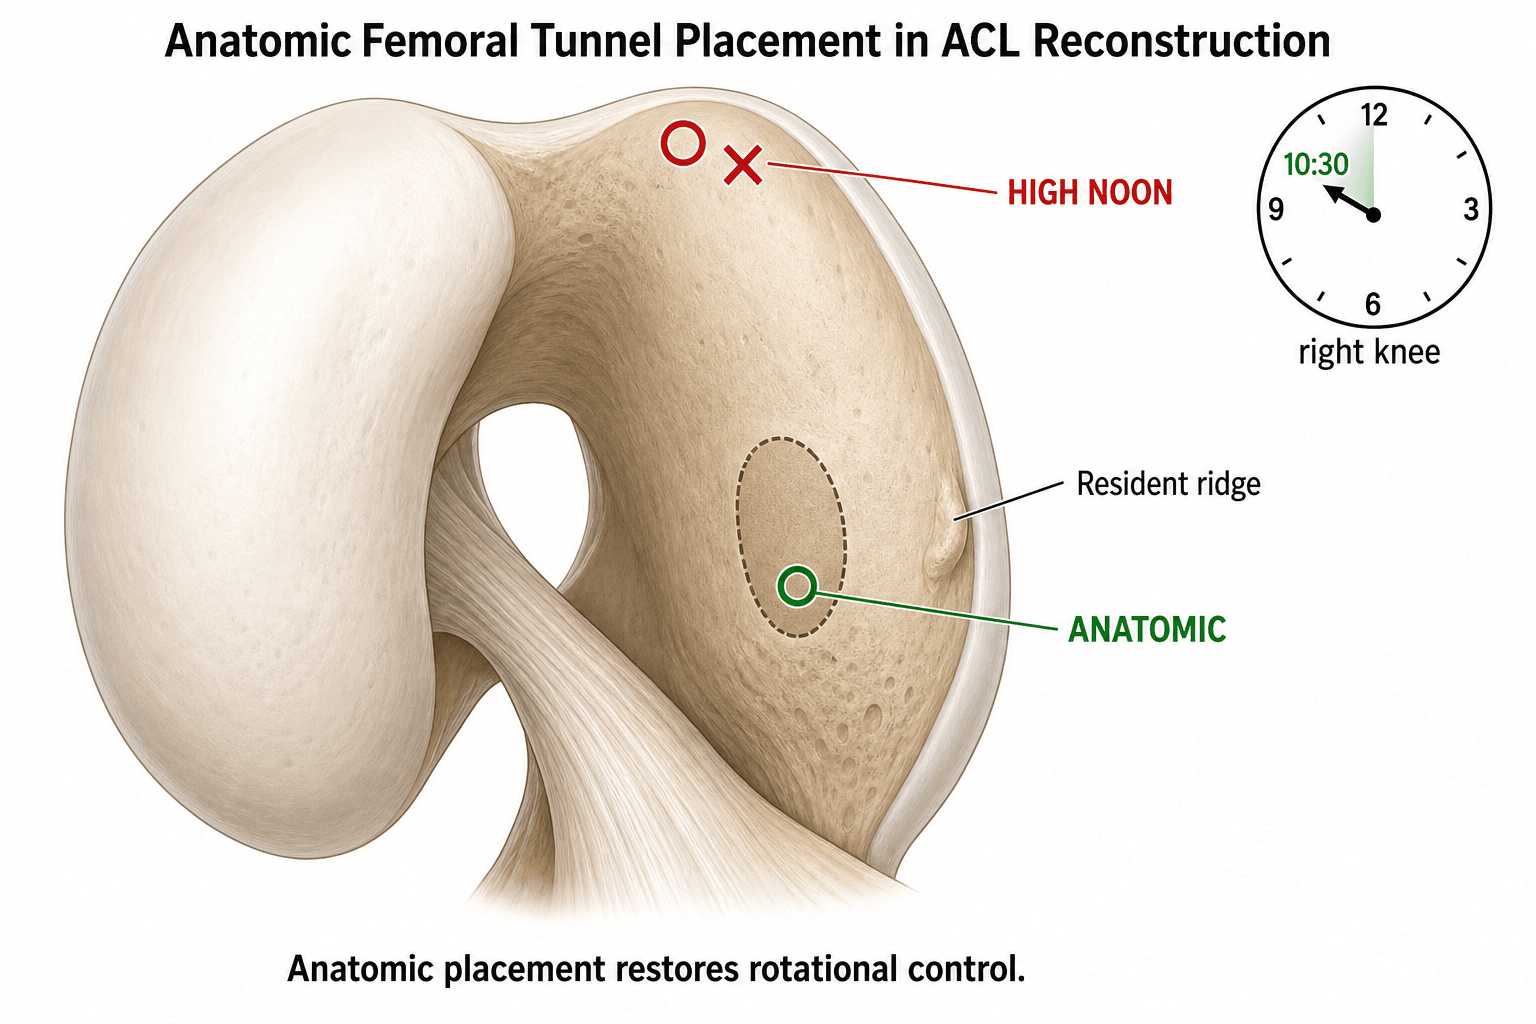
Tibial tunnel. Anterolateral to the medial tibial spine.
The old transtibial technique placed the femoral tunnel too vertically, at high noon. That position is non-anatomic and gives poor rotational control.
Graft preparation. BTB is the central 10mm of the patellar tendon with bone blocks of 9-10mm. Hamstring is gracilis and semitendinosus quadrupled, aiming for a diameter greater than 8mm: in hamstring-autograft cohorts, grafts of 8mm or less had higher early revision rates than grafts over 8mm, especially in patients under 20. Quadriceps is a central strip, with or without bone, of 10mm or more.
Fixation. On the femur, an interference screw for a bone block and suspensory fixation for soft tissue; on the tibia, the interference screw is the gold standard. Tension the graft at 20-30 degrees of flexion with a posterior drawer applied.
The Anterolateral Complex and Lateral Extra-Articular Tenodesis (LET)
The anterolateral complex is a secondary restraint to internal rotation, the motion the pivot shift tests. It comprises the anterolateral ligament (ALL), running from the lateral femoral epicondyle to the anterolateral tibia between Gerdy's tubercle and the fibular head, together with the iliotibial band with its deep Kaplan fibres and the anterolateral capsule.
Lateral extra-articular tenodesis (LET) is an extra-articular augment: classically a strip of iliotibial band (modified Lemaire or MacIntosh technique) left attached distally at Gerdy's tubercle, routed deep to the LCL and fixed to the lateral femur. It reduces anterolateral rotatory instability and offloads the intra-articular graft. Anatomic ALL reconstruction with a free graft is an alternative.
- Why
- Highest re-rupture risk group (STABILITY population)
- Why
- Residual rotatory laxity not controlled by the intra-articular graft alone
- Why
- Greater rotatory load on the graft
- Why
- Protects the revision graft and addresses persistent rotatory instability
- Why
- A recognised driver of graft failure that adds anterior load
In the STABILITY RCT, adding a lateral extra-articular tenodesis to a hamstring ACL reconstruction in young high-risk pivoting patients cut graft rupture from about 11% to 4%. It controls the rotatory instability the intra-articular graft alone may not.
Complications
Arthrofibrosis. The risk factors are early surgery and poor range of motion; prevention is the delay and restored motion described under Management. Treatment is aggressive physiotherapy and lysis.
Graft failure. The highest risk sits with allograft in the young, non-anatomic tunnels and return to sport before 9 months; BTB autograft, anatomic tunnels and delayed return to sport together minimise it. A failed graft is managed by revision reconstruction.
Anterior knee pain. Follows the BTB graft and usually settles.
Infection. A risk of any surgery, prevented by aseptic technique and managed with washout and antibiotics.
ACL Injury in the Skeletally Immature
ACL reconstruction in a child with open physes is a distinct problem because tunnels can injure the growth plate. The distal femoral physis contributes the majority of lower-limb growth, so a misplaced tunnel, a bone block, or hardware across it risks growth arrest, limb-length discrepancy or angular deformity.
Assess skeletal maturity, not just age, by bone age and Tanner stage, and match the technique to it:
- Preferred technique
- Physeal-sparing (all-epiphyseal, or combined intra/extra-articular iliotibial band - Micheli-Kocher)
- Principle
- Avoid crossing the physis entirely
- Preferred technique
- Transphyseal with SOFT-TISSUE graft
- Principle
- Vertical central tunnels, no bone block or fixation across the physis, smaller tunnels
- Preferred technique
- Standard adult reconstruction
- Principle
- Physeal risk negligible
Do not simply wait for maturity in an unstable knee. A complete tear left unreconstructed in an active child leads to recurrent giving way and progressive, often irreparable, meniscal and chondral damage, so age-appropriate reconstruction is favoured over watchful waiting. The displaced tibial eminence (spine) avulsion is the paediatric bony equivalent of a mid-substance tear and is fixed, by arthroscopic suture or screw.
Postoperative Care
Rehabilitation Protocol
Brace locked in extension. Weight-bearing as tolerated with crutches. Range of motion 0-90 degrees. Quad sets, straight-leg raises.
Unlock the brace. Progressive range of motion. Stationary bike. Patellar mobilisation.
Wean crutches. Pool running. Closed-chain exercises. Proprioception.
Straight-line running programme. Progressive resistance. Late agility.
Cutting and pivoting. Sport drills. Psychological readiness.
Full competition once the return-to-sport criteria are met.
Before return to sport: hop test LSI greater than 90%, quadriceps strength greater than 90%, no effusion, full range of motion, ACL-RSI passed, and a minimum of 9 months. Each month of delay reduces the re-injury risk.
Outcomes and Prognosis
What predicts a good result. Anatomic reconstruction, an appropriate graft, compliant rehabilitation, adequate time and an isolated injury.
What predicts a poor one. Malposition, early return to sport, cartilage injury, meniscectomy and non-compliance.
The long term. 50% develop radiographic osteoarthritis by 10-15 years regardless of treatment, and more do if a meniscectomy was performed. The contralateral ACL carries a 10-25% lifetime risk, especially in young females.
Guidelines, Registries & Global Practice
Global Epidemiology
- ACLR incidence ~46/100,000/year (German inpatient data, Domnick 2017)
- Peak age: 15-25 years; second mid-life peak in women
- Males higher absolute volume; females higher per-exposure risk
- Highest-risk sports: football/soccer, basketball, skiing, handball
- ~70% of injuries are non-contact (cutting/landing)
- Female sex (per-exposure), narrow intercondylar notch
- Increased posterior tibial slope
- Generalised ligamentous laxity
- Neuromuscular control (dynamic valgus on landing)
- Prior ACL injury (ipsi- or contralateral)
Major Guidelines, Side by Side
- AAOS CPG 2023
- Reconstruction improves activity/stability in active patients; rehab reasonable in lower-demand
- NICE / UK practice
- Trial of rehab acceptable; reconstruct if instability persists or high demand
- Evidence
- Moderate (KANON, AAOS systematic review)
- AAOS CPG 2023
- Autograft (BTB or hamstring) over allograft, especially in young/active
- NICE / UK practice
- Autograft preferred in young; allograft reserved for selected older/low-demand
- Evidence
- Strong for autograft in young (MOON/MARS)
- AAOS CPG 2023
- Option in high-risk revision/young pivoting patients
- NICE / UK practice
- Increasingly offered to high-risk young pivoting patients
- Evidence
- Level 1 (STABILITY)
- AAOS CPG 2023
- Delay and use objective criteria, not time alone
- NICE / UK practice
- Criteria-based RTS, typically not before 9 months
- Evidence
- Level 3 (Grindem/Delaware-Oslo)
The AAOS 2023 ACL Clinical Practice Guideline (Brophy & Lowry, J Am Acad Orthop Surg) gives 8 recommendations plus 7 options: autograft over allograft in young/active patients, anatomic single-bundle reconstruction, and criteria-based (not purely time-based) return to sport.
Landmark Trials That Shape Practice
- Design
- RCT 121 acute tears
- Take-home
- Rehab + optional delayed ACLR equals early ACLR at 2-5y; many avoid surgery
- Design
- RCT 618, ACLR +/- LET
- Take-home
- LET cut graft rupture 11% to 4% in high-risk young patients
- Design
- Prospective cohort
- Take-home
- Allograft 4x failure vs autograft in young patients
- Design
- 1205 revision ACLRs
- Take-home
- Autograft 2.78x lower re-rupture than allograft at revision
- Design
- Prospective cohort
- Take-home
- Each month RTS delay to 9 months cut re-injury 51%
Global Practice Variation
- Graft default: hamstring dominant in Europe/Scandinavia (~90% in German data); BTB/quadriceps more favoured for high-demand contact athletes elsewhere
- Timing: early reconstruction common in athlete-focused systems; rehab-first with optional delayed ACLR (KANON model) used widely in Scandinavia
- LET use: rising globally after STABILITY, fastest in young pivoting and revision cases
- Surgeon training and registry feedback (e.g. Scandinavian, NZ knee-ligament registries)
- Patient demand profile and sport culture
- Access, theatre capacity and rehab resourcing
- Interpretation of equivalence trials (KANON) vs failure-reduction trials (STABILITY)
ACL injuries are an extremely common viva topic in fellowship examinations worldwide. Know graft selection, the rehab-vs-reconstruct debate (KANON), surgical timing, anatomic tunnel placement, LET indications (STABILITY) and criteria-based RTS (Grindem).
MCQ Practice Points
Q: Primary function of ACL? A: Restraint to anterior tibial translation - 85% of restraint at 30 degrees. Also resists internal rotation and hyperextension.
Q: Most sensitive clinical test for ACL? A: Lachman test (85-95% sensitive). At 20-30 degrees flexion. Assess translation AND endpoint quality.
Q: Most specific clinical test for ACL? A: Pivot shift test. Demonstrates rotational instability causing functional giving way.
Q: What does Segond fracture indicate? A: ACL rupture (pathognomonic). Avulsion lateral tibial plateau. Associated high-grade pivot shift.
Q: Why avoid allograft in young athletes? A: 4x higher failure rate in under 25. Slower incorporation, remodeling issues.
Q: Primary risk of ACL surgery within 3 weeks? A: Arthrofibrosis. Wait for ROM recovery. Optimal timing 4-12 weeks.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 20-year-old male soccer player presents 2 weeks after a non-contact pivoting injury. He heard a pop and had immediate swelling. Examination shows positive Lachman and pivot shift. MRI confirms complete ACL tear without meniscal injury. How would you manage this?”
“A 30-year-old female recreational skier needs ACL reconstruction but is concerned about anterior knee pain as she kneels frequently for work. She asks about graft options. What would you discuss?”
“A 23-year-old presents 18 months after hamstring ACL reconstruction. He returned to soccer at 7 months and now has recurrent instability. MRI shows graft rupture. CT shows vertical femoral tunnel. How would you approach this?”
Clinical Tests
- Lachman: Most sensitive 85-95%
- Anterior drawer: Less sensitive
- Pivot shift: Most specific
- Compare endpoint quality
Graft Selection
- BTB: Gold standard young athletes
- Hamstring: Less anterior knee pain
- Quad: Growing popularity
- Allograft: Over 35 only (4x failure young)
Surgical Timing
- Wait 3+ weeks post-injury
- Regain full ROM extension
- Early surgery = arthrofibrosis
- Optimal: 4-12 weeks
Tunnel Placement
- Anatomic = center of footprint
- Avoid high noon non-anatomic
- Use anteromedial portal
- 10:30 right or 1:30 left
Return to Sport
- Minimum 9 months post-op
- Hop test LSI greater than 90%
- Quad strength greater than 90%
- Each month delay = 51% less re-injury
Evidence Base and Key Studies
KANON Trial - Early ACLR vs Rehab + Optional Delayed
- RCT, 121 young active adults with acute ACL tear
- Early ACLR + rehab vs rehab + optional delayed ACLR
- No difference in 2-year KOOS (between-group 0.2 points)
- 61% of the optional-delayed group avoided surgery
MARS Cohort - Graft Choice in Revision ACLR
- 1205 revision ACLRs, 83 surgeons, 52 sites
- Autograft predicted better 2-year IKDC and KOOS sport/QoL
- Graft re-rupture 3.3% at 2 years
- Autograft 2.78x less likely to re-rupture vs allograft
Timing of ACL Reconstruction (Hamstring)
- RCT, 69 patients, early (within 21 days) vs delayed (beyond 6 weeks)
- Hamstring autograft, identical extension-focused rehab in both arms
- No difference in postoperative range of motion lost
- No difference in KT-1000 stability or subjective scores
STABILITY Trial - LET
- RCT ACLR +/- lateral extra-articular tenodesis
- 618 patients randomized
- ACLR + LET: 4% graft rupture
- ACLR alone: 11% graft rupture
Return to Sport Timing
- 106 pivoting-sport athletes, prospective 2-year cohort (Delaware-Oslo)
- Reinjury rate reduced 51% for each month RTS was delayed up to 9 months (no further reduction after 9 months)
- Returning to level I sport gave a 4.3x higher reinjury rate; failing RTS criteria 38.2% reinjured vs 5.6% who passed
- More symmetrical quadriceps strength before return was protective
Allograft Failure in Young
- MOON prospective longitudinal cohort (model built on 281 ACLRs, validated on a further 645)
- Allograft reconstruction carried ~4x the odds of graft rupture versus autograft
- Age was an independent predictor: odds of rupture rose ~2.3x for each 10-year decrease in age, highest in the 10-19 age group
- Graft type and patient age were the significant predictors of failure