Overgrowth, Hemihypertrophy & Tumour Risk
- Beckwith-Wiedemann syndrome is a rare imprinting/overgrowth disorder (about 1 in 10,000 live births) caused by dysregulation of imprinted genes at 11p15.5 (IGF2/H19 and CDKN1C).
- Diagnosis can be made on clinical criteria where molecular testing is unavailable.
- Lateralised overgrowth (hemihypertrophy) producing limb-length discrepancy is the main reason a child with BWS comes to the orthopaedic surgeon.
- The embryonal-tumour predisposition (Wilms tumour, hepatoblastoma) makes surveillance mandatory, and lateralised overgrowth is itself a marker of higher tumour risk.
- A surgeon assessing a child with lateralised overgrowth must consider BWS and ensure the child is in a tumour-surveillance programme.
- Treat the discrepancy on its predicted size at maturity: timed epiphysiodesis of the longer limb or, less commonly, lengthening, within a multidisciplinary team.
- “Beckwith-Wiedemann = 11p15 imprinting/overgrowth disorder (~1 in 10,000): macrosomia, macroglossia, abdominal wall defects (omphalocele), neonatal hyperinsulinism/hypoglycaemia.
- “Orthopaedic relevance = lateralised overgrowth (hemihypertrophy) → limb-length discrepancy.
- “Embryonal-tumour predisposition (Wilms tumour, hepatoblastoma) → mandatory surveillance (abdominal ultrasound +/- AFP); lateralised overgrowth is a tumour-risk marker.
Overview and Epidemiology
What it is. Beckwith-Wiedemann syndrome (BWS) is a rare imprinting and overgrowth disorder caused by dysregulation of imprinted genes at chromosome 11p15.5, principally IGF2/H19 and CDKN1C. It combines pre- and postnatal overgrowth with a predisposition to embryonal tumours.
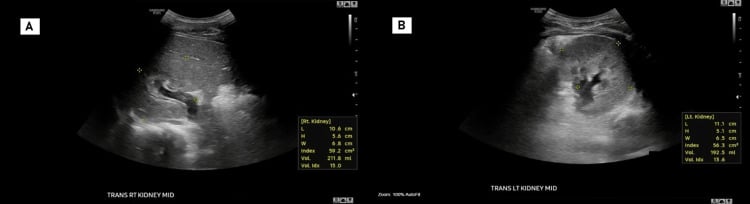
The systemic picture. The features include macrosomia, macroglossia, anterior abdominal wall defects (omphalocele or exomphalos, umbilical hernia), neonatal hyperinsulinism with hypoglycaemia, visceromegaly (nephromegaly, hepatomegaly) and ear creases or pits.
Why the orthopaedic surgeon sees it. Lateralised overgrowth (hemihypertrophy or hemihyperplasia) produces a limb-length discrepancy and limb or segment asymmetry, and that is the main reason a child with BWS reaches orthopaedic clinic. The discrepancy itself is straightforward to treat, within the multidisciplinary care described under management.
The cancer caveat. BWS predisposes to embryonal tumours, especially Wilms tumour (nephroblastoma) and hepatoblastoma, and lateralised overgrowth is itself a marker of higher tumour risk. The overgrowth is therefore not only a limb-length problem: a surgeon assessing a child with lateralised overgrowth or limb-length discrepancy must consider BWS (and related overgrowth syndromes) and ensure the child is in a tumour-surveillance programme.
Missing the syndromic diagnosis behind isolated hemihypertrophy is the error to avoid. A child presenting with hemihypertrophy and limb-length discrepancy may have BWS or a related overgrowth syndrome, and early detection of the tumour markedly improves outcome.
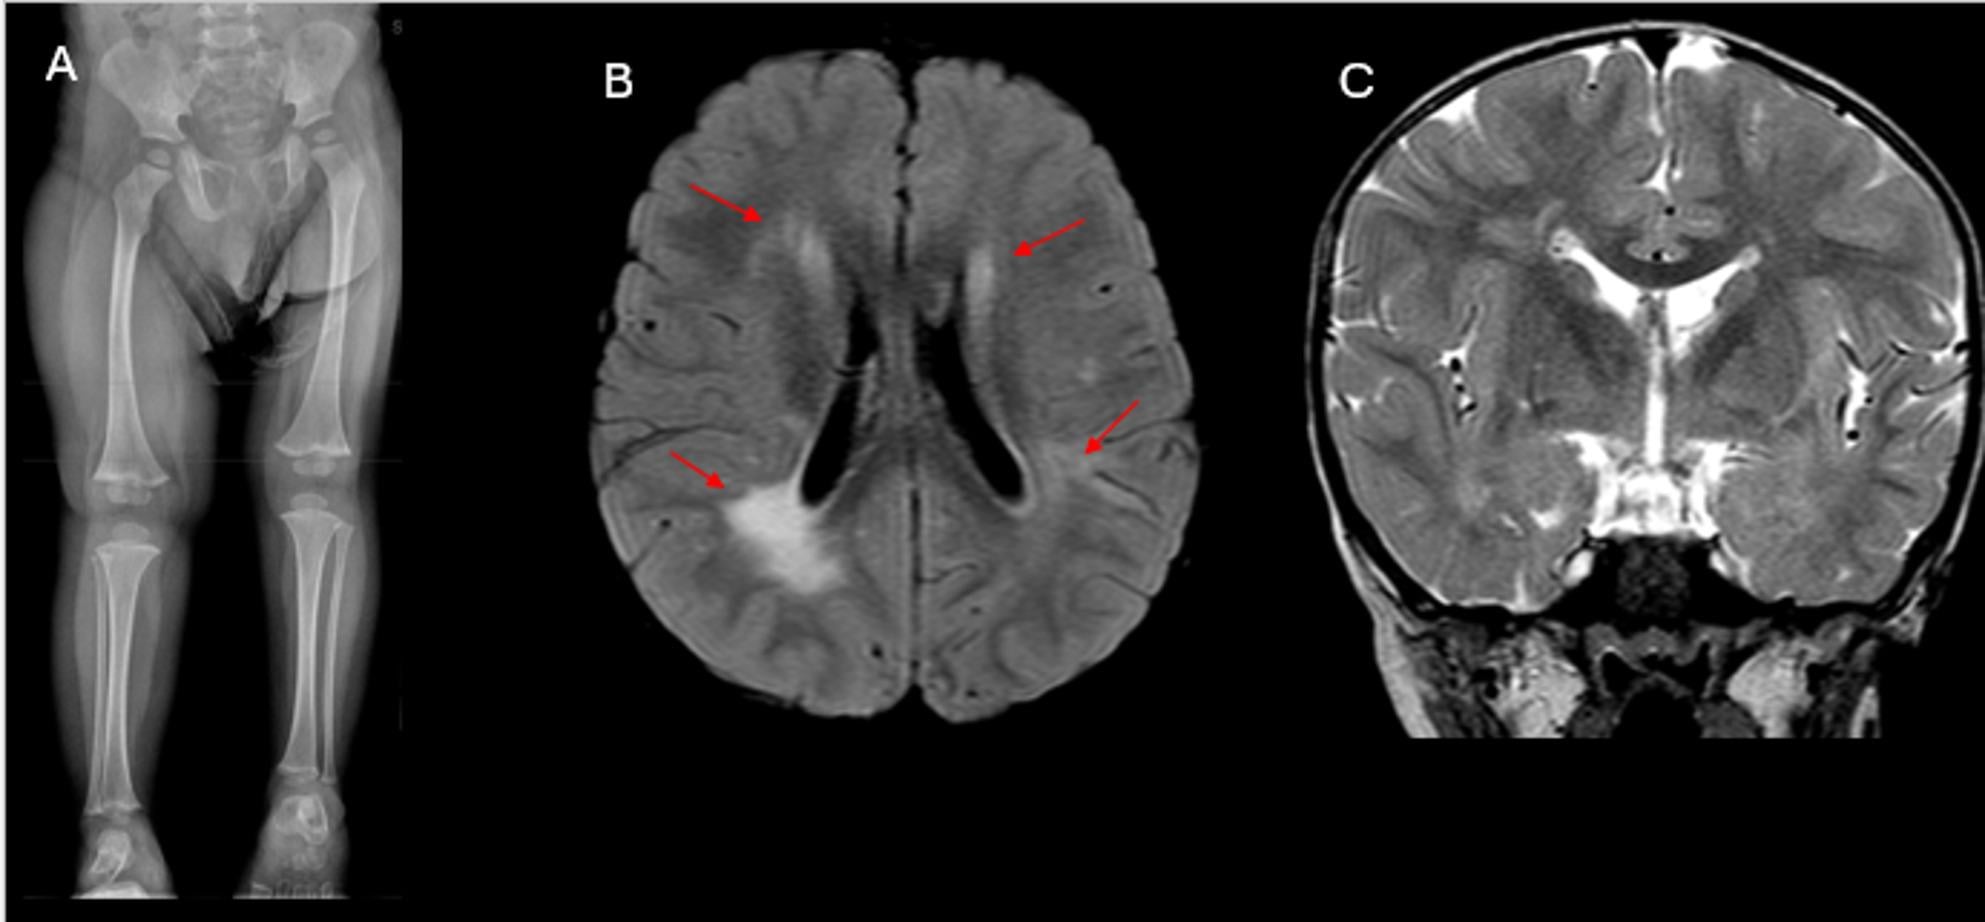
How common. The prevalence is about 1 in 10,000 live births (Hailu 2023; consensus figures), almost certainly an underestimate because milder Beckwith-Wiedemann spectrum presentations go unascertained.
Who gets it. About 85% of cases are sporadic, and the familial minority is driven mainly by maternally transmitted CDKN1C mutations. Two epidemiological quirks are worth knowing for the exam. There is an excess of monozygotic (predominantly female) twins (Weksberg 2005), the imprinting error arising around pre-implantation imprint maintenance. And BWS is over-represented among children conceived by assisted reproductive technology, an association shared with other imprinting disorders and noted in the international consensus (Brioude 2018).
Pathophysiology: The Imprinting Genetics and Why the Subtype Drives Tumour Risk
Two imprinted domains. Two imprinting centres at 11p15.5 set the balance of growth. IC1 controls IGF2, a paternally expressed growth promoter, and H19, which is maternally expressed. IC2 controls CDKN1C, a maternally expressed growth suppressor, and KCNQ1OT1. BWS results from over-expression of the growth driver IGF2, loss of the growth suppressor CDKN1C, or both.
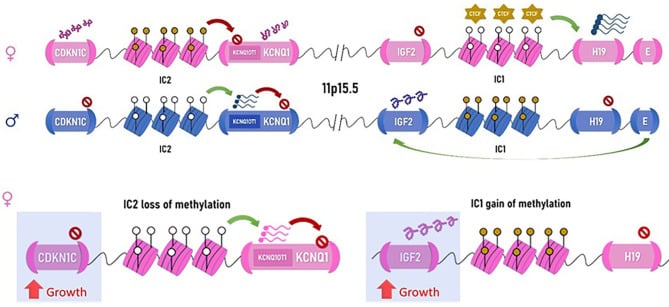
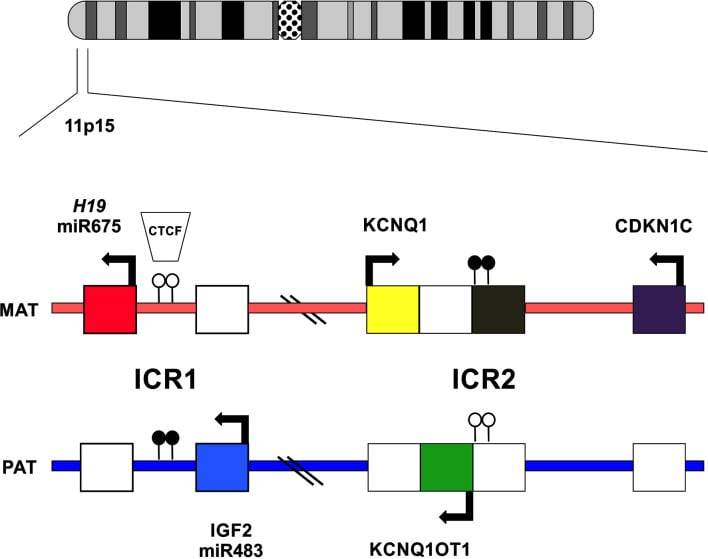
The molecular mechanisms. Most are sporadic:
- Loss of methylation at IC2 - about 50%, the commonest
- Paternal uniparental disomy of 11p15 - about 20%, usually mosaic
- Gain of methylation at IC1 - about 5-10%
- CDKN1C loss-of-function mutations - about 5%, the main inherited (familial) form
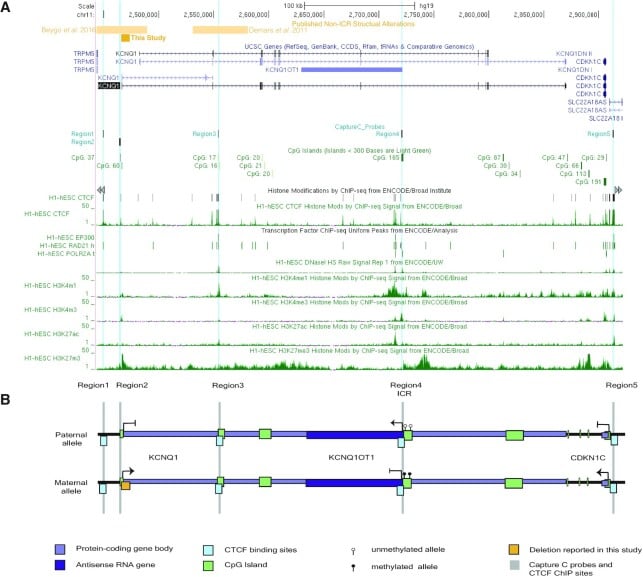
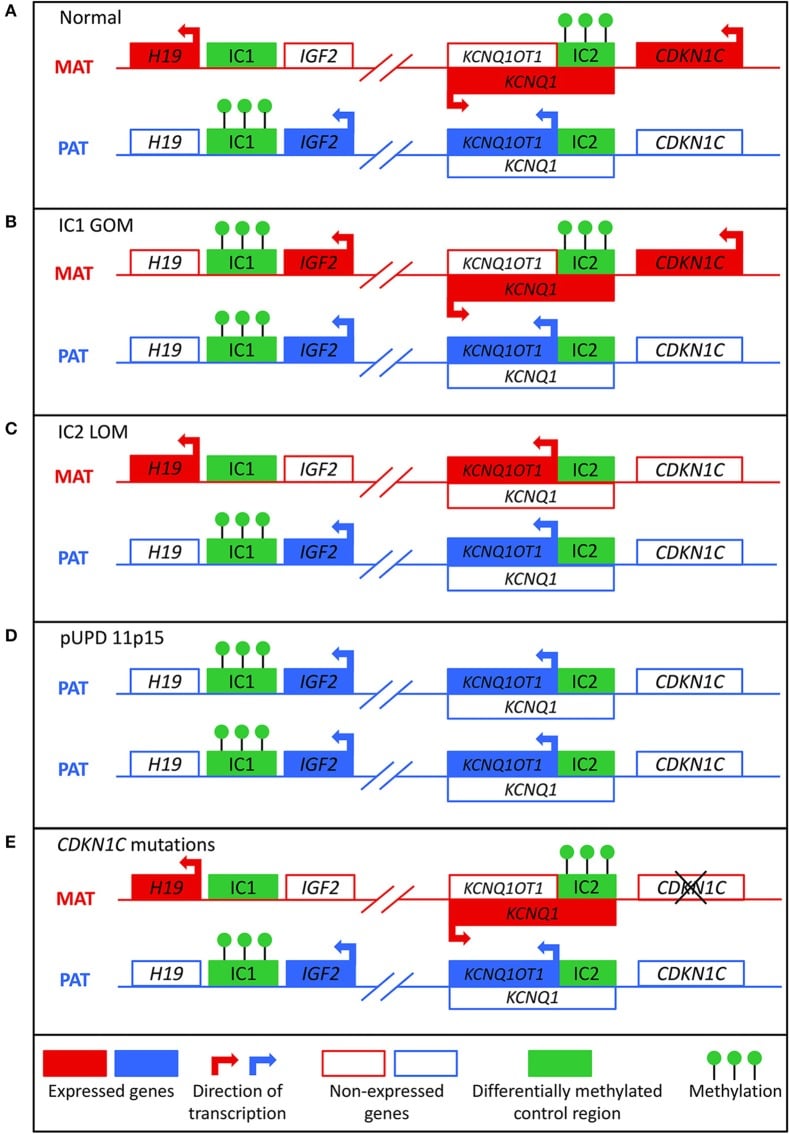
Why the subtype matters. Embryonal-tumour risk varies by molecular subtype. IC1 gain of methylation and paternal uniparental disomy carry the highest Wilms-tumour risk; IC2 loss of methylation carries a lower tumour risk and is more associated with hepatoblastoma, and CDKN1C mutations carry a relatively low tumour risk. The genotype therefore guides how intensively to surveil, and molecular testing is worthwhile where available.
Two caveats. In the largest assembled series of BWS-associated hepatoblastoma (Klein 2023), paternal uniparental disomy was the commonest genotype (38%) and IC2 loss of methylation came second (14%). The same series showed that a blood genotype can misclassify tissue risk, which limits how far the genotype can be used to relax surveillance (below).
Diagnosis: The Consensus Clinical Score
Molecular or clinical. Molecular testing confirms most cases: methylation analysis of the 11p15.5 imprinting centres, with upd(11)pat and CDKN1C sequencing as indicated. BWS can also be diagnosed clinically where testing is unavailable, as in the Hailu case report, and the Brioude 2018 international consensus provides the scoring system.
- Features
- Macroglossia; omphalocele (exomphalos); lateralised overgrowth; bilateral or multifocal Wilms tumour / nephroblastomatosis; prolonged hyperinsulinism (over 1 week); characteristic pathology (e.g. adrenal cytomegaly, placental mesenchymal dysplasia)
- Points
- 2 each
- Features
- Macrosomia; umbilical hernia or diastasis recti; nephromegaly or hepatomegaly; ear pits or creases; polyhydramnios; transient neonatal hypoglycaemia; haemangiomas; structural cardiac anomalies
- Points
- 1 each
- Features
- Score 4 or more = clinical diagnosis (even without a molecular result); score 2 or more = molecular testing indicated; score under 2 does not exclude the spectrum if suspicion persists
- Points
- Thresholds
Where the orthopaedic surgeon fits. The surgeon's row is lateralised overgrowth. A child referred for limb-length discrepancy with hemihypertrophy already holds a 2-point cardinal feature, and the consultation should prompt the question: has this child been assessed for BWS and enrolled in tumour surveillance?
Investigations & The Tumour Surveillance Protocol
The protocol. Two tests, each aimed at one tumour:
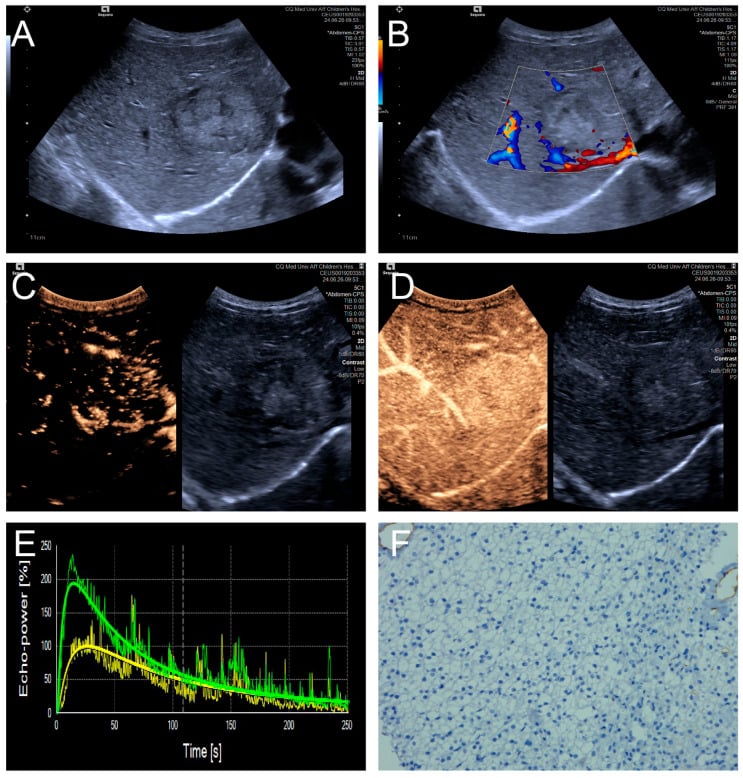
- Abdominal (renal) ultrasound every 3 months from diagnosis until about age 7-8 years, to detect Wilms tumour (and nephroblastomatosis) early
- Serum alpha-fetoprotein (AFP) for hepatoblastoma, historically every few months in the first few years, and increasingly reserved for, or intensified in, the higher-risk IC1 and paternal-UPD genotypes
How big the risk is. The tumour risk quoted from classic BWS cohorts is 8 to 10 percent overall, and it is genuinely higher with IC1 gain of methylation and paternal uniparental disomy. Isolated lateralised overgrowth without full BWS still carries roughly 5 percent Wilms risk, which is why it is surveilled in its own right.
Why it stops around 7-8 years. Embryonal tumours present in early childhood: roughly 95 percent of Wilms tumours occur by about age 7, which is the actual basis for the cut-off. That leaves a real residual. A child with isolated hemihypertrophy has been reported developing a Wilms tumour at age 9, after the surveillance window closed, so stopping is a reasonable trade rather than a guarantee, and new abdominal symptoms after the window still deserve imaging rather than reassurance.
Do not de-escalate on a blood genotype. The Klein hepatoblastoma series (50 patients) found epigenotype mosaicism: the 11p15 alteration differed between blood, tumour and normal liver in the same child, so a reassuring blood result does not reliably mean low tissue risk. Those authors recommend universal screening for all patients with BWS rather than genotype-restricted screening.
The spectrum is not classic BWS. A separate spectrum-wide analysis likewise found that blood testing results are not synonymous with tissue testing results, and that risk across the wider Beckwith-Wiedemann spectrum does not simply mirror classic BWS. Use the genotype to raise vigilance, not to withdraw it.
Management: Orthopaedic Treatment of the Limb-Length Discrepancy
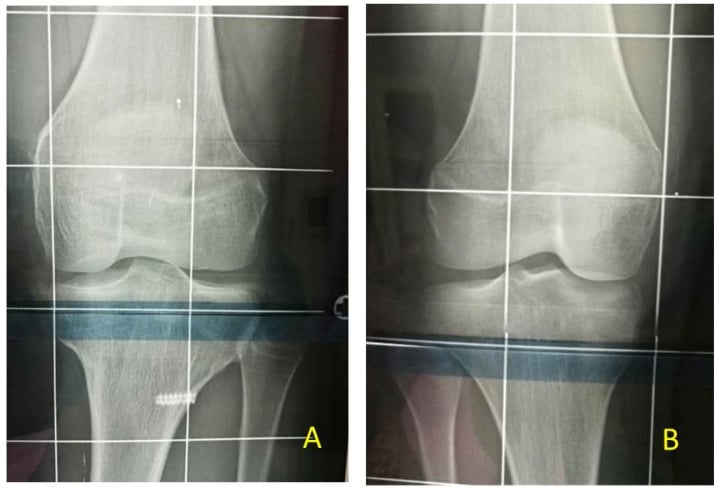
Measure, then predict. Management turns on the predicted discrepancy at skeletal maturity, not today's number. Follow the child with serial clinical assessment (block test, gait observation, pelvic tilt and any compensatory scoliosis) and radiographic measurement, using a standing scanogram or orthoroentgenogram, or low-dose biplanar imaging such as EOS where available. Project the mature discrepancy with a growth-remaining method: the Anderson-Green charts or the multiplier method.
Act on the prediction. The conventional thresholds are consensus-based rather than trial-derived (see the Evidence Attribution box):
- Conventional management
- Observe; shoe raise if symptomatic
- Notes
- Most BWS discrepancies are modest and fall here
- Conventional management
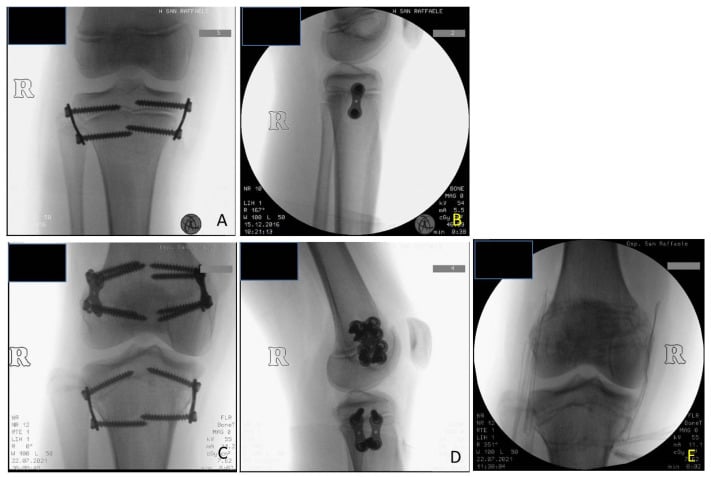
- Timed epiphysiodesis of the longer limb while growth remains
- Notes
- Percutaneous drill epiphysiodesis or guided-growth plating of the distal femoral / proximal tibial physes, timed to growth remaining
- Conventional management
- Limb lengthening (or reconstruction)
- Notes
- Circular frame or intramedullary lengthening nail; higher complication burden - uncommon in BWS
The number is not the whole decision. A symptomatic child with a smaller discrepancy is a different problem from an asymptomatic one with the same number.
Why the longer limb. The discrepancy comes from overgrowth of the longer limb, so epiphysiodesis of that limb is the logical first procedure when the prediction warrants it.
The spine. Screen for secondary postural scoliosis from pelvic tilt, and correct the discrepancy before attributing a curve to a structural cause.
Fitting the operation around surveillance. When the child needs a general anaesthetic, for an epiphysiodesis for example, plan it around the oncology surveillance calendar rather than adding separate attendances.
The rest of the team. The limb programme runs in parallel with the multidisciplinary care of the macroglossia (airway, feeding, speech), repair of the abdominal wall defect, follow-up of the hyperinsulinism and neonatal hypoglycaemia, and genetics and counselling. Above all, the team ensures the tumour surveillance is in place.
Complications & Prognosis
Neonatal hypoglycaemia. Hypoglycaemia from hyperinsulinism is the dangerous early complication. Unrecognised, it risks seizures and neurodevelopmental injury, which is why it is screened for and treated aggressively in the nursery.
Macroglossia. The large tongue causes airway obstruction, feeding difficulty, drooling and speech problems. Most children grow into the tongue, and reduction glossoplasty is reserved for significant functional problems.
The abdomen, kidneys and heart. Abdominal wall defects (omphalocele, umbilical hernia) require surgical repair. Nephromegaly and nephrogenic rests are the substrate the Wilms surveillance watches. Cardiac anomalies and rare cardiomyopathy are described, and most systemic features improve with age.
After epiphysiodesis. Over- or under-correction follows if the timing or growth prediction is off, and angular deformity if the arrest is asymmetric, hence serial measurement before acting.
After lengthening. Lengthening is rarely needed and carries the usual burden (pin-site infection, muscle contracture, joint stiffness and neurovascular stretch), weighed against the modest discrepancies typical of BWS.
Prognosis. Growth velocity is greatest in early childhood and typically normalises later in childhood, so final height is often above average but near-normal. Intellectual development is normal provided neonatal hypoglycaemia was controlled. The dominant determinant of outcome is the embryonal-tumour risk, which the surveillance programme exists to neutralise, because a Wilms tumour caught on surveillance is usually curable.
Mnemonics & Memory Aids
BWS
Hook:BWS: Big (overgrowth/macroglossia), Wilms tumour surveillance, Skeletal (limb-length discrepancy).
LUGC11p15.5 Molecular Subtypes
Hook:LUGC the subtypes: LOM-IC2 commonest, UPD and GOM-IC1 carry the Wilms risk, CDKN1C is the familial one.
SCREENTumour Surveillance
Hook:SCREEN every BWS child: Sonogram, AFP, Renal target, End at 7-8, Even isolated hemihypertrophy, Never trust blood alone.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A child is referred with hemihypertrophy and a limb-length discrepancy. Why must you think beyond the limb, and how do you manage it?”
What it is
- Imprinting/overgrowth disorder (11p15.5 - IGF2/H19, CDKN1C); ~1 in 10,000
- Macrosomia, macroglossia, abdominal wall defects (omphalocele)
- Neonatal hyperinsulinism/hypoglycaemia; visceromegaly
Orthopaedic relevance
- Lateralised overgrowth (hemihypertrophy) → limb-length discrepancy
- Monitor discrepancy / predicted difference at maturity
- Treat with timed epiphysiodesis of the longer limb (or lengthening)
Critical association
- Embryonal-tumour predisposition: Wilms tumour, hepatoblastoma
- Mandatory surveillance: abdominal ultrasound +/- serum alpha-fetoprotein
- Lateralised overgrowth is a tumour-risk marker (not just a limb issue)
Evidence & Key Studies
Beckwith-Wiedemann syndrome with Wilms tumour and lateralised overgrowth
- Beckwith-Wiedemann syndrome is a rare imprinting/overgrowth disorder (prevalence about 1 in 10,000 live births), characterised by a predilection for embryonal tumour growth, especially Wilms tumour, and manifestations such as lateralised overgrowth/hemihypertrophy, macroglossia, macrosomia, anterior abdominal wall defects and hyperinsulinism.
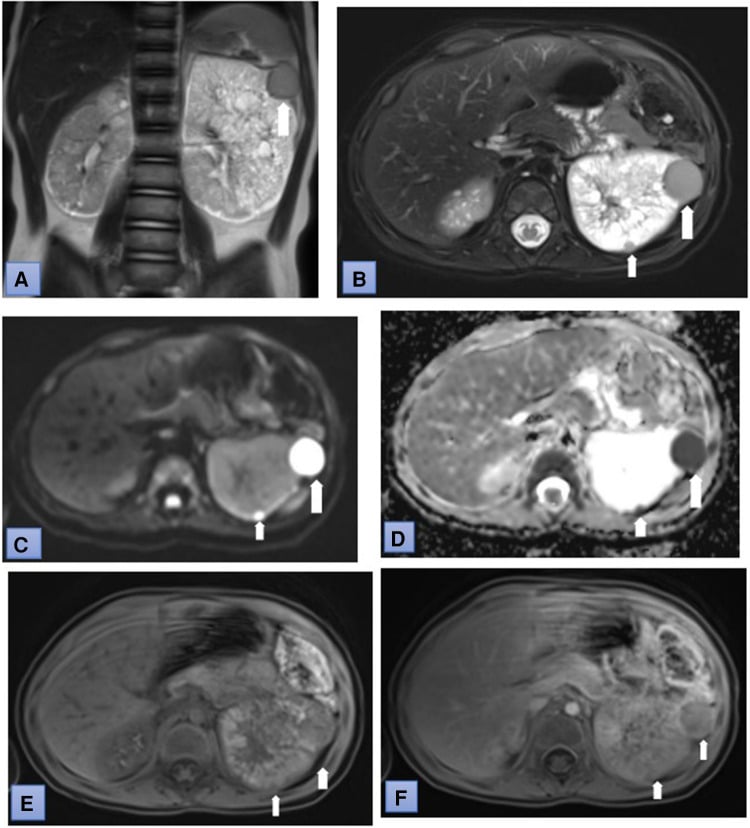
- The reported child presented with abdominal swelling and limb-length discrepancies, with a clinical diagnosis of BWS made on multifocal Wilms tumour, organomegaly and lateralised overgrowth.
- Clinical criteria can diagnose BWS where confirmatory molecular testing is unavailable, changing management of complications such as Wilms tumour.
BWS as a rare imprinting/overgrowth disorder (about 1 in 10,000) with a predilection for embryonal tumours (especially Wilms tumour), the manifestations of lateralised overgrowth/hemihypertrophy, macroglossia, macrosomia, abdominal wall defects and hyperinsulinism, the association of limb-length discrepancy, and the ability to diagnose on clinical criteria come from the cited Hailu report. The 11p15.5 imprinting genetics, the hepatoblastoma risk and alpha-fetoprotein surveillance, and the orthopaedic management of limb-length discrepancy (epiphysiodesis/lengthening) are standard, well-established teaching. The 8 to 10 percent tumour risk from classic BWS cohorts, and the finding that risk across the wider Beckwith-Wiedemann spectrum does not mirror it, come from Duffy and colleagues (Genes 2021, PMID 34828445). The epigenotype mosaicism between blood, tumour and normal liver, and the resulting recommendation for universal rather than genotype-restricted screening, come from the assembled hepatoblastoma series of Klein and colleagues (Cancers 2023, PMID 37174013) - 50 patients, of whom 16 were the authors' own and 34 collected from published case reports, so it is a pooled case series rather than a cohort. That paternal uniparental disomy and IC1 gain of methylation carry the highest Wilms risk is long-established (Weksberg, Am J Med Genet C 2005, PMID 16010676). The 95-percent-by-age-7 figure, the roughly 5 percent Wilms risk in isolated hemihyperplasia and the late case at age 9 are taken in substance from hemihypertrophy, and the limb-length thresholds from limb-length discrepancy and epiphysiodesis, where that topic notes the thresholds are consensus-based rather than supported by high-quality evidence. Lengthening technique is developed in limb lengthening principles. No trial comparing surveillance schedules in this syndrome was retrieved, so the three-monthly interval and the age cut-off are consensus practice rather than trial-derived.