Lateral Column Degenerative Disease | Triple Joint Complex | Often Overlooked
- CC joint is critical for lateral column stability and load transfer
- Rarely occurs in isolation - assess talonavicular and subtalar joints
- Triple arthrodesis indicated when multiple hindfoot joints involved
- Peroneal tendon pathology commonly coexists
- Lateral approach risks sural nerve and peroneal tendons
- “CC joint contributes to lateral column length and forefoot abduction
- “Nutcracker fracture of cuboid predisposes to CC arthritis
- “Isolated CC fusion rare - usually part of triple arthrodesis
- “Sural nerve at risk with lateral approach
Overview and Epidemiology
Calcaneocuboid (CC) arthritis is degeneration of the articulation between the anterior process of the calcaneus and the cuboid. It is a relatively uncommon cause of lateral midfoot pain, about 10-15% of midfoot arthritis, and isolated disease is rare at 5-10%. The joint is critical for lateral column stability and forefoot alignment.
It rarely travels alone. It is commonly associated with adjacent-joint disease, post-traumatic change or an inflammatory arthropathy. Before planning anything, assess the talonavicular and subtalar joints; missing concurrent disease there is the commonest viva trap.
- Peroneal tendon pathology (tears or tendinopathy) coexists in 30-40%
- Talonavicular arthritis - 60% have concurrent CC involvement
- Subtalar arthritis - a 50% association
- Cavovarus foot - chronic lateral column overload
Causes. Post-traumatic disease, after a calcaneal fracture, is the most common.
- Post-traumatic - calcaneal fractures (30-40% develop CC arthritis) and nutcracker injuries of the cuboid
- Inflammatory - rheumatoid arthritis and the seronegative arthropathies
- Degenerative - primary osteoarthritis, uncommon in isolation
- Malalignment - hindfoot varus or valgus loading the joint abnormally
- Peroneal pathology - chronic tendon dysfunction altering the mechanics
How far to trust the numbers. No population study reports the prevalence of CC arthritis, and the rates quoted for how often it follows a given injury come from surgical series of that injury.
Anatomy and Pathophysiology
The joint. A saddle-shaped, concave-convex articulation between the anterior facet of the calcaneus and the cuboid, forming the lateral component of the transverse tarsal (Chopart) joint. Its motion is coupled with the talonavicular and subtalar joints as part of the triple joint complex, contributing to its oblique axis of motion, and on its own it allows only about 5-10° in the sagittal and transverse planes.
What it does. It transmits power from hindfoot to forefoot, allows limited motion for adapting to terrain, and carries about 15-20% of forefoot load in stance, transmitting body weight laterally under high compressive load. It locks to stabilise the lateral column at toe-off, controls forefoot abduction and adduction, and maintains lateral column length. The dorsal calcaneocuboid and bifurcate ligaments stabilise the lateral side of the Chopart joint.
The cyma line. The normal Chopart joint forms a smooth S-shaped line across the talonavicular and calcaneocuboid articulations. A break in the contour suggests malalignment that alters lateral column loading.
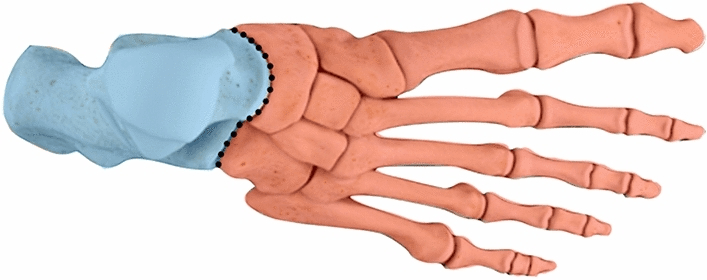
- CC Joint
- Minimal (5-10°)
- TN Joint
- Significant (50-60% hindfoot motion)
- Subtalar Joint
- Significant (50-70% hindfoot motion)
- CC Joint
- 15-20% lateral
- TN Joint
- Major medial column
- Subtalar Joint
- Full body weight
- CC Joint
- Rare (5-10%)
- TN Joint
- Common (40% midfoot OA)
- Subtalar Joint
- Common
- CC Joint
- 75-85%
- TN Joint
- 85-95%
- Subtalar Joint
- 90-95%
When it degenerates. The articular cartilage is progressively lost, the subchondral bone stiffens and scleroses, peripheral osteophytes form and the capsule becomes inflamed. The joint loses height, and the lateral column shortens with it. Loss of lateral column length leads to abnormal load transfer, compensatory forefoot adduction and cavovarus deformity.
After trauma. Following a calcaneal fracture, CC arthritis develops through three routes:
- Direct articular damage from the injury
- Malunion, which loads the joint abnormally
- Lateral column shortening, which alters the biomechanics
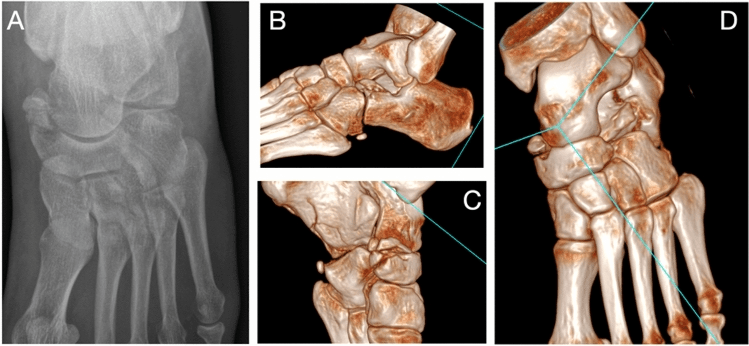
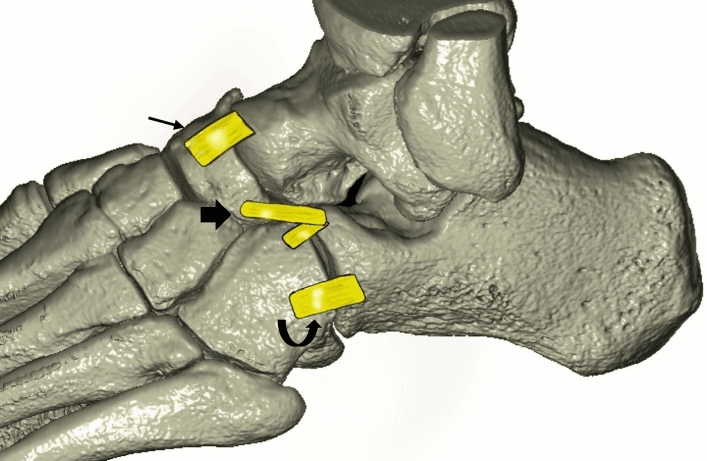
Nutcracker and lateral compression injuries. In the nutcracker mechanism, forced abduction compresses the cuboid between the calcaneus and the bases of the 4th and 5th metatarsals. In a lateral-compression Chopart injury, the anterior calcaneal process is driven into the cuboid while medial distraction avulses the spring-ligament complex, and residual incongruity at the CC surface predisposes to focal post-traumatic arthritis.
Clinical Assessment
History. Pain sits in the lateral midfoot, inferior to the lateral malleolus: a dull ache, worse with activity, walking on uneven ground and lateral stress. Patients struggle with narrow shoes and walk less far. Ask specifically about a previous calcaneal fracture or midfoot injury.
Examination. Localise tenderness and stress pain precisely, against the CC joint, the dorsal calcaneocuboid and bifurcate ligaments and the peroneal tendons, rather than labelling it generically as lateral midfoot pain.
- Inspection, standing - lateral column alignment, swelling, skin changes and overall foot posture; gait for a lateral foot stress pattern
- Palpation - localise tenderness to the CC joint (anterior to the lateral malleolus) and compare it with the TN and subtalar joints
- Range of motion - forefoot abduction and adduction with the hindfoot stabilised, reduced in CC arthritis; compare with the other side
- Special tests - single heel rise for associated tibialis posterior dysfunction, peroneal strength, and the Coleman block test if cavovarus is suspected
- Adjacent joints - the TN, subtalar and ankle joints, systematically, for concurrent disease
Test peroneal strength, palpate along the tendon course for tenderness or thickening, and assess for subluxation. MRI is indicated if clinical suspicion is high.
Differential Diagnosis of Lateral Midfoot Pain
- Key distinguishing feature
- Tenderness directly over CC joint; pain on forefoot abduction/adduction; lateral column degeneration
- Best test
- Weight-bearing radiographs; diagnostic CC injection
- Key distinguishing feature
- Tenderness along tendon course behind/below lateral malleolus; pain on resisted eversion
- Best test
- MRI; dynamic ultrasound
- Key distinguishing feature
- Acute or overuse onset; point tenderness over cuboid; history of forced abduction
- Best test
- MRI / CT; bone scan
- Key distinguishing feature
- Pain in sinus tarsi; reduced inversion/eversion; pain on hindfoot rotation
- Best test
- CT; subtalar injection
- Key distinguishing feature
- Lateral hindfoot pain and instability sensation, often post-sprain
- Best test
- MRI; diagnostic injection
- Key distinguishing feature
- Discrete tender ossicle in peroneus longus, plantar-lateral cuboid
- Best test
- Oblique radiograph; MRI
- Key distinguishing feature
- Rigid flatfoot, restricted subtalar motion, younger patient
- Best test
- Oblique radiograph; CT/MRI
- Key distinguishing feature
- Tenderness more distal at styloid; avulsion or Jones fracture history
- Best test
- AP/oblique radiographs
Investigations
Weight-bearing radiographs first. Standing AP, lateral and oblique views of the foot. Judge the CC joint, the alignment (lateral column length and forefoot position) and the TN and subtalar joints on the same films. The features of CC arthritis are:
- Joint space narrowing
- Subchondral sclerosis and cysts
- Osteophytes, especially dorsal; on the lateral view, look for dorsal osteophytes impinging on the extensor tendons
- Lateral column shortening, judged against the contralateral foot
CT is for surgical planning and deformity: bone stock, subchondral change and the fusion plan, and it identifies occult fractures and coalition. After a calcaneal fracture, multiplanar CT is required to decide whether the fracture actually enters the CC joint or loads it incongruently.
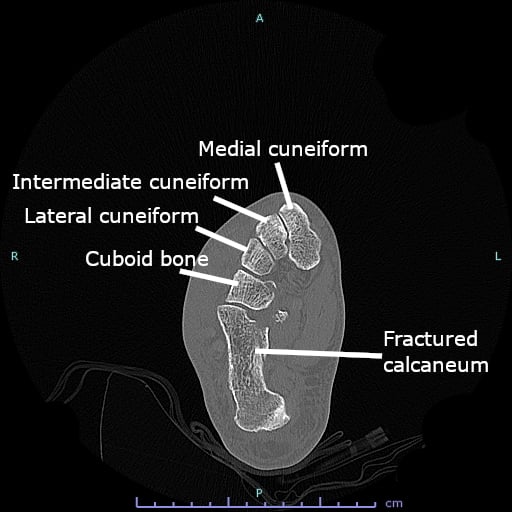
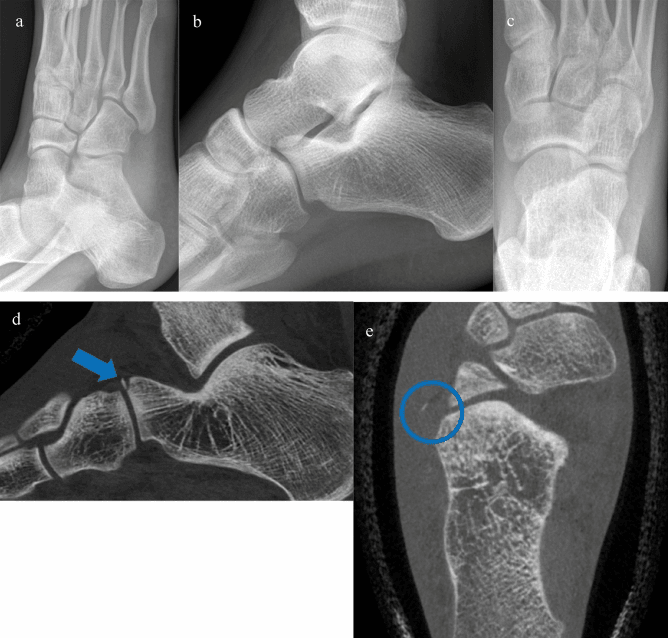
The occult Chopart injury. In the case below, standard views were initially negative despite persistent pain, and cone-beam CT revealed an anterior calcaneal-process fracture and a separate dorsal CC fracture. It shows why cross-sectional imaging matters after an occult Chopart injury.
MRI is selective. It assesses the peroneal tendons, cartilage and soft tissues, showing tendon tears, bone marrow oedema and synovitis, and it earns its place in pre-operative planning when tendon pathology is suspected.
Diagnostic Calcaneocuboid Injection: Confirming the Pain Generator
Why inject. CC arthritis rarely occurs in isolation and lateral midfoot pain has many mimics (peroneal tendinopathy, sinus tarsi syndrome, subtalar arthritis, cuboid or nutcracker pathology, an os peroneum), so radiographic CC degeneration does not by itself prove the CC joint is the source of the pain. An image-guided intra-articular injection of local anaesthetic, with or without corticosteroid, is the single most useful confirmatory test before committing to an irreversible fusion.
How to do it.
- Guidance is essential - fluoroscopy or ultrasound; the saddle joint is small, and blind injection frequently misses or spills into adjacent structures
- Small volume - about 1 mL of local anaesthetic keeps the response joint-specific
- Document the response - a pain diary with a defined task (walking, single-leg stance) recorded during the anaesthetic window
- Positive test - substantial, temporary relief during the anaesthetic window localises the pain generator to the CC joint
Reading the result. Good relief supports the CC joint as the target and, with normal adjacent joints, an isolated CC fusion; it can inform the extent of the fusion. Absent, partial or equivocal relief should stop you proceeding straight to a CC fusion and prompt reassessment of the adjacent joints (a separate subtalar or TN injection), the peroneal sheath, injectate placement and mixed pain sources, though it is not an absolute veto. A separate response pattern may redirect surgery to a double or triple arthrodesis or to tendon surgery. Including corticosteroid adds therapeutic value in the conservative phase.
Its limits. Anaesthetic can diffuse into the adjacent subtalar joint or peroneal sheath, which reduces specificity. A good response supports localisation to the CC region, but it does not guarantee that fusion will relieve the symptoms or unite.
Management
Conservative first. Non-operative care succeeds in about 60-70% of patients with mild to moderate CC arthritis. The aim is to minimise abnormal loading of the degenerate joint.
- Initially - activity modification to reduce lateral column stress; supportive footwear with lateral posting
- Weeks 0-6 - orthoses to redistribute load and support the lateral column: custom orthoses with lateral forefoot support, or off-the-shelf lateral wedge insoles
- Ongoing - NSAIDs; corticosteroid injection under fluoroscopic or ultrasound guidance, which improves accuracy, to a maximum of 2-3 a year
- Weeks 6-12 - physiotherapy: peroneal strengthening, ankle stabilisation exercises and gait retraining, addressing any associated peroneal weakness or dysfunction
When to operate. Failed conservative management for a minimum of 6 months, moderate to severe arthritis and functional limitation. The choice between isolated CC fusion and triple arthrodesis depends primarily on the status of the adjacent joints, assessed clinically and radiographically.
- Indications
- Isolated CC arthritis, adjacent joints normal
- Fusion Rate
- 75-85%
- Considerations
- Higher nonunion than TN, lateral approach risks
- Indications
- CC + TN or subtalar involvement
- Fusion Rate
- 90-95%
- Considerations
- Loss of all hindfoot motion, more predictable
- Indications
- Young, early arthritis, preserved joint space
- Fusion Rate
- N/A
- Considerations
- Limited evidence, experimental
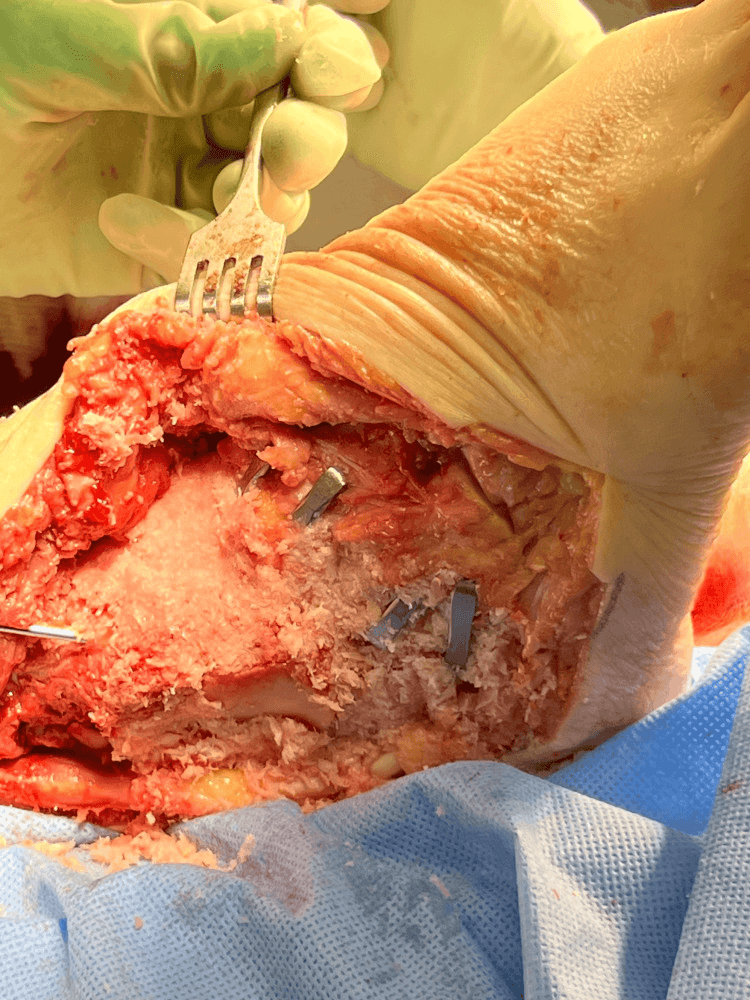
Isolated, double or triple. Triple arthrodesis is the more common operation. When disease or deformity extends beyond the CC joint, the subtalar, talonavicular and calcaneocuboid surfaces are prepared to bleeding bone, grafted and compressed together. Where the CC and TN joints are both involved and the subtalar joint is spared, a double (CC and TN) arthrodesis is the subtalar-sparing alternative (Clain and Baxter, in the evidence below).
Surgical Technique: Isolated CC Arthrodesis
Approach. The CC joint is reached laterally.
- Set-up - supine with a bump under the ipsilateral hip, thigh tourniquet and C-arm; ensure adequate access to the lateral foot with the hip externally rotated
- Incision - oblique, over the CC joint anterior to the lateral malleolus, 6-8 cm long, following Langer's lines to minimise scar contracture
- Superficial dissection - secure the sural nerve, then elevate the peroneal tendons carefully
- Deep dissection - incise the capsule and expose the articular surfaces; inspect the peroneal tendons systematically for tendinopathy and for tears requiring repair
The sural nerve runs along the lateral border of the foot, typically 1-2 cm posterior to the incision but with a variable course. Identify it early and protect it throughout.
Joint preparation. Given the higher nonunion rate of isolated CC fusion, adequate preparation is critical.
- Cartilage - remove it completely with osteotomes and burr, preserving subchondral bone; fish-scaling exposes bleeding bone without excessive bone loss
- Surfaces - create bleeding bone on both calcaneus and cuboid, with multiple drill holes to enhance vascularity, maintaining lateral column length
- Graft - consider autograft or allograft, harvested from the calcaneus or iliac crest; graft is particularly important in revision cases or with risk factors
- Alignment - position the cuboid to maintain lateral column length, avoiding shortening or excessive abduction; confirm with provisional K-wires before definitive fixation
Fixation. Fluoroscopic confirmation of screw position and joint compression is mandatory.
- Configuration
- Parallel 4.0mm cannulated screws
- Notes
- Standard technique
- Configuration
- Lateral plate across joint
- Notes
- Better for revision, osteoporotic bone
- Configuration
- Plate plus screws
- Notes
- Maximum stability for high-risk cases
Aftercare. Radiographic union typically occurs by 10-12 weeks, but may take longer in patients with risk factors.
- Weeks 0-2 - below-knee cast, strict non-weight-bearing; elevation, ice and DVT prophylaxis; wound check and suture removal at 2 weeks
- Weeks 2-8 - non-weight-bearing in the cast, with radiographs at 6 weeks to assess fusion; watch for wound problems, infection and hardware problems
- Weeks 8-10 - transition to weight-bearing in a CAM boot if radiographic union is progressing, increasing as tolerated
- Weeks 10-12 - wean from the boot to supportive footwear and begin physiotherapy for range and strength; expect full weight-bearing by 12 weeks if union is confirmed
Complications
- Incidence
- 15-25% (higher than TN)
- Management
- Revision with bone graft and plate
- Incidence
- 5-10%
- Management
- Usually resolves; neurolysis if persistent
- Incidence
- 25-35% at 10 years
- Management
- Activity modification, possible future fusion
- Incidence
- 10-15%
- Management
- Hardware removal after union
- Incidence
- 5-8%
- Management
- Wound care, antibiotics, possible debridement
Who fails to unite. Smoking is the strongest predictor of CC fusion nonunion. The others are diabetes mellitus, inadequate fixation, poor bone contact, peripheral vascular disease, immunosuppression and revision surgery. Pre-operative smoking cessation for a minimum of 4 weeks is recommended.
Managing the Calcaneocuboid Fusion Nonunion
Why this joint. Isolated CC arthrodesis carries the highest nonunion rate of the individual hindfoot and midfoot fusions (see the complications table), against 10-15% for talonavicular fusion. The reasons are specific to the joint: a small cancellous contact surface, high compressive and rotational loads across the lateral column, and a frequently scarred or relatively avascular post-traumatic bed. Salvage is a predictable examiner question.
Diagnosis. Not every nonunion is symptomatic, and a stable fibrous nonunion in a comfortable patient can be observed. Persistent lateral pain, hardware loosening or lucency and progressive lateral column collapse suggest a symptomatic one. CT is the reference test, because plain films over-call union across the small saddle joint. Exclude low-grade infection, and correct host factors, before revising.
Salvage.
- Correct the cause - confirmed smoking cessation, optimised vitamin D and metabolic status, treatment of any infection
- Prepare a fresh bed - take the fibrous interface down to bleeding bone
- Restore lateral column length - structural autograft or allograft, or a distraction bone-block if shortened
- Upgrade fixation - from screws alone to a rigid compression plate, with or without a lag screw, adding biologic or autologous graft
Where the CC joint is heavily scarred and the adjacent joints are themselves degenerating, extending to a double or triple arthrodesis gives a larger, more reliable fusion surface; the technique is covered in the dedicated arthrodesis topics. Structural graft that restores lateral column length follows the distraction-arthrodesis principle and prevents the forefoot adduction that follows lateral column shortening.
Guidelines, Registries & Global Practice
Global epidemiology. Symptomatic radiographic midfoot OA affects roughly 12% of community-dwelling adults over 50 (Keele Clinical Assessment Study of the Foot), rising with age, female sex, obesity and prior foot/ankle injury - but that definition scored the cuneometatarsal, naviculocuneiform and talonavicular joints and did not include the calcaneocuboid, so it is the risk profile that transfers, not the number. No population study reports the prevalence of CC arthritis, and the figures on this page for how often it follows a given injury come from surgical series of that injury, which are ascertained from the cases that reached an operating theatre. Isolated CC arthritis is uncommon; most CC degeneration is post-traumatic (after calcaneal or cuboid/nutcracker fractures) or part of broader midfoot/hindfoot OA. There is no dedicated arthroplasty registry for the CC joint because management is fusion-based, not implant-based.
Side-by-side guidance. No society publishes a CC-arthritis-specific guideline; recommendations are extrapolated from foot OA and hindfoot fusion principles.
- Region
- US
- Relevant position
- Trial of orthoses, NSAIDs and activity modification before fusion; selective single/double fusion preferred over triple when feasible to preserve motion
- Region
- UK
- Relevant position
- Generic OA guidance (exercise, weight loss, analgesia) first; calcaneal-fracture BOAST stresses anatomic articular reduction to limit later subtalar/CC arthritis
- Region
- Global
- Relevant position
- Restore lateral column length and articular congruity in cuboid/calcaneal fractures; rigid compression fixation for CC fusion with bone graft if risk factors
- Region
- Europe
- Relevant position
- Subtalar-sparing (isolated/double) fusion where adjacent joints preserved; emphasises peri-operative smoking cessation to reduce nonunion
Registry and outcome evidence. Calcaneal fracture registries and the Buckley RCT show that articular malreduction (step-off over 2 mm) drives post-traumatic subtalar and CC arthritis — the dominant route to symptomatic CC disease worldwide.
High- versus limited-resource practice. In well-resourced systems, weight-bearing CT, MRI for peroneal assessment and rigid plate/screw constructs with biologics are standard. In limited-resource settings, plain weight-bearing radiographs and screw-only fixation predominate, late presentation of malunited calcaneal fractures is more common, and accommodative orthoses with footwear modification carry a larger share of definitive care. Smoking cessation for a minimum of 4 weeks before fusion is a universal, low-cost intervention that reduces nonunion.
Controversies & Areas of Uncertainty
Isolated CC fusion or a longer fusion. Whether truly isolated CC arthritis exists often enough to justify isolated fusion is debated. Given its nonunion rate, some surgeons favour double or triple arthrodesis for more predictable union; the counter-argument is preservation of TN and subtalar motion. The evidence is limited to small retrospective series.
Motion preservation. Interposition arthroplasty and joint-preserving distraction for early CC arthritis rest on sparse, low-quality data, with no validated implant or established role. Fusion remains the reference standard for end-stage disease.
How much motion does the CC joint really lose? Beimers' CT helical-axis study (2012) suggests fusing the CC joint may reduce global hindfoot motion less than once feared, since the CC contributes a small share, which challenges the historical reluctance to fuse it within lateral column lengthening. It had five patients in each arm and measured the ankle and subtalar joints rather than the transverse tarsal joint, so it is an absence of evidence of a motion penalty, not evidence that there is none.
Biologics and fixation. The best fixation (parallel screws, plate or combined) and whether routine autograft, allograft or orthobiologics meaningfully lower nonunion are unresolved. Recommendations are extrapolated from general hindfoot fusion data rather than CC-specific trials.
MCQ Practice Points
Q: What percentage of midfoot arthritis cases involve the calcaneocuboid joint? A: 10-15% - CC arthritis is less common than talonavicular arthritis (40% of midfoot arthritis). CC typically occurs as part of triple complex pathology.
Q: What is the most common cause of calcaneocuboid arthritis? A: Post-traumatic - Calcaneal fractures lead to CC arthritis in 30-40% of cases. Nutcracker mechanism cuboid injuries also predispose.
Q: What is the nonunion rate for isolated calcaneocuboid arthrodesis? A: 15-25% - Higher than talonavicular fusion (10-15%). Risk factors include smoking, diabetes, inadequate fixation, and poor bone contact.
Q: What nerve is at risk during lateral approach to the calcaneocuboid joint? A: Sural nerve - Runs along lateral foot border. Injury incidence 5-10%. Must be identified and protected throughout surgery.
Q: What percentage of CC arthritis cases have concurrent peroneal tendon pathology? A: 30-40% - Peroneal tendons should be inspected during lateral approach and any tears addressed with repair or tenosynovectomy.
Q: What happens to the forefoot if lateral column length is not maintained during CC fusion? A: Forefoot adduction - Loss of lateral column length causes relative forefoot adduction and can lead to medial overload and cavovarus deformity.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 58-year-old presents with lateral midfoot pain 3 years after calcaneal fracture treated non-operatively. Examination shows lateral column tenderness. Weight-bearing X-rays show CC joint narrowing with sclerosis. How would you manage?”
“Walk me through your surgical technique for isolated calcaneocuboid arthrodesis.”
“A 62-year-old presents with progressive lateral and medial midfoot pain. X-rays show CC arthritis with concurrent TN arthritis. Subtalar joint appears preserved. What is your management approach?”
Key Anatomy
- CC joint = lateral column stabilizer
- Part of triple joint complex with TN and subtalar
- Maintains lateral column length and forefoot alignment
- Sural nerve runs lateral - at risk with lateral approach
Classification
- Mild = joint space narrowing, minimal osteophytes
- Moderate = significant narrowing, sclerosis
- Severe = bone-on-bone, deformity
- Rarely isolated - usually part of triple complex
Treatment Algorithm
- Conservative: 6 months with orthoses, NSAIDs, lateral posting
- Isolated CC = isolated CC fusion (if adjacent joints normal)
- CC + TN or subtalar = triple arthrodesis
- Post-traumatic from calcaneal fracture most common
Surgical Pearls
- Lateral approach with sural nerve protection
- Two 4.0mm parallel screws standard fixation
- Consider bone graft (higher nonunion risk than TN)
- Non-weight-bearing 8 weeks minimum
- Assess peroneal tendons during approach
Complications
- Nonunion: 15-25% (higher than TN)
- Sural nerve injury: 5-10%
- Adjacent joint arthritis: 25-35% at 10 years
- Peroneal tendon pathology: 30-40% coexistence
Evidence Base
Epidemiology of Symptomatic Midfoot Osteoarthritis
- Symptomatic radiographic midfoot OA present in 12.0% of community adults aged over 50 years
- Higher in women, those over 75, obesity, prior foot/ankle injury and pain in other weight-loaded joints
- Scored joints were 1st/2nd cuneometatarsal, naviculocuneiform and talonavicular - the CC joint was NOT scored
- Findings interpreted as consistent with mechanical (load-transmission) pathogenesis
Triple Arthrodesis: Long-Term (25 and 44 Year) Follow-Up
- 67 feet in 57 patients reviewed at average 25 and then 44 years after triple arthrodesis
- Pseudarthrosis in 13 feet; residual but non-progressive deformity in 78%
- By second follow-up all ankles showed degenerative change, with naviculocuneiform and TMT progression
- Despite progressive adjacent-joint arthritis, 95% of patients remained satisfied
Simultaneous Calcaneocuboid and Talonavicular (Double) Fusion
- 16 feet followed mean 83 months after combined CC and TN fusion
- Objectively 4 excellent, 8 good, 4 fair and none poor - so 12 of 16 excellent or good; only one asymptomatic TN nonunion
- Progressive ankle OA in 6 and naviculocuneiform OA in 7 patients
- Biomechanically superior to isolated TN fusion and a simpler alternative to triple arthrodesis
Displaced Fractures of the Cuboid (Nutcracker Injury)
- Four displaced cuboid fractures treated by open reduction, bone grafting and internal fixation
- ORIF advocated where one or more articular surfaces are appreciably displaced
- Preliminary results better than historical conservative treatment or late midtarsal fusion
- Restoration of cuboid length protects lateral column and the CC joint
Operative vs Nonoperative Treatment of Calcaneal Fractures (RCT)
- 424 patients with 471 displaced intra-articular calcaneal fractures randomized; 309 followed at least 2 years
- No overall difference in SF-36 or VAS between operative and nonoperative care
- After excluding Workers' Compensation cases, selected subgroups did better with ORIF (younger, anatomic reduction, lower workload)
- Anatomic reduction (step-off 2 mm or less) predicted better outcome
Calcaneal Malunion and Nonunion (Review)
- Calcaneal malunion produces heel widening, subfibular impingement, hindfoot varus/valgus and peroneal tendon dysfunction
- Subtalar arthrosis is a well-established consequence; CC immobilisation contributes to the low true nonunion rate
- Reconstruction is a salvage procedure with persistently lower SF-36 and AOFAS hindfoot scores
- Lateral wall decompression suffices only with minimal arthrosis and no deformity
Calcaneocuboid Distraction Arthrodesis vs Osteotomy: Hindfoot Motion
- CT helical-axis motion compared after CC distraction arthrodesis (CCDA) versus anterior calcaneal distraction osteotomy (ACDO)
- Ankle motion 49.0 deg (CCDA) versus 52.2 deg (ACDO); subtalar 24.4 deg versus 22.8 deg
- Differences were small with wide variance between the two lateral column lengthening techniques
- Concern that CCDA reduces hindfoot motion was not borne out in this cohort
Calcaneal Fracture-Dislocation and the Calcaneocuboid Joint
- 10 acute calcaneal fracture-dislocations; the calcaneocuboid joint was involved in 9 of 10
- Often overlooked at presentation; a dislocation approach over fibula to sinus tarsi to CC joint gives access
- After anatomic ORIF, Foot Function Index averaged 12.8 and EQ-5D 0.89 at mean 3 years
- No secondary subtalar fusions were required when recognised and fixed early
References
-
Thomas MJ, Peat G, Rathod T, et al. The epidemiology of symptomatic midfoot osteoarthritis in community-dwelling older adults. Arthritis Res Ther. 2015;17(1):178. PMID 26166410. doi:10.1186/s13075-015-0693-3
-
Saltzman CL, Fehrle MJ, Cooper RR, et al. Triple arthrodesis: twenty-five and forty-four-year average follow-up of the same patients. J Bone Joint Surg Am. 1999;81(10):1391-402. PMID 10535589.
-
Clain MR, Baxter DE. Simultaneous calcaneocuboid and talonavicular fusion: long-term follow-up study. J Bone Joint Surg Br. 1994;76(1):133-6. PMID 8300657.
-
Sangeorzan BJ, Swiontkowski MF. Displaced fractures of the cuboid. J Bone Joint Surg Br. 1990;72(3):376-8. PMID 2341430. doi:10.1302/0301-620X.72B3.2341430
4a. Buckley R, Tough S, McCormack R, et al. Operative compared with nonoperative treatment of displaced intra-articular calcaneal fractures: a prospective, randomized, controlled multicenter trial. J Bone Joint Surg Am. 2002;84(10):1733-44. PMID 12377902. doi:10.2106/00004623-200210000-00001
4b. Reddy V, Fukuda T, Ptaszek AJ. Calcaneus malunion and nonunion. Foot Ankle Clin. 2007;12(1):125-35. PMID 17350514. doi:10.1016/j.fcl.2006.12.004
4c. Beimers L, Louwerens JWK, Tuijthof GJM, et al. CT measurement of range of motion of ankle and subtalar joints following two lateral column lengthening procedures. Foot Ankle Int. 2012;33(5):386-93. PMID 22735280. doi:10.3113/FAI.2012.0386
4d. Rammelt S, Marx C, Swords G, Swords M. Recognition, treatment, and outcome of calcaneal fracture-dislocation. Foot Ankle Int. 2021;42(6):706-13. PMID 33478259. doi:10.1177/1071100720980012
-
Myerson MS. Adult acquired flatfoot deformity: treatment of dysfunction of the posterior tibial tendon. Instr Course Lect. 1997;46:393-405.
-
Johnson JE, Johnson KA. Dowel arthrodesis for degenerative arthritis of the tarsometatarsal (Lisfranc) joints. Foot Ankle. 1986;6(5):243-53.
-
Mann RA, Beaman DN, Horton GA. Isolated subtalar arthrodesis. Foot Ankle Int. 1998;19(8):511-9.
-
Clain MR, Baxter DE. Simultaneous calcaneocuboid and talonavicular fusion: long-term follow-up study. J Bone Joint Surg Br. 1994;76(1):133-6.
-
O'Malley MJ, Deland JT, Lee KT. Selective hindfoot arthrodesis for the treatment of adult acquired flatfoot deformity: an in vitro study. Foot Ankle Int. 1995;16(7):411-7.
-
DiGiovanni CW, Patel A, Calfee R, et al. Osteonecrosis in the foot. J Am Acad Orthop Surg. 2007;15(4):208-17.
-
Beischer AD, Brodsky JW, Pollo FE, et al. Functional outcome and gait analysis after triple or double arthrodesis. Foot Ankle Int. 1999;20(9):545-53.
-
Thordarson DB. Fusion in posttraumatic foot and ankle reconstruction. J Am Acad Orthop Surg. 2004;12(5):322-33.