Median Nerve Entrapment | Most Common Compression Neuropathy | 9 Tendons + 1 Nerve
- Carpal tunnel contents: 9 flexor tendons (4 FDS + 4 FDP + FPL) + median nerve (most superficial)
- Thenar atrophy = SEVERE: APB wasting indicates axonal loss, requires urgent surgery, incomplete recovery
- Palmar cutaneous branch spared: Branches proximal to tunnel, preserves palmar sensation
- Phalen's test: Wrist flexion 60 seconds reproduces symptoms (68% sensitive, 73% specific)
- NCS criteria: Motor latency greater than 4.5ms, sensory latency greater than 3.5ms across wrist
- “Flick sign is NOT diagnostic: the famous 93% is a POSITIVE PREDICTIVE VALUE from 1984 (PMID 6470728); replication gives 37% sensitivity (PMID 15100625)
- “Durkan's compression test is the most specific provocative test (pooled 83%) but not the most sensitive (64%, against 68% for Phalen's)
- “Open vs endoscopic CTR = similar outcomes, faster recovery with endoscopic
- “Pillar pain (10-20%) = most common post-op complication, resolves by 3 months
Overview and Epidemiology
Carpal tunnel syndrome (CTS) is compression of the median nerve beneath the transverse carpal ligament at the wrist, and it is the most common peripheral nerve compression neuropathy. It affects 3-6% of the general population and accounts for approximately 90% of all entrapment neuropathies.
Who presents. Women outnumber men 3:1, attributed to hormonal factors and a smaller carpal tunnel, and incidence peaks at 40-60 years. Both hands are involved in 50-60% of cases, and the dominant hand is typically the more symptomatic. Repetitive wrist flexion and vibration exposure at work raise the risk.
What crowds the tunnel. Greater than 50% of cases are idiopathic, with no identifiable cause; these are the associations to ask about.
- Diabetes mellitus, the commonest systemic association - 10% prevalence in diabetics against 3% in the general population
- Pregnancy - 2-7% incidence, usually resolving post-partum
- Other oedematous states - congestive cardiac failure, renal failure
- Hypothyroidism - myxoedema deposition in the tunnel; amyloid and acromegaly belong on the same list
- Rheumatoid arthritis - synovial proliferation; also osteoarthritis
- Obesity - BMI greater than 30 increases the risk two-fold
- Masses in the tunnel - ganglion, lipoma, anomalous muscles
- Previous wrist fracture - distal radius fractures, especially malunion
Anatomy
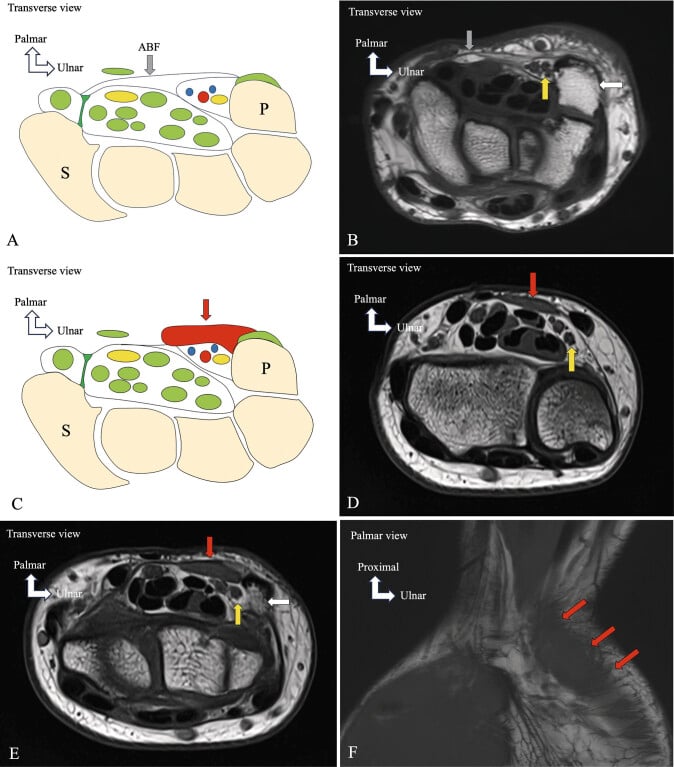
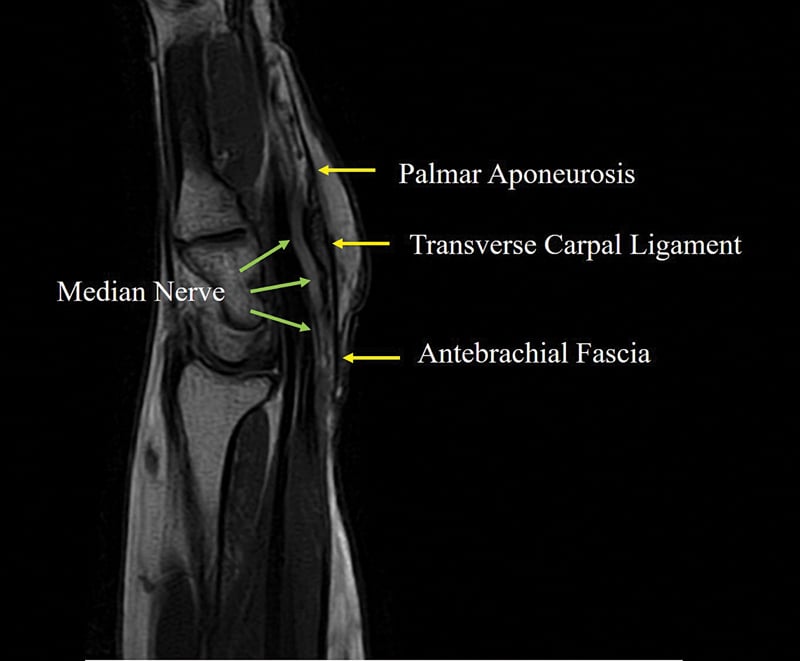
The canal. A fibro-osseous tunnel at the wrist: the floor is the concave arch of the carpal bones, and the roof is the transverse carpal ligament (flexor retinaculum), running from the scaphoid tubercle and trapezium radially to the pisiform and hook of hamate ulnarly. The ligament is approximately 2.5-3cm long and 2-3mm thick, and it thickens with age and loading.
- Proximal row: scaphoid (radial), lunate, triquetrum, pisiform (ulnar)
- Distal row: trapezium (radial), trapezoid, capitate, hamate (ulnar)
Ten structures pass through it. Nine flexor tendons and one nerve, in layers: the four flexor digitorum superficialis (FDS) tendons to the index, middle, ring and little fingers superficially, the four flexor digitorum profundus (FDP) tendons deep to them, the flexor pollicis longus (FPL) tendon radial to the FDP tendons, and the median nerve.
The median nerve lies most superficial in the tunnel, directly beneath the transverse carpal ligament, and on the radial side of the contents, between the FPL tendon radially and the FDS tendon to the index finger.
The course of the nerve. It enters the forearm between the two heads of pronator teres, runs deep to FDS, and gives off the anterior interosseous nerve (pure motor) in the proximal forearm. It then passes into the carpal tunnel deep to the transverse carpal ligament, and beyond the tunnel gives off the recurrent motor branch to the thenar muscles before dividing into the digital sensory branches.
The palmar cutaneous branch. It arises 5-6cm proximal to the wrist crease and passes superficial to the transverse carpal ligament to supply sensation over the thenar eminence and central palm. Because it never enters the tunnel, palmar sensation is spared in true CTS, and that is how the level of the lesion is established.
The recurrent motor branch. Its relationship to the ligament is the variation that matters on the operating table.
- Extraligamentous - 50%. Exits distal to the ligament; the safest arrangement.
- Subligamentous - 30%. Travels under the ligament, then exits.
- Transligamentous - 20%. Pierces the ligament, and is the variant at risk during release.
LOAFMedian Nerve Motor Supply (LOAF)
Hook:LOAF muscles = what you can't do when median nerve fails - can't hold a loaf of bread!
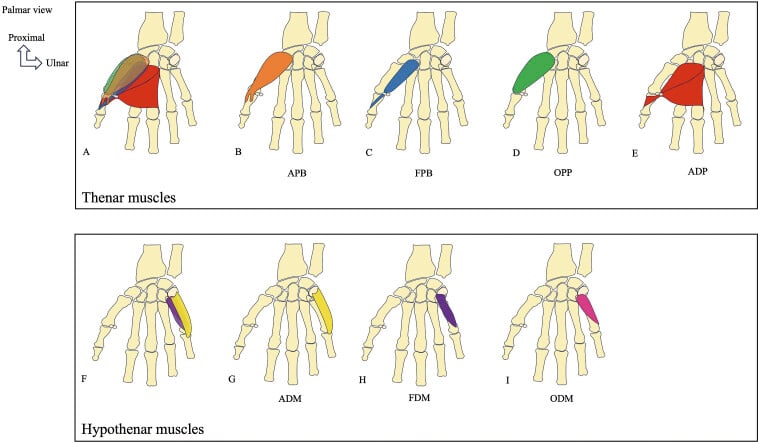
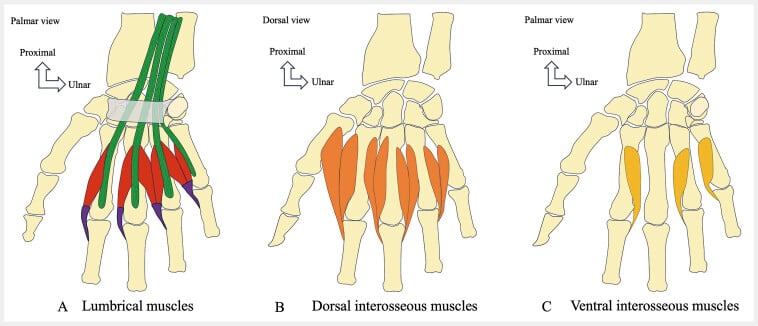
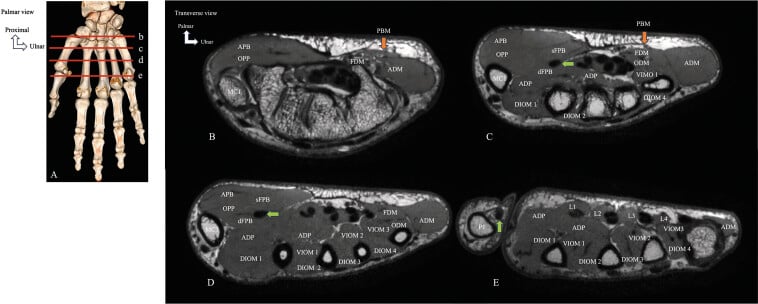
Pathophysiology
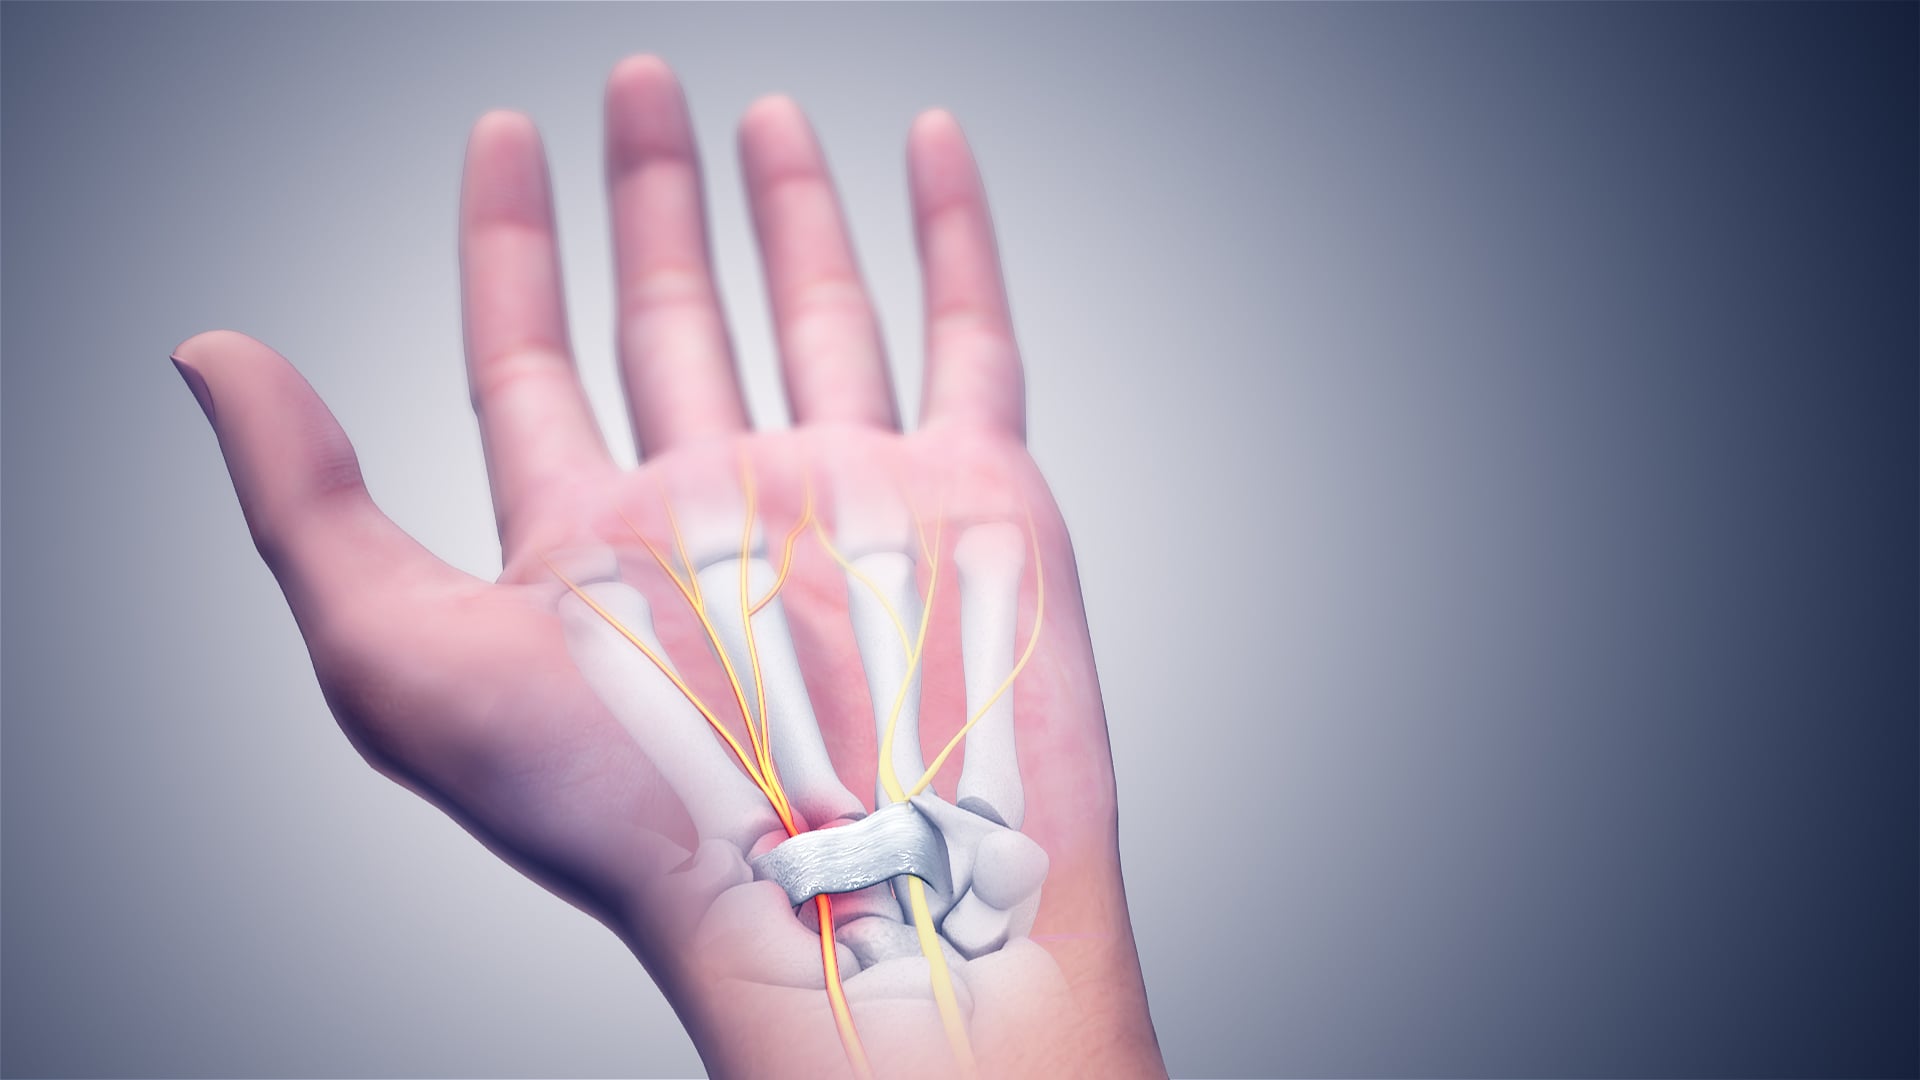
Pressure first. Normal intracarpal pressure is 2-10 mmHg. In CTS it runs 30-110 mmHg, and 30 mmHg is the threshold at which symptoms appear; moving the wrist into flexion or extension raises it further. From there the sequence is predictable.
- Venous congestion. Raised pressure obstructs venous outflow, oedema collects within the epineurium, and the oedema raises the pressure again - a vicious cycle.
- Ischaemia and demyelination. Chronic ischaemia produces focal demyelination. This stage is reversible with decompression, and it is the one that gives sensory symptoms and prolonged latencies on nerve conduction studies.
- Axonal damage. Severe chronic compression causes axonal loss with Wallerian degeneration. It is irreversible, it is what produces thenar atrophy, and recovery is limited even after decompression.
The wrist falls into flexion during sleep, which raises tunnel pressure; the dependent position of the hand causes venous congestion; and lying recumbent redistributes fluid, adding to the oedema. All three are the argument for a neutral night splint.
Classification Systems
Clinical grade sets the urgency of treatment rather than the diagnosis: mild disease earns a conservative trial, and severe disease does not.
- Symptoms
- Intermittent paraesthesia, nocturnal symptoms
- Examination
- Normal sensation, normal motor, positive provocative tests
- Management
- Splinting 6-8 weeks, activity modification
- Symptoms
- Persistent paraesthesia, occasional weakness
- Examination
- Sensory deficit in median distribution, positive Phalen's/Durkan's
- Management
- Injection trial OR proceed to surgery
- Symptoms
- Constant numbness, weakness, thenar wasting
- Examination
- Thenar atrophy, APB weakness, impaired 2PD
- Management
- Urgent carpal tunnel release
Acute CTS is a separate entity from the chronic compressive disease graded above, and it is a surgical emergency - never manage it down the splint-then-electrodiagnostics-then-elective-surgery pathway. It is a closed-compartment phenomenon: a sudden rise in intracarpal pressure damages the median nerve over hours.
The causes. Distal radius fracture (especially high-energy injuries, and iatrogenically from an over-flexed, ulnar-deviated "Cotton-Loder" reduction position), perilunate or lunate dislocation, carpal or crush trauma, bleeding into the tunnel (anticoagulation, haemophilia, vascular injury), high-pressure injection injury, local infection, burns, and a tight constricting cast or dressing.
Recognition. Rapidly progressive, severe and unrelenting median-territory pain and paraesthesia, pain that is out of proportion and worsened by passive finger extension - in contrast to the intermittent, nocturnal, slowly progressive symptoms of chronic CTS. Worsening or non-resolving median symptoms after a distal radius fracture reduction are acute CTS until proven otherwise.
Management. Do not wait for nerve conduction studies. Split or remove constricting casts and dressings, take the wrist out of excessive flexion, elevate, and proceed to urgent open carpal tunnel decompression (combined with fracture stabilisation when relevant). Delay risks permanent median nerve injury. This differs from the transient median paraesthesia that settles immediately on reducing a fracture, which can be observed.
Clinical Assessment
The history. Nocturnal paraesthesia - waking at night with numbness - is the classic story and occurs in 75% of patients, and the symptoms sit in the thumb, index, middle and radial half of the ring finger with palmar sensation preserved. Shaking or flicking the hand to relieve the symptoms is the flick sign, a useful question to ask rather than a pathognomonic finding. Progression runs sensory to motor, the motor complaints being weakness, clumsiness and dropping objects.
What makes it worse. Sustained wrist flexion (driving, reading, phone use), repetitive gripping or pinching, vibration exposure and cold weather. Pain radiates to the forearm or shoulder in 25%, and patients describe difficulty with buttoning and writing and weakness of pinch grip.
Ask the question - it is a good question. "What do you do with the hand when the symptoms are at their worst?" A demonstrated flicking movement of the wrist and fingers is a positive response.
But know what the number means, because it is one of the most widely misquoted figures in hand surgery. Pryse-Phillips' original 1984 paper (PMID 6470728) reported that a positive flick sign predicted electrodiagnostic abnormality in 93% of cases, with a false-positive rate under 5% among other neural lesions in the arm. That 93% is a POSITIVE PREDICTIVE VALUE in a referred population, not a sensitivity - and a predictive value rises and falls with prevalence, so it does not transfer to your clinic.
It did not replicate. Hansen et al (Am J Phys Med Rehabil 2004, PMID 15100625) applied the flick, Phalen and Tinel manoeuvres to 142 patients referred for nerve conduction studies (67% of whom had CTS) and found the flick sign 37% sensitive with a 26% false-positive rate - concluding it is "of limited clinical utility". The JAMA Rational Clinical Examination systematic review (PMID 10865306) placed the flick sign among manoeuvres that "require validation by other studies before they can be recommended".
Exam answer: a positive flick sign raises your suspicion; a negative one does not lower it much (it misses roughly two-thirds of cases). Never call it pathognomonic in a viva.
Inspection. Compare the thenar bulk of both hands palms-up: APB wasting shows as a depression over the thenar eminence. Trophic skin changes appear in severe cases.
Sensory testing. Light touch over the radial three and a half digits palmarly, compared against the little finger as an ulnar control, with Semmes-Weinstein monofilaments if objective testing is wanted. Two-point discrimination greater than 6mm is abnormal (normal 2-5mm), but it is a late finding reflecting large-fibre loss, and the JAMA systematic review found two-point testing of little diagnostic value - a normal result does not exclude CTS.
Motor testing. The abductor pollicis brevis is the muscle to test. With the hand palm-up on the table, ask the patient to point the thumb at the ceiling against resistance, palpate the muscle as it contracts, and grade it 0-5. Add opponens pollicis (thumb tip to little finger tip) and pinch strength, which is weak in advanced disease.
Provocative tests. Each sets out to reproduce the patient's symptoms in the median distribution; they differ in how reliably they do it.
- Technique
- Maximum wrist flexion 60 seconds
- Positive Finding
- Paraesthesia in median distribution
- Sensitivity
- 68%
- Specificity
- 73%
- Technique
- Maximum wrist extension 60 seconds
- Positive Finding
- Paraesthesia in median distribution
- Sensitivity
- 48%
- Specificity
- 76%
- Technique
- Tap over carpal tunnel at wrist crease
- Positive Finding
- Electric sensation in median distribution
- Sensitivity
- 50%
- Specificity
- 77%
- Technique
- Direct compression over tunnel 30 seconds
- Positive Finding
- Paraesthesia in median distribution
- Sensitivity
- 64%
- Specificity
- 83%
- Technique
- BP cuff inflated above systolic for 60s
- Positive Finding
- Reproduction of symptoms
- Sensitivity
- 70%
- Specificity
- 80%
Every manoeuvre in the table above performs worse in practice than its quoted figure, because most were derived in referred populations already enriched for CTS and validated against nerve conduction studies, which are themselves an imperfect reference standard. The JAMA Rational Clinical Examination review of 12 studies (PMID 10865306) found that in patients presenting with hand dysaesthesia the findings that best distinguish CTS are:
- Likelihood ratio (95% CI)
- 3.1 (2.0-5.1)
- Likelihood ratio (95% CI)
- 2.4 (1.6-3.5)
- Likelihood ratio (95% CI)
- 1.8 (1.4-2.3)
- Likelihood ratio (95% CI)
- 0.2 (0.0-0.7)
- Likelihood ratio (95% CI)
- 0.5 (0.4-0.7)
The same review found nocturnal paraesthesia, Phalen's sign, Tinel's sign, thenar atrophy and two-point, vibratory and monofilament testing had little or no diagnostic value taken individually. Note the asymmetry that matters clinically: an unlikely hand diagram and normal thumb abduction are the two findings that genuinely argue a patient does NOT have CTS - the provocative tests cannot do that job, because their sensitivity is too low for a negative to reassure.
The Katz hand diagram is simply a hand outline the patient marks themselves with the site and type of symptom, then rated classic / probable / possible / unlikely. It costs nothing and outperforms the manoeuvres most candidates recite.
- Distinguishing features
- Nocturnal paraesthesia, flick sign, median digits
- Palmar sensation
- Spared (palmar cutaneous branch proximal)
- Key test
- Durkan's compression; NCS
- Distinguishing features
- Neck pain, dermatomal arm pain, reflex changes (biceps/triceps)
- Palmar sensation
- Often affected (proximal to branch)
- Key test
- Spurling's test; cervical MRI
- Distinguishing features
- Proximal forearm pain, NO night symptoms, FDS/FPL/AIN may be weak
- Palmar sensation
- Affected (lesion proximal to branch)
- Key test
- Resisted pronation/FDS provocation
- Distinguishing features
- Provoked by arm elevation, often ulnar (C8-T1) distribution
- Palmar sensation
- Variable
- Key test
- Roos/EAST test; Adson's
- Distinguishing features
- Little and ulnar-ring finger, hypothenar/interossei wasting
- Palmar sensation
- Median palm spared (ulnar territory affected)
- Key test
- Elbow flexion test; Froment's; NCS
- Distinguishing features
- Symmetrical stocking-glove, systemic (diabetes, alcohol)
- Palmar sensation
- Affected diffusely, not median-specific
- Key test
- Bloods, generalised NCS
- Distinguishing features
- Radial-sided wrist PAIN (not numbness), 1st extensor compartment
- Palmar sensation
- Normal
- Key test
- Finkelstein / Eichhoff test
- Distinguishing features
- Mechanical thumb-base pain, crepitus, grind
- Palmar sensation
- Normal
- Key test
- Grind test; radiographs
Where each of those differentials is worked up in full. The distinction that carries the most weight in an exam is the level of the lesion, and the palmar cutaneous branch is the anatomical reason it works: a lesion proximal to the tunnel takes the palm with it. C6/C7 cervical radiculopathy and pronator (proximal median) syndrome both sit proximal to that branch and both spare nothing; thoracic outlet syndrome is more often ulnar-sided and positional. Cubital tunnel syndrome is the mirror-image compression at the other side of the hand and is the neuropathy most often confused with CTS when the patient reports "the whole hand". Where a release has failed, or symptoms outrun the territory, the double-crush pearl below and nerve injury and regeneration explain why a technically complete decompression can still disappoint.
- Bilateral severe symptoms with rapid onset - consider cervical myelopathy
- Numbness in the palm itself - not true CTS, consider a proximal lesion
- Weakness without sensory symptoms - consider motor neuron disease or C8 radiculopathy
- Atypical distribution - consider an alternative diagnosis
A classic examinable concept absent from the simple "CTS versus cervical radiculopathy" differential: the two can coexist and compound each other. The double-crush hypothesis (Upton and McComas, 1973) proposes that a single axon compressed at one point becomes more vulnerable to a second, often subclinical, compression elsewhere along its course - impaired axoplasmic flow from the proximal lesion lowers the threshold for symptoms at the distal site, so two mild lesions together produce disproportionate symptoms.
Why it matters in CTS. The relevance is to the failed release and the atypical presentation.
- A proximal lesion - most commonly C6/C7 cervical radiculopathy, but also thoracic outlet or a proximal median (pronator) compression - frequently coexists with median compression at the wrist; either lesion alone may be mild or subclinical.
- It is a recognised explanation for persistent symptoms after a technically complete carpal tunnel release - the unaddressed proximal lesion remains. When release fails to relieve symptoms, or when symptoms are atypical, extend beyond the median territory, or include neck/proximal arm features, actively look for a proximal source (cervical spine examination and imaging, proximal nerve conduction studies).
- A "reverse" double crush (a distal lesion sensitising a proximal segment) is also described.
Exam point: always consider a second compression site - especially the cervical spine - when CTS presentation is atypical or surgery does not deliver the expected relief.
Investigations
Nerve conduction studies are the gold standard for confirming the diagnosis and grading severity. Request them when the presentation is atypical, when symptoms are bilateral and severe, to confirm the diagnosis before surgery, in a young patient (under 40), for medico-legal cases, and to put a number on severity and prognosis.
How it is done. Sensory studies are performed orthodromically (digit to wrist) or antidromically (wrist to digit), stimulating at the wrist and recording from the index or middle finger, measuring distal sensory latency and amplitude - normal is less than 3.5ms. The motor study stimulates the median nerve at the wrist and records from APB, with a normal distal motor latency under 4.5ms, and the ulnar nerve to ADM serves as the internal control.
What makes it diagnostic. Beyond the absolute latencies, the comparisons matter: a median-ulnar sensory latency difference greater than 0.5ms, or a motor difference greater than 1.0ms. Amplitudes fall as disease advances, a reduced motor amplitude indicating axonal loss. The study may be normal in early mild disease, so compare with the contralateral side and the ulnar nerve before calling it negative.
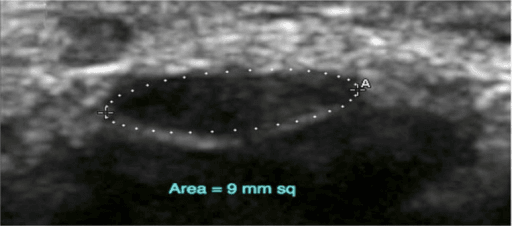
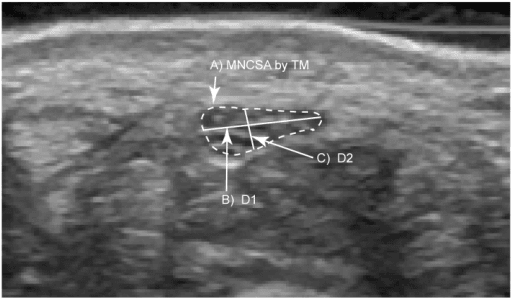
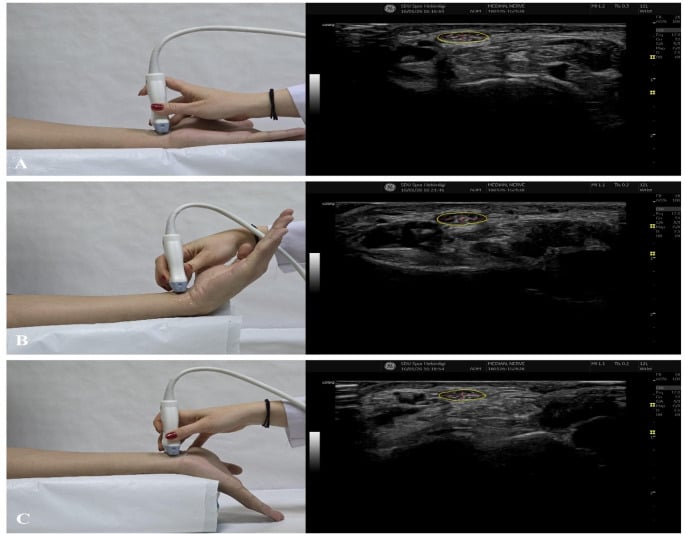
Ultrasound is used increasingly, and it answers structural questions electrophysiology cannot: it is non-invasive with no electrical stimulation, shows the nerve in real time, identifies structural causes such as a ganglion or a persistent median artery, and can guide an injection. It is operator-dependent, does not assess function, and cannot quantify severity the way nerve conduction studies do.
- Cross-sectional area greater than 10-12mm² at the tunnel inlet
- Flattening ratio - anterior-posterior against medial-lateral diameter
- Bowing of the retinaculum - displacement greater than 2mm
- Dynamic assessment - nerve movement with finger flexion
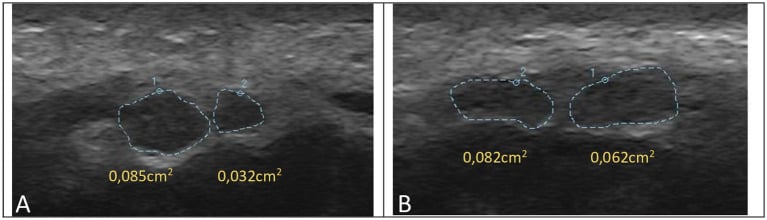
MRI is not routine. Reserve it for a suspected mass lesion, an atypical presentation, failed surgery, and research. It shows T2 hyperintensity and enlargement of the nerve, muscle oedema if denervation is acute, and thenar atrophy once the change is chronic.
Bloods, when the cause is not obvious. TSH for hypothyroidism, HbA1c for diabetes, rheumatoid factor and anti-CCP for rheumatoid arthritis, and serum protein electrophoresis if amyloid is suspected.
Management Algorithm
The decision. Thenar wasting, objective weakness, denervation on electrodiagnostics or severe persistent symptoms mean advanced compression, and those patients are offered release straight away rather than a conservative trial; counsel them that sensory symptoms improve but thenar strength may not fully return. Everyone else - mild to moderate disease with normal thenar muscles - starts with a splint, and the injection sits between the two as a temporising measure.
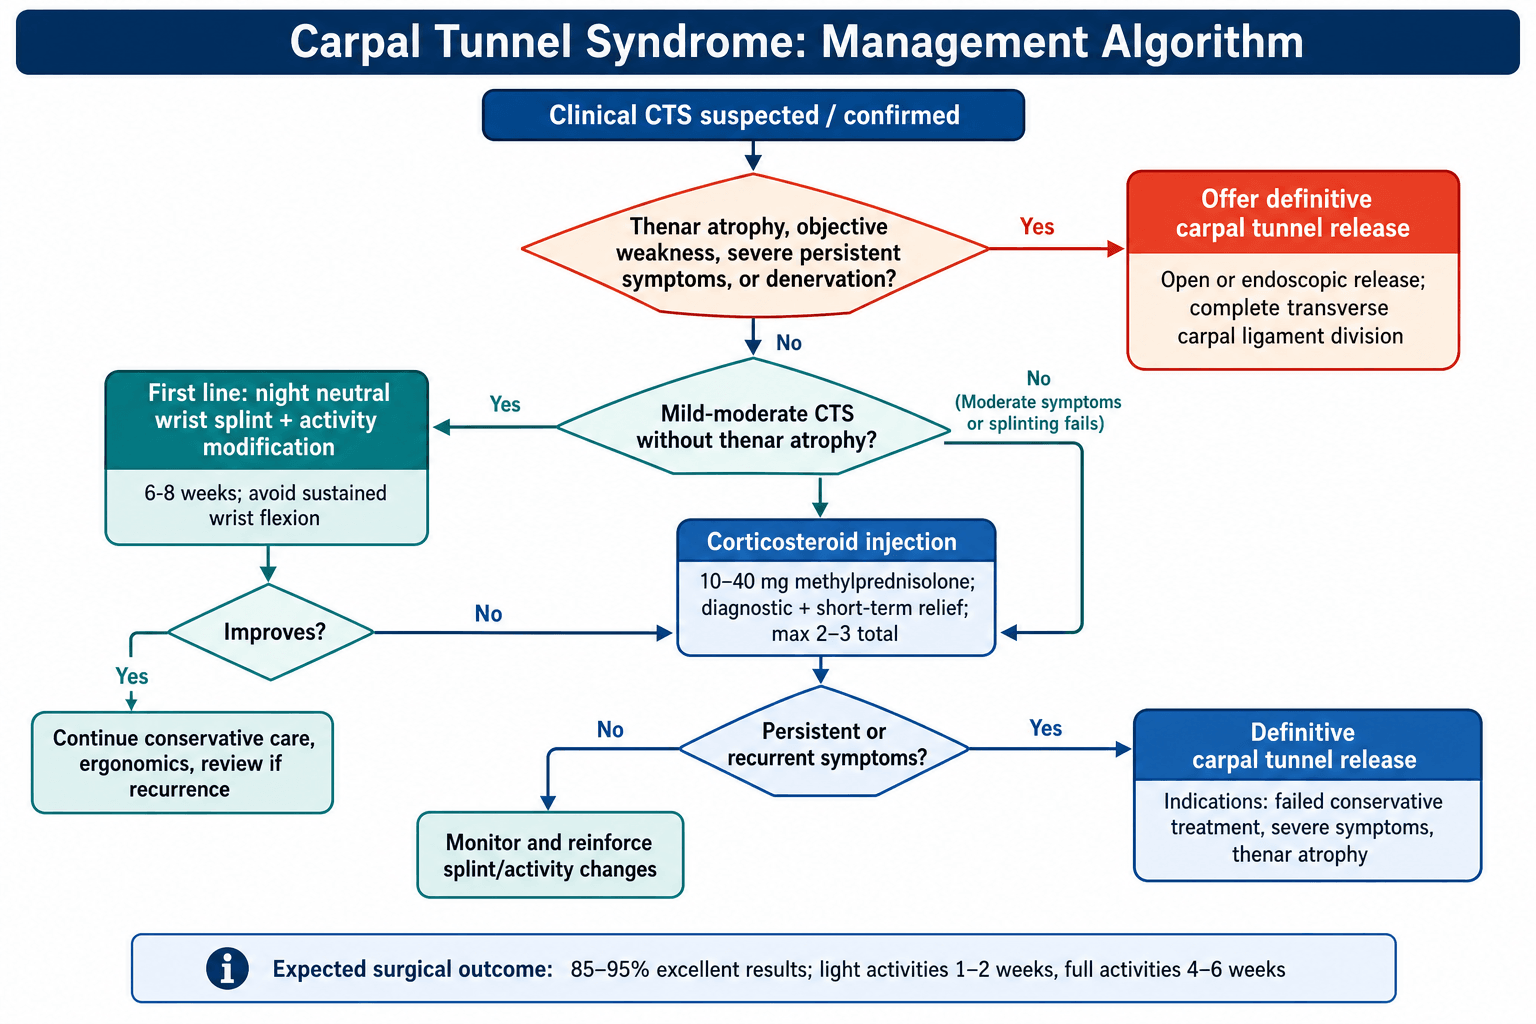
The night splint. Hold the wrist neutral (0-5 degrees of extension), not flexed and not hyperextended, worn during sleep for a minimum of 6-8 weeks. Full-time splinting is no better than night-only. It works best in mild disease, in pregnancy and in recent-onset symptoms, with a success rate of 30-50% at six months.
How that squares with the trial evidence. Gerritsen's randomised comparison against open release found splinting successful in 54% at three months - a little above the 30-50% quoted above - against 80% for surgery. By 18 months 41% of the splinted group had crossed over to surgery. Splinting is a reasonable first step, not a destination.
Activity modification. Avoid sustained wrist flexion (computer use, driving), take frequent breaks from repetitive tasks, adjust the workstation (keyboard height, mouse position), and modify the grip in cycling and tennis.
Corticosteroid injection. Both a treatment and a diagnostic test: relief within days that lasts weeks to months confirms the tunnel is the site of the problem. Give 1ml (10-40mg) methylprednisolone with 1ml of local anaesthetic, and splint for two weeks afterwards. Expect 70-80% short-term relief and 20-30% long-term benefit, with a maximum of 2-3 injections in total.
- Position the wrist slightly extended
- Enter 1cm proximal to the distal wrist crease, ulnar to palmaris longus
- Angle the needle 45 degrees distally
- Advance just past the retinaculum, felt as a loss of resistance
- Inject 0.5ml of saline first; it should meet no resistance, which guards against an intraneural injection
What the injection can and cannot buy. The Cochrane review found reliable benefit at one month against placebo but no demonstrated relief beyond that, and a second injection added nothing significant. The five-year randomised follow-up is blunter still: a single injection delayed surgery and modestly reduced the eventual surgery rate, but 84-97% of patients across all three arms had been operated on by five years. Most patients with moderate to severe disease will eventually need a release.
Everything else has thin evidence. Oral corticosteroids as a short course only; vitamin B6 with no proven benefit in trials; NSAIDs for symptom control without disease modification; diuretics with no evidence of efficacy; therapeutic ultrasound with inconsistent evidence; and yoga or stretching, with some evidence for symptom relief.
Surgical Technique
Who is offered surgery. Failed conservative treatment (6 months or more), moderate to severe changes on nerve conduction studies, thenar atrophy or weakness, persistent disabling symptoms, a patient who prefers definitive treatment, and acute carpal tunnel syndrome from trauma or haemorrhage.
Setup. Supine with the arm on a hand table as day surgery, an upper arm tourniquet at 250 mmHg, and either local anaesthetic (1% lidocaine with adrenaline) or a regional block. Prepare and drape the hand and forearm, and mark the incision with the wrist flexed and then extended so that the transverse crease is avoided.
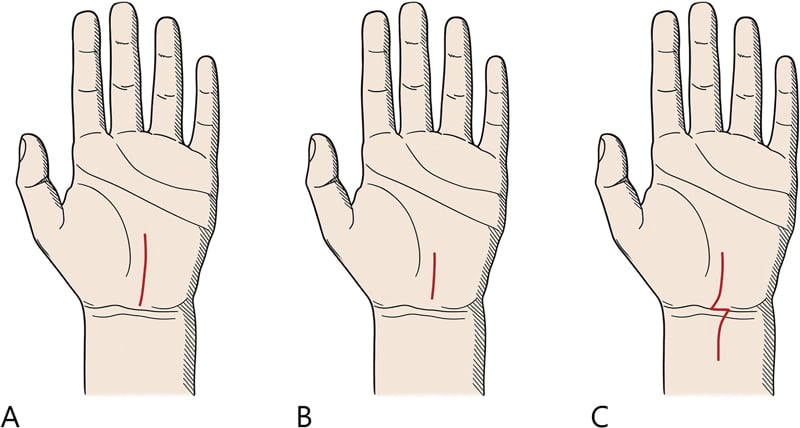
The incision. Longitudinal, in line with the radial border of the ring finger, from the distal wrist crease to mid-palm, staying ulnar to the thenar crease: 3-4cm for an extended release, 2-3cm for a mini-open. Do not cross the wrist crease transversely, which produces a hypertrophic scar.
The steps.
- Skin and subcutaneous dissection. Incise the skin, identify and protect the superficially running palmar cutaneous branch, divide the palmar fascia in line with the incision, and find the transverse carpal ligament as a white fibrous band.
- Identify the landmarks. Palmaris longus as the surface landmark to stay ulnar to, flexor carpi radialis as the radial boundary to avoid, and the ulnar neurovascular bundle as the ulnar boundary to stay radial to.
- Divide the ligament. Pass mosquito forceps under the ligament to protect the nerve, elevate the ligament away from it, and divide it with knife or scissors under direct vision. Carry the release distally to the superficial palmar arch, where the tissue gives, and proximally into the antebrachial fascia 2cm proximal to the crease, then run a probe underneath to confirm the division is complete.
- Inspect the contents. The median nerve should look flattened, sometimes hourglass-shaped. Look for anatomical variations (a bifid nerve, a persistent median artery), for masses (ganglion, lipoma), and for proliferative synovitis, which may need debulking. Do not perform an internal neurolysis: it increases scarring and worsens outcomes.
- Haemostasis and closure. Release the tourniquet and achieve meticulous haemostasis to prevent a haematoma. Do not repair the transverse carpal ligament - that recreates the compression you came to relieve. Close skin only with interrupted 4-0 nylon, apply a bulky dressing in the functional position, and allow immediate finger movement.
The technical pearls that prevent revision. Divide the ligament completely, extending the release proximally into the forearm fascia and distally to the superficial arch. Protect the recurrent motor branch, which leaves the ulnar side of the nerve distally; if the thenar muscles are not visible, assume the branch is extraligamentous.
Structures at risk. The palmar cutaneous branch, superficial and easily caught by the skin incision; the recurrent motor branch, with its variable course; the superficial palmar arch at the distal limit of the release; and the ulnar nerve and artery at the ulnar boundary of the incision.
Complications
- Incidence
- 10-20%
- Presentation
- Pain at thenar/hypothenar eminence for 3-6 months
- Management
- Reassurance, hand therapy, resolves spontaneously
- Incidence
- 2-5%
- Presentation
- Persistent symptoms unchanged from pre-op
- Management
- Repeat NCS, revision surgery if confirmed
- Incidence
- 5-10%
- Presentation
- Tender incision scar for months
- Management
- Desensitisation, silicone gel, massage
- Incidence
- 0.1-0.5%
- Presentation
- Immediate post-op numbness or weakness
- Management
- Urgent exploration if transection suspected
- Incidence
- 0.3-1%
- Presentation
- Thenar weakness post-operatively
- Management
- Exploration and repair if identified early
- Incidence
- Under 1%
- Presentation
- Haematoma, brisk bleeding
- Management
- Immediate control, vascular repair
- Incidence
- 1-5%
- Presentation
- Severe pain, stiffness, autonomic changes
- Management
- Multidisciplinary pain management, PT/OT
- Incidence
- Under 1%
- Presentation
- Wound erythema, drainage, fever
- Management
- Antibiotics, wound care, possible I&D
- Incidence
- Rare
- Presentation
- Weakness of grip, visible tendon prominence
- Management
- Rare, usually asymptomatic
Pillar pain is the commonest complication and follows from the operation itself: dividing the ligament separates the thenar and hypothenar muscle origins from it. Patients describe an ache at the bases of the thumb and the hypothenar eminence, worse with grip and pinch. It typically resolves by 3 months, can persist across the 3-6 months given in the table above, and occasionally runs to 6-12 months; it is managed with reassurance, grip strengthening and thenar massage. Releasing the ligament only partially to avoid it is not the answer, because it risks an incomplete decompression.
Incomplete release is the commonest cause of persistent symptoms: a ligament not divided fully distally or proximally, an inadequate proximal release of the antebrachial fascia, or anomalous anatomy that went unrecognised. Repeat nerve conduction studies and ultrasound showing residual compression make the case, and the treatment is revision open release with an extended division.
Median nerve laceration is rare and devastating. It presents immediately after surgery with dense numbness and weakness, and it needs urgent exploration and primary repair, with a nerve graft if there is a gap.
Recurrent motor branch injury is commoner, particularly with the transligamentous variant, and presents as thenar weakness. Explore and repair if it is recognised within 72 hours; late recognition is managed conservatively, with tendon transfers if needed.
Complex regional pain syndrome brings disproportionate pain, stiffness and swelling with autonomic changes in temperature, colour and sweating. Recognising it early is what changes the course. Management is multidisciplinary - pain specialist, physiotherapy and occupational therapy, psychology - with gabapentin, vitamin C prophylaxis (some evidence) and sympathetic blocks if severe.
Postoperative Care and Recovery
Postoperative Protocol
Protection, with the fingers moving from the outset.
- Bulky dressing with the wrist in neutral, kept dry
- Elevate the hand above the heart to prevent oedema
- Immediate finger movement - flex and extend hourly
- Ice and oral analgesia (paracetamol, NSAIDs)
The wound is checked and the sutures come out.
- Dressing off at 1 week, sutures out at 10-14 days
- Scar massage with moisturiser
- Light activities of daily living permitted; avoid lifting more than 2kg
- Grip strengthening - squeezing a soft ball
Loading is progressive and guided by the scar and the grip.
- Progressive grip strengthening, full finger movement expected
- Desensitisation if the scar is tender
- Driving once the patient can control the vehicle safely, typically 1-2 weeks
Sensation recovers first and motor function last.
- Sensory recovery complete by 3-6 months
- Motor recovery depends on pre-operative severity and may take 6-12 months
- Scar maturation continues for 6-12 months
Refer for hand therapy when recovery is not following that course: severe pre-operative stiffness, pillar pain persisting beyond 6 weeks, symptoms of complex regional pain syndrome, slow functional recovery, grip weakness or a sensitive scar. The therapist works on oedema control (elevation, retrograde massage), scar desensitisation and massage, progressive grip and pinch strengthening, tendon gliding, and conditioning for return to work.
- Timeline
- Immediate to weeks
- Notes
- Nocturnal symptoms resolve immediately
- Timeline
- Weeks to months
- Notes
- Depends on severity, mild = weeks
- Timeline
- Months
- Notes
- Incomplete if severe atrophy
- Timeline
- 3-6 months
- Notes
- Open slower than endoscopic initially
- Timeline
- 1-2 weeks
- Notes
- Variable by patient
- Timeline
- 4-6 weeks open, 2-4 weeks endo
- Notes
- Depends on demands
- Timeline
- 3-6 months
- Notes
- 85-95% satisfied
Outcomes and Prognosis
What release achieves. 85-95% of patients report an excellent or good outcome, 90-95% get relief of nocturnal paraesthesia, and 80-90% recover sensation completely if they were mild to moderate before surgery. Motor recovery is the variable one, depending on severity and duration of compression.
Where the lower figures come from. Bland's postal survey of 1268 decompressions returned a self-reported success rate of 69%, well below the figures above, and found middle-grade nerve conduction abnormality did better than either very severe or normal studies. Satisfaction is higher with appropriate patient selection, which is what the factors below describe.
- Favorable Prognosis
- Less than 1 year
- Poor Prognosis
- Greater than 2 years
- Favorable Prognosis
- Mild to moderate (no atrophy)
- Poor Prognosis
- Severe with thenar wasting
- Favorable Prognosis
- Under 50 years
- Poor Prognosis
- Over 65 years
- Favorable Prognosis
- Sensory changes only
- Poor Prognosis
- Absent responses, denervation
- Favorable Prognosis
- No diabetes
- Poor Prognosis
- Diabetes present
- Favorable Prognosis
- Normal BMI
- Poor Prognosis
- BMI greater than 35
- Favorable Prognosis
- No WC claim
- Poor Prognosis
- Active WC claim
- Favorable Prognosis
- Unilateral
- Poor Prognosis
- Bilateral severe
Measuring the outcome. The Boston Carpal Tunnel Questionnaire (BCTQ) is the most widely used validated measure, with an 11-question Symptom Severity Scale and an 8-question Functional Status Scale; an improvement of 1.0 point or more is clinically significant. After release the symptom score improves from 3.2 to 1.5 out of 5 and the functional score from 2.8 to 1.4, with maximal improvement at 3-6 months. 85-90% of patients would have the operation again, and 10-15% are disappointed by persistent symptoms or complications.
Recurrence and persistence are different problems. True recurrence - scar tissue recompressing the nerve - affects 5-10% over ten years, is commoner in diabetes, rheumatoid arthritis and dialysis patients, and presents as a gradual return of symptoms after a period of genuine relief. Persistent symptoms, the commoner of the two, never had that symptom-free interval, and mean the ligament was not fully divided. Both are confirmed by repeat nerve conduction studies and ultrasound, and both are treated by revision release - with neurolysis and fat flap or vein wrap coverage where scar is the problem.
Guidelines, Registries & Global Practice
Carpal tunnel syndrome is the most common compression neuropathy worldwide and is managed in essentially every health system, but diagnostic pathways and thresholds for surgery differ by region and resource setting.
Global Epidemiology
The best population-based estimate comes from Atroshi et al (JAMA 1999, DOI), a Swedish general-population survey of 2466 responders: clinically certain CTS prevalence was 3.8%, electrophysiologically confirmed median neuropathy 4.9%, and combined clinical-plus-electrophysiological CTS 2.7%. Hand paraesthesia symptoms were far more common (14.4%), so symptoms alone over-estimate disease.
- Prevalence: roughly 3-5% of the general adult population, with a consistent female predominance (about 3:1 in most series).
- Occupational burden: markedly higher in jobs with forceful, repetitive or vibratory hand use (e.g. food/meat processing, assembly, construction) - work-related attributable fractions are concentrated in a small number of high-risk jobs (Roquelaure et al, BMC Public Health 2018, DOI).
- Systemic associations: diabetes, obesity, hypothyroidism, pregnancy, rheumatoid arthritis and amyloid raise risk across all populations.
Major Guidelines, Side by Side
- Diagnosis
- Clinical diagnosis; electrodiagnostics recommended to confirm and grade, especially pre-operatively
- First-line
- Immobilisation (splint), steroid injection, oral steroid for mild-moderate
- Surgery / key stance
- Surgical release recommended over no surgery; routine internal neurolysis, flexor tenosynovectomy and epineurotomy NOT recommended (moderate-strong evidence)
- Diagnosis
- Largely clinical; nerve conduction studies if diagnosis uncertain or before surgery
- First-line
- Splinting and/or corticosteroid injection for mild-moderate symptoms
- Surgery / key stance
- Refer for decompression if severe, persistent, or with motor signs; open and endoscopic both accepted
- Diagnosis
- Clinical + electrodiagnostic confirmation; ultrasound as adjunct (nerve CSA)
- First-line
- Splint and injection; steroid injection has best short-term evidence
- Surgery / key stance
- Decompression for refractory or severe disease; technique by surgeon preference
- Diagnosis
- Predominantly clinical (NCS often unavailable)
- First-line
- Splinting and injection where available
- Surgery / key stance
- Open release under local anaesthetic / WALANT favoured (low cost, no NCS dependency)
Across guidelines the common threads are: (1) CTS is fundamentally a clinical diagnosis; (2) electrodiagnostic testing confirms the diagnosis, grades severity and predicts outcome but is not mandatory in classic cases; (3) splinting and a single corticosteroid injection are reasonable first-line measures for mild-moderate disease; and (4) surgical decompression is the definitive treatment, indicated urgently when there is thenar wasting or motor loss. The main genuine divergence is how readily electrodiagnostics are required before surgery (more emphasised in North America and for medico-legal/occupational cases) versus a more clinically driven pathway elsewhere.
Registry and Large-cohort Evidence
CTS is not an implant procedure, so it is not captured by the arthroplasty joint registries (NJR, AJRR, AOANJRR, SHAR). The closest "registry-scale" evidence comes from large national audit and administrative cohorts. Bland (Muscle Nerve 2001, DOI) analysed 1268 decompressions and reported a 69% self-reported success rate, with pre-operative nerve-conduction grade the strongest outcome predictor - very severe (axonal) and entirely normal studies both did worse than mid-grade abnormality.
Global Practice Variation
- Anaesthesia: wide-awake local anaesthetic no-tourniquet (WALANT) and field-block open release are increasingly standard worldwide and are particularly valuable where theatre and anaesthetic resources are limited.
- Technique: endoscopic release is more common in well-resourced centres for faster return to work, but Cochrane evidence (Vasiliadis 2014) shows no long-term advantage over open release.
- Imaging: high-resolution ultrasound (median nerve cross-sectional area) is used as a first-line confirmatory test in some European and Asian centres, reducing reliance on nerve conduction studies.
Medico-Legal and Consent Considerations (universal)
Informed consent should cover the natural history, conservative options and their success rates, and surgical risks: median or recurrent motor branch injury (0.1-0.5%), pillar pain (10-20%), incomplete relief (especially when thenar atrophy is already present), complex regional pain syndrome (rare), and the recovery/return-to-work timeline. Documentation of severity grading, thenar assessment, electrodiagnostic results and the duration of conservative treatment is good practice in any jurisdiction. The recurring litigation themes are nerve transection, incomplete release with persistent symptoms, and delayed diagnosis leading to irreversible thenar wasting.
MCQ Practice Points
Q: How many structures pass through the carpal tunnel?
A: 10 structures - Nine flexor tendons (4 FDS, 4 FDP, 1 FPL) plus the median nerve. The median nerve is the most superficial and radial structure. Note that the ulnar nerve and artery pass through Guyon's canal, NOT the carpal tunnel.
Q: Why is palmar sensation preserved in carpal tunnel syndrome?
A: The palmar cutaneous branch of the median nerve branches 5-6cm proximal to the wrist crease and passes superficial to the transverse carpal ligament. Therefore it is not compressed in the tunnel. This is a key feature that distinguishes CTS from more proximal median nerve lesions or C6 radiculopathy.
Q: Which muscles are supplied by the recurrent motor branch of the median nerve?
A: LOAF - Lumbricals 1 and 2, Opponens pollicis, Abductor pollicis brevis, Flexor pollicis brevis (superficial head only). The deep head of FPB is supplied by the ulnar nerve. Adductor pollicis is also ulnar nerve.
Q: Of the three standard provocative tests, which has the highest sensitivity for diagnosing CTS?
A: Phalen's test (68% sensitivity, 73% specificity in MacDermid and Wessel's pooled review). Durkan's compression test - direct compression over the carpal tunnel for 30 seconds - is slightly less sensitive (64%) but the most specific of the three (83%), and Tinel's sign is the least sensitive (50% sensitivity, 77% specificity).
Q: What are the nerve conduction criteria for diagnosing CTS?
A: Prolonged distal motor latency greater than 4.5ms (wrist to APB) and/or prolonged sensory latency greater than 3.5ms (wrist to digit). May also see reduced amplitudes if severe. Always compare to ulnar nerve as internal control. Median-ulnar sensory latency difference greater than 0.5ms is significant.
Q: What is the most common anatomical variant of the recurrent motor branch?
A: Extraligamentous (50%) - the motor branch exits the median nerve distal to the transverse carpal ligament. This is the safest variant during surgery. Subligamentous (30%) travels under the ligament before exiting. Transligamentous (20%) pierces through the ligament and is at risk during endoscopic release.
Q: What is the most common complication after carpal tunnel release?
A: Pillar pain (10-20% incidence) - aching pain at the thenar and hypothenar eminences due to separation of muscle origins from the divided ligament. Typically resolves spontaneously by 3-6 months. Managed with reassurance and hand therapy.
Q: How should you manage carpal tunnel syndrome in pregnancy?
A: Conservative management - night splinting in neutral position is first-line. Symptoms usually resolve post-partum (2-4 weeks after delivery). Corticosteroid injection is safe if splinting fails. Avoid surgery during pregnancy unless severe progressive motor loss. Most cases resolve without intervention.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 52-year-old woman presents with 8 months of waking at night with numbness in her right hand. She shakes her hand for relief. Her symptoms are worse after driving. Examination shows normal thenar bulk, positive Phalen's test. How would you manage this patient?”
“A 65-year-old diabetic man presents with constant numbness and difficulty buttoning his shirt. On examination, there is obvious thenar muscle wasting and weakness of thumb abduction. What is your management?”
“A 45-year-old woman returns 6 months after open carpal tunnel release with persistent symptoms identical to pre-operative. Her nerve conduction studies showed severe CTS pre-operatively. What is your approach?”
Key Anatomy
- Tunnel contents: 9 tendons (4 FDS + 4 FDP + FPL) + median nerve = 10 total
- Floor = carpal bones; Roof = transverse carpal ligament (2.5-3cm long)
- Median nerve most superficial and radial (at risk)
- Palmar cutaneous branch: 5cm proximal, travels superficial (SPARED)
- Recurrent motor branch: Extraligamentous 50%, subligamentous 30%, transligamentous 20%
- LOAF muscles: Lumbricals 1-2, Opponens, APB, FPB superficial head
Clinical Diagnosis
- Classic triad: Nocturnal paresthesia + flick sign + median distribution - TYPICAL, not diagnostic (flick 37% sensitive on replication)
- Distribution: Thumb, index, middle, radial half ring (palmar ONLY)
- Thenar atrophy = SEVERE (APB wasting, urgent surgery needed)
- Provocative tests: Phalen's 68% sens, Durkan's 64% sens (83% spec, most specific), Tinel's 50% sens
- Differential: C6 radiculopathy (palmar sensation affected), pronator syndrome, TOS
Investigations
- NCS gold standard: Motor latency greater than 4.5ms, sensory greater than 3.5ms
- EMG: Denervation in APB if severe (fibrillations, positive sharp waves)
- Ultrasound: Nerve CSA greater than 10mm² at inlet, can identify masses
- MRI not routine (only if mass or atypical)
- Screen: TSH (hypothyroid), HbA1c (diabetes), RF (RA)
Management Algorithm
- Mild-moderate WITHOUT atrophy: Splint neutral position 6-8 weeks first
- Injection: 70-80% short-term relief, 20-30% long-term, limit 2-3 max
- Severe OR thenar atrophy: Urgent CTR (do NOT delay)
- Surgery success: 85-95% excellent outcomes
- Open vs endoscopic: Similar long-term, endoscopic faster recovery
Surgical Technique (Open CTR)
- Incision: Longitudinal in line with ring finger, ulnar to thenar crease, 3-4cm
- Protect palmar cutaneous branch (superficial), recurrent motor branch (variable)
- Divide TCL completely: Distal to superficial arch, proximal into forearm 2cm
- Do NOT repair ligament (recreates compression)
- Do NOT perform neurolysis (increases scar, worse outcomes)
Complications
- Pillar pain: 10-20%, thenar/hypothenar ache, resolves 3-6 months
- Incomplete release: 2-5%, most common cause persistent symptoms
- Median nerve injury: 0.1-0.5%, urgent exploration if suspected
- Recurrent motor branch injury: 0.3-1%, thenar weakness
- CRPS: 1-5%, severe pain/stiffness, multidisciplinary management
Exam Favorites
- Why palmar sensation spared? Palmar cutaneous branch proximal to tunnel
- Most sensitive provocative test? Phalen's (68%); Durkan's compression is the most specific (83%)
- Thenar atrophy management? Urgent surgery, counsel incomplete motor recovery
- Most common complication? Pillar pain 10-20%, resolves 3-6 months
- NCS criteria? Motor greater than 4.5ms, sensory greater than 3.5ms
- Pregnancy CTS? Splinting first-line, usually resolves post-partum
Evidence Base
Gerritsen et al (JAMA 2002) - Splinting vs Surgery RCT
- Open carpal tunnel release vs night wrist splinting for idiopathic CTS
- General-improvement success at 3 months: 80% surgery vs 54% splinting (difference 26%, 95% CI 12-40%)
- Success at 18 months: 90% surgery vs 75% splinting (difference 15%, 95% CI 3-27%)
- By 18 months, 41% of the splint group had crossed over to surgery
Vasiliadis et al (Cochrane 2014) - Endoscopic release for CTS
- No difference from open release in symptom severity or functional status at 3 months or in the long term
- Return to work or daily activities 8 days earlier after endoscopic release (mean difference -8.10 days, 95% CI -14.28 to -1.92)
- Fewer minor complications with endoscopic release (more transient nerve problems, fewer wound problems); no difference in major complications, recurrence or reoperation
- Overall quality of evidence low, with a high risk of bias
Sayegh & Strauch (CORR 2015) - Open vs endoscopic release meta-analysis
- Similar symptom relief and Boston Carpal Tunnel Questionnaire scores
- Better early grip and pinch strength after endoscopic release, with no advantage after 6 months
- Lower risk of scar tenderness (RR 0.53) but higher risk of nerve injury (RR 2.84), mostly transient neurapraxia
- Similar risk of pillar pain and reoperation; return to work 8.7 days earlier
MacDermid & Wessel (J Hand Ther 2004) - Clinical diagnosis of CTS
- Sensitivity and specificity averaged across studies, weighted by sample size
- Phalen's test: 68% sensitivity, 73% specificity
- Tinel's sign: 50% sensitivity, 77% specificity
- Carpal compression (Durkan's) test: 64% sensitivity, 83% specificity
Marshall et al (Cochrane 2007) - Local corticosteroid injection
- 12 randomised/quasi-randomised studies, 671 participants
- Local steroid injection improved symptoms at 1 month vs placebo (RR 2.58, 95% CI 1.72-3.87)
- Significant symptom relief beyond 1 month vs placebo was not demonstrated
- Two injections gave no significant added benefit over a single injection
Hofer, Ranstam & Atroshi (JAMA Netw Open 2021) - Steroid injection 5-year RCT
- Methylprednisolone 80 mg vs 40 mg vs saline placebo, all 111 patients followed to 5 years
- No significant difference in symptom severity score between steroid and placebo at 5 years
- Subsequent surgery rate: 84% (80 mg), 92% (40 mg) and 97% (placebo)
- Steroid significantly delayed and modestly reduced eventual surgery (log-rank P=.002 for 80 mg vs placebo)
Atroshi et al (JAMA 1999) - Prevalence of CTS in a general population
- Population-based study of 2466 responders in southern Sweden
- Clinically certain CTS prevalence 3.8% (95% CI 3.1-4.6%)
- Electrophysiologically confirmed median neuropathy 4.9% (95% CI 4.1-5.8%)
- Clinically AND electrophysiologically confirmed CTS 2.7% (95% CI 2.1-3.4%)
Padua et al (Ital J Neurol Sci 1997) - Neurophysiological classification
- 600 clinically symptomatic hands graded purely on median nerve electrodiagnostics
- Six classes: negative, minimal, mild, moderate, severe, extreme
- Distribution: extreme 3%, severe 14%, moderate 36%, mild 24%, minimal 21%, negative 3%
- Advanced (severe/extreme) classes concentrated in older patients; milder classes in younger women
Bland (Muscle Nerve 2001) - NCS as a predictor of surgical outcome
- 1268 carpal tunnel decompressions assessed by postal questionnaire
- Overall self-reported surgical success rate 69%
- Greater age, lower symptom scores, longer duration and male sex predicted poorer outcome
- Middle-grade NCS abnormality had better outcomes than either very severe or normal studies