Anatomy, predicted growth, foot function and lifetime mobility planning
- Do not reduce congenital limb deficiency to centimetres; hip, knee, ankle, foot, soft tissue and prosthetic function change the plan.
- Congenital femoral deficiency requires assessment of proximal femur, hip stability, knee stability, predicted LLD and possible prosthetic or rotationplasty pathways.
- Fibular hemimelia is a postaxial deficiency; foot rays, ankle valgus, subtalar coalition, knee valgus and knee ligament deficiency are central.
- Tibial hemimelia is rare and often severe; knee extension mechanism, foot support and reconstructability determine whether salvage is realistic.
- Lengthening must be staged around joint stability, nerve stretch, regenerate quality, family burden and rehabilitation capacity.
- Amputation or rotationplasty can be planned functional reconstruction, not failure, when anatomy makes limb preservation a poor mobility strategy.
- “A longer limb with an unstable knee or non-plantigrade foot may function worse than a shorter limb with a good prosthesis.
- “Foot height contributes to total discrepancy and should be included in prediction.
- “A plantigrade, painless, shoeable foot is a prerequisite for many reconstruction pathways.
- “Knee cruciate deficiency may be asymptomatic in a small child but problematic during growth and lengthening.
- “The family needs neutral comparison of burden, risks and expected mobility for each pathway.
Overview and Epidemiology
Congenital lower limb deficiency includes a spectrum of femoral, fibular, tibial and foot deficiencies. The child may present at birth with an obvious short limb, missing rays or a foot deformity, or later, when gait asymmetry, shoe wear, brace difficulty or limb length discrepancy becomes apparent.
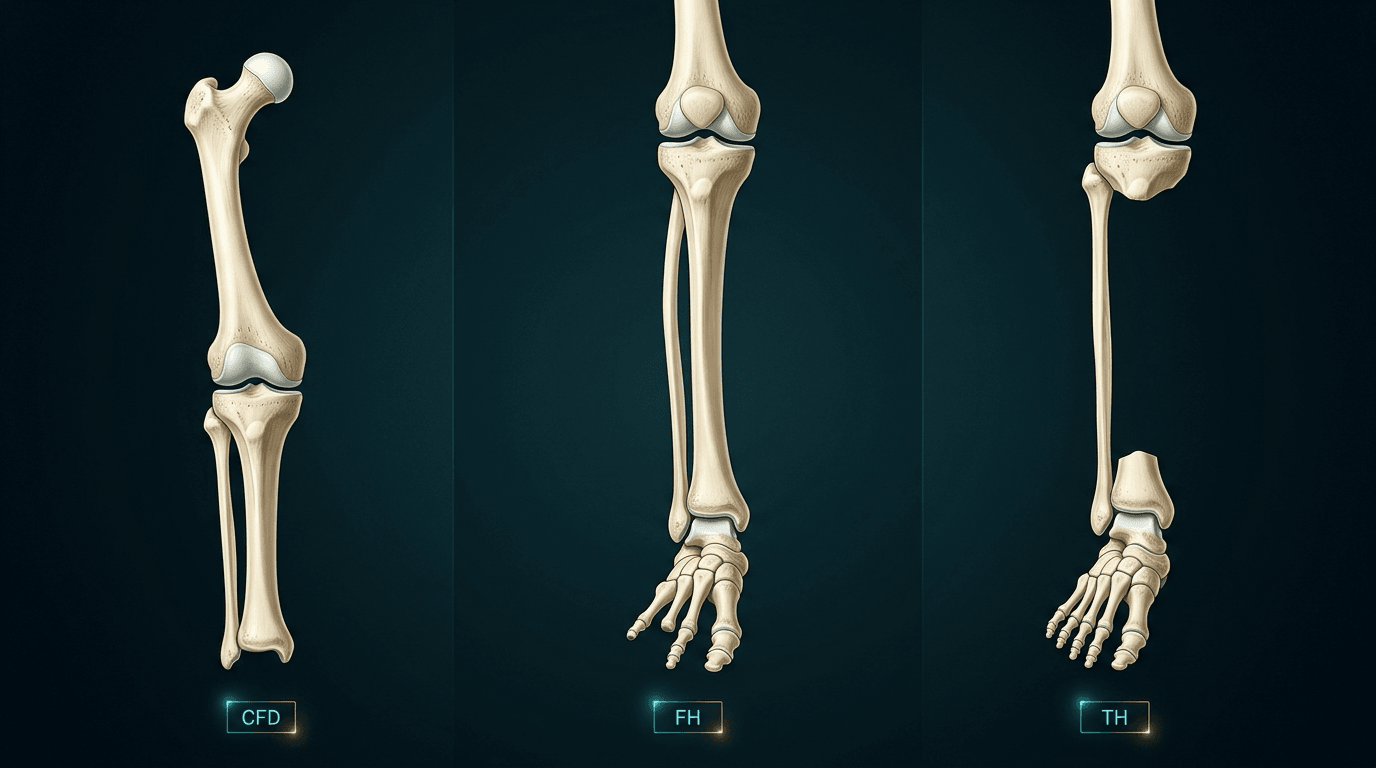
The real question. The visible discrepancy is only the surface problem. Length prediction is essential, but it is only one part of decision-making; the real decision is whether the limb can become a stable, pain-free, efficient lever for walking, and a safe plan proves that each of the following can tolerate the pathway:
- Hip: contained, mobile and able to support the pelvis. An unstable proximal femur or poor abductor function may limit reconstruction.
- Knee: stable, mobile and controllable in stance. Cruciate deficiency, valgus or extensor deficiency can make lengthening unsafe.
- Foot and ankle: plantigrade, shoeable or prosthesis-friendly. A non-reconstructable foot may make prosthetic care more functional than repeated salvage.
- Soft tissues: skin, vessels, nerves and muscles that can tolerate treatment. Nerve stretch, contracture and regenerate problems increase during lengthening.
- Family pathway: a child and family who can complete staged care and rehabilitation. A technically possible pathway may still be the wrong burden.
Pathophysiology
Formation, not injury. The deficiency pattern reflects abnormal limb formation rather than a postnatal injury. Each diagnosis is a whole-limb pattern, not a single missing bone.
Growth. Limb length discrepancy commonly increases proportionally with growth. Femoral shortening, tibial shortening and reduced foot height all add to the final difference, so the segment contribution matters as much as the total. The child also adapts as growth progresses: a ball-and-socket ankle, pelvic obliquity, compensatory equinus, shoe lifts, brace reliance and an altered gait may all appear.
Why lengthening is different here. The lengthening biology is also abnormal. Short soft tissues, altered nerves and vessels, deficient muscles and unstable joints make repeated lengthening more hazardous than ordinary limb equalisation, which is why reconstruction planning starts with stability and foot function before the amount to lengthen.
Classification
Classifications are useful only if they guide treatment. For congenital femoral deficiency they describe proximal femoral anatomy and reconstructability. For fibular hemimelia the older systems described fibular absence, but modern treatment planning places more weight on foot and ankle deformity, rays, coalition and stability. For tibial hemimelia they describe the amount of tibia present and knee or ankle reconstructability.
Congenital femoral deficiency: Aitken and Paley
The classic classification of congenital femoral deficiency (proximal focal femoral deficiency, PFFD) is the Aitken classification, based on the presence of the femoral head and the femoral segment, and it directly predicts hip stability and reconstructability:
- Aitken A: femoral head present with an adequate acetabulum; a short femur with a subtrochanteric defect that ossifies and unites. The most reconstructable pattern, with a stable hip.
- Aitken B: femoral head present but the acetabulum more dysplastic, with a pseudarthrosis between the head and the short femoral shaft that does not unite (a tuft of bone on the proximal shaft).
- Aitken C: femoral head absent or only a small ossific tuft, with a severely dysplastic acetabulum and no connection between head and shaft.
- Aitken D: both the femoral head and the acetabulum absent. The most severe pattern, with no hip joint.
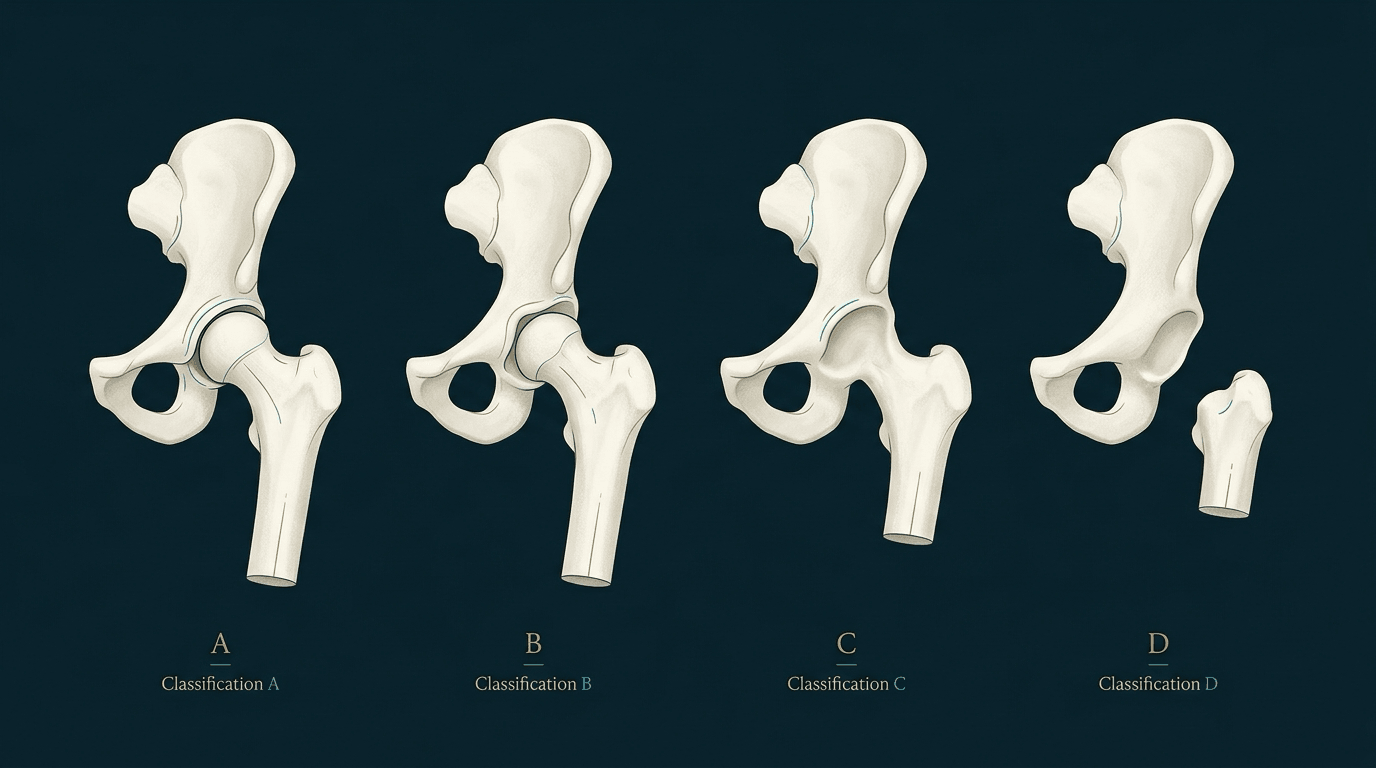
The modern Paley classification of CFD refines this around what can be reconstructed: Type 1 is an intact femur with a mobile, stable hip and knee, Type 2 a mobile pseudarthrosis, and Type 3 a diaphyseal deficiency. It guides the lengthening-versus-prosthetic decision.
A present, stable femoral head and acetabulum (Aitken A / Paley 1) is the prerequisite for lengthening reconstruction, whereas an absent head or acetabulum (Aitken C/D) pushes toward a prosthetic or rotationplasty pathway.
Fibular deficiency: Achterman-Kalamchi, and why it is no longer enough
The Achterman-Kalamchi classification was derived from 97 limbs in 81 patients:
- Type I: the fibula is present but hypoplastic. In Type IA the proximal fibular epiphysis lies distal to the proximal tibial physis and the distal fibular physis lies proximal to the talar dome; in Type IB 30 to 50 percent of the fibula is missing, and the distal fibula fails to support the ankle.
- Type II: the fibula is completely absent, usually with a fibrous anlage running in its place.
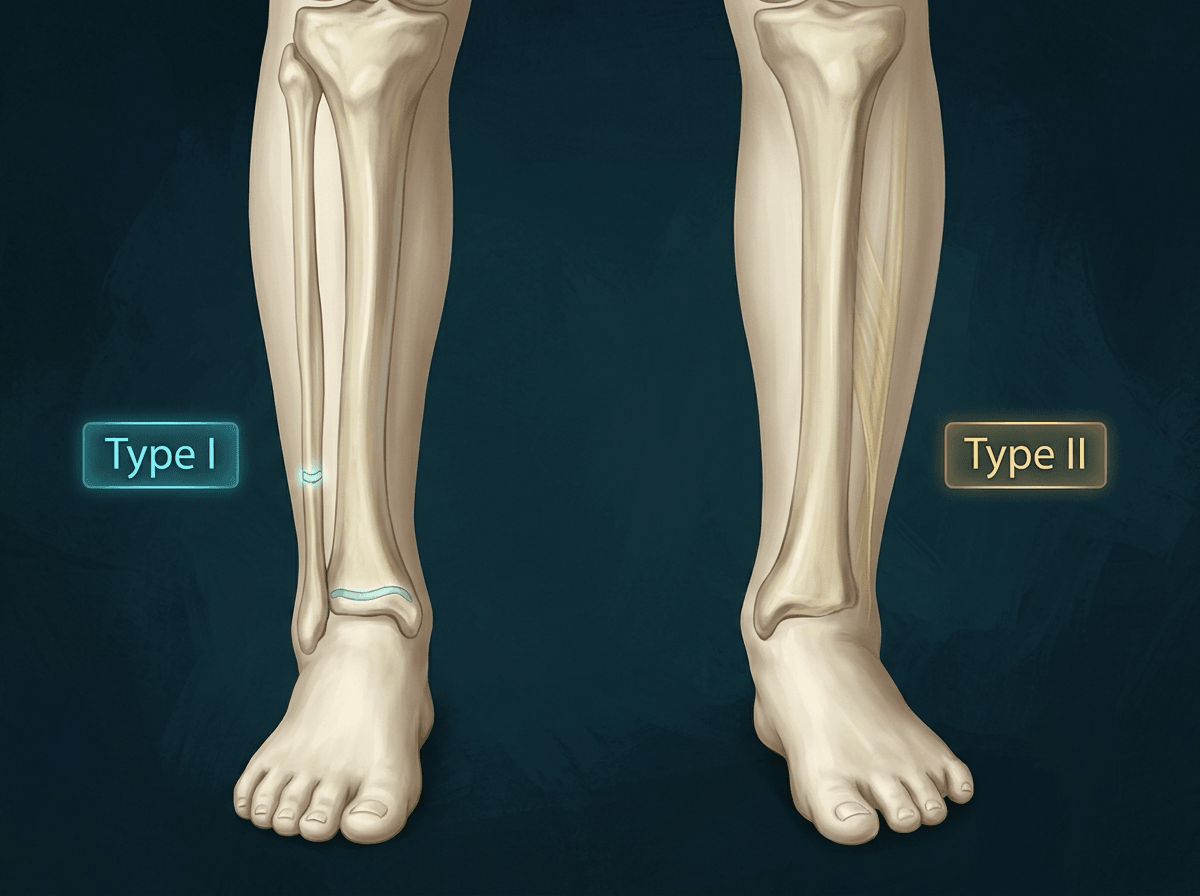
Two findings that cut against intuition. Femoral anomalies are commoner in the milder type, not the severer one: 76 percent in Type I against 59 percent in Type II. A modest-looking fibula therefore buys no reassurance about the femur, so image the whole limb in every case rather than reserving femoral assessment for complete absence.
Percentage shortening was fairly constant through growth, roughly 13 percent of limb length in Type I and 19 percent in Type II. This is the single most useful planning fact on the topic, because it means the discrepancy can be projected from one early measurement rather than waiting years for a trend.
Why Paley grades the ankle instead. The limitation of the classification is that it grades the bone that matters least to the decision. Reconstruction fails because of residual or recurrent foot deformity, not because of how much fibula is missing, so Paley's classification grades the ankle joint and matches a named procedure to each pattern:
- Type 1: a stable ankle.
- Type 2: dynamic valgus. A hypoplastic distal fibula with an ankle that deviates under load but is not fixed is addressed by the SHORDT procedure, shortening and realigning the distal tibia relative to the fibula.
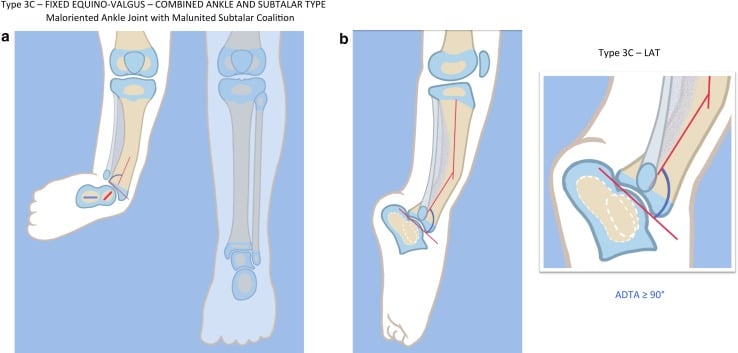
- Type 3: fixed equinovalgus (3A ankle, 3B subtalar, 3C combined). A fixed equinovalgus foot requires the SUPERankle procedure: a supramalleolar shortening-realignment osteotomy, with subtalar osteotomies and resection of the fibular anlage as needed.
- Type 4: fixed equinovarus.
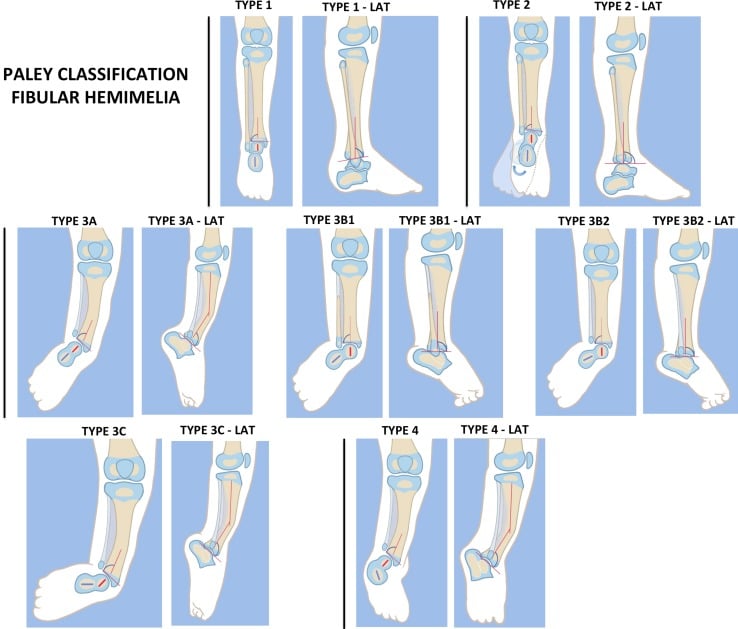
Both procedures correct through bone rather than soft tissue, which is what prevents recurrence, and shortening the tibia rather than lengthening tendons preserves gastro-soleus and peroneal power. Reconstruction advocates report that where a plantigrade, painless foot is achieved and serial lengthening follows, function compares well with a Syme amputation and prosthesis. How that claim sits against the pooled evidence is taken up under Controversies below.
Tibial deficiency: the Jones classification, and the one question it answers
Tibial deficiency is graded by the Jones, Barnes and Lloyd-Roberts classification. It is worth knowing precisely, because the type determines whether a knee can be built at all, and the decisive distinction, between Type 1a and Type 1b, is invisible on a plain radiograph in an infant.
- What is present
- No tibia visible; no cartilaginous anlage. Quadriceps mechanism absent or inadequate.
- The radiographic clue
- Hypoplastic, narrow distal femoral epiphysis - the femur has never been loaded through a tibia.
- Usual pathway
- Knee disarticulation and prosthetic fitting.
- What is present
- No tibia visible on radiograph, but a cartilaginous proximal tibial anlage IS present, with a functioning extensor mechanism.
- The radiographic clue
- Distal femoral epiphysis is NORMAL in size. Ultrasound or MRI demonstrates the unossified anlage.
- Usual pathway
- Potentially reconstructable: tibiofibular synostosis or fibular transfer with a Syme or Boyd ankle.
- What is present
- Proximal tibia present and ossified; distal tibia absent. Knee extension present.
- The radiographic clue
- Proximal tibial ossification with the fibula riding proximally.
- Usual pathway
- Tibiofibular synostosis to the proximal tibia, with Syme or Boyd amputation distally.
- What is present
- Distal tibia present, proximal tibia absent. Very rare.
- The radiographic clue
- Reverse pattern - ossified distal tibia with no proximal segment.
- Usual pathway
- Individualised; knee is the problem, not the ankle.
- What is present
- Distal tibiofibular diastasis - the tibia is shortened and the fibula migrates proximally, with the foot held in severe varus.
- The radiographic clue
- Widened distal tibiofibular interval with proximal fibular migration.
- Usual pathway
- Distal tibiofibular synostosis, or Syme amputation if the foot cannot be brought under the leg.
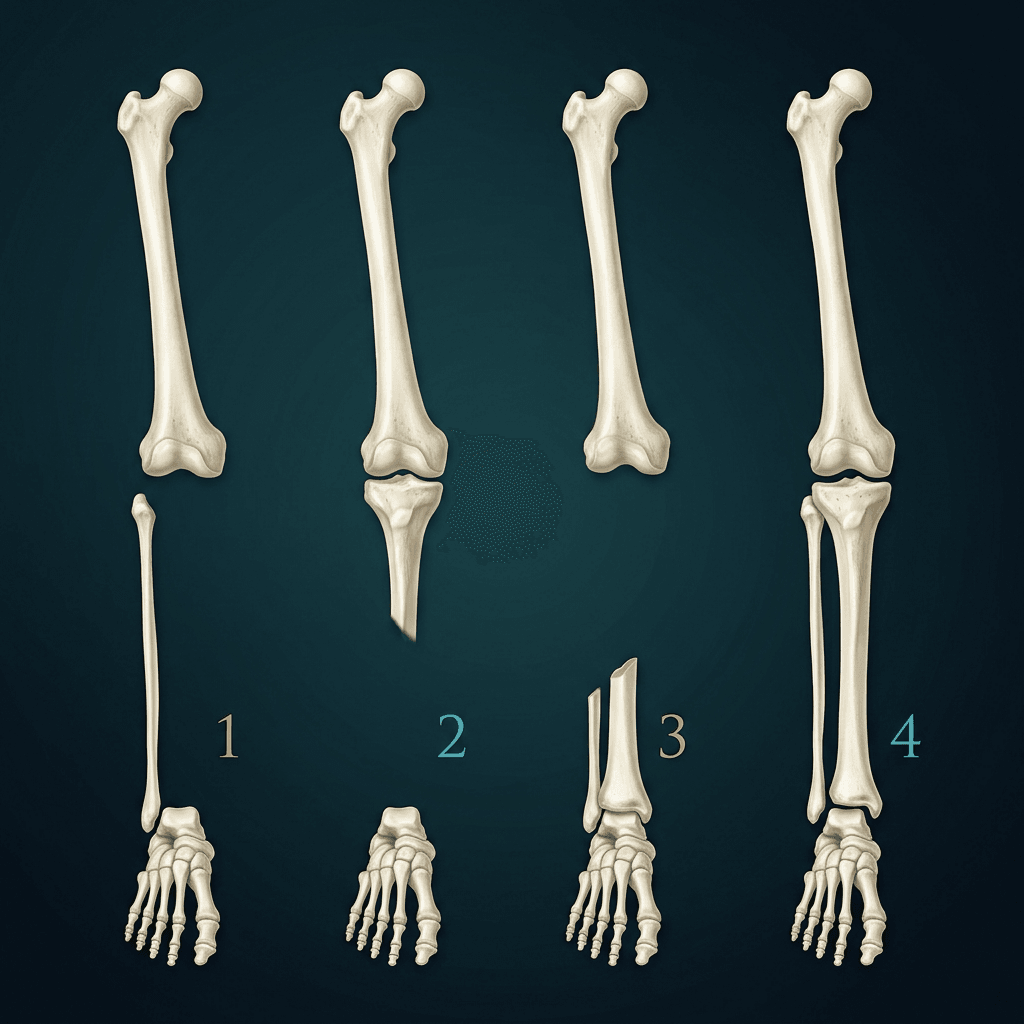
The 1a/1b distinction is the examinable one, and it is the reason you image before you decide. Both look like an absent tibia on a plain film of an infant. The size of the distal femoral epiphysis is the free clue on that same radiograph, hypoplastic in 1a and normal in 1b, and ultrasound or MRI then confirms whether a cartilaginous anlage exists. Getting this wrong in either direction is costly: a 1b disarticulated has lost a reconstructable knee, while a 1a offered reconstruction faces repeated surgery on a knee that was never going to extend.
Whatever the type, the functional question comes before the anatomical one: is there active knee extension? A tibia that can be reconstructed is of no use beneath a quadriceps that cannot work it, and this is why the examination finding of active knee extension carries more weight in tibial deficiency than any single radiographic feature.
Clinical Presentation
History. Ask what changes the pathway. Five domains do:
- Diagnosis and associations: how it was recognised, prenatal imaging, other limb findings and systemic anomalies, which define whether this is isolated or part of a broader syndrome.
- Function: crawling, standing, walking distance, stairs, running, sport, falls, pain and fatigue, which determine whether the current limb is useful and what must improve.
- Devices and skin: braces, prostheses, sockets, shoe raises, pressure areas and skin breakdown, which show whether orthotic or prosthetic care is succeeding.
- Previous treatment: casts, foot reconstruction, lengthening, epiphysiodesis, amputation, revision surgery and psychological impact, which identify scars, expectations and remaining options.
- Family and child priorities: limb preservation, fewer operations, sport, shoe wear, appearance, independence and predictable mobility, which make counselling honest rather than surgeon-centred.
Examination. Examine from pelvis to toes, then watch gait with and without the orthosis or prosthesis. Each level informs a different decision:
- Pelvis and hip: pelvic balance, hip abduction, flexion, containment and Trendelenburg, which decide whether the limb can support walking and lengthening.
- Femur and knee: femoral length, knee range, valgus, sagittal stability, patellar tracking and the extensor mechanism, which decide whether the knee is safe for reconstruction or prosthetic control.
- Tibia, ankle and foot: tibial bowing, ankle valgus or equinus, subtalar motion, rays, width, callosities and shoeability, which decide whether the foot is reconstructable, braceable or prosthesis-friendly.
- Length contribution: the femur, tibia and foot height measured separately, which prevents treating a total discrepancy without knowing the segment.
- Soft tissue and devices: skin, scars, sockets, pressure areas and tolerance, which predict complication risk and the practical burden of the pathway.
LIMBAssessment
Hook:LIMB keeps the assessment broader than centimetres.
Investigations
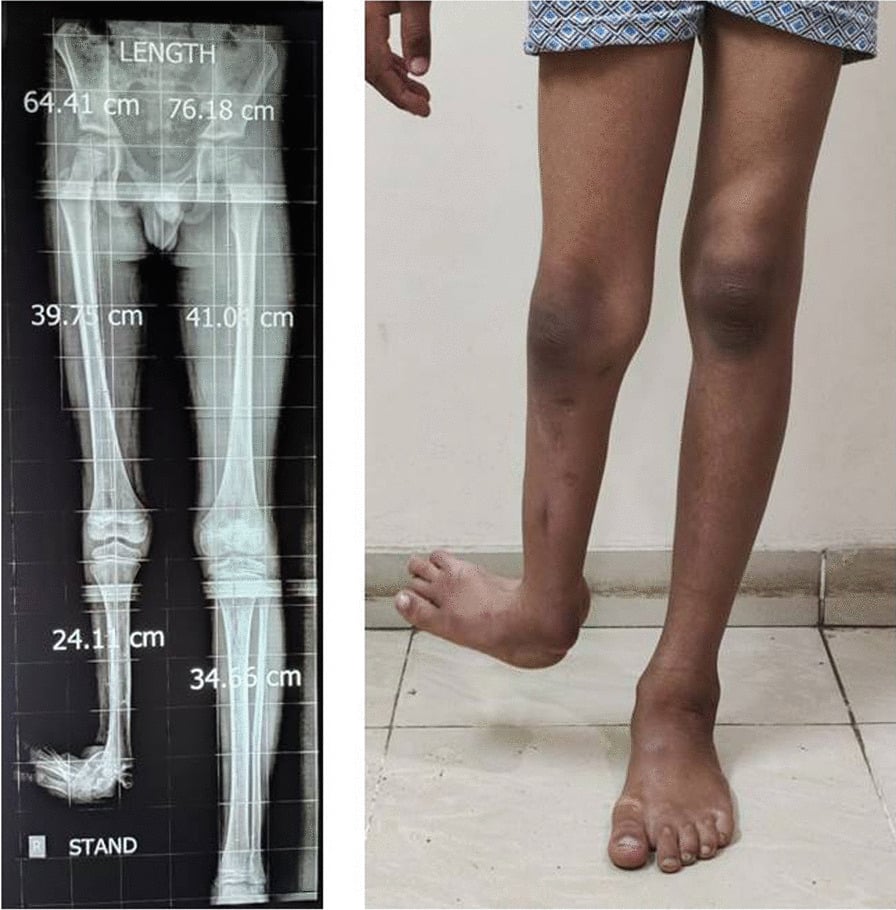
Radiographs. Radiographs should answer treatment questions. Full-length calibrated standing films, with an appropriate block under the short limb when possible, help measure segment lengths, mechanical axis and pelvic balance, and dedicated hip, knee, ankle and foot radiographs define reconstructability. In younger children, cartilage and unossified structures may limit plain film interpretation.
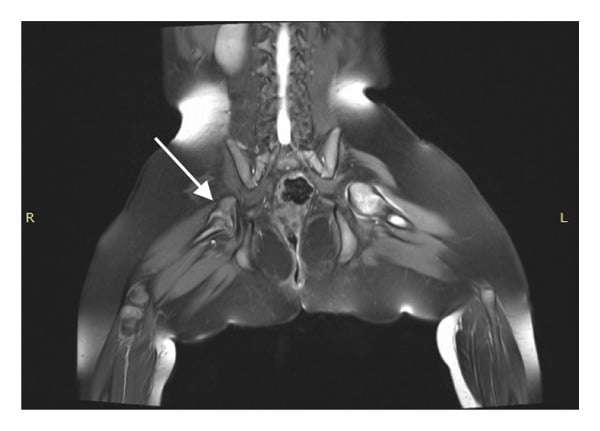
MRI and CT. MRI is useful in selected cases: hip cartilage, knee cruciate absence, the fibular anlage, subtalar coalition, and soft tissue and vascular anomalies can all change reconstruction planning. CT may help complex foot and ankle or rotational planning but should be used selectively.
How the prediction is made
Naming three methods is not a plan; a viva will ask which one and why.
The multiplier method is the one to reach for in congenital deficiency, and the reason is specific to this group of conditions. In a congenital deficiency the short limb grows at a fixed proportion of the long limb, so the discrepancy expressed as a percentage of limb length stays essentially constant throughout growth, the ratio Achterman and Kalamchi measured directly. Because the ratio does not drift, a single reliable measurement at almost any age can be multiplied by an age-and-sex-specific factor to give the discrepancy at maturity. There is no need to accumulate years of serial films before committing to a strategy, which matters when the decision in front of you is whether an infant is heading for a Syme amputation or a reconstruction programme.
The two older methods. They answer a slightly different question and remain useful. The Green-Anderson growth-remaining charts estimate how much growth is left in each physis, which is what you need when timing an epiphysiodesis rather than predicting a congenital ratio. The Moseley straight-line graph plots serial measurements against skeletal age and converts the growth curves into straight lines, so a deviation from the line signals that growth is not behaving as assumed; it needs several measurements over time, which is precisely what the multiplier method avoids, but it is the better tool where growth may not be proportional, such as an acquired arrest after trauma, sepsis or a physeal bar.
Two arithmetic anchors worth carrying. Around the knee the distal femoral physis contributes roughly 9 to 10 mm of growth per year and the proximal tibial physis roughly 6 mm, so an epiphysiodesis at the knee removes on the order of 16 mm per remaining year. Getting the timing wrong by a year therefore costs more than a centimetre, in either direction.
From prediction to pathway
What the prediction has to answer. Serial calibrated lengths with the femur, tibia and foot height measured separately give the total discrepancy without underestimating the real functional deficit. The projected discrepancy at maturity, divided into safe staged gains after joint and foot preparation, gives the number of lengthenings, and large predicted discrepancies may make prosthetic or amputation pathways more predictable. Clinical and imaging assessment of hip containment, knee stability, ankle and foot position and the soft-tissue envelope decides whether the joints can tolerate lengthening; unstable joints or a non-plantigrade foot should be corrected first, or may redirect the pathway. The practical pathway is then settled at multidisciplinary review with limb reconstruction, prosthetics, therapy and family counselling, comparing complete pathways rather than isolated procedures.
Discrepancy bands. These are planning conventions rather than rules, and in congenital deficiency joint stability and foot function override them, but a candidate should be able to state them.
- Usual strategy
- No treatment, or a shoe raise for comfort.
- The caveat that changes it
- Rarely symptomatic; treat the child, not the number.
- Usual strategy
- Well-timed epiphysiodesis of the longer limb, or a shoe raise.
- The caveat that changes it
- Requires accurate skeletal age and remaining growth; shortens the normal limb, which some families decline.
- Usual strategy
- Staged lengthening, usually combined with epiphysiodesis, after the foot and joints have been made safe.
- The caveat that changes it
- Each stage carries real complication risk; an unstable hip or knee or a non-plantigrade foot must be corrected first or the pathway changes.
- Usual strategy
- Prosthetic pathway, with amputation or rotationplasty planned as reconstruction.
- The caveat that changes it
- The number of lengthenings needed becomes a decade-long programme with cumulative risk.
Do not forget foot height. The heel-to-floor contribution is part of the functional discrepancy and is easily omitted when segment lengths are measured off a radiograph, yet it is what the shoe raise or the prosthetic foot actually has to make up.
Major Conditions
Congenital femoral deficiency. The findings that matter are femoral shortening, the proximal femoral abnormality, hip containment, abductor function, knee level and stability, projected length, pelvic support and the prosthetic implications; it often coexists with fibular hemimelia. Hip containment and predicted femoral length, not the tibia, set lengthening versus prosthetic strategy, because a short stable femur is a different problem from an absent proximal femur with an unstable hip. Stable mild patterns may suit staged lengthening once hip stability is confirmed; severe unstable patterns may need a prosthetic strategy, rotationplasty or other reconstruction. Bilateral disease changes the counselling: there is no normal contralateral limb to equalise against, and prosthetic or rotationplasty logic is applied to function rather than to matching a normal side.
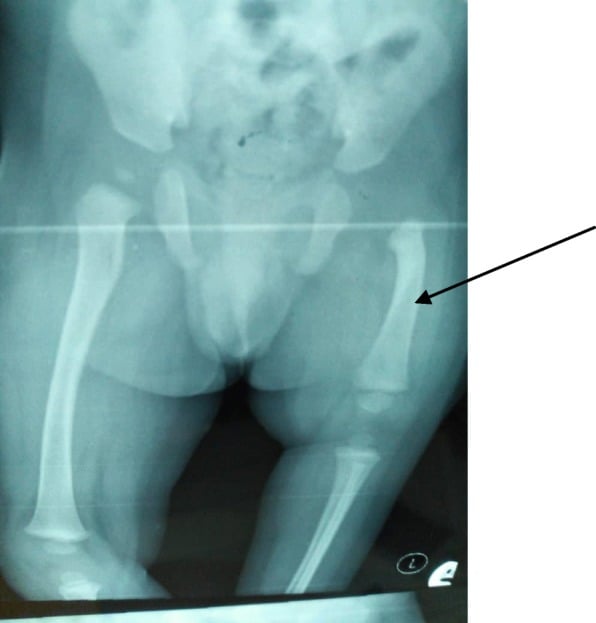
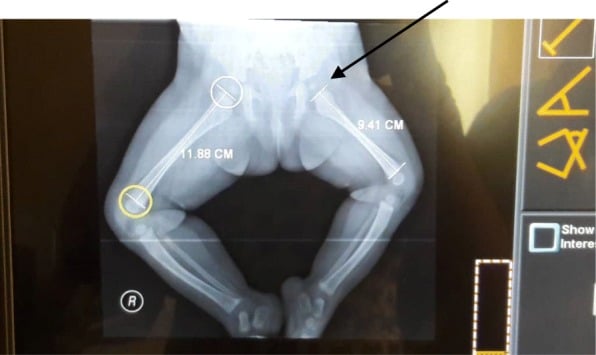
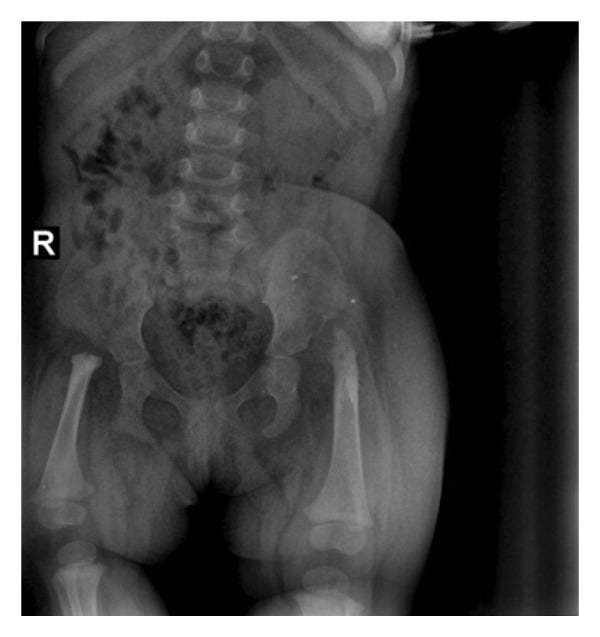
Fibular hemimelia. The findings are limb length discrepancy, partial or complete fibular deficiency, absent or hypoplastic lateral rays, ankle valgus, equinovalgus or a ball-and-socket ankle, tarsal coalition, tibial bowing, knee valgus and cruciate deficiency, and possible femoral involvement. Foot and ankle reconstructability is usually the pathway-defining issue: a stable plantigrade foot supports reconstruction, whereas a severely deficient, non-shoeable foot may do better with a prosthetic pathway. The family's willingness for staged lengthening is part of the same decision.
Tibial hemimelia. Rare and often severe. The findings are a partial or absent tibia, knee flexion contracture, a deficient extensor mechanism, ankle instability and a varus foot deformity, and the condition may be familial or syndromic. Knee extensor function and tibial presence determine salvage versus amputation: reconstruction is possible in selected specialist settings, but amputation remains appropriate for many severe patterns, and if the knee-foot unit cannot become useful a prosthetic strategy may be safer.
Mixed deficiencies. Combined femoral, fibular, tibial or foot involvement requires individualised multidisciplinary life planning. Sequence treatment so that hip, knee and foot stability are secured before lengthening exposes another weak level.
Differential Diagnosis
A short or deformed lower limb in a child is not always a longitudinal deficiency. The task is to separate true congenital segmental deficiency from bowing, dysplasia, constriction and acquired growth arrest, because each has a different natural history and a different treatment pathway.
- Discriminating features
- Short abnormal femur, proximal femoral abnormality, variable hip and knee instability, often with coexisting fibular hemimelia.
- Why it changes the plan
- Hip and knee stability decide whether lengthening, prosthetic fitting or rotationplasty is realistic.
- Discriminating features
- Lateral (postaxial) deficiency, absent lateral rays, ankle valgus or ball-and-socket ankle, tarsal coalition, knee valgus and cruciate deficiency.
- Why it changes the plan
- Foot and ankle reconstructability is usually the pathway-defining issue.
- Discriminating features
- Medial (preaxial) deficiency, knee flexion contracture, deficient extensor mechanism, varus foot; may be familial or syndromic.
- Why it changes the plan
- Knee extensor function and tibial presence determine salvage versus amputation.
- Discriminating features
- Calcaneovalgus foot at birth, apex posteromedial bow that remodels, but predictable residual limb length discrepancy.
- Why it changes the plan
- Bowing largely corrects; the management issue is the discrepancy, not deficiency.
- Discriminating features
- Apex anterolateral bow, narrowed sclerotic canal, association with neurofibromatosis type 1.
- Why it changes the plan
- High fracture and non-union risk; must not be confused with benign posteromedial bowing.
- Discriminating features
- Circumferential skin grooves, distal transverse loss, asymmetric and non-genetic with normal proximal anatomy.
- Why it changes the plan
- Distal transverse pattern rather than longitudinal deficiency; soft-tissue and prosthetic focus.
- Discriminating features
- Disproportionate shortening, other dysmorphic features, family history or genetic diagnosis.
- Why it changes the plan
- Systemic condition needing geneticist input, not isolated limb reconstruction.
- Discriminating features
- Previously normal limb, physeal scar or bar, history of injury, sepsis or surgery.
- Why it changes the plan
- Targeted at the arrested physis (bar resection, epiphysiodesis, lengthening), not congenital reconstruction.
Management Principles
The first step is not surgery. It is to explain the diagnosis, establish current function, predict future discrepancy and compare realistic pathways. Each stage should preserve the next option, because this is growth-long care rather than a single operation.
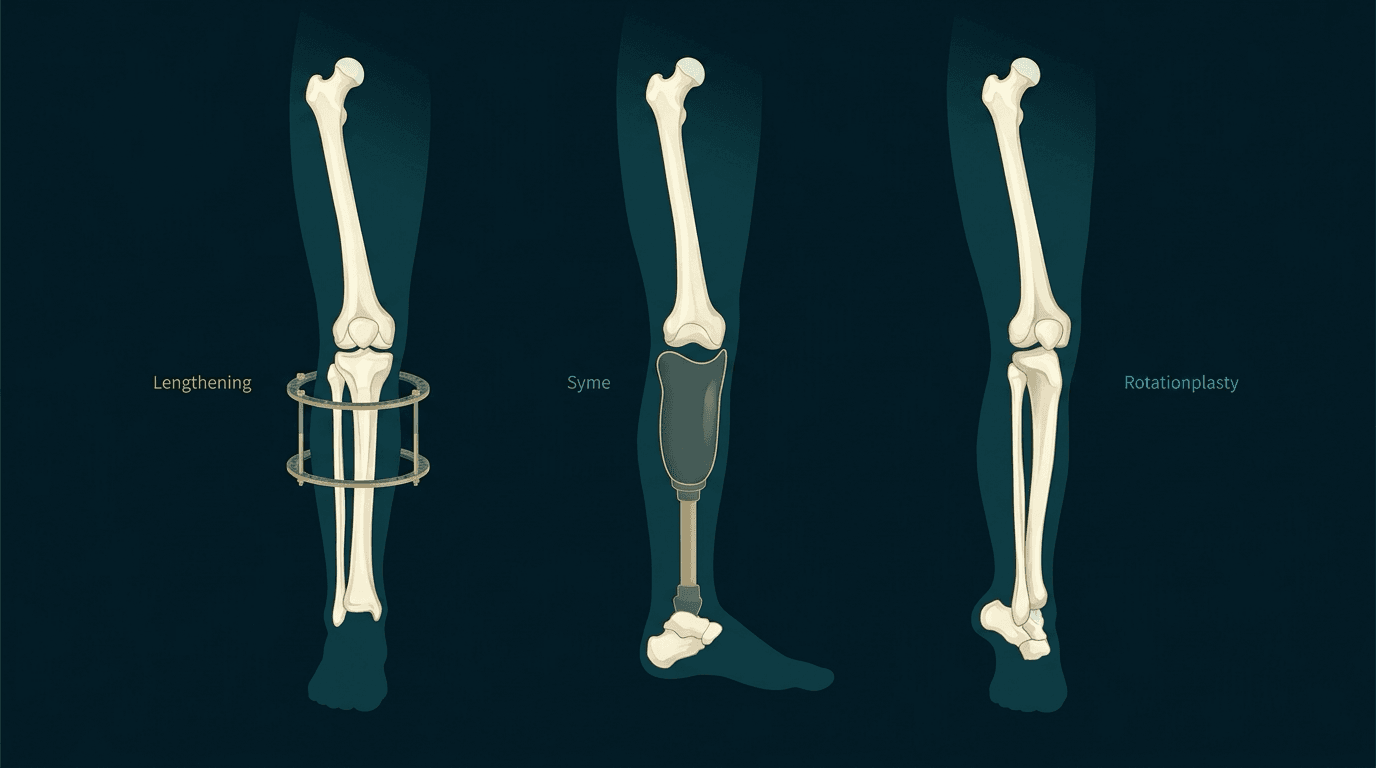
Support and surveillance. Mild discrepancy or stable function may be managed with monitoring, a shoe lift, orthosis, physiotherapy, prosthetic review or delayed equalisation, with the prediction updated through growth. This is the right pathway for a mild discrepancy, stable function, a young child or an uncertain final pathway.
Reconstruction. Reconstruction usually requires a sequence: make the foot plantigrade and shoeable, protect or reconstruct the joints, correct alignment, then lengthen safely, with intensive rehabilitation throughout. Epiphysiodesis of the longer limb may reduce the number or amount of lengthening procedures. It makes sense where the joints and foot are reconstructable, the treatment burden is acceptable and the functional gain is clear.
Prosthetic or amputation pathway. Syme or Boyd amputation can create a durable end-bearing limb for prosthetic fitting in selected severe fibular or tibial deficiencies, and rotationplasty may be considered in severe femoral deficiency when hip and femur anatomy make ordinary reconstruction poor. It makes sense where the foot or joints are non-reconstructable, or when predictable mobility is better than repeated salvage.
Hybrid plan. Some children need a combination: an orthosis during early walking, limited reconstruction to improve alignment, later lengthening or epiphysiodesis, and ongoing prosthetic or bracing support. This suits the child who has useful anatomy but still needs long-term device support.
The salvage procedures: Syme, Boyd and Van Nes rotationplasty
Syme amputation. An ankle disarticulation through the malleoli that removes the entire foot including the calcaneus, leaving an end-bearing stump capped by the durable heel pad sutured over the distal tibia. Simple and durable, but the heel pad can migrate and the stump is bulbous.
Boyd amputation. A calcaneotibial fusion: the talus is removed but the calcaneus is preserved and fused to the distal tibia, giving a longer, more robust end-bearing stump and anchoring the heel pad so it cannot migrate, which is its advantage over Syme. It requires the fusion to heal and leaves a slightly longer limb, which is relevant in a growing child.
Van Nes rotationplasty. For severe femoral deficiency, the limb is rotated 180 degrees so the ankle becomes a "knee": active plantarflexion now extends the prosthetic shank and dorsiflexion flexes it, converting an above-knee amputee into the functional equivalent of a below-knee amputee with far better gait efficiency. The trade-off is the obvious cosmetic and psychosocial impact of a backward-facing foot, which must be discussed and is the main barrier to acceptance.
Why all three are disarticulations or fusions rather than a cut across a long bone. In a growing child, a transdiaphyseal amputation is liable to terminal bony overgrowth: the cut end of the diaphysis continues to lay down bone appositionally, and because that new bone is not capped by a physis or an epiphysis it advances as a spike into the soft tissues. It causes a painful, tender stump, bursa formation and eventually skin penetration, and it recurs after excision until skeletal maturity, so a child may face repeated stump revisions purely to manage it. Disarticulation removes the risk because the joint surface and its cartilage cap remain, which is why a Syme or Boyd is preferred over a below-knee amputation in this population even though a below-knee stump would be shorter to fit.
The unifying principle: amputation or rotationplasty is planned functional reconstruction that creates a stable, end-bearing, prosthesis-ready limb, not a failure of reconstruction, when it gives earlier, safer, more predictable mobility.
Lengthening and Reconstruction Risks
Not a passive increase in bone length. Lengthening can be highly effective in selected children, but it stresses bone, joints, muscle, nerve, vessel, skin and family life. The major preventable errors are lengthening before joint stability is secured, ignoring foot deformity, underestimating soft-tissue tightness, and failing to plan rehabilitation.
Protect the knee. Congenital knees are often cruciate-deficient, and a tibial-only frame lengthens the tibia off the femur. Span the knee, or reconstruct the ACL in the same programme, so the joint stays reduced; anterior subluxation is a planning failure, not bad luck.
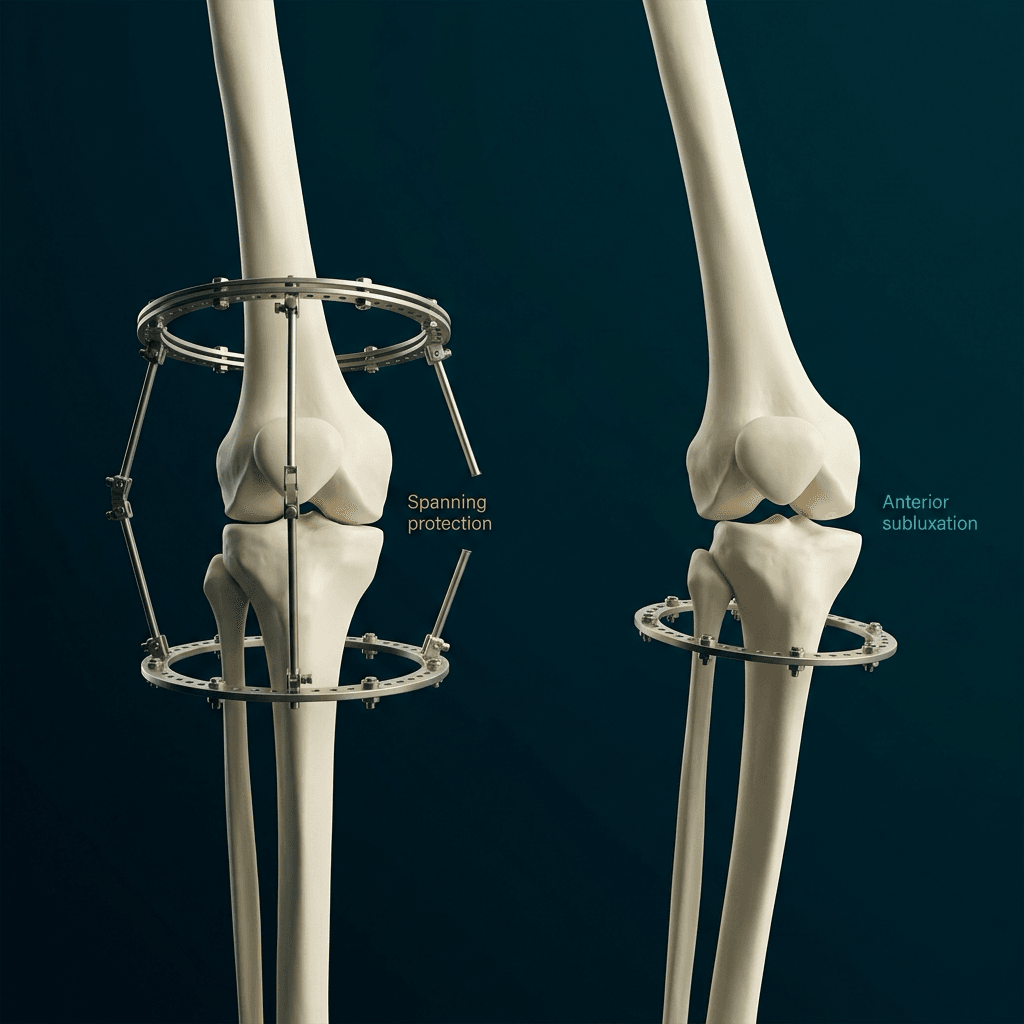
How much per stage. Cohort data link larger lengthening, over 6 cm or 25 percent of the segment, to worse pain and comfort scores, supporting conservative staged gains. The timing debate, aggressive early equalisation against staged lengthening closer to maturity with epiphysiodesis, turns on the same facts: larger predicted discrepancies and unstable joints push toward fewer lengthenings or a prosthetic strategy, and complication risk rises with the magnitude per stage.
Complications
Left alone. The natural history is one of increasing limb length discrepancy, progressive gait asymmetry and pelvic obliquity, foot and ankle deformity limiting shoe wear, knee valgus or instability, and pain, fatigue, falls and reduced activity.
With treatment. Each risk area carries its own complications, and the counselling point that goes with it:
- Complications
- Poor regenerate, delayed union, fracture and recurrent deformity.
- Counselling point
- Lengthening requires repeated imaging and may need rate changes or revision.
- Complications
- Hip, knee or ankle subluxation, stiffness, contracture and nerve stretch symptoms or palsy.
- Counselling point
- Joint protection and therapy are as important as the bone length.
- Complications
- Pin-site or deep infection, hardware irritation, device problems and further surgery.
- Counselling point
- Device care and follow-up are part of the treatment.
- Complications
- Socket and skin problems after prosthetic fitting, and revision surgery through growth.
- Counselling point
- Socket fitting and revisions through growth are part of the pathway.
- Complications
- Pain, school disruption, psychological fatigue and treatment abandonment.
- Counselling point
- The likely number of procedures and rehabilitation load must be discussed before starting.
Counselling and Follow-up
Neutral and specific. Families should hear that reconstruction and prosthetic care can both be excellent when matched to anatomy. Avoid framing amputation as giving up or reconstruction as automatically superior, and discuss what the child is likely to experience: number of operations, therapy, pain, device time, school disruption, sport participation, prosthetic revisions, cosmesis and psychological support.
Follow-up updates the plan. Each review should update prediction, function and goals. A plan made in infancy may change when foot deformity, knee instability, child preference, family capacity or technology changes, and the child should increasingly participate in decisions as they mature.
Saying it in words a parent will hear
"Neutral counselling" is easy to assert and hard to do, and an examiner in a clinical station will ask you to actually say it. Three things reliably help.
Name the decision as being about function, not about keeping or losing a limb. A parent hears "amputation" as loss and "reconstruction" as repair, and that framing decides the conversation before any evidence is heard. It helps to say plainly that both routes end with the child walking, and that the question is which route gets there with the fewest operations and the most reliable foot, something like: "Both of these paths are ways of building your child a leg that works. One builds it from the foot she has; the other builds it from a prosthesis. Neither is giving up."
Give the burden as a number, because families can weigh a number. "On average, children who have the reconstruction have about four operations; children who have the amputation have about one or two. Complications are around six times more common with reconstruction." That is more use than "reconstruction is demanding", and it is the information families later say they wanted.
Say out loud what you do not yet know. In infancy the foot has not declared itself and the discrepancy prediction still carries error. Committing to a pathway on the day of diagnosis is rarely necessary, and saying "we do not have to decide this today, and here is what we are watching for" removes pressure without withholding anything.
Two further points belong in the same conversation. Where a rotationplasty is on the table, the backward-facing foot has to be described in advance and, if possible, shown; families who meet the operation only as a diagram are far less likely to accept it, and the objection is cosmetic rather than functional. And where amputation is chosen in infancy, it is worth saying that children who grow up with it generally regard it as how their leg has always been, rather than as something taken from them.
Decision-Making in Practice
Congenital lower-limb deficiency management is a lifetime mobility plan. The clinical decision is not reconstruction versus amputation in the abstract; it is which pathway gives the child a plantigrade, braceable or prosthesis-friendly limb with the least morbidity and the best function over growth. A stable knee is central to walking and to prosthetic control, lengthening is a programme rather than a single operation, and shared decision-making is essential because both paths are demanding.
Clinical Reasoning Notes
Structured clinical approach
Start with age, side, ambulatory status and the condition pattern. Describe each anatomical level: pelvis and hip, femur, knee, tibia and fibula, ankle, foot rays and skin. State the current and predicted discrepancy, foot reconstructability, joint stability and the family's goals, then present a neutral pathway comparison.
Common pitfalls
- Planning from the current centimetre discrepancy alone.
- Forgetting the foot-height contribution to total LLD.
- Lengthening above an unstable hip, knee or ankle.
- Ignoring foot reconstructability in fibular hemimelia.
- Naming a classification without being able to define it, Jones 1a versus 1b in particular.
- Reserving femoral imaging for the severe fibular patterns.
- Presenting prosthetic care as a failure.
- Underestimating rehabilitation and family burden.
- Not updating predictions through growth.
- Forgetting the child's own preference in later childhood.
Integrated clinical approach
"I would not decide from the discrepancy alone. I would define the anatomical deficiency, assess hip and knee stability, decide whether the foot can become plantigrade and shoeable, predict LLD at maturity, and discuss reconstruction, prosthetic or hybrid pathways with the family. The goal is reliable painless mobility with an acceptable lifetime treatment burden."
Guidelines, Registries & Global Practice
Congenital lower-limb deficiency has no single society "guideline" in the way arthroplasty does; practice is shaped by classification-based specialist consensus, prosthetic-rehabilitation standards and resource availability. The picture is genuinely global, and the right pathway shifts with what reconstruction, prosthetics and follow-up a setting can sustain.
Global epidemiology
- Approximate figure
- Most common congenital long-bone deficiency.
- Source context
- Consistently reported across registries and case series.
- Approximate figure
- About 1 per 1,000,000 live births; frequently syndromic or familial.
- Source context
- Fernandez-Palazzi series and rarity reviews.
- Approximate figure
- Femoral anomalies in roughly 59 to 76 percent of fibular deficiency limbs.
- Source context
- Achterman-Kalamchi classification cohort.
- Approximate figure
- Often unilateral; tibial hemimelia may be bilateral and shows familial clustering.
- Source context
- Heterogeneous across small series.
Side-by-side practice frameworks
- Emphasis
- Classification-led decision-making, shared decision-making and outcome measurement (e.g. PODCI).
- Practical message
- Match pathway to Paley/Jones type and document patient-reported function.
- Emphasis
- Centralisation of complex limb deficiency to specialist paediatric limb-reconstruction units with MDT and prosthetic services.
- Practical message
- Refer early; complex reconstruction belongs in high-volume centres.
- Emphasis
- Stability before length: protect joints, achieve a plantigrade foot, then lengthen with monitored regenerate.
- Practical message
- Lengthening is a staged programme, not a single procedure.
- Emphasis
- Multidisciplinary, family-centred counselling comparing reconstruction and prosthetic pathways neutrally.
- Practical message
- Present complete pathways, not isolated operations.
- Emphasis
- Durable end-bearing residual limb and access to growth-adapted prosthetic care.
- Practical message
- Surgical choice must consider lifelong prosthetic and rehabilitation capacity.
Registry and surveillance notes
Unlike arthroplasty, there is no implant registry for these conditions; population data come from congenital-anomaly surveillance networks such as EUROCAT (Europe), the US National Birth Defects Prevention Network and the International Clearinghouse for Birth Defects Surveillance and Research. These define prevalence and associated anomalies but not long-term functional outcomes, which still rely on specialist cohorts.
High- versus limited-resource practice variation
- Typical reality
- Access to staged lengthening, frames, MDT, child psychology and growth-adapted prosthetics.
- Pathway consequence
- Reconstruction and prosthetic pathways can be compared on near-equal footing.
- Typical reality
- Limited frame surgery, fewer revisions feasible, variable prosthetic supply and follow-up.
- Pathway consequence
- A single durable amputation with reliable prosthetic fitting may give better lifetime mobility than incomplete reconstruction.
- Typical reality
- Established deformity, fixed contracture or large discrepancy at first contact.
- Pathway consequence
- Some reconstruction windows are closed; pragmatic prosthetic or salvage planning dominates.
Controversies and Areas of Uncertainty
Several decisions in congenital lower-limb deficiency remain genuinely debated, and a strong exam candidate acknowledges the uncertainty rather than asserting a single right answer.
Reconstruction versus amputation in fibular hemimelia. The two positions are staged reconstruction preserving a plantigrade foot, against early Syme or Boyd amputation for predictable prosthetic mobility. Specialist series report excellent results in selected reconstructable feet, and the pooled cohorts cannot adjust for the fact that the worst feet were amputated.
Be careful how you present that in an exam or a clinic, because the only pooled synthesis points the other way. The meta-analysis cited later on this page (Elmherig, 7 retrospective cohorts, 169 limbs) found amputation ahead on every outcome it could pool: patient satisfaction odds ratio 6.8 (CI 2.4 to 19.2), complications odds ratio 28 against reconstruction (CI 7.8 to 100.3), 1.2 versus 0.2 complications per limb, and 4.2 versus 1.5 operations per patient. The favourable reconstruction figures are conditioned on having achieved a plantigrade painless foot, which is the outcome in question, not a starting condition, whereas the pooled data count every child who set out down that path.
The two literatures are reconcilable once you separate the endpoints, and that is the answer to give. What is not in dispute is the burden of treatment: reconstruction costs roughly three times the operations and six times the complications per limb. Those are counts, not opinions. What is genuinely comparable is the destination: the dedicated comparative study on the fibular hemimelia page (Birch, 20 primary amputations against 22 staged reconstructions, assessed at a mean age of 9) found no significant functional or psychological difference, psychosocial and quality-of-life scores in both groups comparable to healthy populations, and the majority of patients and parents in both groups satisfied and willing to choose the same again, with the honest caveat that the groups differed socioeconomically as well as in treatment.
So the question is unsettled because the evidence is weak and the protocols are not uniform, Level III retrospective cohorts, obvious selection and reporting bias, no randomised comparison, not because reconstruction has been shown to cost nothing extra. Counsel on that split: a similar likely destination, reached by a much longer and more complicated road. A family that understands both and still wants the foot is making a defensible choice.
Salvage in severe tibial hemimelia. Reconstruction, for example fibular transfer or knee reconstruction, is set against knee disarticulation or below-knee amputation. Amputation remains the stated gold standard; reconstruction is type-dependent and unproven in controlled comparison.
Rotationplasty versus prosthetic fitting in severe congenital femoral deficiency. Rotationplasty converts the ankle into a knee for an active end-bearing limb, against an extension prosthesis or other reconstruction. It gives excellent function, but acceptance varies by family and culture.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A newborn has unilateral fibular hemimelia. How do you counsel the family?”
“What matters when assessing congenital femoral deficiency?”
“The family wants limb lengthening because they want to avoid amputation. How do you respond?”
“A two-year-old has unilateral tibial hemimelia with a fixed knee flexion contracture and a deficient extensor mechanism. The parents are strongly against amputation. How do you proceed?”
Assess (LIMB)
- Length: current and predicted at maturity, including foot height
- Instability: hip containment, knee cruciates, ankle and subtalar
- Missing anatomy: femur, tibia, fibula, rays, muscles, nerves, vessels
- Burden: number of stages, rehabilitation and family capacity
- Active knee extension - decisive in tibial deficiency
Classifications - know the definitions
- Aitken A-D (CFD): A head present + adequate acetabulum, subtrochanteric defect unites; B head present, pseudarthrosis that does not unite; C head absent/tuft, acetabulum dysplastic; D head and acetabulum both absent
- Achterman-Kalamchi (fibula): I hypoplastic (IA proximal/distal physes malpositioned, IB 30-50% missing); II complete absence
- Paley (fibula): grades the ANKLE, not the fibula - dynamic valgus to SHORDT, fixed equinovalgus to SUPERankle
- Jones (tibia): 1a no anlage + hypoplastic distal femoral epiphysis; 1b anlage present + NORMAL distal femoral epiphysis; 2 proximal tibia only; 3 distal tibia only; 4 tibiofibular diastasis
Numbers That Decide
- Femoral anomalies in fibular deficiency: 76% Type I vs 59% Type II - commoner in the MILDER type, so image the femur regardless
- Percentage shortening is constant through growth: about 13% Type I, 19% Type II - so predict early with the multiplier method
- Knee physes: distal femur about 9-10 mm/yr, proximal tibia about 6 mm/yr
- Amputation vs reconstruction in fibular hemimelia: 1.5 vs 4.2 procedures, 0.2 vs 1.2 complications per limb, satisfaction OR 6.8
- Lengthening over 6 cm or over 25% of segment length gives worse pain and comfort scores
Discrepancy Bands
- Under 2 cm: observe or shoe raise
- 2-5 cm: well-timed epiphysiodesis of the longer limb
- 5-20 cm: staged lengthening, after the foot and joints are made safe
- Over 20 cm: prosthetic pathway - amputation or rotationplasty as planned reconstruction
- Joint stability and foot function override all of these bands
Salvage Procedures
- Syme: ankle disarticulation removing the whole foot including calcaneus; heel pad can migrate
- Boyd: calcaneotibial fusion - talus out, calcaneus fused to tibia; anchors the heel pad and gives a longer stump
- Van Nes rotationplasty: 180 degree rotation so the ankle acts as a knee; barrier is cosmetic, not functional
- All are disarticulations or fusions because a transdiaphyseal cut in a child causes terminal bony overgrowth
Pitfalls
- Planning from centimetres alone, or omitting foot height
- Lengthening above an unstable hip, knee or ankle
- Missing a Jones 1b anlage and disarticulating a reconstructable knee
- Reserving femoral imaging for severe fibular deficiency
- Counselling with adjectives instead of procedure and complication counts
- Presenting prosthetic care as failure
Evidence Base
Achterman-Kalamchi: the landmark fibular deficiency classification
- Reviewed 97 limbs in 81 patients with congenital fibular deficiency and divided it into Type I (partial hypoplasia) and Type II (complete absence).
- Associated femoral anomalies were present in 76 percent of Type I and 59 percent of Type II limbs, and limb shortening was roughly proportional throughout growth (about 13 percent Type I, 19 percent Type II).
- Type I deficiency was treated by length equalisation, whereas Type II commonly required foot amputation and prosthetic fitting for satisfactory function.
Paley reconstruction classification for fibular hemimelia
- Proposes a classification based on ankle joint morphology rather than the degree of fibular deficiency, because residual or recurrent foot deformity is the main cause of reconstruction failure.
- The SHORDT procedure stabilises a dynamic valgus ankle, while the SUPERankle procedure corrects a fixed equinovalgus foot using bony supramalleolar and subtalar realignment with anlage resection.
- Serial lengthening combined with a plantigrade, painless, functional foot is reported as comparable to or better than Syme amputation with a prosthesis.
SUPERankle plus lengthening: a reconstruction outcomes series
- 29 limbs treated using the Paley classification: 27 reconstructed and 2 treated with primary Syme amputation.
- Excellent or good ASAMI results were achieved in 21 of 27 reconstructed patients (55 percent excellent, 22 percent good).
- Mean limb length discrepancy improved from 3.55 cm at presentation to 1.01 cm after treatment, and operating before age 5 reduced recurrent foot deformity.
Amputation versus reconstruction for fibular hemimelia: meta-analysis
- Pooled 7 retrospective cohorts and 169 fibular hemimelia cases comparing amputation with limb reconstruction.
- Amputation showed higher patient satisfaction (odds ratio 6.8, 95 percent CI 2.4 to 19.2) and far fewer complications (reconstruction odds ratio 28 for complications).
- Reconstruction averaged 4.2 procedures per patient versus 1.5 for amputation, with 1.2 versus 0.2 complications per limb.
Lengthening is effective for mild and moderate congenital femoral deficiency
- 30 patients with Paley Type 1a, 1b or 2a congenital femoral deficiency and stable hip and knee joints were lengthened with a monolateral external fixator.
- Mean lengthening was 6 cm (correcting about 112 percent of the discrepancy) without significant loss of hip or knee range of motion.
- Complications occurred in 30 of 60 planned procedures (50 percent), and lengthening greater than 6 cm or over 25 percent of femoral length gave worse pain and comfort scores.
Paley reconstruction classification for tibial hemimelia
- Tibial hemimelia is a rare deficiency with a wide spectrum of anomalies, duplications and deficiencies, where amputation with prosthetic fitting has long been the gold standard.
- A new classification is proposed to guide prognosis and reconstructive technique selection based on improved understanding of pathoanatomy.
- Reconstructive options (including fibular transfer and patelloplasty techniques) are matched to specific anatomical types.
Tibial hemimelia: reconstruction versus amputation systematic review
- Pooled 11 studies and 131 patients; Jones Type I was the most common pattern (40.9 percent).
- Reconstruction complications included external fixator tract infection, knee flexion contracture and reduced knee and ankle motion.
- No evidence proved superiority of reconstruction, and amputation remained the stated gold standard.
Tibial deficiency: rarity, the Jones classification and early amputation
- Tibial hemimelia has an incidence of approximately 1 per 1 million live births and is usually associated with other anomalies.
- 22 limbs in 18 patients were classified by Jones, Barnes and Lloyd-Roberts (types Ia, Ib, II, III, IV), and treatment was always surgical.
- Earlier amputation was associated with easier, faster rehabilitation and prosthetic adaptation, accepted by the child as a congenital amputation.