Often an Iatrogenic Shoulder Catastrophe
- DELTOID RUPTURE/AVULSION is an uncommon but disabling injury of the shoulder's prime mover; the cause most often described is IATROGENIC - DETACHMENT or avulsion of the deltoid origin from the ANTERIOR and LATERAL ACROMION after OPEN or ARTHROSCOPIC ACROMIOPLASTY or open rotator-cuff surgery - and the resulting insufficiency is a devastating problem causing poor function and debilitating pain. BE PRECISE ABOUT THE ANATOMY: the segment at risk is the anterior part of the ACROMIAL (middle) head, which arises from the acromion; the CLAVICULAR (anterior) head arises from the lateral third of the CLAVICLE and is not what an acromioplasty detaches.
- TREAT 'COMMONEST' WITH CARE - the published literature on this injury is case reports and small series, so there is no denominator. No cohort establishes what proportion of deltoid ruptures are iatrogenic, and no study gives an incidence of deltoid detachment per acromioplasty. What is defensible is that iatrogenic detachment is the mechanism most often REPORTED, not that its frequency has been measured.
- OTHER causes are TRAUMATIC rupture/avulsion (rare, high-energy or in the elderly/atrophic muscle) and secondary deltoid dehiscence or overload in MASSIVE IRREPARABLE ROTATOR CUFF tears, where the deltoid is the principal remaining elevator.
- The clinical consequence is DELTOID INSUFFICIENCY: WEAKNESS of shoulder abduction/elevation, PAIN, a visible or palpable DEFECT/dimple over the deltoid, and ANTEROSUPERIOR ESCAPE of the humeral head (when combined with cuff deficiency) - producing significant functional disability that activities of daily living tolerate poorly.
- DIAGNOSIS is by CLINICAL examination (deltoid contour defect, weakness, the operative history) supported by IMAGING - ULTRASOUND and especially MRI to define the deltoid defect, retraction and any associated cuff pathology.
- TREATMENT is difficult: surgical REPAIR/RECONSTRUCTION of the deltoid (direct repair to the acromion - e.g. transosseous/suture-anchor repair - or, for larger/chronic defects, local flap/allograft reconstruction) is undertaken for symptomatic insufficiency, but results are variable and the repair is technically demanding (there are no firmly established standard guidelines) - so realistic expectations are important.
- The dominant clinical message is PREVENTION: during open or arthroscopic acromioplasty and cuff surgery the deltoid ORIGIN must be PROTECTED and, where detached/split, METICULOUSLY REPAIRED (secure deltoid-to-acromion reattachment) - because an iatrogenic deltoid detachment is far easier to avoid than to reconstruct, and a postoperative deltoid defect should be recognised and repaired early rather than left.
- THE PREVENTION ARGUMENT GOES ONE STEP FURTHER THAN TECHNIQUE. A complication of an operation is only worth risking if the operation works. In the CSAW trial - 313 patients, 32 UK hospitals, placebo-controlled - arthroscopic subacromial DECOMPRESSION was no better than arthroscopy alone (Oxford Shoulder Score difference -1.3 points, 95% CI -3.9 to 1.3) and both surgical arms beat no treatment by only 2.8 and 4.2 points against a pre-specified clinically important difference of 4.5. So for subacromial pain with an intact cuff, the surest way to avoid an iatrogenic deltoid injury is to question the indication before questioning the technique.
- “Deltoid rupture/avulsion = uncommon but disabling; the mechanism most often REPORTED is IATROGENIC detachment of the anterior-lateral ACROMIAL origin at acromioplasty/open cuff surgery (the clavicular head comes off the clavicle, not the acromion). Also traumatic / massive-cuff-related. The literature is case reports - there is no measured frequency.
- “Consequence = DELTOID INSUFFICIENCY: weak abduction/elevation, pain, contour defect, anterosuperior escape. Diagnose with examination + MRI/ultrasound.
- “Repair/reconstruction is DIFFICULT (variable results, no firm standard). PREVENTION is key: protect + securely repair the deltoid origin at shoulder surgery; recognise/repair an iatrogenic detachment early.
Deltoid Anatomy: Why the Anterior Origin Is Vulnerable
Three heads. The anterior (clavicular) head arises from the lateral third of the clavicle, the middle (acromial) head from the acromion, and the posterior (spinous) head from the scapular spine. The middle head is a strong multipennate segment and the main power abductor. All three converge on the deltoid tuberosity of the lateral humerus.
The segment at risk. It is the anterior portion of the acromial head, arising from the anterior and lateral acromion, that is resected around, exposed or detached in acromioplasty and in the deltoid-splitting or deltoid-off approaches for open cuff surgery. That segment sits directly over the humeral head, so its failure produces weak forward elevation and a visible dimple at the acromial edge.
The axillary nerve. The deltoid is supplied by the axillary nerve (C5-6) from the posterior cord. The nerve passes through the quadrangular space and runs on the deep surface of the deltoid about 5 cm below the acromial edge, which is why a deltoid-splitting approach is limited to roughly 5 cm distal to the acromion to avoid denervating the anterior deltoid.
Q: Which part of the deltoid does an acromioplasty endanger?
A: Say "the anterior-lateral acromial origin", the front of the acromial (middle) head, not "the anterior deltoid comes off the anterior acromion". That loose shorthand misleads: the clavicular (anterior) head comes off the clavicle, and an acromioplasty does not detach it.
Causes and Consequences
What it is. Deltoid rupture or avulsion is an uncommon but disabling injury of the shoulder's prime mover, most often of its anterior-lateral acromial origin.
How much is known. The published literature is case reports and small series, so there is no denominator: no cohort gives the proportion that is iatrogenic, and no study gives an incidence per acromioplasty.
Iatrogenic detachment. The mechanism most often reported is detachment or devitalisation of the deltoid origin from the anterior and lateral acromion during open or arthroscopic acromioplasty or open rotator-cuff surgery. It is a recognised and devastating complication, and it is far easier to avoid than to reconstruct.
Other causes. Less commonly, the deltoid ruptures after high-energy trauma. It can also fail secondarily, by dehiscence or overload, in massive irreparable rotator cuff tears, where the deltoid is the last remaining elevator.
Deltoid insufficiency. The result is weakness of abduction and elevation, pain, a visible or palpable contour defect and, when combined with cuff deficiency, anterosuperior escape of the humeral head. Because the deltoid is the prime mover, the disability is poorly tolerated and hard to reverse.
Where the rest lives. The indication that puts the deltoid origin at risk in the first place is discussed under subacromial impingement, where the randomised evidence on decompression is set out in full. The secondary dehiscence pattern belongs with massive rotator cuff tears and, once the head has migrated and the joint has worn, rotator cuff arthropathy; the operative approaches that split the deltoid are covered under rotator cuff tears.
Diagnosis and Imaging
Clinical diagnosis. The diagnosis is made on examination: the deltoid contour defect, the weakness and the operative history. Ultrasound and especially MRI then define the deltoid defect, its retraction and any associated cuff pathology.
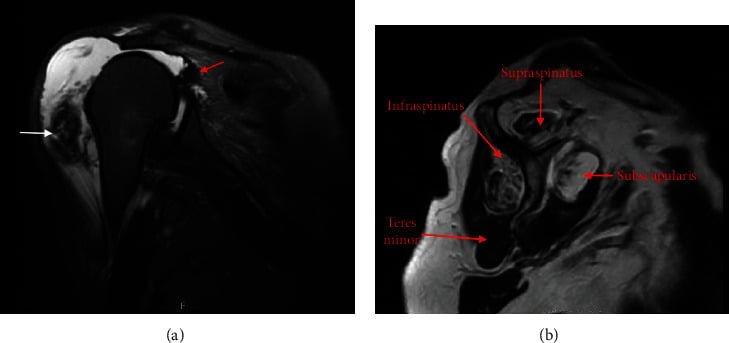
Secondary failure. The deltoid origin can also tear and retract from the acromion in cuff-tear arthropathy.
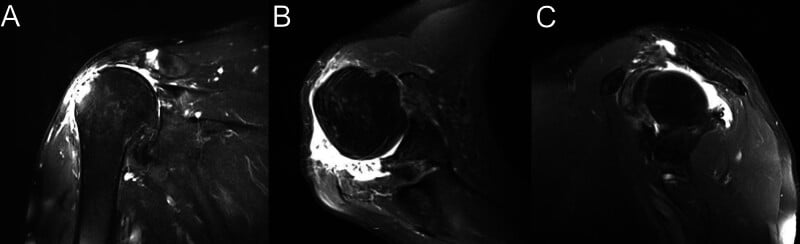
The distal pattern. Trauma can instead avulse the deltoid from its humeral insertion, a rare pattern distinct from the acromial-origin detachment.
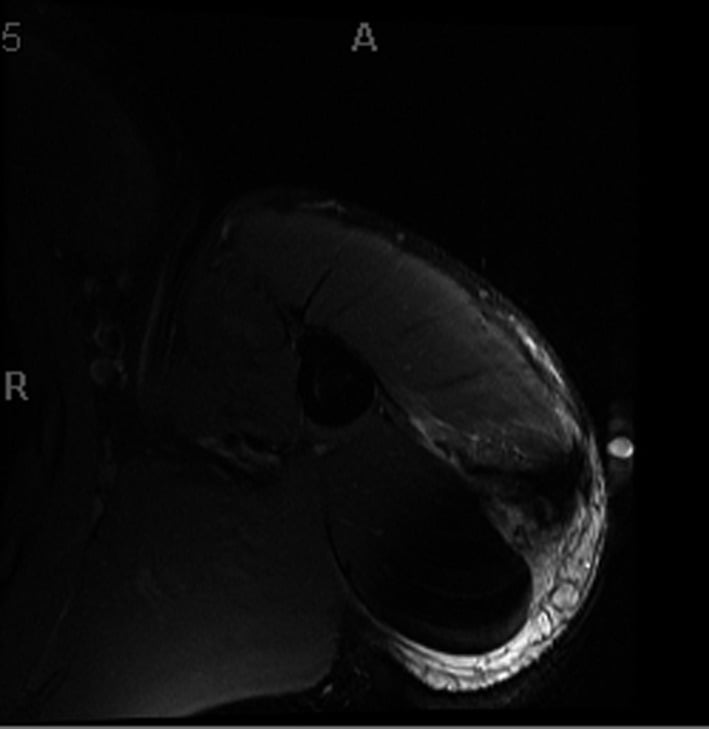
Detachment versus Axillary Nerve Palsy
A deltoid that is weak and wasted after shoulder surgery has two very different causes, a mechanical deltoid detachment and an axillary nerve palsy, and the distinction changes the treatment entirely.
- Mechanical detachment
- Palpable or visible contour defect/dimple
- Axillary nerve palsy
- Wasting without a mechanical defect
- Mechanical detachment
- Corresponds to the detached segment
- Axillary nerve palsy
- Deltoid weakness
- Mechanical detachment
- Normal
- Axillary nerve palsy
- Often numb over the regimental-badge area (upper lateral arm over the deltoid)
- Mechanical detachment
- Normal EMG
- Axillary nerve palsy
- Denervation
- Mechanical detachment
- Deltoid defect and retraction
- Axillary nerve palsy
- Diffuse denervation oedema/atrophy rather than a torn origin
- Mechanical detachment
- Repair/reconstruction
- Axillary nerve palsy
- Observation/neurolysis, or nerve grafting for a confirmed complete lesion
Both at once. The two can coexist, for example after a traumatic anterior dislocation or extensive surgery, so seek both a defect and a neurological deficit. EMG/nerve conduction studies and MRI usually separate them.
Management and Prevention
Expectations. Surgical repair or reconstruction is undertaken for symptomatic insufficiency. It is technically demanding, results are variable and there are no firmly established standard guidelines, so realistic expectations are important.
The options.
- Direct repair to the acromion, transosseous or with suture anchors
- Local flap or allograft reconstruction for larger or chronic defects
Direct repair. It needs mobilisable, viable muscle and sufficient acromial bone. The intact fascia can conceal the tear, and the muscle is mobilised before it is reattached to the remaining acromion. Mason-Allen sutures obtain broad deltoid purchase and can be tied over a three-hole plate on the superior acromion to distribute load and limit bone cut-out.
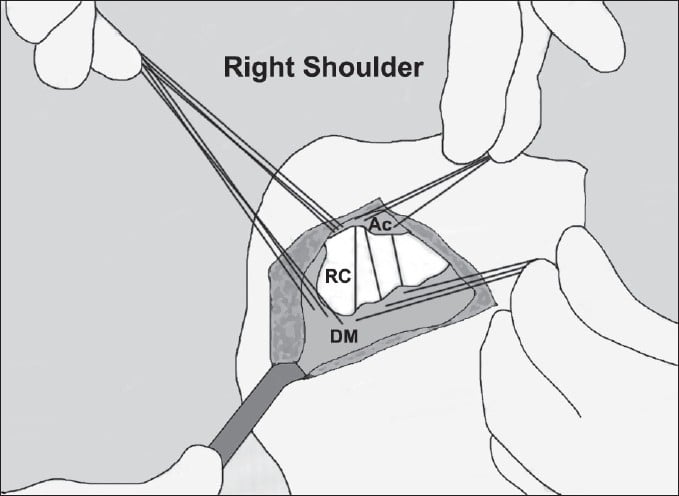
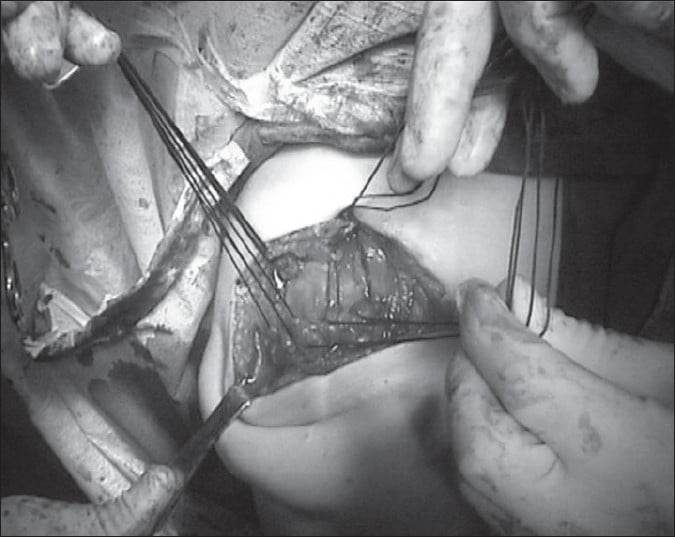
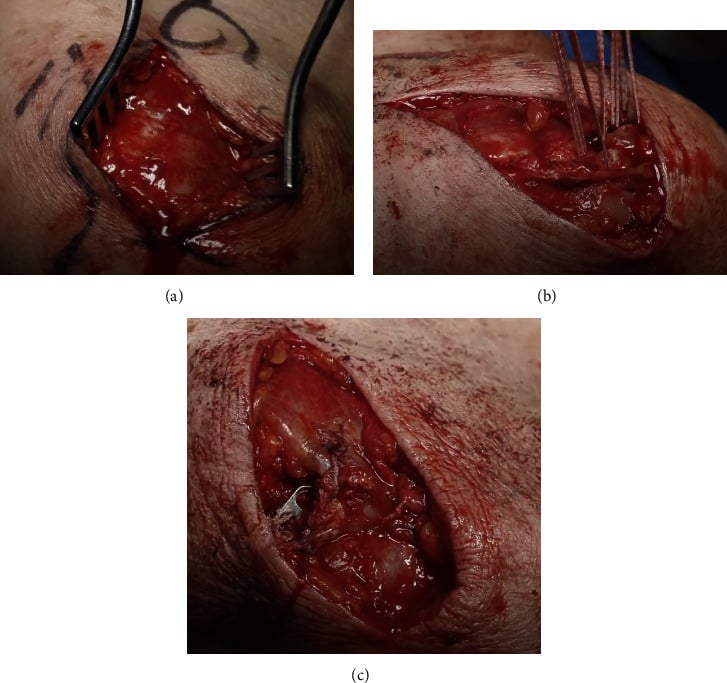
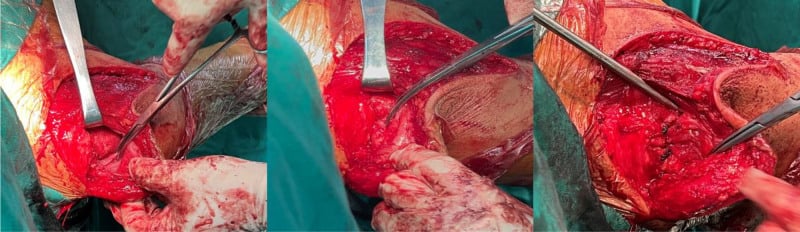
Prevention. This is the dominant message. During open or arthroscopic acromioplasty and cuff surgery the deltoid origin must be protected, and any necessary split or detachment meticulously repaired to bone at closure.
A deltoid detachment recognised after surgery is better repaired early, before retraction and atrophy make reconstruction even harder.
Mnemonics & Memory Aids
DELTOID
Hook:DELTOID: Detachment (iatrogenic), Elevation weak, Look for defect/escape, Traumatic/cuff causes, Origin = anterior-lateral acromial, Imaging, Difficult repair (prevent it).
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A patient has weak shoulder elevation and a contour defect over the deltoid after a previous acromioplasty. What has happened and how do you manage it?”
Causes
- Iatrogenic (most often reported, never counted): detachment of the anterior-lateral acromial origin at acromioplasty/open cuff surgery
- Traumatic (rare); secondary to massive irreparable rotator cuff tear
- The acromial (middle) head arises from the acromion; the clavicular head from the clavicle
- Prevention starts with the indication: CSAW found decompression no better than placebo for subacromial pain with an intact cuff
Consequence & diagnosis
- Deltoid insufficiency: weak abduction/elevation, pain, contour defect
- Anterosuperior escape of the humeral head (with cuff deficiency)
- Examination + operative history; MRI/ultrasound (defect/retraction)
Management
- Difficult repair/reconstruction (direct acromial reattachment; flap/allograft for large/chronic) - variable results
- No firmly established standard technique
- Prevention is key: protect + securely repair the deltoid origin; repair an iatrogenic detachment early
Evidence & Key Studies
Delayed surgical repair of the deltoid following acromioplasty
- Because part of the anterior deltoid originates from the anterior acromion, there is a risk of violation and iatrogenic rupture/avulsion during arthroscopic acromioplasty.
- Deltoid insufficiency following acromioplasty can be a devastating problem leading to poor function and debilitating pain.
- Surgical repair (here, arthroscopic evaluation followed by open deltoid repair) improved pain and disability, but there are no standard guidelines and the suture-repair technique is one option for this difficult injury.
Arthroscopic subacromial decompression for subacromial shoulder pain (CSAW): a multicentre, pragmatic, parallel group, placebo-controlled, three-group, randomised surgical trial
- 313 patients across 32 UK hospitals and 51 surgeons with subacromial pain for at least 3 months, intact cuff tendons, and a completed non-operative programme including exercise and at least one steroid injection, randomised 1 to 1 to 1 between decompression, investigational arthroscopy alone as a placebo, and no treatment.
- At 6 months the Oxford Shoulder Score did not differ between decompression and placebo arthroscopy (mean difference -1.3 points, 95% CI -3.9 to 1.3, p=0.31). Both surgical arms exceeded no treatment by 2.8 and 4.2 points, below the pre-specified clinically important difference of 4.5, and that gap may reflect placebo effect or postoperative physiotherapy.
- The trial excluded full-thickness cuff tears and had substantial crossover (23, 42 and 12 percent did not receive the assigned treatment by 6 months), so it does not speak to decompression performed alongside a cuff repair - but for isolated subacromial pain it questions the value of the operation.
The iatrogenic mechanism of deltoid rupture/avulsion (anterior-deltoid violation during arthroscopic acromioplasty because it originates from the anterior acromion), its devastating functional/pain consequences, and the difficulty of surgical repair (no standard guidelines) come from the cited Sherwani report. The randomised evidence questioning the value of isolated subacromial decompression comes from the CSAW trial. The deltoid-insufficiency clinical picture (weakness, contour defect, anterosuperior escape), the traumatic and massive-cuff-related causes, the deltoid's segmental origins, the MRI/ultrasound diagnosis, and the prevention principle (protect and securely repair the deltoid origin) are standard, well-established teaching. The published literature on deltoid rupture itself is case reports and small series: there is no cohort giving the proportion of deltoid ruptures that are iatrogenic, no incidence per acromioplasty, and no comparative series establishing one repair technique over another, so none of those figures is quoted here.