Destructive Arthropathy of an Insensate Joint
- Destruction out of proportion to pain, in an insensate joint, is the key clue
- Syringomyelia is the classic cause at the elbow: examine for dissociated sensory loss and MRI the cervical spine up to the craniocervical junction
- Exclude infection and tumour before calling it neuropathic - the expansile, destructive appearance can mimic malignancy
- Protect the joint and treat the cause; decompressing the syrinx appears to protect the joint, not just the cord
- Joint surgery (arthrodesis or arthroplasty) is limited and high-risk - an extrapolation, as no neuropathic-elbow outcome series was retrieved
- “Charcot elbow = destruction of an insensate joint, out of proportion to the (relatively painless) symptoms
- “Classic cause = syringomyelia, so MRI the cervical spine; other sensory neuropathies also cause it
- “Differential = infection and tumour; management = protect/brace + treat the cause
What It Is and How It Presents
The disease. A Charcot, or neuropathic, joint is a progressive, destructive arthropathy of an insensate joint. Loss of protective pain sensation and proprioception leads to repeated, unperceived microtrauma and accelerating joint destruction, with fragmentation and intra-articular debris.
The presentation. The picture is paradoxical: a strikingly swollen, often grossly unstable elbow with marked destruction on radiographs (fragmentation, debris, sometimes an expansile, destructive, 'mass-like' appearance) that is relatively painless. Destruction out of proportion to the pain is the key clue. Because the gross destruction comes with little pain, its severity can be under-appreciated.
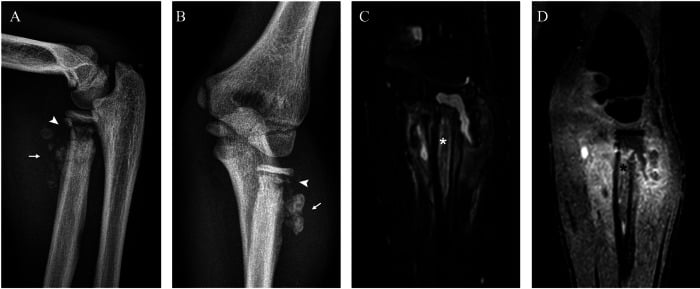
The Site Points to the Cause
An insensate elbow or shoulder should trigger a search for a syrinx, whereas an insensate foot points to diabetes. The location of the neuropathic joint directs the neurological work-up.
- Upper limb (elbow, shoulder, wrist, hand). Syringomyelia is the classic cause: a cervical-cord syrinx produces the upper-limb sensory loss. Other causes are cervical spondylotic myelopathy or radiculopathy, brachial plexus injury, leprosy (Hansen disease) and peripheral nerve injury.
- Lower limb and foot, for contrast. Diabetes mellitus is now the commonest cause overall, and tabes dorsalis (neurosyphilis) is the historical classic, at the knee, hip and spine. Alcoholic and other peripheral neuropathies, spinal cord injury and myelomeningocele or spina bifida complete the list.
How often the elbow. Syringomyelia is described as a prevalent cause of Charcot arthropathy, notably affecting the elbow. A neurosurgical cohort of 12 patients with neuropathic arthropathy from syringomyelia counted joints and found the elbow the commonest: 10 of 16 involved joints, ahead of the shoulder (three), interphalangeal joints (two) and wrist (one).
The Syrinx and the Dissociated Sensory Loss
Why the loss is dissociated. A syrinx expands the central canal and first interrupts the decussating spinothalamic fibres, carrying pain and temperature, as they cross in the anterior commissure. The dorsal columns (fine touch, proprioception, vibration) are spared early. The result is loss of pain and temperature with preserved light touch, "dissociated" or "suspended" sensory loss, classically in a cape or shawl distribution over the shoulders and upper limbs.
Why the elbow. A cervical or upper-thoracic syrinx affects the upper limbs. That is why the neuropathic joint occurs at the elbow or shoulder, and why the loss of protective pain sensation there allows the joint to be destroyed unnoticed.
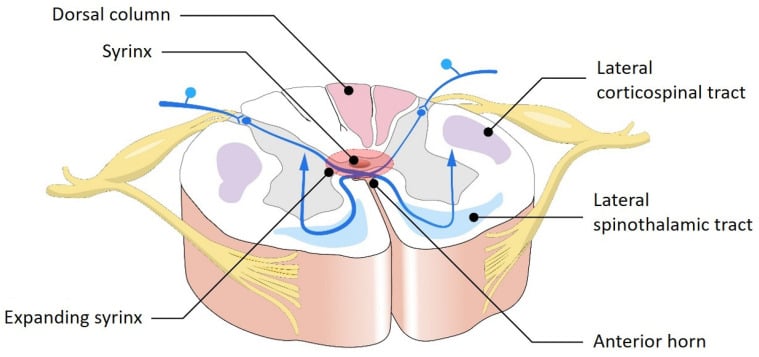
The rest of the neurology. Examine beyond the elbow for:
- Lower-motor-neuron signs in the hands (wasting and weakness from anterior-horn-cell involvement) and lost upper-limb reflexes
- With expansion, long-tract (spastic lower-limb) signs, scoliosis and Horner syndrome
- The common association with a Chiari I malformation
Work-up and Differential Diagnosis
Examine, then image. Examine for the sensory deficit, the dissociated pain and temperature loss of syringomyelia. Radiographs and CT of the elbow show the destruction and debris. The essential investigation is MRI of the cervical spine to detect a syrinx, extended to the craniocervical junction: in the neurosurgical series a Chiari malformation was present in 11 of 12 patients and a tethered cord in the twelfth.
Check the side. In that series the side of the syrinx on axial cervical MRI matched the side of the affected limb in every patient. A syrinx contralateral to the destroyed elbow should prompt a rethink rather than reassurance.
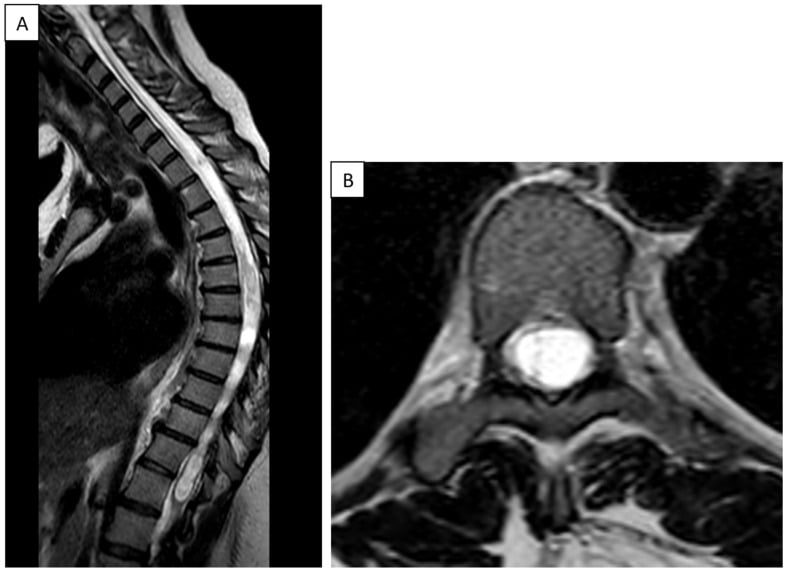
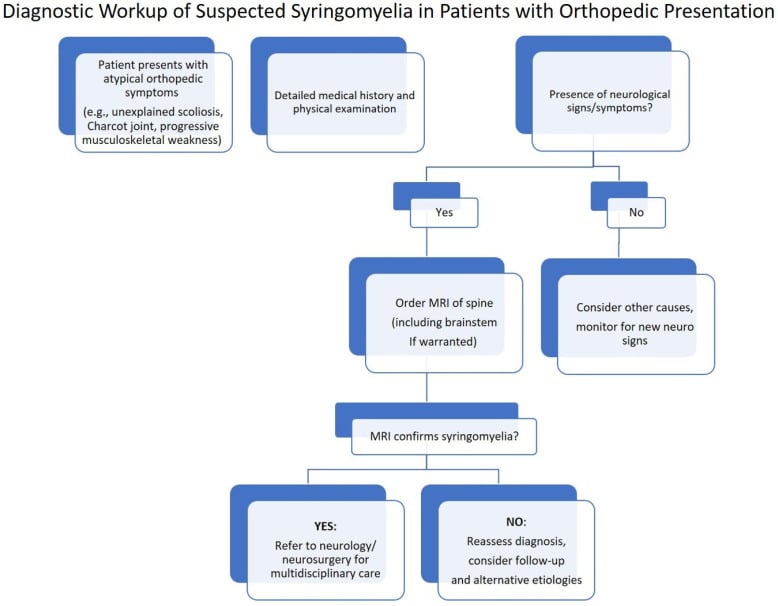
The crucial differential is infection (septic arthritis or osteomyelitis) and tumour. The grossly destructive, sometimes expansile appearance can mimic malignancy or infection, so a thorough work-up, with biopsy where genuinely uncertain, is needed and other causes must be excluded before the destruction is attributed to neuropathic arthropathy.
Management
Protect the joint, treat the cause. Management is largely supportive: protect the joint with bracing or splinting and activity modification, and treat the underlying cause, for example by neurosurgical decompression of a syrinx. A multidisciplinary approach, with neurosurgery, is important.
Does treating the syrinx change the joint? Telling a patient to have neurosurgery for the sake of the elbow needs more than plausibility behind it. The neurosurgical cohort of 12 patients followed exactly this question over a mean of 39 months:
- Five had neurosurgery (four posterior fossa decompression, one syringo-subarachnoid shunt). None deteriorated, and all reported improved neurological function.
- Seven did not. Five had aggravation of the arthropathy, four of them with worsening neurological symptoms, and only two remained stable.
- No patient had surgery on the joint.
The series is small, retrospective and unrandomised, and the patients offered neurosurgery were selected, so the comparison is confounded. It is still the closest available answer, and it supports treating the syrinx as disease-modifying for the joint rather than merely for the neurology, which is why decompression is offered.
Surgery on the joint. Arthrodesis or arthroplasty is limited, and in the neuropathic, insensate joint it is generally held to carry high failure and complication rates. It is reserved for selected severe cases within a multidisciplinary approach that includes neurosurgery. No series reporting its outcome specifically at the neuropathic elbow was retrieved, so that caution is extrapolated rather than measured.
Mnemonics & Memory Aids
CHARCOT
Hook:CHARCOT: Cervical syrinx (MRI), Hugely swollen, (relatively) Asymptomatic, Radiographic destruction, exClude infection/tumour, Offload/protect, arThrodesis high-risk.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A patient has a grossly swollen, unstable, but relatively painless elbow with marked destruction on radiographs. What is the diagnosis, what must you investigate, and how do you manage it?”
What it is
- Progressive destructive arthropathy of an insensate joint
- Repeated unperceived microtrauma → fragmentation/debris
- Destruction out of proportion to (relatively painless) symptoms
Cause & work-up
- Classic cause at elbow/upper limb = syringomyelia (also other sensory neuropathies)
- MRI the cervical spine for a syrinx; examine for dissociated sensory loss
- Exclude infection (septic arthritis/osteomyelitis) and tumour (can mimic malignancy)
Management
- Largely supportive: protect/brace, activity modification
- Treat the underlying cause: after decompression 0 of 5 progressed, against 5 of 7 untreated (n=12, confounded)
- MRI must cover the craniocervical junction (Chiari in 11 of 12) and the syrinx side should match the affected limb
- Joint surgery limited and held high-risk - no elbow-specific outcome series exists; multidisciplinary care
Evidence & Key Studies
Neuropathic arthropathy from a chronic syrinx (Charcot joint of the upper limb)
- Syringomyelia is a prevalent cause of Charcot arthropathy, notably affecting the elbow and (less frequently) the shoulder; neuropathic arthropathy can present as an expansile destructive mass on imaging, raising suspicion of malignancy.
- Diagnosis relies on a comprehensive assessment - clinical signs/symptoms, radiological imaging and tests to exclude other causes including soft-tissue tumours - and laboratory tests/biopsy were used to exclude malignancy.
- Management strategies range from conservative approaches to surgical interventions such as neurosurgical decompression (for the syrinx) and arthroplasty, with a multidisciplinary approach important for optimal outcomes.
Neuropathic arthropathy caused by syringomyelia: 12 patients, and what neurosurgery did to the joints
- Retrospective single-department review of 12 patients referred to neurosurgery between 2003 and 2012, with 16 involved joints and a mean follow-up of 39 months.
- The ELBOW was the commonest joint (10 of 16), followed by shoulder (3), interphalangeal (2) and wrist (1).
- MRI showed a syrinx in all 12, with Chiari malformation in 11 and a tethered cord in 1 - so imaging must cover the craniocervical junction.
- The side of the syrinx on axial cervical MRI was concordant with the side of the affected limb in EVERY patient.
- Five patients had neurosurgery (4 posterior fossa decompression, 1 syringo-subarachnoid shunt): all reported neurological improvement and NONE deteriorated with respect to the arthropathy. Of the 7 without neurosurgery, 5 had aggravation of the arthropathy and 2 were stable.
- No patient underwent surgery on the neuropathic joint itself.
- Of the 5 whose arthropathy worsened without neurosurgery, 4 also had DETERIORATION OF THEIR NEUROLOGICAL SYMPTOMS - so joint decline tracked neurological decline rather than occurring independently.
Syringomyelia as a prevalent cause of Charcot arthropathy notably affecting the elbow, the presentation as an expansile destructive 'mass' that can mimic malignancy, the need for a comprehensive assessment to exclude tumour/other causes (including biopsy where uncertain), and the management spectrum (conservative to neurosurgical decompression of the syrinx and arthroplasty, with a multidisciplinary approach) come from the cited Edara report. The general nature of neuropathic arthropathy (destruction of an insensate joint out of proportion to pain), the need to image the cervical spine for a syrinx, and the high-risk/limited role of joint surgery in neuropathic joints are standard, well-established teaching. The joint distribution, the Chiari and side-concordance findings and the outcomes with and without neurosurgical decompression come from the cited Deng series - 12 patients referred to a single neurosurgical department, retrospective and unrandomised, in which the patients offered decompression were selected, so it is confounded by indication and shows an association rather than a treatment effect. No series reporting the outcome of arthroplasty or arthrodesis specifically in the NEUROPATHIC ELBOW was retrieved; the statement that joint surgery carries high failure and complication rates is therefore an extrapolation from neuropathic joints at other sites and from general principle, and is labelled as such rather than given a rate. For contrast, a 10-patient shoulder series found reverse arthroplasty gave good or excellent results in the two patients who had it while conservative treatment relieved symptoms without restoring motion - shoulder data, not elbow. See also Charcot neuroarthropathy, neuropathic arthropathy of the shoulder, syringomyelia, Chiari malformation, total elbow arthroplasty and septic arthritis pathophysiology.