Neuropathic Arthropathy of the Glenohumeral Joint
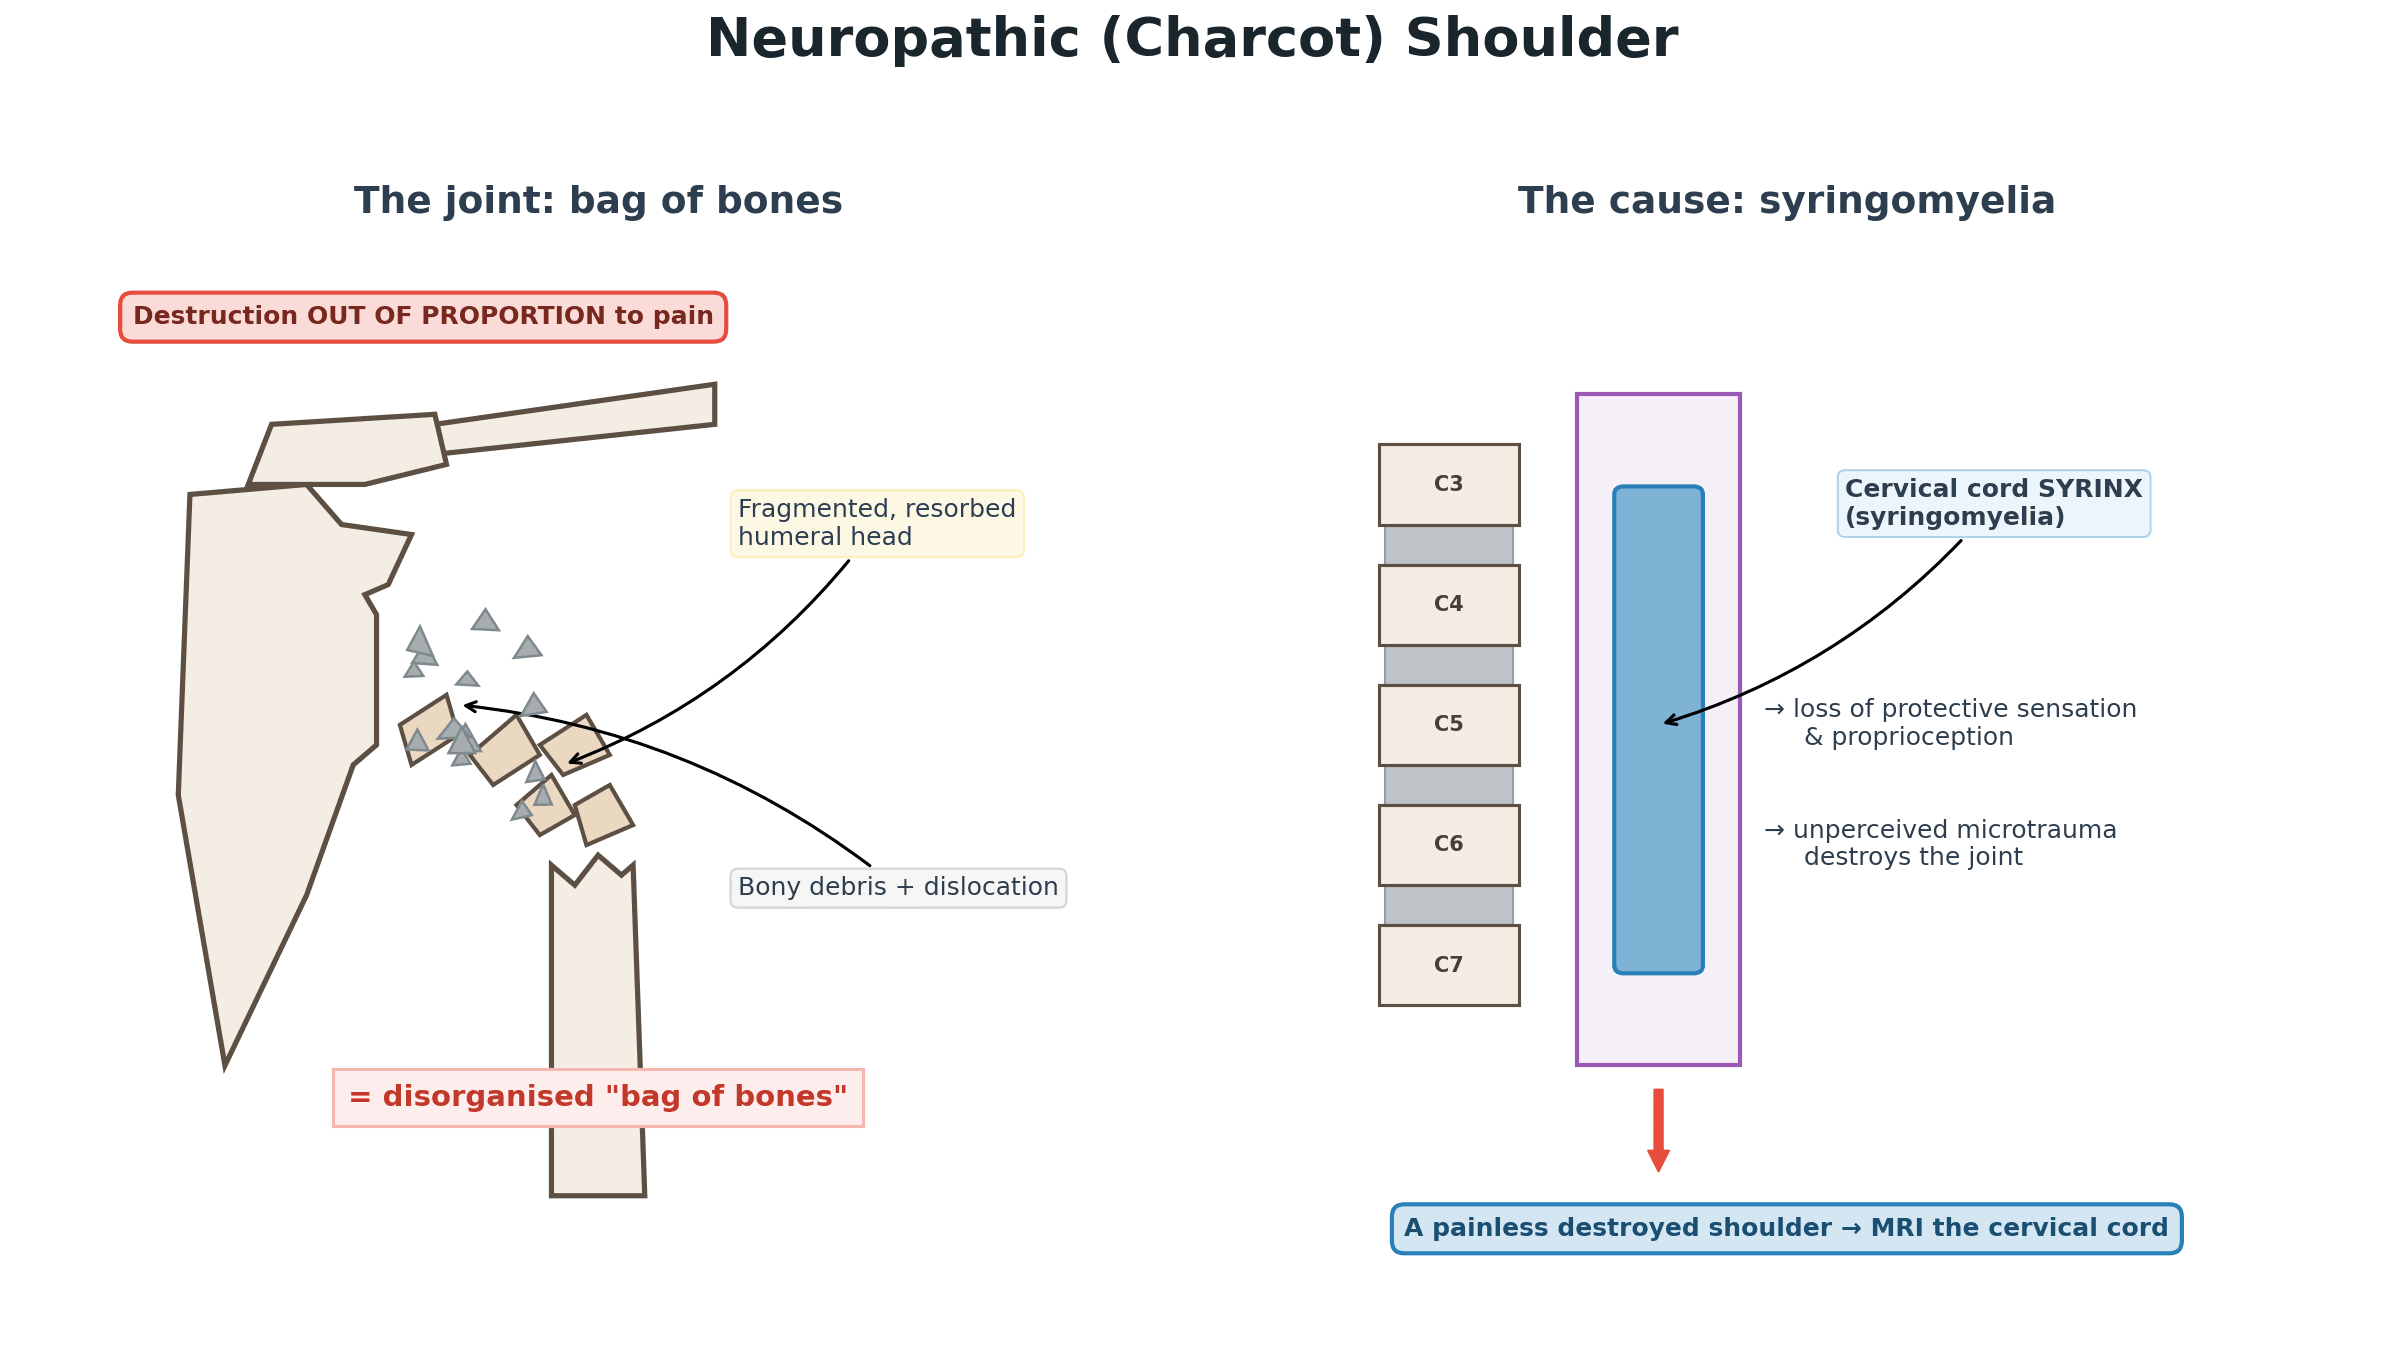
- Charcot (neuropathic) arthropathy of the shoulder is a progressive, grossly destructive arthropathy in which the joint destruction is OUT OF PROPORTION to the pain - the hallmark is a markedly swollen, often unstable shoulder with surprisingly LITTLE pain, because the underlying problem is loss of protective sensation and proprioception.
- SYRINGOMYELIA is the leading cause of an upper-limb (elbow and shoulder) neuropathic joint, so a painless destroyed shoulder should prompt MRI of the CERVICAL SPINAL CORD to look for a syrinx (often associated with a Chiari malformation); other causes include cervical cord lesions and peripheral neuropathies.
- The pathophysiology combines the NEUROTRAUMATIC theory (loss of protective sensation allows repetitive unperceived microtrauma and progressive destruction) and the NEUROVASCULAR theory (autonomic dysregulation increasing blood flow and bone resorption); the result is fragmentation, resorption and disorganisation of the joint.
- RADIOGRAPHS show gross destruction - resorption and fragmentation of the humeral head, bony debris and a disorganised 'BAG OF BONES' appearance - and the classic teaching summarises the changes as the 6 Ds (Destruction, Density increase/sclerosis, Debris, Dislocation, Disorganisation, Distension); the shoulder is often grossly swollen with effusion.
- The crucial step is the DIFFERENTIAL: the swollen, destroyed, fluid-filled shoulder can mimic a soft-tissue or bone TUMOUR (an expansile mass) or INFECTION (septic arthritis/osteomyelitis), so these must be excluded with appropriate imaging and, when there is doubt, aspiration and/or biopsy, before the destruction is attributed to a neuropathic process.
- Management is largely SUPPORTIVE - treat the underlying neurological cause (e.g. neurosurgical decompression of a syrinx where indicated), protect the joint, and manage symptoms - because surgery on a Charcot joint has high complication and failure rates; arthrodesis is difficult and unreliable, and arthroplasty is reserved for carefully selected cases, ideally after the neurological process is addressed and within a multidisciplinary team.
- “Charcot shoulder = PAINLESS gross destruction (destruction out of proportion to pain) - think SYRINGOMYELIA; image the cervical cord (MRI).
- “Radiograph: 'bag of bones' - the 6 Ds (Destruction, Density, Debris, Dislocation, Disorganisation, Distension).
- “Always exclude TUMOUR and INFECTION first; management mainly supportive + treat the cause; surgery is unreliable and selective.
Pathophysiology and Cause
The painless destroyed shoulder. The defining feature of a Charcot shoulder is destruction out of proportion to pain. The joint is hot, grossly swollen and disorganised, often unstable, yet relatively painless, because the underlying problem is loss of protective sensation and proprioception.
Why the joint breaks down. Two theories are combined. The neurotraumatic theory holds that loss of protective sensation allows repetitive, unperceived microtrauma and progressive destruction; the neurovascular theory adds autonomic dysregulation that increases blood flow and bone resorption. Together they produce fragmentation, resorption and disorganisation of the joint.
The cause. Syringomyelia is the leading cause of an upper-limb neuropathic joint, at the elbow and the shoulder. A painless destroyed shoulder should therefore prompt MRI of the cervical spinal cord to find a syrinx, which is often associated with a Chiari malformation.
Causes of a Neuropathic Joint: Which Disease, Which Joint
Let the joint point to the cause. Syringomyelia is the classic upper-limb cause, but the joint distribution usually points to the underlying neurological disease. A destroyed shoulder or elbow is syringomyelia until proven otherwise.
- Typical joint(s)
- UPPER LIMB - shoulder and elbow
- The investigation that identifies it
- MRI of the cervical cord and craniocervical junction - the single most important test in a destroyed shoulder
- Typical joint(s)
- FOOT and ankle (commonest cause overall)
- The investigation that identifies it
- Glucose and HbA1c with bedside sensory testing (monofilament, vibration)
- Typical joint(s)
- KNEE, hip and spine (large lower-limb joints)
- The investigation that identifies it
- Treponemal serology - rare now, but the classic answer and a treatable cause
- Typical joint(s)
- Hands and feet
- The investigation that identifies it
- Slit-skin smear and nerve examination for thickened peripheral nerves; consider in endemic or migrant populations
- Typical joint(s)
- Lower limb and spine (below the level)
- The investigation that identifies it
- The history gives it; image the cord if the level or function has changed
- Typical joint(s)
- Feet (hereditary neuropathy); the injected joint (steroid)
- The investigation that identifies it
- Family history with nerve conduction studies; a drinking history; a record of injections
Each of these is developed separately in syringomyelia, Chiari malformation, Charcot neuroarthropathy, diabetic neuropathy, spinal cord injury, myelomeningocele, hereditary motor and sensory neuropathies and, for the elbow, Charcot neuropathic joint of the elbow.
Clinical Diagnosis and Radiographs
The bedside sign that makes the diagnosis is the sensory pattern, not the joint. A cervical syrinx expands first through the crossing spinothalamic fibres in the anterior commissure, so it produces dissociated sensory loss: pain and temperature sensation are lost while light touch, vibration and proprioception are preserved. The loss lies over the shoulders and upper trunk in the classic "cape" or "shawl" distribution.
The rest of the neurological examination. Look for wasting and weakness of the small muscles of the hand (anterior horn involvement) and for lost upper-limb reflexes. A patient who cannot feel a pinprick over the shoulder but can feel light touch there has declared the cause of their destroyed joint.
Radiographs. The humeral head is resorbed and fragmented, with bony debris, in a disorganised 'bag of bones', and the shoulder is often grossly swollen with effusion. Classic teaching summarises the changes as the 6 Ds.
6 Ds
Hook:The 6 Ds of a Charcot joint: Destruction, Density, Debris, Dislocation, Disorganisation, Distension.
Atrophic versus hypertrophic. Charcot joints take two radiographic forms, and the limb predicts which. The upper limb, and syringomyelic joints in particular, tend to the atrophic pattern: pure osteolysis and resorption of the humeral head with little new bone, so the head appears to dissolve or be "licked" away. The hypertrophic pattern, with exuberant sclerosis, osteophyte and periosteal new bone and the full 6 Ds, is more characteristic of the weight-bearing lower limb, as in the diabetic Charcot foot. At the shoulder, expect resorption and do not be reassured by the absence of florid new bone.
Differential Diagnosis
Exclude the dangerous mimics first. The grossly swollen, destroyed, fluid-filled shoulder can look like a tumour (an expansile mass) or infection (septic arthritis or osteomyelitis). Image appropriately and, when there is doubt, aspirate and/or biopsy before attributing the destruction to neuropathy.
Infection can coexist with a neuropathic joint rather than merely mimic it. A raised inflammatory response therefore does not exclude the diagnosis, and it does not excuse skipping the aspirate.
The two classic errors with a Charcot shoulder are at opposite ends. The first is mistaking the swollen, fluid-filled, destroyed joint for a malignancy or an infection, and either over-investigating destructively or missing a genuine concurrent tumour or sepsis. The second is operating too readily on a joint that tolerates surgery poorly.
Milwaukee shoulder is the other destroyed shoulder to know: a rapidly destructive cuff-tear arthropathy driven by basic calcium phosphate crystals, in an elderly patient with a large effusion and a massive cuff tear. It is distinguished by the absence of a neurological deficit and by pain that fits the destruction, where the Charcot shoulder is painless out of proportion. It is developed in the Milwaukee Shoulder and Rotator Cuff Arthropathy topics.
Management
Find and treat the cause. The cervical-cord MRI looks for the syrinx, and neurosurgical decompression may be indicated for a progressive one.
Support the joint. Joint care is largely supportive and is the default: protect the joint, modify activity, manage symptoms and maintain function, with a role for bracing.
Why surgery fails. The 'bag of bones' gives poor bone stock for fixation or fusion. More important, the neuropathy persists, so protective sensation is still absent and continued unperceived loading drives recurrent destruction, implant loosening and non-union. Rates of infection and instability are high, and the painless instability is often surprisingly well tolerated.
When surgery is considered. Surgery is selective and unreliable, with high complication and failure rates. It is considered for intractable pain, gross instability or functional loss, and is best undertaken only after the neurological process has been addressed and is quiescent, within a multidisciplinary team. The options all carry guarded outcomes and high complication rates:
- Resection arthroplasty
- Arthrodesis - technically difficult, with a high non-union rate in the neuropathic joint
- Arthroplasty - reserved for carefully selected cases, typically a constrained or reverse total shoulder replacement for the unstable, often cuff-deficient neuropathic shoulder
Counselling. The aim is function and symptom control, and the patient should not expect a normal joint. The procedures themselves are developed in the Shoulder Arthrodesis and Reverse Total Shoulder Arthroplasty topics.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A patient has a grossly swollen, destroyed shoulder on X-ray but very little pain. What is your diagnosis and what is the key investigation?”
“How would you manage a confirmed neuropathic shoulder due to syringomyelia?”
Recognition
- Gross destruction with little pain (destruction out of proportion to symptoms)
- Swollen, often unstable shoulder; radiograph 'bag of bones' / 6 Ds
- Mechanism: loss of protective sensation + proprioception (neurotraumatic + neurovascular)
Cause & key investigation
- Syringomyelia is the leading upper-limb cause (elbow and shoulder)
- MRI the cervical cord (syrinx, often with Chiari malformation)
- Also consider cervical cord lesions, peripheral neuropathy
Differential (exclude first)
- Tumour (expansile fluid-filled mass) - biopsy if doubt
- Infection (septic arthritis/osteomyelitis) - aspirate if doubt
- Do not attribute to neuropathy until mimics excluded
Management
- Largely supportive: protect joint, activity modification, bracing, symptom control
- Treat the cause (neurosurgical decompression of progressive syrinx)
- Surgery selective/unreliable (arthrodesis often fails; arthroplasty high risk); MDT
Evidence & Key Studies
Orthopedic manifestations of syringomyelia: a comprehensive review (with neuropathic shoulder case)
- Orthopaedic involvement in syringomyelia includes progressive spinal deformities (scoliosis, often with Chiari malformation) and neurogenic joint destruction, particularly affecting the shoulder and elbow.
- Charcot joints result from impaired proprioception and protective sensation; these orthopaedic complications may be early diagnostic clues yet are often under-recognised.
- Conservative treatment is the mainstay in stable cases, with surgery reserved for progressive disease; early recognition and multidisciplinary management prevent irreversible sequelae.
Neuropathic arthropathy of the shoulder in chronic syrinx mimicking malignancy
- Syringomyelia is a prevalent cause of Charcot arthropathy, notably affecting the elbow and less frequently the shoulder.
- Shoulder neuropathic arthropathy can present as an expansile fluid-filled mass with significant bone destruction, raising suspicion of malignancy - bone biopsy was needed to exclude tumour.
- Diagnosis relies on clinical signs, imaging and exclusion of other causes (including soft-tissue tumours); management spans conservative care to neurosurgical decompression and shoulder arthroplasty, within a multidisciplinary approach.
The link between syringomyelia and neurogenic destruction of the shoulder and elbow, the mechanism (impaired proprioception and protective sensation), and the conservative-mainstay/surgery-for- progressive-disease approach come from the cited Fadila review; the fact that syringomyelia is a prevalent cause of Charcot arthropathy, that the shoulder can present as an expansile fluid-filled mass mimicking malignancy requiring biopsy to exclude tumour, and the management spectrum (conservative to neurosurgical decompression and arthroplasty) from the cited Edara case report. The neurotraumatic/neurovascular pathophysiology and the radiographic '6 Ds / bag of bones' description are standard, well-established teaching. (See also our Charcot Neuroarthropathy and Septic Arthritis topics.)