Repetitive-stress osteolysis of the lateral clavicle | Young athletic adults, especially weightlifters | Diagnose on Zanca view and MRI | Most respond to activity modification; surgery is distal clavicle excision
- What it is: a painful, self-limiting but often recurrent osteolysis of the lateral end of the clavicle caused by repetitive microtrauma or direct injury to the acromioclavicular joint
- Who gets it: young athletic adults, especially weightlifters (bench press, overhead press, push-ups), overhead athletes, and manual labourers - classically called 'weightlifter's shoulder'
- How it presents: insidious aching pain over the AC joint, worse with cross-body adduction, overhead activity, and at night; local tenderness over the distal clavicle
- The key investigation: a Zanca view (15-degree cephalic tilt anteroposterior radiograph) shows osteopenia, cystic change, tapering or erosion of the distal clavicle; MRI confirms bone marrow oedema and excludes other pathology
- Management: stop the offending activity, modify technique, physiotherapy, and NSAIDs; if symptoms persist beyond 6 to 12 months, distal clavicle excision (open or arthroscopic) gives reliable relief
- “The Zanca view is essential - a standard AP shoulder often misses the subtle osteopenia and cystic change at the distal clavicle
- “Cross-body adduction test reproduces pain by compressing the AC joint - it is sensitive but not specific
- “Always ask about bench-press volume, overhead lifting, and training changes - the history is often diagnostic
- “MRI is the best second-line test when radiographs are equivocal or when you need to exclude rotator cuff or labral pathology
Overview
Distal clavicle osteolysis is a painful, non-infectious resorption of the lateral end of the clavicle that most often affects young athletic adults. It was first described in weightlifters and is still commonly called "weightlifter's shoulder", although it is now recognised in anyone who loads the acromioclavicular joint repetitively: overhead athletes, manual labourers and military personnel.
Why it matters. The condition is often misdiagnosed as rotator cuff tendinopathy, AC joint arthritis or a cervical radiculopathy. Once it is considered, the history of repetitive loading (especially bench press or overhead press) and the characteristic imaging on a Zanca view usually make the diagnosis straightforward. Most cases respond to activity modification and physiotherapy; a minority need surgical excision of the distal clavicle, which is a reliable and low-morbidity operation.
Anatomy
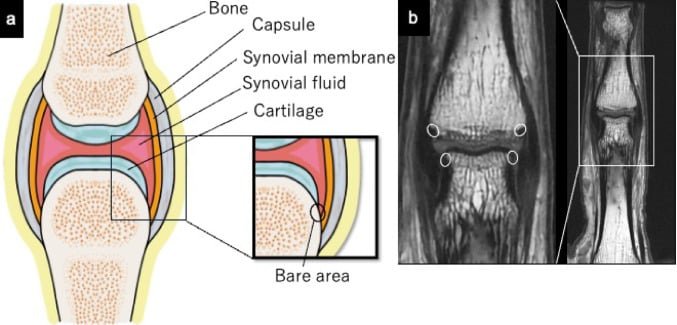
The joint. The acromioclavicular (AC) joint is a diarthrodial synovial joint between the lateral end of the clavicle and the medial facet of the acromion. A thin capsule reinforced by the superior and inferior AC ligaments surrounds it. The coracoclavicular ligaments (conoid and trapezoid) sit medial to the joint and are the main vertical stabilisers; they do not cross the joint itself but are critical to AC joint mechanics.
The disc and the load. A small meniscus-like intra-articular fibrocartilaginous disc degenerates with age; in young athletes it is still present and the joint surfaces are relatively congruent. The joint is subjected to compressive, shear and rotational forces with every overhead movement and loaded upper-limb exercise.
Pathophysiology
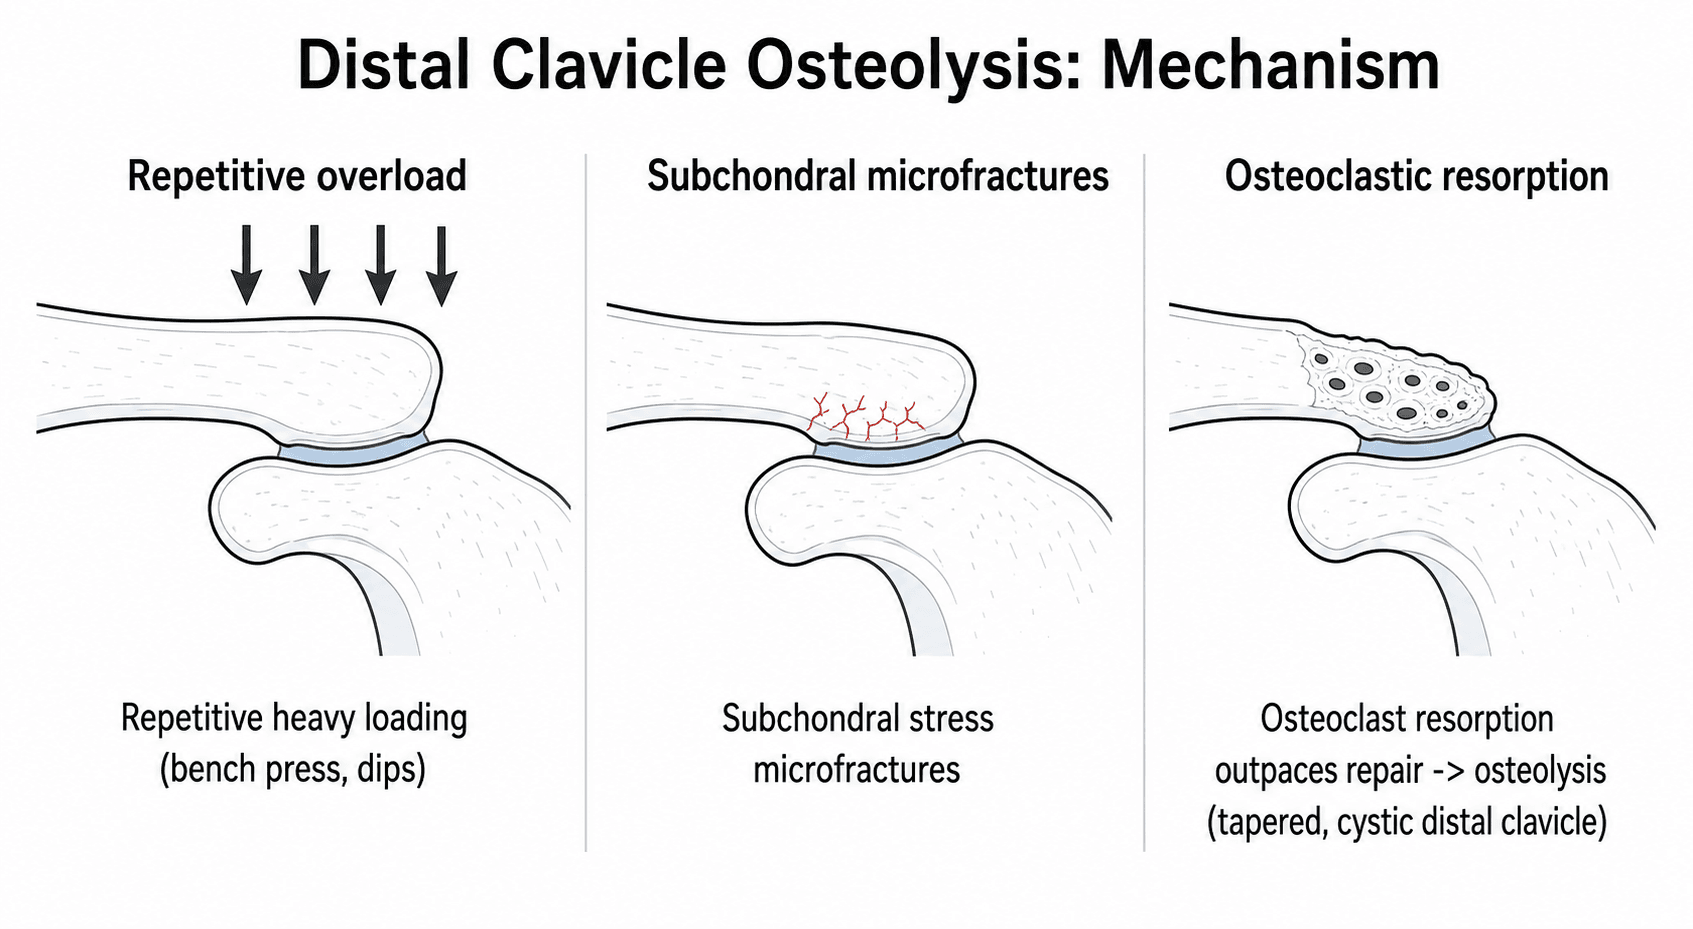
The leading theory. The exact mechanism is not fully understood. The leading theory is repetitive microtrauma causing an imbalance between bone resorption and formation at the distal clavicle, and three contributions are proposed:
- Mechanical overload: high-volume bench pressing, overhead pressing, push-ups and heavy manual work apply repeated compressive and shear forces across the AC joint. The distal clavicle, with its relatively small cross-sectional area and cortical shell, is vulnerable to stress-induced bone resorption.
- Vascular compromise: some authors propose that repetitive loading impairs the subchondral blood supply of the lateral clavicle, leading to avascular bone resorption similar to osteonecrosis.
- Inflammatory cascade: microfractures and trabecular damage trigger an inflammatory response with osteoclast activation, producing the cystic change and tapering seen on imaging.
What it is not. The process is not neoplastic, not infectious and not truly inflammatory in the sense of rheumatoid arthritis. It is a stress response of bone, and one that can stabilise or even reverse if the loading is removed.
Classification
There is no universally accepted radiographic staging system for distal clavicle osteolysis; the division that matters is by cause.
The commonest form. Repetitive microtrauma from weightlifting, overhead sport or manual labour (construction and similar work).
The patient. Classically a young adult male weightlifter or overhead athlete, but do not use that to exclude the diagnosis. Nearly a quarter of adolescent cases are female, the risk is highest where overhead sport is combined with supplemental weight training, and in adult MRI series the mean age is closer to 40.
Treatment. Activity modification is the cornerstone; surgery only after prolonged failure.
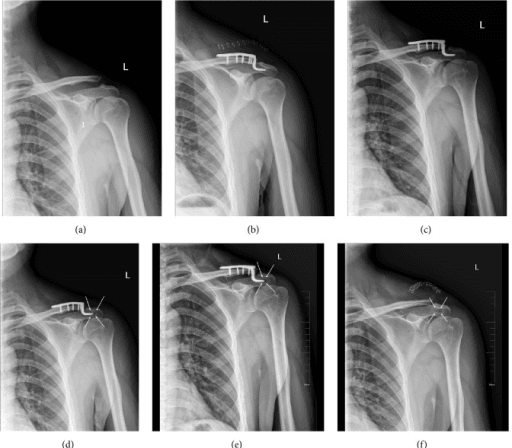
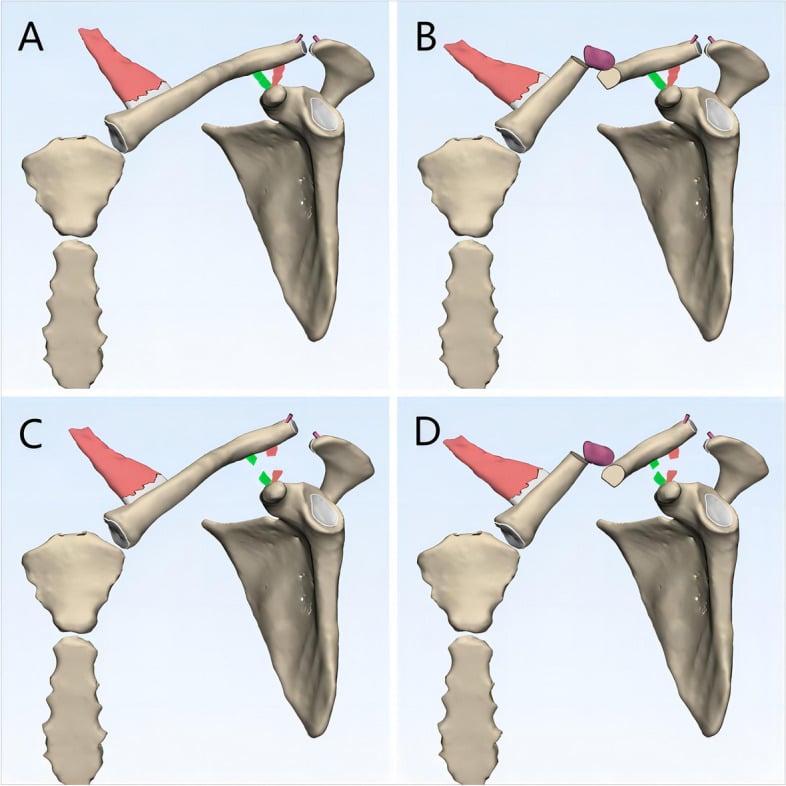
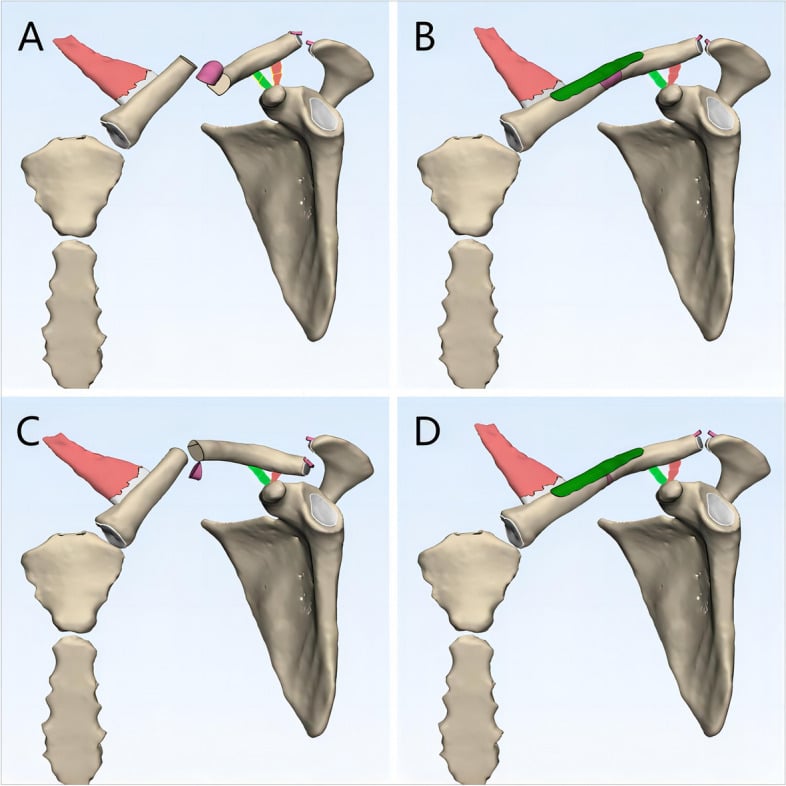
The iatrogenic form. Subacromial osteolysis beneath a clavicle hook plate is a distinct iatrogenic entity from atraumatic distal clavicle osteolysis, but it illustrates the same mechanically driven bone resorption around the lateral clavicle. Post-traumatic and iatrogenic forms are increasingly seen after AC joint stabilisation surgery.
Describing severity. In practice severity is described by the extent of bone loss (mild tapering versus marked osteolysis) and by the response to activity modification.
Clinical Presentation
History. The typical patient is a man aged 20 to 40 years with insidious aching pain over the AC joint, often localised to the lateral end of the clavicle. In weightlifters a rapid jump in training volume or intensity precipitates symptoms, so ask about bench-press volume, overhead lifting, push-ups and training changes: the activity history is usually more revealing than any single physical sign. The pain is:
- Worse with cross-body adduction (reaching across the chest), overhead activity and pushing movements
- Exacerbated by bench press, overhead press, dips and push-ups
- Often present at night, especially when lying on the affected side
The other histories. In post-traumatic cases there is a direct blow to the point of the shoulder or a fall onto an outstretched hand. In iatrogenic cases there is previous AC joint surgery with hardware or a synthetic ligament.
Inspection and palpation. There may be subtle swelling or prominence over the AC joint, but often the shoulder looks normal. Tenderness over the distal clavicle and AC joint is the most consistent sign; palpate with the thumb posterior to the clavicle and the index finger anterior to feel the joint line.
Range of motion. Active and passive movement is usually full, with pain at the extreme of cross-body adduction and at end-range flexion and abduction.
Special tests. Each is positive when it reproduces pain at the AC joint:
- Cross-body adduction test: the arm is passively brought into 90 degrees of flexion and then adducted across the chest. Pain over the AC joint is positive; the test compresses the joint and reproduces the symptoms.
- Active compression test (O'Brien test): the arm is forward-flexed to 90 degrees, adducted 10 to 15 degrees across the body and internally rotated with the thumb down, and the patient resists downward pressure. Pain localised to the AC joint (rather than deep in the shoulder) suggests AC joint pathology.
- Paxinos test: the examiner's thumb is placed on the posterior aspect of the acromion and the index finger on the distal clavicle; squeezing them together reproduces AC joint pain.
The cross-body adduction test is sensitive for AC joint pathology but not specific: it is positive in AC joint arthritis as well as osteolysis. Combine it with the patient's age, activity history and imaging.
Investigations
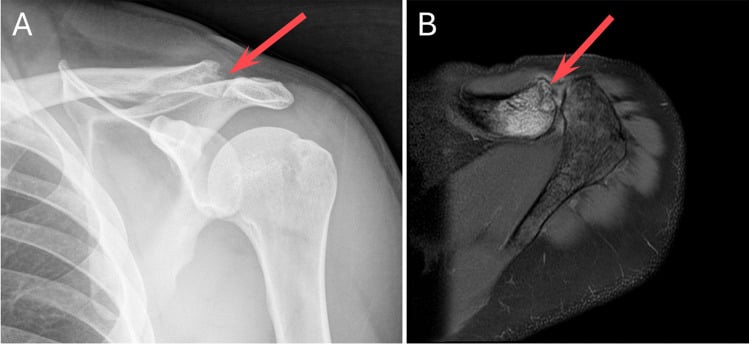
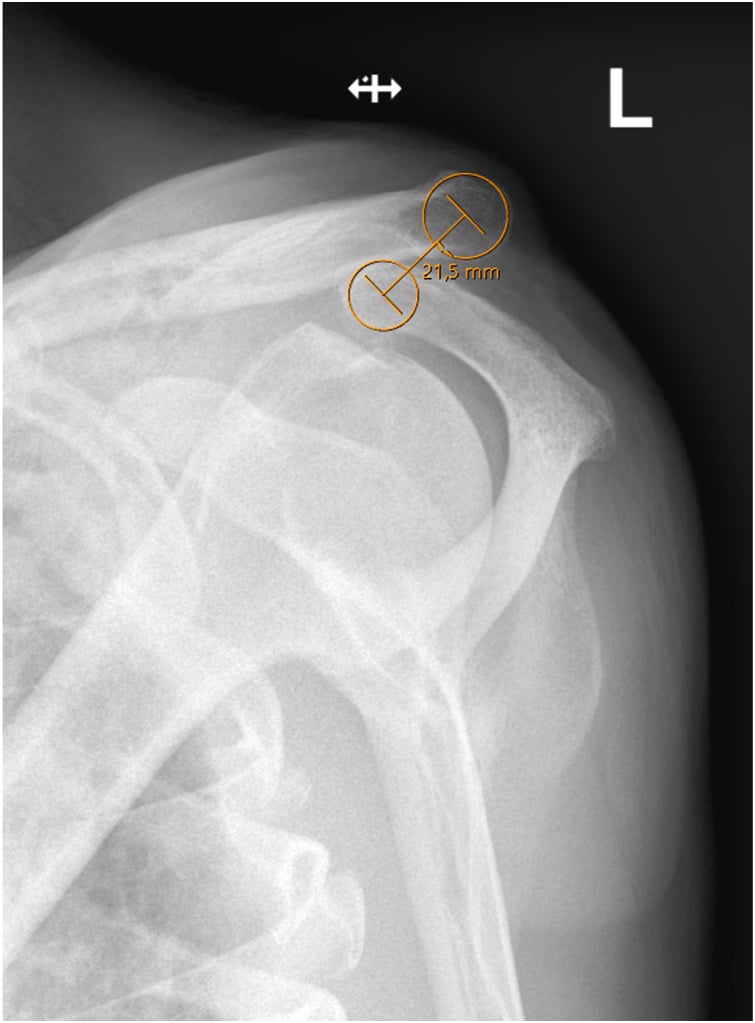
The Zanca view. The single most important radiograph is an anteroposterior view with a 15-degree cephalic tilt, centred on the AC joint, which projects the joint clear of the scapular spine and humeral head. A standard shoulder AP may miss the changes because the joint is superimposed on both, so request a Zanca view whenever the diagnosis is suspected. It shows:
- Osteopenia of the lateral clavicle
- Subchondral cystic change within the distal clavicle
- Tapering, pointing or erosion of the lateral clavicle tip, which loses its normal squared contour
- Widening of the AC joint space, due to bone loss rather than true dislocation
- Loss of the normal cortical margin at the distal clavicle
The acromion is not always spared. Osteolysis crosses the joint to involve the anterior acromion in roughly a third of cases, more often in men and with heavier bench-press loads, so acromial change does not exclude the diagnosis.
MRI. The best second-line investigation, indicated when:
- Radiographs are equivocal
- There is suspicion of associated pathology (rotator cuff tear, labral tear, cervical radiculopathy)
- Symptoms are atypical and the diagnosis is uncertain
It shows bone marrow oedema in the distal clavicle on fluid-sensitive sequences (T2 fat-suppressed or STIR), subchondral cystic change, joint effusion and capsular thickening, and the absence of a mass or destructive lesion, which helps to exclude tumour and infection.
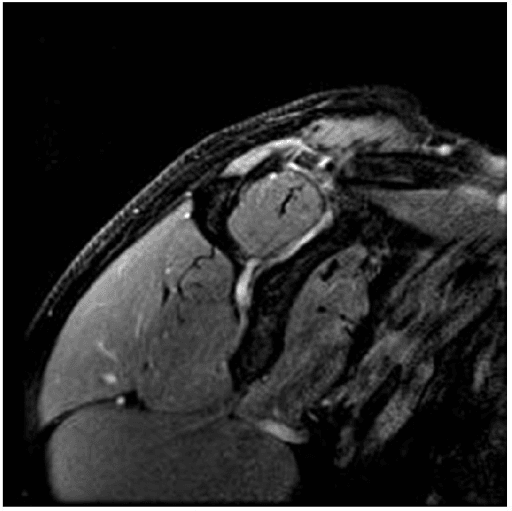
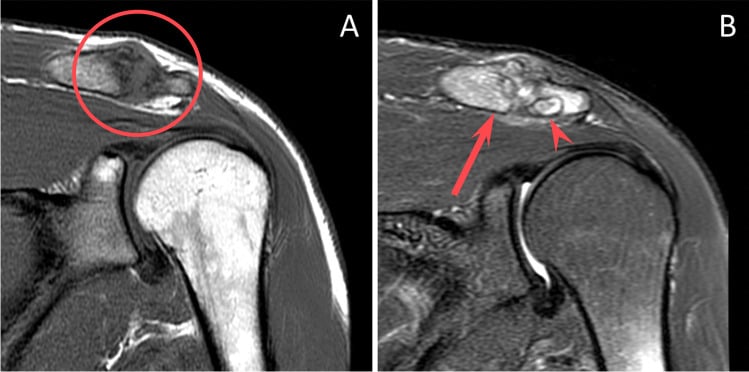
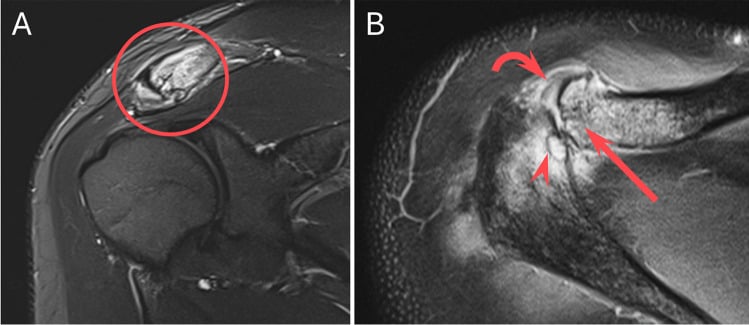
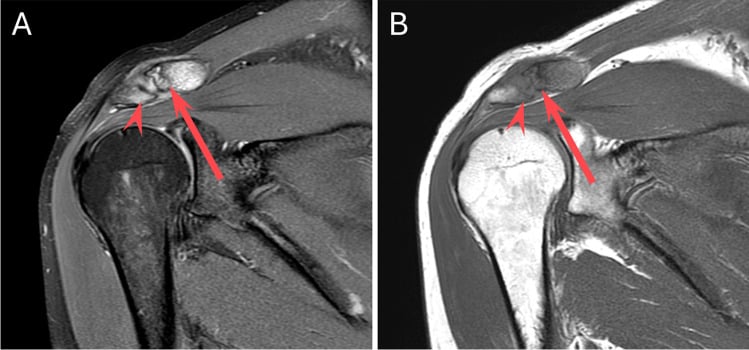
CT. Rarely needed, but it resolves subtle subchondral resorption better than plain radiographs and can delineate bone loss and cystic change when surgical planning is complex, for example after previous surgery or fracture.
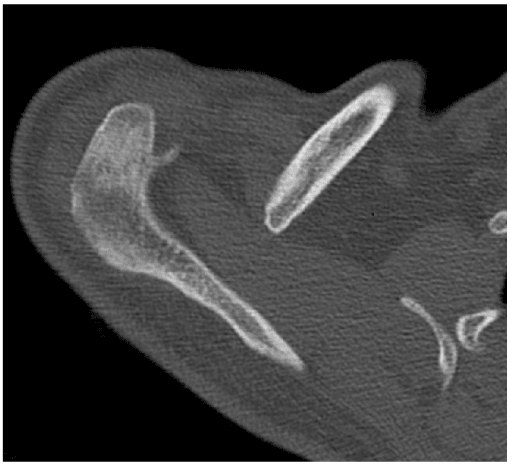
Bone scintigraphy and ultrasound. Scintigraphy is not routine, but will show focal increased uptake in the distal clavicle if performed. Ultrasound can demonstrate AC joint effusion and synovitis and guide injection, but is not diagnostic for osteolysis.
Differential Diagnosis: Causes of a Resorbed Distal Clavicle
Osteolysis is only one cause of a lucent, tapered or eroded distal clavicle. The examiner's favourite trap is the patient whose film looks like "weightlifter's shoulder" but whose resorption is systemic, so know the full list and the features that should redirect you.
- Clue that points to it
- Young athlete, repetitive loading or prior AC injury
- Typical pattern
- Usually UNILATERAL, isolated to the loaded shoulder
- Clue that points to it
- Subperiosteal resorption elsewhere (radial border of phalanges), raised calcium and PTH
- Typical pattern
- Often BILATERAL distal clavicle resorption
- Clue that points to it
- Other small-joint erosive disease, morning stiffness, seropositivity
- Typical pattern
- Bilateral, erosive, with marginal erosions
- Clue that points to it
- Skin changes, Raynaud phenomenon, acro-osteolysis of the tufts
- Typical pattern
- Resorption with soft-tissue calcinosis
- Clue that points to it
- Fever, raised inflammatory markers, aggressive destruction
- Typical pattern
- Rapid, ill-defined lysis crossing the joint
- Clue that points to it
- Older patient, night pain, weight loss, known primary
- Typical pattern
- Destructive lytic lesion, possible soft-tissue mass
Isolated, unilateral distal clavicle change in a young loader is osteolysis. Bilateral resorption should prompt thoughts of hyperparathyroidism (check calcium and PTH, look for phalangeal subperiosteal resorption) or rheumatoid / collagen-vascular disease; an aggressive lytic lesion with night pain or constitutional symptoms, or resorption in an older patient with constitutional symptoms, needs bloods (calcium, PTH, inflammatory markers, myeloma screen) and often MRI or biopsy to exclude infection or malignancy (metastasis, myeloma) before it is dismissed as weightlifter's shoulder.
AC joint osteoarthritis. Arthritis also causes AC joint pain and cross-body adduction tenderness, but it shows joint-space narrowing, osteophytes and subchondral sclerosis on both sides of the joint rather than osteolysis and cystic change concentrated in the distal clavicle. Age helps at presentation but is not the discriminator it looks like, because the two are sequential rather than alternative: in athletic teenagers followed for two years after atraumatic osteolysis, 71% had developed AC joint osteoarthritis against 35% of controls, with the joint widening to a mean of 5.0 mm against 2.4 mm, and the more marrow oedema at presentation the more likely the later arthritis.
The other mimics. Rotator cuff disease declares itself with a painful arc, weakness and positive impingement signs; cervical radiculopathy is the third diagnosis this condition is mistaken for.
Management
Non-operative treatment succeeds in the majority of cases and should be pursued for at least 6 months before surgery is considered.
Activity modification. Complete cessation of the offending activity (bench press, overhead press, push-ups, dips) is the single most important step. Many athletes resist it, but without it the other treatments fail.
Technique on return. When symptoms settle, return with a narrower grip, a reduced range of motion (avoiding deep descent to the chest), scapular retraction and a reduced load. Some athletes switch to dumbbells to allow more natural scapular movement.
Physiotherapy. Scapular stabilisation, rotator cuff strengthening, thoracic mobility and posture correction, all aimed at reducing abnormal loading across the AC joint.
NSAIDs. A short course (2 to 4 weeks) for pain relief and to reduce inflammation.
Corticosteroid injection. An intra-articular AC joint injection gives diagnostic confirmation and therapeutic relief. It is not curative, but it can break the pain cycle while rehabilitation proceeds.
Resection of more than 10 mm risks compromising the coracoclavicular ligament attachments and causing posterior clavicular instability: the clavicle subluxes posteriorly through the deficient AC joint. Over-resection that detaches the superior and posterior AC capsule produces a painful unstable clavicle that is far harder to salvage, while inadequate resection that leaves bony contact is the commonest reason for persistent pain. Aim for 5 to 10 mm and preserve the superior capsule and ligament.
Arthroscopic Distal Clavicle Excision: Direct vs Indirect
When the candidate says "arthroscopic excision", the examiner will ask how. There are two recognised arthroscopic routes, and each has a characteristic pitfall.
- Technique
- Portals placed directly into the AC joint from above (anterosuperior and posterosuperior)
- Strengths and pitfalls
- Excellent view of the whole distal clavicle and easy posterosuperior resection; but the space is small and the working room limited
- Technique
- Enter the subacromial space and resect the clavicle from below through the inferior AC joint
- Strengths and pitfalls
- Allows concurrent subacromial decompression and glenohumeral/cuff inspection; but the POSTEROSUPERIOR corner is easily UNDER-resected, the commonest cause of residual pain
Whichever route. The principles are the same: resect roughly 5 to 8 mm, within the 5 to 10 mm principle above; confirm an even gap throughout the arc of motion, especially at the posterosuperior corner; and preserve the superior and posterior AC capsule and ligaments to protect against posterior instability. "Co-planing" (shaving the adjacent acromial undersurface to match) is optional, and many surgeons avoid it to limit bleeding and reactive bone.
Complications
Of non-operative management. The main risk is chronic pain and functional limitation if the patient continues to load the AC joint. There is no risk of malignant transformation or systemic disease.
Of surgery.
- Resection inadequacy or excess: too little leaves symptomatic bone; too much risks posterior clavicle instability
- Posterior clavicle instability: from excessive resection or loss of the superior AC ligament and capsule; presents with painful clicking and prominence
- Infection: low risk (less than 1 percent) but possible with any open or arthroscopic procedure
- Neurovascular injury: the suprascapular nerve and cephalic vein are at risk during open approaches; careful dissection avoids them
- Persistent pain: if the diagnosis was incorrect or there is associated pathology (rotator cuff, cervical spine) that was not addressed
- Deltoid detachment: specific to open approaches where the deltoid is taken off the clavicle; reattachment failure causes weakness
Guidelines, Registries and Global Practice
- Diagnosis: there is no single international guideline for distal clavicle osteolysis, but the diagnosis is established by characteristic history (repetitive loading in a young adult), physical examination (AC joint tenderness, positive cross-body adduction), and imaging (Zanca view showing osteopenia, cystic change, and tapering of the distal clavicle). MRI is widely used as a second-line test to confirm bone marrow oedema and exclude associated pathology.
- Non-operative management: activity modification is the consistent first-line recommendation across sports medicine and shoulder surgery literature worldwide. Cessation of bench press, overhead press, push-ups, and dips for a minimum of 6 to 12 weeks is standard, with gradual return under physiotherapy guidance and technique modification.
- Surgical management: distal clavicle excision (resection arthroplasty) is the accepted operative treatment when non-operative care fails. Both open and arthroscopic techniques are described and yield comparable outcomes. The recommended resection is 5 to 10 mm of the distal clavicle, with preservation of the superior AC ligament and capsule to prevent posterior clavicle instability.
- Iatrogenic osteolysis: subacromial osteolysis after hook plate fixation is a recognised complication. Early plate removal (typically 3 to 6 months after implantation) is recommended to prevent this. Hardware removal is the first step; distal clavicle excision is reserved for persistent symptoms.
- Emerging therapies: platelet-rich plasma and other biologic injections have been reported in case series and small studies, but high-quality evidence is lacking and these are not yet standard of care.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 28-year-old man presents with 3 months of aching pain over the top of his right shoulder. He trains 5 days per week and has recently increased his bench press from 80 kg to 110 kg. On examination there is tenderness over the AC joint and pain with cross-body adduction. The shoulder AP radiograph is reported as normal.”
“A 35-year-old man had a clavicle hook plate inserted 8 months ago for a Rockwood type III AC joint dislocation. He now complains of persistent pain over the lateral clavicle and AC joint, worse with overhead activity. Radiographs show lucency around the hook tip and erosion of the undersurface of the acromion.”
“You are shown a Zanca view of a 32-year-old weightlifter with AC joint pain. The distal clavicle shows osteopenia, subchondral cystic change, and tapering of the lateral tip. The joint space appears widened. The examiner asks you to interpret the film and differentiate the findings from AC joint osteoarthritis.”
Definition and Mechanism
- Painful osteolysis of the lateral clavicle from repetitive microtrauma
- Classic in weightlifters (bench press, overhead press)
- Also post-traumatic and iatrogenic (hardware-related)
- Stress-induced bone resorption, not infection or tumour
History and Examination
- Young adult, insidious AC joint pain, worse with cross-body adduction
- Recent increase in training volume or intensity
- Tenderness over distal clavicle; cross-body adduction test positive
- O'Brien and Paxinos tests may localise pain to AC joint
Imaging
- Zanca view (15-degree cephalic tilt AP) - shows osteopenia, cysts, tapering
- MRI for equivocal cases or associated pathology - bone marrow oedema in distal clavicle
- CT rarely needed; ultrasound for injection guidance only
Management
- Activity modification first - stop bench press, overhead press, push-ups
- NSAIDs, physiotherapy (scapular stabilisation), AC joint injection
- Surgery: distal clavicle excision (5-10 mm), open or arthroscopic
- Preserve superior AC ligament; do not resect more than 10 mm
Evidence
Frequency, Imaging Findings, Risk Factors, and Long-Term Sequelae of Distal Clavicular Osteolysis in Young Patients
- Retrospective review of 1,432 consecutive shoulder MRIs in 13-19 year-olds: atraumatic DCO present in 6.5% (93 patients), of whom 24% were female
- The combination of an overhead sport (basketball, volleyball, tennis, swimming) plus supplemental weight training was the key risk factor (odds ratio 38, p=0.01)
- 93% responded to conservative therapy; MRI showed distal clavicle marrow oedema, and oedema severity correlated with pain
- Long-term sequelae at 2 years: 71% developed AC joint osteoarthritis (vs 35% controls) with flattening of the distal clavicle and AC joint widening to a mean of 5.0 mm (vs 2.4 mm controls)
A Sports Medicine Clinician's Guide to the Diagnosis and Management of Distal Clavicular Osteolysis
- Comprehensive clinical review of distal clavicle osteolysis for sports medicine practice
- Emphasises activity modification as the cornerstone of treatment, with cessation of bench press and overhead loading
- Describes the Zanca view as the key radiographic investigation and MRI for equivocal cases
- Recommends distal clavicle excision (open or arthroscopic) for refractory cases after 6 to 12 months of non-operative care
Distal Clavicular Osteolysis Treated With Platelet-Rich Plasma: A Case Report
- Case report of refractory atraumatic distal clavicle osteolysis after failure of activity modification, analgesia and physiotherapy
- Treated with a single ultrasound-guided platelet-rich plasma injection of the acromioclavicular joint, with symptomatic improvement
- First published account of PRP used specifically for distal clavicle osteolysis (no prior efficacy studies existed)
Involvement of the Acromion in Cases of Distal Clavicular Osteolysis
- Retrospective MRI review of 128 cases of DCO in 127 patients (93 male, mean age 39.5 years, mean symptom duration ~13 months)
- Describes a variant in which osteolysis crosses the AC joint to involve the anterior acromion as well as the distal clavicle - present in 42 cases (32.8%)
- Acromial involvement was commoner in males (p=0.049); maximum bench-press weight was the only other significant associated factor (p=0.027), implicating load
- 62.5% reported weightlifting and 45.3% an antecedent trauma history