Laceration or Rupture | Zone Classification | Early Repair | Protected Mobilization
- Tibialis anterior is the most important extensor - always repair if injured
- Zone classification guides repair technique and prognosis (8 zones from muscle belly to toe)
- Early repair (within 2 weeks) gives best outcomes - delayed repair more difficult
- Protected mobilization balances tendon healing with preventing adhesions
- EDL tendons to lesser toes may not require repair if extensor digitorum brevis intact
- “TA rupture causes foot drop - unopposed plantar flexion during swing phase
- “EHL injury prevents hallux IP extension - important for propulsion
- “Multiple tendon injuries common with lacerations across dorsum of foot
- “Repair strength depends on suture technique - modified Kessler or Krackow preferred
Overview and Epidemiology
Extensor tendon injuries of the foot and ankle run from the acute laceration to the chronic degenerative rupture. The extensors lie more superficially than the flexor tendons and are more exposed to laceration, but they have better healing potential. Their paratenon is looser and their vascular supply from it more robust, their gliding requirements are less critical and their tensile loads lower. They still require formal repair for optimal function, the tibialis anterior above all.
Mechanism. The tendon is cut, torn, avulsed or worn through:
- Laceration - the most common, often from glass, machinery or sharp objects across the dorsum of the foot
- Closed rupture - the tibialis anterior is the most susceptible, usually at the musculotendinous junction or the insertion
- Avulsion - avulsion of the terminal extensor causes mallet toe
- Attrition rupture - from chronic inflammatory arthropathy or repetitive trauma
Who. Lacerations are most common in young active males aged 20-40; closed tibialis anterior rupture typically affects older patients, 40-60, with degenerative changes. Extensive lacerations commonly divide several tendons at once, and EHL injuries are often associated with tibialis anterior injuries because the two lie close together.
The tibialis anterior matters most. It is the most powerful dorsiflexor, providing 80% of dorsiflexion strength, and it is critical for toe clearance in swing. Its loss causes foot drop and an altered gait; the EHL can partially compensate but is inadequate alone. Explore any suspected injury, and repair it.
The other three. The EHL extends the hallux IP and MTP joints and matters in terminal stance and push-off; its loss impairs propulsion and causes clawing, and repair is strongly recommended. The EDL extends the lesser toes at the MTP and IP joints, but the extensor digitorum brevis provides backup extension at the MTP, so its loss is less severe and it is repaired when feasible. Peroneus tertius, an accessory dorsiflexor and everter, is the weakest and least important of the four, and repair is not always necessary.
Anatomy and Biomechanics
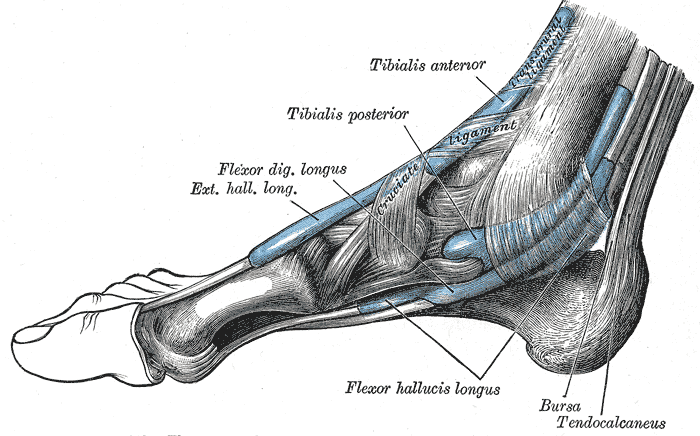
The anterior compartment. Four muscles and tendons, all supplied by the deep peroneal nerve:
- Origin
- Lateral tibial condyle, proximal lateral tibia, interosseous membrane
- Insertion
- Medial cuneiform and base of first metatarsal
- Action
- Dorsiflexion (primary), inversion (secondary)
- Nerve roots
- L4, L5
- Origin
- Middle anterior fibula, interosseous membrane
- Insertion
- Base of hallux distal phalanx
- Action
- Hallux IP and MTP extension, weak dorsiflexion
- Nerve roots
- L5, S1
- Origin
- Lateral tibial condyle, proximal fibula, interosseous membrane
- Insertion
- Middle and distal phalanges of the lesser toes (2-5)
- Action
- Toe extension at MTP and IP joints, weak dorsiflexion
- Nerve roots
- L5, S1
- Origin
- Distal anterior fibula (part of the EDL complex)
- Insertion
- Dorsal base of the 5th metatarsal
- Action
- Dorsiflexion, eversion
- Nerve roots
- L5, S1
Features worth knowing. The tibialis anterior has the largest cross-sectional area and is the most medial tendon at the ankle. The EDL divides into four slips on the dorsum of the foot. Peroneus tertius is absent in a substantial minority, and cadaveric and imaging series disagree widely on the figure, so check for it rather than assume it.
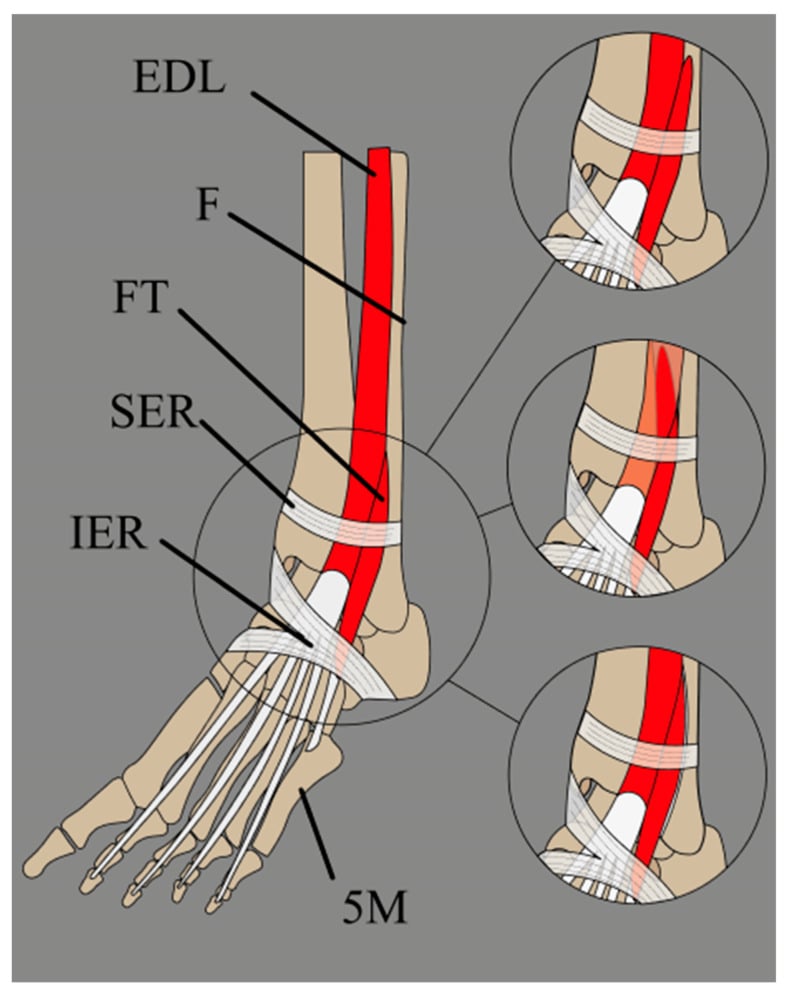
At the ankle (Zone 4). The tendons pass deep to the superior and inferior extensor retinacula, in order from medial to lateral tibialis anterior, EHL, EDL, peroneus tertius. The deep peroneal nerve and anterior tibial artery pass deep to the inferior retinaculum. The retinaculum prevents bowstringing and provides mechanical advantage.
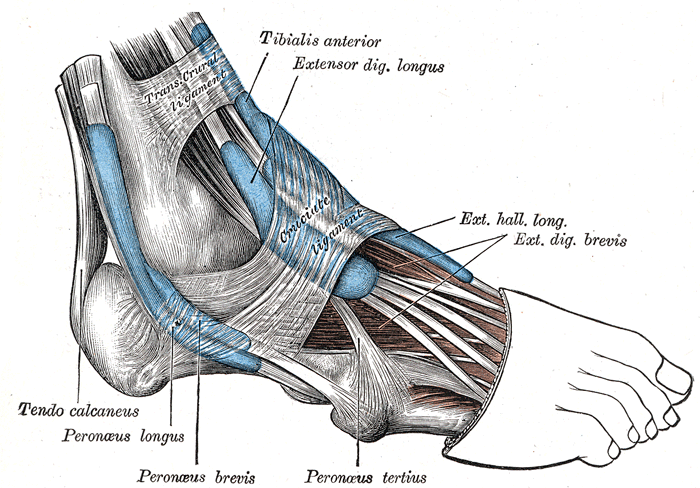
On the dorsum of the foot (Zone 5). The tendons diverge as they run distally. The extensor digitorum brevis arises from the calcaneus and inserts on the EDL tendons, so it provides MTP extension even when the EDL is divided. The EHL crosses superficial to the dorsalis pedis artery.
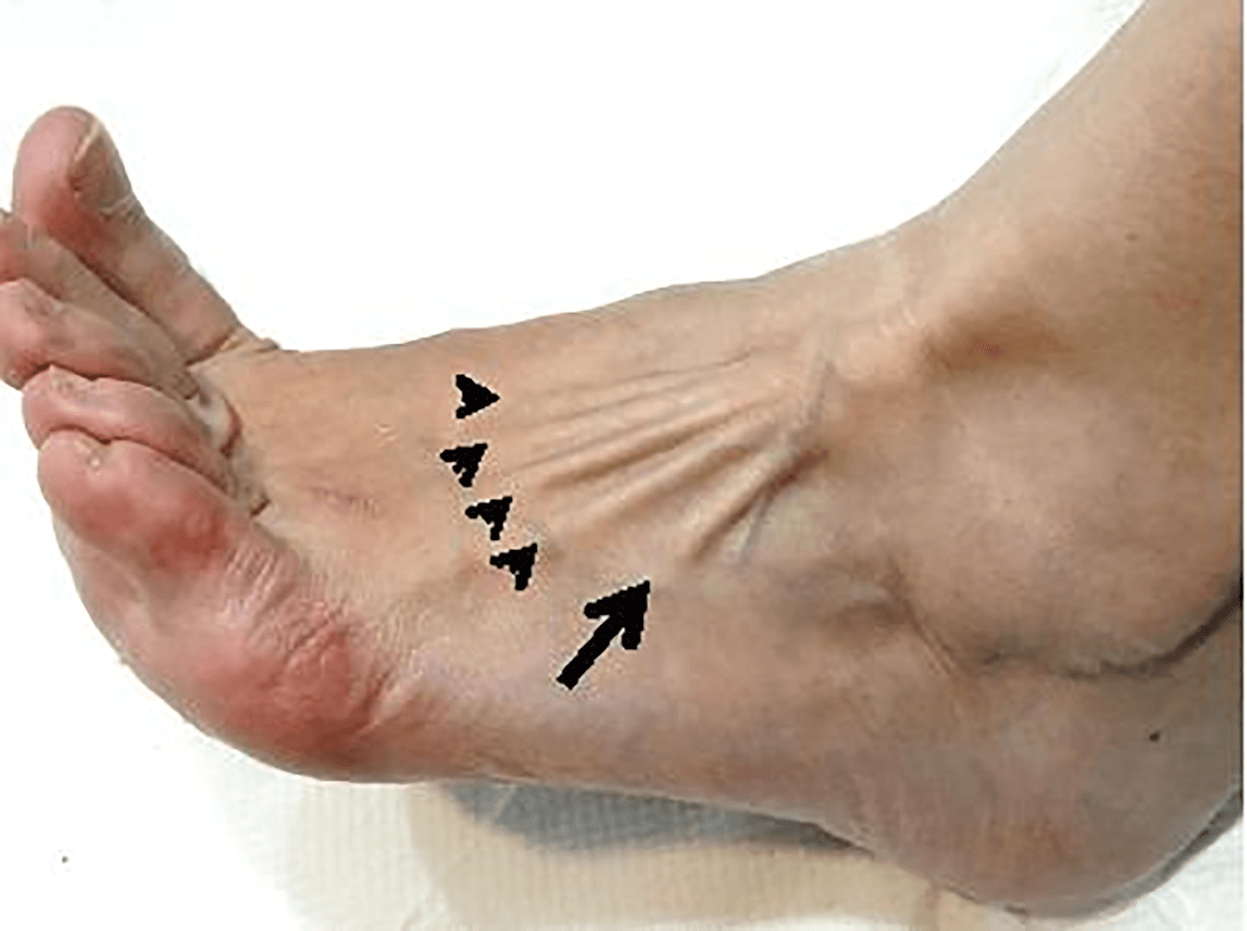
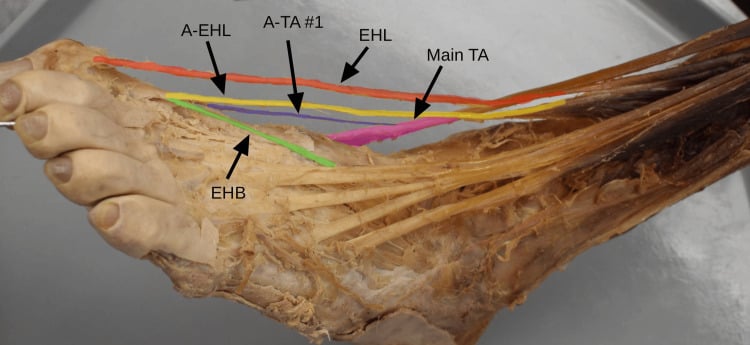
Blood supply. The paratenon provides a diffuse blood supply, and the anterior tibial artery gives small branches. Preserving it is critical during repair.
Loads and excursion. In normal gait the tibialis anterior carries 300-500N, the EHL 50-100N during push-off and the EDL 30-50N per toe, with peak loads at heel strike and toe-off. Excursion is limited compared with the hand extensors: 20-30mm for the tibialis anterior over the gait cycle, 15-20mm for the EHL and 10-15mm for the EDL.
The extensors in gait. In swing they contract to dorsiflex the foot and clear the toes; at heel strike they control plantarflexion eccentrically; in midstance they stabilise the ankle. In terminal stance the EHL holds the hallux extended for push-off.
Pathophysiology
Two entirely different diseases share this page. The wound in the emergency department and the painless foot drop in clinic are not variants of one another, and the literature cited here is dominated by the second while the teaching is usually built around the first. In Sammarco's nineteen tibialis anterior ruptures only three were traumatic; the other sixteen ruptured spontaneously. In Ouzounian's twelve, three patients were unaware of any acute event at all. Read that as the commonest way a tibialis anterior rupture actually presents.
Where the attritional rupture happens. The hypovascular watershed of the tibialis anterior lies roughly 5 to 30 mm proximal to its insertion on the medial cuneiform and first metatarsal base, between the proximal muscular supply and the distal periosteal supply, and spontaneous ruptures cluster here. The tendon also turns sharply under the superior and inferior extensor retinacula, so the same segment sees repeated angular load and compression against the retinacular edge.
Degeneration comes first. Contributing factors reported in these series and in the wider literature include increasing age, inflammatory arthropathy, diabetes, gout, local or systemic corticosteroid exposure and fluoroquinolone use. The tendon that ruptures without trauma was abnormal first.
The surgical consequence. The tendon ends are frayed and retracted rather than cleanly divided, which is why an interpositional graft was required in twelve of Sammarco's nineteen and why direct end-to-end repair is frequently impossible even when the diagnosis is made early.
Laceration is a different problem with a different timeline. Division is transverse and clean and the tendon quality is normal, so direct repair is usually achievable if the injury is addressed before the muscle contracts and the ends retract; Wong achieved primary EHL repair in 80% of cases. Zone matters because the tendon's cross-section, its retinacular constraint and the adjacent structures change along its length, and a dorsal midfoot laceration threatens the deep peroneal nerve and dorsalis pedis alongside the tendon. Contamination, not the tendon injury, drives the timing decision.
Why the deficit appears when it does. Loss of the tibialis anterior removes the principal dorsiflexor and the eccentric brake at heel strike, so the patient reports a slapping foot and, in swing, a steppage gait. The extensor digitorum longus and hallucis longus recruit as accessory dorsiflexors, which is why weakness can be partially masked on casual examination and why a palpable gap and the absent tendon bowstring on resisted dorsiflexion matter more than the presence of some dorsiflexion.
Tolerated losses. Loss of the extensor digitorum longus to the lesser toes is well tolerated while the extensor digitorum brevis is intact. Loss of the extensor hallucis longus is tolerated at rest but produces a functionally significant failure of hallux clearance and of terminal-stance push-off.
Classification Systems
The zone system. An anatomical classification of eight zones, running proximal to distal from muscle belly to toe and analogous to the hand extensor zones. The zone guides repair technique and prognosis and predicts adhesion risk: zones 1-3 carry the best prognosis, and zone 4, where the tendons are confined beneath the retinacula, is the one graded high for adhesions. Zones 6-8, at the MTP joints and phalanges, have limited excursion.
- Location
- Muscle belly, proximal and mid leg
- Typical injury
- Laceration or direct trauma
- Management
- Debridement, loose approximation of muscle and fascia
- Prognosis and adhesion risk
- Excellent healing potential, the muscle can reapproximate. Adhesion risk low
- Repair priority
- Moderate
- Location
- Musculotendinous junction, distal leg
- Typical injury
- Closed rupture more common (especially TA); a transition zone of variable strength
- Management
- Direct repair with nonabsorbable suture
- Prognosis and adhesion risk
- Good, but re-rupture risk higher than in purely tendinous zones. Adhesion risk low
- Repair priority
- Moderate
- Location
- Distal leg, above the ankle and before the retinaculum
- Typical injury
- Laceration, closed rupture of TA; full tendon
- Management
- End-to-end repair with core and epitenon sutures
- Prognosis and adhesion risk
- Excellent with appropriate repair. Adhesion risk low
- Repair priority
- High for TA/EHL
- Location
- Ankle, beneath the superior and inferior extensor retinacula
- Typical injury
- Laceration or closed rupture (TA); tendons confined
- Management
- Careful repair; consider retinacular release if tight
- Prognosis and adhesion risk
- Good, but adhesions to the retinaculum can limit motion. Adhesion risk high
- Repair priority
- Essential for TA and EHL
- Location
- Dorsum of foot, inferior retinaculum to MTP joints
- Typical injury
- Laceration (glass, lawn mowers), often several tendons
- Management
- Repair TA and EHL; consider EDL repair, as EDB provides backup
- Prognosis and adhesion risk
- Good for the major tendons. Adhesion risk moderate
- Repair priority
- High for TA/EHL
- Location
- Metatarsal heads and MTP joints
- Typical injury
- Laceration, sagittal band injury; the tendon broadens into an expansion
- Management
- Repair the expansion carefully
- Prognosis and adhesion risk
- Good, but stiffness possible. Adhesion risk moderate
- Repair priority
- Moderate
- Location
- Proximal and middle phalanx
- Typical injury
- Laceration or central slip disruption, the equivalent of the central slip in the hand
- Management
- Repair and splint in extension
- Prognosis and adhesion risk
- Good with immobilisation. Adhesion risk moderate
- Repair priority
- Moderate
- Location
- Distal phalanx, DIP joint level (terminal tendon)
- Typical injury
- Mallet toe: avulsion or laceration, similar to mallet finger
- Management
- Closed: splint in extension for 6 weeks. Open: repair
- Prognosis and adhesion risk
- Excellent with conservative treatment for closed injuries. Adhesion risk low
- Repair priority
- Low - splint often sufficient
Zone 2. The tibialis anterior most commonly ruptures at the musculotendinous junction in middle-aged patients with degenerative changes. It often occurs during eccentric loading, such as deceleration or downhill walking, and presents with sudden pain and foot drop.
Zone 4 (ankle/retinaculum) is critical because: (1) Tendons confined in tight compartments under retinaculum, (2) TA and EHL most vulnerable here, (3) Adhesions to retinaculum common, (4) Deep peroneal nerve at risk during exploration.
Zone 5. Lacerations here often involve several tendons, and every injured structure has to be identified. The tibialis anterior and EHL should always be repaired; the EDL to the lesser toes may not need repair if the EDB is intact (test by passive toe extension).
By mechanism. A clean laceration from a sharp object with minimal contamination is the best case for primary repair. A contaminated laceration, a dirty wound or a delayed presentation, is washed out and repaired later. An extensive laceration involving several tendons with nerve or vessel injury calls for staged reconstruction.
Closed ruptures. An acute rupture follows a sudden event with a distinct timeline and can be repaired primarily. A chronic rupture, of gradual onset or presenting late, often needs reconstruction. A degenerative rupture arises from underlying tendinopathy in older patients and brings poor tissue quality.
By severity. A partial laceration of less than 50% may not require repair if tendon continuity is maintained. A complete laceration of the tibialis anterior or EHL requires repair; the EDL and peroneus tertius are the exceptions described above. A complete rupture with retraction may require tendon advancement or a graft.
Clinical Assessment
History after a laceration. Establish the mechanism (sharp object, glass, machinery) and the timing, which decides between primary and delayed repair. Assess contamination, with tetanus status and infection risk, and ask about hand dominance and occupation, which set the functional demands.
History after a closed rupture. Ask whether the onset was a sudden pop or gradual weakness and what the patient was doing (eccentric loading, sport). Ask about antecedent tendinopathy or pain, and about diabetes, inflammatory arthropathy and fluoroquinolone use.
Look. Note the wound's location, extent and contamination. With a tibialis anterior rupture the foot rests plantarflexed, dropping under gravity when the patient sits, and the anterior ankle contour is lost; swelling reflects haematoma or oedema. In gait look for foot drop, a slapping foot and toe drag in swing: the toe catches, and running is difficult.
Feel. A palpable gap in tendon continuity, tenderness along the tendon's course, and crepitus, which suggests tendinopathy or a partial tear.
Test the tibialis anterior. Ask the patient to dorsiflex against gravity and test inversion, which the tibialis anterior also performs. Inability to heel walk is pathognomonic for tibialis anterior dysfunction, and testing of a ruptured tibialis anterior shows grade 0-1 power. Grade dorsiflexion and toe extension against manual resistance on the MRC scale and compare with the other side: 0 no movement, 1 flicker, 2 movement with gravity eliminated, 3 against gravity, 4 against resistance, 5 normal.
Test the EHL and EDL. Extend the great toe IP joint against resistance; loss indicates EHL injury. Test the MTP separately, because the EHB can compensate there. Test each lesser toe individually: the EDB extends the MTP, so preserved MTP extension with weak IP extension suggests an EDL injury, and an intact EDB can mask one.
Squeeze test. The tibialis anterior equivalent of the Thompson test: with the patient prone or sitting, squeeze the anterior compartment. The foot should dorsiflex; no dorsiflexion suggests a tibialis anterior rupture.
Tenodesis. Passive plantarflexion should make the toes extend and passive dorsiflexion should make them flex if the extensors are intact. Loss of the effect suggests complete tendon disruption.
Deep peroneal nerve runs with anterior tibial artery beneath inferior extensor retinaculum. Assess: (1) Sensation in first web space, (2) EDB function (extends toes at MTP), (3) Dorsalis pedis pulse. Injuries to nerve/artery require urgent vascular surgery consultation.
- Active Test
- Dorsiflexion, inversion
- Loss of Function
- Foot drop, slapping gait
- Compensation
- EHL weak dorsiflexion (inadequate)
- Active Test
- Hallux IP extension
- Loss of Function
- Weak push-off, claw hallux
- Compensation
- EHB at MTP only
- Active Test
- Lesser toe extension
- Loss of Function
- Weak toe extension
- Compensation
- EDB at MTP preserved
- Active Test
- Dorsiflexion, eversion
- Loss of Function
- Minimal functional loss
- Compensation
- TA dorsiflexes, peroneals evert
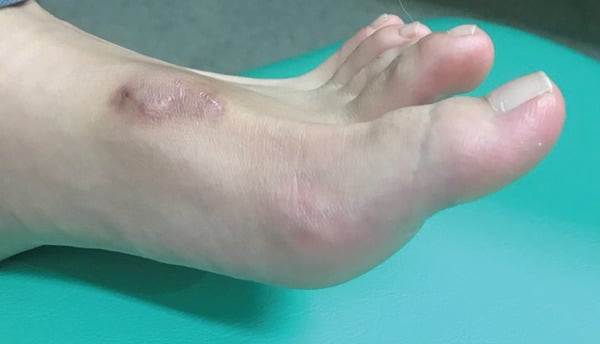
Differential diagnosis. A palpable tendon gap with focal anterior ankle weakness points to a tendon injury, but several non-tendinous causes of foot drop mimic it. Distinguishing them prevents an unnecessary operation.
- Key Discriminator
- Palpable gap, loss of anterior ankle contour, isolated DF weakness
- Sensation
- Normal
- Investigation
- Ultrasound or MRI shows tendon gap
- Key Discriminator
- Weak DF AND eversion AND EHL/toe extension; positive Tinel at fibular neck
- Sensation
- Loss over dorsum and first web space
- Investigation
- Nerve conduction studies, MRI of nerve
- Key Discriminator
- Back/leg pain, dermatomal sensory change, may have hip abductor weakness (L5)
- Sensation
- L5 dermatome change
- Investigation
- MRI lumbar spine, EMG
- Key Discriminator
- Exercise-induced pain and weakness that resolves with rest
- Sensation
- Transient first web space numbness
- Investigation
- Compartment pressure testing
- Key Discriminator
- Spasticity, hyperreflexia, pyramidal pattern weakness
- Sensation
- Variable, central pattern
- Investigation
- Brain imaging, neurology review
The single most useful bedside discriminator: an isolated dorsiflexion deficit with preserved eversion and intact sensation in the first web space favours a tibialis anterior tendon lesion. Add weak eversion, weak toe/hallux extension, and first web space numbness and you are dealing with a common (or deep) peroneal nerve problem instead.
Investigations
When to image. Clinical diagnosis is usually sufficient for an acute open laceration with obvious tendon injury: take radiographs, but MRI and ultrasound are not needed before exploration and repair in theatre. Imaging earns its place in closed ruptures, delayed presentations and surgical planning, where MRI or ultrasound confirms the diagnosis, measures the gap, judges tendon quality, identifies retraction and plans the reconstruction.
Radiographs. Indicated after all trauma to exclude fracture, in chronic injuries to look for a bony avulsion, and in mallet toe to identify a terminal phalanx avulsion. Take AP, lateral and oblique views of the foot, with AP and lateral views of the ankle if the injury is near it. The films are usually normal in a tendon injury, but may show an avulsion fragment at an insertion injury, or soft tissue swelling and gas if the wound is infected.
Ultrasound. Inexpensive, readily available and dynamic: it shows the gap and the retraction, assesses tendon continuity and quality, and allows real-time comparison with the other side. It is operator dependent, limited for deep structures and difficult when swelling is extensive.
MRI. The gold standard for soft tissue, multiplanar, and able to assess muscle quality (atrophy, fatty infiltration). T1 gives anatomical detail, T2 or STIR shows oedema and fluid in the tendon sheath, and proton density shows tendon morphology. Its indications:
- Closed rupture with an uncertain diagnosis
- Chronic injury, for surgical planning
- Suspected involvement of several tendons
- Associated soft tissue or bone injury
- Ultrasound
- Gap with retracted tendon ends
- MRI
- High signal, gap, retraction, surrounding oedema
- Ultrasound
- -
- MRI
- Tendon ends, scar tissue, muscle atrophy
- Ultrasound
- Hypoechoic defect, thickening
- MRI
- Increased signal within the tendon
- Ultrasound
- Thickened, hypoechoic, loss of fibrillar pattern
- MRI
- Thickening, intermediate signal
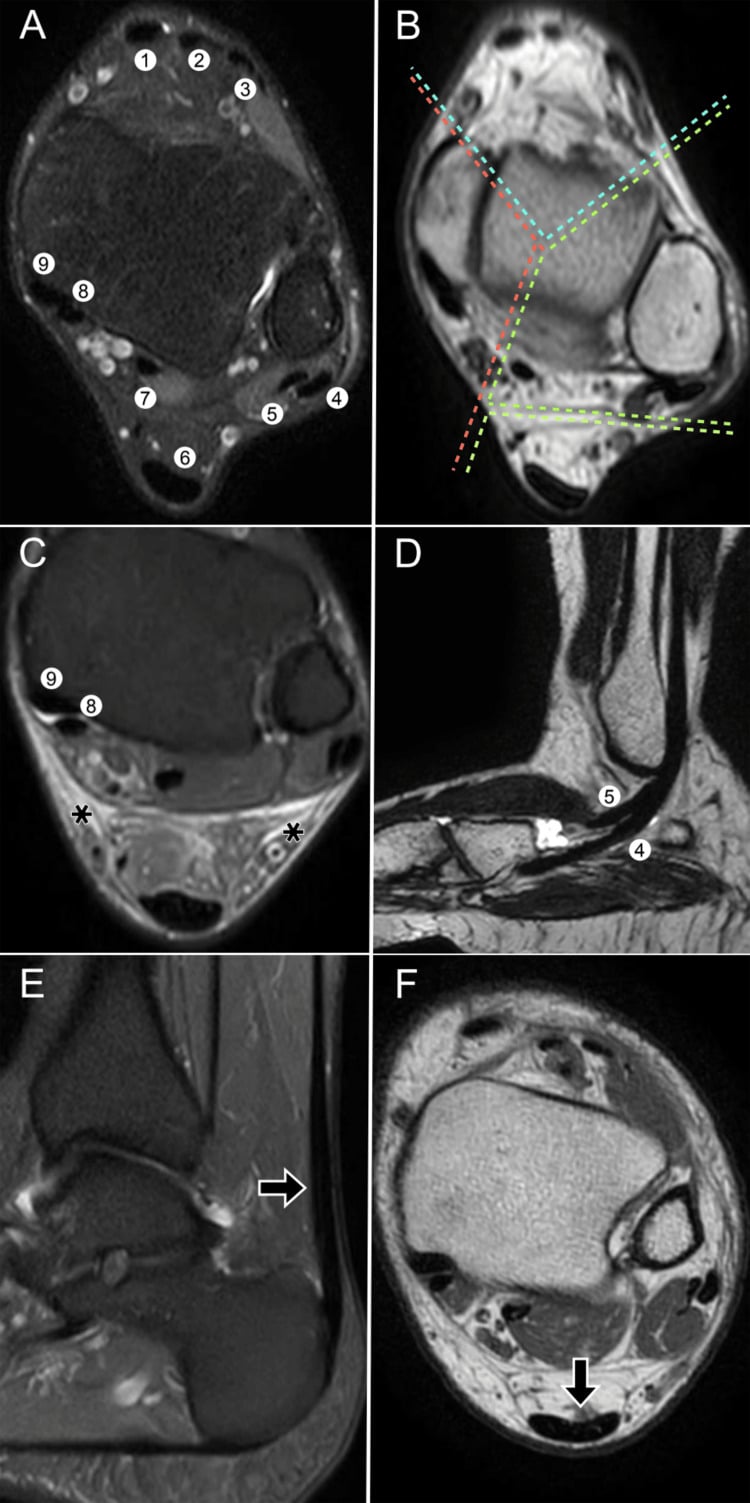
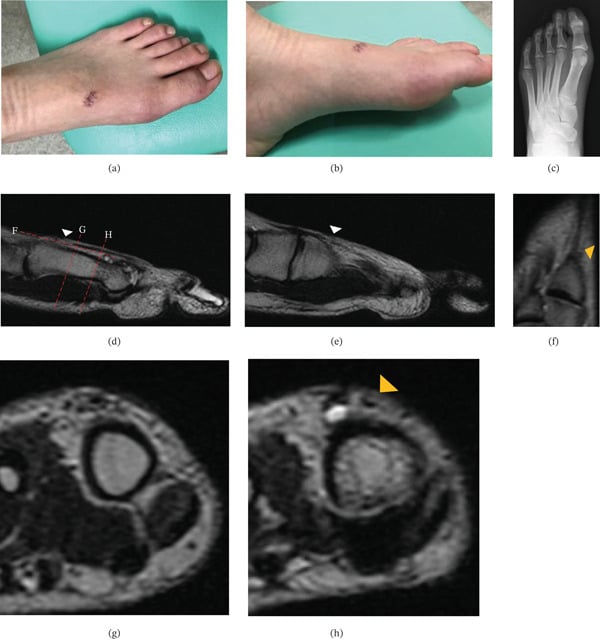
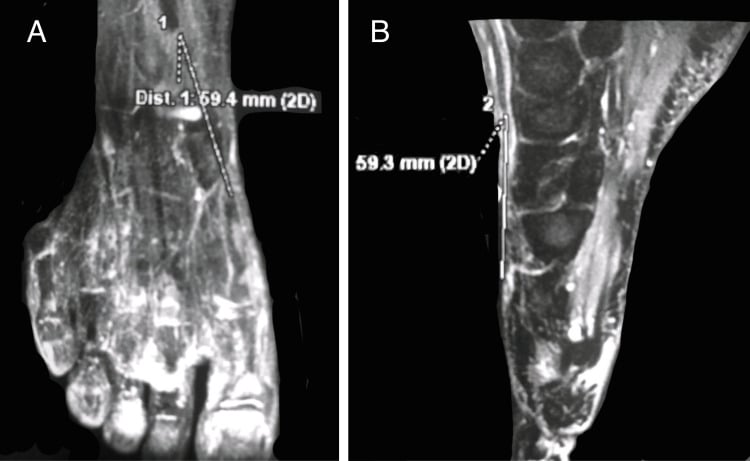
CT has a limited role: bony avulsion injuries and fracture displacement. Diagnostic local anaesthetic is not typically used, but may differentiate a tendon from a neurological cause of weakness.
Management Algorithm
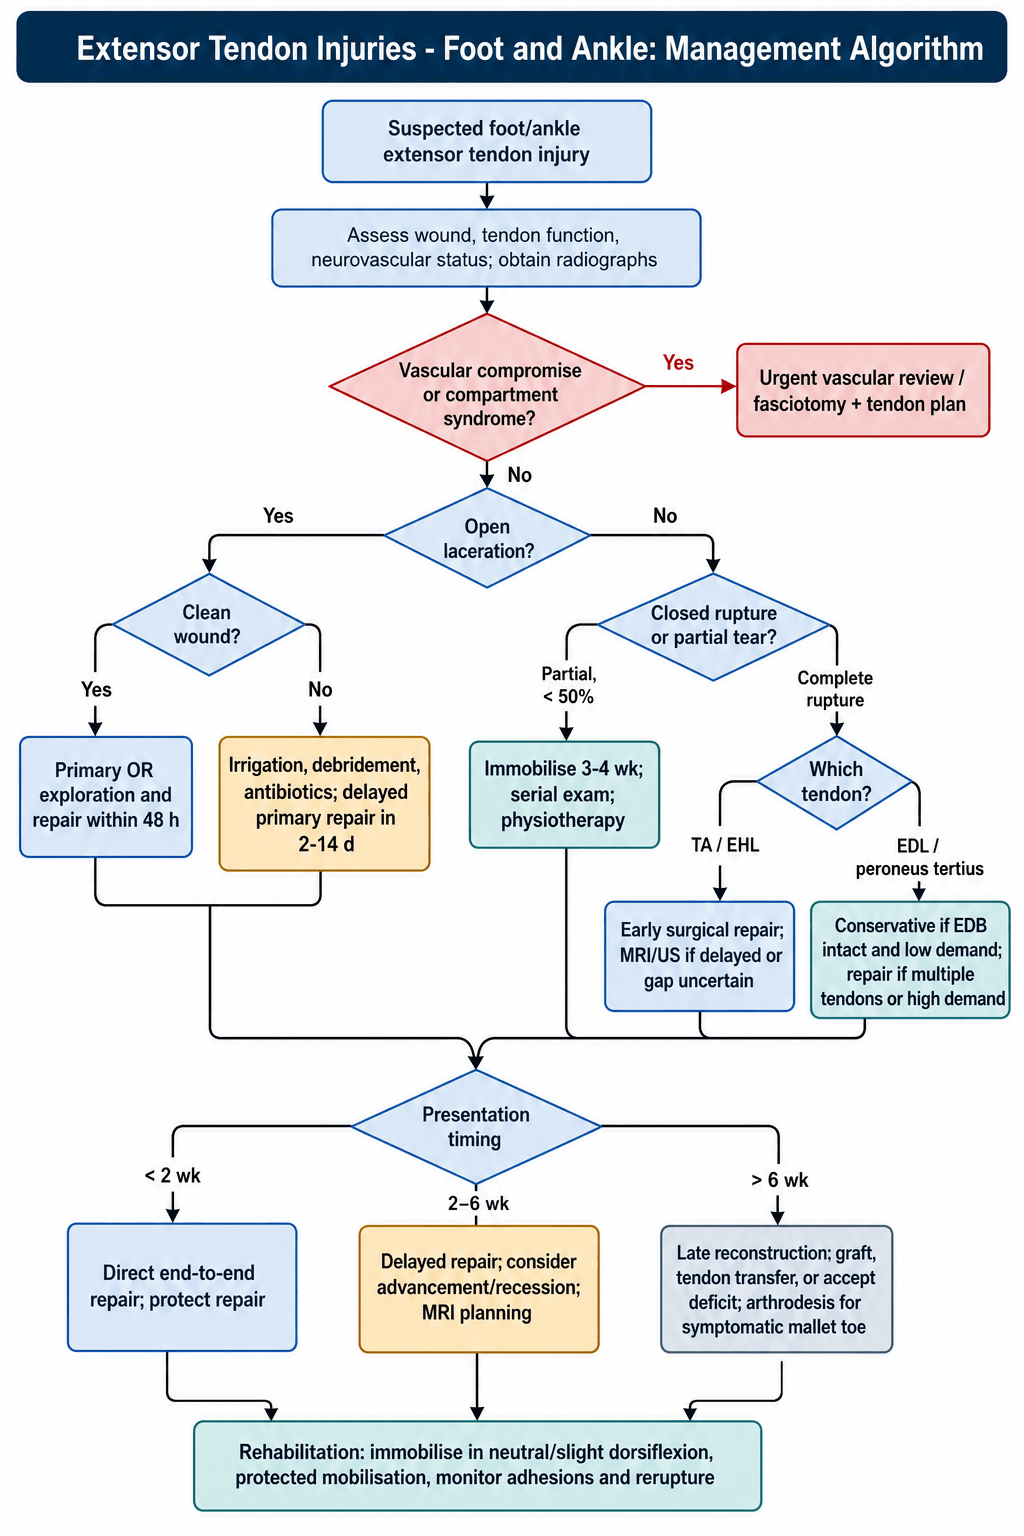
The acute assessment. Within 2 weeks of injury: history and examination to establish the diagnosis, the wound judged clean or contaminated, the deep peroneal nerve and dorsalis pedis documented, and radiographs to exclude fracture. Vascular compromise or compartment syndrome takes priority: urgent vascular review or fasciotomy, with the tendon plan to follow.
The decision that follows.
- Clean laceration - primary exploration and repair in theatre, within 48 hours
- Contaminated wound - irrigation, debridement and antibiotics, then delayed primary repair at 2-14 days
- Closed partial tear of less than 50% - immobilise for 3-4 weeks with serial examination and physiotherapy
- Complete closed rupture of the tibialis anterior or EHL - early surgical repair, with MRI or ultrasound if the presentation is delayed or the gap uncertain
- EDL or peroneus tertius - conservative if the EDB is intact and demand is low; repair if several tendons are involved or demand is high
Time since injury sets the technique. Under 2 weeks, direct end-to-end repair. At 2-6 weeks the tendon ends are still identifiable, but repair may require tendon advancement or recession, is less predictable than primary repair, and MRI is worth considering for planning. Beyond 6 weeks the ends are retracted and scarred and direct repair is usually not possible: the options are a tendon graft, a tendon transfer, or arthrodesis for a symptomatic mallet toe, and whether to reconstruct or accept the deficit depends on functional demands.
- Advantages
- Direct repair, no retraction, best outcomes
- Disadvantages
- May need to delay if contaminated
- Best For
- Clean lacerations
- Advantages
- Allows wound optimization, still repairable
- Disadvantages
- Some retraction, more difficult repair
- Best For
- Contaminated wounds after washout
- Advantages
- Allows full assessment, planned reconstruction
- Disadvantages
- Often needs graft or transfer, worse outcomes
- Best For
- Missed injuries, chronic ruptures
Conservative management. Indicated for:
- Partial lacerations of less than 50% with continuity preserved
- EDL injuries to the lesser toes with an intact EDB
- Peroneus tertius injuries
- Closed mallet toe
- Medical comorbidities precluding surgery
- Low functional demands
Immobilise in a boot or cast with the ankle in neutral to slight dorsiflexion, for 3-4 weeks for partial injuries, with serial examination to ensure no progression and physiotherapy for strengthening afterwards.
What conservative care achieves. No cited series on this page quantifies nonoperative outcome for partial tears; Al-Qattan's two partial EHL lacerations were managed without suturing and mobilised immediately, and both did well. Loss of the EDL to the lesser toes leaves minimal functional deficit if the EDB is intact. Outcome after splinting a mallet toe is not quantified in any source cited here.
Surgical indications.
- Complete tibialis anterior laceration or rupture - absolute indication
- Complete EHL laceration or rupture - strong relative indication
- EDL lacerations - repair when feasible
- Multiple tendon injuries
- Associated nerve or vascular injury
- Failed conservative management
Goals of surgery. Restore tendon continuity and the length-tension relationship, achieve a repair stable enough for early mobilisation, minimise adhesions, and restore function.
Surgical Technique
Planning.
- Mark the tendon course on the skin with the ankle in neutral
- Identify the injury zone from history and examination
- Plan the incision - curvilinear or longitudinal, avoiding skin creases
- Consent for possible nerve injury, adhesions, weakness and re-rupture
Set-up. Supine, with a thigh tourniquet and a bump under the ipsilateral hip if needed for positioning. An image intensifier should be available but is rarely needed; loupe magnification helps for distal repairs.
Incision by zone. In zones 3-4 (leg and ankle) a longitudinal incision centred over the tendon; in zone 5 (dorsum of the foot) a curvilinear incision that avoids crossing joints at right angles; in zones 6-8 (toes) a longitudinal incision over the dorsum of the toe. Extend the incision as needed to retrieve retracted tendon ends.
Dissection.
- Incise skin and subcutaneous tissue
- Identify and protect the superficial nerves (superficial peroneal branches on the dorsum)
- Identify the deep peroneal nerve, which runs with the anterior tibial artery beneath the retinaculum
- Locate and retrieve the tendon ends - for retracted ends, see below
- Debride the minimum of nonviable tendon, to preserve length
- Assess tendon quality - healthy tendon is white and glistening
Throughout, handle the tissue gently and strip as little as possible to preserve the blood supply.
Proximal retraction is common, especially with TA. Techniques to find tendon: (1) Passive motion - plantarflex ankle and watch for tendon movement, (2) "Milking" muscle belly proximally, (3) Extended incision if needed, (4) Contralateral side for reference anatomy.
Zone 4. The retinaculum may need to be partially released to reach the tendons; preserve it for later repair, since it prevents bowstringing. Identify the anterior tibial artery and deep peroneal nerve, and identify every structure, because several tendons may be injured.
Reconstructing an Irreparable EHL (Second-Toe EDL Transfer)
When the EHL cannot be brought together end-to-end, from retraction, tissue loss or a chronic laceration, active hallux extension can usually be restored rather than sacrificed.
Why not just fuse. A simple hallux IP arthrodesis removes deformity but leaves the toe with no active dorsiflexion, weakening toe clearance and push-off. A bridging reconstruction keeps the hallux moving.
Second-toe EDL transfer (deep transfer). The extensor digitorum longus slip to the second toe is divided and woven into the distal EHL stump, rerouting a nearby expendable extensor to power hallux dorsiflexion. Wong et al used it whenever the EHL ends were not opposable, and it avoided any need for allograft. The second toe tolerates the donor loss because the extensor digitorum brevis still extends it at the MTP.
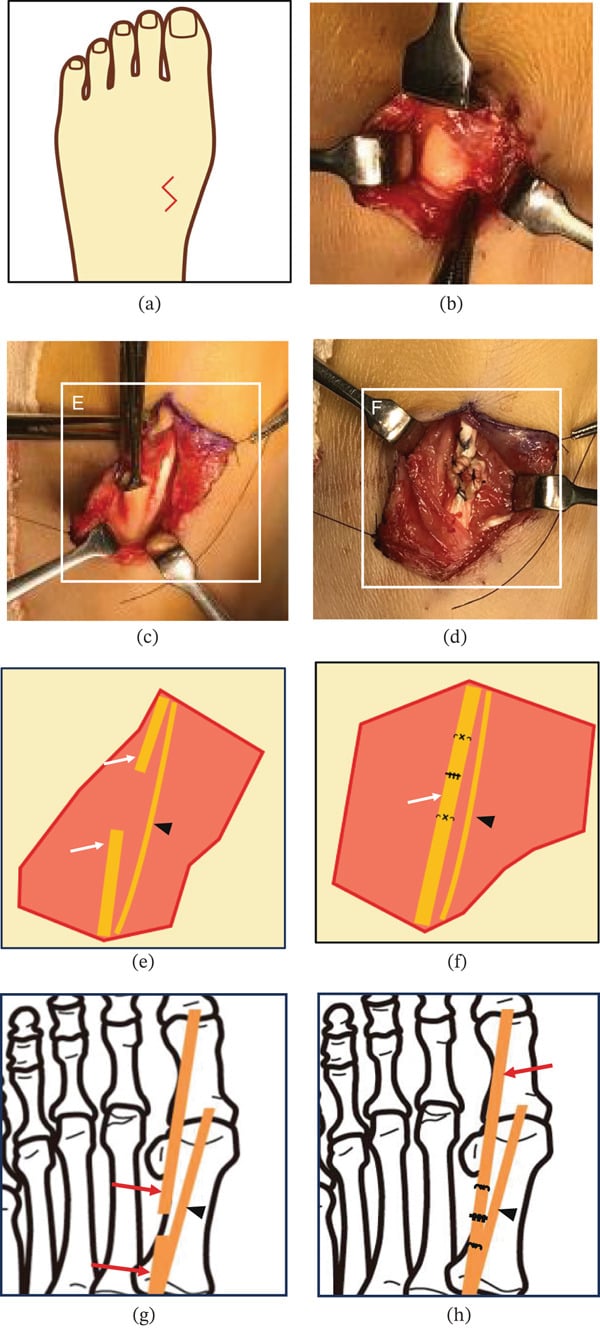
Free graft as the alternative bridge. A free tendon graft, plantaris or a toe-extensor slip, woven across the gap is the other graft-based option. The EHL-to-tibialis anterior transfer (Surgical Technique) solves the opposite problem, an irreparable tibialis anterior.
How to choose. Prefer a reconstruction that preserves active hallux extension (second-toe EDL transfer or a bridging graft) in any patient who needs push-off; reserve IP fusion for the genuinely low-demand patient or when no donor is available.
Chronic Tibialis Anterior Rupture: Interposition Graft and Gastrocnemius Recession
The Sammarco series (the largest reported) found that once a tibialis anterior rupture is more than a few weeks old, direct end-to-end repair is usually impossible: an interposition graft was needed in most cases, and a gastrocnemius recession may be required to balance the repair.
Why direct repair fails late. The ruptured tibialis anterior retracts and its muscle loses excursion, so the ends cannot be brought together at a physiological length. Bridging the gap needs an interposition graft.
The interposition graft. A free tendon graft (the options are listed under Repair Techniques) is Pulvertaft-woven into the proximal muscle-tendon unit and the distal stump or medial cuneiform, restoring a continuous dorsiflexion vector. In Sammarco's series outcomes were good regardless of age or delay.
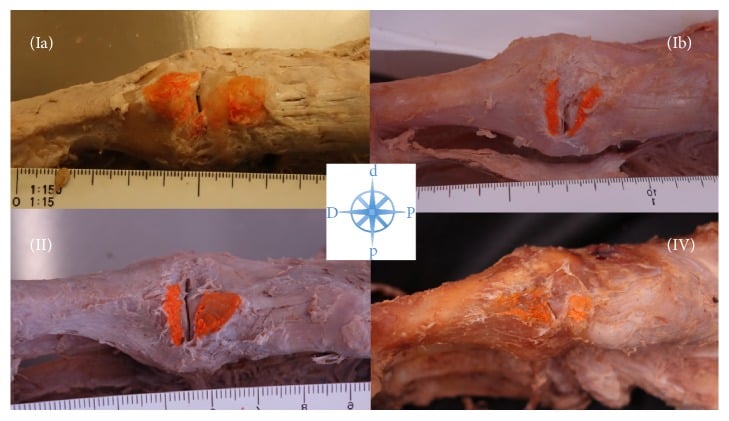
Why a gastrocnemius recession. With the tibialis anterior out of action, the unopposed gastroc-soleus pulls the ankle into a fixed equinus contracture. If the tight calf is left alone, the reconstruction is fighting a plantarflexion deformity and will over-tension or stretch out. A gastrocnemius (or gastroc-soleus) recession lengthens the posterior calf so the reconstructed dorsiflexor can hold the foot at neutral without excessive load, which protects the graft.
Tensioning. Set the graft with the ankle in neutral dorsiflexion, and confirm the foot rests plantigrade once the calf has been released.
Complications
Early complications arise in the first six weeks: re-rupture, infection, wound dehiscence, nerve injury, vascular injury and compartment syndrome. Late complications come after that: adhesions and stiffness, weakness, tendon elongation, chronic pain, mallet toe, functional limitation and claw toes.
Re-rupture (5-10% with modern repair techniques). Inadequate repair strength, premature weight bearing and poor compliance are the risk factors. It presents with sudden pain, loss of dorsiflexion and a palpable gap, and is treated by revision repair if early (within 2 weeks) or reconstruction if late.
Re-rupture is devastating complication. Prevention requires: (1) Strong repair - Krackow or Kessler core suture plus epitenon, (2) Protected mobilization - Non-weight bearing for 4 weeks, (3) Patient education - compliance with restrictions critical, (4) Graduated return - progressive loading over 8-12 weeks.
Infection (2-5%, higher with contaminated wounds). Contamination, delayed treatment, diabetes and immunosuppression raise the risk; it presents with wound erythema, drainage, fever and pain. Culture the wound, give antibiotics, and wash out a deep infection. Prophylactic antibiotics, meticulous wound care and early coverage prevent it.
Wound dehiscence (5-10%). Poor skin quality, tension, infection and poor vascularity are the risk factors. Manage with local wound care, delayed closure or a skin graft if needed; prevent it with tension-free closure and by avoiding incisions over bony prominences.
Nerve injury (2-5% iatrogenic). Deep peroneal nerve injury causes first web space numbness and EDB weakness; superficial peroneal nerve injury causes numbness on the dorsum of the foot. Most neurapraxias recover with observation, with neurolysis if needed; careful identification and protection during dissection prevents them.
Vascular injury. Injury to the anterior tibial artery is rare but catastrophic, presenting with loss of the dorsalis pedis pulse and foot ischaemia, and needs immediate vascular surgery consultation. Identify the artery during dissection and retract carefully.
Compartment syndrome (rare, less than 1%). Extensive trauma, prolonged tourniquet time and postoperative haematoma are the risk factors. Severe pain, a tense anterior compartment and pain on passive stretch call for urgent fasciotomy; monitor high-risk patients and avoid overly tight dressings.
Adhesions and stiffness (20-30% have some limitation). Zone 4 injuries, prolonged immobilisation and extensive dissection are the risk factors, and stiffness is more common than re-rupture. Limited ankle dorsiflexion and painful motion are treated with aggressive physiotherapy, and with tenolysis if severe and disabling. Gentle tissue handling, early protected mobilisation and retinacular release prevent them.
Weakness (10-20% have some residual weakness). From elongation at the repair site, muscle atrophy or adhesions, with dorsiflexion weaker than on the other side. Manage with strengthening exercises, orthotic support or acceptance; adequate tensioning, early mobilisation and strengthening prevent it.
Tendon elongation (10-15%). Gap formation, suture pull-through or an inadequate repair leave the patient weak despite an intact tendon on imaging. Plicate or reconstruct if severe; a strong repair technique and appropriate tensioning prevent it.
Chronic pain (5-10%). From neuroma, adhesions, tendinopathy or complex regional pain. Manage with physiotherapy, nerve blocks, or neuroma excision if one is identified; protect the sensory nerves and handle tissue gently.
Mallet toe after a Zone 8 injury (5-10% develop fixed deformity). A DIP flexion deformity with nail deformity is treated by splinting, or arthrodesis if symptomatic and rigid. Adequate extension splinting, 6 weeks minimum, prevents it.
Functional limitations. After tibialis anterior rupture or repair: difficulty with stairs (especially descending), a tripping risk from subtle weakness, and a slapping gait that may persist. After EHL rupture or repair: claw hallux, reduced push-off power and problems with shoe wear.
Claw toes. Occur with EDL over-pull or FDL tightness, cause metatarsalgia and shoe-fitting problems, and may require flexor tenotomy or transfer.
Postoperative Care and Rehabilitation
0-2 weeks. Stay in the back-slab or boot with the ankle in neutral dorsiflexion, non-weight bearing on crutches, the limb elevated above heart level to reduce swelling. Change the first dressing at 48-72 hours, keep it clean and dry, inspect the wound for infection, and remove sutures at 10-14 days. Simple analgesia (paracetamol, NSAIDs) and ice packs for swelling; avoid excessive opioid use.
2-4 weeks: protected immobilisation. Convert to a removable walking boot and continue non-weight bearing. With the boot removed, a therapist begins gentle passive dorsiflexion; there is no active dorsiflexion and no resisted exercise yet. The aims are to maintain ankle range in plantarflexion, prevent adhesions without stressing the repair, and reduce swelling and inflammation.
4-6 weeks: early active motion. Begin partial weight bearing in the boot at 4 weeks and progress to full weight bearing by 6 weeks, weaning from the boot as tolerated (typically at 6 weeks). Add gentle active dorsiflexion against gravity without resistance, ankle circles, toe flexion and extension and intrinsic strengthening, with gentle passive gastrocnemius and soleus stretching, avoiding aggressive stretching. The goals are active range, prevention of an Achilles contracture, and the start of muscle re-education.
6-12 weeks: strengthening. Light resistance begins at 6 weeks with a resistance band, progressing to strengthening of the tibialis anterior, EHL and EDL, proprioception work on a balance board and heel walking. Gait re-education, stair training, single-leg balance and sport-specific drills follow. The targets are strength at 80% of the other side, a normal gait and return to daily activities; sedentary work resumes at 8-12 weeks.
3-6 months: return to sport. Plyometrics, agility drills, sport-specific training and a running progression. Unrestricted daily activities and light sport return at 3-4 months, and full competitive sport at 4-6 months if the criteria are met, with strengthening continued:
- Full pain-free range of motion
- Strength approaching the contralateral side on isokinetic or manual testing - no cited source on this page sets a numerical threshold
- Normal gait without limp
- Sport-specific testing passed
Rehabilitation is complete when the functional goals are achieved and the patient is satisfied with the outcome.
Varying the protocol. Tibialis anterior repairs need longer protection (immobilisation may extend to 6 weeks) and a more conservative return to sport, because the tendon is critical for gait. EHL and EDL repairs carry less critical loads and can progress faster, with earlier active motion, guided by functional demands. A mallet toe is splinted in extension for 6 weeks continuously, then at night for a further 4-6 weeks, with buddy taping during mobilisation.
Balance is key in extensor tendon rehab: (1) Too aggressive = re-rupture, elongation, failure, (2) Too conservative = adhesions, stiffness, weakness. Modern approach favors protected early motion - passive/active-assisted ROM early, graduated resistance later. Goal: optimal healing AND function.
Expected outcomes. No study cited on this page grades results into an excellent/good/poor distribution, and the two series that did grade their outcomes are less flattering than such a distribution would suggest. Quote them directly.
Tibialis anterior repair (Sammarco, 19 tendons, mean 53 months). Dorsiflexion strength 5/5 in 15, 4/5 in 3, and 3/5 with a poor clinical result in 1. Recovery of functional dorsiflexion and improved gait in 18 of 19. Three patients required a second operation. Mean AOFAS hindfoot score 55.5 to 93.6, with no nonoperative comparison group.
EHL laceration repair (Al-Qattan, 17 patients, mean 3 months). By Lipscomb and Kelly grading the result was good in 4 and fair in 13, with no poor results. AOFAS hallux pain 40/40 in every patient and mean functional score 42.1 of 45. All returned to work at 2.5 to 5 months. The author's own conclusion is the one to counsel with: a completely normal range of hallux motion is difficult to obtain, but a pain-free return to work should be expected.
EHL repair, longer term (Wong, 20 of 23 patients, mean 5.1 years by telephone). Primary repair and second-toe EDL transfer together gave active hallux dorsiflexion in 19 of 20, and mean FAAM ADL and Sports scores were both 94.2% - but the range extends down to 58.3%, so a minority function considerably worse than the mean.
Guidelines, Registries & Global Practice
Global epidemiology:
- Tibialis anterior rupture is rare - the literature consists of small series and case reports rather than population data (largest surgical series 19 tendons).
- Two demographic peaks: young active patients with traumatic lacerations (glass, machinery, lawn mowers) and older patients (50-70 years) with atraumatic/degenerative rupture, often at the musculotendinous junction.
- Open extensor lacerations cluster in occupational and agricultural settings; dorsal foot lacerations frequently involve multiple tendons.
- Risk factors for atraumatic rupture: degenerative tendinopathy, diabetes, inflammatory arthropathy, corticosteroid injection and fluoroquinolone exposure.
Guideline landscape (no dedicated society guideline):
- Position on extensor tendon injury
- No injury-specific guideline; covered under general soft-tissue trauma. Endorses early diagnosis, repair of complete disruptions, and early controlled mobilization.
- Position on extensor tendon injury
- No specific BOAST; principles of the Open Fractures and Wound Management BOASTs apply to contaminated dorsal lacerations (early washout, antibiotics, soft-tissue cover).
- Position on extensor tendon injury
- Provides tendon repair principles - atraumatic handling, core plus epitenon suture, balanced tensioning, protected early motion.
- Position on extensor tendon injury
- No formal consensus; European practice mirrors individualized, demand-based decision-making.
- There is no implant or arthroplasty registry relevant here - these are soft-tissue repairs, not tracked by NJR/AJRR/AOANJRR-type registries. Outcome evidence therefore comes from institutional series, which limits the strength of any recommendation.
- Well-resourced settings: MRI/ultrasound for closed or delayed presentations; allograft and microsurgical nerve repair available; structured physiotherapy-led rehabilitation.
- Limited-resource settings: Clinical diagnosis predominates; autograft (hamstring, peroneus, FHL) preferred over costly allograft; reliance on casting and self-directed rehabilitation; later presentation increases the proportion needing reconstruction rather than direct repair.
- Document neurovascular status (deep peroneal nerve, dorsalis pedis) before surgery.
- Consent must cover infection, iatrogenic nerve injury, re-rupture, adhesions/stiffness and residual weakness.
- Counsel that delayed presentation worsens prognosis and may convert a simple repair into a graft reconstruction.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 32-year-old construction worker presents to ED 4 hours after stepping through a glass window. He has a 6cm laceration across the anterior ankle. On examination, he cannot dorsiflex the ankle against gravity and there is a palpable gap. Neurovascular status is intact. What is your assessment and management?”
“A 58-year-old recreational runner presents with 3-week history of anterior ankle pain and weakness after feeling a 'pop' while running downhill. Examination reveals weak dorsiflexion (3/5 power) and a palpable gap 5cm above the ankle. MRI confirms complete TA rupture at the musculotendinous junction with 4cm gap. He wants to return to running. How would you manage this patient?”
“A 25-year-old presents with a lawn mower injury causing extensive laceration across the dorsum of the foot at the mid-foot level. Wound is contaminated with grass and dirt. On examination, there is a 10cm laceration with obvious injury to multiple structures. She cannot dorsiflex the ankle or extend any toes. Pulses are intact but sensation in the first web space is diminished. How do you proceed?”
Four Main Tendons
- Tibialis Anterior - strongest dorsiflexor, ALWAYS repair
- Extensor Hallucis Longus - hallux IP extension, repair recommended
- Extensor Digitorum Longus - lesser toe extension, repair when feasible
- Peroneus Tertius - weakest, accessory dorsiflexor/everter, repair optional
Zone Classification (8 Zones)
- Zone 1-2: Muscle belly and MTJ - good healing, TA rupture common at MTJ
- Zone 3: Distal leg - primary repair with core plus epitenon
- Zone 4: Ankle/retinaculum - CRITICAL zone, adhesion risk high
- Zone 5: Dorsum foot to MTP - multiple tendon injuries common
- Zone 6-8: MTP and phalanges - mallet toe at Zone 8
TA Rupture Clinical Features
- Dorsiflexion weak or absent (0-2/5 power)
- Foot drop and slapping gait
- Palpable gap anterior ankle
- Cannot heel walk or lift foot against gravity
- MTJ rupture most common (Zone 2)
Surgical Repair Technique
- Core suture: Krackow (strongest, 50-60N) or Kessler (30-40N)
- Add running epitenon (adds 15-20% strength)
- Ankle in neutral dorsiflexion for repair
- Primary repair ideal within 2 weeks
- Delayed primary 2-6 weeks, reconstruction more than 6 weeks
Rehabilitation Protocol
- 0-4 weeks: Non-weight bearing, gentle passive ROM
- 4-6 weeks: Progress to full weight bearing, active ROM
- 6-12 weeks: Strengthening with resistance, proprioception
- 3-6 months: Return to sport if criteria met (80-90% strength)
Key Complications
- Re-rupture 5-10% - prevented by adequate suture technique and compliance
- Adhesions 20-30% (especially Zone 4) - early motion helps prevent
- Infection 2-5% - higher with contaminated wounds
- Deep peroneal nerve injury - assess first web space sensation and EDB
- Weakness 10-20% - some residual deficit expected
Exam Traps to Avoid
- Not documenting neurovascular exam (deep peroneal nerve critical)
- Offering conservative management for active patient with TA rupture
- Using inadequate suture technique (simple sutures insufficient)
- Too aggressive rehab (risk re-rupture before 4 weeks)
- Not recognizing Zone 4 as critical zone for adhesions
High Yield Exam Points
- TA provides 80% of dorsiflexion - ALWAYS repair
- Zone 4 (retinaculum) worst outcomes due to adhesions
- Krackow suture strongest technique (50-60N breaking strength)
- Early protected motion superior to prolonged immobilization
- EDL repair optional if EDB intact (lesser toe function preserved)
- Surgical repair achieves 85% strength vs 60% conservative for TA
- Deep peroneal nerve runs with anterior tibial artery at ankle
Evidence Base
The literature on foot/ankle extensor tendon injury is low-level (case series, Level IV, and one comparative study). There are no randomized trials. Recommendations rest on small cohorts and biomechanical reasoning, so individualize by patient demand and tendon involved.
Surgical Repair of Acute and Chronic Tibialis Anterior Tendon Ruptures
- AOFAS hindfoot score improved 55.5 to 93.6 points
- Direct repair only in 7 of 19 - the rest needed interposition tendon graft
- 5/5 dorsiflexion strength regained in 15 of 19 cases
- Outcomes independent of age, sex or comorbidity; delayed cases more complex
Tibialis Anterior Ruptures: Operative versus Nonoperative Outcomes
- 8 operative versus 8 nonoperative, no statistically significant outcome difference
- Difference is confounded by selection bias (age/demand bimodality)
- Authors still recommend repair/reconstruction in young high-demand patients
- Nonoperative care is appropriate for low-demand elderly patients
Anterior Tibial Tendon Rupture: Individualized Reconstruction
- All 7 operatively reconstructed patients gained function and strength
- Reconstruction technique was individualized (repair, advancement, transfer)
- AFO improved function in 2 of the nonoperative patients
- Operative reconstruction recommended for suitable (active) patients
Repair of Acute Extensor Hallucis Longus Tendon Injuries
- Primary repair achieved in 80% of EHL injuries
- Active hallux dorsiflexion restored in 19 of 20 patients
- Mean FAAM ADL and Sports scores both 94.2%
- EDL-to-hallux transfer is a graft-free option when ends are not opposable
Open Extensor Hallucis Longus Lacerations: Zone-Based Treatment
- All 17 patients healed without infection or symptomatic neuroma
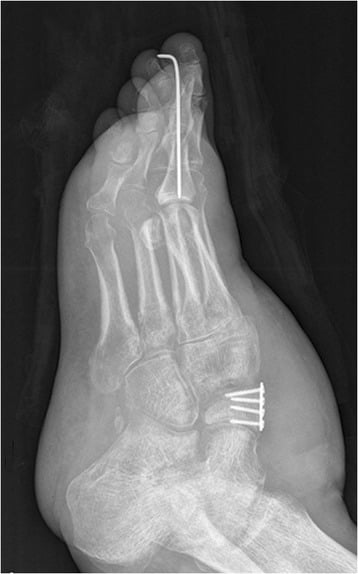
- Complete lacerations repaired and protected 6 weeks (K-wire plus cast)
- Partial lacerations did well with conservative care and early motion
- AOFAS hallux pain score 40/40 in all; mean function 42.1/45
Hallux Extensor/Flexor Tendon Injuries: Decision Framework
- Treatment is dictated by mechanism, site, timing and associated injuries
- Not every hallux tendon injury requires operative repair
- Define surgical goals (pain, motion, deformity) before operating
- Satisfactory results are expected when goals are clearly set
- No specific guideline for extensor tendon injuries (included in general soft tissue trauma)
- Recommend early diagnosis and repair for complete tendon disruptions
- Support early controlled mobilization protocols
- Primary repair within 2 weeks for complete TA and EHL disruptions
- Core suture technique (Krackow or Kessler) plus epitenon
- Protected early mobilization starting at 2-4 weeks
- EDL repairs recommended when feasible but not critical for lesser toes
- MRI or ultrasound for diagnosis of closed ruptures
- Some authors advocate repair of all EDL tendons
- Others suggest selective repair (only if EDB absent or patient high-demand)
- Consensus: Repair when feasible but low priority if EDB intact
- Traditional: 6 weeks strict immobilization
- Modern: Early protected motion starting at 2-4 weeks
- Consensus shifting toward early motion based on biomechanical and clinical data
- Some advocate up to 6 months for TA reconstruction
- Others suggest diminishing returns after 6 weeks
- Consensus: Best outcomes with repair within 6 weeks; reconstruction possible up to 6 months in motivated patients
References
-
Scaduto AA, Cracchiolo A. Lacerations and ruptures of the flexor or extensor hallucis longus tendons. Foot Ankle Clin. 2000;5(3):725-736. PMID: 11232406.
-
Markarian GG, Kelikian AS, Brage M, et al. Anterior tibialis tendon ruptures: an outcome analysis of operative versus nonoperative treatment. Foot Ankle Int. 1998;19(12):792-802. PMID: 9872465. doi:10.1177/107110079801901202.
-
Sammarco VJ, Sammarco GJ, Henning C, Chaim S. Surgical repair of acute and chronic tibialis anterior tendon ruptures. J Bone Joint Surg Am. 2009;91(2):325-332. PMID: 19181976. doi:10.2106/JBJS.G.01386.
-
Wong JC, Daniel JN, Raikin SM. Repair of acute extensor hallucis longus tendon injuries: a retrospective review. Foot Ankle Spec. 2014;7(1):45-51. PMID: 24334369. doi:10.1177/1938640013514271.
-
Al-Qattan MM. Surgical treatment and results in 17 cases of open lacerations of the extensor hallucis longus tendon. J Plast Reconstr Aesthet Surg. 2007;60(4):360-367. PMID: 17349589. doi:10.1016/j.bjps.2006.05.003.
-
Ouzounian TJ, Anderson R. Anterior tibial tendon rupture. Foot Ankle Int. 1995;16(7):406-410. PMID: 7550953. doi:10.1177/107110079501600705.
-
Bernstein RM. Spontaneous rupture of the tibialis anterior tendon. J Foot Surg. 1985;24(5):354-357.
-
Anagnostakos K, Bachelier F, Fürst OA, Kelm J. Rupture of the tibialis anterior tendon: a case report and literature review. Arch Orthop Trauma Surg. 2006;126(1):59-62.
-
Trouillas J, Fessy MH. Rupture of the anterior tibial tendon: 5 cases. Rev Chir Orthop Reparatrice Appar Mot. 2003;89(3):262-267.
-
Larsen E, Lauridsen F. Rupture of the tibialis anterior tendon. Injury. 1984;16(3):150-151.
-
Kashyap S, Prince R. Spontaneous rupture of the tibialis anterior tendon. Clin Orthop Relat Res. 1987;(216):159-161.
-
Christman RA. Foot and Ankle Radiology. Churchill Livingstone. 2003:425-430.
-
Kausch T, Rutt J, Schuler P. Ultrasonographic findings in tendon diseases of the ankle. Foot Ankle Surg. 2004;10(2):73-78.
-
Mengiardi B, Pfirrmann CW, Vienne P, et al. Anterior tibial tendon abnormalities: MR imaging findings. Radiology. 2005;235(3):977-984.