Nine Compartments | Calcaneal Fracture Association | Fasciotomy Controversy | Claw Toe Sequelae
- Foot has nine distinct compartments separated by fascial septa
- Calcaneal fractures cause compartment syndrome in up to 10 percent of cases
- Clinical diagnosis relies on pain out of proportion and pain on passive stretch
- Fasciotomy versus delayed reconstruction remains controversial
- Untreated leads to intrinsic-minus claw toes and permanent stiffness
- “Always measure pressures in calcaneal fractures with tense swelling
- “Central calcaneal compartment contains the lateral plantar nerve
- “Late claw toes result from intrinsic muscle necrosis and fibrosis
- “Fasciotomy incisions must address all nine compartments
Overview and Epidemiology
Foot compartment syndrome is a limb-threatening emergency, and one that is frequently underdiagnosed when it follows a calcaneal fracture or a Lisfranc injury. The foot's nine rigid fascial compartments leave little room for swelling, and a delayed diagnosis leads to irreversible muscle necrosis, intrinsic-minus claw toes, chronic pain and, in severe cases, amputation. Early pressure measurement and timely fasciotomy remain the only means of preventing these sequelae, yet controversy persists over whether every case that meets the pressure thresholds needs a fasciotomy.
Mechanism. The injuries that produce it:
- Calcaneal fractures - axial loading produces massive swelling within the calcaneal and central compartments, from bleeding from the bone and the surrounding soft tissues; pressures within the calcaneal compartment often exceed 40-60 mmHg
- Lisfranc fracture-dislocations - tarsometatarsal disruption bleeds into multiple interosseous and central compartments, the haemorrhage tracking along the tarsometatarsal joints
- Crush injuries - industrial or motor-vehicle trauma directly compresses the plantar compartments
- Tight casting - a circumferential cast applied to a swollen foot creates an iatrogenic compartment syndrome
- High-energy axial load - falls from height or motorcycle accidents
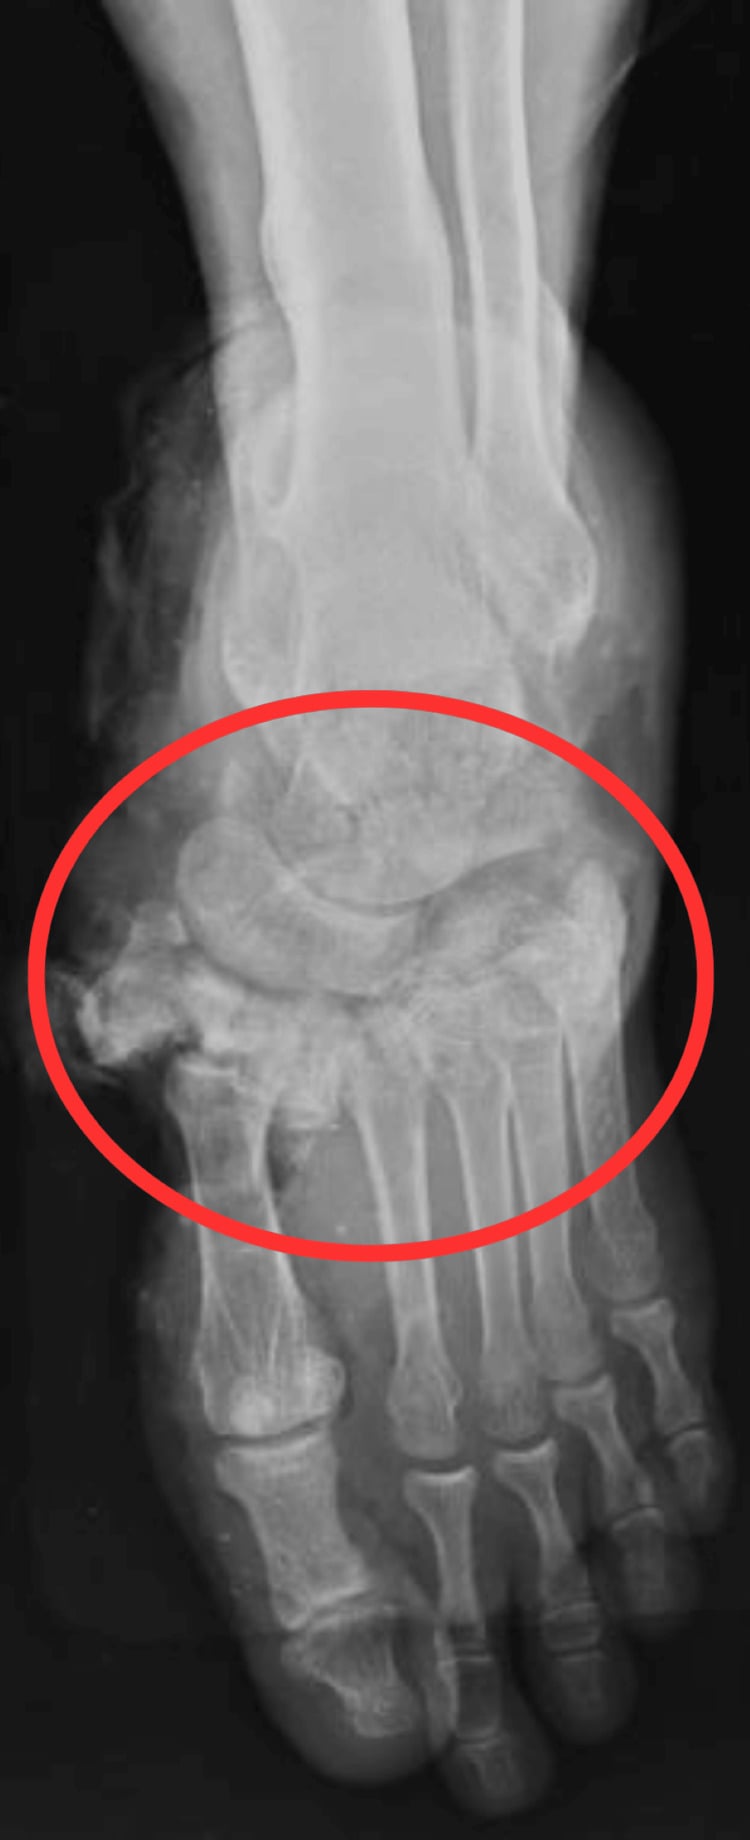
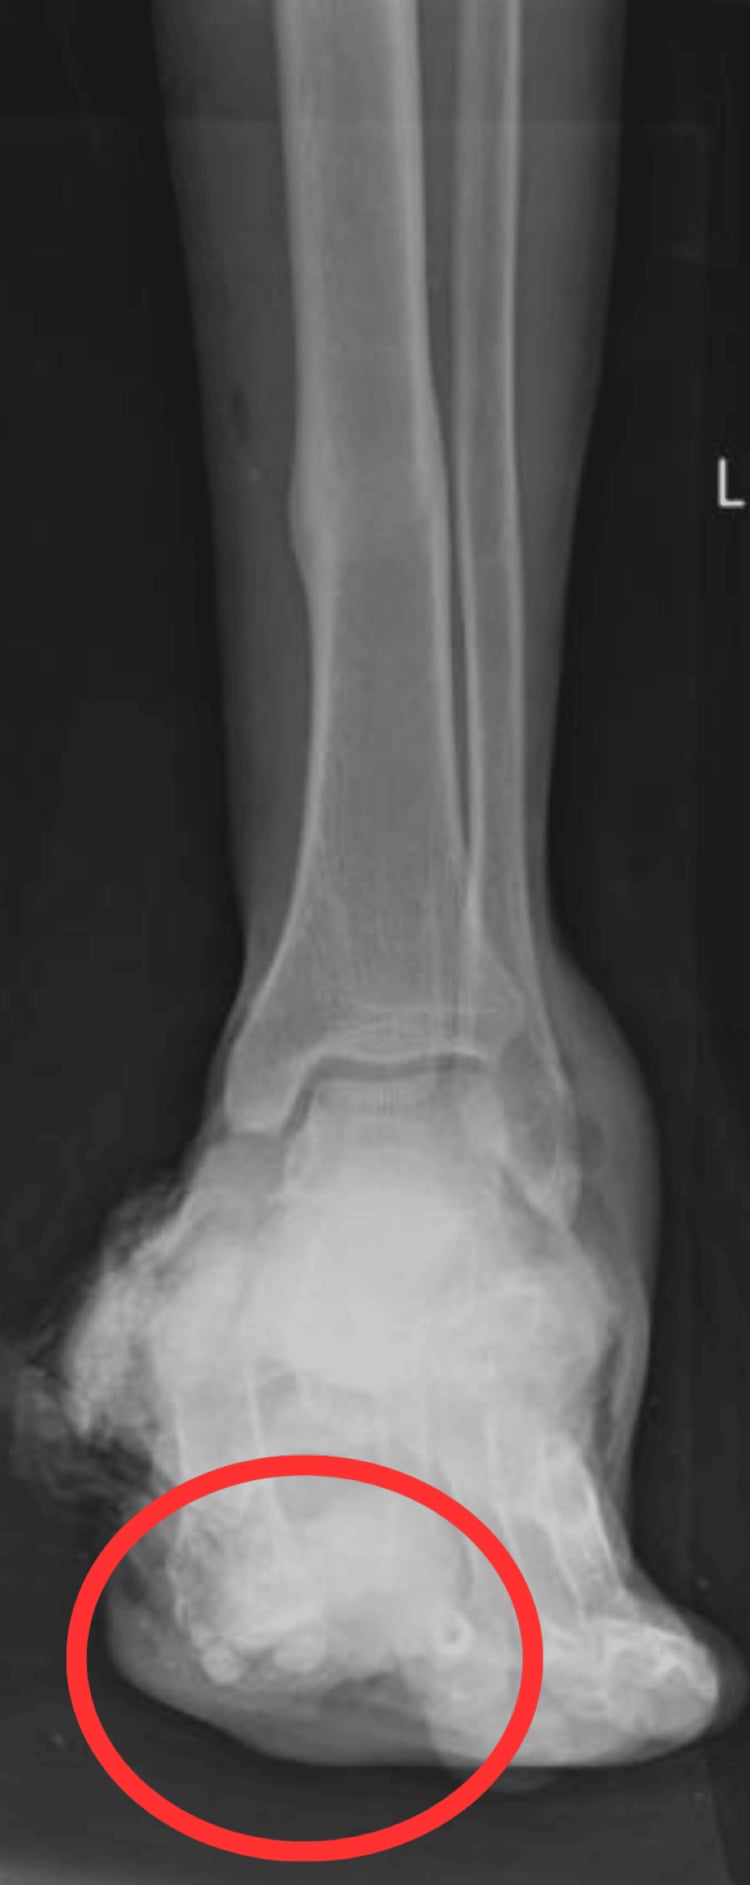
Anatomy and Pathophysiology
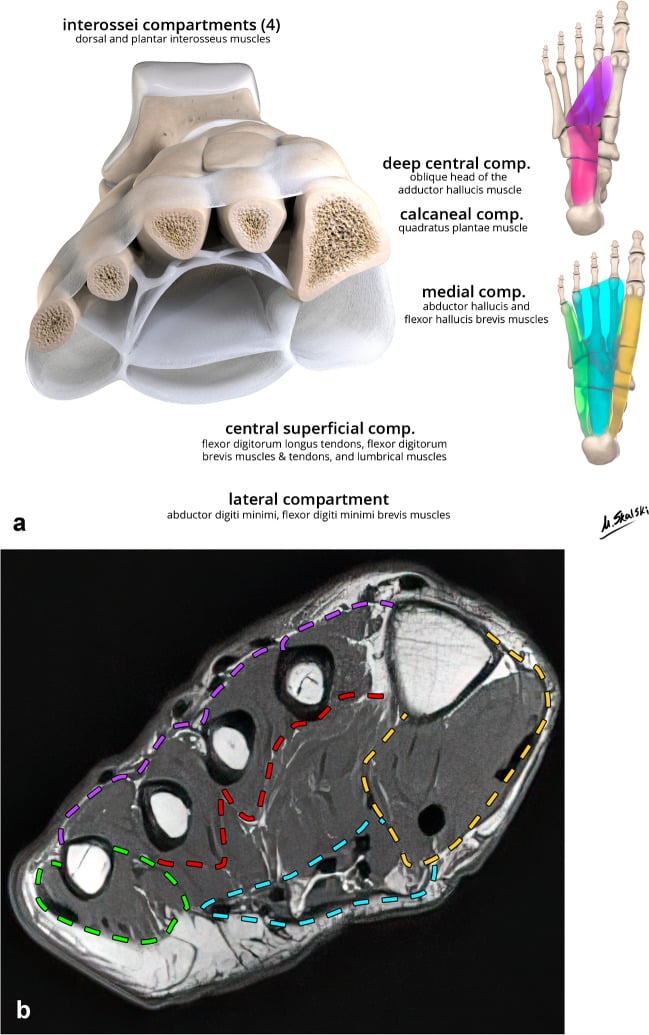
The nine compartments. Tough fascial septa arising from the plantar aponeurosis and the intermetatarsal ligaments divide the foot into nine compartments. The central compartment is subdivided into a superficial layer and a deep, calcaneal layer, and the adductor hallucis occupies its own transverse and oblique head compartment.
- Medial - abductor hallucis and the medial plantar nerve
- Lateral - abductor digiti minimi and a branch of the lateral plantar nerve
- Superficial central - flexor digitorum brevis
- Calcaneal (deep central) - quadratus plantae with the lateral plantar nerve and vessels
- Interosseous (four) - the dorsal and plantar interossei and the metatarsal arteries, in four separate compartments between the metatarsals
- Adductor - the transverse and oblique heads of adductor hallucis
The tarsal tunnel. The calcaneal compartment communicates proximally with the deep posterior compartment of the leg through the tarsal tunnel, so pressure is transmitted in both directions: a rise in the leg compartments can reach the foot, and a rise in the foot can pass proximally.
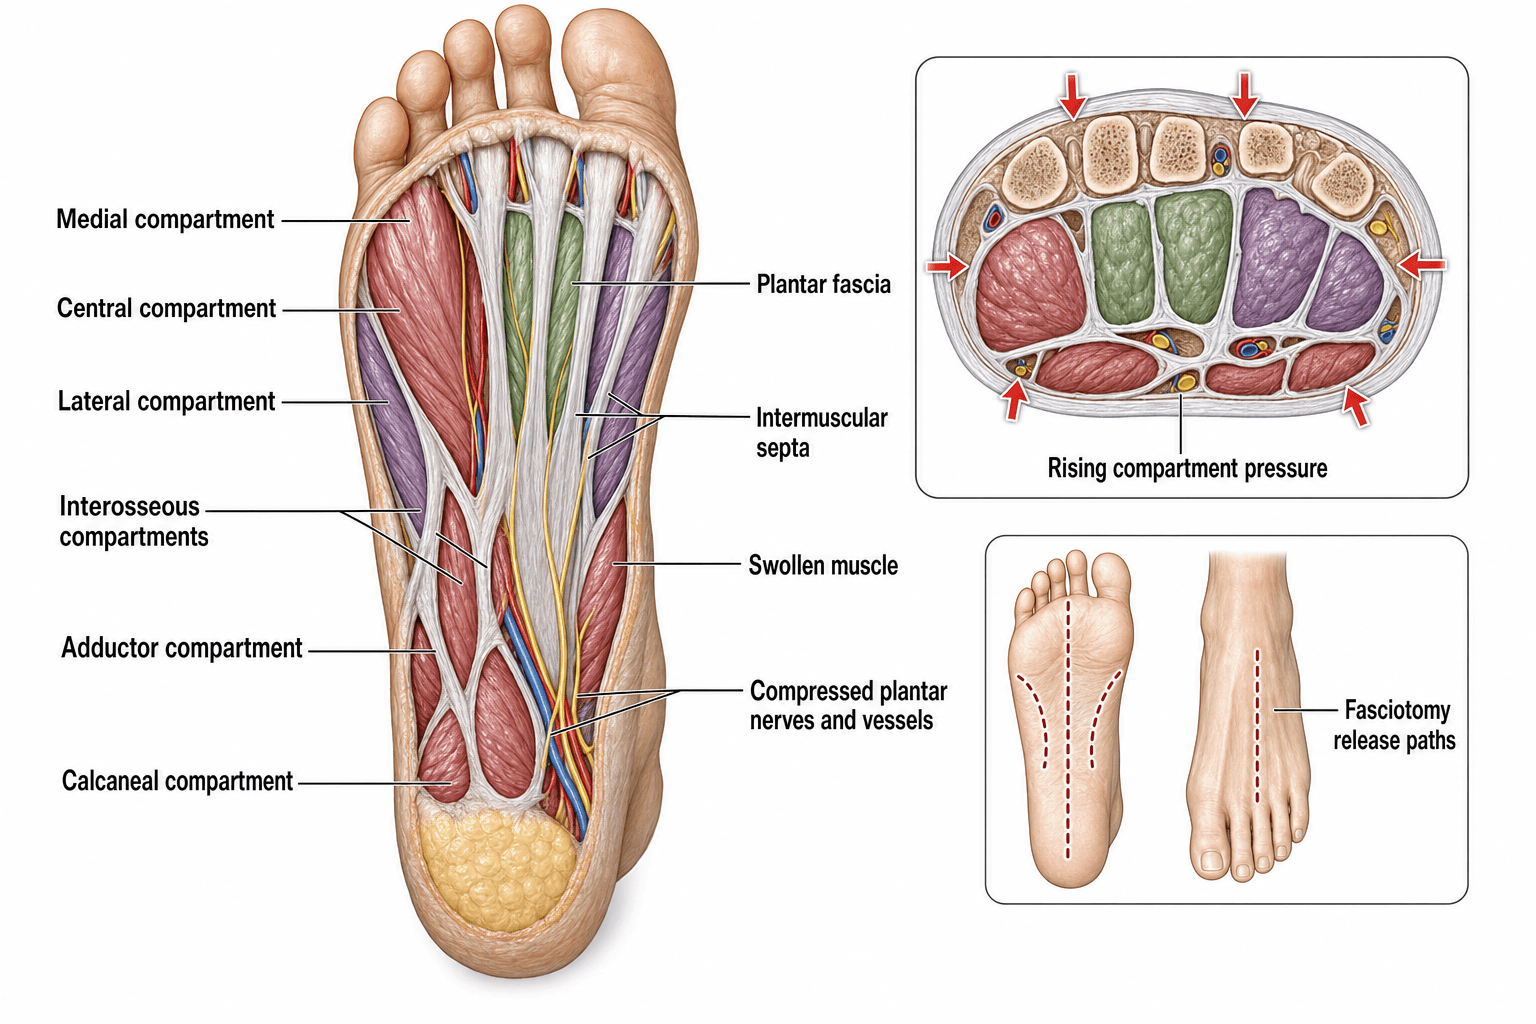
- Clinical Consequence if Necrotic
- Loss of great toe abduction, medial foot pain
- Release Incision
- Medial hindfoot incision
- Clinical Consequence if Necrotic
- Little toe abduction loss, lateral foot pain
- Release Incision
- Lateral hindfoot incision
- Clinical Consequence if Necrotic
- Intrinsic-minus clawing, plantar numbness
- Release Incision
- Plantar central deep release
- Clinical Consequence if Necrotic
- Metatarsal head necrosis, web-space pain
- Release Incision
- Dorsal intermetatarsal incisions
Why the foot is vulnerable. Nine separate envelopes with minimal compliance and a small volume, so even modest bleeding produces a rapid rise in pressure. The foot is dependent, and gravity adds hydrostatic pressure; collateral flow is limited, with a single dominant contribution from the posterior tibial artery.
How the ischaemia happens. Compartment syndrome does not cause ischaemia by occluding the main arteries; the pathology is at the capillary level. Rising interstitial pressure within the rigid fascial envelope first collapses the thin-walled veins and obstructs venous outflow, which raises venous pressure and reduces the local arteriovenous pressure gradient that drives capillary perfusion. As the gradient falls, capillary perfusion fails and the tissue becomes hypoxic, a self-amplifying cycle because congestion raises the pressure further.
Why the pulses mislead. The large arteries carry a far higher pressure, so the distal pulses are typically preserved until very late; palpable dorsalis pedis and posterior tibial pulses do not exclude compartment syndrome. The same physiology is why the decision rests on the delta (perfusion) pressure, diastolic blood pressure minus compartment pressure: perfusion fails as tissue pressure rises towards diastolic, so a low delta pressure signals critical hypoperfusion even with a normal systolic pressure and present pulses. The threshold is set out under Investigations.
Pulses and capillary refill are normal until late. Never be reassured by a palpable pulse.
Classification and Types
Classification by Associated Injury
High-energy calcaneal fractures remain the strongest predictor of foot compartment syndrome and should trigger routine pressure monitoring in the first 24-48 hours.
- Compartment Risk
- Calcaneal and central compartments highest
- Typical Pressures
- Often greater than 40 mmHg
- Fasciotomy Rate
- Up to 10 percent require fasciotomy
- Compartment Risk
- Interosseous and central compartments
- Typical Pressures
- 30-50 mmHg common
- Fasciotomy Rate
- Selective, 5-15 percent
- Compartment Risk
- Multiple compartments simultaneously
- Typical Pressures
- Variable, often all nine elevated
- Fasciotomy Rate
- High fasciotomy rate
- Compartment Risk
- Global elevation possible
- Typical Pressures
- Reversible if cast removed early
- Fasciotomy Rate
- Rare if recognised promptly
Clinical Assessment
History. The mechanism (a high-energy axial load, a calcaneal fracture, a Lisfranc injury or a crush) and the timing of the pain relative to the injury or to the application of a cast. The pain is deep, burning and out of proportion to the visible injury, and the opioid requirement escalates despite the fracture having been stabilised. Ask about numbness in the plantar distribution, the territory of the lateral plantar nerve.
Examination. Inspect for tense, shiny plantar skin with loss of the skin wrinkles and massive swelling, and palpate for rock-hard compartments, especially the calcaneal and central, and a tense plantar arch. Intrinsic function is weak or absent, plantar sensation is diminished with two-point discrimination over 6 mm, and the dorsalis pedis and posterior tibial pulses are usually preserved until late.
Pain on passive stretch is the most sensitive sign. Stabilise the ankle and gently extend or flex the toes while watching the patient: pain out of proportion, or disproportionate guarding, indicates rising compartment pressure. It is positive in over 90% of confirmed cases before any neurological deficit appears, but in the multiply injured or sedated patient it may be masked, and there the diagnosis rests on pressure measurement and serial examination.
Pain, pallor, paraesthesia, paralysis and pulselessness are late, irreversible signs. Never wait for them.
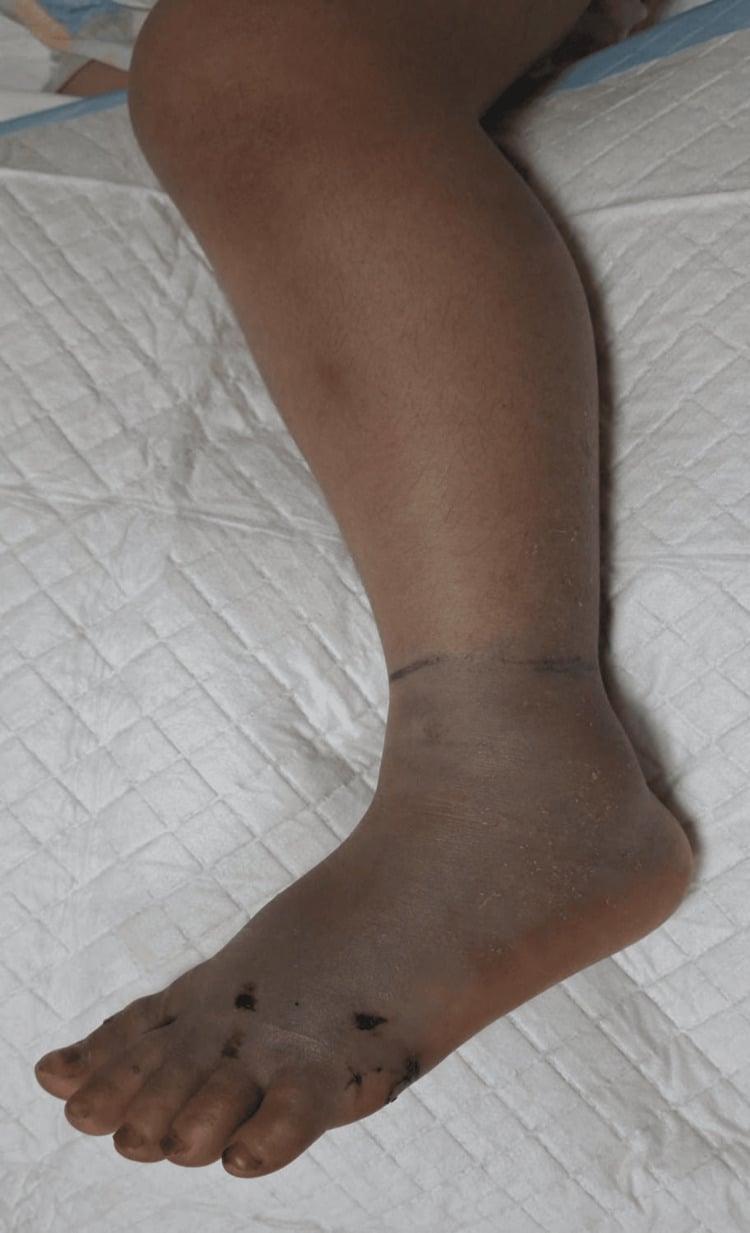
- Distinguishing Feature
- Pain on passive stretch, tense compartments
- Pressure Measurement
- Sustained fall in delta pressure (threshold under Investigations)
- Management Difference
- Fasciotomy of all nine compartments
- Distinguishing Feature
- Heel pain, swelling, no disproportionate pain
- Pressure Measurement
- Normal or mildly elevated
- Management Difference
- Fracture management, elevation, monitoring
- Distinguishing Feature
- Erythema, warmth, systemic signs
- Pressure Measurement
- Normal pressures
- Management Difference
- Antibiotics, possible drainage
- Distinguishing Feature
- Calf swelling, Homan sign positive
- Pressure Measurement
- Normal foot pressures
- Management Difference
- Anticoagulation, vascular consult
Investigations
Compartment pressure measurement, read with the clinical picture, makes the diagnosis; imaging confirms the fracture. Measure immediately in:
- Any calcaneal fracture with tense swelling
- A Lisfranc injury with severe pain
- A crush injury
- Clinical suspicion on any other ground
Technique. Use a handheld manometer or an arterial-line transducer. Measure all nine compartments through separate needle insertions, keeping the needle away from fascia or fracture haematoma, and record the absolute pressure and the delta pressure calculated from the diastolic blood pressure. Normal resting pressure is 0-8 mmHg.
Threshold. A delta pressure (diastolic blood pressure minus compartment pressure) under 30 mmHg, sustained for more than 2 hours, warrants fasciotomy. An absolute compartment pressure over 30 mmHg on its own does not: it is common and usually transient after injury, and acting on it alone would have sent 43% of continuously monitored tibial fractures to an unnecessary fasciotomy in the study that defined the delta-P rule. When the values are borderline, take serial measurements every 1-2 hours; a borderline reading is also worth repeating after 30-60 minutes of observation or after fracture reduction. Measure before and after fracture fixation, and document both the absolute and the delta pressure in the notes before proceeding to fasciotomy.
In a calcaneal fracture, measure the calcaneal (deep central) compartment first: it is the most commonly elevated and it contains the lateral plantar nerve.
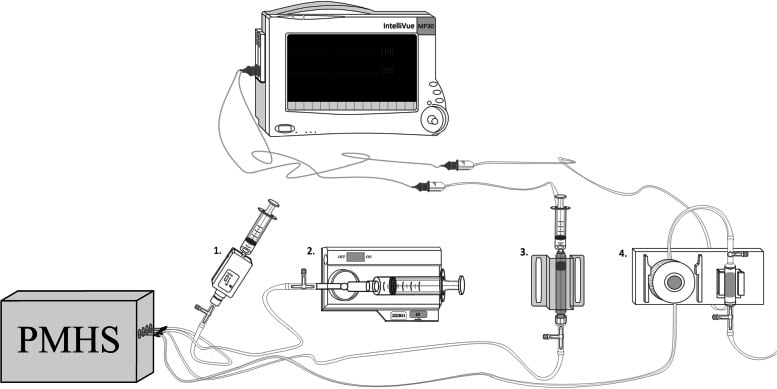
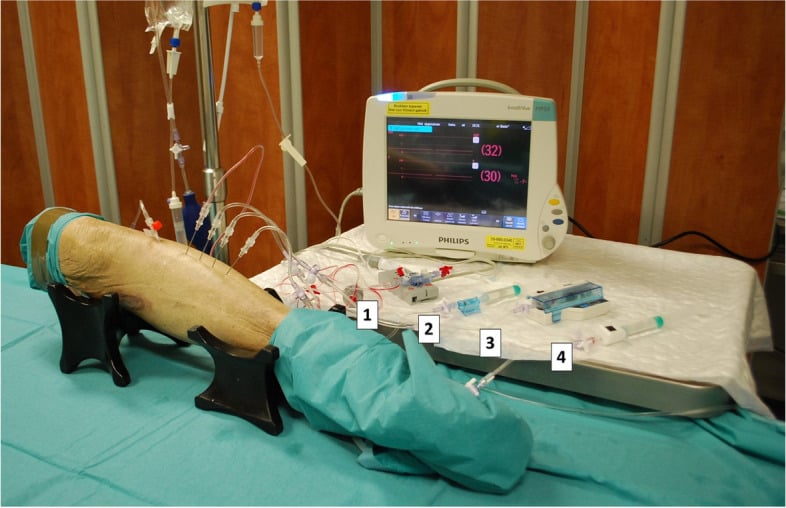
Radiographs are taken at the same time: AP, lateral, oblique and Harris heel views of the foot and ankle. They identify the calcaneal fracture pattern (Essex-Lopresti or Sanders classification), Lisfranc displacement or another bony injury that may require fixation in the same sitting as the fasciotomy. Fracture classification does not predict compartment pressure, so measure regardless of the fracture type.
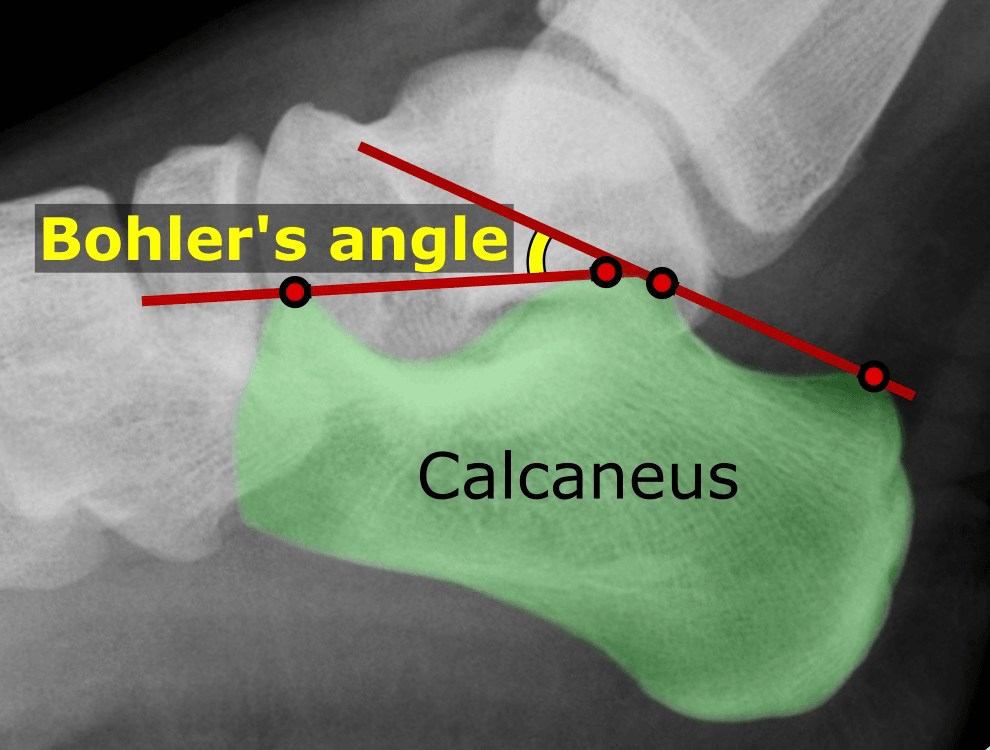
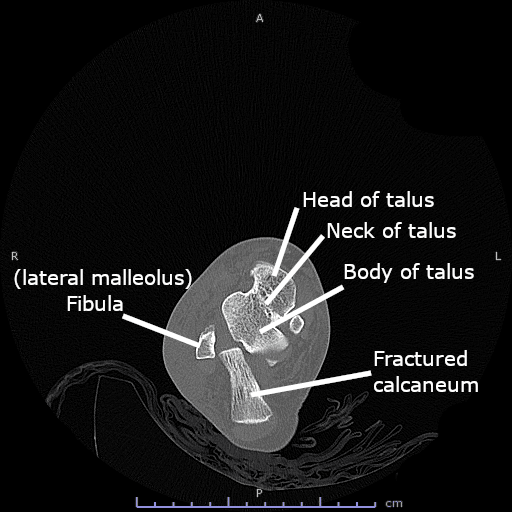
CT and MRI. CT is useful for planning calcaneal fracture fixation once the fasciotomy decision has been made. MRI is rarely required acutely: it may show muscle oedema, but it delays intervention and is not used to diagnose compartment syndrome.
Management Algorithm
The decision. Early fasciotomy remains the standard for a confirmed acute compartment syndrome. Many centres now favour selective fasciotomy with close monitoring, because late reconstruction of claw toes and contractures can be performed electively with reasonable functional outcomes; the trend reflects a recognition that many patients with moderately elevated pressures recover without surgery, while those who develop fixed claw toes can still achieve useful function with delayed reconstruction.
When to observe. Observation with close monitoring, serial pressures and neurovascular checks every 2 hours, is an option when:
- The delta pressure is 25-35 mmHg and the clinical signs are improving
- The injury is low-energy with minimal swelling
- Patient factors preclude multiple operations
Acute Compartment Syndrome Requiring Fasciotomy
Goal. Release all nine compartments through minimal incisions while protecting the neurovascular structures and allowing subsequent fracture fixation.
Surgical Protocol
Supine with a bump under the ipsilateral hip and the foot at the end of the table. A tourniquet is used only if needed for fracture fixation; avoid prolonged tourniquet time before the fasciotomy. Have a handheld manometer in theatre for confirmation, fine scissors, retractors and a skin-marking pen.
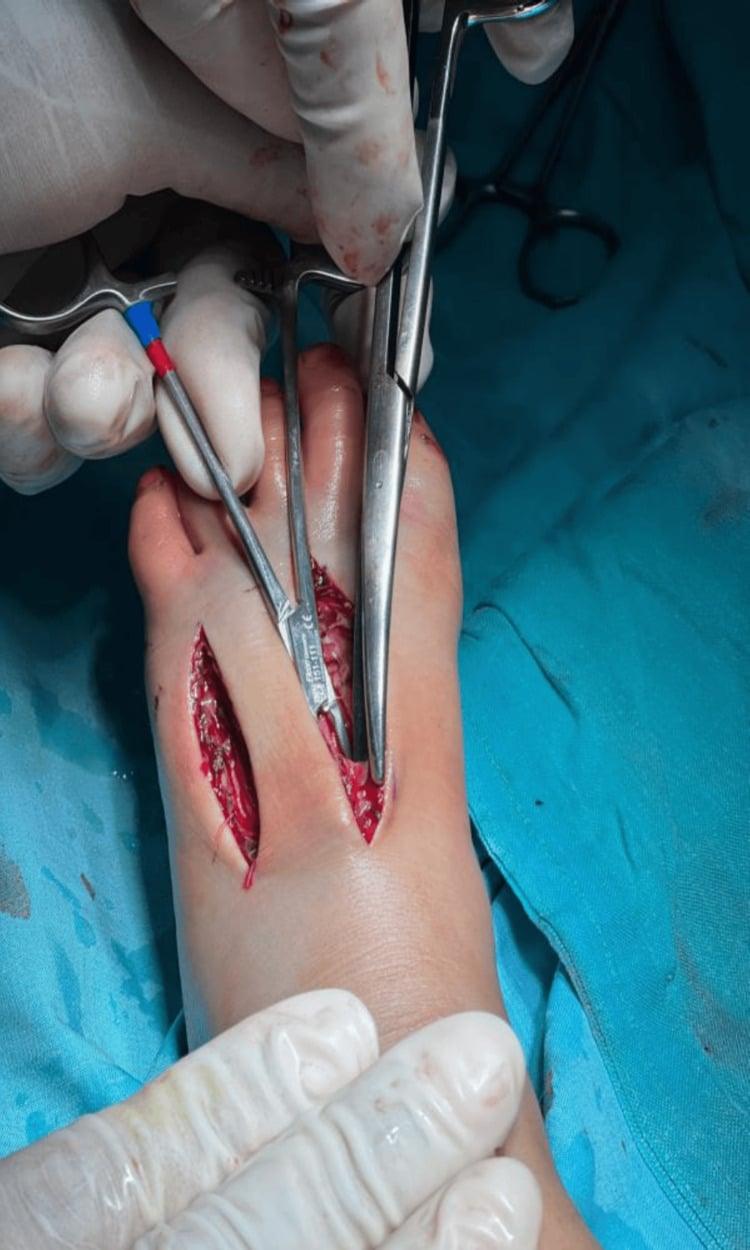
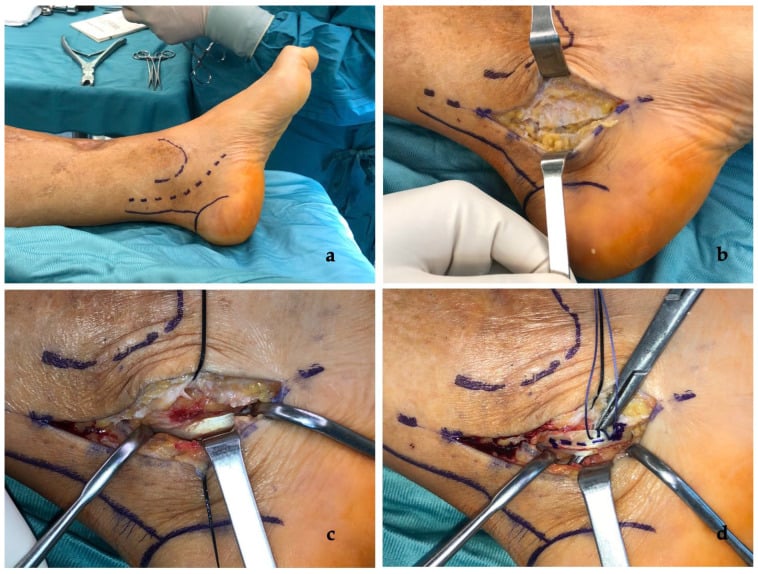
- Medial - a 6 cm incision along the medial foot from the navicular to the calcaneal tuberosity, releasing the medial and superficial central compartments
- Lateral - a 6 cm incision along the lateral foot parallel to the plantar surface, releasing the lateral and interosseous compartments
- Plantar central - either connected to another incision or made separately, to release the calcaneal (deep) compartment while protecting the lateral plantar nerve
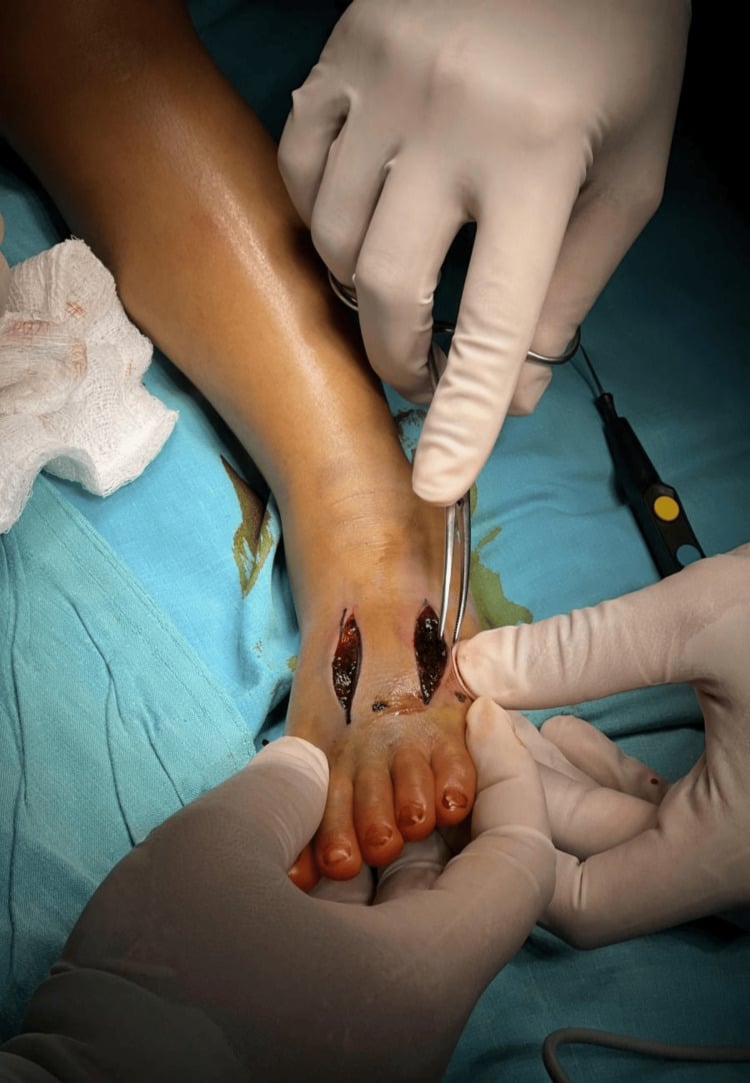
- Dorsal intermetatarsal - two or three dorsal incisions between the metatarsals to release all four interosseous compartments and the adductor hallucis
Divide the fascia completely so that each compartment is released from proximal to distal, identifying and preserving the medial and lateral plantar nerves during the central release. Any obviously dead muscle is excised at the index procedure. Leave the wounds open and plan delayed primary closure or skin grafting at 5-7 days.
Strict elevation for 48 hours to reduce oedema, with a negative-pressure dressing or moist gauze and a return to theatre at 48-72 hours for inspection and possible closure. ORIF of the calcaneal or Lisfranc injury follows once the swelling allows, usually 7-14 days later. Rehabilitation is early active toe motion and progressive weight-bearing once the wounds are stable.
The calcaneal compartment. It lies beneath the superficial central compartment and must be released through a separate deep plane; the medial (Henry) approach reliably reaches it. It is the most commonly under-released compartment, and an apparently complete fasciotomy that misses it leaves quadratus plantae and the lateral plantar nerve compressed, with persistent clawing and plantar numbness despite release of the other eight.
Complications
Complications arise both from a missed or late-treated compartment syndrome, the ischaemic sequelae, and from the fasciotomy required to treat it.
The ischaemic sequelae. The intrinsic muscles die within 4-6 hours of critical ischaemia, and their fibrosis produces the intrinsic-minus posture.
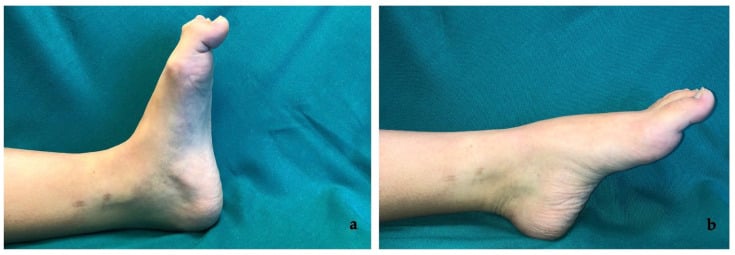
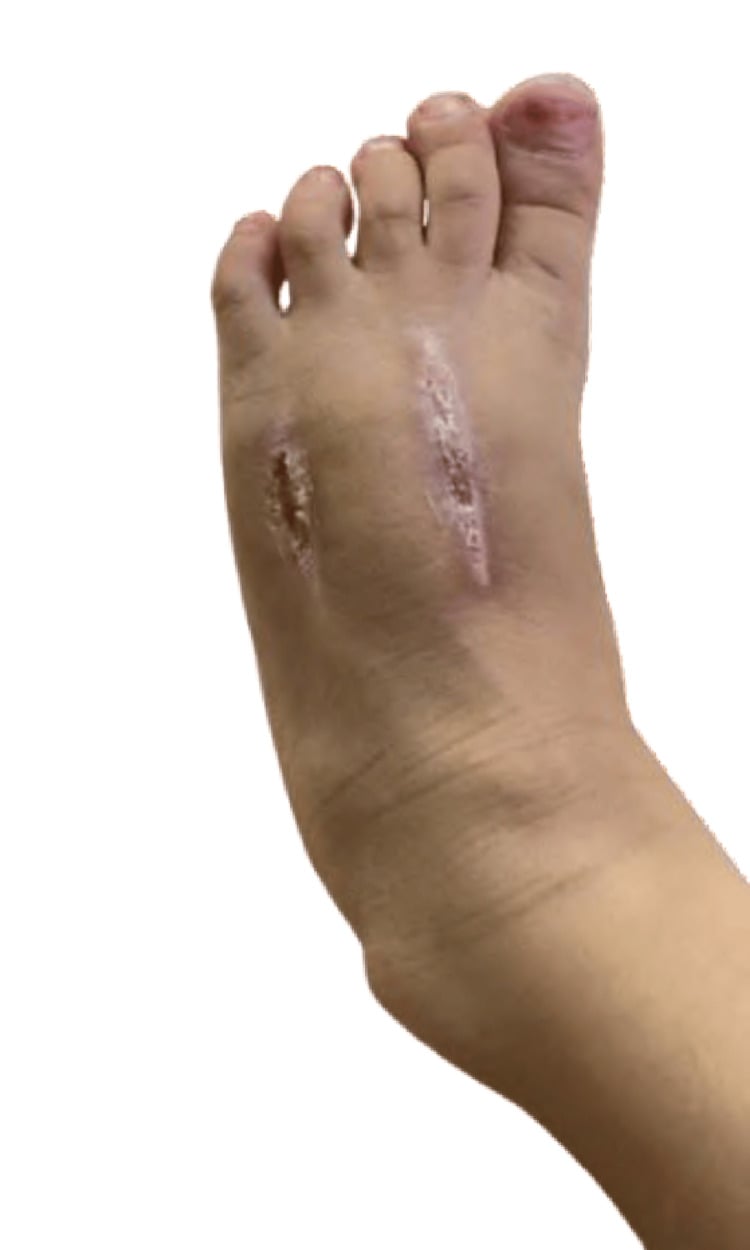
- Claw-toe deformity of the lesser toes, the hallmark late deformity, from ischaemic contracture of the intrinsic (interosseous and lumbrical) muscles
- Fixed cavus, clawing and forefoot deformity with painful, stiff toes
- Sensory loss and dysaesthesia in the medial and lateral plantar nerve distributions, with persistent plantar neuropathic pain from nerve compression
- Chronic pain, weakness and global stiffness, with difficulty in push-off, gait and shoe wear
- Amputation - up to 10% of severe untreated cases progress to a below-knee amputation
Complications of fasciotomy. The release has costs of its own:
- Open wounds requiring delayed closure or split-skin grafting, with attendant scarring
- Wound infection and dehiscence, especially with associated open fractures
- Incomplete release, classically of the deep calcaneal compartment, a cause of persistent ischaemia and ongoing deformity
- Delay of calcaneal ORIF until the fasciotomy wounds heal, prolonging recovery
Systemic Sequelae: Rhabdomyolysis and Reperfusion
The foot is small, but extensive or crush-related muscle necrosis, and the reperfusion that follows fasciotomy or restored flow, can cause systemic harm that the local picture hides.
Rhabdomyolysis. Ischaemic and necrotic muscle releases myoglobin, potassium, phosphate and creatine kinase when it is reperfused; with a large enough muscle load this becomes crush syndrome. The dangers are hyperkalaemia (arrhythmia, cardiac arrest), myoglobinuric acute kidney injury (pigment nephropathy), metabolic acidosis and hypocalcaemia.
Monitoring and treatment. Monitor creatine kinase, urea and electrolytes and an ECG, and check the urine for myoglobin (tea-coloured urine that is dipstick-positive for blood without red cells). Management is aggressive intravenous crystalloid to maintain a brisk urine output, prompt treatment of hyperkalaemia, and renal support if acute kidney injury develops; urinary alkalinisation is sometimes used but is debated.
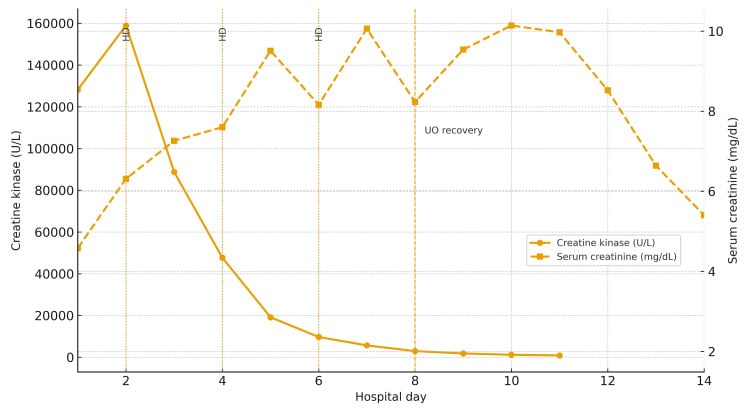
This systemic risk is one reason very late fasciotomy of frankly necrotic muscle is approached with caution: debriding dead muscle may be safer than reperfusing it.
Outcomes and Prognosis
- Muscle Viability
- Greater than 90 percent viable
- Claw Toe Rate
- Less than 10 percent
- Return to Work
- 80-90 percent at 3-6 months
- Muscle Viability
- 70-80 percent viable
- Claw Toe Rate
- 20-30 percent
- Return to Work
- 60-70 percent at 6 months
- Muscle Viability
- Less than 50 percent viable
- Claw Toe Rate
- Greater than 70 percent
- Return to Work
- Less than 40 percent, many require late surgery
What decides the result. The key threshold is 6 hours from the onset of critical pressure elevation; beyond that window muscle necrosis becomes irreversible in most patients.
- Best prognosis - early diagnosis (under 6 hours), complete nine-compartment release, a young patient, a low-energy mechanism, compliant rehabilitation
- Poor prognosis - delayed presentation (over 24 hours), incomplete release (especially of the calcaneal compartment), a high-energy crush, an associated open fracture or vascular injury, smoking, diabetes
Guidelines, Registries & Global Practice
- Calcaneal fractures account for 1-2 percent of all fractures worldwide and are the leading cause of foot compartment syndrome
- Incidence of compartment syndrome after calcaneal fracture ranges from 4-10 percent in published series across trauma centres
- High-energy axial loading mechanisms predominate in industrial and motor-vehicle settings globally
- Missed diagnosis remains a significant source of litigation in foot and ankle trauma worldwide
- High-resource centres: routine pressure monitoring with handheld manometers, dedicated foot and ankle trauma lists, negative-pressure wound therapy for open fasciotomy wounds
- Limited-resource settings: reliance on clinical signs and serial examination, improvised fasciotomy incisions, delayed wound closure with skin grafts when available
- Universal principle: outcome depends on early recognition and complete release of all nine compartments regardless of available technology
- Surgery: late reconstruction expertise is concentrated in specialist foot and ankle units globally
- Diagnosis emphasis
- Pressure measurement in all high-risk calcaneal and Lisfranc injuries
- Acute treatment
- Fasciotomy when delta P under 30 mmHg sustained over 2 hours (not the absolute reading alone)
- Late reconstruction
- Tendon transfers and osteotomies for established claw toes
- Diagnosis emphasis
- High index of suspicion, serial clinical examination, selective pressure measurement
- Acute treatment
- Early fasciotomy for confirmed cases, close monitoring for borderline
- Late reconstruction
- Multidisciplinary foot and ankle reconstruction pathways
- Diagnosis emphasis
- Compartment pressure monitoring as standard in calcaneal fracture protocols
- Acute treatment
- Complete nine-compartment release through described incisions
- Late reconstruction
- Staged reconstruction after soft-tissue recovery
- Diagnosis emphasis
- Awareness of tarsal tunnel communication with leg compartments
- Acute treatment
- Individualised decision-making integrating pressure and clinical data
- Late reconstruction
- Emphasis on prevention and early referral to specialist units
No dedicated international registry tracks foot compartment syndrome outcomes. Evidence is derived from small prospective series and expert consensus. The trend toward selective rather than routine fasciotomy reflects recognition that many patients with moderately elevated pressures recover without surgery, while those who develop fixed claw toes can still achieve useful function with delayed reconstruction. Documentation of pressure measurements and clinical rationale for or against fasciotomy is essential for medicolegal protection worldwide.
Controversies & Areas of Uncertainty
Delta pressure thresholds have driven fasciotomy in many centres, yet recent series suggest selective monitoring is safe when delta pressure stays above 25-30 mmHg and clinical signs are improving. The absolute reading alone is not a trigger. No randomised trial exists to settle the question.
Classic teaching requires four separate incisions to release all nine compartments reliably. Some surgeons advocate three-incision techniques with acceptable release rates, but cadaveric studies show incomplete deep central release when incisions are minimised.
Indwelling catheter systems provide continuous readings but add cost, infection risk, and potential for measurement error. Intermittent handheld manometry remains the global standard; no high-quality evidence demonstrates superiority of continuous systems in the foot.
Traditional teaching delays ORIF 7-14 days until swelling subsides. Some centres now perform acute fixation at the time of fasciotomy using minimally invasive techniques, but wound complication rates and long-term outcomes require further study.
MCQ Practice Points
Q: How many compartments does the foot have and which is most clinically important in calcaneal fractures? A: The foot has nine compartments. The calcaneal (deep central) compartment is most clinically important in calcaneal fractures because it contains the quadratus plantae and the lateral plantar neurovascular bundle; its release is frequently incomplete if not specifically addressed through a deep plane.
Q: What are the pressure thresholds for fasciotomy in foot compartment syndrome? A: The threshold is a delta pressure (diastolic blood pressure minus compartment pressure) under 30 mmHg, sustained for more than 2 hours. An absolute compartment pressure over 30 mmHg is NOT on its own an indication - it is common and usually transient after injury, and acting on it alone would have sent 43% of continuously monitored fractures to an unnecessary fasciotomy in the study that defined the delta-P rule. Serial measurements are essential when values are borderline, and the decision integrates the sustained delta-P with the clinical picture.
Q: What late deformity occurs if foot compartment syndrome is missed? A: Intrinsic-minus claw toe deformity. Necrosis of the intrinsic muscles (especially quadratus plantae and interossei) removes their opposition to the long flexors and extensors, producing hyperextension at the metatarsophalangeal joints and flexion at the interphalangeal joints.
Q: What incisions are required for complete nine-compartment release? A: Medial hindfoot incision (medial and superficial central compartments), lateral hindfoot incision (lateral and interosseous compartments), separate deep central release for the calcaneal compartment, and two to three dorsal intermetatarsal incisions for the four interosseous compartments and adductor hallucis.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 42-year-old roofer falls 4 metres onto his right heel. He has a closed Sanders type III calcaneal fracture with massive foot swelling. Six hours after injury he complains of severe burning plantar pain despite opioid analgesia. The foot is tense, especially over the medial arch. What is your assessment and management?”
“A 35-year-old man sustained a crush injury to his foot 8 weeks ago that was treated non-operatively elsewhere. He now presents with fixed clawing of all lesser toes, loss of plantar sensation, and inability to wear normal shoes. The foot is stiff and painful. How would you manage this?”
Key Anatomy
- Nine compartments: medial, lateral, superficial central, calcaneal (deep central), four interosseous, adductor hallucis
- Calcaneal compartment contains quadratus plantae and lateral plantar neurovascular bundle
- Tarsal tunnel communication allows pressure transmission between leg and foot
- Intrinsic muscles (especially quadratus plantae) are critical for toe balance
Diagnosis
- Pain out of proportion and pain on passive toe stretch are most sensitive clinical signs
- Pressure thresholds: delta P (diastolic minus compartment) under 30 mmHg sustained over 2 hours - not the absolute reading alone
- Measure all nine compartments serially when suspicion exists
- Calcaneal fractures and Lisfranc injuries carry highest risk
Treatment Algorithm
- Acute confirmed compartment syndrome: urgent nine-compartment fasciotomy
- Medial, lateral, plantar central, and dorsal intermetatarsal incisions required
- Selective monitoring acceptable in borderline cases with close observation
- Late claw toes treated with FHL transfer, osteotomies, and joint fusions
Critical Thresholds
- Delta P under 30 mmHg sustained over 2 hours = fasciotomy (absolute over 30 alone is not an indication)
- Delta pressure less than 30 mmHg = consider fasciotomy
- Time window for reversible muscle ischaemia approximately 4-6 hours
- Delayed presentation (greater than 24 hours) shifts focus to late reconstruction
Sequelae & Prevention
- Missed compartment syndrome produces intrinsic-minus claw toe deformity
- Late reconstruction improves but rarely normalises function
- Best outcome achieved by early recognition and complete release
- Always document pressure measurements and clinical rationale in high-risk fractures
Evidence Base and Key Trials
Compartment syndromes of the foot after calcaneal fractures
- Approximately 10% of calcaneal fractures develop a foot compartment syndrome, and about half of those go on to clawing of the lesser toes, stiffness and neurovascular dysfunction
- Tense swelling and severe pain are the hallmarks; diagnosis confirmed by multistick catheterisation, particularly of the calcaneal compartment in the hindfoot
- Recommended immediate fasciotomy to prevent ischaemic contracture, with calcaneal ORIF delayed until the fasciotomy wounds are closed
Experimental decompression of the fascial compartments of the foot--the basis for fasciotomy in acute compartment syndromes
- In 40 paired fresh cadaver feet, compared a double-incision dorsal fasciotomy with a single medial longitudinal approach using slit-catheter pressure monitoring
- Both approaches satisfactorily decompressed the compartments, but pressures normalised more slowly after the dorsal approach (11 min vs 1 min, p<0.01)
- The double-incision dorsal approach is easier to perform and may be preferred when forefoot fractures also require internal fixation
Foot compartment syndrome
- Review of diagnosis and management emphasizing clinical signs and pressure thresholds
- Highlighted calcaneal compartment as most frequently elevated in trauma
Compartment syndrome of the foot after calcaneal fracture
- Case report of compartment syndrome following calcaneal fracture
- Stressed importance of early recognition and fasciotomy in emergency setting