Both-Bone Fractures, Greenstick, and Monteggia-Galeazzi
- Younger children remodel more (under 10 years: 20° acceptable)
- Sagittal plane remodels better than coronal
- Rotational deformity does NOT remodel - must reduce
- Always obtain true elbow views to exclude Monteggia
- Greenstick fractures may need completion plus overcorrection
- “Check radiocapitellar line on all forearm fractures
- “10° residual angulation is maximum in children over 10
- “Pronation-supination measured clinically, not on X-ray
- “ESIN preferred over plating in pediatric fractures
Overview and Epidemiology
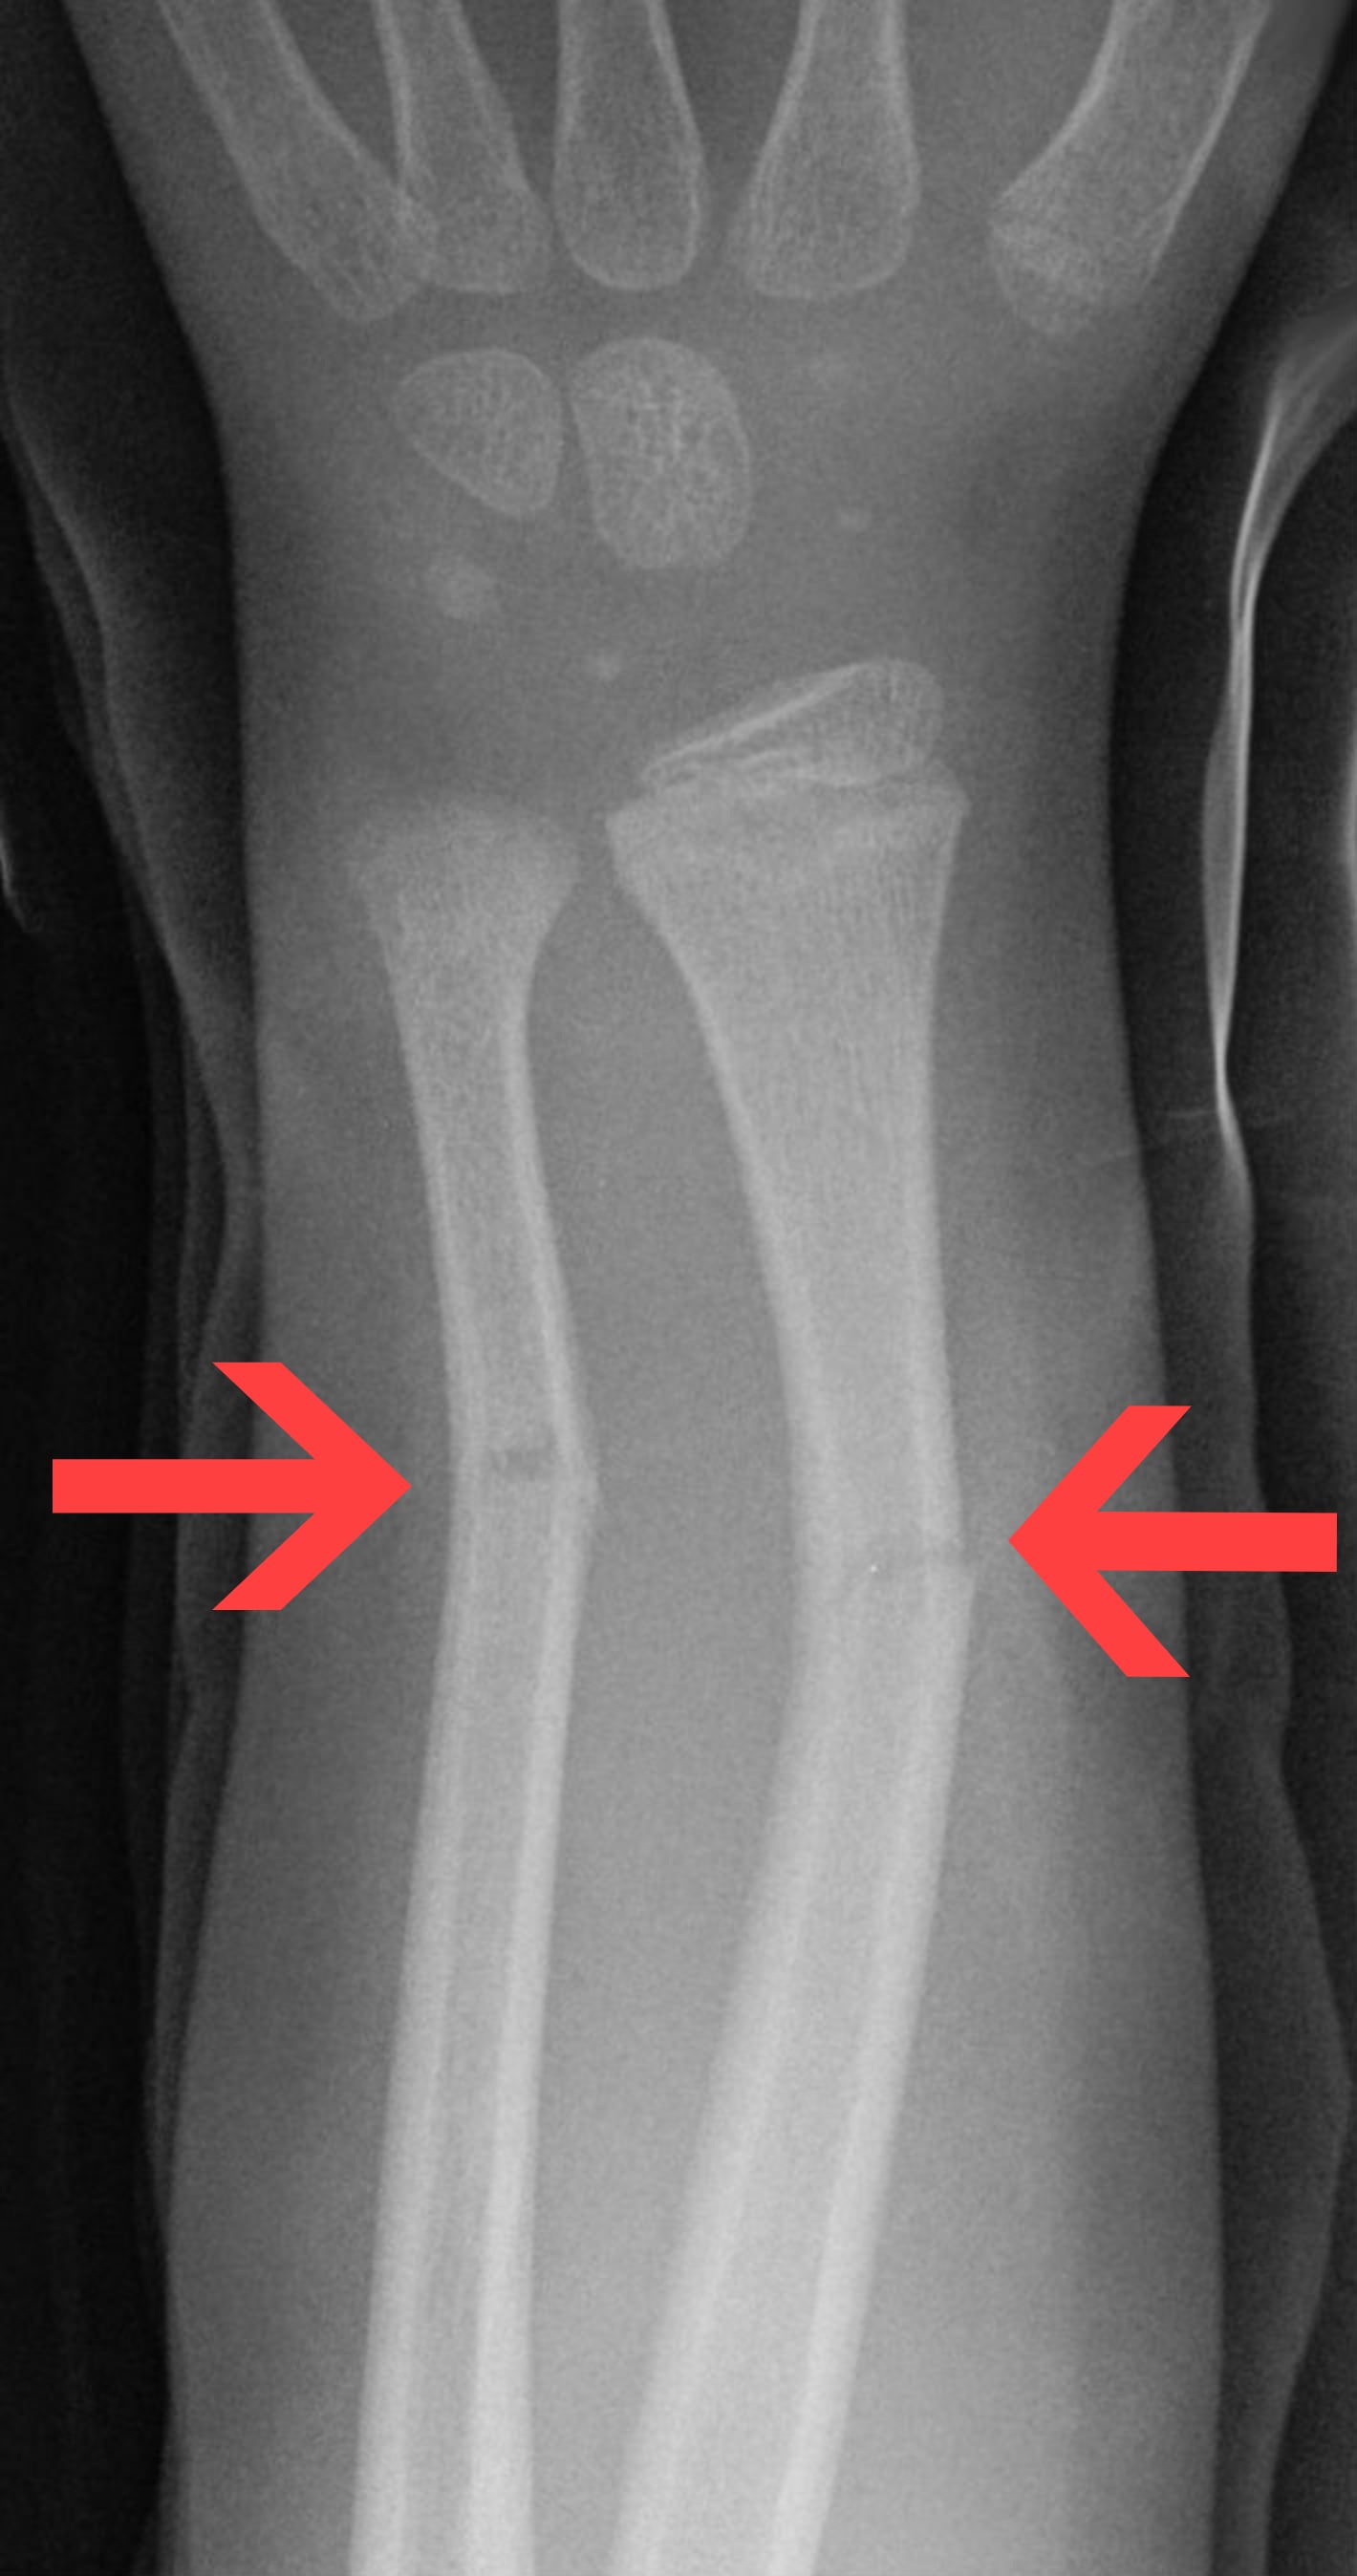
Forearm fractures are the most common paediatric fractures, accounting for up to 45% of all childhood fractures. The distal third is the most frequently affected site, but the mid-shaft both-bone fracture is the one that matters most, because a malreduced shaft costs the child forearm rotation.
Who. The peak age is 4-14 years, boys more often than girls, hurt on playground equipment and in sport. Both-bone fractures are more common than single-bone fractures, and the incidence is increasing as play becomes more active.
Mechanism. Falls from height on playground equipment, sports injuries and cycling accidents. Direct trauma is less common. An unusual pattern should raise the question of non-accidental injury.
Anatomy and Biomechanics
A functional unit. The radius and ulna work as one, connected by the proximal and distal radioulnar joints and stabilised by the interosseous membrane. Forearm rotation is pronation and supination; in neutral rotation the thumb points up and the radial bow lies lateral.
The radial bow. The natural bow of the radius gives clearance for the muscle bellies and is essential for full pronation-supination. Lose the bow and rotation is restricted.
Why Monteggia and Galeazzi injuries occur. Because the two bones are bound together, an injury to one can affect the other or the proximal or distal radioulnar joint. That is the whole reason an ulna fracture can present with a dislocated radial head, and a radius fracture with a disrupted DRUJ.
Deforming forces. The muscle attachments decide the position in which a fracture is reduced and held:
- Proximal fractures (above pronator teres): the proximal fragment is supinated by biceps and supinator while the distal fragment is pronated by pronator teres, so reduce in supination
- Mid-shaft fractures (below pronator teres): both fragments carry pronation and supination forces, so reduce in neutral
- Distal fractures: reduce in pronation, the most common reduction position
Classification Systems
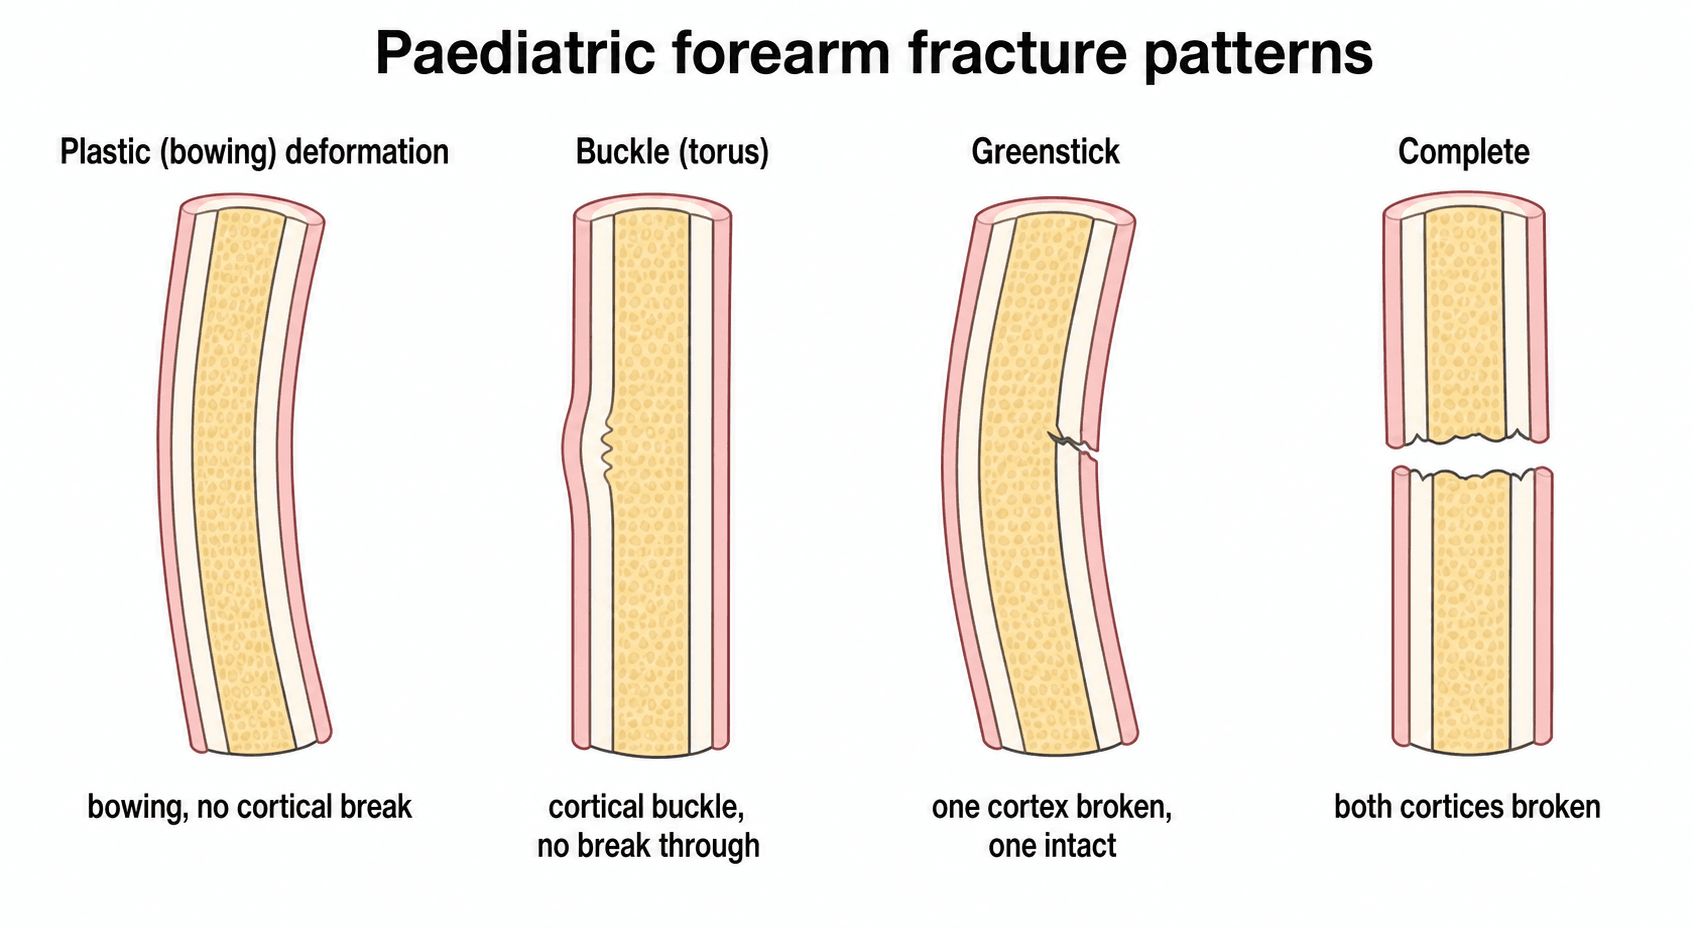
The four patterns. Paediatric forearm fractures are classified by how the cortex fails, and the patterns reflect the soft bone and thick periosteum of the child:
- Plastic (bowing) deformation: the bone bows with no visible fracture line or cortical break. Stable if the bow is under 20°
- Buckle (torus): compression of one cortex with no displacement and no break-through. Stable
- Greenstick: one cortex breaks completely while the other stays intact. Stability is variable
- Complete: both cortices are disrupted. Unstable
Monteggia: the Bado classification. A Monteggia lesion is an ulna fracture with a dislocated radial head; the Bado types are set out below.
- Ulna Angulation
- Apex anterior
- Radial Head Direction
- Anterior dislocation
- Frequency
- 70% (most common)
- Ulna Angulation
- Apex posterior
- Radial Head Direction
- Posterior dislocation
- Frequency
- 15%
- Ulna Angulation
- Apex lateral
- Radial Head Direction
- Lateral dislocation
- Frequency
- 10%
- Ulna Angulation
- Apex anterior
- Radial Head Direction
- Anterior + radial fracture
- Frequency
- 5% (rare)
Type I is an extension injury and by far the most common in children.
Galeazzi. A fracture of the radius, typically in the distal third, with subluxation or dislocation of the DRUJ. It is less common in children than in adults and often more stable, because the periosteum is intact.
Clinical Assessment
History. The mechanism and the time since injury, hand dominance and sports involvement, previous fractures, and any numbness or tingling in the hand.
Examination. Look for deformity and swelling and for any open wound, even a needle-prick. Document the neurovascular status of the median, ulnar and radial nerves and look for the signs of compartment syndrome. Palpate the elbow and the wrist for tenderness; rotational alignment is hard to judge in the acute setting.
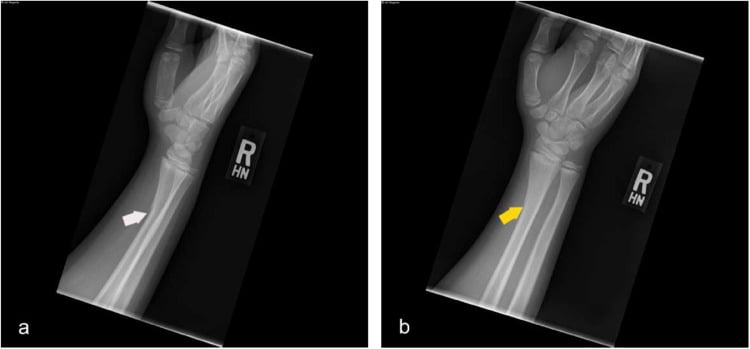
Check the elbow on every forearm fracture. Examine for elbow tenderness and get proper elbow radiographs. If the ulna is fractured, even by a plastic bow, the radial head must be checked. A missed Monteggia leads to chronic radial head dislocation and functional impairment, and is a medicolegal disaster.
Rotation. Rotation cannot be assessed on a radiograph. Compare pronation and supination with the opposite side clinically; after reduction the hand should lie flat with the forearm supinated. Any rotational malunion is permanent.
Differential diagnosis. A child with a painful, swollen forearm after a fall is not always a simple shaft fracture. Distinguishing these patterns changes management entirely, and the most dangerous error is treating an isolated bone fracture and missing the associated joint injury.
- Key Distinguishing Feature
- Both radius and ulna fractured at similar level
- Pitfall if Missed
- Loss of forearm rotation if malreduced
- Key Distinguishing Feature
- Isolated ulna fracture/plastic bow PLUS broken radiocapitellar line
- Pitfall if Missed
- Chronic radial head dislocation, fixed pronation loss
- Key Distinguishing Feature
- Distal radius fracture PLUS widened or incongruent DRUJ
- Pitfall if Missed
- DRUJ instability, painful rotation
- Key Distinguishing Feature
- Single cortical wrinkle, no second-bone or joint injury
- Pitfall if Missed
- Overtreatment with rigid cast and follow-up
- Key Distinguishing Feature
- Tenderness/widening at the physis, not the shaft
- Pitfall if Missed
- Growth arrest if reduction forced repeatedly
- Key Distinguishing Feature
- Bowing with NO visible cortical break
- Pitfall if Missed
- Persistent rotational block; underestimated as 'no fracture'
- Key Distinguishing Feature
- Mechanism inconsistent with injury, multiple ages of injury, delayed presentation
- Pitfall if Missed
- Repeat injury or fatality if safeguarding missed
Investigations
The views. The joint above and below a forearm fracture must be imaged, so a forearm series is never complete without the elbow and the wrist.
- What to Check
- Fracture pattern, displacement, angulation
- Don't Miss
- Both bone involvement
- What to Check
- Sagittal angulation, radial bow
- Don't Miss
- Bayonet apposition
- What to Check
- Radiocapitellar alignment
- Don't Miss
- Monteggia - radial head dislocation
- What to Check
- Radiocapitellar line
- Don't Miss
- Posterior fat pad (effusion)
- What to Check
- DRUJ congruence
- Don't Miss
- Galeazzi - DRUJ subluxation
The radiocapitellar line. A line drawn through the centre of the radial shaft should pass through the centre of the capitellum on every view: AP, lateral and obliques. It can only be judged on a true lateral of the elbow, so insist on one. If the line misses the capitellum, the radial head is dislocated.
Measuring angulation. On the AP view measure the coronal-plane angulation, apex medial or lateral; this plane is less forgiving of residual deformity. On the lateral view measure the sagittal-plane angulation, apex anterior or posterior; this plane, the plane of elbow and wrist motion, remodels better. If you are concerned that the radial bow has been lost, compare it with the opposite side.
Management
What can be accepted. Remodelling decides, and remodelling depends on age, plane and level. Younger children remodel more, and rotation never remodels:
- Under 10 years: up to 15-20° in the sagittal plane and 10-15° in the coronal plane
- Over 10 years: a maximum of 10° in either plane
- Rotation: zero tolerance; it must be anatomically reduced
- Level: a mid-shaft fracture is less forgiving than a metaphyseal one, and a fracture near the physis is more forgiving
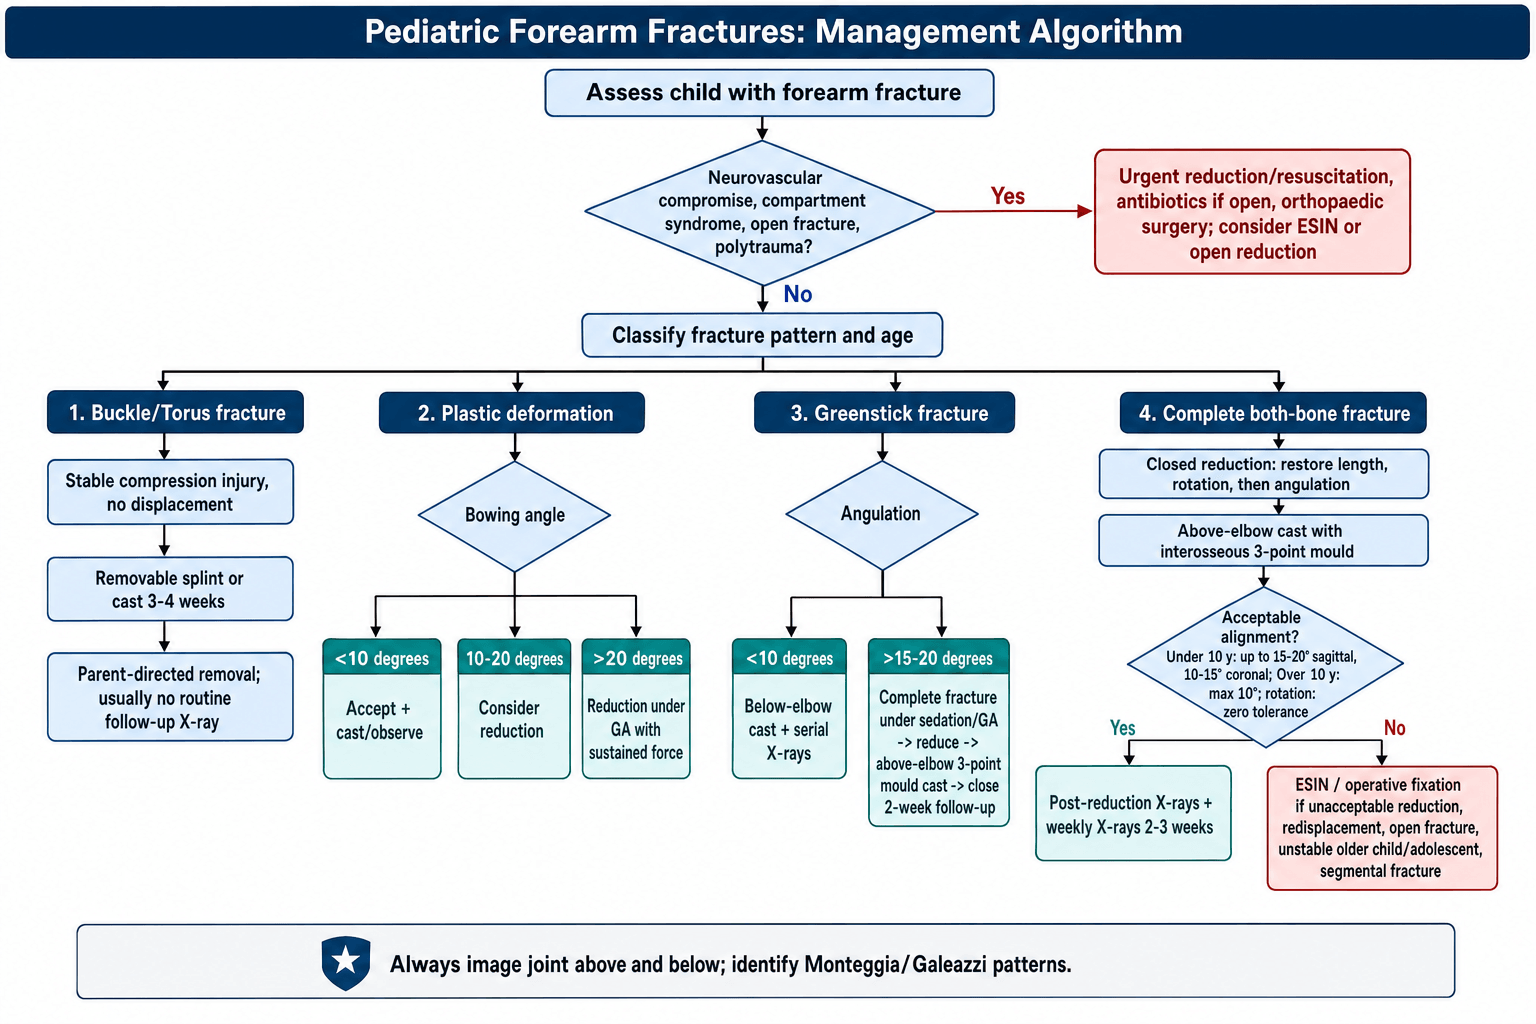
Buckle (torus) fractures. A stable cortical compression injury without displacement, and inherently stable. A splint or removable cast for 3-4 weeks, taken off by the parents, is safe, and follow-up radiographs are usually unnecessary; after FORCE, a soft bandage or removable splint with immediate discharge and no routine follow-up, the child stopping its use when it stops hurting. Do not overtreat them with an above-elbow cast; early mobilisation is safe.
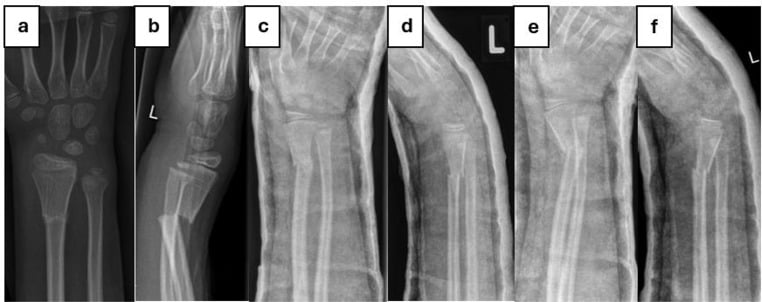
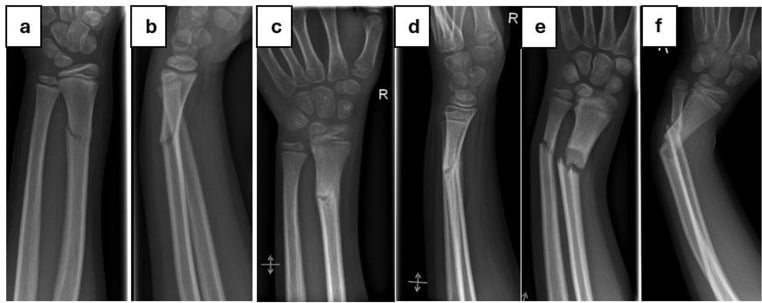
Greenstick fractures. Under 10° of angulation, a below-elbow cast for 4-6 weeks with serial radiographs, because a greenstick can re-angulate. Over 15-20°, complete the fracture under sedation or general anaesthesia by breaking the intact cortex: left intact, that cortex acts as a spring, and completing it allows full reduction without spring-back and stops the cast loosening and the fracture re-angulating as the swelling subsides. Then an above-elbow cast with a proper three-point mould and close follow-up for the first 2 weeks, when loss of reduction is common. An incomplete reduction leads to cast loosening and re-angulation.
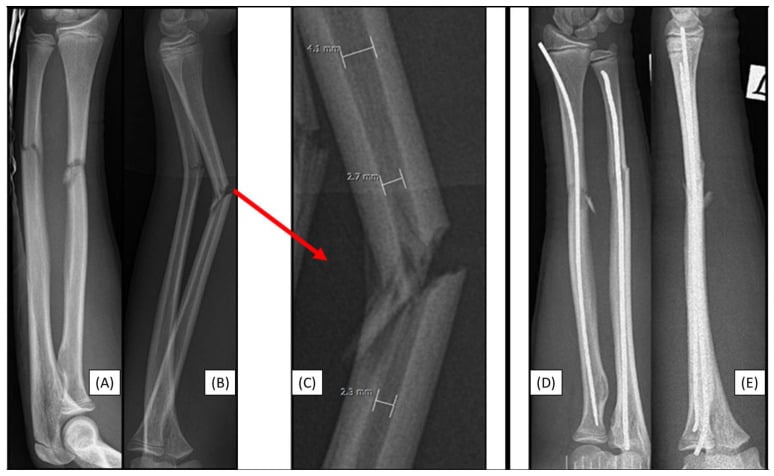
Complete both-bone fractures. Closed reduction under finger-trap or manual traction, correcting length, then rotation, then angulation, followed by an above-elbow cast with a well-moulded interosseous space and the forearm rotated as the deforming forces dictate (see Anatomy and Biomechanics). Post-reduction radiographs confirm the position: length re-established, angulation within the limits above, rotation anatomic. Consider ESIN if the fracture cannot be held.
The cast. A proper three-point mould is what holds the reduction, and the interosseous mould is the key part of it. Pad the bony prominences and make the cast well fitted but with room for swelling. Weekly radiographs for the first 2-3 weeks detect loss of reduction.
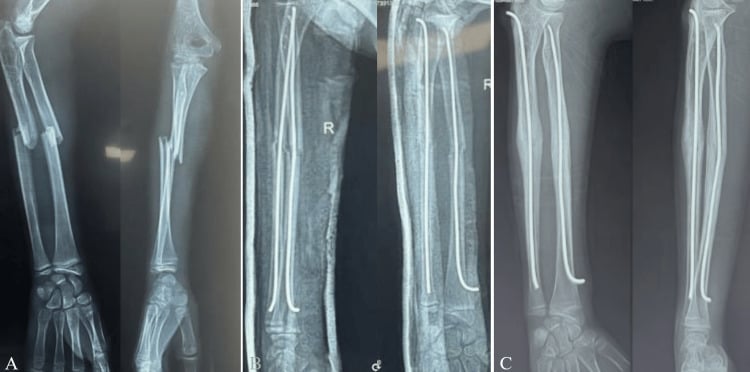
Elastic stable intramedullary nailing. ESIN is preferred over plating in paediatric fractures, and its place is the fracture that a cast cannot hold. The indications:
- Unacceptable reduction after a closed attempt
- Re-displacement in the cast
- Open fracture
- Polytrauma
- An older child or adolescent with an unstable pattern
- Segmental fractures
- Stability
- Stable
- Treatment
- Soft bandage or removable splint, immediate discharge, no routine follow-up (FORCE)
- Key Pearl
- Comfort duration only - the child stops using it when it stops hurting
- Stability
- Relatively stable
- Treatment
- Below elbow cast 4-6 weeks
- Key Pearl
- Watch for re-angulation
- Stability
- Unstable when completed
- Treatment
- Complete, reduce, above elbow cast
- Key Pearl
- 3-point mould essential
- Stability
- Unstable
- Treatment
- Closed reduction, above elbow cast
- Key Pearl
- Consider ESIN if unstable
- Stability
- Unstable
- Treatment
- Reduce ulna, check radial head
- Key Pearl
- Closed vs open reduction of ulna
- Stability
- Unstable
- Treatment
- Reduce radius, DRUJ usually stable
- Key Pearl
- Less common than in adults
Cast Quality and the Cast Index
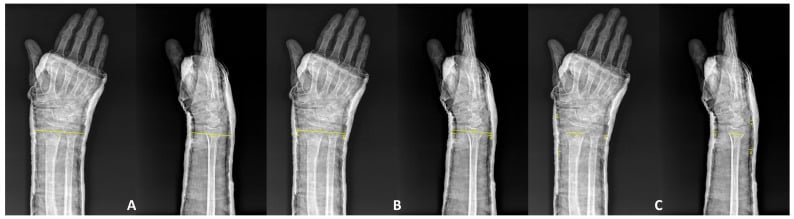
The management section stresses a well-moulded three-point cast, and the evidence (Bowman) shows that loss of reduction is common and happens early. The quality of the mould can be measured rather than judged by eye, and these indices are increasingly examined as the radiographic answer to "how do you know the cast is good?".
- What It Measures
- Internal cast width on the LATERAL view divided by the internal width on the AP view, at the fracture level
- Threshold / Meaning
- About 0.7 or less indicates good oval moulding; a value above 0.8 (a round cast) predicts loss of reduction
- What It Measures
- Quantifies the three-point mould relative to the fracture displacement
- Threshold / Meaning
- Higher values predict redisplacement of completely displaced distal radius fractures
- What It Measures
- Padding thickness relative to bone width at the apex of deformity
- Threshold / Meaning
- Excess padding lets the fracture move and the position slip
- What It Measures
- Space between the cast and the limb
- Threshold / Meaning
- A loose cast (large gap) permits redisplacement as swelling settles
Oval, not round. A well-moulded forearm cast is oval in cross-section, flattened over the volar and dorsal surfaces by the three-point mould, and that oval is what the cast index measures. A round, over-padded cast is the commonest technical reason for loss of reduction, which usually occurs within the first three weeks (Bowman). If the cast index looks poor on the check radiograph, re-mould or re-cast rather than wait for the fracture to slip.
Surgical Technique Considerations
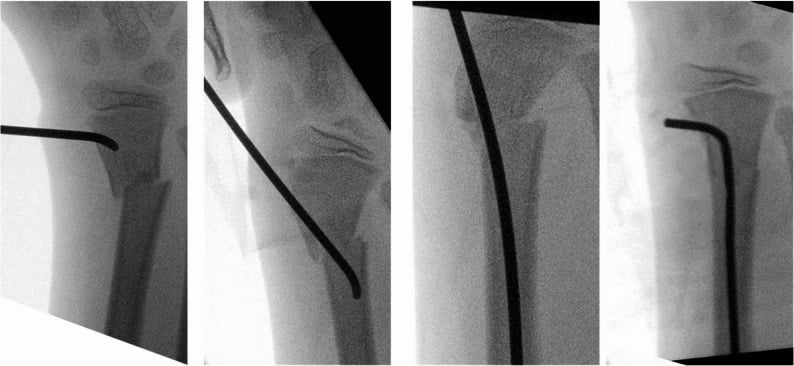
Radius entry. The radial nail is passed retrograde, from a dorsal entry just proximal to Lister's tubercle or a lateral entry above the distal radial physis. Avoid a palmar entry because of the flexor tendons.
Ulna entry. The ulnar nail is passed antegrade, from the olecranon or the proximal metadiaphysis. Avoid the distal ulnar physis, which is small and subcutaneous.
Technical points. Pre-bend the nails to recreate the radial bow and keep clear of the physis. Nails of 2-2.5 mm are typical, and both bones should ideally be nailed. Seat the nails well to avoid irritation and protrusion, and remove them at 6-12 months.
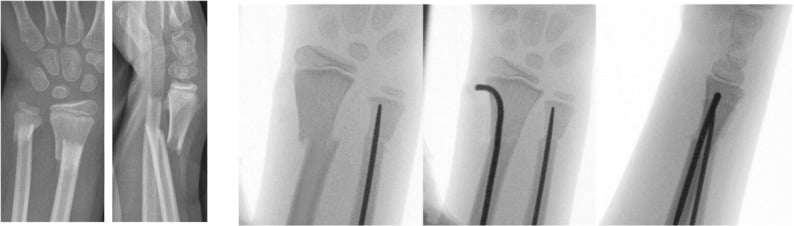
Open reduction. It is needed when:
- Closed reduction has failed
- The fracture is open
- There is an associated vascular injury
- A Monteggia is irreducible
- A Monteggia presents late
Approach. Henry's anterior approach for the radius and a direct subcutaneous approach for the ulna. Preserve the periosteum and avoid extensive stripping.
ESIN: Complications and Pitfalls
- Mechanism
- Prominent or long nail ends, especially over the subcutaneous distal ulna
- Avoidance / Management
- Trim and bury the nail ends; bursitis may settle or prompt earlier removal
- Mechanism
- Lateral/dorsal radial entry lies near the superficial radial nerve and the EPL tendon at Lister's tubercle
- Avoidance / Management
- Open entry with nerve protection; EPL can be irritated or, rarely, rupture
- Mechanism
- Open reduction or proximal radial manipulation
- Avoidance / Management
- Recognise the at-risk approach; usually a recovering neurapraxia
- Mechanism
- Closed passage fails to cross the fracture, common in adolescents
- Avoidance / Management
- Up to around 76% of nailed adolescents need open reduction of at least one bone (Freese)
- Mechanism
- A straight elastic nail fails to recreate the radial bow, especially near maturity
- Avoidance / Management
- Pre-bend the nails; consider plating in older adolescents (Freese)
- Mechanism
- Excess soft-tissue stripping, a single incision for both bones, or multiple passes
- Avoidance / Management
- Minimise passes and stripping; use separate incisions for the two bones
- Mechanism
- Stress riser through the healing bone and entry site
- Avoidance / Management
- Protect after removal and time removal appropriately (6-12 months)
- Mechanism
- Multiple forceful reduction and nailing passes with soft-tissue swelling
- Avoidance / Management
- Limit the number of passes; monitor closely with a low threshold for fasciotomy
Where the trouble is. ESIN is elegant in younger children, but its problems cluster in adolescents near skeletal maturity, where a straight elastic nail struggles to restore the radial bow and often forces an open reduction. That is why plating is increasingly chosen as the child approaches maturity; the numbers, and their limits, are in Areas of Uncertainty and Debate below.
Complications
- Incidence
- Up to 20%
- Cause
- Poor mould, swelling resolution
- Management
- Re-manipulate or ESIN
- Incidence
- Varies
- Cause
- Missed re-displacement
- Management
- Remodel if young, osteotomy if old
- Incidence
- Permanent
- Cause
- Inadequate reduction
- Management
- Osteotomy if symptomatic
- Incidence
- Rare but serious
- Cause
- Tight cast, soft tissue swelling
- Management
- Fasciotomy urgently
- Incidence
- 5-10%
- Cause
- Early return to activity
- Management
- Cast longer, protect 6+ months
- Incidence
- Rare
- Cause
- High-energy, single-incision for both bones
- Management
- Excision if symptomatic
- Incidence
- Rare
- Cause
- Incomplete imaging
- Management
- Late reconstruction
Refracture. It occurs in 5-10% of forearm fractures. The risk factors are an early return to full activity, removal of the cast too early, initial cortical comminution and stress risers from the previous fracture. Protect for 6 months after healing by avoiding high-risk activities; some surgeons recommend a splint for sport during this period, others recommend no specific protection, and either way the family is counselled about the risk.
Postoperative Care
Post-Treatment Protocol
Elevate the limb. Check the neurovascular status. Watch for compartment syndrome. Above-elbow cast if treated closed.
Weekly radiographs to check for re-displacement. Check the cast for tightness or looseness. Finger exercises.
Radiograph at 4 weeks to assess union. May convert to a below-elbow cast or removable brace mid-treatment.
Remove the cast once healing is clinical and radiological. Radiograph out of the cast. Commence range-of-motion exercises.
Avoid contact sports and high-risk activities; this is the refracture window. Full activities at 6 months.
Outcomes and Prognosis
Good outcomes. Expect an excellent result when the rotation is anatomically reduced, the angular malunion is within acceptable limits, any Monteggia or Galeazzi has been identified and treated, and the forearm has been protected from refracture.
Poor prognostic factors. The failures of those same steps:
- Rotational malunion
- Missed Monteggia, with chronic radial head dislocation
- Late diagnosis of compartment syndrome
Guidelines, Registries & Global Practice
- Forearm fractures are among the most common childhood fractures worldwide, with the distal radius the single most frequent site
- Peak incidence in the pre-pubertal growth spurt (boys ~12-14, girls ~10-12 years)
- Incidence has risen over recent decades in several high-income populations, linked to activity, body mass and reduced bone density
- Boys affected more than girls overall; trampolines, playground falls and contact sport dominate mechanisms
- No implant registry tracks paediatric forearm fixation the way arthroplasty registries do; evidence comes from RCTs and large cohorts
- The UK FORCE trial (965 children) is the landmark dataset for torus fractures, driving de-implementation of casting and follow-up
- Cohort data (Bowman) quantify that ~half of displaced both-bone fractures lose acceptable position, mostly within 3 weeks
Side-by-Side Guideline and Society Positions
- Torus (buckle)
- Removable support, discharge, no routine follow-up (post-FORCE)
- Displaced shaft
- Reduction; surgery if unstable or unacceptable position
- Emphasis
- Minimising overtreatment and radiation
- Torus (buckle)
- Splint or short-arm cast, minimal imaging
- Displaced shaft
- Closed reduction; ESIN/plate for failed or unstable
- Emphasis
- Shared decision-making, function
- Torus (buckle)
- Stable - immobilise symptomatically
- Displaced shaft
- PDFC algorithm: cast vs ESIN vs external fixation by pattern
- Emphasis
- Pattern-based fixation, preserve periosteum
- Torus (buckle)
- Removable splint increasingly standard
- Displaced shaft
- ESIN favoured for unstable diaphyseal fractures
- Emphasis
- Less invasive surgery, early function
High-Resource vs Limited-Resource Practice
- Image intensifier and procedural sedation/GA readily available for closed reduction
- ESIN and locking plates stocked; theatre access within hours to days
- Trend toward de-implementation: fewer casts, fewer follow-up radiographs for stable patterns
- Closed reduction and well-moulded casting remain the mainstay and give excellent results in growing bone
- Implants and intra-operative imaging may be scarce; emphasis on getting the first cast right and on clinical rotation assessment
- Strong reliance on remodelling means angular deformity is more often accepted; rotational reduction and exclusion of Monteggia remain non-negotiable everywhere
Special Considerations
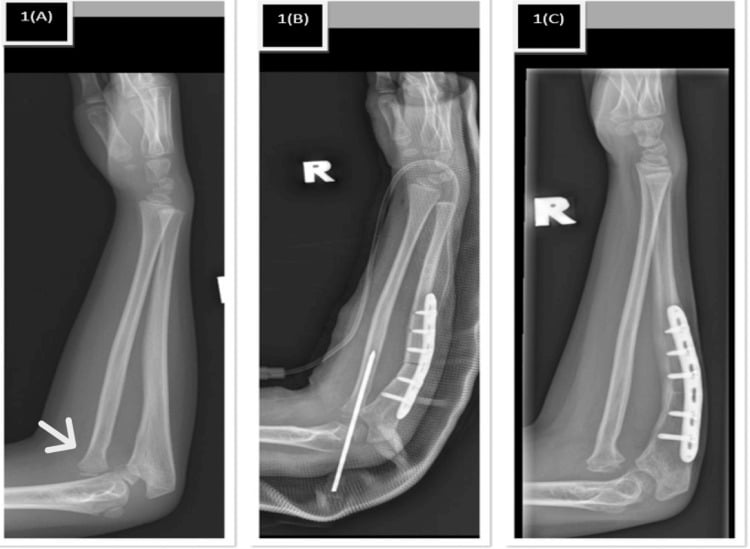
Monteggia fracture-dislocation. The triad is an ulna fracture, a radial head dislocation and a disrupted annular ligament. The most common lesion in children is Bado type I, an extension injury with apex-anterior ulnar angulation and anterior dislocation of the radial head. Closed reduction of the ulna usually reduces the radial head with it; the arm is held in an above-elbow cast in flexion and supination, and the radiocapitellar line is checked again after reduction. If the radial head remains dislocated, open reduction may be needed, because the annular ligament may be entrapped.
Galeazzi fracture-dislocation. Reduce the radius fracture; the DRUJ usually reduces spontaneously in children. Hold in an above-elbow cast in supination.
Plastic deformation. Bowing of the bone without a visible fracture line is unique to paediatric bone, and a significant bow restricts rotation. A bow under 10° is accepted; 10-20° is considered for reduction; over 20° requires reduction under general anaesthesia with sustained force. The technique is sustained pressure over the apex of the deformity for 2-3 minutes, under which the bone slowly straightens; it cannot be snapped and must be bent gradually.
Areas of Uncertainty and Debate
Exact acceptable angulation thresholds. There is no universally agreed figure. Published thresholds vary by age, fracture level and plane, and most are based on retrospective series rather than trials. The figures used here, 10 degrees over 10 years and 15-20 degrees under 10 years, are pragmatic conventions, not hard biological limits.
One bone or both at surgery. When operating on a both-bone fracture, some surgeons nail only the more unstable bone, arguing that the second reduces and stays once one is stabilised. Others routinely fix both to maximise stability. Evidence is limited and practice varies.
ESIN versus plating in adolescents. As children approach skeletal maturity, remodelling falls and ESIN may fail to restore the radial bow. Comparative data (Freese et al.) show plating restores anatomy more reliably: the radial bow was significantly smaller and more distal after nailing, and 76% of nailed patients needed an open reduction of at least one bone. The complication comparison points the same way but is not statistically significant in a series of 32 plated against 70 nailed, so it is a trend rather than a proven difference. Plating costs a larger scar; the frequently quoted 91% reoperation rate for nails is mostly planned implant removal, not failure.
Routine implant removal after ESIN. Whether nails should always be removed is debated. Removal avoids late irritation and theoretical refracture through a stress riser, but adds a second anaesthetic and procedure. Practice ranges from routine removal at 6-12 months to leaving asymptomatic nails in situ.
Follow-up radiographs in stable patterns. Following the FORCE trial, torus fractures increasingly receive no follow-up imaging at all. Extending a 'minimal follow-up' approach to other stable patterns, such as the minimally angulated greenstick, is an active area of de-implementation.
MCQ Practice Points
Q: Which type of deformity in pediatric forearm fractures does NOT remodel? A: Rotational deformity. Angular deformity remodels well, especially in the sagittal plane and in younger children. Rotational malunion is permanent and must be anatomically reduced.
Q: What is a Bado Type I Monteggia lesion? A: Ulna fracture with apex anterior angulation and anterior dislocation of the radial head. This is the most common type in children (70%).
Q: How much angulation is acceptable in a forearm fracture in a 12-year-old child? A: Maximum 10 degrees. Over 10 years of age, remodeling potential is limited. Under 10 years, up to 15-20 degrees may be accepted.
Q: Why should a significantly angulated greenstick fracture be 'completed' during reduction? A: To prevent spring-back re-angulation. The intact cortex acts as a spring. Completing the fracture allows full correction and prevents cast loosening and re-angulation.
Q: What does the radiocapitellar line assess? A: Position of the radial head relative to the capitellum. A line through the radial shaft should pass through the capitellum center on all views. Deviation indicates radial head dislocation (Monteggia).
Q: What is the main indication for ESIN in pediatric forearm fractures? A: Unstable fractures that cannot be maintained in cast, including failed closed reduction, re-displacement in cast, open fractures, and polytrauma.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 7-year-old boy fell off playground equipment. X-rays show complete both-bone forearm fractures at the mid-shaft with 25 degrees of angulation on both AP and lateral views and 100% displacement. Neurovascular exam is normal. How would you manage this?”
“A 5-year-old girl presents after a fall with a displaced ulna fracture with apex anterior angulation. She has pain and limited motion at the elbow. How would you assess and manage this?”
“A 9-year-old presents with a greenstick fracture of the distal radius with 20 degrees of apex volar angulation on the lateral view. The intact cortex is on the volar (palmar) side. How would you manage this?”
Key Facts
- Most common pediatric fracture (45%)
- Rotation does NOT remodel
- Sagittal plane remodels better than coronal
- Always check radiocapitellar line
Acceptable Angulation
- Under 10 years: 15-20°
- Over 10 years: maximum 10°
- Mid-shaft less forgiving than metaphyseal
- Rotation: ZERO tolerance
Fracture Patterns
- Buckle: Splint 3-4 weeks
- Greenstick: Complete if angulated greater than 15-20°
- Complete: Closed reduction, above elbow cast
- Monteggia: Ulna + radial head dislocation
ESIN Indications
- Failed closed reduction
- Re-displacement in cast
- Open fracture
- Polytrauma, older child
Monteggia Bado Types
- Type I: Anterior radial head (70%)
- Type II: Posterior radial head
- Type III: Lateral radial head
- Type IV: Anterior + radial fracture
Evidence Base and Key Studies
FORCE Trial - Torus (Buckle) Fracture Immobilisation
- Multicentre randomised equivalence trial across 23 UK emergency departments, 965 children aged 4-15 years
- Offer of a soft bandage with immediate discharge was equivalent to rigid immobilisation for pain at 3 days (adjusted difference -0.10, 95% CI -0.37 to 0.17)
- No between-group difference in function or quality of life over 6 weeks
- Complication rates very low and similar (offer-of-bandage 1.0% vs rigid immobilisation 0.6%)
Davidson et al. - Simple Treatment of Distal Radius Torus Fractures
- Prospective randomised trial of 201 children comparing plaster cast vs a removable Futura-type wrist splint for 3 weeks
- No difference in outcome between groups; all patients achieved a good result
- Only 1 child did not tolerate the splint
- No evidence that follow-up beyond the day after diagnosis was required
Bowman et al. - Predictors of Failure of Nonoperative Both-Bone Fractures
- 321 children with complete both-bone shaft fractures; 282 treated by closed reduction and casting
- 51% exceeded acceptable angulation thresholds within follow-up; of these, 55% failed by the end of week 1 and 95% by week 3
- Highest odds of failure: age 10 years or older (OR 2.79), proximal-third radius fractures (OR 6.81), and initial ulnar angulation under 15 degrees (OR 2.94)
- Thresholds used: 10 degrees proximal, 15 degrees middle, 20 degrees distal in younger children; 10 degrees at all levels in older children
Schmittenbecher - State-of-the-Art Forearm Shaft Fracture Treatment
- Synthesis of a single-institution series since 1976; before ESIN, 95.9% of fractures were treated conservatively and a significant proportion healed with malalignment and poor function
- Introduction of elastic-stable intramedullary nailing (ESIN) produced very satisfactory functional results for unstable fractures
- External fixation reserved for open, comminuted or distal dia-metaphyseal fractures in older children/adolescents
- Proposes a 'primary definitive fracture care' algorithm matching method to fracture pattern
Freese et al. - Plate vs Intramedullary Fixation in Adolescents
- 102 adolescents (10-16 years) with diaphyseal both-bone fractures: 32 plated, 70 nailed
- Of the complications that occurred in the nailed group, 55% were graded major, against no major complications in the plate group - but read both halves carefully: this is 55% OF COMPLICATIONS, not of patients, and the comparison did NOT reach significance (P=0.1)
- 76% of nailed patients required open reduction of at least one bone; radial bow was smaller and more distal after nailing
- Second operation needed in 91% of nailed vs 3% of plated patients (mostly planned implant removal)
Price et al. - Outcome of Malunited Forearm Fractures in Children
- 39 skeletally immature children with malunited diaphyseal both-bone fractures followed a mean of 5 years 9 months (Monteggia/Galeazzi/greenstick excluded)
- 92% had good or excellent results despite residual angulation, complete displacement or loss of radial bow
- Only 9 of 39 had any loss of motion; age at injury did not correlate with recovery of rotation
- Distal fractures had a better prognosis than proximal fractures
Ko et al. - Predictors of Outcome After Chronic Monteggia Reconstruction
- 28 children reconstructed for chronic (missed) Monteggia with radial-head open reduction, ulnar osteotomy and annular ligament reconstruction
- Shorter interval from injury and lower skeletal maturity (Sauvegrain score) predicted better outcomes
- With low skeletal maturity and an interval of 7 months or less, ideal outcomes were achieved in 85.7% with no redislocation or arthritis
- Above skeletal ages of ~14 years (boys)/11.5 years (girls), reconstruction should be approached with great caution