Angular Knee Deformities | Physiological vs Pathological | Blount Disease | Guided Growth
- Physiological evolution: Birth varus (10-15°) → neutral (18-24mo) → peak valgus (3-4yrs, 10-15°) → adult alignment (7yrs, 5-7° valgus)
- Red flags for pathology: Asymmetry, rapid progression, extreme angle, short stature, onset after walking established
- Blount disease: Tibia vara from disrupted medial proximal tibial physis. Infantile (1-3yrs) vs adolescent types
- Rickets: Systemic cause of angular deformity - nutritional or renal. Bilateral, symmetric, physeal widening
- Guided growth: Hemiepiphysiodesis with 8-plates to correct angular deformity in skeletally immature patients
- “Measure intercondylar distance (varus) or intermalleolar distance (valgus) clinically
- “Mechanical axis deviation on standing long leg X-ray is the gold standard
- “Metaphyseal-diaphyseal (Drennan) angle greater than 16° suggests Blount disease (original cut-off was 11°)
- “Always check calcium, phosphate, vitamin D, ALP in bilateral deformity
Overview and Epidemiology
Definitions. Genu varum, "bow-legs", is a tibiofemoral angle in varus: with the ankles together the knees stand apart. Genu valgum, "knock-knees", is the reverse: with the knees together the ankles stand apart. Both are coronal-plane malalignments of the knee, and the first job in clinic is to decide whether the one in front of you is a stage of normal development or a disease.
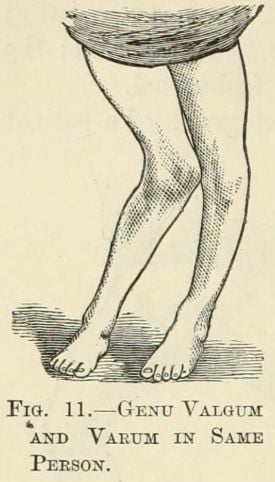
The physiological arc. Newborns are bowed, about 10-15° of varus, from intrauterine positioning. The legs straighten to neutral by 18-24 months, swing into a maximum valgus of 10-15° at 3-4 years, and then settle gradually to the adult alignment of 5-7° valgus by 6-7 years. Physiological deformity is symmetric and keeps to this timetable, and that is the whole of its definition.
Who has the pathological forms. Physiological angular deformity is extremely common and usually normal. Infantile Blount disease is more common in children of African descent, early walkers and the obese. The nutritional form of rickets is rare in developed countries; renal osteodystrophy is its counterpart in chronic kidney disease.
Pathophysiology and Mechanisms
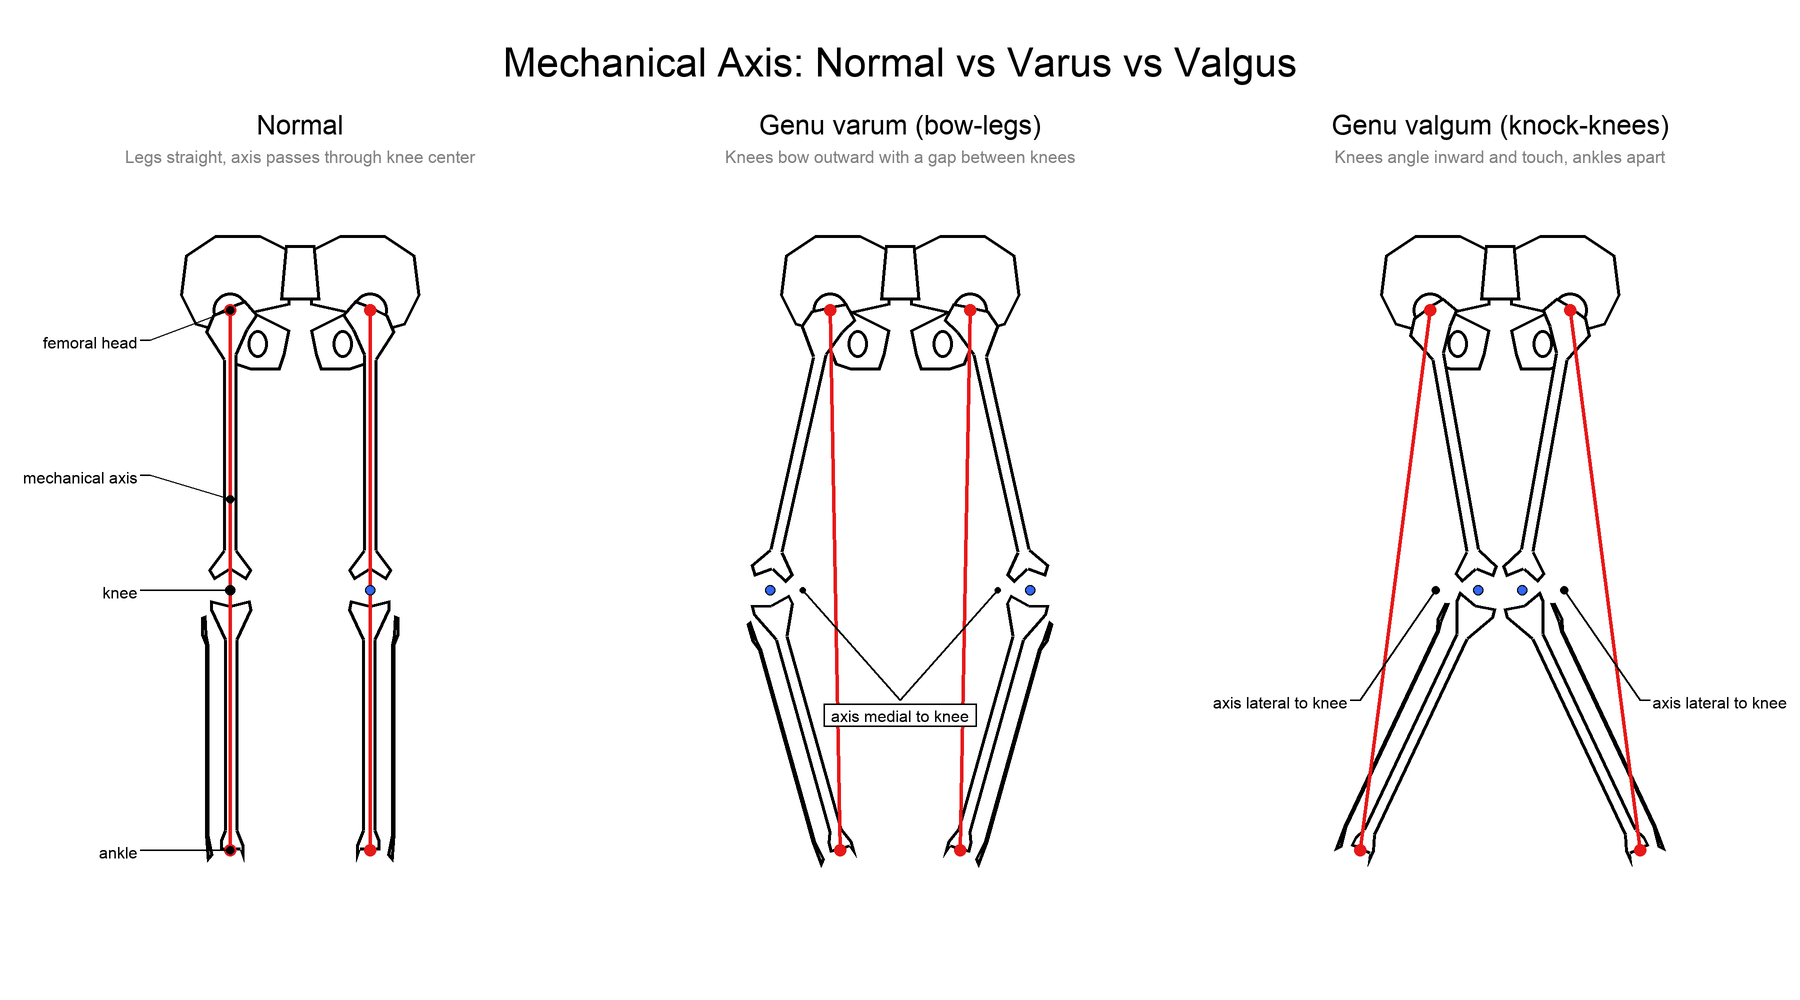
The mechanical axis. The mechanical axis of the limb is the line from the centre of the femoral head to the centre of the ankle, assessed on a standing long-leg radiograph. Normally it passes through or just medial to the centre of the knee, the reference figure being about 8 to 10 mm medial; the distance from the axis to the knee centre is the mechanical axis deviation (MAD). In genu varum the knees bow apart and the axis passes further medial to the knee, overloading the medial compartment. In genu valgum the knees touch with the ankles apart and the axis passes lateral to the knee, overloading the lateral compartment.
- Definition
- Centre of femoral head to centre of ankle
- Normal Value
- Passes through or just medial to knee centre
- Definition
- Femoral and tibial diaphyseal axes
- Normal Value
- 5-7° valgus tibiofemoral angle
- Definition
- Medial proximal tibial angle
- Normal Value
- 85-90°
- Definition
- Lateral distal femoral angle
- Normal Value
- 85-90°
Where the growth is. The proximal tibial physis provides 55% of tibial growth. The distal femoral physis provides 70% of femoral growth and 37% of the length of the leg. The distal femur contributes more to angular correction than the proximal tibia because it grows faster. Asymmetric loading affects physeal growth according to the Hueter-Volkmann law, compression retarding growth and tension stimulating it.
Guided growth. Hemiepiphysiodesis retards growth on one side of the physis and lets the other side, still growing, bring the limb back into line. The 8-plate does this by creating a tension-band effect; screw and staple methods are also used. Overcorrection is a risk if the hardware is not removed promptly. When planning surgery, consider the site of maximum deformity, the centre of rotation of angulation (CORA).
Classification Systems
Aetiology-Based Classification
Identifying the cause is essential for appropriate management.
- Examples
- Normal developmental pattern
- Management Approach
- Observation, reassurance
- Examples
- Infantile tibia vara, adolescent tibia vara
- Management Approach
- Bracing (infantile), surgery
- Examples
- Rickets (nutritional, X-linked hypophosphatemic, renal)
- Management Approach
- Treat metabolic cause, then guided growth
- Examples
- Achondroplasia, multiple epiphyseal dysplasia
- Management Approach
- Manage deformity, often complex
- Examples
- Physeal injury, malunion
- Management Approach
- Depends on growth remaining
- Examples
- Post-septic physeal damage
- Management Approach
- May need surgical correction
Blount disease. Tibia vara from a disorder of the medial proximal tibial physis, isolated to the knee and without systemic features. The infantile form presents at 1-3 years and is often bilateral, though it may be asymmetric; the adolescent form presents after 10 years and is often unilateral. Obesity is the major risk factor, especially in the adolescent. The infantile form may respond to bracing; the adolescent form requires surgery.
Rickets. A systemic disease of impaired mineralisation from low calcium or phosphate. The deformity is bilateral and symmetric, with short stature from generalised growth impairment. The physes are wide, cupped and frayed on the radiograph, and the costochondral junctions swell into a rachitic rosary. Rickets can produce either pattern, knock-knees or bow-legs; the metabolic cause is treated first.
The classic acquired cause of childhood genu valgum is the Cozen phenomenon: a proximal tibial metaphyseal fracture (often a minimally displaced greenstick injury in a child around 2-8 years) is followed weeks to months later by a progressive valgus deformity of that tibia. The mechanism is asymmetric medial overgrowth or physeal stimulation rather than malunion, so it occurs even after an anatomically reduced fracture. The crucial examinable point is the natural history: the valgus usually peaks at 12-18 months and then spontaneously remodels and largely corrects over several years, so management is observation and parental counselling, not acute osteotomy (early osteotomy tends to recur). Persistent severe deformity in an older child with little growth remaining is the exception that may need guided growth (medial hemiepiphysiodesis). Warn parents at the time of the original fracture that valgus may develop and is usually self-correcting.
Clinical Assessment
History. The story tells you whether the deformity is keeping to the physiological timetable, and it screens for the systemic causes before you examine a single joint. Ask about:
- Age of onset - when the parents first noticed the deformity
- Progression - improving, stable or worsening
- Walking age - early walkers are at risk of Blount disease
- Family history - skeletal dysplasia, rickets
- Diet and sun exposure - vitamin D intake, the risk of nutritional rickets
- Medical history - renal disease, gastrointestinal malabsorption
Gait. Watch the knee in stance for a lateral thrust, the knee appearing to "pop out" laterally as the limb loads. In-toeing or out-toeing may coexist with an angular deformity, so assess the overall gait pattern and the foot progression angle as well.
A lateral thrust during gait is NEVER physiological. It indicates significant varus with medial collateral laxity or tibia vara. This finding warrants investigation and likely treatment.
Standing examination. With the ankles together, measure the intercondylar distance for varus; with the knees together, measure the intermalleolar distance for valgus. Compare the two sides, and record the rotational profile, because internal tibial torsion may coexist.
Systemic examination. Short stature suggests skeletal dysplasia or rickets. Feel the wrists for the physeal widening of rickets and the chest for a rachitic rosary, and look for the dysmorphic features of a skeletal dysplasia.
Red flags. Physiological deformity corrects; pathological deformity persists. Suspect pathology when there is:
- Asymmetry between the two sides
- Rapid progression beyond the expected pattern
- An extreme angle: varus over 15° after age 2, valgus over 15° after age 5
- Short stature
- A lateral thrust in gait
- Deformity persisting or worsening after the age at which it should have corrected
- Physiological Varus
- Less than 2 yrs, resolving
- Blount Disease
- Infantile: 1-3yrs, progressive
- Rickets
- Any age, often bilateral
- Physiological Varus
- Symmetric
- Blount Disease
- Often bilateral but may be asymmetric
- Rickets
- Symmetric
- Physiological Varus
- Normal physes
- Blount Disease
- Medial tibial beaking, MDA greater than 16°
- Rickets
- Physeal widening, cupping, fraying
- Physiological Varus
- None
- Blount Disease
- Lateral thrust, internal tibial torsion
- Rickets
- Short stature, rachitic rosary, bowing
- Physiological Varus
- Observation
- Blount Disease
- Brace (early) or surgery
- Rickets
- Vitamin D/phosphate, guided growth
Investigations
When to image. Request radiographs for the child with any of the red flags, asymmetry, an extreme angle, a pattern that is not physiological, a lateral thrust or short stature, and for the child who simply concerns you clinically. The film to ask for is a standing AP long-leg radiograph, for accurate assessment of the mechanical axis. Bilateral deformity earns bloods as well.
- When Used
- Angular deformity requiring assessment
- What to Look For
- Mechanical axis deviation, site of deformity
- When Used
- Initial assessment, Blount diagnosis
- What to Look For
- Physeal changes, metaphyseal beaking, MDA
- When Used
- Suspected rickets
- What to Look For
- Physeal widening, cupping, fraying
- When Used
- Bilateral deformity, suspected metabolic cause
- What to Look For
- Low Ca/PO4/Vit D, high ALP in rickets
- When Used
- Physeal bar suspected, Blount assessment
- What to Look For
- Physeal status, bar extent
The metaphyseal-diaphyseal angle. Described by Levine and Drennan with an original threshold of over 11°; the higher cut-off of over 16° popularised by Feldman and Schoenecker is the modern working value suggesting Blount disease, with an indeterminate grey zone between 9° and 16°. Use the two thresholds for opposite purposes, because the test is asymmetric. Feldman found that only one Blount limb measured under 11°, so an MDA below 11° effectively rules Blount out and is the number to reassure with. But 37% of physiologically bowed limbs (66 of 179) also exceeded 11°, so that threshold cannot rule it in; on its own it would label more than a third of normally bowed toddlers. Above 16° the separation is real (means 9° physiological versus 19° Blount). And Feldman's own conclusion stands: the MDA "should not be the sole criterion", so combine it with age, symmetry, progression and the rest of the radiograph.
Other measurements. The tibial metaphyseal angle assesses the severity of tibia vara. Gordon's epiphyseal-metaphyseal angle is an adjunct that may improve early discrimination of Blount disease from physiological bowing.
Focal fibrocartilaginous dysplasia (FFCD) is an under-recognised cause of unilateral infantile tibia vara that mimics infantile Blount disease. It is caused by an abnormal focal fibrocartilaginous lesion at the insertion of the pes anserinus on the medial proximal tibial metaphysis, which tethers medial growth. The radiographic clue separates it from Blount: FFCD shows a sharply marginated, sclerotic cortical defect or radiolucency at the medial metaphyseal-diaphyseal junction (often an abrupt "step" or beak with focal angulation) rather than the medial physeal and epiphyseal beaking or depression of Blount, and the proximal tibial physis itself looks normal. The examinable point is the benign natural history: most FFCD spontaneously resolves with growth over 1-3 years, so management is usually observation, with corrective osteotomy reserved for the minority with progressive or non-resolving deformity. Consider it whenever an apparent unilateral "infantile Blount" has a focal metaphyseal lesion but a normal physis.
Management Algorithm
Conservative Management
Who. The physiological deformity is the most common presentation: it follows the expected pattern for age, it is symmetric, and there is no lateral thrust.
What to do. Reassure and educate the parents, and review the child clinically every 6-12 months; serial clinical photographs document the change. Radiographs are rarely needed if the pattern is typical. Expect correction by age 6-7 for valgus, earlier for varus.
What not to do. No bracing or orthotics are required for true physiological deformity. They do not hasten correction.
Surgical Technique
Tension-Band Plating (8-Plate)
This is the standard guided growth technique for angular deformity.
Surgical Steps
The standing long-leg radiograph gives the mechanical axis and the site or sites of deformity, the CORA, and from that the decision between distal femur, proximal tibia or both.
Supine on a radiolucent table, with the affected side accessible and the image intensifier available.
A small incision, 2-3 cm, over the physis on the convex side of the deformity: the medial distal femur for valgus, the lateral proximal tibia for varus.
Identify the physis with fluoroscopy and place the 8-plate extraperiosteally, one screw in the epiphysis and one in the metaphysis, the screws parallel and the plate on the tension side.
Confirm the position on imaging and close in layers. No immobilisation is required.
Technical points. The screws must be parallel for the tension-band effect to work, and the plate should sit flush on the bone. Only the screws cross the physis; the plate must not violate it.
Afterwards. Weight-bear as tolerated, with follow-up radiographs every 3 months.
Complications
- Incidence
- Common if hardware not removed
- Prevention/Management
- Regular monitoring, prompt removal
- Incidence
- Variable
- Prevention/Management
- Ensure adequate growth remaining
- Incidence
- Blount: significant if growth remaining
- Prevention/Management
- Address physeal bar, consider osteotomy
- Incidence
- Common (8-plate)
- Prevention/Management
- May need removal after correction
- Incidence
- Rare with 8-plate
- Prevention/Management
- Proper technique, avoid physeal damage
- Incidence
- Rare but serious
- Prevention/Management
- Prophylactic fasciotomy for large corrections
Overcorrection is common if 8-plates are not removed promptly. Correcting past neutral is easy but creates the opposite deformity.
Postoperative Care and Rehabilitation
After guided growth. Wound care, weight-bearing as tolerated immediately, no immobilisation, and discharge on day 0 or 1. Normal activities resume quickly; the first follow-up radiograph at 6-8 weeks assesses early correction.
Monitoring. Every 3 months, a clinical and radiographic assessment with the mechanical axis measured on long-leg films, continued until the correction is achieved.
At correction. Once the alignment has normalised or is slightly overcorrected, the 8-plate is removed as day surgery. The limb may rebound slightly after removal, so a post-removal radiograph is taken at 3-6 months.
After osteotomy. Protected weight-bearing for 6-8 weeks with knee range-of-movement exercises, then progression to full weight-bearing and activity.
Outcomes
Physiological deformity. Near-universal spontaneous resolution; no intervention is needed in the vast majority.
Guided growth. A high success rate in appropriate candidates, with predictable correction, low morbidity, and reversibility if overcorrection occurs.
Blount disease. Infantile disease has a better prognosis when treated early; adolescent disease shows higher recurrence and often needs osteotomy. Residual malalignment carries a long-term risk of medial compartment osteoarthritis.
Guidelines, Registries & Global Practice
Global Epidemiology:
- Physiological angular variation is near-universal in toddlers and is the single commonest reason for paediatric orthopaedic referral for "bent legs"; the vast majority require only reassurance.
- Infantile Blount disease shows a higher reported prevalence in populations of African ancestry, in early walkers, and with rising childhood obesity; late-onset (adolescent) Blount tracks closely with the global obesity epidemic.
- Nutritional rickets remains an important and preventable cause worldwide, concentrated in infants with darker skin, limited sun exposure, exclusive prolonged breastfeeding without supplementation, and low dietary calcium; X-linked hypophosphataemic rickets and renal osteodystrophy are the main non-nutritional metabolic causes.
Guidelines, Side by Side:
- Focus
- Nutritional rickets
- Key Position
- Defines diagnosis (biochemistry plus physeal change); universal infant vitamin D supplementation and food fortification to prevent and eradicate rickets
- Focus
- Angular deformity work-up
- Key Position
- Standing long-leg alignment film as the reference standard; guided growth favoured while physis is open
- Focus
- Referral and observation
- Key Position
- Reassure and observe physiological patterns; refer red-flag features (asymmetry, lateral thrust, short stature, extreme angle)
- Focus
- Vitamin D prophylaxis
- Key Position
- Routine infant vitamin D supplementation to prevent rickets-related deformity
There is broad international agreement on the principles (observe physiological deformity, screen for metabolic causes in bilateral deformity, prefer guided growth while the physis is open) and no major society-level disagreement on the core algorithm — the genuine debates are technical (thresholds, timing) rather than national.
- There is no dedicated paediatric angular-deformity arthroplasty registry; evidence is from institutional series and multicentre study groups rather than national joint registries.
- Long-term registry-style follow-up matters because residual malalignment is a recognised risk factor for early medial compartment osteoarthritis, linking childhood correction to adult arthroplasty burden captured in national joint registries.
- Well-resourced settings: standing long-leg radiographs, MRI for physeal-bar assessment, tension-band plating and computer-assisted/hexapod external fixators are routinely available.
- Limited-resource settings: the priority shifts to public-health prevention of nutritional rickets (supplementation, fortification), clinical screening without long-leg films, and definitive osteotomy where staged guided growth or repeat hardware procedures are impractical.
- Parental concern is often driven by cultural norms about leg shape; clear reassurance about the physiological arc prevents unnecessary imaging and intervention everywhere.
Controversies and Areas of Uncertainty
Angular knee deformity is a high-volume but evidence-thin area: most data are retrospective single-centre series, and several practical questions remain genuinely unsettled. Examiners reward a candidate who can state what is established versus what is debated.
The MDA threshold and its grey zone. The original Drennan threshold (over 11°) over-calls Blount disease; the over 16° cut-off improves specificity but leaves a 9-16° grey zone where physiological bowing and early Blount overlap. Serial measurement and adjunct angles (for example Gordon's epiphyseal-metaphyseal angle) are more reliable than any single number.
Bracing, real or placebo? Reported bracing success in early infantile tibia vara is confounded by the fact that many young, low-stage cases would resolve spontaneously. There is no randomised evidence; brace type, dose and the true threshold for abandoning bracing remain debated.
Guided growth versus osteotomy in Blount disease. Guided growth is attractive but has a higher failure and recurrence rate in advanced Blount disease (Langenskiöld IV and above) and in obese adolescents, where many surgeons favour acute or gradual osteotomy. The optimal crossover point is not defined by high-level evidence.
Rebound and the timing of removal. Rebound after plate removal is common, over 40% of segments in long-term series. Whether to deliberately overcorrect, when to remove hardware, and whether to leave the plate in situ in younger children are all unresolved trade-offs against iatrogenic deformity.
State the principle, acknowledge the uncertainty, then commit to a defensible plan: "The evidence base is largely retrospective. I would use the MDA alongside serial clinical assessment rather than a single cut-off, reserve osteotomy for advanced or adolescent Blount disease, and counsel families that rebound is common and follow-up to maturity is mandatory."
MCQ Practice Points
Q: At what age is peak physiological genu valgum expected? A: Age 3-4 years, with approximately 10-15° valgus. This corrects to adult alignment (5-7° valgus) by age 7.
Q: What metaphyseal-diaphyseal (Drennan) angle suggests Blount disease? A: The original Drennan threshold was over 11°; the modern working value (Feldman and Schoenecker) of over 16° is more specific, with a 9–16° grey zone overlapping physiological bowing.
Q: Where is an 8-plate placed for genu valgum and what is its correction rate? A: On the medial side of the distal femur (convex side) to retard medial growth; expect roughly 1° per month, slightly slower at the proximal tibia.
Medicolegal Considerations
- Age, height, and clinical measurements (ICD/IMD)
- Gait assessment including lateral thrust
- Family history and dietary assessment
- Radiographic findings and measurements
- Need for hardware removal after correction
- Risk of overcorrection or undercorrection
- May need additional surgery (recurrence, other side)
- Osteotomy risks: compartment syndrome, nerve injury
Missing follow-up after 8-plate insertion can lead to overcorrection. Emphasize the importance of regular monitoring and document the follow-up plan clearly.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A mother brings her 18-month-old child concerned about 'bowlegs'. The child started walking at 11 months and the mother feels the legs are bowed.”
“A 2.5-year-old child presents with progressive bowlegs. They have been walking since 10 months. On examination, there is a noticeable lateral thrust during gait, and the varus appears worse on the right side.”
“A 9-year-old child presents with bilateral knock-knees that have been present for several years. The parents are concerned it is getting worse. The child is otherwise well and of normal height.”
Physiological Pattern
- Birth: 10-15° varus (bowlegs)
- 18-24 months: Neutral
- 3-4 years: Peak valgus (10-15°)
- 7 years: Adult alignment (5-7° valgus)
Red Flags for Pathology
- Lateral thrust during gait
- Asymmetry between sides
- Extreme angle beyond expected
- Short stature or systemic features
Blount Disease
- Tibia vara from medial proximal tibial physis
- Infantile (1-3yrs) vs Adolescent (greater than 10yrs)
- MDA greater than 16° diagnostic
- Langenskiöld staging determines treatment
Guided Growth (8-Plate)
- On convex side of deformity
- Valgus: medial distal femur
- Varus: lateral proximal tibia
- Correct approximately 1°/month
- Remove promptly after correction
Key Numbers
- MDA greater than 16° = Blount disease
- 5-7° = Normal adult tibiofemoral angle
- 1°/month = 8-plate correction rate
- At least 2 years growth needed for guided growth
Evidence Base
Salenius & Vankka — Natural History of the Tibiofemoral Angle
- Defined the developmental arc of the tibiofemoral angle from birth to maturity
- Maximal physiological varus in infancy, transitioning to peak valgus at approximately 3 years
- Spontaneous correction toward the adult value of mild valgus by around 7 years
- Wide spread of normal values reinforces that single measurements should be interpreted with age
Levine & Drennan — Metaphyseal-Diaphyseal Angle
- Introduced the metaphyseal-diaphyseal (Drennan) angle to quantify proximal tibial bowing
- 29 of 30 limbs with an angle over 11 degrees later developed radiographic tibia vara
- Only 3 of 58 limbs with an angle of 11 degrees or less progressed
- Approximately 60% of deformity in tibia vara arises in the proximal metaphysis versus around 20% in physiological bowing
Feldman & Schoenecker — Refining the MDA Threshold
- Mean MDA was 9 degrees in physiological bowing versus 19 degrees in Blount disease (p less than 0.0000001)
- An angle between 9 and 16 degrees carried over 5% risk of false-positive and false-negative classification
- 37% of physiological limbs exceeded 11 degrees, exposing the limitation of the original cut-off
- A threshold of 16 degrees better separates Blount disease from physiological bowing