PIPJ Flexion Deformity
- Hammer Toe: PIPJ flexion with neutral DIPJ and MTPJ - most common lesser toe deformity.
- Claw Toe: MTPJ hyperextension with PIPJ AND DIPJ flexion - often neurological cause.
- Mallet Toe: Isolated DIPJ flexion only - least common, affects terminal tendon.
- Flexible vs Rigid: Correctable with ankle plantarflexed (FDL relaxed) = flexible.
- Flexibility Test: Critical - determines soft tissue vs bone surgery.
- “Plantarflex ankle to test flexibility (relaxes FDL)
- “Always assess MTPJ stability - Drawer test
- “Flexible = FDL tenotomy/transfer
- “Rigid = PIPJ arthroplasty or arthrodesis
- “Address MTPJ if subluxed (Weil osteotomy)
Overview and Epidemiology
A hammer toe is flexed at the proximal interphalangeal joint (PIPJ), with the MTPJ neutral or extended and the DIPJ neutral. It is the most common lesser toe deformity, about 80% of all lesser toe pathology, and it predominantly affects the second toe, which is often the longest ray and is crowded by hallux valgus.
Who. Prevalence is 2-20% of the adult population. Women are affected 4-5 times more often than men, a difference put down to footwear, and the peak age is 40-60 years. The second toe is involved in 80% of cases, and 40% of patients have bilateral involvement.
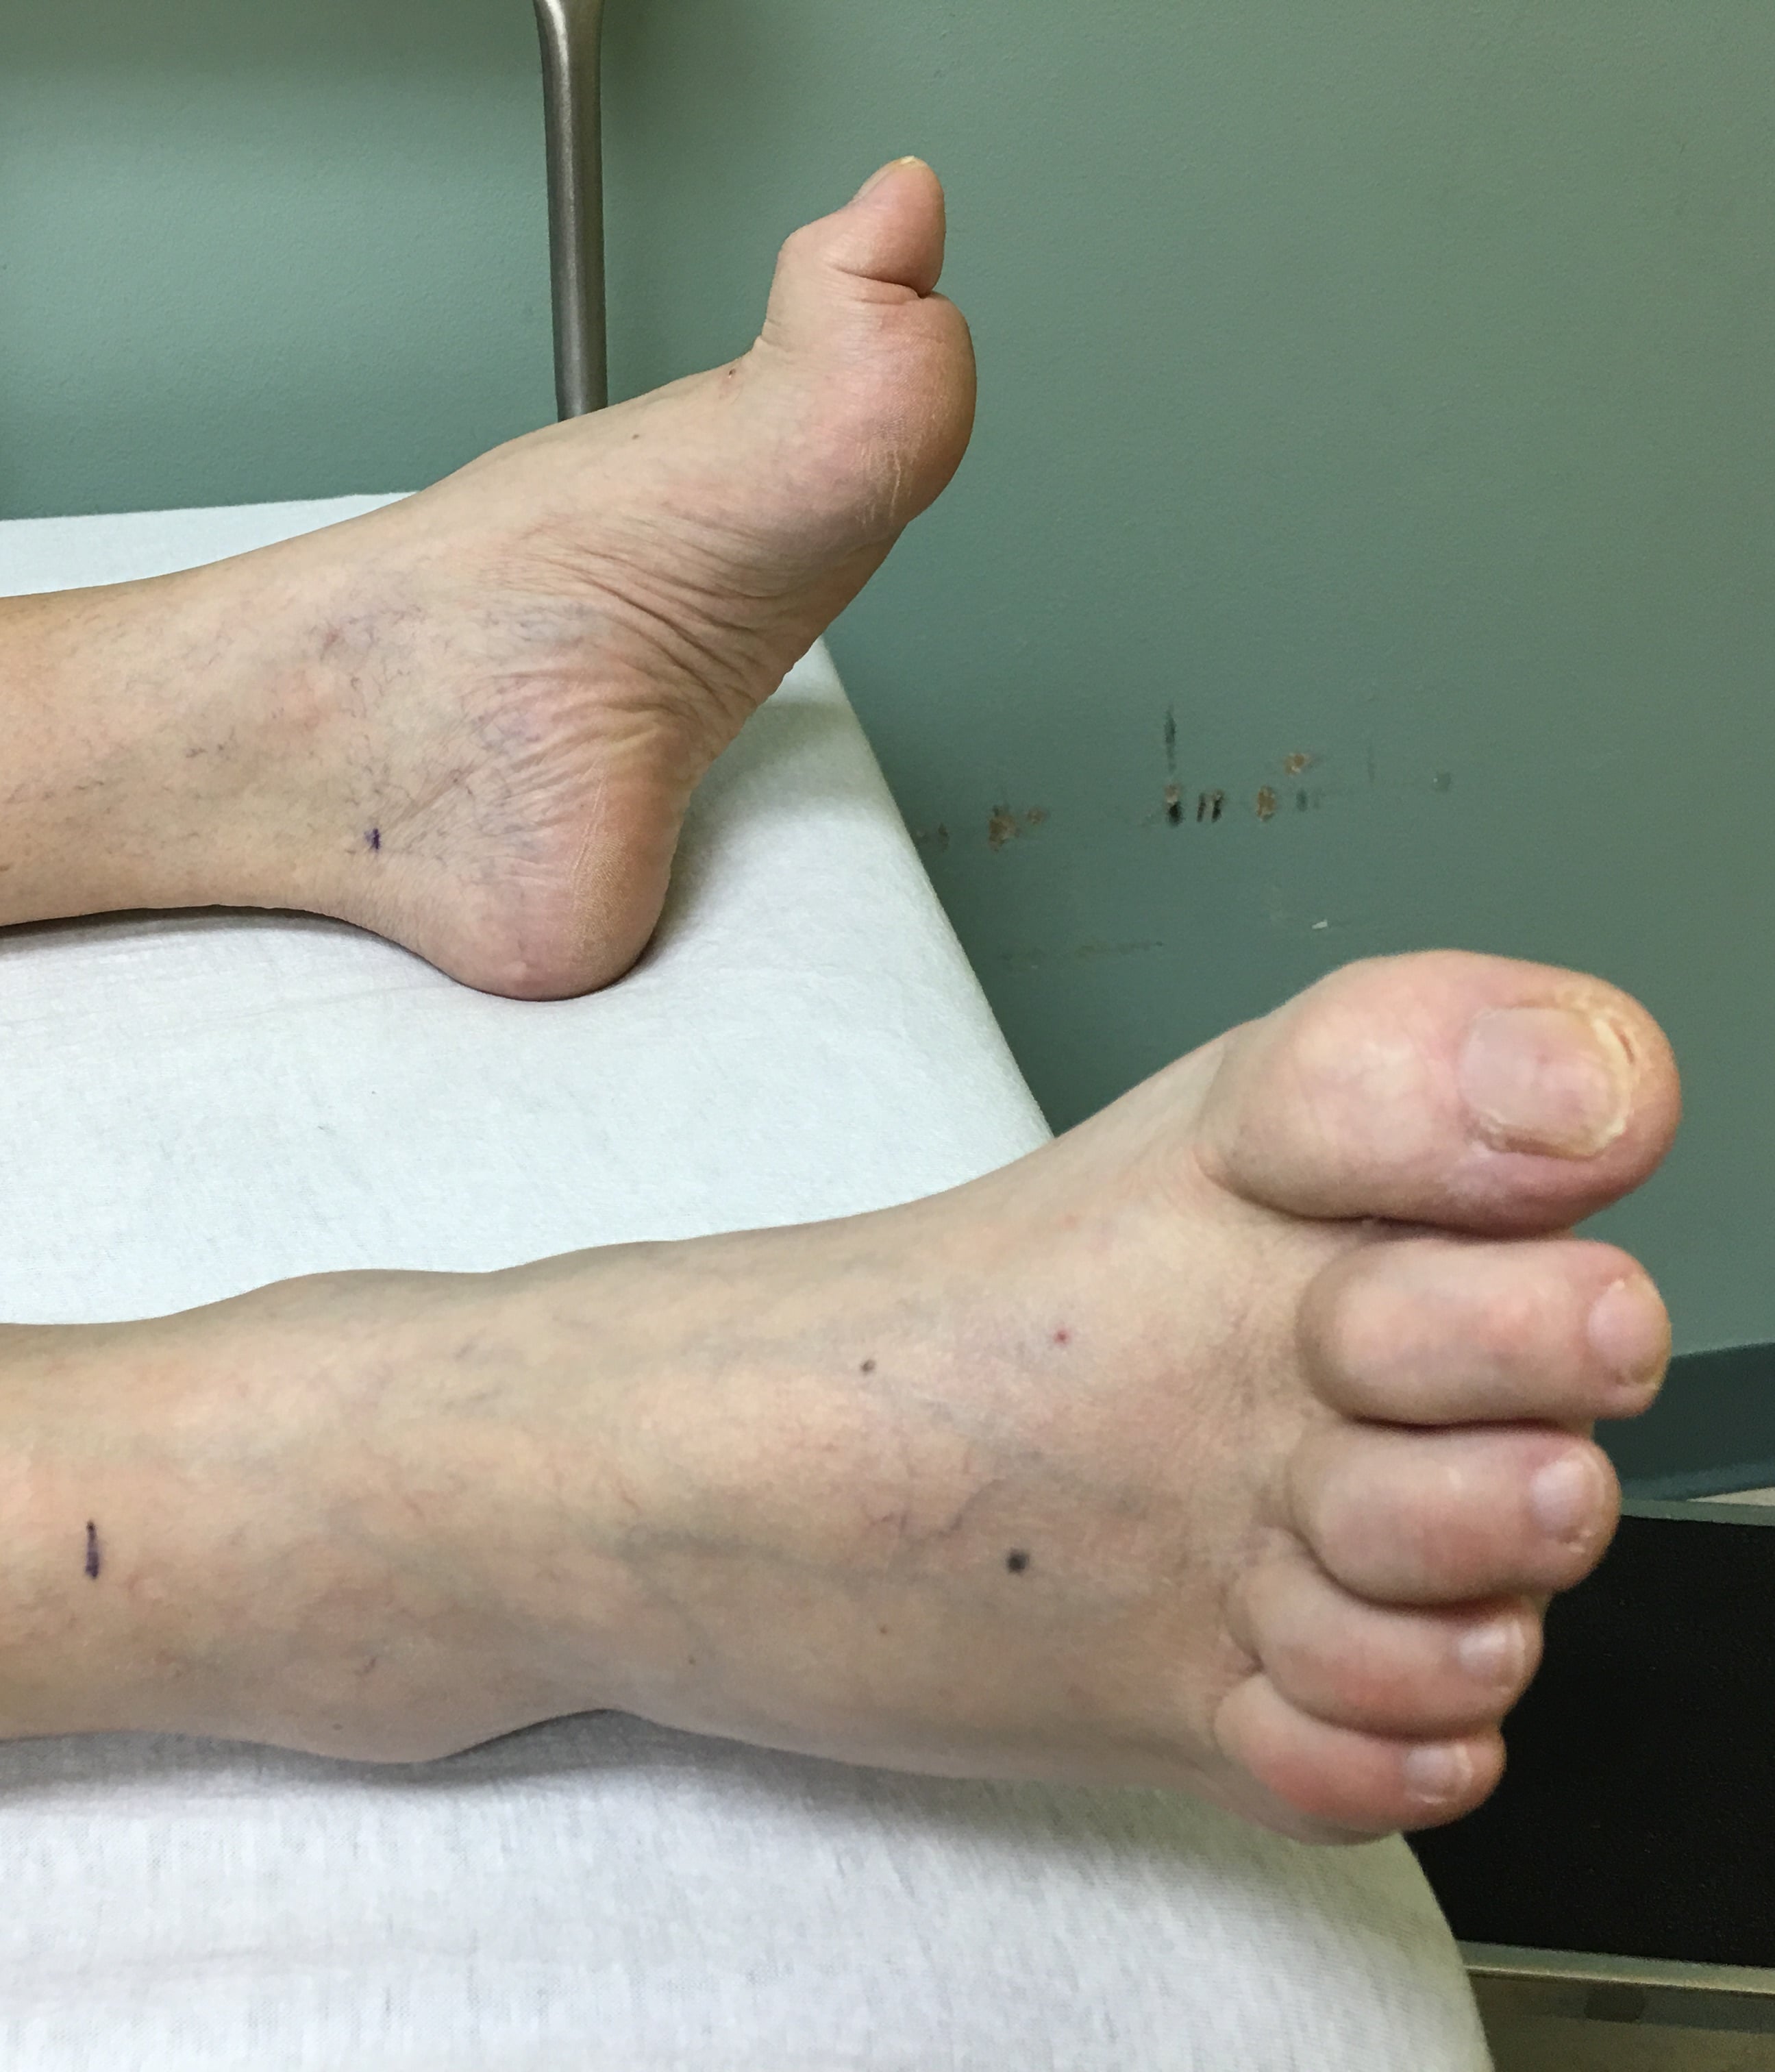
Hammer, claw and mallet. These are told apart by which joints are bent. Claw toe is often neurological in origin, and mallet toe, the least common, is a problem of the terminal tendon.
- Hammer Toe
- Neutral/Extended
- Claw Toe
- HYPEREXTENDED
- Mallet Toe
- Neutral
- Hammer Toe
- FLEXED
- Claw Toe
- FLEXED
- Mallet Toe
- Neutral
- Hammer Toe
- Neutral
- Claw Toe
- FLEXED
- Mallet Toe
- FLEXED
- Hammer Toe
- 80% of lesser toe
- Claw Toe
- 15% of lesser toe
- Mallet Toe
- 5% of lesser toe
- Hammer Toe
- Shoe wear, hallux valgus
- Claw Toe
- Neurological (CMT, DM)
- Mallet Toe
- Trauma, long 2nd toe
- Hammer Toe
- FDL/FDB overpull
- Claw Toe
- Intrinsic weakness
- Mallet Toe
- FDP/terminal tendon
Pathophysiology and Anatomy
The balance of the toe. The PIPJ is the site of the primary deformity, and its posture is set by the tendons that cross it. The intrinsics flex the MTPJ and extend the interphalangeal joints. When the flexors overpull relative to the extensors, or intrinsic function is lost, the PIPJ flexes.
- Flexors - flexor digitorum longus (FDL) and flexor digitorum brevis (FDB)
- Extensors - extensor digitorum longus (EDL) and extensor digitorum brevis (EDB)
- Intrinsics - interossei and lumbricals
The plantar plate. Plantar plate failure drives an instability-based hammer toe. On drawer testing the toe translates dorsally at the MTPJ, which corresponds to MTP subluxation and a degenerative PIP contracture.
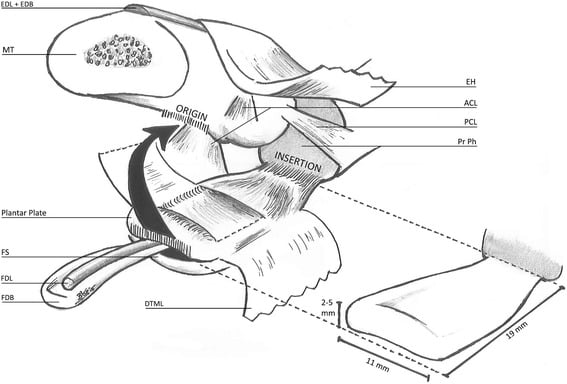
Causes. Footwear is the most common cause:
- Footwear - high heels and a narrow toe box; a tight toe box makes the toe adapt in flexion
- Hallux valgus - commonly associated: the drifting hallux crowds the second toe and forces it to flex, though no source cited here quantifies the proportion
- Long second metatarsal - increased pressure
- Inflammatory arthritis - rheumatoid and psoriatic; joint destruction and subluxation
- Neurological - diabetic neuropathy, CMT, CVA; these usually produce a claw toe
- Trauma - compartment syndrome, crush injury
Classification
Two systems grade the lesser toe deformity, both moving from a flexible toe to one with a subluxed or dislocated MTPJ.
- Coughlin classification
- Flexible deformity, reducible
- Dhukaram classification
- Flexible, correctable
- Coughlin classification
- Semi-rigid, partially reducible
- Dhukaram classification
- Rigid PIPJ, flexible MTPJ
- Coughlin classification
- Rigid, fixed deformity
- Dhukaram classification
- Rigid PIPJ and MTPJ
- Coughlin classification
- Rigid with MTPJ subluxation/dislocation
- Dhukaram classification
- With MTPJ dislocation
Clinical Assessment
History. Pain sits over the dorsal PIPJ where the shoe rubs, at the tip of the toe, or under the metatarsal head, with a callus or corn at the dorsal PIPJ, the tip of the toe or between the toes. Patients also mind the crooked appearance, struggle to find comfortable shoes, and may have bunion symptoms. The deformity is flexible at first and becomes rigid over time.
Standing. Observe the toe weight-bearing, check for hallux valgus, and assess the arch and hindfoot alignment.
The flexibility test. The most critical examination finding, because it decides the operation. With the patient seated, plantarflex the ankle to relax FDL and try to correct the PIPJ. If it corrects, the deformity is flexible and soft-tissue surgery is indicated; if it stays fixed, it is rigid and needs bone surgery.
The drawer test. Grasp the toe and try to translate the proximal phalanx dorsally at the MTPJ. A positive test means MTPJ instability from plantar plate injury, and a subluxed MTPJ needs a Weil osteotomy. Assess MTPJ range of movement at the same time.
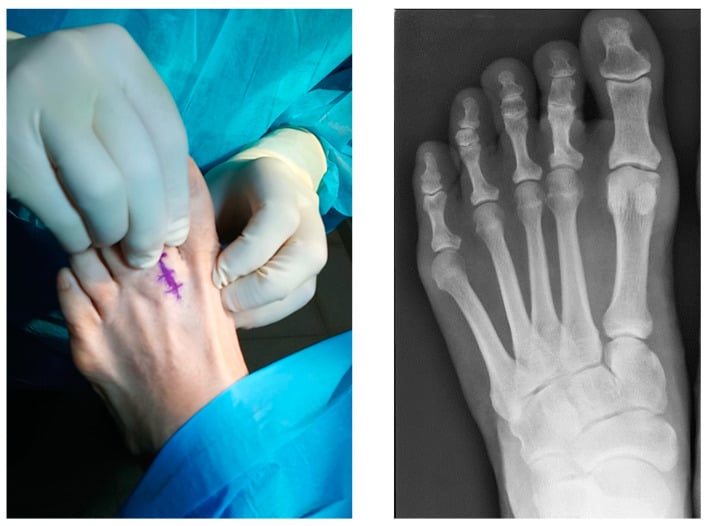
The push-up (Kelikian) test. The flexibility test tells you whether the interphalangeal contracture is fixed. The push-up test answers a complementary question: is the deformity driven from the MTPJ, and will it reduce when the forefoot is loaded? With the patient seated, push upward (dorsally) on the plantar aspect of the metatarsal head, simulating weight-bearing and toe-off, and watch the toe.
- Corrects on push-up - a flexible, dynamic deformity. The toe straightens as the MTPJ is reduced, so the interphalangeal posture is secondary to MTPJ position, and soft-tissue balancing (with metatarsal-level correction where the MTPJ is unstable) can realign it
- Fails to correct - a fixed interphalangeal contracture, which needs bony PIPJ correction by resection arthroplasty or arthrodesis
Taken with the flexibility test and the drawer test, the push-up test localises the deformity (isolated PIPJ or MTPJ-driven) and grades its rigidity. That is exactly what selects soft-tissue or bony surgery and decides whether a Weil osteotomy is needed. Formal plantar plate grading and repair are covered under plantar plate insufficiency.
The skin. Where the callus sits shows where the pressure comes from:
- Dorsal PIPJ - shoe pressure
- Tip of the toe - ground contact
- Interdigital - the adjacent toe
Neurovascular. Check capillary refill and sensation; diabetic neuropathy is common.
Differential diagnosis. A painful lesser toe has other causes, and each has its own deformity or sign.
- Key Deformity / Sign
- PIPJ flexion, neutral MTPJ/DIPJ
- Distinguishing Feature
- Flexibility test guides treatment; dorsal PIPJ corn
- Key Deformity / Sign
- MTPJ extension + PIPJ/DIPJ flexion
- Distinguishing Feature
- Usually multiple toes; look for neurological cause (CMT, diabetes)
- Key Deformity / Sign
- Isolated DIPJ flexion
- Distinguishing Feature
- Tip-of-toe corn; terminal tendon pathology
- Key Deformity / Sign
- Medial/dorsal drift over hallux
- Distinguishing Feature
- Plantar plate tear, positive drawer; precedes fixed deformity
- Key Deformity / Sign
- Dorsal MTPJ subluxation
- Distinguishing Feature
- Positive drawer/squeeze; pain at plantar MTPJ rather than PIPJ
- Key Deformity / Sign
- MTPJ pain, flattened metatarsal head
- Distinguishing Feature
- AVN of metatarsal head on X-ray; joint-line tenderness, not PIPJ
- Key Deformity / Sign
- Interdigital pain, Mulder click
- Distinguishing Feature
- No fixed osseous deformity; numbness in adjacent toes
Investigations
Weight-bearing radiographs. Three views, each answering its own question:
- AP - MTPJ alignment, subluxation, joint space
- Oblique - PIPJ deformity, osteophytes
- Lateral - degree of flexion, PIPJ arthritis
Weight-bearing X-rays are essential - non-weight-bearing images miss MTPJ subluxation and underestimate deformity severity.
What to look for. MTPJ subluxation, with the proximal phalanx displaced dorsally; destruction or arthritis of the PIPJ; the hallux valgus angle; metatarsal length; and bone quality where inflammatory arthritis is present.
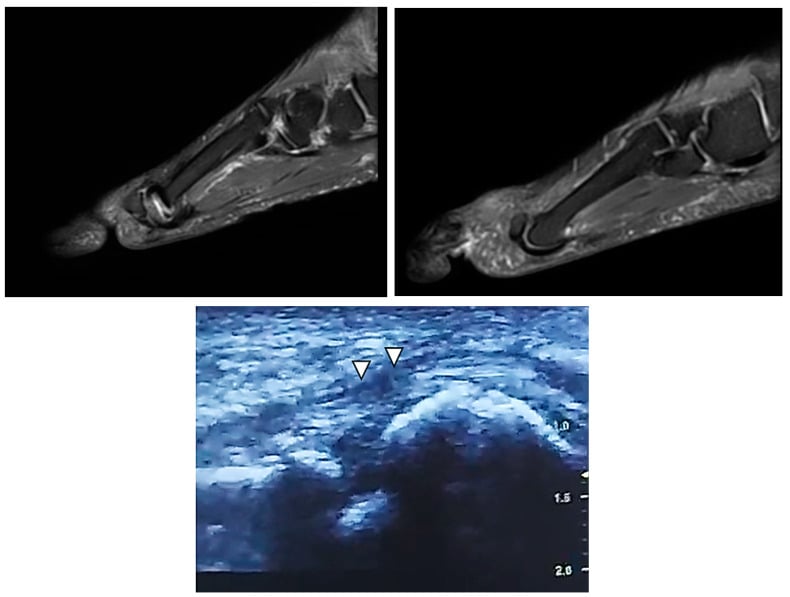
Special investigations. Each has a specific trigger:
- HbA1c - if diabetic neuropathy is suspected
- ESR and CRP - if inflammatory arthritis is suspected
- Nerve conduction studies - if a neurological cause such as CMT is suspected
Management
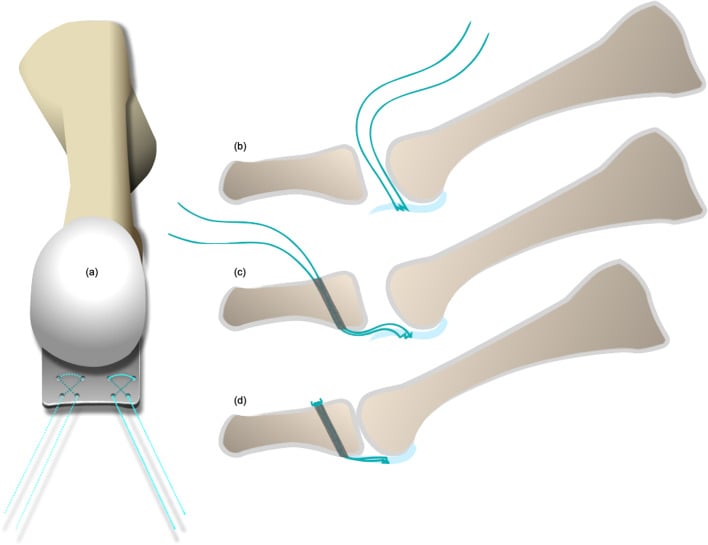
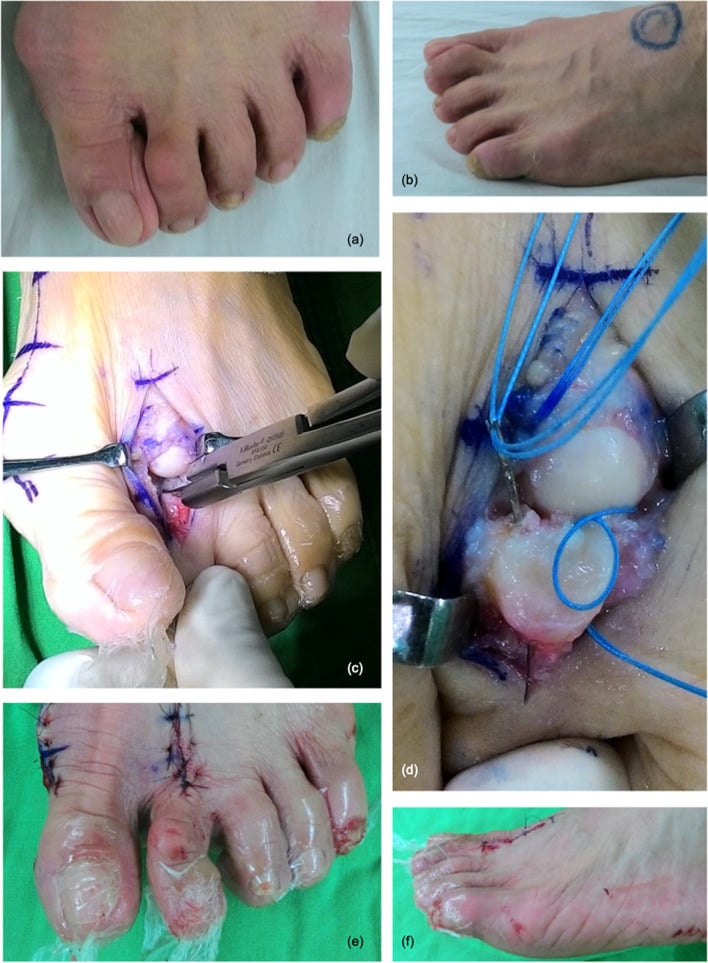
The decision. Flexibility and the MTPJ decide the operation. A flexible deformity is treated with soft tissue (FDL tenotomy or Girdlestone-Taylor transfer), a rigid one with bone (PIPJ resection arthroplasty or arthrodesis). A subluxed MTPJ must be addressed at the same time to prevent recurrence.
Who. Conservative measures are first-line for all hammer toes. The indications are mild symptoms, a flexible deformity, a poor surgical candidate and patient preference.
What to expect. Symptoms are relieved in 50-70%, and 30-50% fail conservative management. Conservative care does not correct the deformity, which typically progresses; on average, 2-3 years pass before surgery.
The options.
- Footwear modification - a wide toe box (the most important measure), low heels under 2.5 cm, a soft upper, and depth shoes if the deformity is severe
- Orthotic devices - toe props or crests, silicone hammer toe sleeves, toe separators, metatarsal pads
- Padding - corn pads over the dorsal PIPJ, gel toe caps, felt pads
- Strapping - buddy strapping or plantar-directed strapping, a temporary correction only
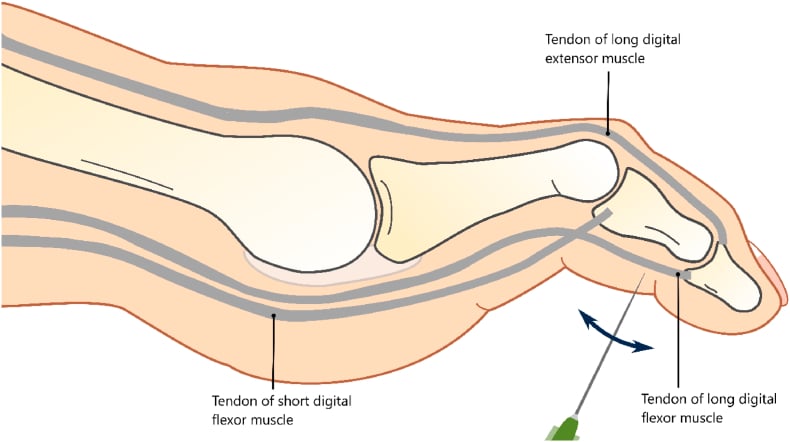
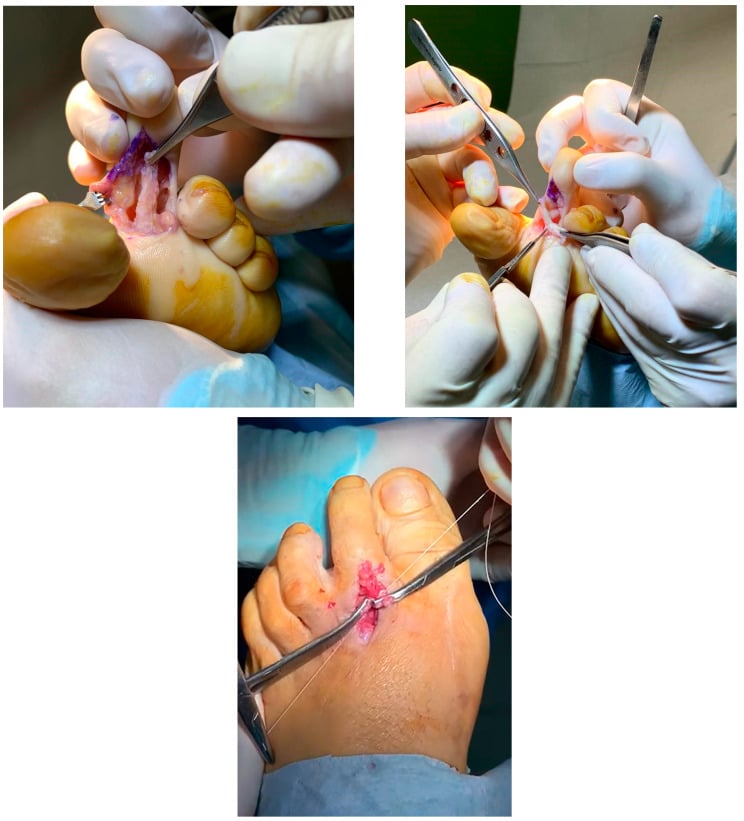
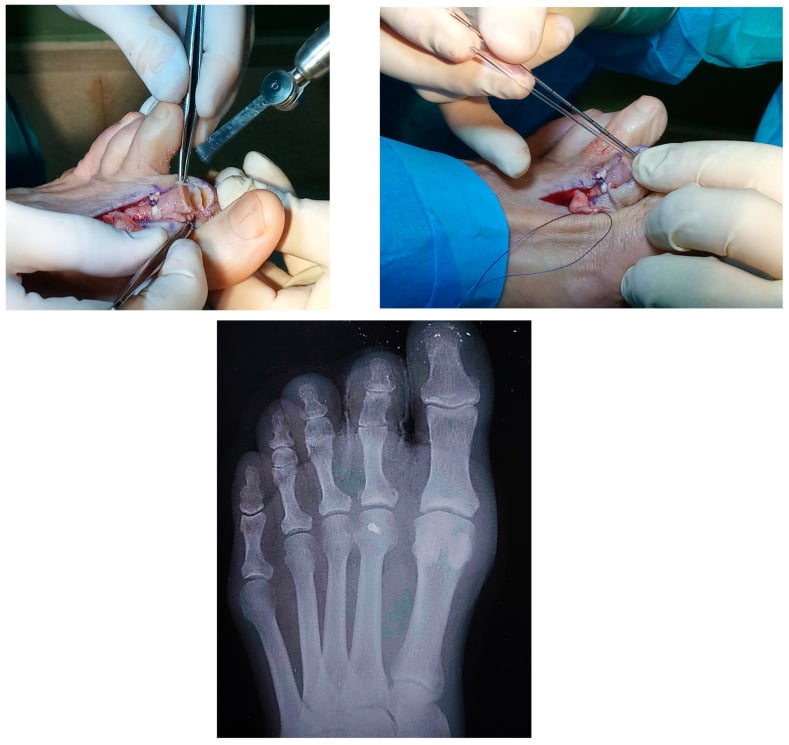
Complications
Early and late. Early problems are wound and K-wire infection, pin tract irritation, swelling and bruising. The late ones are in the table below; vascular compromise is rare, and the digits should be checked post-op.
The rates. Reported rates vary, and where figures differ the range below spans them.
- Incidence
- 2-15%
- Risk Factors
- Over-resection, tendon imbalance, MTPJ instability, excessive plantar plate release
- Prevention/Management
- Limit resection, arthrodesis, address MTPJ
- Incidence
- 5-15%
- Risk Factors
- Inadequate correction, not addressing MTPJ
- Prevention/Management
- Complete correction, treat all pathology, proper patient selection
- Incidence
- 3-8%
- Risk Factors
- Pin track contamination, diabetes
- Prevention/Management
- Pin care, early removal if infected
- Incidence
- 2-5% (1-3% quoted for infection overall)
- Risk Factors
- —
- Prevention/Management
- Standard wound care; K-wire pin site care
- Incidence
- 5-20%
- Risk Factors
- Arthrodesis, excessive scarring, prolonged immobilisation
- Prevention/Management
- Early mobilisation and ROM after fixation, physiotherapy; consider arthroplasty in elderly
- Incidence
- 3-8%
- Risk Factors
- Iatrogenic from FDL tenotomy
- Prevention/Management
- Check DIPJ mobility preoperatively
- Incidence
- 5% with arthrodesis
- Risk Factors
- —
- Prevention/Management
- See the note below on union rates
- Incidence
- 2-5%
- Risk Factors
- Technical error, inadequate fixation
- Prevention/Management
- Careful intraoperative assessment
- Incidence
- 5-10%
- Risk Factors
- Shortening adjacent ray, overcorrection; overloading adjacent rays
- Prevention/Management
- Address all metatarsals and 1st ray pathology, balanced correction; consider Weil osteotomy
Floating toe is the most common post-operative complaint and the most common complication to counsel about. The toe has no ground purchase and feels floppy, and salvage is difficult.
Prevention. Keep bone resection conservative and avoid over-resection at the PIPJ, prefer arthrodesis over arthroplasty for a more stable correction of rigid deformity, and perform a Weil osteotomy if the MTPJ is subluxed. Keep pin sites clean and the K-wire in for an adequate duration (3-4 weeks), and avoid surgery in poorly controlled diabetics.
Non-union and the union figures. The 5% non-union figure sits uneasily beside the fixation review in the Evidence Base, where PIPJ arthrodesis united in 72-87% depending on the fixation. That review's arms were unequal and its implant and wire series defined and imaged union differently, so its rates are not directly comparable; quote the range with that caveat rather than a single non-union figure.
Over-release. Unbalanced or overly extensive flexor release has its own consequences: clawing, loss of toe purchase and apical callus from transfer pressure.
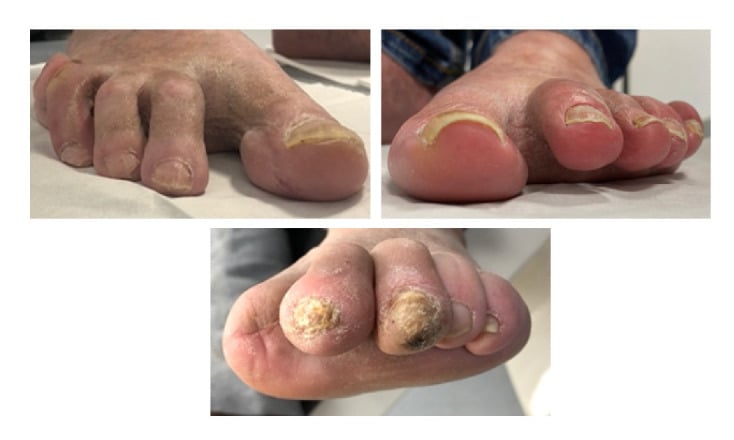
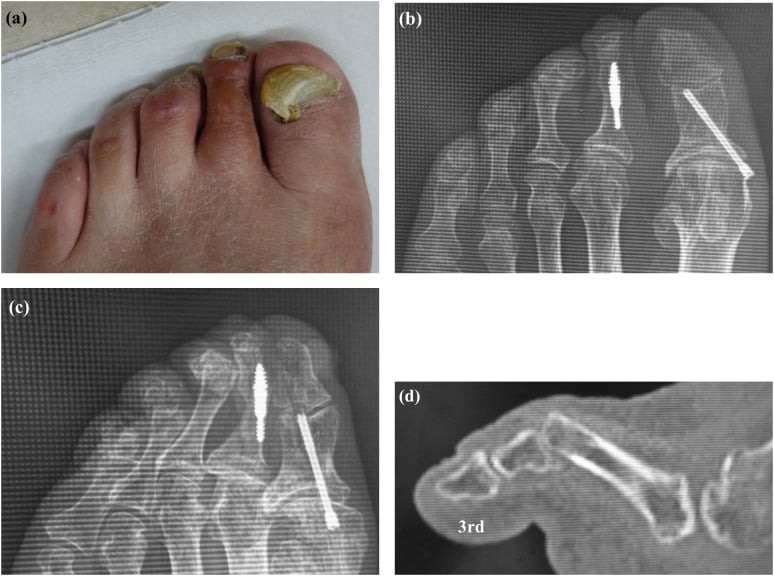
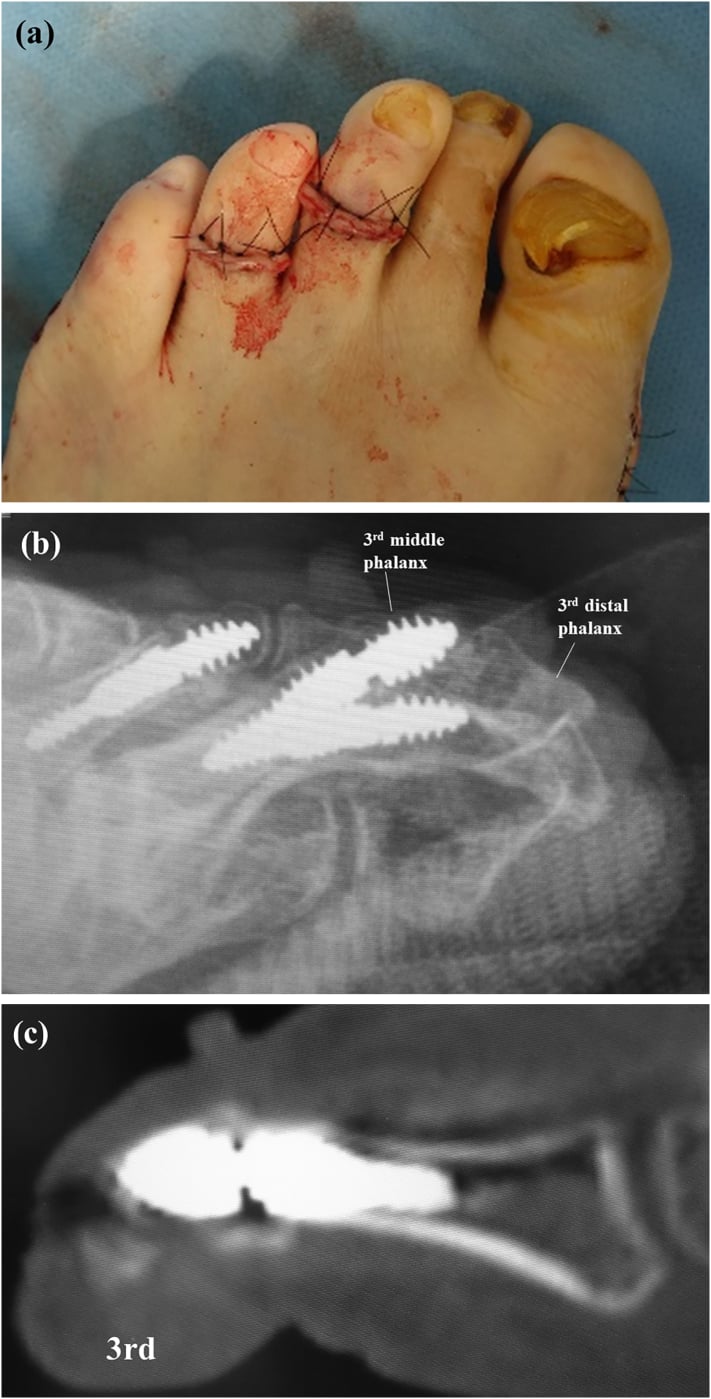
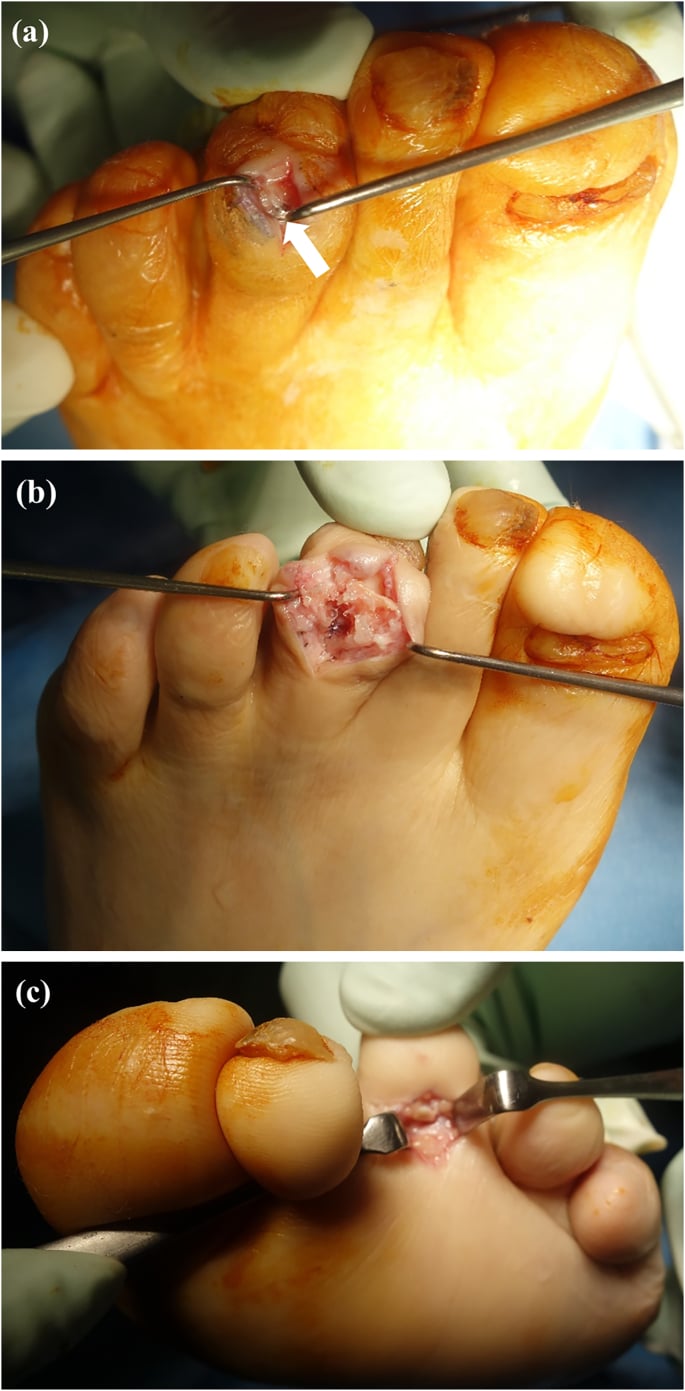
Hardware failure. Implants can fail too. In the case below, a prominent distal implant produced ulceration and a secondary mallet deformity; it was exposed through the middle phalanx cortex, removed, and followed by a plantar flexor tenotomy.
Postoperative Care
Day 0-1. A bulky dressing holds the toe aligned. A K-wire, if used, exits dorsally and is kept dry and protected. Elevation above heart level is essential to minimise swelling, and the patient heel weight-bears in a stiff-soled postoperative shoe.
Weeks 1-2. Check the wound at 10-14 days and remove non-absorbable sutures at 2 weeks. Walking is limited to essential activities, and significant toe swelling is expected for 6-8 weeks.
Weeks 2-4. The K-wire, if used, is removed in clinic. Gentle active toe movements begin once it is out, and the corrected toe is buddy-taped to its neighbour for 4-6 weeks after wire removal. The stiff-soled shoe continues, then gives way to an accommodative shoe with a stiff sole.
Weeks 4-6. Progressive weight-bearing into a supportive athletic shoe; physiotherapy focused on PIPJ mobility if the toe is stiff; scar massage once the wound has completely healed.
Weeks 6-12. A gradual return to regular shoes, with a wide toe box at first. Alignment and range of movement are assessed at 12 weeks.
Postoperative Swelling Timeline: Inform patients that toe swelling following hammer toe correction typically peaks at 2-3 weeks and may persist for 3-6 months. Prolonged swelling does not indicate failure if alignment is maintained.
Return to activity. The usual milestones:
- Walking - 2-4 weeks
- Driving - 4-6 weeks
- Low-impact exercise and dress shoes - 6-8 weeks
- Sports - 8-12 weeks
- Final result - 6-12 months
Outcomes and Prognosis
Surgery overall. Satisfaction is 80-90%, pain relief 85-95% and deformity correction 75-90%, with complications in 10-20%.
By procedure. Quote outcomes by procedure rather than as one figure where you can. PIPJ arthrodesis unites in 72-87% across nearly 3,900 pooled cases depending on the fixation used, and flexor-to-extensor transfer for flexible deformity recurs in about 16% at eight months.
What predicts the result. A flexible deformity, an isolated PIPJ and no MTPJ involvement favour a good result. A rigid deformity, MTPJ subluxation, inflammatory arthritis and diabetes count against it.
Guidelines, Registries & Global Practice
Global Epidemiology
Lesser-toe deformities are among the most common forefoot complaints worldwide. Population studies report hammer/claw/mallet toes in a substantial minority of adults, rising steeply with age and strongly female-predominant (footwear and a longer second ray are the dominant drivers). Prevalence is higher in older, shod populations and lower in habitually barefoot communities, supporting footwear as a key modifiable factor. Hallux valgus coexists in the majority of symptomatic second-toe deformities.
Side-by-Side Guidance
- Position on lesser-toe surgery
- Flexible vs rigid distinction drives treatment; soft-tissue balancing for flexible, bony correction (arthroplasty/arthrodesis) for rigid; address MTPJ instability concurrently
- Position on lesser-toe surgery
- Exhaust footwear and orthotic measures first; reserve surgery for failed conservative care; counsel explicitly on floating toe and recurrence
- Position on lesser-toe surgery
- Endorses plantar plate staging (Coughlin-Nery) and combined Weil osteotomy plus plantar-plate repair for instability-driven deformity
- Position on lesser-toe surgery
- In neuropathic feet, prioritise deformity offloading and ulcer prevention; weigh surgical correction against wound-healing and vascular risk
There is no single international registry for lesser-toe surgery; comparative evidence comes from case series, the Jay/Malay fixation RCT, and large pooled fixation reviews rather than from arthroplasty-style joint registries.
High- vs Limited-Resource Practice Variation
- High-resource settings: Day-case surgery; growing use of intramedullary fusion implants despite cost and hardware-failure data favouring K-wires; frequent combined bunion + lesser-toe correction.
- Limited-resource settings: Percutaneous K-wire fixation and FDL tenotomy/transfer predominate (low cost, reliable); emphasis on footwear modification and offloading where surgical access is limited.
- Diabetic / neuropathic populations: Worldwide, the threshold for elective bony surgery is raised because of impaired healing; offloading, accommodative footwear and ulcer prevention take priority.
Pathomechanics: The Three Deformity Patterns
Hammer, claw and mallet toes are the visible endpoint of a dynamic imbalance between the extrinsic (long) tendons and the intrinsic muscles of the foot. Three classic patterns, long described in the podiatric and orthopaedic literature, explain how that imbalance arises and predict the foot type that accompanies it.
Flexor stabilisation. The commonest mechanism behind the acquired hammer toe. In a pronated or flat foot, FDL and FDB fire earlier and for longer during stance to try to stabilise an unstable forefoot, and overpower the intrinsics. The unopposed flexors buckle the PIPJ, often with an adductovarus lesser toe; this is the pattern to expect in the flexible, footwear-driven patient with hallux valgus.
Extensor substitution. During swing phase EDL is over-recruited to help a weak tibialis anterior dorsiflex the ankle. It overpowers the lumbricals and hyperextends the MTPJ, and the toe then buckles at the interphalangeal joints. It goes with a high-arched (cavus) foot and produces a claw-type posture with prominent MTPJ dorsiflexion.
Flexor substitution. The least common. When the triceps surae is weak, the deep flexors, tibialis posterior and peroneus longus substitute for push-off; the flexors again overpower the intrinsics and claw the toes. It is seen in the supinated or cavus foot.
Why the pattern matters. It points to the underlying driver. A flexible flexor-stabilisation hammer toe responds well to flexor balancing (FDL tenotomy or Girdlestone-Taylor transfer). An extensor- or flexor-substitution pattern warns that an unaddressed hindfoot or cavus deformity, and often a neurological cause, will drive recurrence if the toe is treated in isolation, so look for that cause (see claw toe and cavus foot) before operating on the toe alone.
Controversies & Areas of Uncertainty
Arthroplasty or arthrodesis for rigid deformity. Arthrodesis offers a more stable, lower-recurrence construct at the cost of a stiff toe and a non-union risk; resection arthroplasty preserves some motion but is more prone to recurrence and floating toe. No high-quality RCT directly settles the choice, so selection remains driven by patient age, activity and surgeon preference.
Intramedullary implants or K-wire. The single RCT favours implants for fusion rate and patient-reported scores, although only its complication comparison, which found no difference, is reported as statistically tested. Pooled reviews show higher hardware-failure rates and a 640-894x cost premium with no clear complication benefit. Whether the avoided pin-tract morbidity justifies the cost is unresolved.
When to address the MTPJ and plantar plate. There is debate over whether all crossover and instability-driven deformities need formal plantar plate repair, or whether a Weil osteotomy with soft-tissue balancing alone suffices. The Coughlin-Nery staging is increasingly used to guide this, but thresholds vary.
Floating toe is partly unavoidable. Even with meticulous technique, floating toe occurs in a meaningful proportion after Weil osteotomy and plantar plate work; its true preventability and the best salvage remain uncertain.
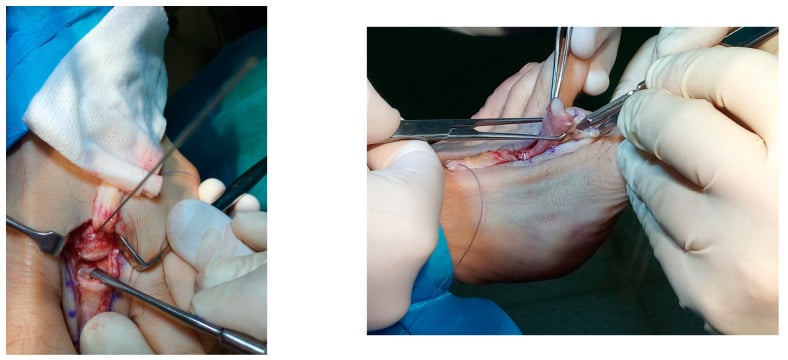
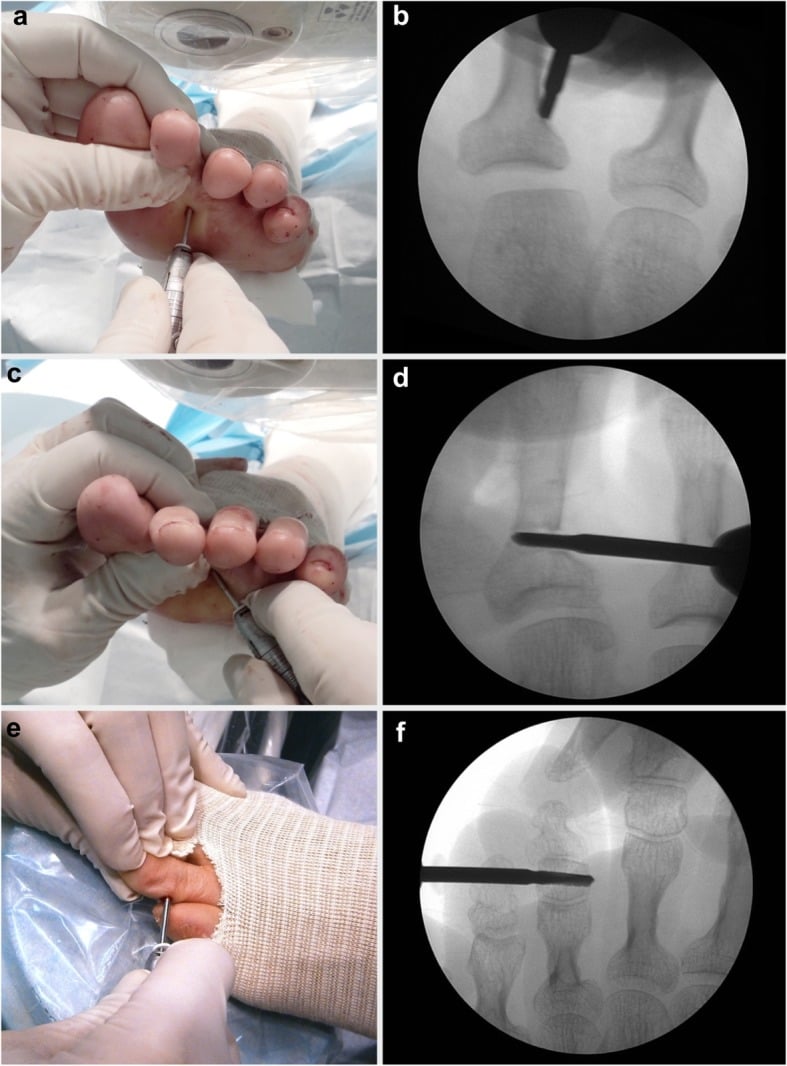
Percutaneous techniques. Percutaneous flexor tenotomy and minimally invasive osteotomies, such as incomplete proximal and middle phalanx osteotomies made through plantar mini-incisions under fluoroscopy, are expanding. Long-term comparative data against open correction are still limited.
MCQ Practice Points
Q: What distinguishes a hammer toe from a claw toe?
A: Hammer toe = PIPJ flexion with neutral MTPJ and DIPJ Claw toe = MTPJ hyperextension + PIPJ/DIPJ flexion
Hammer toe is most commonly 2nd toe, associated with hallux valgus. Claw toe typically affects multiple toes and has neurological associations (Charcot-Marie-Tooth, diabetic neuropathy).
Q: A 55-year-old woman has a painful 2nd hammer toe. The PIPJ deformity corrects passively. What is the first-line surgical treatment?
A: Flexor-to-extensor transfer (Girdlestone-Taylor procedure) - indicated for flexible deformities. Preserves joint motion.
If the PIPJ is fixed/rigid → PIPJ arthrodesis is indicated.
Q: What does the push-up test assess in hammer toe evaluation?
A: Tests MTPJ stability. With examiner pressure under the metatarsal head, a positive test shows correction of PIPJ deformity → indicates the problem is plantar plate/MTPJ driven, not isolated PIPJ contracture. May need Weil osteotomy in addition to toe surgery.
Q: Following hammer toe correction, a patient develops progressive DIPJ hyperextension ("floppy toe"). What is the cause?
A: FDL transection or excessive release during surgery. The FDL is the only active DIPJ flexor. If cut or transferred, unopposed EDL causes DIPJ hyperextension. Prevention: careful identification of FDL vs FDB.
Self-Assessment Quiz
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 55-year-old woman presents with a painful 2nd toe deformity. She has a callus over the dorsal aspect of the PIPJ. On examination, the deformity corrects manually when you plantarflex her ankle.”
“A 62-year-old man has a painful, rigid 2nd toe deformity. The PIPJ does not correct even with the ankle plantarflexed. You also notice the toe is dorsally displaced at the MTPJ level with a positive Drawer test.”
“A patient returns 3 months after hammer toe surgery complaining their 2nd toe feels floppy and doesn't touch the ground when standing. They are unhappy with the result.”
DEFINITION & TYPES
- Hammer = PIPJ flexion, neutral MTPJ/DIPJ (80% of lesser toe)
- Claw = MTPJ extension + PIPJ/DIPJ flexion (neurological)
- Mallet = DIPJ flexion only (5%, terminal tendon)
- 2nd toe most common (80%) - length, hallux valgus
FLEXIBILITY TEST
- Plantarflex ankle (relaxes FDL)
- Attempt to correct PIPJ
- Corrects = FLEXIBLE → soft tissue surgery
- Fixed = RIGID → bone surgery
MTPJ ASSESSMENT
- Drawer test - anterior subluxation
- Positive = plantar plate rupture/MTPJ instability
- Must address if subluxed (Weil osteotomy)
- Missing MTPJ = recurrence
FLEXIBLE SURGERY
- FDL tenotomy (percutaneous stab incision)
- Girdlestone-Taylor (FDL split and transfer dorsally)
- May need MTPJ capsulotomy
- No bone resection needed
RIGID SURGERY
- PIPJ resection arthroplasty (resect P1 head)
- PIPJ arthrodesis (more stable, lower recurrence)
- K-wire 3-4 weeks or intramedullary device
- Weil osteotomy if MTPJ subluxed
COMPLICATIONS
- Floating toe - MOST COMMON (floppy, no purchase)
- Recurrence (5-10%)
- K-wire infection (3-8%)
- Stiffness, mallet toe, transfer lesions
OUTCOMES
- 80-90% satisfaction
- Arthrodesis lower recurrence than arthroplasty
- Conservative doesn't correct deformity
- Full recovery 6-12 months
Evidence Base
Jay, Malay, Landsman et al - IM Implant vs K-wire RCT
- Multicentre RCT, 91 patients randomised to K-wire (n=46) vs 2-piece intramedullary implant (n=45) for PIPJ fusion
- No statistically significant difference in complication rates between groups
- Intramedullary implant group had higher mean Bristol Foot Score, Foot Function Index and a higher fusion rate
- Mean age 58.7 years, confirming the typical older demographic
Nery, Coughlin, Baumfeld, Mann - Plantar Plate Staging & Repair
- Prospective series of 22 patients (40 lesser MTP joints) with instability treated by direct dorsal plantar plate repair plus Weil osteotomy
- Second MTP joint most commonly affected (63%); Grade III tears most frequent
- Defined the anatomical grading correlated with clinical staging for plantar plate dysfunction
- AOFAS score improved from a mean of 52 to 92 points postoperatively
Coughlin - Rheumatoid Forefoot Reconstruction (Long-term)
- Retrospective series of 32 patients (47 feet) at mean 6-year follow-up
- Fixed hammer toes corrected by PIPJ arthrodesis with intramedullary Kirschner-wire fixation
- Dislocated lesser MTP joints reduced from 70% preoperatively to 7% postoperatively
- 23 feet excellent, 22 good, 2 fair; no poor results - a stable first ray protected lateral rays
Arbab et al - FDL Transfer for Flexible Deformity
- 24 toes with flexible PIPJ and/or MTPJ deformity treated by Girdlestone-Taylor FDL flexor-to-extensor transfer
- 92% (22 toes) aligned at SIX WEEKS - but 16% (4 toes) had recurrent or persistent MTPJ extension at final follow-up
- No infections, overcorrection or transverse malalignment
Hendrick & Kannegieter - Fixation Methods Review
- Review of 3878 PIPJ arthrodesis outcomes (3255 percutaneous K-wires, 347 SmartToe, 218 ToeGrip, 58 buried K-wire)
- Infection rates low across all methods (K-wire 0.3-7%, SmartToe 1.2-5%)
- SmartToe implant had the highest hardware failure rate (up to 20.7%); K-wire the lowest (0.1-4.3%)
- Implants cost 640-894x more than a K-wire with no clear superiority in union
Sorensen & Weil - Lesser Metatarsal Osteotomy
- Reviews indications and technique of central (Weil) metatarsal osteotomy for forefoot pain and MTPJ instability
- The review warns of a complication ‘potpourri’ without enumerating it; the floating toe and joint stiffness named here are the well-recognised Weil-osteotomy complications rather than figures from this paper
- Treating only the pain focus underserves the deformity - the high point must be addressed
- Emphasises managing patient expectations and proactive complication avoidance