Posterosuperior Labrum Contact in ABER | GIRD Essential Sign | Posterior Capsule Stretching First-Line
- Internal impingement is contact between posterosuperior rotator cuff and posterosuperior labrum in ABER position
- GIRD (side-to-side IR difference greater than 20-25 degrees) is the hallmark finding of posterior capsular contracture and the main rehabilitation target - but be precise about what it does and does not do. In the largest prospective cohort (296 professional pitchers) GIRD did NOT predict shoulder injury or surgery; insufficient external-rotation gain did (2.2x injury, 4.0x surgery). Measure BOTH rotations and the total arc, and never screen a thrower on internal rotation alone
- SICK scapula (Scapular malposition, Inferior medial border prominence, Coracoid pain, dysKinesis) commonly coexists
- Conservative treatment first - posterior capsule stretching and scapular stabilization for 3-6 months
- Arthroscopic debridement only after failed conservative care - debride labrum/cuff, consider posterior capsular release
- “Internal impingement is a normal contact phenomenon exaggerated in throwers
- “GIRD is caused by posterior capsule contracture from repetitive throwing
- “Distinguish from external impingement (subacromial) - different pathology
- “Return to throwing requires extensive rehab - 6-12 months typical
Overview and Epidemiology
Internal impingement is contact between the posterosuperior rotator cuff (supraspinatus and infraspinatus) and the posterosuperior glenoid labrum with the shoulder in ABER, abduction and external rotation. The contact happens in all shoulders in that position. It is a normal phenomenon, and it becomes pathological only when it is exaggerated, which is what a tight posterior capsule does to it.
How a normal contact becomes a lesion. Repetitive overhead throwing creates adaptive changes, among them contracture of the posterior capsule from repetitive microtrauma. The contracture costs the shoulder internal rotation, and the humeral head has to translate to reach full external rotation, so the cuff and labrum meet with excessive force. The pathological changes, labral fraying and partial-thickness articular-sided cuff tears, follow from that force.
Who. Overhead athletes, and the case-mix follows the sport:
- Baseball pitchers (most common)
- Volleyball players (servers, spikers)
- Tennis players (servers)
- Swimmers (freestyle, butterfly)
- Javelin throwers
- Handball players
Age and sex. Adolescents to young adults, typically 15-35 years. Professional and elite amateur athletes are the most affected, though a recreational athlete with a high enough volume can develop it. Males are affected more often than females, reflecting sport participation.
Pathophysiology and Mechanisms
The throw. The overhead throw runs through distinct phases, and the pathology belongs to one of them:
- Wind-up: preparation
- Early cocking: the arm moves into abduction and external rotation
- Late cocking: maximum external rotation (layback), the ABER position
- Acceleration: internal rotation and forward propulsion
- Deceleration: eccentric posterior cuff activity slows the arm
- Follow-through: completion of the motion
Late cocking is the moment. The shoulder sits at 90 degrees of abduction and maximum external rotation, up to 180 degrees in elite throwers. The posterosuperior cuff is maximally tightened, and the greater tuberosity and the undersurface of the posterosuperior cuff are swung against the posterosuperior rim of the glenoid labrum. That degree of contact is physiological in everyone; it becomes pathological with the repetition of throwing.
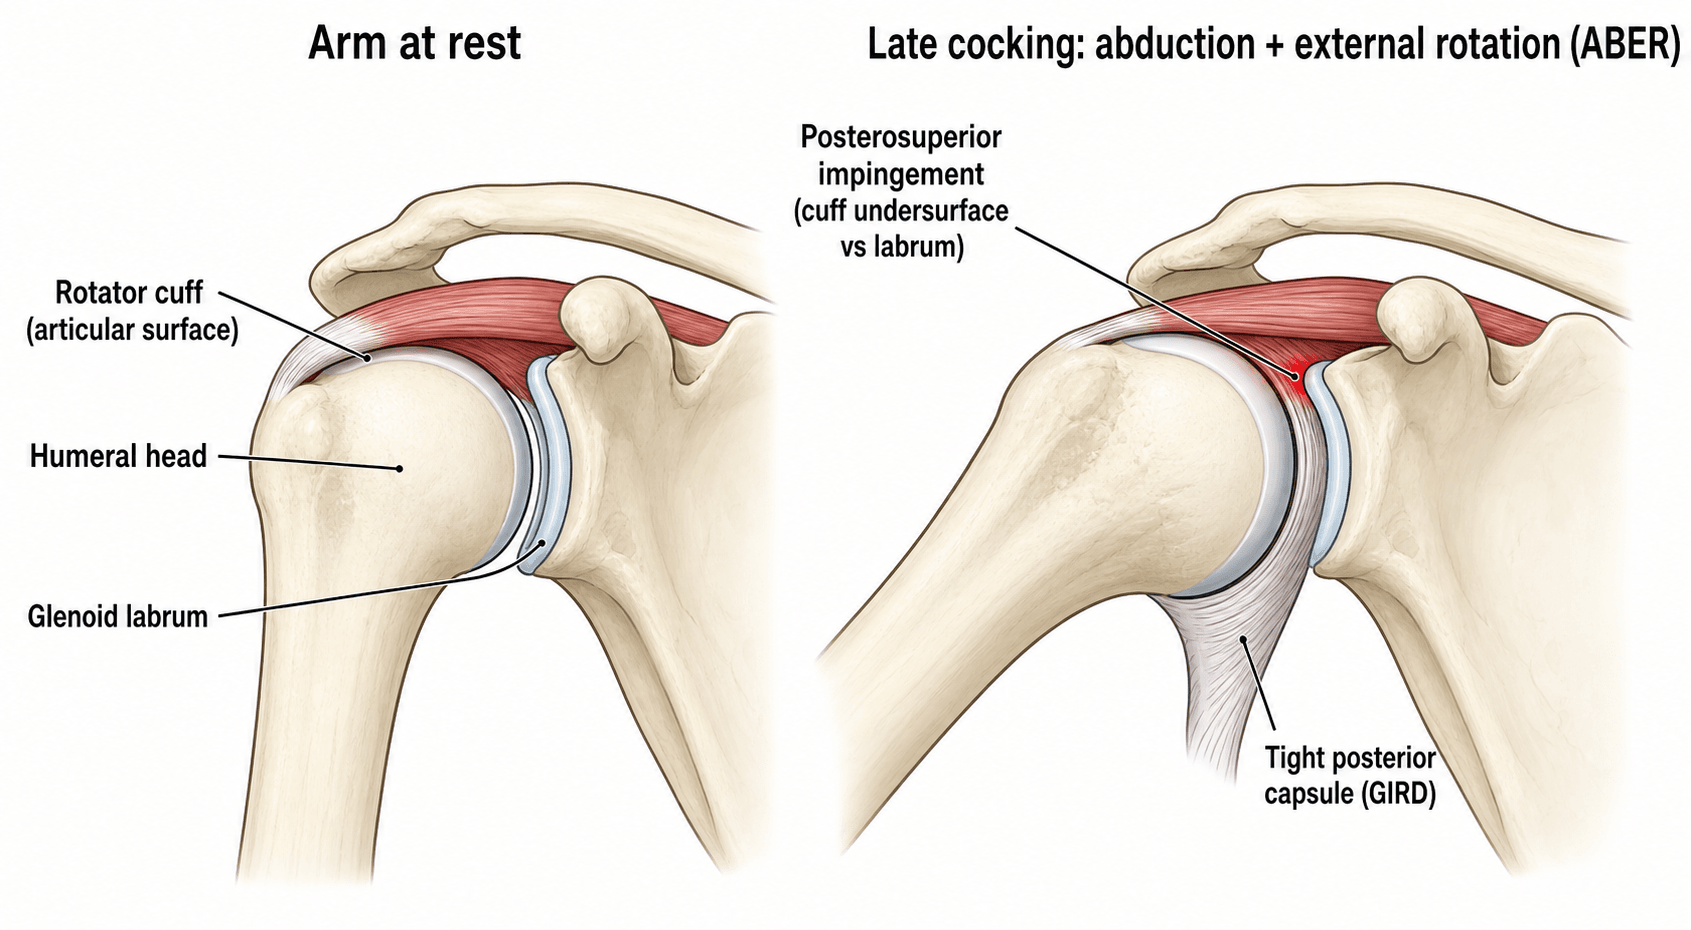
GIRD. Glenohumeral internal rotation deficit is the loss of glenohumeral internal rotation in the throwing shoulder compared with the non-throwing shoulder, measured at 90 degrees of abduction. It is the clinical signature of the tight posterior capsule, which shifts the humeral head's contact point further posterosuperiorly and amplifies the pinch; how it is measured, and the numbers that make it pathological, are in the assessment section.
Where the tightness comes from. Repetitive eccentric loading during the deceleration phase contracts the posterior capsule, and the posterior rotator cuff, infraspinatus and teres minor, tightens with it. Humeral retroversion, the bony adaptation of the young thrower, is not the same thing as GIRD, and an acquired capsular contracture must be distinguished from bony retroversion.
GIRD creates a kinematic chain dysfunction: Posterior capsule tightness → Loss of internal rotation → Obligate anterosuperior humeral translation to achieve external rotation → Increased contact force at posterosuperior labrum → Labral fraying and articular-sided cuff tears → Pain and dysfunction.
Total rotational motion. Healthy throwers often gain external rotation and lose internal rotation, with the total arc of rotation (ER plus IR) preserved: the arc has shifted, not shrunk. GIRD is pathological when the total arc is decreased rather than shifted, when the loss of internal rotation exceeds the gain in external rotation, and when the side-to-side difference in total arc is greater than 5-10 degrees.
SICK scapula. Scapular dyskinesis commonly coexists with internal impingement. Repetitive throwing overloads pectoralis minor, which protracts and anteriorly tilts the scapula; scapular stability is lost, and the impingement is perpetuated. The acronym names its components.
SICKSICK - Scapular Dysfunction Pattern
Hook:SICK scapula perpetuates internal impingement - must address both issues
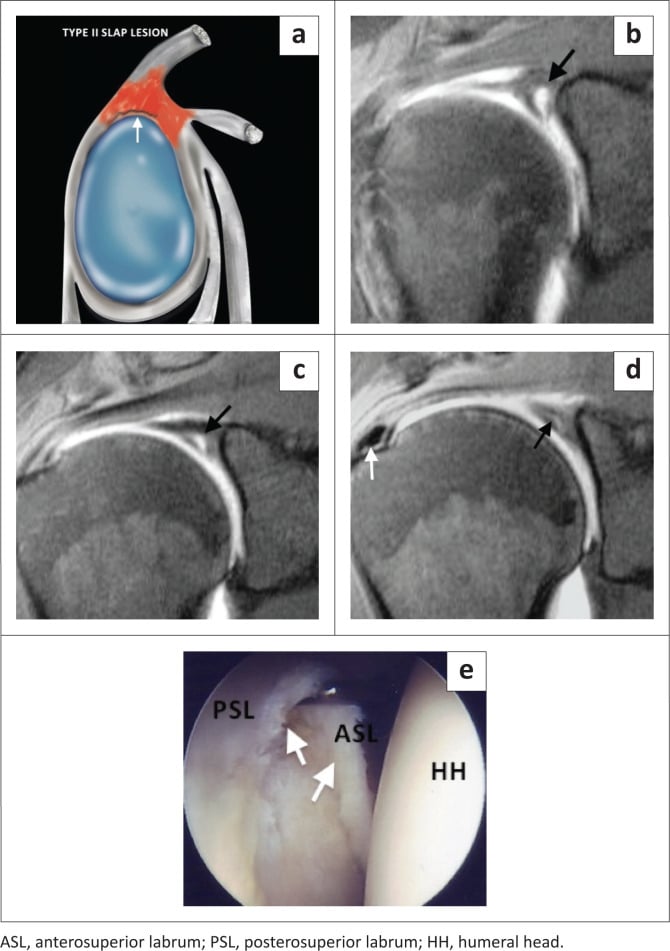
What the tissues do. Early, the posterior capsule thickens and contracts, the posterosuperior labrum frays and degenerates, the articular side of the cuff develops a partial-thickness tear of less than 50%, and the infraspinatus shows tendinopathy and signal change. Advanced disease brings severe capsular tightness with adhesions, labral detachment with SLAP-like tears, and progression of the cuff tear to high-grade partial or full thickness.
Internal impingement is usually the posterosuperior type described above, but a distinct anterosuperior internal impingement (Gerber) also exists and is worth recognising. Here the undersurface of the subscapularis and the biceps-pulley/anterosuperior structures impinge against the antero-superior glenoid rim and labrum when the arm is placed in forward flexion, adduction and internal rotation — the opposite arm position to the late-cocking ABER that drives posterosuperior impingement. It is seen less in the classic late-cocking thrower and more in patients who repeatedly load the arm in flexion-adduction-internal-rotation, and its associated lesions are anterosuperior labral fraying, articular-sided (upper-border) subscapularis tears and biceps-pulley lesions — quite different from the posterosuperior labrum / posterior-cuff pattern. The exam point: when a shoulder reproduces deep pain in flexion-adduction-internal-rotation rather than in ABER, think anterosuperior (not posterosuperior) internal impingement and scrutinise the subscapularis and biceps pulley.
Classification and Staging
The disease is staged as a whole, and the two lesions it produces, the cuff tear and the labral tear, are each graded on their own terms. The stage tells you where the athlete is; the lesion grades tell you what, if anything, there is to operate on.
The Jobe classification, modified for internal impingement, stages the disease by what has happened to the tissues, and the stage carries the treatment with it. Most athletes present in Stage II, with contact pathology but no complete structural failure.
- Description
- Adaptive phase
- Pathology
- Posterior capsule tightness, GIRD present, no structural damage
- Treatment
- Conservative management
- Description
- Contact phase
- Pathology
- Posterosuperior labral fraying, partial articular-sided cuff tears
- Treatment
- Conservative first, surgery if failed
- Description
- Failure phase
- Pathology
- Full-thickness rotator cuff tear, labral detachment
- Treatment
- Surgical repair indicated
Clinical Presentation and Assessment
History. The patient is an overhead athlete, most often a baseball pitcher, then a volleyball or tennis player. Onset is usually gradual and related to a high volume of throwing, late in the season. The answers that place the diagnosis:
- Pain in the posterior shoulder
- Pain in the late cocking position, arm back in maximal external rotation
- Loss of velocity, control or endurance
- An occasional sensation of anterior instability, from the anterior translation
Examination. The examination has two jobs: to reproduce the contact, and to measure the rotation that explains it. The table lists the findings; the rotation measurements are worth a paragraph of their own.
- Technique
- Supine, 90deg abduction, measure IR
- Positive Finding
- Greater than 20-25deg loss vs contralateral
- Significance
- Hallmark finding - diagnostic of posterior capsule contracture
- Technique
- Same position; compare ER on throwing vs non-throwing side
- Positive Finding
- LESS than 5deg more ER on the throwing side
- Significance
- The measurement that actually predicted injury: 2.2x risk of being placed on the disabled list and 4.0x risk of surgery in 296 professional pitchers. A thrower who has NOT gained external rotation is the one at risk
- Technique
- Sum of ER + IR at 90deg abduction
- Positive Finding
- Decreased total arc vs contralateral
- Significance
- Indicates true capsular contracture (not just adaptation)
- Technique
- 90deg abduction, maximum ER
- Positive Finding
- Posterior shoulder pain reproduced
- Significance
- Reproduces impingement contact
- Technique
- Side-lying on affected side, IR arm
- Positive Finding
- Posterior pain, resistance
- Significance
- Tests posterior capsule tightness
- Technique
- Observe scapular motion with arm elevation
- Positive Finding
- Winging, lack of smooth rhythm, asymmetry
- Significance
- SICK scapula pattern
- Technique
- Palpate coracoid process
- Positive Finding
- Focal tenderness
- Significance
- Part of SICK scapula syndrome
- Technique
- ER, IR, supraspinatus testing
- Positive Finding
- Weakness suggests tear progression
- Significance
- Indicates structural damage
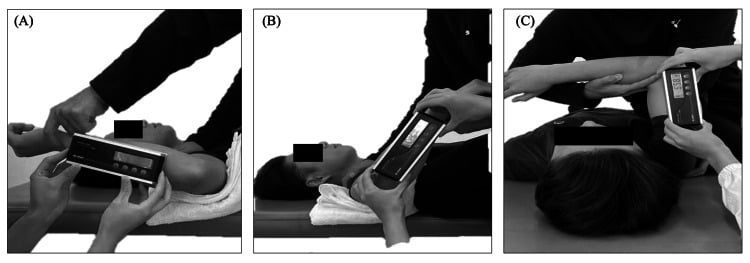
Measuring the rotation. The technique must be standardised and the scapula stabilised, or scapulothoracic motion will hide the deficit:
- Patient supine
- Shoulder abducted to 90 degrees
- Elbow flexed to 90 degrees
- Stabilise the scapula at the coracoid to isolate glenohumeral motion
- Measure maximum passive internal rotation and compare with the contralateral side
What the numbers mean. A slight loss of internal rotation on the dominant arm, 10-15 degrees, is normal adaptation, and the total arc should be preserved or increased. The findings of pathological GIRD:
- Loss of internal rotation greater than 20-25 degrees compared with the contralateral side
- Loss of the total arc of motion (ER plus IR)
GIRD is the key finding of posterior capsular contracture, and it is the rehabilitation target - but it is not the injury predictor, and the distinction is examinable.
Measure external rotation on the same visit. In 505 examinations of 296 professional pitchers followed prospectively, GIRD, total-rotation deficit and flexion deficit were none of them significantly associated with shoulder injury or surgery. What predicted both was insufficient external rotation - less than 5 degrees more ER on the throwing side than the non-throwing side - carrying 2.2 times the risk of a shoulder injury and 4.0 times the risk of surgery.
The two facts sit together without conflict once you separate mechanism from prediction: tight posterior capsule genuinely drives the impingement (cadaveric loading confirms it raises contact pressure), but the thrower who is about to be injured is identified by the external rotation he has failed to gain, not by the internal rotation he has lost. Screening a squad on internal rotation alone will miss him.
Additional tests. The remaining provocations complete the examination:
- Posterior impingement sign: pain with horizontal adduction and internal rotation
- Internal rotation resistance strength test (IRRST): resisted internal rotation at 90 degrees of abduction reproduces the pain
- Relocation test: may be positive, from the anterior translation component
Differential diagnosis. Posterior pain in a thrower has a short list of alternatives, each with a discriminating feature:
- Key Differentiating Features
- Pain in forward flexion, positive Neer/Hawkins, different location
- Key Differentiating Features
- Apprehension in ABER, history of dislocation, positive relocation
- Key Differentiating Features
- Biceps-related symptoms, O'Brien's test positive, overhead motion pain
- Key Differentiating Features
- Neck pain, dermatomal symptoms, Spurling's test positive
- Key Differentiating Features
- Vascular/neurologic symptoms, positive Adson's test
Investigations
Plain radiographs. AP, scapular Y and axillary views. They are usually normal in early internal impingement; when they are not, they may show:
- Subtle sclerosis at the posterosuperior glenoid
- Calcification in the posterior capsule (chronic)
- A Bennett lesion, which is related pathology rather than the impingement itself
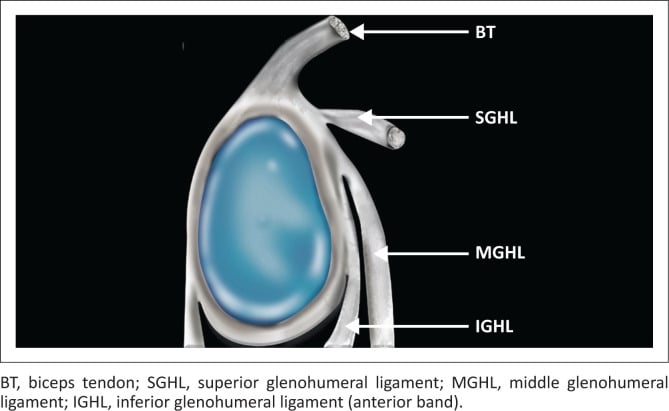
Bennett lesion is a posteroinferior glenoid ossification of the posterior band of the inferior glenohumeral ligament at its glenoid insertion. In a systematic review of thrower's exostoses, a radiographic lesion was present in roughly half of imaged throwing athletes, of whom about three-quarters were symptomatic, and the posteroinferior location predominated (Freehill 2020). It represents a separate throwing adaptation, not internal impingement itself, although both can coexist.
MRI is the gold standard for the pathology of internal impingement. MR arthrography may improve sensitivity for labral tears, and the ABER sequence, imaging in abduction and external rotation, best visualises the posterosuperior pathology because it images the contact zone. The findings to look for:
- Posterosuperior labral fraying or detachment
- Partial-thickness articular-sided rotator cuff tear, high signal on T2
- Cystic change in the posterosuperior humeral head, at the contact zone
- Posterior capsular thickening
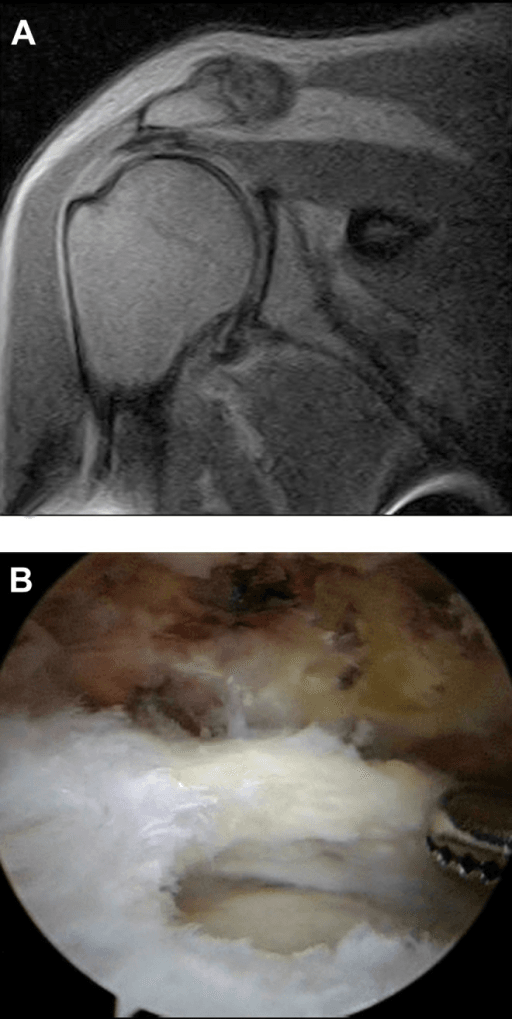
Findings by severity. The MRI picture progresses with the stage:
- Early
- Normal
- Intermediate
- Fraying, increased signal
- Advanced
- Detachment
- Early
- Normal or signal change
- Intermediate
- Partial articular-sided tear
- Advanced
- High-grade partial or full-thickness
- Early
- Subtle thickening
- Intermediate
- Moderate thickening
- Advanced
- Severe contracture
- Early
- Normal
- Intermediate
- Cystic change humeral head
- Advanced
- Posterosuperior glenoid wear
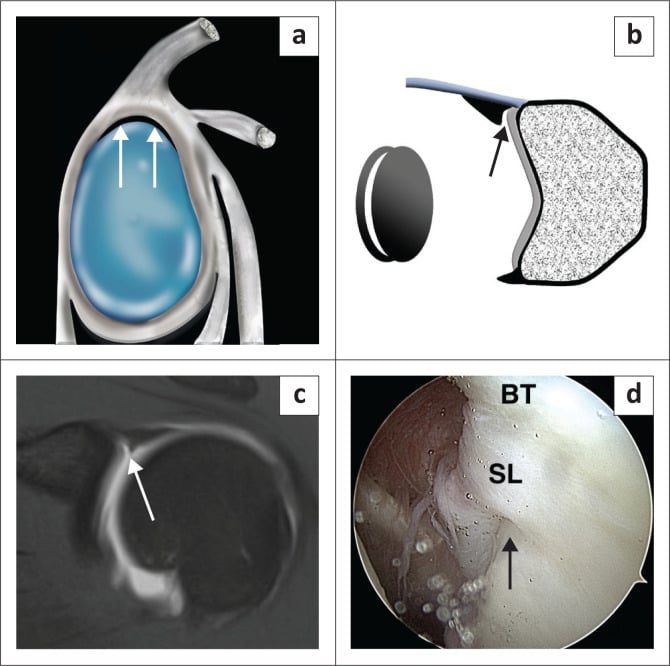
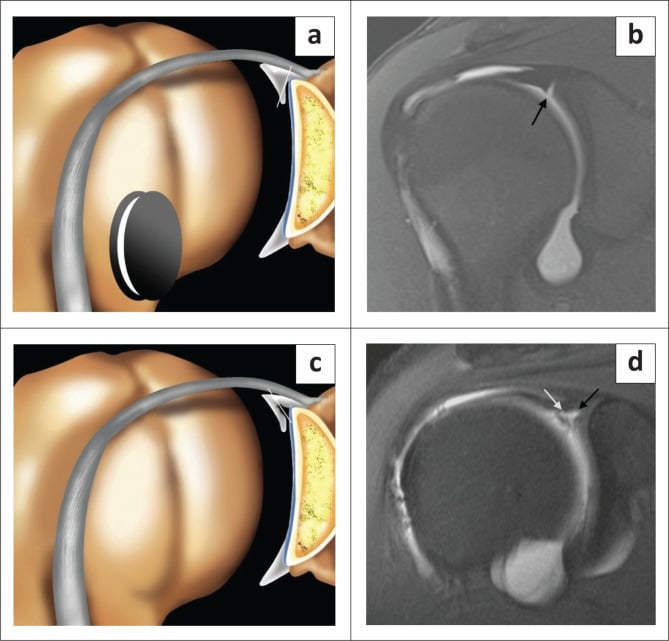
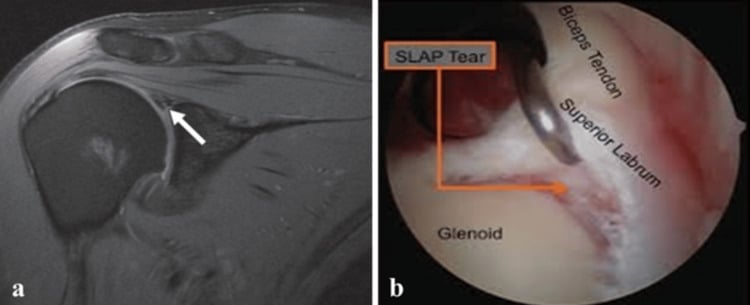
The false positive. The commonest is the sublabral recess. A recess directs contrast medially and follows the glenoid contour, and on the coronal oblique image it gives a single line of contrast between labrum and glenoid, the single Oreo cookie sign. A SLAP tear extends laterally into the labral substance; two lines, or contrast tracking laterally, indicate a genuine detachment. Calling a normal recess a tear commits a thrower to unnecessary surgery, and MRI alone overcalls the diagnosis, so correlate the imaging with the arthroscopic findings before operating.
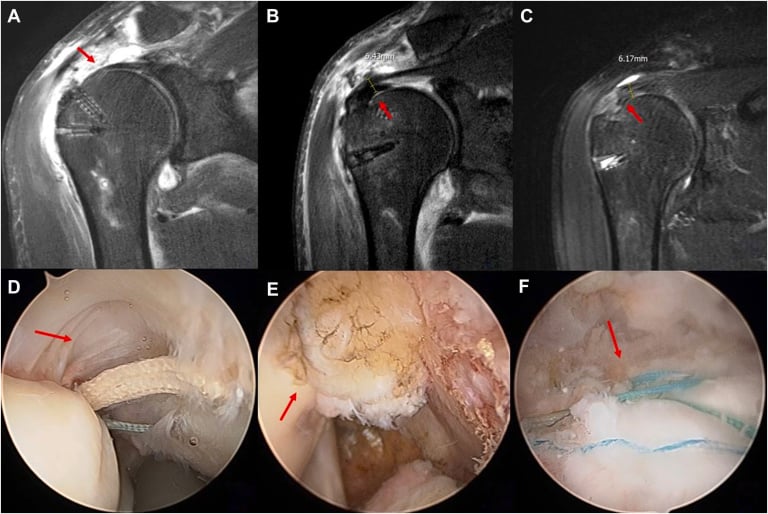
Measure the tear. Internal impingement damages the undersurface of the cuff, so measure the residual tendon thickness on the coronal fat-suppressed sequence rather than simply reporting a partial tear. The thickness is what decides debridement against repair (see Surgical Technique).
Ultrasound allows a dynamic examination and can show partial-thickness cuff tears, but it is operator-dependent and less useful for the labrum.
CT is not typically indicated. It is used when the bone is the question:
- Humeral retroversion, the bony adaptation in young throwers
- Glenoid version
- An osseous Bennett lesion
Management Algorithm
The decision. Non-operative treatment is first-line for all internal impingement, and it is trialled for a minimum of 3-6 months before surgery is considered. It returns more athletes to sport than surgery does (the figures are in Outcomes), so surgery is a salvage after non-operative care has failed, not a shortcut to recovery, and it is offered only to the thrower who still has performance-limiting pain and a structural lesion.
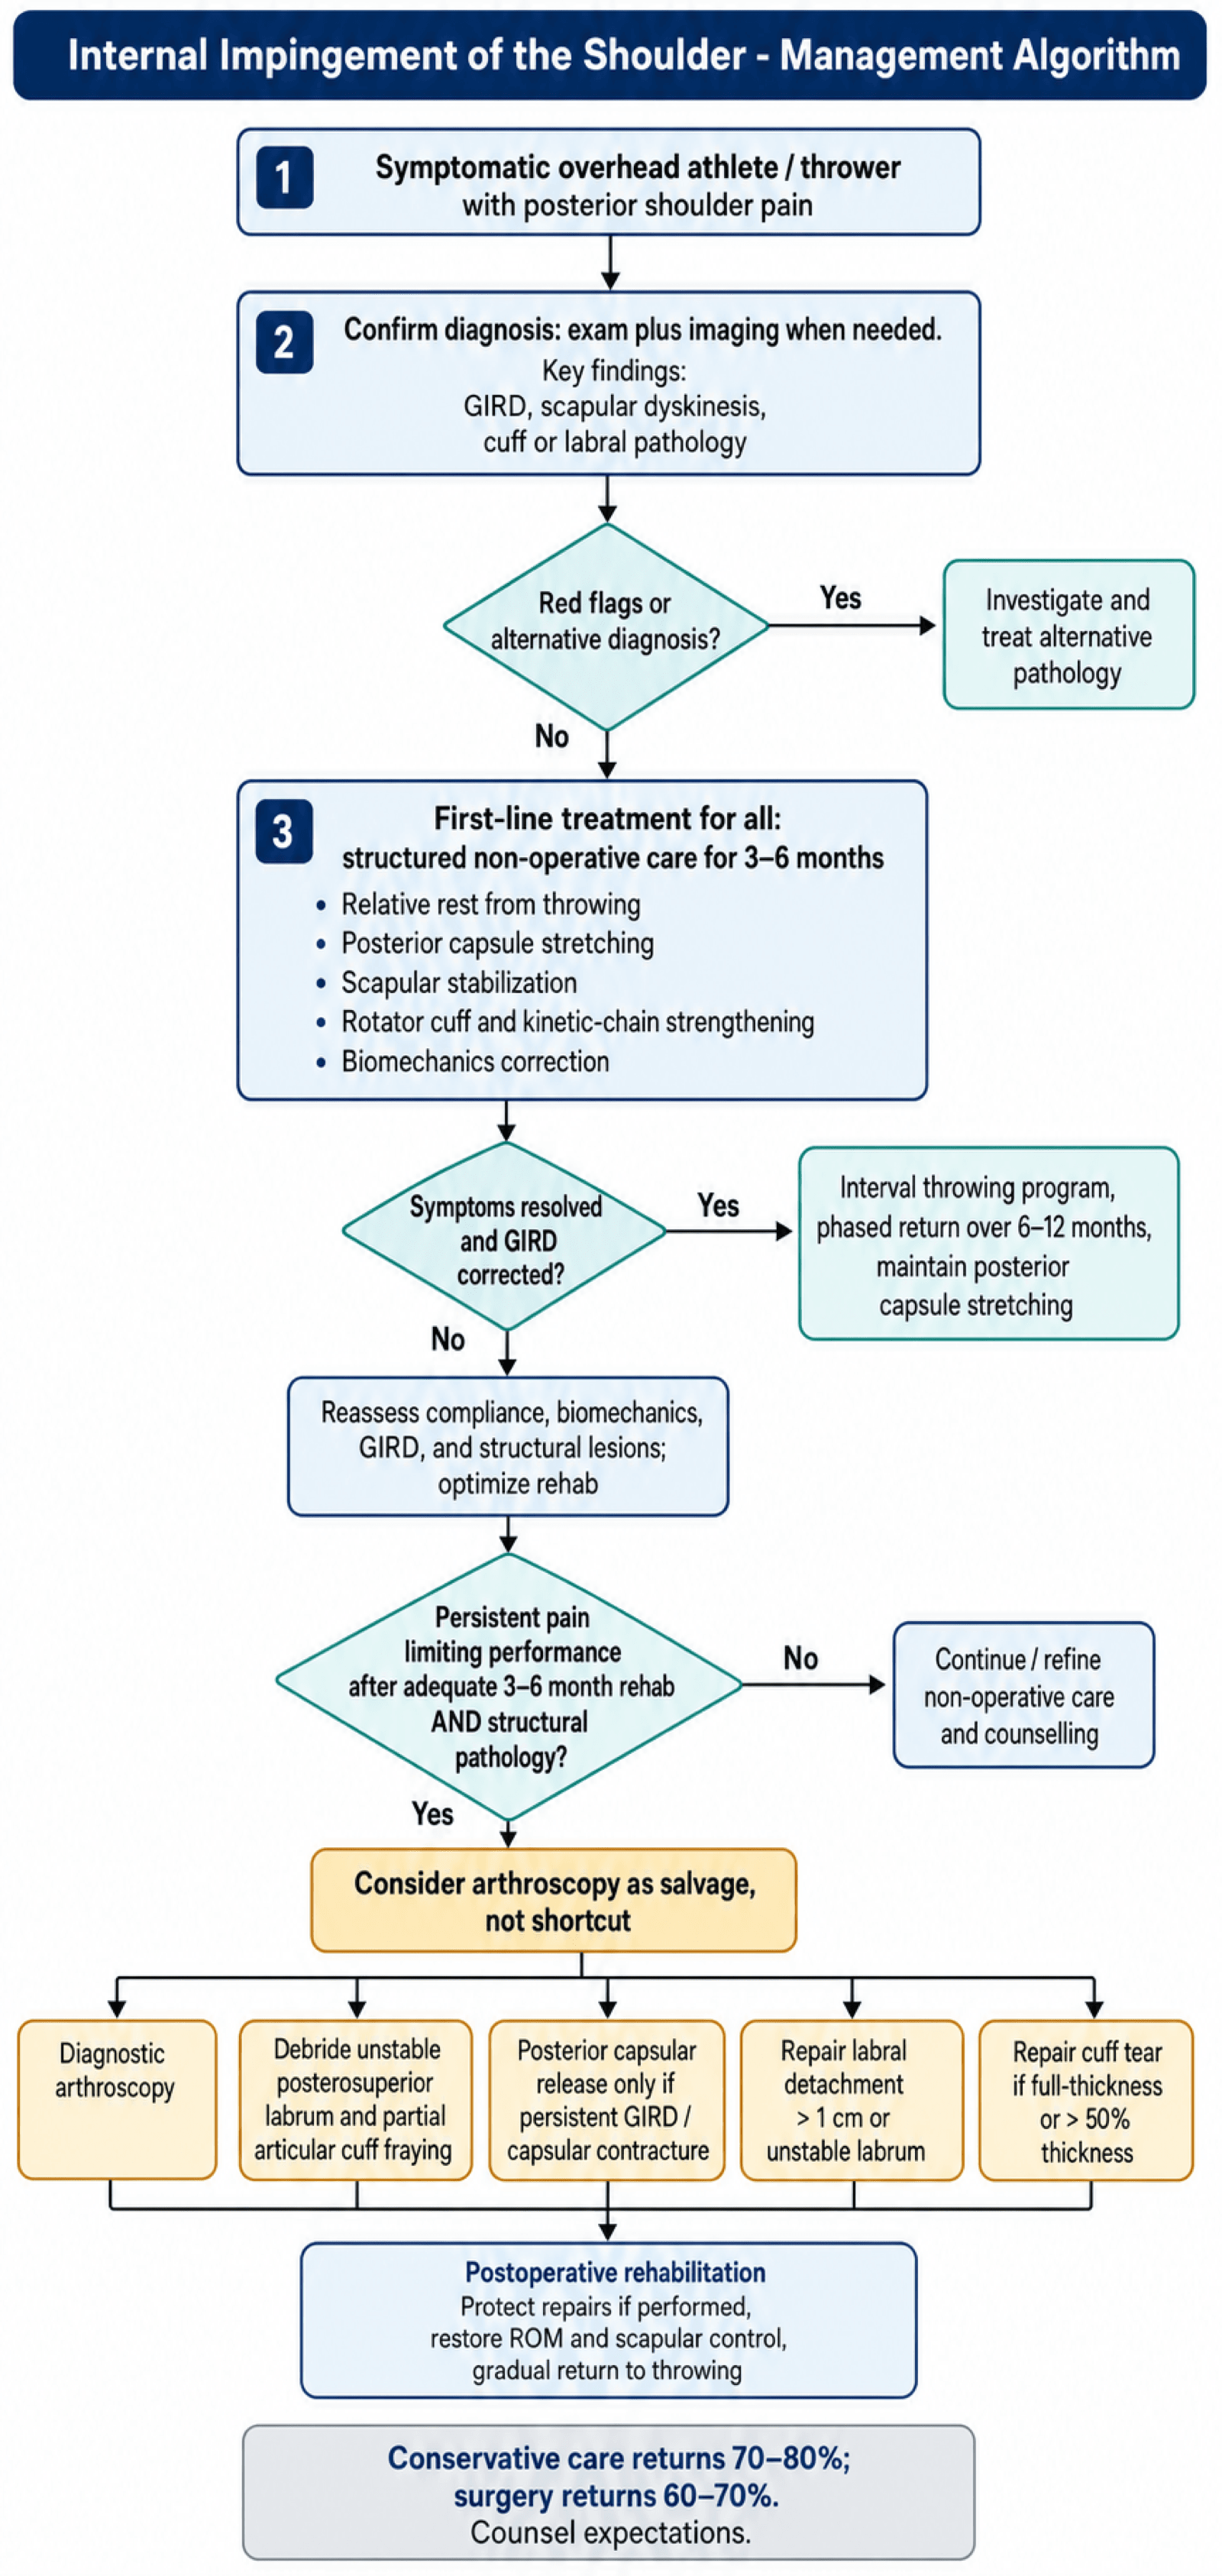
The principles. Complete rest from throwing is not required, and the programme should address the entire kinetic chain, core, legs and trunk included:
- Relative rest from throwing
- Posterior capsule stretching, the primary intervention
- Scapular stabilisation exercises
- Maintain rotator cuff strength
- A progressive return to throwing programme
Posterior capsule stretching. Three stretches; the sleeper and cross-body stretches are each held for 30 seconds and repeated 5 times, three times daily:
- Sleeper stretch: lie on the throwing shoulder with the arm forward at 90 degrees and push the throwing arm into internal rotation with the opposite hand
- Cross-body adduction stretch: bring the throwing arm across the body and assist the stretch with the opposite hand
- Horizontal adduction stretch: as the cross-body stretch but at 90 degrees of flexion, an effective posterior capsule stretch
Scapular stabilisation. Strengthen the stabilisers and stretch pectoralis minor:
- Serratus anterior: wall slides, push-up plus
- Lower trapezius: prone Y, T and W exercises
- Middle trapezius: rows
- Pectoralis minor stretching: doorway stretch
Rotator cuff strengthening. Focus on the external rotators, infraspinatus and teres minor, and maintain internal rotator strength, but avoid excessive external rotator strengthening, which can worsen the GIRD.
Surgical Technique
Position. Beach chair or lateral decubitus. Lateral decubitus gives better access to the posterior structures, with the arm in 10-15 lb of traction.
Portals. The standard set:
- Posterior viewing portal: the standard posterior portal
- Anterior working portal: mid-glenoid or low anterior
- Posterolateral accessory portal: for access to the posterior labrum
- Port of Wilmington: anterosuperior portal for suture passage
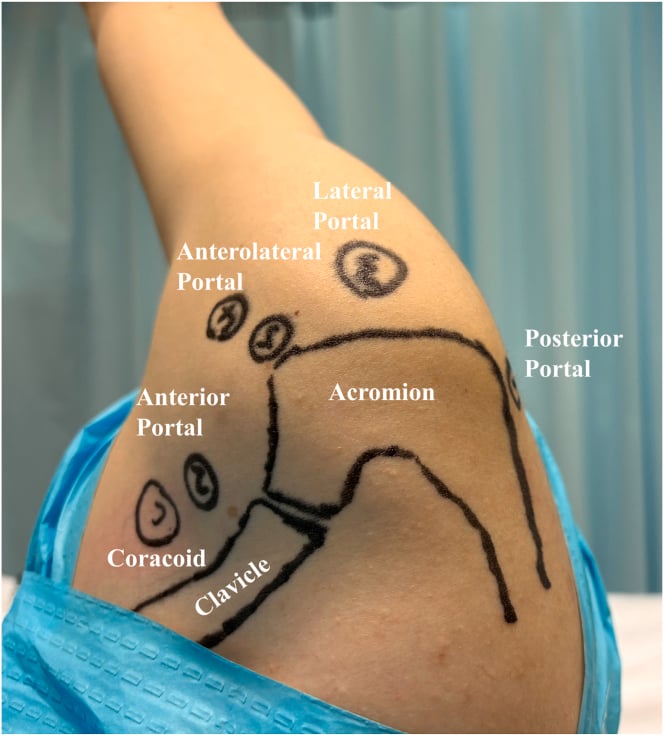
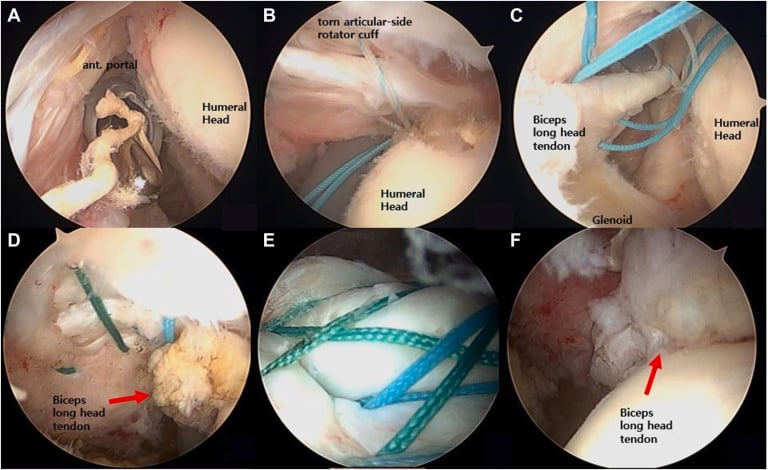
Diagnostic sequence. A systematic examination finds all the pathology before any of it is treated:
- Glenohumeral joint, anterior and superior
- Posterosuperior inspection, the key area
- Labrum: fraying, detachment
- Rotator cuff, articular side, from within the joint
- Subacromial space, to rule out external impingement
Complications
- Incidence
- 30-40% (surgery)
- Prevention/Management
- Extensive preop and postop rehab, realistic expectations
- Incidence
- Common if stretching stopped
- Prevention/Management
- Lifelong posterior capsule stretching programme
- Incidence
- 10-20%
- Prevention/Management
- Early ROM, avoid over-aggressive capsular release
- Incidence
- Rare (under 5%)
- Prevention/Management
- Conservative capsular release, avoid excessive release
- Incidence
- 10-15% if partial tear
- Prevention/Management
- Consider repair if greater than 50% thickness
- Incidence
- Rare (under 1%)
- Prevention/Management
- Stay glenoid-side during posterior capsular release
- Incidence
- 20-30%
- Prevention/Management
- Address biomechanics, kinetic chain, return to sport criteria
Failure to return to sport is the complication that matters most to an athlete. It follows inadequate rehabilitation, poor biomechanics and unrealistic expectations, and it is prevented by comprehensive rehabilitation, attention to the kinetic chain and a gradual return. When it happens, the options are continued non-operative care, and career counselling is considered.
Recurrent GIRD is very common once the stretching programme is abandoned. Educate the athlete that maintenance is lifelong, and when GIRD is detected again, resume the stretching programme immediately.
Stiffness can follow surgery, particularly after a capsular release. Prevention is early range-of-motion exercises and the avoidance of immobilisation; established stiffness is treated with aggressive physiotherapy, and manipulation under anaesthesia is considered if it is severe.
Postoperative Care and Rehabilitation
After arthroscopic debridement, with or without posterior capsular release, the protocol below applies. Athletes who undergo simple debridement can typically return to throwing by 4-6 months with good outcomes.
- Sling for comfort (not strict immobilisation)
- Pendulum exercises day 1
- Passive ROM to tolerance
- No stretching yet (allow capsule to heal if released)
- Ice, pain control
- Progress to active-assisted ROM
- Begin gentle posterior capsule stretching (week 3-4)
- Scapular stabilisation exercises
- Light rotator cuff strengthening (isometrics)
- Goal: Full passive ROM by 6 weeks
- Advance to full active ROM
- Progressive rotator cuff strengthening
- Scapular stabilisation progression
- Light sport-specific activities (no throwing)
- Confirm GIRD correction
- Interval throwing programme begins
- Start at 45 feet, light toss
- Maintain stretching programme
- Monitor symptoms closely
- Progress distance gradually
- Progress throwing distance and intensity
- Introduce mound throwing (pitchers)
- Sport-specific training
- Return to competition if asymptomatic
- Typical return 6-9 months for debridement
Outcomes and Prognosis
Conservative management returns most athletes to their previous level, and the table shows how the rest are distributed.
- Percentage
- 70-80%
- Notes
- With comprehensive rehab program
- Percentage
- 10-15%
- Notes
- Modified participation
- Percentage
- 10-15%
- Notes
- Career-ending
What predicts conservative success. The factors are:
- Early intervention, before structural damage
- Compliance with the stretching programme
- Correction of GIRD, with a greater than 20 degrees improvement
- Scapular dyskinesis addressed
- Biomechanical coaching
- Younger age
- Shorter symptom duration
Surgical management returns fewer athletes to sport than conservative care does. The idea that surgery is a fix is incorrect; it is a salvage procedure after non-operative failure.
- Return to Sport
- 60-70%
- Satisfaction
- 70-80%
- Timeline
- 6-9 months
- Return to Sport
- 65-75%
- Satisfaction
- 75-85%
- Timeline
- 6-9 months
- Return to Sport
- 50-60%
- Satisfaction
- 60-70%
- Timeline
- 9-12 months
What predicts surgical success, and its mirror image. The athlete who does well had the GIRD corrected preoperatively, has limited structural damage with no full-thickness tear, has a debridement rather than a repair, has good preoperative strength, complies fully with the postoperative rehabilitation and holds realistic expectations. The athlete who does badly has the opposite on each count, a full-thickness cuff tear, persistent GIRD postoperatively, poor biomechanics left unaddressed, inadequate rehabilitation or unrealistic expectations, or simply returns too early.
The long view. Symptoms recur if maintenance is abandoned, the cuff degenerates progressively in some athletes, career longevity may be shortened, and some will need to modify their throwing mechanics or volume.
Guidelines, Registries & Global Practice
Internal impingement is a clinical/biomechanical diagnosis of the overhead athlete; there is no joint-replacement registry for it and no single national society has issued a dedicated standalone guideline. The evidence base is therefore built from the original arthroscopic description, biomechanical models, prospective athlete cohorts and society-level overhead-athlete/shoulder-instability consensus. The world standard of care is consistent: non-operative management first, surgery only for refractory structural failure.
Global epidemiology (PubMed-backed):
- Evidence
- Throwing/overhead athletes; dominant arm; typically 15-35 years
- Source
- Walch 1992 (PMID 22959196)
- Evidence
- Insufficient external-rotation gain → 2.2x shoulder injury, 4.0x surgery; isolated GIRD NOT independently significant in a 296-pitcher prospective cohort
- Source
- Wilk 2015 (PMID 26272516)
- Evidence
- Pitchers with GIRD nearly twice as likely to be injured, but not statistically significant (P=0.17) in a 122-pitcher series
- Source
- Wilk 2010 (PMID 21131681)
- Evidence
- Thrower's exostosis (incl. Bennett lesion) on imaging in roughly half of throwers; ~75% symptomatic; posteroinferior predominant
- Source
- Freehill 2020 (PMID 32704507)
The classic teaching that "GIRD greater than 20-25 degrees causes injury" is a useful clinical screen but is not a clean independent predictor in the best prospective data (Wilk 2015, PMID 26272516). The more robust message is to assess the total rotational arc and whether the expected external-rotation gain is preserved. Treat loss of total arc and posterior capsular contracture, not an isolated IR number.
Side-by-side guidance (overhead athlete shoulder):
- Position on internal impingement
- No disease-specific guideline; consensus within overhead-athlete and shoulder-instability literature favours structured non-operative care first, debridement/capsular management for failures
- Evidence level
- Expert consensus / Level IV-V
- Position on internal impingement
- Managed within shoulder instability and atraumatic instability pathways; physiotherapy-led rehabilitation (e.g. structured programmes) is first-line for atraumatic/overhead shoulder dysfunction
- Evidence level
- Level IV-V, programme-based RCT evidence for rehab
- Position on internal impingement
- Recognise posterosuperior impingement as a distinct entity; arthroscopic options range from debridement to selective SLAP/biceps and capsular procedures after failed rehabilitation
- Evidence level
- Level IV
- Position on internal impingement
- Not a fracture/fixation topic — no AO guidance; relevant only for associated bony glenoid lesions
- Evidence level
- N/A
- Position on internal impingement
- GIRD / posterior capsular contracture model and SICK scapula drive rehabilitation worldwide
- Evidence level
- Burkhart 2003 (PMID 12671624)
Not applicable — this is a soft-tissue/biomechanical sports diagnosis, not an arthroplasty or implant procedure, so the joint registries (NJR, AJRR, AOANJRR, SHAR, NZJR) do not capture it. Outcome data derive from athlete cohort studies and case series rather than registries.
- Sport mix drives the case-mix, not the pathology. Baseball pitchers dominate North American series; cricket fast bowlers (similar late-cocking biomechanics), handball, javelin, tennis serving, volleyball and competitive swimming predominate in Europe, Australasia and Asia. The underlying GIRD/posterior-capsule mechanism is identical.
- High-resource settings use MR arthrography with ABER sequences and arthroscopy for refractory cases; limited-resource settings rely on clinical GIRD assessment, plain radiographs and supervised physiotherapy, with strong outcomes given that non-operative care is first-line everywhere.
- Return-to-sport timing is shaped by the competitive calendar (e.g. off-season surgery), professional contracts and access to sports physiotherapy, rather than by differing surgical doctrine.
- Key history
- Posterior 'deep' pain in late cocking (ABER), velocity loss, gradual onset
- Discriminating examination
- GIRD / reduced total arc, pain reproduced in ABER, positive posterior impingement sign
- Imaging / confirmation
- MRA/ABER MRI: posterosuperior labral fraying + articular-sided cuff tear
- Key history
- Pain with forward elevation/overhead reaching, older or non-throwing patient
- Discriminating examination
- Positive Neer and Hawkins-Kennedy, painful arc, subacromial tenderness
- Imaging / confirmation
- Bursal-sided changes, acromial morphology; relief with subacromial block
- Key history
- Apprehension/'dead arm' in ABER, history of subluxation/dislocation
- Discriminating examination
- Positive apprehension AND relocation (pain relieved by posterior force)
- Imaging / confirmation
- MRA: anteroinferior labral (Bankart) lesion
- Key history
- Mechanical clicking, biceps-region pain, overhead pain in multiple positions
- Discriminating examination
- Positive O'Brien (active compression), dynamic labral shear; peel-back at arthroscopy
- Imaging / confirmation
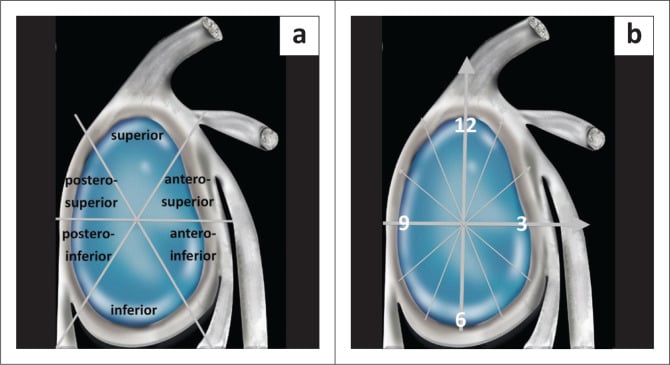
- MRA superior labral detachment at 12 o'clock (vs 10-11 o'clock for internal impingement)
- Key history
- Posterior shoulder ache in throwers, may be incidental
- Discriminating examination
- Posteroinferior glenoid tenderness, often coexists with GIRD
- Imaging / confirmation
- Posteroinferior glenoid ossification on axillary radiograph/CT (Freehill 2020)
- Key history
- Neck pain, dermatomal arm symptoms, paraesthesia
- Discriminating examination
- Positive Spurling, neurological deficit, normal local shoulder tests
- Imaging / confirmation
- Cervical MRI; nerve root compression
- Key history
- Positional arm heaviness, vascular or neurological symptoms
- Discriminating examination
- Positional provocation (Roos/Adson), pulse/colour change
- Imaging / confirmation
- Vascular studies, dynamic imaging
Be prepared to describe the pathomechanics of GIRD causing internal impingement (Burkhart 2003; Mihata 2015 cadaveric model). Understand that structured non-operative management is first-line with the majority of athletes returning to sport. Know the GIRD measurement technique (90 degrees abduction, scapula stabilised) and the classic pathologic threshold (greater than 20-25 degrees), but be ready to qualify it with the prospective evidence (Wilk 2015) that the total rotational arc and preserved external-rotation gain matter more than an isolated IR deficit. Emphasise that surgery is reserved for failed conservative care and has inferior return-to-sport rates to successful non-operative management.
MCQ Practice Points
Q: What is the anatomic contact in internal impingement of the shoulder? A: Posterosuperior rotator cuff (supraspinatus-infraspinatus junction) contacts the posterosuperior glenoid labrum when the shoulder is in ABER (abduction-external rotation) position. This is a normal phenomenon that becomes pathologic with repetitive overhead activity.
Q: What is the pathologic threshold for GIRD (glenohumeral internal rotation deficit)? A: Greater than 20-25 degrees loss of internal rotation compared to the contralateral shoulder, measured at 90 degrees of shoulder abduction with the scapula stabilized. This indicates posterior capsule contracture requiring treatment.
Q: What is first-line treatment for internal impingement syndrome in a throwing athlete? A: Conservative management with posterior capsule stretching (sleeper stretch, cross-body adduction stretch) and scapular stabilization exercises for minimum 3-6 months. This has 70-80% success rate for return to sport, which is superior to surgical outcomes.
Q: What does the SICK scapula mnemonic stand for? A: S: Scapular malposition (inferior and protracted), I: Inferior medial border prominence, C: Coracoid pain and tenderness, K: dysKinesis (abnormal scapular motion). This commonly coexists with internal impingement and must be addressed in treatment.
Q: When should arthroscopic debridement be considered for internal impingement? A: After failed conservative management (minimum 3-6 months trial) with persistent pain limiting performance despite GIRD correction efforts, AND documented structural pathology on MRI (posterosuperior labral fraying, partial articular-sided rotator cuff tear).
Q: What percentage of overhead athletes return to pre-injury level after arthroscopic treatment for internal impingement? A: 60-70% after arthroscopic debridement, which is actually lower than the 70-80% success rate with conservative management alone. This emphasizes that surgery is a salvage procedure, not a superior treatment option.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 22-year-old professional baseball pitcher presents with posterior shoulder pain during the late cocking phase of throwing. He has lost 10 mph velocity over the past 2 months. On examination, he has 55 degrees of internal rotation on the throwing side vs 80 degrees on the non-throwing side, measured at 90 degrees abduction. External rotation is 95 degrees bilaterally. What is your diagnosis and management?”
“The pitcher from Scenario 1 has undergone 4 months of intensive physical therapy with posterior capsule stretching. His GIRD has improved from 25 degrees to 15 degrees. However, he still has posterior shoulder pain when attempting to throw and cannot achieve full velocity. MRI shows posterosuperior labral fraying and a 30% partial articular-sided tear of the infraspinatus. He wants to continue his professional career. What is your recommendation?”
“A 19-year-old collegiate volleyball player presents with shoulder pain during serving and spiking. She describes the pain as 'deep inside' her shoulder when her arm is back. She also notes occasional clicking. On examination, she has GIRD of 15 degrees, pain with ABER position, and a positive O'Brien's test. MRI shows posterosuperior labral signal abnormality and a possible SLAP lesion. How do you differentiate between internal impingement and a SLAP tear, and how does this affect your management?”
CORE PATHOPHYSIOLOGY
- Contact between posterosuperior rotator cuff and posterosuperior labrum in ABER position
- Normal phenomenon that becomes pathologic with repetitive overhead activity
- GIRD (glenohumeral internal rotation deficit) is the hallmark clinical finding
- Posterior capsule contracture → GIRD → Obligate anterior translation → Excessive contact
- Results in posterosuperior labral fraying and partial articular-sided cuff tears
GIRD MEASUREMENT
- Patient supine, shoulder 90 degrees abduction, elbow 90 degrees flexion
- Stabilize scapula to isolate glenohumeral motion
- Measure maximum passive internal rotation bilaterally
- Pathologic threshold: greater than 20-25 degrees side-to-side difference
- Also measure total arc (ER + IR) - loss of total arc indicates true contracture
CLINICAL PRESENTATION
- Overhead throwing athletes (baseball, cricket, volleyball, tennis, swimming)
- Posterior shoulder pain in late cocking phase (ABER position)
- Loss of velocity or performance in throwing/serving
- GIRD on examination (greater than 20-25 degrees)
- Pain reproduced in ABER position
- SICK scapula commonly coexists
SICK SCAPULA
- S: Scapular malposition (inferior and protracted)
- I: Inferior medial border prominence
- C: Coracoid pain and tenderness
- K: dysKinesis (abnormal scapular motion)
- Must address scapular dysfunction in treatment
CONSERVATIVE MANAGEMENT (FIRST-LINE)
- 70-80% return to sport success rate (superior to surgery)
- Minimum 3-6 months trial before considering surgery
- Posterior capsule stretching: Sleeper stretch, cross-body adduction (5x30sec, 3x daily)
- Scapular stabilization exercises (serratus, trapezius strengthening)
- Rotator cuff strengthening maintenance
- Interval throwing program after symptoms resolve (6-12 months total)
- Lifelong maintenance stretching required
SURGICAL MANAGEMENT
- Indications: Failed 3-6 months conservative care, persistent symptoms
- Arthroscopic debridement: Posterosuperior labral fraying, partial cuff tear
- Posterior capsular release: For persistent GIRD
- Do NOT repair partial tears under 50% thickness (avoid conversion to full-thickness)
- Do NOT repair degenerative labral fraying (debride only)
- Return to sport: 60-70% (inferior to conservative management)
- Timeline: 6-9 months (debridement), 9-12 months (if repair needed)
IMAGING
- Plain radiographs: Usually normal, rule out Bennett lesion
- MRI/MRA: Posterosuperior labral fraying, partial articular-sided cuff tear
- ABER view MRI: Best visualizes contact zone
- Cystic changes in posterosuperior humeral head (contact zone)
- Posterior capsular thickening
KEY EXAM PEARLS
- Internal impingement is NORMAL contact that becomes PATHOLOGIC
- GIRD greater than 20-25 degrees is pathologic threshold
- Conservative management has BETTER outcomes than surgery (70-80% vs 60-70%)
- Posterior capsule stretching is PRIMARY treatment
- Surgery is SALVAGE after failed conservative care, not first-line
- SICK scapula commonly coexists - must address scapular dysfunction
- Lifelong maintenance stretching required (no cure, only management)
- Distinguish from SLAP tears (can coexist but different treatment)
Evidence Base
Walch et al. Impingement of the deep surface of supraspinatus on the posterosuperior glenoid rim — original arthroscopic description
- Original description of internal (posterosuperior) impingement. 17 throwing athletes (mean age 25 years) with unexplained shoulder pain and NO clinical/radiological/arthroscopic anterior instability underwent arthroscopy.
- With the arm in 90 degrees abduction and full external rotation (throwing position), impingement was directly observed between the posterosuperior glenoid rim and the undersurface of supraspinatus/infraspinatus.
- Partial articular-sided cuff rupture in 8 patients, capsulotendinous tears in 9, and posterosuperior labral lesions in 12 — defining a distinct entity from Neer subacromial and Jobe instability-related impingement.
Burkhart, Morgan & Kibler. The Disabled Throwing Shoulder: Spectrum of Pathology, Part I — Pathoanatomy & Biomechanics
- Landmark unified concept rejecting microinstability as the universal cause of the disabled throwing shoulder.
- Proposed that posteroinferior capsular contracture produces glenohumeral internal rotation deficit (GIRD), posterosuperior shift of the glenohumeral contact point and scapulohumeral hyperangulation, driving pathologic internal impingement and peel-back SLAP lesions.
- Companion Parts II (SLAP evaluation/treatment) and III (SICK scapula, scapular dyskinesis, kinetic chain) frame rehabilitation around restoring internal rotation and scapular control.
Mihata et al. Effect of posterior shoulder tightness on internal impingement in a cadaveric model of throwing
- Seven cadaveric shoulders tested at 90 degrees abduction and maximum external rotation (late cocking). Posteroinferior capsular plication was used to simulate contracture and induce GIRD.
- Simulated GIRD significantly increased glenohumeral contact pressure (P less than 0.05) and shifted the humeral head posteriorly during internal impingement.
- Confirms the mechanical link between posterior capsular tightness/GIRD and forceful internal impingement.
Wilk et al. Deficits in Glenohumeral Passive Range of Motion Increase Risk of Shoulder Injury in Professional Baseball Pitchers (prospective)
- 505 examinations on 296 professional pitchers over 8 seasons; 75 shoulder injuries and 20 surgeries. ROM measured supine at 90 degrees abduction with the scapula stabilised at the coracoid.
- Contrary to common teaching, isolated GIRD, total-rotation deficit and flexion deficit were NOT significantly associated with shoulder injury or surgery in this cohort.
- Insufficient external rotation (less than 5 degrees more ER on the throwing side) carried 2.2x risk of shoulder injury and 4.0x risk of surgery — i.e. loss of the expected ER gain, not IR loss alone, was the predictor.
Heyworth & Williams. Internal Impingement of the Shoulder (review with diagnostic/therapeutic algorithm)
- Comprehensive review of pathomechanics, examination and imaging of internal impingement, integrating instability, posterior capsular contracture and scapular dyskinesis as contributing factors.
- Presents a structured diagnostic and therapeutic algorithm: structured non-operative care first (posterior capsular stretching, scapular and cuff rehabilitation), with arthroscopy reserved for failure.
- Emphasises MR arthrography and the ABER sequence for demonstrating posterosuperior labral and articular-sided cuff lesions.
Spiegl, Warth & Millett. Symptomatic Internal Impingement of the Shoulder in Overhead Athletes (review)
- Reaffirms that internal impingement is normal physiological posterosuperior contact that becomes symptomatic with repetitive overhead load, producing partial articular-sided cuff tears and posterosuperior labral lesions.
- Implicates a combination of factors — repetitive load, physiological humeral remodelling (retroversion), posterior capsular contracture and scapular dyskinesis causing scapulohumeral hyperangulation.
- Supports critical, individualised assessment and non-operative-first management.
Freehill et al. Thrower's Exostosis of the Shoulder: A Systematic Review with a Novel Classification (Bennett lesion)
- 27 studies; 158 of 306 athletes (52%) had a thrower's exostosis on imaging, of whom 75% were symptomatic. Lesions were posteroinferior in 70%, posterosuperior in 28%.
- Bennett lesion is a posteroinferior glenoid ossification of the posterior band of the inferior glenohumeral ligament — a throwing adaptation that can coexist with, but is distinct from, internal impingement.
- Surgery is reserved for refractory cases; only 61% returned to pre-injury performance after operative excision/repair.