Low Back Pain — Assessment & Non-operative Management
Overview & Epidemiology
Low back pain is one of the leading causes of disability worldwide: a near-universal lifetime experience, a leading global contributor to years lived with disability and to health-care cost, and a daily clinical problem. It is an exam staple because the skill tested is judgement, not a structural diagnosis: the triage, the red-flag and cauda-equina safety net, the do-not-over-image rule, and the opioid and surgery overuse problem are all high-yield governance points.
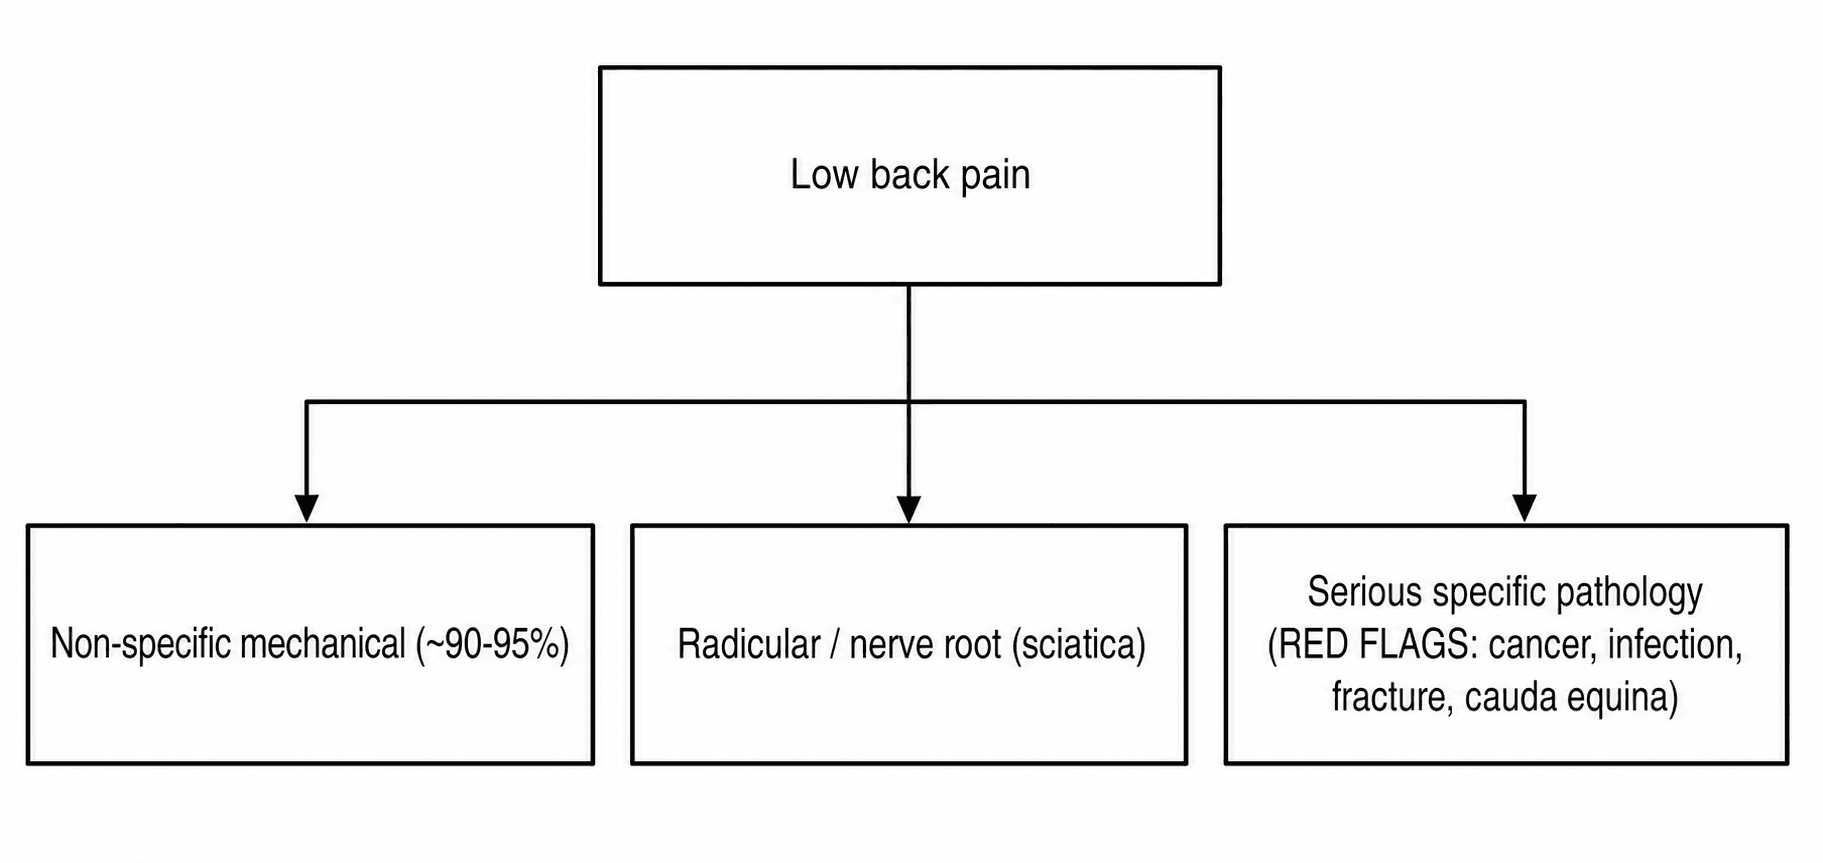
Proportions. About 90-95% is "non-specific" mechanical pain with no identifiable pathoanatomical cause. A minority is radicular, and only a small fraction is serious specific pathology.
Natural history. Most acute episodes have a favourable course and many need little formal care. A substantial minority become chronic and disabling, and that transition is predicted by the yellow flags described below.
Pathophysiology: why triage, not a structural hunt
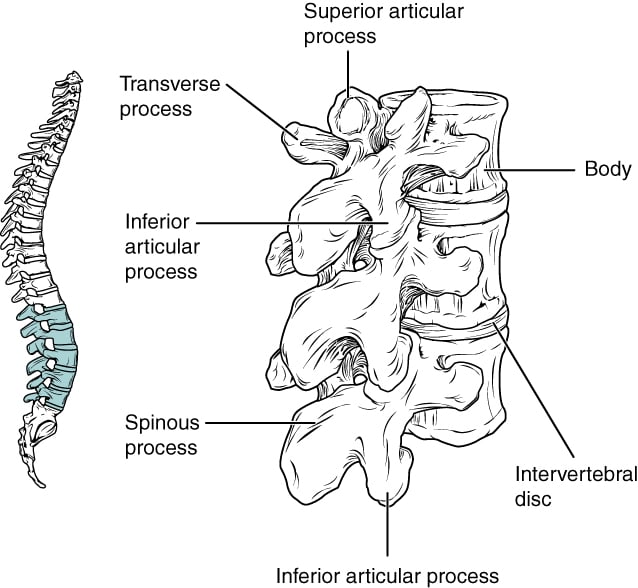
Many sources, low imaging specificity. The lumbar spine has many potential pain sources: the vertebral bodies and intervertebral discs, the zygapophyseal (facet) joints, the sacroiliac joints, and the surrounding muscles, ligaments and neurovascular structures. Imaging has low specificity, because degenerative changes are near-universal with age and correlate poorly with pain. Most low back pain therefore cannot be ascribed to a single pathoanatomical cause and is labelled non-specific.
The useful approach. Sort the patient into one of three groups (non-specific mechanical, radicular, or serious specific pathology flagged by red flags) and understand why pain becomes disabling through the biopsychosocial model. The triage, not a structural diagnosis, drives investigation and management.
Red flags — don't miss serious pathology
Red flags are the features that mark the small group with serious specific pathology, grouped here by the disease each set points to.
- Red-flag features
- Age over 50 or under 20, history of cancer, unexplained weight loss, night/rest pain, pain not relieved by lying down, systemic illness
- Red-flag features
- Fever/rigors, IV drug use, immunosuppression, recent infection/procedure, night sweats
- Red-flag features
- Significant trauma; or minor trauma with osteoporosis, prolonged steroids, or older age
- Red-flag features
- Saddle anaesthesia, bladder dysfunction (retention/overflow incontinence), bowel incontinence, sexual dysfunction, bilateral leg pain/weakness
- Red-flag features
- Age under 45, insidious onset, morning stiffness over 30 minutes, improves with exercise not rest, night pain, alternating buttock pain
TUNA FISHRed flags
Hook:TUNA FISH = the low-back-pain RED FLAGS (and don't miss cauda equina among the neurological).
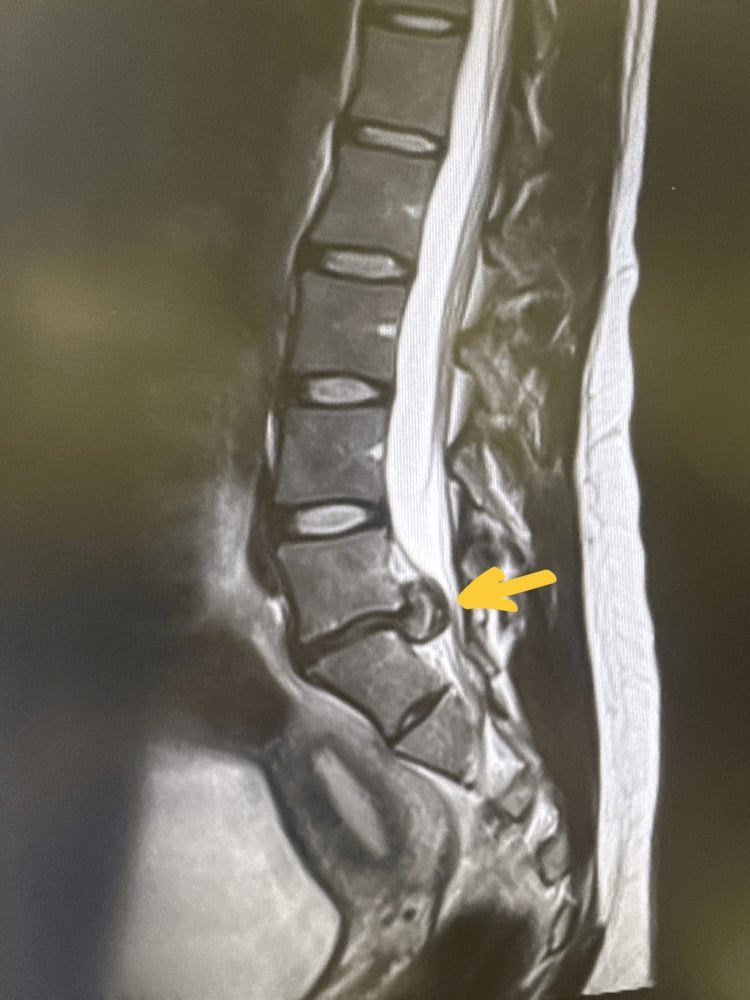
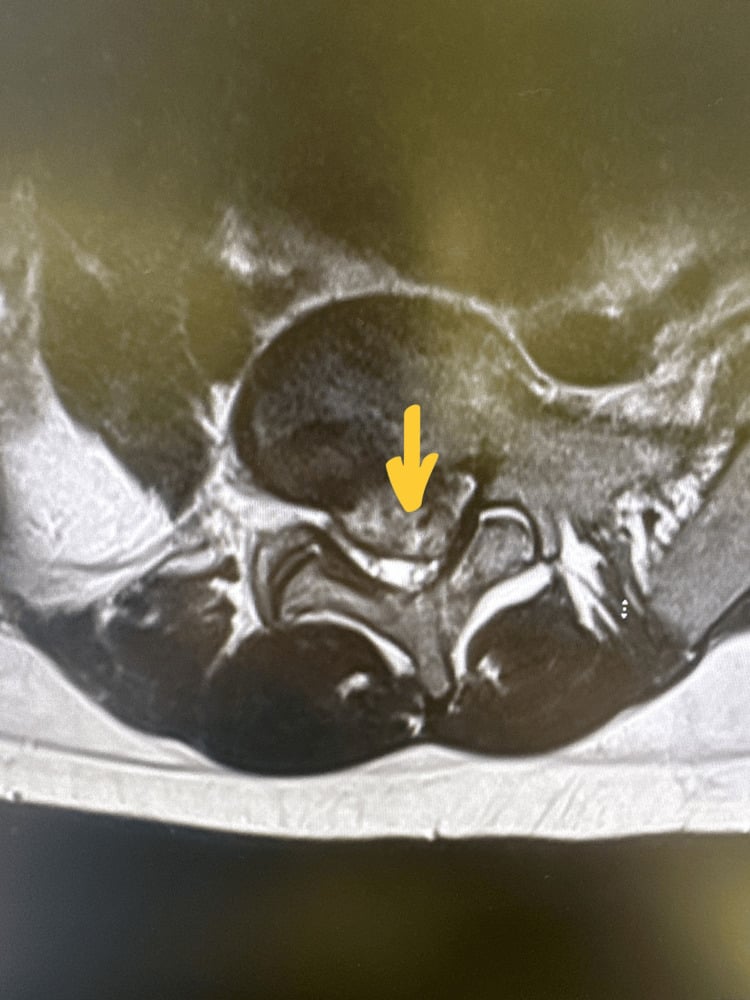
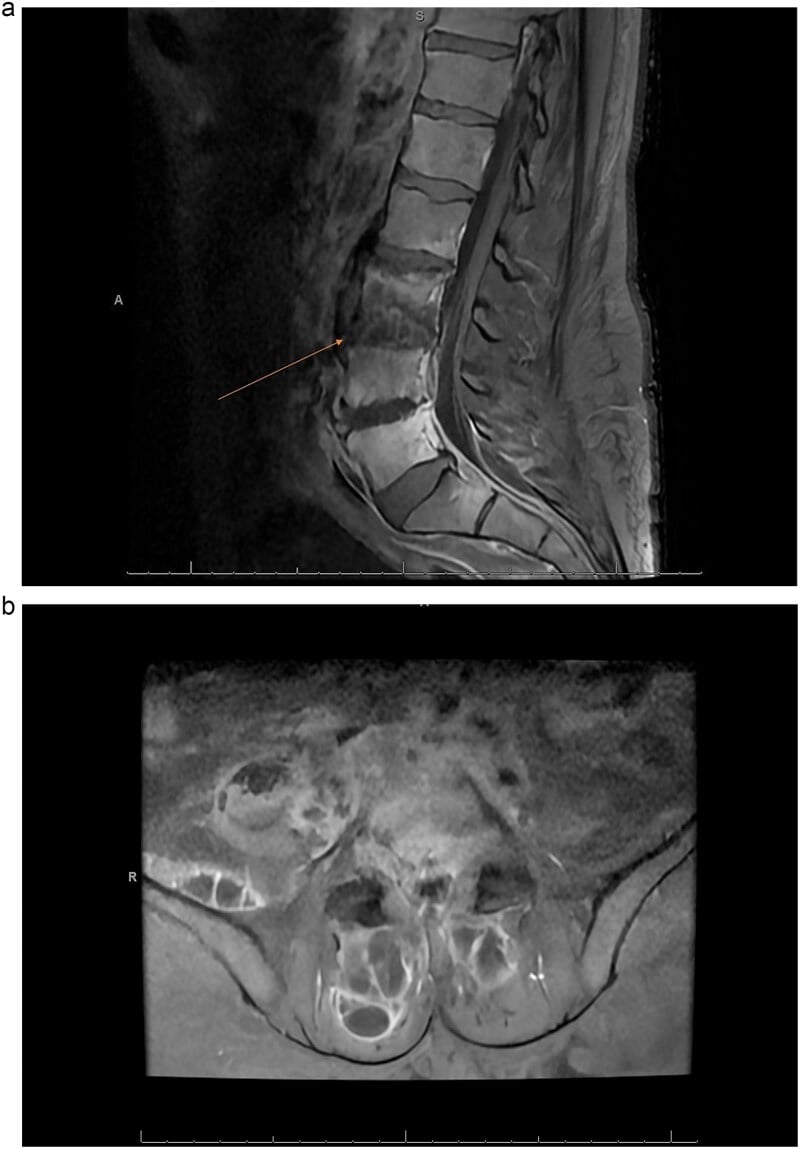
Cauda equina syndrome is the emergency in the table. A massive central disc herniation, or any other compression of the lumbosacral nerve roots, produces the saddle, bladder, bowel, sexual and bilateral leg features listed above. Urinary retention with overflow incontinence is the classic late sign, so do not wait for it, and never reassure away new urinary symptoms. It demands urgent MRI and emergency surgical decompression, because delay risks permanent bladder, bowel and sexual dysfunction and weakness.
Assessing suspected cauda equina. Beyond asking about saddle and bladder symptoms, the assessment is objective and staged. Examine perianal (S2-S4) sensation, resting anal tone and voluntary anal squeeze, and the bulbocavernosus / anal-wink reflex, and assess the bladder with a post-void residual on bladder ultrasound: a high residual supports a neurogenic, retentive bladder.
CES-I versus CES-R. Bladder status classifies the syndrome and drives prognosis. CES-incomplete (CES-I) is neurogenic urinary symptoms (altered sensation of voiding or fullness, hesitancy, poor stream) with preserved voluntary control, the better-prognosis group; CES-with-retention (CES-R) is painless urinary retention with overflow incontinence, an established neurogenic bladder, the worse-prognosis group. Outcome worsens with delay and CES-I does better than CES-R, so suspected CES needs an urgent (out-of-hours) MRI and, if confirmed, decompression as early as possible, before CES-I progresses to retention. Detailed operative management lives in the dedicated Cauda Equina topic.
Infection and fracture. Fever, intravenous drug use or immunosuppression plus back pain is not mechanical pain: CRP and MRI, not a plain film. Minor trauma in an osteoporotic or steroid-treated spine is a fracture red flag, not a sprain, and a plain film can miss the acute marrow change, so image when the history is trauma plus bone fragility, not as a routine for non-specific pain.
Yellow flags predict chronicity, not serious disease; do not confuse them with red flags. They are the psychosocial factors that predict chronic pain and disability: fear-avoidance beliefs, catastrophising, depression or anxiety, job dissatisfaction, low expectation of recovery, and reliance on passive coping. Identifying them early, with a tool such as STarT Back, lets you target more intensive, psychologically informed care to those at high risk, a core part of modern low-back-pain management.
Clinical Presentation
The three triage groups are separated by the history and the neurological examination:
- Non-specific mechanical (the large majority): activity-related paraspinal or axial pain, no identifiable pathoanatomical cause, no neurology
- Radicular (sciatica): dermatomal leg pain with or without paraesthesiae or weakness, a positive straight-leg-raise or femoral-stretch test, often a single nerve root
- Serious specific pathology: flagged by the red flags in the next section (cancer, infection, fracture, cauda equina, inflammatory)
History. Characterise the pain (onset; mechanical versus inflammatory versus night or rest pain) and screen red and yellow flags in every patient. Note the psychosocial context: work, mood, beliefs and the expectation of recovery.
Examination. A neurological examination of the lower limbs (power, reflexes, sensation, straight-leg-raise and femoral stretch), and in every patient the cauda equina questions: saddle sensation and bladder, bowel and sexual function.
Localising the radicular level. The root is named from the motor, reflex, sensory and provocation findings; the disc typically responsible is in the second column:
- Disc typically responsible
- L3/4
- Motor
- Knee extension (quadriceps)
- Reflex
- Knee (patellar)
- Sensation
- Medial leg to the medial malleolus
- Provocation
- Femoral stretch test
- Disc typically responsible
- L4/5
- Motor
- Great-toe and ankle dorsiflexion (EHL, tibialis anterior); hip abduction (gluteus medius, a Trendelenburg gait)
- Reflex
- No routine reflex
- Sensation
- Lateral leg, dorsum of the foot and first web space
- Provocation
- Straight-leg-raise
- Disc typically responsible
- L5/S1
- Motor
- Ankle plantarflexion and eversion (gastrocnemius, toe-walking)
- Reflex
- Ankle (Achilles)
- Sensation
- Posterolateral leg, lateral foot and sole
- Provocation
- Straight-leg-raise
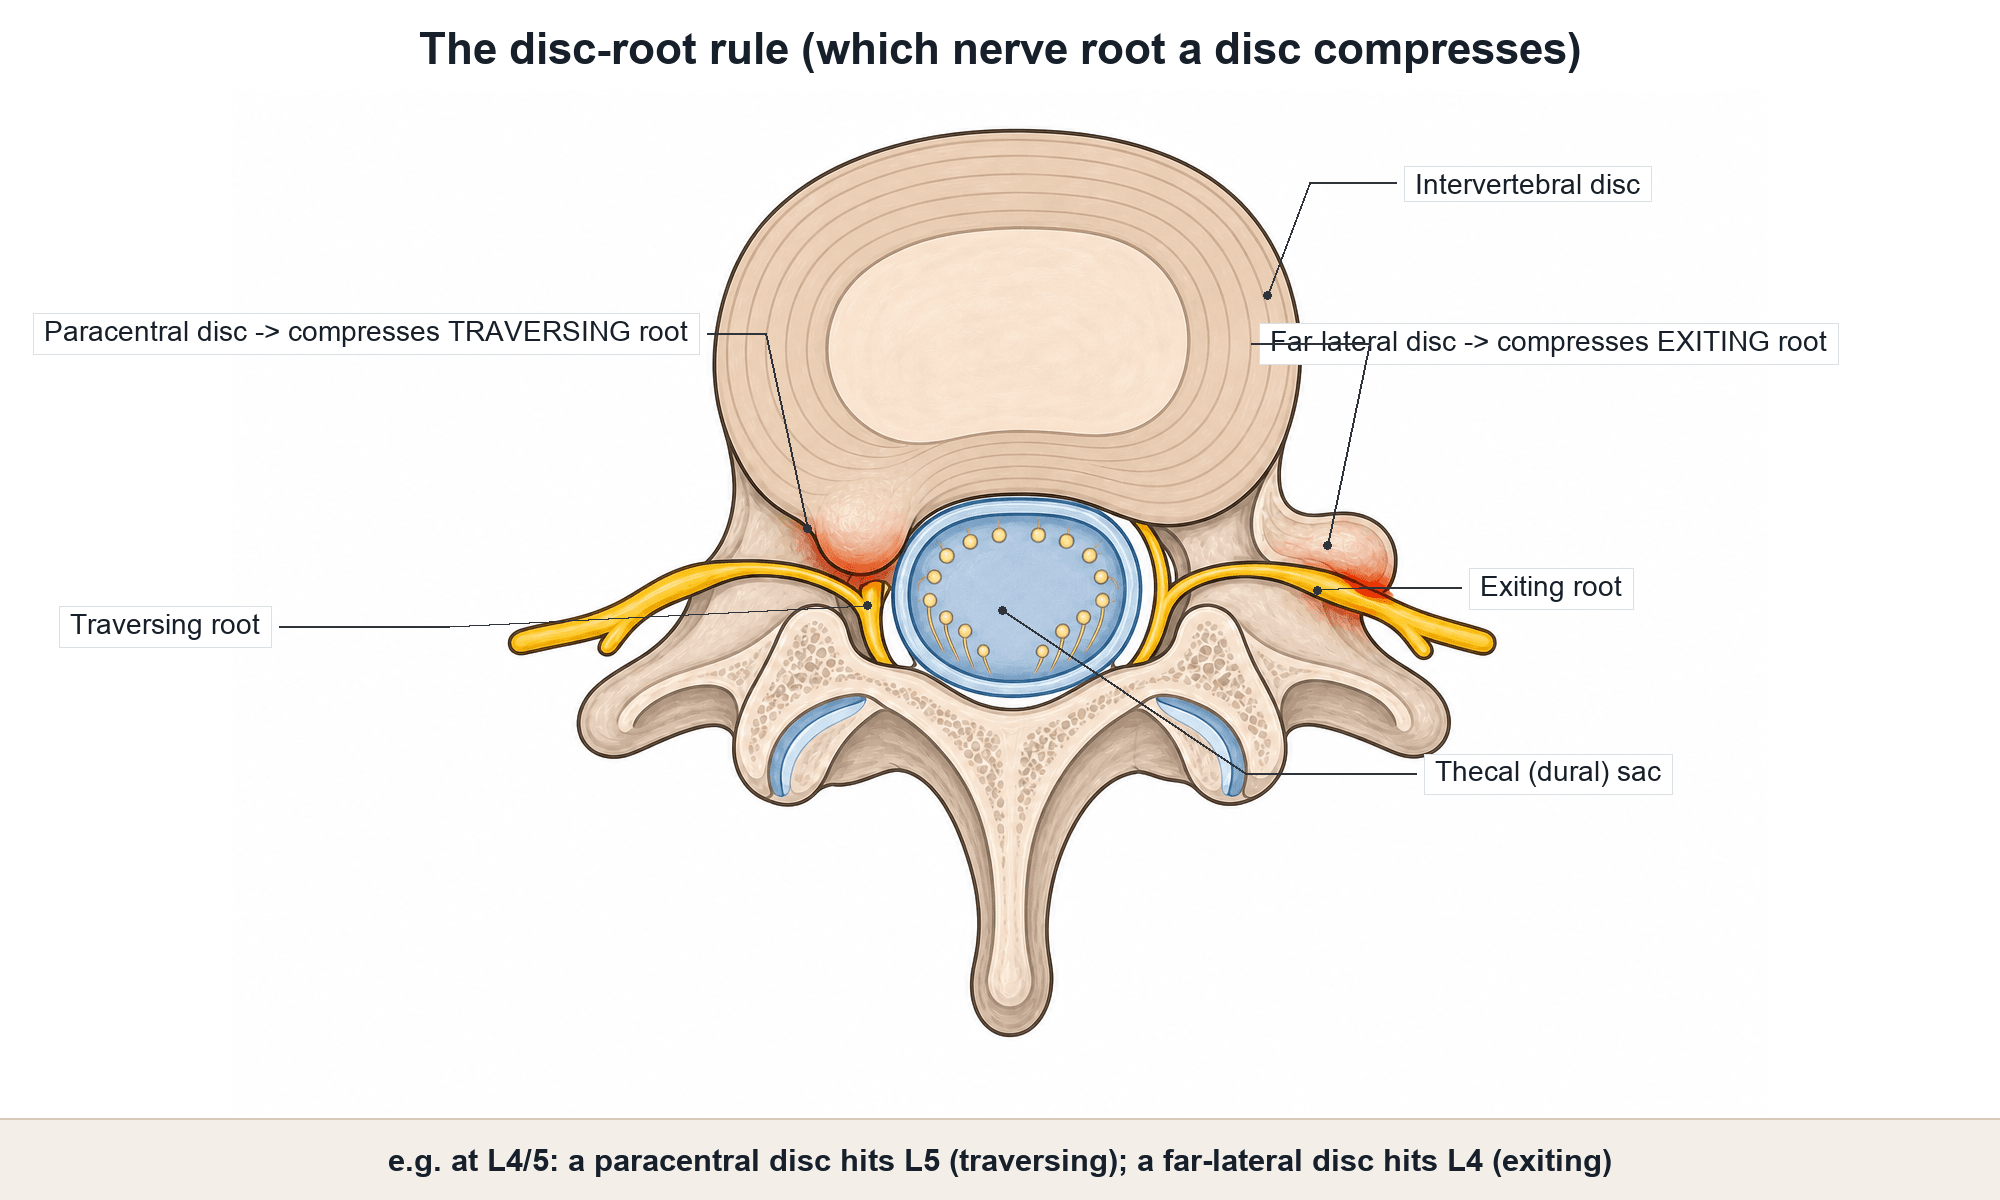
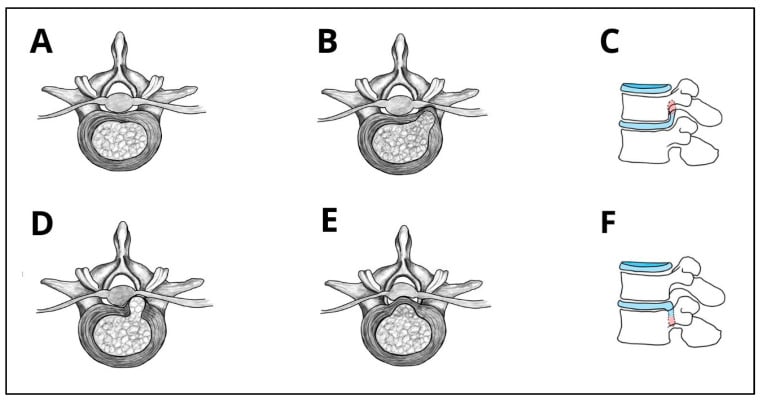
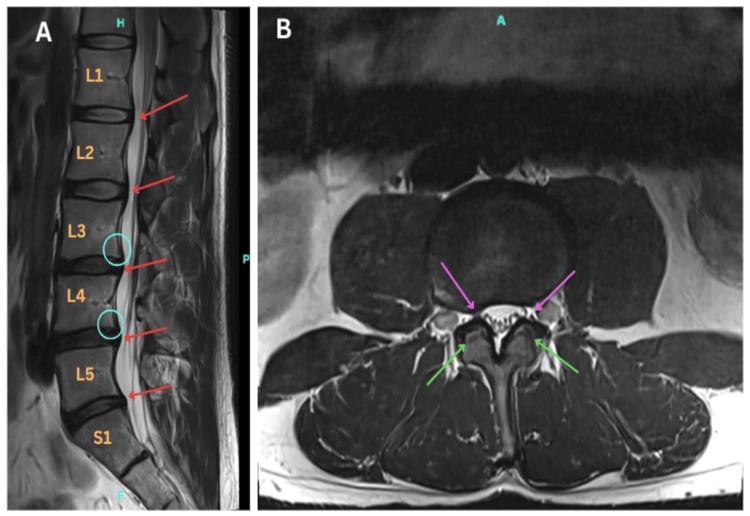
The disc-root rule. A posterolateral (paracentral) disc, the common pattern, protrudes into the lateral recess and compresses the traversing root: an L4/5 disc hits L5 and an L5/S1 disc hits S1. A far-lateral (foraminal) disc lies out in the foramen and compresses the exiting root, so a far-lateral L4/5 disc hits L4 instead. Match the level and direction of the herniation to the clinical root before you order a scan, and read the rule on the axial image, not the sagittal. Cranial or caudal migration and sequestration of a fragment change the surgical corridor, not the triage.
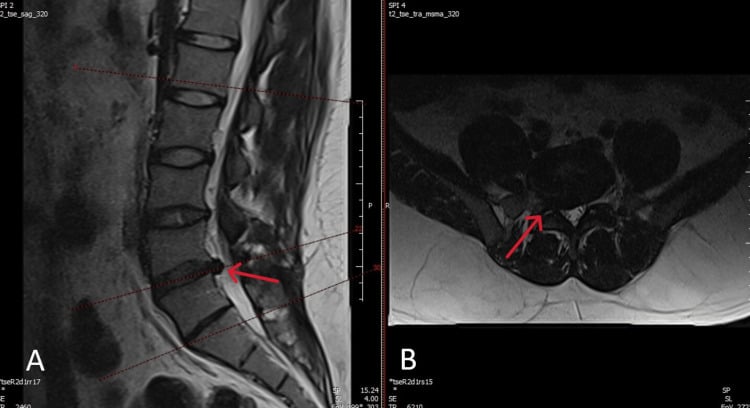
Provocation tests. The straight-leg-raise (Lasègue) reproduces radicular pain at about 30 to 70° and is sensitive but not specific for a lower lumbosacral root. The crossed SLR, raising the good leg to reproduce the affected side's pain, is highly specific for disc herniation. The femoral stretch test examines the upper (L2-L4) roots.
Investigations: mostly NOT imaging
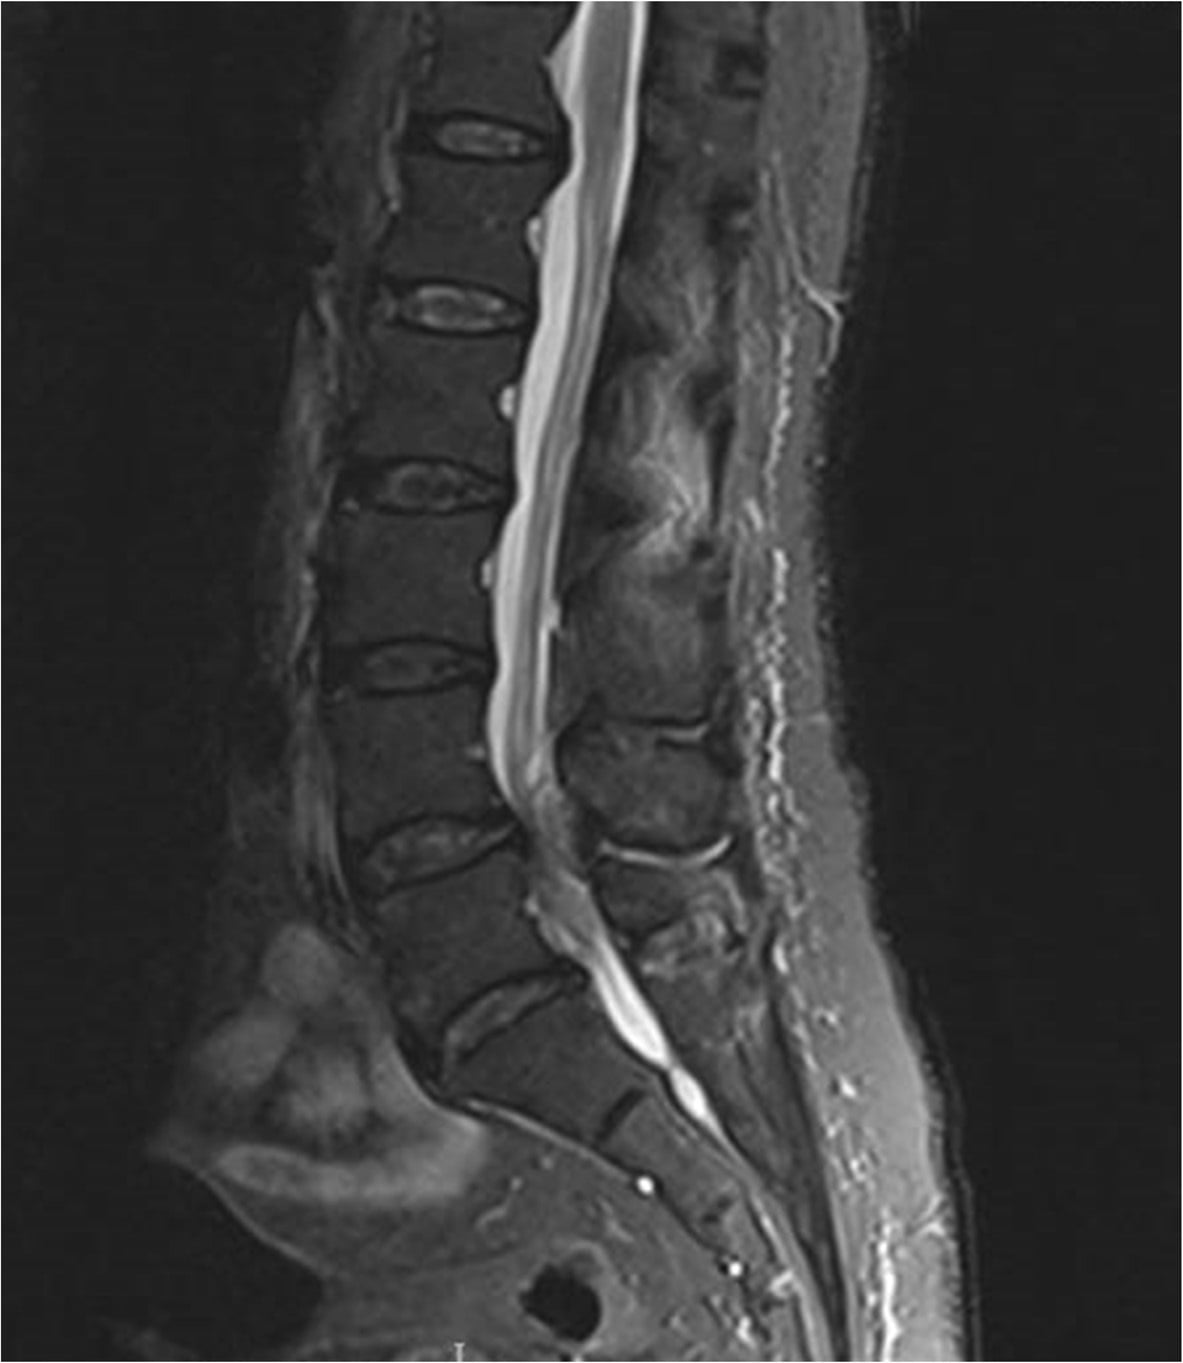
Image only when it will change management. For non-specific low back pain without red flags, routine imaging does not improve outcomes and is discouraged. The findings correlate poorly with symptoms, for the reasons given above, and imaging prompts incidental findings, anxiety and over-treatment; degeneration on MRI is not a surgical target. The overuse of imaging is a recognised, costly problem.
When to image. Three situations:
- Red flags, with urgent MRI for suspected cauda equina, infection or malignancy/cord compression
- A progressive neurological deficit
- Persistent radicular pain in a potential surgical candidate
Blood tests (CRP, ESR and the like) are directed by the suspected red-flag pathology.
Management
For non-specific low back pain, and the initial management of most radicular pain, treatment is non-operative and follows the biopsychosocial model. The pathway is triage, screen the flags and usually do not image, then the steps below, with intensity matched to the risk of chronicity.
Education, reassurance and staying active. Explain the favourable natural history and the value of remaining active; advice to stay active and avoid bed rest (bed rest is harmful) is the single most consistent recommendation. For acute and subacute pain the ACP guideline starts with non-pharmacological options: superficial heat, massage, acupuncture and spinal manipulation.
Analgesia. NSAIDs are first-line, at the lowest effective dose for the shortest time, with a short-term muscle relaxant in selected patients. Avoid routine opioids: the benefit is limited and the harms real, and the ACP allows them only if everything else fails and benefits outweigh risks. For chronic low back pain the second-line options are duloxetine or tramadol.
Exercise and psychological care. Exercise and physiotherapy for all. For persistent pain or yellow flags, CBT and multidisciplinary rehabilitation, and (per the ACP) mindfulness, motor-control exercise, yoga and tai chi; the mainstay of chronic low back pain is non-pharmacological.
Stratified care. Risk-stratified or stepped care (STarT Back) matches treatment intensity to prognosis, with timely review.
Refractory cases may be offered selected interventions: epidural steroid injection for refractory radicular pain, facet or radiofrequency procedures for proven mechanical pain, and, in carefully selected patients with a clear neural-compression target, surgery. Never surgery for non-specific pain: the overuse of opioids and surgery is a recognised harm.
Complications
The two big errors are opposite: missing serious pathology, and over-medicalising non-specific pain. Screen red flags and never miss cauda equina, and at the same time resist routine imaging, opioids and surgery for non-specific pain, keep the patient active and address the yellow flags.
- Complication
- Cauda equina → permanent bladder/bowel/sexual dysfunction
- Note
- Delayed decompression risks irreversible deficit - the never-miss emergency
- Complication
- Undiagnosed cancer/infection/fracture
- Note
- Red-flag screening exists precisely to catch these early
- Complication
- Transition to chronic, disabling pain
- Note
- Predicted by YELLOW flags (fear-avoidance, catastrophising, low recovery expectation)
- Complication
- Incidental findings → anxiety, over-treatment, cost
- Note
- Routine imaging of non-specific LBP worsens outcomes
- Complication
- Opioid dependence/harm; unnecessary surgery
- Note
- Opioid and surgery overuse are recognised, widespread harms
Viva practice
Viva practice
Practise clinical reasoning and management decisions out loud
“How do you approach a patient presenting with low back pain, and what red flags do you specifically screen for?”
“A patient has non-specific low back pain with no red flags. How would you manage them non-operatively, and what would you avoid?”
Exam cheat sheet
Triage
- Non-specific mechanical (~90-95%, no pathoanatomical cause)
- Radicular (sciatica/nerve root)
- Serious specific pathology (red flags)
Red flags
- Cancer (age over 50/under 20, prior cancer, weight loss, night pain), infection (fever, IVDU, immunosuppression)
- Fracture (trauma, osteoporosis/steroids), inflammatory (axial SpA features)
- CAUDA EQUINA = emergency: saddle anaesthesia, bladder/bowel/sexual dysfunction, bilateral leg signs → urgent MRI + decompression
Investigation
- Do NOT image routine non-specific LBP (low specificity, incidental findings, harms)
- Image for red flags, progressive deficit, or persistent radicular pain in a surgical candidate
- Screen yellow flags (psychosocial) - predict chronicity
Non-op management
- Education/reassurance + stay active (avoid bed rest)
- NSAIDs first-line; AVOID routine opioids; exercise/physio; CBT for persistent/yellow flags
- Stepped or risk-stratified care (STarT Back); avoid overuse of imaging/opioids/surgery
Evidence Base
Non-specific low back pain
- Non-specific low back pain is a leading global contributor to disability; guidelines endorse triage to identify the rare serious causes needing work-up or referral.
- Because it has no known pathoanatomical cause, treatment focuses on reducing pain and its consequences - education/reassurance, analgesics, non-pharmacological therapies and timely review; the course is often favourable.
- Two strategies - stepped care and simple risk-stratification; the overuse of imaging, opioids and surgery remains a widespread problem.
Low back pain
- LBP spans overlapping nociceptive, neuropathic, nociplastic and non-specific types; many lumbar structures contribute and imaging/diagnostic injections have low specificity.
- The biopsychosocial model frames LBP as a dynamic social-psychological-biological interaction and should guide interdisciplinary treatment.
- Therapy depends on pain classification - self-care and pharmacotherapy with non-pharmacological methods first; refractory cases have non-surgical and surgical options in selected patients.
Comparison of stratified primary care management for low back pain with current best practice (STarT Back): a randomised controlled trial
- RCT in ten English general practices: 1,573 assessed, 851 randomised 2:1 to stratified care (568) or non-stratified current best practice (283), with low, medium and high prognostic-risk pathways
- Roland-Morris disability favoured stratified care at 4 months (mean change 4.7 vs 3.0; between-group difference 1.81, 95% CI 1.06-2.57) and at 12 months (4.3 vs 3.3; difference 1.06, 95% CI 0.25-1.86)
- THOSE DIFFERENCES CORRESPOND TO EFFECT SIZES OF 0.32 AT 4 MONTHS AND 0.19 AT 12 MONTHS - statistically significant, but small, and the 12-month figure of about one Roland-Morris point sits below most published estimates of the minimal clinically important difference for that scale
- The economic case is the stronger half: 0.039 additional QALYs with lower back-pain-related costs (£240.01 vs £274.40) at 12 months
Noninvasive treatments for acute, subacute, and chronic low back pain: an ACP clinical practice guideline
- RECOMMENDATION 1 - acute or subacute low back pain usually improves regardless of treatment, so start with NON-pharmacological options: superficial heat (moderate-quality evidence), then massage, acupuncture or spinal manipulation (LOW-quality evidence). If drugs are wanted, NSAIDs or skeletal muscle relaxants (moderate-quality). Graded a STRONG recommendation
- RECOMMENDATION 2 - chronic low back pain: non-pharmacological first, with exercise, multidisciplinary rehabilitation, acupuncture and mindfulness-based stress reduction (moderate-quality), or tai chi, yoga, motor control exercise, progressive relaxation, EMG biofeedback, low-level laser, operant therapy, CBT or spinal manipulation (LOW-quality). Also graded STRONG
- RECOMMENDATION 3 - only where non-pharmacological treatment has failed: NSAIDs first-line, then tramadol or duloxetine second-line. Opioids only if all of the above have failed, only if benefit outweighs risk for that individual, and only after discussing known risks and realistic benefits - and this recommendation is graded WEAK
- Note the grading asymmetry: the treatments the guideline pushes hardest carry a STRONG recommendation, while the opioid option carries a WEAK one despite resting on moderate-quality evidence
The triage/treat-the-consequences framework and the imaging/opioid/surgery-overuse caution come from Maher et al. 2017 (DOI); the pain-classification and biopsychosocial framing from Knezevic et al. 2021 (DOI); the risk-stratified-care evidence from the STarT Back RCT, Hill et al. 2011 (DOI); and the non-pharmacological-first/opioid-last treatment hierarchy from the ACP guideline, Qaseem et al. 2017 (DOI). The specific red-flag/yellow-flag lists and the cauda-equina emergency are standard, well-established teaching. (See also our Lumbar Disc Herniation, Lumbar Radiculopathy, Lumbar Spinal Stenosis and Cauda Equina material.)