Low-Intensity Pulsed Ultrasound
- LOW-INTENSITY PULSED ULTRASOUND (LIPUS) is a NON-INVASIVE, low-risk device that delivers low-intensity pulsed acoustic energy to a fracture, typically applied for about 20 minutes DAILY by the patient at HOME, with the aim of promoting or accelerating bone healing; it has been used both in fresh fractures (to stimulate the stages of healing) and in delayed/non-unions.
- The proposed MECHANISM is MECHANOTRANSDUCTION - the micromechanical acoustic stimulus is sensed by bone-forming and other cells and stimulates the repair process at the MOLECULAR LEVEL across the stages of healing (modulating inflammation, chondrogenesis and endochondral ossification, gene/protein expression, angiogenesis and mineralisation).
- LIPUS is a LOW-RISK intervention: the only side effect reported is minor SKIN reactions in a small number of patients; it is non-invasive, used independently at HOME, and AVOIDS the disadvantages of surgery - re-hospitalisation, anaesthetic and operative complications, post-operative infection and thromboembolism - which is its main attraction.
- The EVIDENCE is the crux of the topic and must be framed honestly: while early and registry data and many case reports are encouraging, high-quality randomised trials and meta-analyses have shown INCONSISTENT or limited benefit for ACUTE/fresh fracture healing (leading some bodies to recommend against routine use for fresh fractures), whereas the rationale and interest are STRONGEST in DELAYED UNION and NON-UNION - where it offers a non-invasive option - with definitive non-inferiority trials versus surgery ongoing.
- For ESTABLISHED NON-UNION, SURGICAL revision remains the GOLD STANDARD treatment, but it carries the disadvantages of re-hospitalisation, anaesthesia and operative complications; LIPUS is positioned as a low-risk NON-INVASIVE alternative or adjunct that the patient can self-administer, and trials (e.g. non-inferiority studies of LIPUS versus surgery for non-union) aim to define whether it can substitute for surgery in selected cases.
- PRACTICALLY, LIPUS is reasonable to consider as a low-risk ADJUNCT in delayed/non-union and in high-risk fractures, set against an honest discussion of the inconsistent evidence and the fact that it is not a substitute for sound fracture management (stability, alignment, treating infection and addressing biological/host factors); non-union remains MULTIFACTORIAL and management must address the underlying cause, not rely on a device alone.
- “LIPUS = non-invasive, low-risk daily (~20 min) home-applied low-intensity pulsed ultrasound to promote bone healing. Proposed mechanism = MECHANOTRANSDUCTION stimulating repair at the molecular level.
- “Evidence (quote it): TRUST randomised 501 operatively-managed TIBIAL fractures against SHAM - no effect on function (SF-36 PCS difference 0.55, 95% CI -0.75 to 1.84, against a 3-5 point minimal important difference) or on time to radiographic healing (HR 1.07, CI 0.86-1.34); the BMJ Rapid Recommendation then advised STRONGLY AGAINST routine use in fresh fractures.
- “But say WHY non-union remains open: TRUST EXCLUDED fractures left with under 25% cortical contact and a gap over 1 cm - exactly the biologically compromised fracture a stimulus might help. Definitive non-inferiority-vs-surgery trials are ongoing and none has yet reported.
- “Surgical revision remains the GOLD STANDARD for established non-union; LIPUS is a low-risk non-invasive adjunct/alternative. Non-union is multifactorial - address the cause (stability, alignment, infection, host); don't rely on a device alone.
What It Is and How It Is Thought to Work
The device. LIPUS delivers low-intensity pulsed acoustic energy to a fracture to promote bone healing. The patient places a transducer over the fracture site with coupling gel and applies it once daily at home. It is painless.
The parameters. The standard device delivers 1.5 MHz ultrasound at a low intensity of about 30 mW/cm² (spatial-average temporal-average), as pulsed bursts (200 microseconds on, at a 1 kHz pulse-repetition frequency), for 20 minutes once daily. The "low-intensity" is the point: it is far below therapeutic or high-intensity ultrasound, and it is a non-thermal, mechanical stimulus rather than the tissue-heating of higher-intensity ultrasound.
The proposed mechanism. Mechanotransduction: the micromechanical stimulus is sensed by bone cells and stimulates repair at the molecular level across the stages of fracture healing, with proposed effects on inflammation, chondrogenesis and endochondral ossification, gene and protein expression, angiogenesis and mineralisation.
The risk profile. The only reported adverse effect is minor skin irritation under the transducer. Because it is non-invasive and self-administered, it avoids the re-hospitalisation, anaesthesia and operative complications of surgery, and that is its main appeal.
The regulatory history. The FDA approved LIPUS for accelerating the healing of fresh fractures in 1994 and for established non-unions in 2000. Both approvals rested on early positive randomised trials (accelerated tibial and distal-radius union, for example), which is why the device entered practice before the later high-quality trials tempered the fresh-fracture claim.
Place in Practice
Where the rationale is strongest. In delayed union and non-union, where LIPUS offers a non-invasive option. Case reports are encouraging, and non-inferiority trials comparing LIPUS with surgery are underway to define its role. In fresh fractures it should not be promoted as routinely accelerating ordinary fracture union.
Surgery remains the gold standard. Surgical revision is the standard treatment for an established non-union, with its known disadvantages of re-hospitalisation, anaesthesia and operative complications. LIPUS is best framed to the patient as a low-risk adjunct or, in selected cases, an alternative, with an honest account of the inconsistent evidence.
Non-union is multifactorial, and the device must not be used as a substitute for sound fracture management. Mechanical stability and alignment must be adequate, infection must be excluded and treated, and host and biological factors (smoking, diabetes, vascularity, metabolic bone disease) must be addressed. LIPUS supplements that work; it does not replace it.
The figures follow one distal radius fracture from injury, through fixation and delayed union, to union after LIPUS.
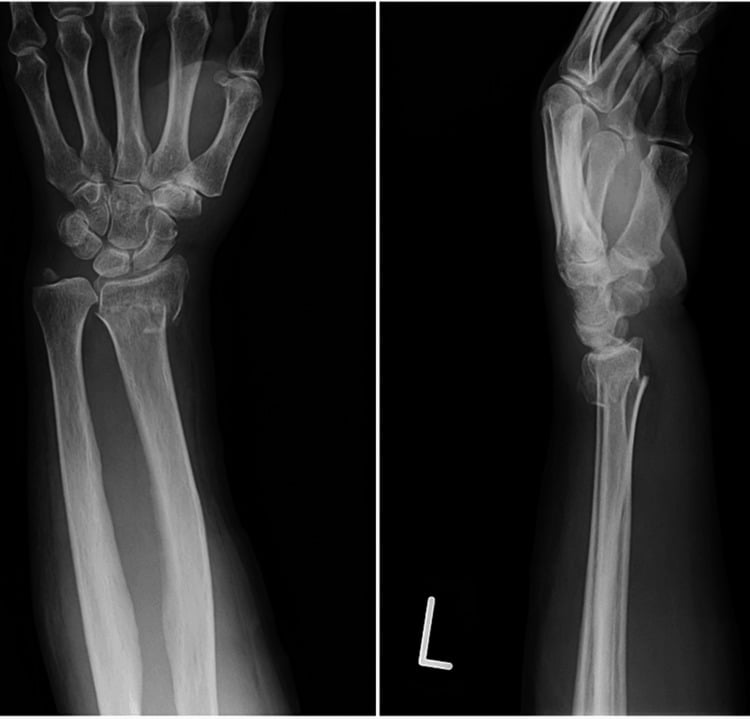
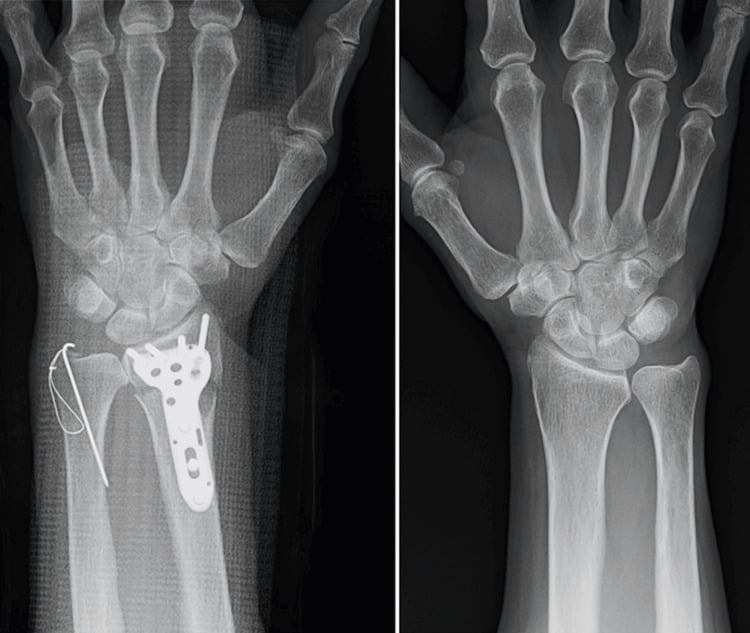
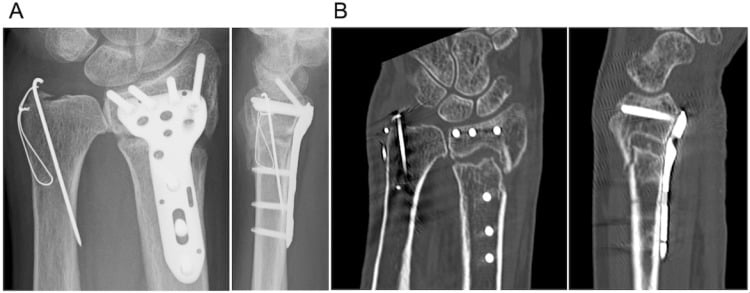
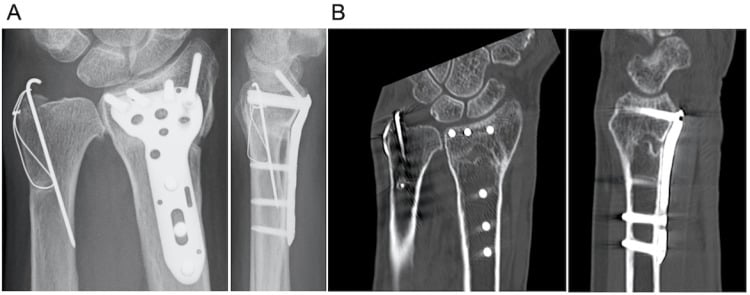
Who is a reasonable candidate. A motivated patient with a delayed union or a stable, well-aligned, uninfected non-union, in whom the mechanical work has been done (or is not needed), who understands the evidence and prefers to defer surgery, or in whom surgery carries disproportionate risk.
Who is not.
- An unstable or malaligned non-union needing mechanical correction
- An infected non-union: eradicate the infection first
- A fresh fracture, where the guideline recommendation against routine use applies directly
The counselling sentence. "The best trials show no benefit in fresh fractures; in non-union the honest answer is that we do not have the trial yet, the risk is essentially nil, the cost is time and money, and surgery remains the proven treatment."
Running a course. Treatment continues daily until radiographic progression is confirmed. No trial defines when to abandon it, so there is no validated stop-point; the practical rule is to review the films on the usual non-union schedule and stop if there is no progression between successive reviews.
Compliance is the weak link. Even inside TRUST, with motivated, consented patients, compliance was only moderate. In routine practice, assume adherence is imperfect and build it into the review conversation rather than discovering it at six months.
Documentation. The device is only ever an adjunct, never a substitute, so the record should show what it is an adjunct to:
- The indication: delayed union or established non-union
- The fracture's stability and alignment
- That infection has been excluded
- The host factors being addressed
Cost and funding. The BMJ Rapid Recommendation panel flagged routine use as an inefficient use of resources and raised de-implementation as a quality-improvement measure. Where funding is contested, the Poolman guideline is the document to cite.
LIPUS is safe, cheap in effort, and biologically plausible - and the best randomised evidence in fresh fractures is null, with a strong guideline recommendation against routine use. In established non-union the pivotal comparison with surgery has not yet reported, so it remains a reasonable low-risk option in carefully selected patients after stability, alignment, infection and host factors have been addressed - never instead of addressing them.
The topics this sits between are worth reading together. The biology it claims to accelerate is set out in fracture healing, and the problem it is offered for in non-union management, with the commonest site in tibial non-union. The other non-invasive stimulus with a comparable evidence problem is electrical stimulation. The interventions that do have an effect on union - correcting the mechanics and the biology - are covered under bone grafts and, for the single most modifiable host factor, smoking cessation.
Mnemonics & Memory Aids
LIPUS
Hook:LIPUS: Low-intensity pulsed ultrasound, Ineffective in fresh # (TRUST), Promotes repair (mechanotransduction), Use in delayed/non-Union (TRUST excluded them), Surgery still gold standard.
TRUST
Hook:TRUST: Tibial, Randomised sham-controlled, Unaffected outcomes, Strict exclusions, Therefore silent on the compromised fracture.
ADJUNCT
Hook:ADJUNCT: Address the cause, Daily 20 minutes, Justified in non-union, Union endpoint, Not a substitute, Counsel honestly, Trials ongoing.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A patient with a tibial non-union asks about low-intensity pulsed ultrasound. How do you counsel them?”
“Your hospital's procurement committee asks whether it should keep funding LIPUS devices for the fracture clinic. What is your evidence-based answer?”
What it is
- Low-intensity pulsed ultrasound - non-invasive device
- ~20 min daily, self-applied at home
- Used in fresh fractures and delayed/non-unions
Mechanism & risk
- Proposed mechanotransduction drives repair at the molecular level (across healing stages)
- Low-risk: minor skin reactions the only reported side effect
- Avoids re-hospitalisation/anaesthesia/operative complications
Evidence
- TRUST (n=501, sham-controlled): no effect on function (SF-36 diff 0.55, CI -0.75 to 1.84) or healing (HR 1.07)
- BMJ Rapid Recommendation: strong recommendation AGAINST routine use in fractures and osteotomies
- Rationale strongest in delayed union/non-union - because TRUST excluded fractures with poor contact and a gap
- Non-inferiority trials vs surgery ongoing (non-union 2-10%, up to 30% with risk factors)
Place in practice
- Surgical revision = gold standard for established non-union
- LIPUS = low-risk non-invasive adjunct/alternative
- Non-union is multifactorial - address stability/alignment/infection/host; not a substitute
The Landmark Evidence and the Bench-to-Bedside Gap
The overall picture. High-quality randomised trials and meta-analyses show inconsistent or limited benefit for acute fracture healing, so LIPUS is not established as routinely beneficial for fresh fractures. Systematic reviews of the randomised trials find no effect on functional recovery and only low-quality or inconsistent evidence for radiographic surrogates. The earlier small positive trials were at higher risk of bias.
The landmark trial. TRUST (Busse et al, BMJ 2016) randomised 501 patients (250 LIPUS, 251 sham) with operatively managed tibial fractures across 43 North American trauma centres. It was blinded and sham-controlled, with follow-up for one year. LIPUS was no better than sham:
- Function. SF-36 physical component summary mean difference 0.55 (95% CI -0.75 to 1.84, p=0.41), against a minimal important difference of 3 to 5 points, so the confidence interval excludes any clinically important benefit
- Time to radiographic healing. Hazard ratio 1.07 (95% CI 0.86 to 1.34, p=0.55)
- Safety. No difference
- Compliance. Only moderate: 73 percent administered at least half the recommended treatments
A linked BMJ Rapid Recommendation (2017) then made a strong recommendation against routine LIPUS for fresh fractures.
What TRUST excluded. Of 3,105 patients screened, only 599 were eligible. The exclusions included pathological, segmental and bilateral fractures and, critically, any fracture with less than 25 percent cortical contact and more than a 1 cm gap after fixation. That is precisely the biologically compromised fracture in which a healing stimulus would be expected to matter most. TRUST is therefore a definitive answer for the ordinary, well-reduced, well-fixed tibia, and silent on the population the non-union argument is actually about.
The bench-to-bedside gap. The in-vitro and animal data are robust, showing accelerated endochondral ossification and upregulated osteogenic genes, yet the high-quality human trials are neutral. The explanations offered:
- Surrogate (radiographic) versus patient-important (functional) outcomes
- Small-trial and publication bias
- Coupling, dosing and compliance issues
- A ceiling effect, since ordinary fractures heal well anyway
Whether the biology helps in non-union, where there is more to gain, remains the open question the ongoing trials address.
Evidence & Key Studies
Re-evaluation of low intensity pulsed ultrasound in treatment of tibial fractures (TRUST): randomized clinical trial
- Concealed, randomised, blinded, sham-controlled trial of 501 patients (250 LIPUS, 251 sham) with operatively managed tibial fractures amenable to intramedullary nailing, across 43 North American academic trauma centres, enrolled 2008 to 2012 and followed for one year.
- No effect on function: SF-36 physical component summary mean difference 0.55 (95% CI -0.75 to 1.84, p=0.41) against a minimal important difference of 3 to 5 points, with no difference in other functional measures. No effect on time to radiographic healing (hazard ratio 1.07, 95% CI 0.86 to 1.34, p=0.55). Safety outcomes did not differ.
- Compliance was moderate - 73 percent administered at least half the recommended treatments. Of 3,105 patients screened only 599 were eligible: exclusions included pathological, segmental and bilateral fractures and, importantly, any fracture left with under 25 percent cortical contact and a gap over 1 cm after fixation. The trial therefore answers the question for the well-reduced, well-fixed tibia and does not address the biologically compromised fracture.
LIPUS versus surgery for non-union (PiNGUin) - non-inferiority RCT protocol
- Non-unions (fractures not healed after at least 6 months) occur in 2-10% of all fractures and up to 30% of patients with certain risk factors, with high treatment costs, pain and loss of function; surgical revision is the current gold standard but carries re-hospitalisation, secondary disease and operative side effects.
- LIPUS is a low-risk procedure (skin reactions the only side effect in a very small number of patients) that patients can use independently at home, eliminating repeated hospital visits.
- The trial is designed to test whether daily LIPUS (20 minutes for 200 days) is non-inferior to surgical intervention for healing of upper- or lower-extremity non-unions - reflecting that LIPUS is a potential non-invasive alternative to surgery pending definitive evidence.
LIPUS for paediatric fracture non-union - a case report
- LIPUS is a conservative option used both in fresh fractures (to stimulate the stages of healing) and in non-unions, working by promoting repair at the molecular level.
- A child's distal-third humeral shaft atrophic non-union treated with LIPUS showed encouraging signs of union at 3 months and successful union at 6 months.
- While LIPUS is well studied in adult non-unions, evidence in children is limited; this case supports further trials of LIPUS for paediatric non-union (single case report - low-level evidence).
LIPUS for bone healing: systematic review of randomized controlled trials
- 26 randomised controlled trials (median sample size 30, range 8-501) of LIPUS versus sham or no device for any fracture or osteotomy, searched to November 2016 with GRADE assessment.
- The most trustworthy evidence came from four low-risk-of-bias trials in tibia or clavicle fractures: LIPUS did not reduce time to return to work, pain, or subsequent operations, and probably has no effect on radiographic healing.
- Concludes that in fresh fractures LIPUS does not improve patient-important outcomes; applicability to other fractures and osteotomies is described as open to debate.
LIPUS for bone healing: a clinical practice guideline (BMJ Rapid Recommendation)
- International guideline panel, working from the linked Schandelmaier review, issued a STRONG recommendation against the routine use of LIPUS for patients with fractures or osteotomies - in adults and children.
- Moderate-to-high certainty that LIPUS provides no meaningful benefit on return to work, full weight-bearing, pain, subsequent operations, or radiographic healing in the trustworthy trials.
- The panel flagged cost and resource inefficiency and suggested funders consider de-implementation as a quality-improvement initiative.
The epidemiology of non-union (2-10% of fractures, up to 30% with risk factors), the status of surgical revision as the current gold standard with its disadvantages, the low-risk home-use profile of LIPUS (skin reactions the only side effect), and the framing of LIPUS as a potential non-invasive alternative whose non-inferiority to surgery is being tested come from the cited Steinhausen (PiNGUin) trial protocol; the conservative use of LIPUS in fresh fractures and non-unions and an example of successful union in paediatric non-union from the cited Basa case report. The proposed mechanotransduction mechanism, the inconsistent high-quality-trial evidence for fresh fractures, and the principle that non-union is multifactorial (requiring attention to stability/alignment/infection/host factors) are standard, well-established teaching. The trial figures
- the sample size, the SF-36 and radiographic-healing effect estimates with their confidence intervals, the compliance rate and the eligibility criteria - come from TRUST, which studied operatively managed tibial fractures only and explicitly excluded those left with poor cortical contact and a residual gap. The PiNGUin citation is a published protocol, so it reports no results, and the paediatric citation is a single case report. No completed randomised trial compares LIPUS with surgery for established non-union, no trial establishes a treatment duration or a point at which to abandon it, and no cohort gives a union rate attributable to LIPUS in non-union - so none is quoted here. The pooled-trial verdict and the strong guideline recommendation against routine use come from the cited Schandelmaier review (26 trials) and Poolman BMJ Rapid Recommendation respectively.