A calcified or ossified fragment lying free within the joint — the differential runs from a sesamoid you should have ignored to a synovial sarcoma you must not miss
- A fragment is only 'loose' if it moves. Compare the lateral and skyline with any previous film, or repeat in a different degree of flexion.
- Purely chondral loose bodies are radiographically invisible — a normal radiograph in a locking knee does not exclude a loose body.
- Always hunt the donor site: a defect on the lateral aspect of the medial femoral condyle (classic OCD), the patellar median ridge or lateral trochlea (post-dislocation osteochondral fracture), or the femoral condyle articular surface (SONK/AVN).
- Multiple bodies of uniform size in a young adult with a boggy effusion = primary synovial chondromatosis. Multiple bodies of varied size in an osteoarthritic knee = secondary chondromatosis.
- Rice bodies in inflammatory arthritis and tuberculous synovitis are fibrinous, not calcified — they never appear on plain film.
- A locked knee with a mechanical block to extension is a surgical problem regardless of what the radiograph shows.
- “The fabella is in the lateral head of gastrocnemius, posterolateral, and is present in roughly 20 per cent of knees bilaterally — never intra-articular.
- “Segond fracture is a lateral capsular avulsion, not a loose body, and means ACL rupture until proven otherwise.
- “Neuropathic (Charcot) knee: gross debris and disorganisation out of proportion to pain — ask about diabetes, syphilis, syringomyelia.
- “Say 'well-corticated' for a chronic body and 'sharp non-corticated margin' for an acute osteochondral fracture — the examiner is listening for it.
Recognising the Pattern
Definition. An intra-articular loose body is a fragment of bone, cartilage, or osteocartilage lying free (or pedunculated) within the synovial cavity, capable of moving between recesses and of causing mechanical symptoms. Three things have to be true of a fragment before it earns the name.
It is inside the capsule. On the lateral view the suprapatellar pouch, the intercondylar notch and the posterior recesses are the resting places. A posterolateral ossicle superimposed behind the lateral femoral condyle and lying within the gastrocnemius tendon shadow is almost always the fabella: a sesamoid in the lateral head of gastrocnemius, outside the capsule, present in about one in five knees and often bilateral, whose position relative to the condyle is constant on every film. The cyamella, in popliteus, is the rarer cousin.
It moves. Compare with any prior radiograph, or repeat the lateral in a different degree of flexion. A change in position between studies is the single most specific plain-film sign. If the position is fixed and typical you have finished: this is a sesamoid or an osteophyte and needs nothing further.
It is not attached. Osteophytes are contiguous with the joint margin, so look for a stalk of cortex. A fragment fully surrounded by lucency on two orthogonal views is free.
Saying it out loud. A report that names the fragment, the donor bed and the next test:
"This is an AP and lateral radiograph of a skeletally immature left knee. There is a well-corticated ovoid ossific fragment measuring approximately 12 millimetres lying in the intercondylar notch. There is a corresponding lucent defect with a sclerotic base on the lateral aspect of the medial femoral condyle on the tunnel view. Joint space is preserved and there is a moderate effusion. The appearances are those of a detached osteochondritis dissecans fragment — a loose body — and I would confirm with MRI to assess the donor bed, the stability of any remaining lesion, and to look for further chondral bodies."
Mimics. The false positives, and what gives each away:
- Why it is not a loose body
- Constant posterolateral position, in gastrocnemius, extracapsular, often bilateral
- Why it is not a loose body
- Sesamoid within popliteus tendon, lateral, constant
- Why it is not a loose body
- Contiguous with joint margin; look for the cortical bridge
- Why it is not a loose body
- Superolateral, smooth sclerotic margins, no matching defect, usually bilateral
- Why it is not a loose body
- Lateral tibial rim avulsion, extra-articular capsular, means ACL tear
- Why it is not a loose body
- Ossification at the femoral MCL origin, teardrop-shaped, medial, attached
- Why it is not a loose body
- Repeat the film; not projected within the joint on two views
- Why it is not a loose body
- Linear, in the meniscal or hyaline cartilage position, does not migrate
Next Investigation
Plain radiographs, always first. Request four views:
- AP and lateral
- Skyline, for post-dislocation fragments
- Tunnel (Rosenberg or intercondylar), essential for OCD of the lateral aspect of the medial femoral condyle
The films confirm ossification, position, cortication, joint space and the presence of a donor bed. They change management by identifying secondary osteoarthritis, in which case symptomatic bodies are treated arthroscopically or the joint is managed as OA. What they cannot do is exclude a loose body: around a third to a half are purely cartilaginous and radiolucent.
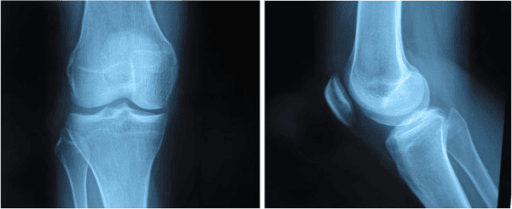
When to stop. No further imaging is needed when the fragment is a fabella, a cyamella, a bipartite patella or an attached marginal osteophyte in an asymptomatic knee, or when established osteoarthritis with multiple bodies is evident and management is non-operative regardless. Reassure and stop.
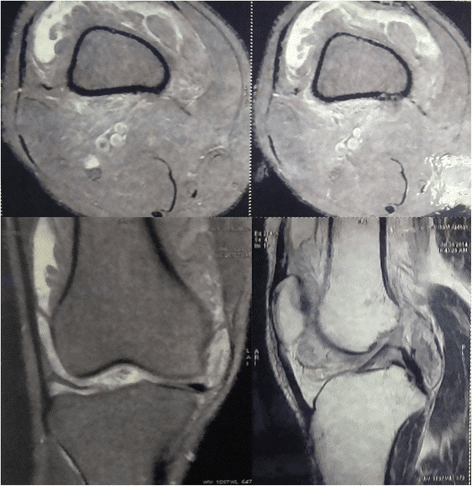
MRI, the workhorse. Indicated for any suspected chondral-only body, a locked knee with normal radiographs, suspected OCD staging, or a soft tissue mass. It shows the donor bed, the signs of an unstable OCD fragment listed in the differential above, meniscal tears, ligament injury and the haemosiderin blooming of PVNS. It changes management by distinguishing a stable OCD lesion (non-operative, restricted loading) from an unstable or detached one (fixation, or removal plus marrow stimulation or graft).
CT and CT arthrogram. Best for characterising ossified bodies, counting them before arthroscopy, and mapping the donor bed geometry when MRI is contraindicated or metal artefact degrades it. A CT arthrogram outlines radiolucent chondral bodies. In synovial chondromatosis it determines how many bodies there are and how far into the posterior recesses they extend, which decides whether an open or posterior portal approach is needed.
Joint aspiration. Mandatory if infection is possible. Fat globules in a haemarthrosis indicate an intra-articular fracture, and crystals confirm gout or pseudogout as an alternative cause of a painful effusion with calcification.
Staged biopsy, never incidental. A soft tissue mass goes to a sarcoma unit, and the biopsy is taken through a planned incision, not the arthroscopy portal. An unplanned arthroscopy of a synovial sarcoma contaminates all portals and compartments and may convert a limb-salvage case into an amputation.
Arthroscopy. Both diagnostic and therapeutic for the locked knee, mechanical symptoms, or bodies confirmed on imaging. In primary synovial chondromatosis, phase the disease at arthroscopy rather than applying one rule (Milgram): in phase 3, free bodies with a quiet synovium, removal alone may suffice, while in phases 1 and 2 a synovectomy is reasonable but does not guarantee against recurrence, because the cartilaginous lesions that regrow may already lie outside the synovium. Document all recesses, including posteromedial and posterolateral.
The Differential
The list runs from a sesamoid to a sarcoma. The table sorts it with the diagnoses a miss would cost most at the top; the next section is how to walk it against the film in front of you.
- Typical age / setting
- 15-40, juxta-articular, deep to fascia
- Discriminating feature
- Soft tissue mass with faint punctate/eccentric calcification and possible bone erosion — not discrete chondroid ring-and-arc bodies within the capsule
- What confirms it
- MRI showing heterogeneous 'triple sign' mass with fluid levels, then planned core biopsy; SS18 (SYT) rearrangement
- Typical age / setting
- Teenager/young adult, acute injury, haemarthrosis with fat globules
- Discriminating feature
- Sharp NON-corticated fragment margin plus a matching defect on the patellar median ridge or lateral femoral condyle on the skyline view
- What confirms it
- Skyline radiograph and MRI showing medial patellofemoral ligament disruption and lateral condyle bone bruise
- Typical age / setting
- 20-50, insidious recurrent haemarthrosis
- Discriminating feature
- Nodular synovial mass causing pressure erosions with preserved joint space; NO calcification on plain film
- What confirms it
- MRI blooming artefact on gradient echo from haemosiderin; synovial biopsy
- Typical age / setting
- Any age; TB in immunocompromised or endemic exposure
- Discriminating feature
- Systemic upset, juxta-articular osteopenia and marginal erosions with late joint space loss (Phemister triad in TB); 'rice bodies' are non-calcified
- What confirms it
- Joint aspiration with cell count, Gram stain, culture, AFB/PCR
- Typical age / setting
- 10-20, male, sporting; lateral aspect of medial femoral condyle in about 70 per cent
- Discriminating feature
- Crescentic subchondral lucency with sclerotic base and a fragment of matching size and shape — the donor bed is visible
- What confirms it
- Tunnel view plus MRI: high-signal line behind fragment, cysts greater than 5 mm and a breached cartilage cap indicate instability
- Typical age / setting
- Over 50, established OA
- Discriminating feature
- Multiple bodies of VARYING size and irregular shape with joint space narrowing, subchondral sclerosis and other osteophytes present
- What confirms it
- Weight-bearing AP and lateral; no further imaging usually required
- Typical age / setting
- 30-50, male predominance, monoarticular
- Discriminating feature
- Multiple bodies of UNIFORM size with ring-and-arc chondroid calcification and a relatively preserved joint space early on
- What confirms it
- MRI or CT showing multiple intracapsular bodies plus synovial proliferation; histology confirms cartilaginous metaplasia
- Typical age / setting
- 20-40, twisting injury, true locking
- Discriminating feature
- Radiograph often normal — the 'loose body' is soft tissue; mechanical block to full extension
- What confirms it
- MRI: double PCL sign or absent bow-tie on sagittals; arthroscopy
- Typical age / setting
- Over 60, female, abrupt medial pain
- Discriminating feature
- Subchondral lucency and flattening of the medial femoral condyle WEIGHT-BEARING zone (not the classic OCD lateral-of-medial-condyle site)
- What confirms it
- MRI showing subchondral fracture line with surrounding marrow oedema
- Typical age / setting
- 20-50, risk factors present
- Discriminating feature
- Serpiginous double-line sclerotic rim, often bilateral and multifocal including hip and shoulder
- What confirms it
- MRI both knees and hips; screen for the underlying cause
- Typical age / setting
- Diabetes, syringomyelia, tabes
- Discriminating feature
- Gross fragmentation, debris and disorganisation with dense sclerosis and painlessness disproportionate to the appearances
- What confirms it
- Radiographs plus neurological assessment, HbA1c, syphilis serology, cervical MRI if syrinx suspected
- Typical age / setting
- 40-60, chronic painless effusion
- Discriminating feature
- Frond-like synovial mass following FAT signal on all MRI sequences — no calcification at all
- What confirms it
- MRI with fat suppression showing signal drop-out
- Typical age / setting
- 8-14 skeletally immature, or adult hyperextension
- Discriminating feature
- Fragment sits at the anterior intercondylar eminence with a matching bed — Meyers and McKeever type II/III
- What confirms it
- Lateral radiograph and CT/MRI for displacement and entrapped meniscus
- Typical age / setting
- Any age, prior surgery
- Discriminating feature
- Metallic density or manufactured geometry (screw thread, bioabsorbable tack tunnel)
- What confirms it
- Compare with immediate post-operative films; CT if metal artefact permits
Narrowing It Down
Once the fragment is real, six questions take it to a diagnosis. Set the differential by age before interpreting the fragment itself.
How old is the patient? Under 20 with a single body: osteochondritis dissecans or an acute osteochondral fracture. Between those ages, multiple bodies mean primary synovial chondromatosis (30-50) or, if there is no calcification, PVNS (20-50). Over 55 with multiple irregular bodies and joint space loss: osteoarthritis or SONK. Age alone removes half the list.
Solitary or multiple, and are they the same size? Count the bodies and compare their sizes and internal matrix with one another. A solitary body points to OCD, osteochondral fracture or ACL avulsion. Multiple bodies of uniform size with a chondroid ring-and-arc pattern is primary synovial chondromatosis; multiple bodies of varying size in a degenerate joint is secondary chondromatosis. This single question separates the two chondromatoses.
Where is the donor defect within the bone? Find the bed the fragment came from, and name its exact location rather than the bone. The lateral aspect of the medial femoral condyle, non-weight-bearing beside the notch, is classic OCD; the weight-bearing zone of the medial femoral condyle in an elderly patient is SONK; the patellar median ridge or lateral trochlea is a post-dislocation osteochondral fracture; the anterior intercondylar eminence is an ACL avulsion. No defect at all means the origin is synovial. Reporting the fragment without describing where it came from loses the diagnosis, and the tunnel view for OCD and the skyline for a post-dislocation fracture are both needed before you say the origin is unknown.
Is the fragment corticated or sharp? Inspect the margins and ask whether the fragment would jigsaw back into a matching bed. Well corticated with smooth rounded margins means chronic: it has been free long enough to be nourished by synovial fluid, remodel, and possibly grow. A sharp non-corticated margin with a matching bed means an acute fracture, and changes the plan to urgent fixation if the fragment is large and the bed is fresh. In children after patellar dislocation nearly half of these fractures are invisible on the plain film (44 per cent radiograph-negative in Seeley's series), so a normal radiograph does not settle it.
Is there a soft tissue mass or a systemic feature? Look beyond the fragment at the soft tissues, and check temperature, CRP and the history of effusions. A juxta-articular soft-tissue mass with faint punctate calcification and bone erosion in a 15-40 year old is synovial sarcoma until proven otherwise and demands a sarcoma work-up before any arthroscopy; synovial chondromatosis gives discrete ring-and-arc chondroid bodies inside the capsule, not an amorphous mass eroding bone. Fever, a raised CRP and an effusion demand aspiration. Recurrent atraumatic haemarthrosis with erosions and a preserved joint space suggests PVNS, and painless gross debris suggests a neuropathic joint.
Does the knee have a true mechanical block? Test passive extension yourself rather than accepting the word "locking" from the history; true locking is a sudden mechanical block that the patient has to manoeuvre out of. A knee that cannot be passively extended is a surgical indication irrespective of the radiograph. If the film is normal the culprit is most often a bucket-handle meniscal tear or a purely chondral body: go to MRI, then arthroscopy.
MCQ Practice Points
Q: What is the commonest site of osteochondritis dissecans in the knee?
A: The lateral (intercondylar) aspect of the medial femoral condyle, adjacent to the notch and outside the principal weight-bearing zone — best profiled on the tunnel or intercondylar view. This is distinct from SONK, which involves the weight-bearing surface of the medial femoral condyle in an older patient.
Q: How do you distinguish primary from secondary synovial chondromatosis on a radiograph?
A: By the uniformity of the bodies and the state of the joint. Primary shows numerous bodies of relatively uniform size with ring-and-arc chondroid calcification in a joint with preserved space, typically aged 30 to 50. Secondary shows fewer bodies of varying size and irregular shape in a joint with obvious degenerative change — narrowing, sclerosis and osteophytes.
Q: A patient has primary synovial chondromatosis. Does removal of the bodies need to be accompanied by synovectomy?
A: It depends on the phase, and Milgram's answer is more nuanced than the usual teaching. He described three phases: (1) active intrasynovial disease with no loose bodies; (2) transitional, with both intrasynovial proliferation and free bodies; (3) multiple free bodies with no demonstrable intrasynovial disease. In phase 3, synovectomy may not be necessary. And in phases 1 and 2 synovectomy does not guarantee against recurrence, because extrasynovial intra-articular cartilaginous lesions can persist afterwards and grow. Phase the disease at arthroscopy and document every recess.
Q: A posterolateral ossicle behind the lateral femoral condyle appears on every lateral film — what is it?
A: The fabella, a sesamoid in the lateral head of gastrocnemius. It is extracapsular, present in roughly one in five knees and often bilateral, and it never migrates. The cyamella, within the popliteus tendon, is the rarer analogous mimic.
Q: Which MRI features indicate an unstable osteochondritis dissecans fragment?
A: Four. A high-signal line at the fragment–bone interface on T2; subchondral cysts greater than 5 mm; fluid tracking through a full-thickness breach in the overlying cartilage; and a displaced fragment. Any one shifts management towards operative fixation, or excision with treatment of the defect.
Q: Which condition presents with recurrent atraumatic haemarthrosis, bone erosions on both sides of the joint, preserved joint space and NO calcification?
A: Pigmented villonodular synovitis. MRI shows blooming artefact on gradient-echo sequences from haemosiderin. Treatment is synovectomy, with radiosynoviorthesis or targeted CSF1R therapy considered for diffuse or recurrent disease.
Q: Which single plain-film feature most reliably confirms a fragment is a true loose body?
A: A change in its position between two radiographs taken at different times or in different degrees of flexion. Note the corollary though — a normal radiograph does not exclude a fragment: in children after a first patellar dislocation, 44 per cent of MRI-confirmed osteochondral fractures were reported as radiograph-negative (Seeley).
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are shown an AP and lateral radiograph of the knee of a 14-year-old boy with six months of vague pain and two episodes of the knee locking. There is a small ossific density in the intercondylar region and a lucency with a sclerotic rim on the medial femoral condyle.”
“You are shown a lateral radiograph of the knee of a 38-year-old man with a two-year history of swelling, crepitus and occasional catching. There are more than fifteen rounded calcified bodies of similar size, several in the suprapatellar pouch and several posteriorly. Joint space is preserved.”
“You are shown normal AP and lateral radiographs of a 24-year-old rugby player who sustained a twisting injury three days ago. He has a tense effusion and cannot extend the knee beyond 25 degrees.”
Confirm it is real
- Intra-articular on two orthogonal views, not in gastrocnemius (fabella) or popliteus (cyamella)
- Not contiguous with the joint margin (osteophyte has a cortical bridge)
- Position changes between films — the single most specific sign
- Views: AP, lateral, skyline, tunnel/intercondylar
Age shortcuts
- Less than 20, solitary body: OCD or acute osteochondral fracture
- 30-50, multiple uniform bodies: primary synovial chondromatosis
- 20-50, no calcification, recurrent haemarthrosis: PVNS
- 15-40, soft tissue mass with punctate calcification: synovial sarcoma
- Over 55, multiple varied bodies with joint space loss: osteoarthritis / secondary chondromatosis
Donor site tells you the diagnosis
- Lateral aspect of medial femoral condyle: classic OCD
- Weight-bearing medial femoral condyle in the elderly: SONK
- Patellar median ridge or lateral trochlea: post-dislocation osteochondral fracture
- Anterior intercondylar eminence: ACL tibial spine avulsion
- No defect at all: synovial origin
Fragment morphology
- Well-corticated, rounded, may have enlarged: chronic, nourished by synovial fluid
- Sharp, non-corticated, jigsaws into a fresh bed: acute — consider urgent fixation
- Ring-and-arc calcification: chondroid matrix
- Metallic or manufactured geometry: retained implant or foreign body
Must-not-miss
- Synovial sarcoma — refer before arthroscopy; unplanned surgery contaminates compartments
- Septic or tuberculous arthritis — aspirate before anything else
- Locked knee with normal radiographs — chondral body or bucket-handle tear; MRI then arthroscopy
- Neuropathic joint — debris out of proportion to pain; find the neurological cause
When no further imaging is needed
- Fabella, cyamella, bipartite patella in an asymptomatic knee
- Attached marginal osteophyte
- Established osteoarthritis where management is non-operative regardless
Numbers worth quoting
- Fabella present in approximately 20 per cent of knees, often bilateral
- OCD affects the lateral aspect of the medial femoral condyle in about 70 per cent of cases
- Subchondral cysts greater than 5 mm on MRI suggest an unstable OCD fragment
- Milgram stages I, II and III for synovial chondromatosis
Evidence Base
Synovial Osteochondromatosis - A Histopathological Study of Thirty Cases
- Thirty cases studied clinically and pathologically, establishing that the disease follows a temporal sequence of three recognisable phases
- PHASE 1 - active intrasynovial disease only, with NO loose bodies
- PHASE 2 - transitional: active intrasynovial proliferation AND free loose bodies together
- PHASE 3 - multiple free osteochondral bodies with NO demonstrable intrasynovial disease
- If gross examination at operation shows phase 3 disease, SYNOVECTOMY MAY NOT BE NECESSARY
- In phases 1 and 2, extrasynovial intra-articular cartilaginous lesions may PERSIST after synovectomy and grow, causing recurrent symptoms in the absence of any new intrasynovial disease