Canal narrowing causing leg symptoms with walking - relieved by flexion (shopping cart sign)
- Neurogenic vs vascular claudication: neurogenic relieved by FLEXION, vascular by stopping
- Shopping cart sign: patient prefers flexed position (opens canal)
- Absolute stenosis: less than 10mm AP diameter, relative 10-12mm. Treat these as TEXTBOOK CONVENTION - they trace to Verbiest's 1954 developmental-stenosis series, published without a retrievable abstract, and quoted values differ between sources. No canal diameter has an established sensitivity or specificity for symptoms
- SPORT stenosis: intention-to-treat was significant on SF-36 bodily pain ONLY (7.8, 95% CI 1.5-14.1), not physical function or Oswestry. The 'surgery superior on all outcomes' claim comes from the AS-TREATED analysis. Never merge this with SPORT's spondylolisthesis arm, where ITT showed nothing
- Add fusion if instability or spondylolisthesis present
- “Often normal neurological examination at rest - symptoms reproduced with walking
- “Wide-based gait and forward-flexed posture are classic
- “L4-5 most commonly affected level followed by L3-4
- “MRI is gold standard - CT myelogram if MRI contraindicated
Lumbar Spinal Stenosis
Overview and Epidemiology
Lumbar spinal stenosis is one of the most common causes of low back and leg symptoms in older adults: a progressive narrowing of the spinal canal that compresses the neural elements. Narrowing on imaging is present in 20-30% of the population over 60, and only 5-10% of those with imaging stenosis are symptomatic.
Who. The peak age is 60-70 years, with equal sex distribution or a slight male predominance. It is the number one reason for spine surgery in patients over 65.
Where. L4-5 is the most commonly affected level (80%), then L3-4. Multi-level disease is common in advanced disease. L5-S1 is less commonly affected, protected by the iliolumbar ligament.
Pathophysiology
The canal. These are the dimensions examiners expect:
- Normal value
- 15-18mm
- Stenosis threshold
- Under 10mm (absolute); 10-12mm relative
- Normal value
- 20-25mm
- Stenosis threshold
- Under 15mm
- Normal value
- 200-400mm2
- Stenosis threshold
- Under 100mm2 (severe)
- Normal value
- 5-7mm
- Stenosis threshold
- Under 3mm (stenosis)
- Normal value
- 20-23mm
- Stenosis threshold
- Under 15mm
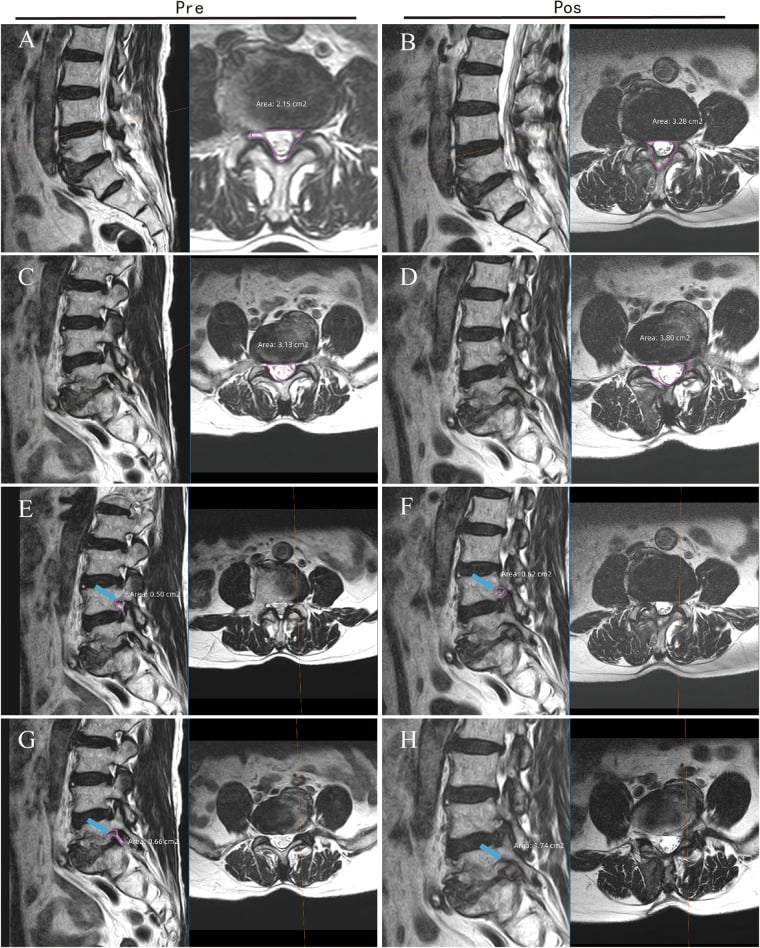
Read every figure in that table as convention, not as a validated cut-off. None has an established sensitivity or specificity for symptoms, published values differ between sources, and the AP thresholds descend from Verbiest's 1954 series on developmental narrowing, measured before CT and MRI existed: a different population and a different modality from the degenerative stenosis in front of you. This is exactly why morphological grading of the dural sac (Schizas, in the classification section) was devised. Boden's asymptomatic-MRI work showed that radiological narrowing is common in pain-free people, so a number alone can never make the diagnosis; correlate with a concordant claudication history and examination, every time.
What narrows it. Degenerative stenosis is encroachment from several directions at once:
- Contribution
- Anterior narrowing
- Mechanism
- Bulging, height loss
- Contribution
- Posterolateral narrowing
- Mechanism
- Hypertrophy, arthrosis
- Contribution
- Posterior narrowing
- Mechanism
- Hypertrophy, infolding
- Contribution
- Lateral narrowing
- Mechanism
- Congenital short pedicle
- Contribution
- Dynamic narrowing
- Mechanism
- Forward translation
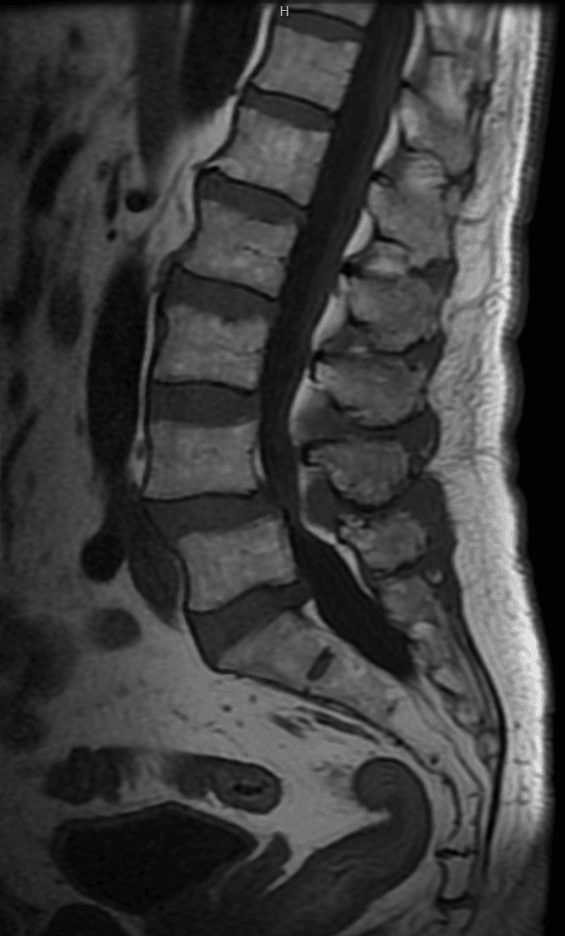
Why the legs hurt. Four mechanisms contribute to the symptoms:
- Mechanical compression - direct neural compression
- Venous congestion - impaired venous drainage and oedema
- Arterial ischaemia - reduced blood flow during exercise
- Inflammatory mediators - chemical irritation of the nerves
Why flexion helps. Flexion increases the canal diameter: the ligamentum flavum stretches and the foramina open. Extension decreases it: the ligamentum flavum buckles and the foramina narrow. That is the whole basis of the shopping cart sign, the patient's preference for a flexed position.
Classification Systems
Three classifications answer three different questions: where the narrowing is, how tight it is, and what caused it.
By location. The anatomical type predicts the clinical pattern. Central narrowing compresses the cauda equina and produces bilateral claudication; narrowing of the lateral recess or the foramen compresses a single root and produces a radiculopathy.
- Location
- Spinal canal
- Structure affected
- Cauda equina
- Clinical pattern
- Bilateral claudication, diffuse leg symptoms
- Location
- Anterolateral gutter, between pedicle and facet
- Structure affected
- Traversing root
- Clinical pattern
- Radiculopathy, unilateral or asymmetric
- Location
- Neural foramen
- Structure affected
- Exiting root
- Clinical pattern
- Radiculopathy, dermatomal pattern
- Location
- Beyond the foramen
- Structure affected
- Exiting root
- Clinical pattern
- Often missed on imaging
- Location
- Multiple areas
- Structure affected
- Clinical pattern
- Mixed symptoms
Clinical Presentation
The cardinal symptom is neurogenic claudication. Heaviness, burning, aching or cramping in the buttocks, thighs and legs, often bilateral, comes on with walking or prolonged standing and is relieved by sitting or bending forward. The walking distance shortens progressively. A back pain component may be less prominent than the leg symptoms.
The questions that make the diagnosis.
- Walking distance before symptoms begin (the claudication distance)
- Relief with flexion: sitting, leaning forward
- Cycling tolerance, usually good, because the position is flexed
- Stairs: descending is often worse, because the spine extends
- Back pain relative to leg symptoms
- Bowel or bladder symptoms, screening for cauda equina syndrome
Cauda equina syndrome. Bladder retention or incontinence, saddle (perineal) anaesthesia and bilateral leg weakness, with sexual dysfunction sometimes present. It is a surgical emergency; do not wait.
Neurogenic or vascular? Vascular claudication is the differential; the history and the pulses separate them.
- Neurogenic
- Buttocks, thighs, diffuse
- Vascular
- Calves primarily
- Neurogenic
- With walking OR standing
- Vascular
- With walking only
- Neurogenic
- Sitting/flexing forward
- Vascular
- Standing still
- Neurogenic
- Variable, may take minutes
- Vascular
- Rapid (1-2 minutes)
- Neurogenic
- Usually tolerated well
- Vascular
- May provoke symptoms
- Neurogenic
- Positive (prefers flexion)
- Vascular
- Negative
- Neurogenic
- Normal
- Vascular
- May be diminished
- Neurogenic
- Often better
- Vascular
- Worse
- Neurogenic
- Often worse
- Vascular
- Better
Examination. Watch the patient walk in: a wide-based, shuffling gait, a forward-flexed posture (the simian stance) and any walking aid they use. Then examine the lumbar spine with the posture-dependence of the symptoms in mind.
- Technique
- Flexion/extension
- Finding in stenosis
- Extension often limited or provocative
- Technique
- Maintain extension for 30 seconds
- Finding in stenosis
- May reproduce leg symptoms
- Technique
- Walk, then stop flexed
- Finding in stenosis
- Longer walking if allowed to flex
- Technique
- Cycling (flexed)
- Finding in stenosis
- Better tolerance than walking
The neurological examination is often normal at rest, which is the trap: weakness may develop only after the patient has walked. Document the pulses, because a normal pulse is part of the case against vascular claudication.
- Findings
- Often normal at rest
- Notes
- May develop weakness after walking
- Findings
- May have patchy changes
- Notes
- Multi-dermatomal in central stenosis
- Findings
- Variable, may be diminished
- Notes
- L4 (knee jerk), S1 (ankle jerk)
- Findings
- Normal
- Notes
- Important to document (exclude vascular)
Investigations
The sequence. Radiographs first, for alignment and instability; MRI for the compression; CT where bony detail is needed, and CT myelogram where MRI is contraindicated.
- Investigation
- Weight-bearing radiographs
- Purpose
- Alignment, instability, spondylolisthesis
- Investigation
- MRI lumbar spine
- Purpose
- Canal dimensions, soft tissue, neural compression
- Investigation
- CT (if needed)
- Purpose
- Bony detail, surgical planning
- Investigation
- CT myelogram
- Purpose
- MRI contraindicated, dynamic assessment
Radiographs. Look for disc space narrowing, facet arthropathy, spondylolisthesis, scoliosis and the sagittal alignment. Take flexion-extension views when spondylolisthesis is suspected: translation over 3-4mm or angular change over 10-15 degrees defines instability, and that finding is important for surgical planning because it informs the fusion decision.
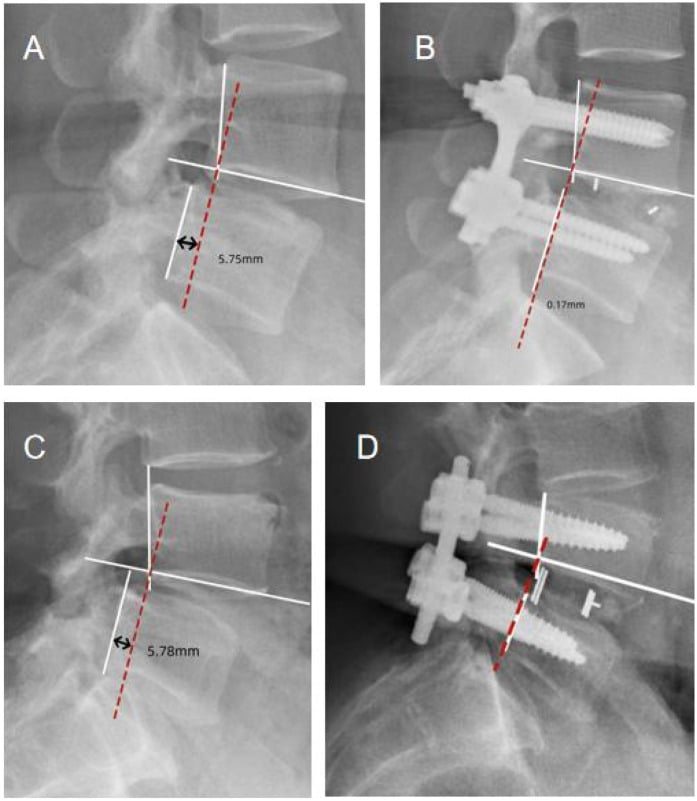
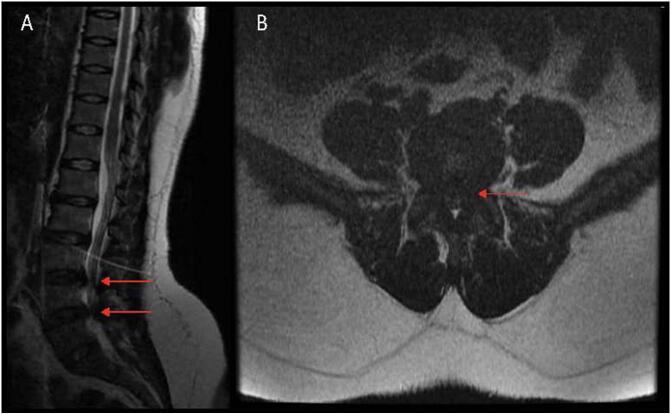
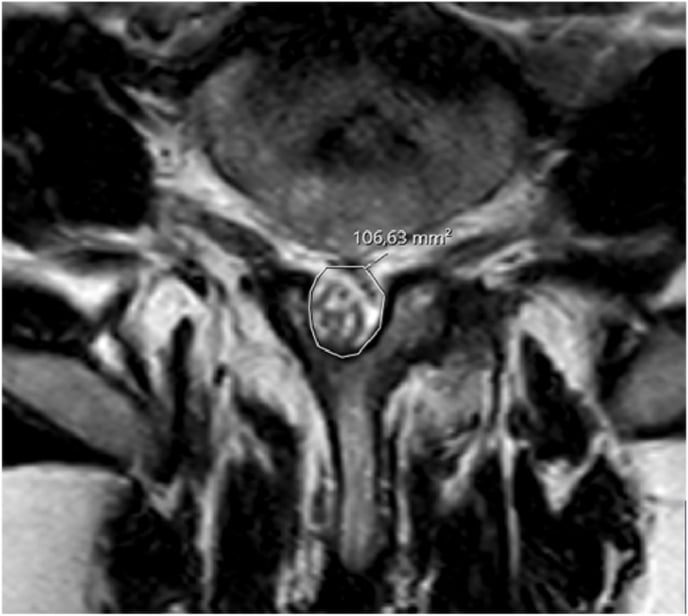
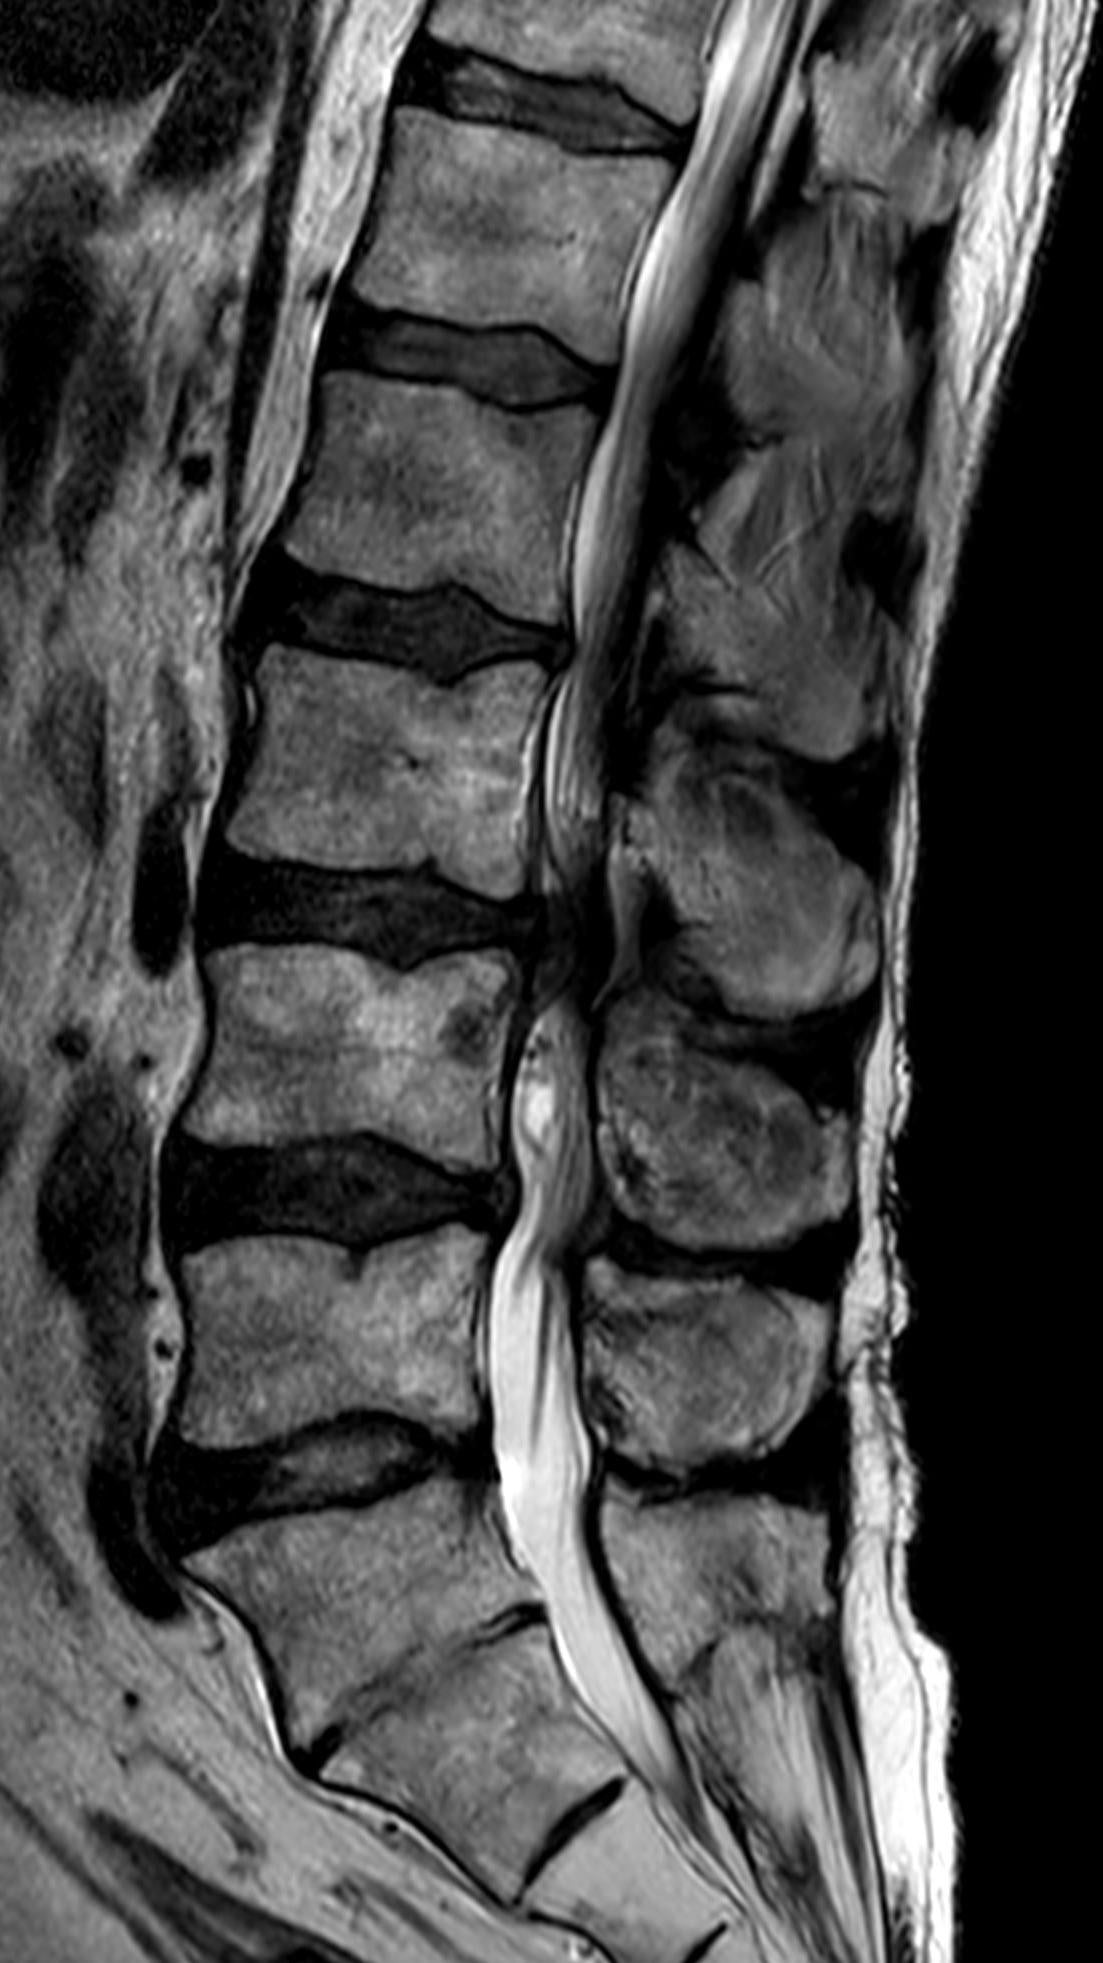
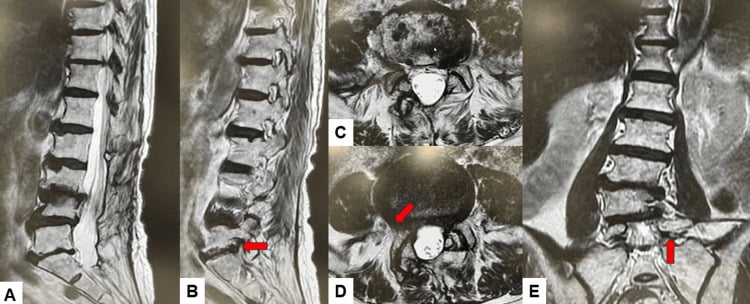
MRI is the gold standard. It shows the canal dimensions, the soft tissues that narrow it and the neural compression, and the findings to report are these:
- Description
- Loss of CSF signal around the cauda
- Significance
- Indicates compression
- Description
- Concentric disc expansion
- Significance
- Anterior canal narrowing
- Description
- Hypertrophy on T1/T2
- Significance
- Posterior canal narrowing
- Description
- Enlarged facet joints
- Significance
- Lateral narrowing
- Description
- Roots pressed together
- Significance
- Severe stenosis
- Description
- Loss of epidural fat
- Significance
- Canal compromise
- Description
- Elongated, tortuous, serpiginous cauda equina roots above (and sometimes below) the stenosis on sagittal T2
- Significance
- Marker of severe, long-standing stenosis; associated in some series with poorer or slower recovery
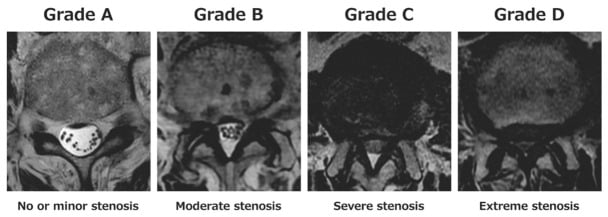
Grade and correlate. Grade the dural sac morphologically (the Schizas grade, in the classification section) rather than by a measured area alone, and then match the scan to the patient: many people have radiographic stenosis and no symptoms, so the level of maximum stenosis should match the clinical syndrome.
Other tests, each for a specific question:
- Indication
- Unclear diagnosis, radiculopathy versus neuropathy
- Information
- Localises nerve dysfunction
- Indication
- Suspected vascular claudication
- Information
- Under 0.9 suggests peripheral vascular disease
- Indication
- Suspected tumour, infection
- Information
- Uptake pattern
- Indication
- Osteoporosis assessment
- Information
- Guides fusion considerations
Differential Diagnosis
- Distinguishing Features
- Calf pain, absent pulses, rapid relief with standing
- Investigation
- ABI, Doppler, angiography
- Distinguishing Features
- Groin pain, limited hip ROM, FABER positive
- Investigation
- Hip X-ray, MRI hip
- Distinguishing Features
- Stocking-glove distribution, diabetic history
- Investigation
- EMG/NCS, glucose, B12
- Distinguishing Features
- Radicular pattern, positive SLR, younger patient
- Investigation
- MRI shows focal disc
- Distinguishing Features
- Buttock pain, positive SI tests, FABER pain
- Investigation
- SI X-rays, CT, injection
- Distinguishing Features
- Bladder/bowel dysfunction, saddle anesthesia
- Investigation
- Urgent MRI
- Distinguishing Features
- Buttock pain, positive piriformis tests
- Investigation
- Clinical, MRI may show muscle
- Distinguishing Features
- Night pain, constitutional symptoms, progressive
- Investigation
- MRI with contrast
Management
The trial. A 6-12 week trial of conservative treatment, continued if the patient is improving.
Activity. Flexion-based activities such as cycling and swimming, avoiding prolonged extension, rest breaks during walking, a walking aid if needed and weight loss if applicable.
Drugs. Paracetamol and a short course of NSAIDs first-line. Gabapentin or pregabalin second-line for a neuropathic component, and a muscle relaxant for acute spasm. Avoid prolonged opioids.
Physiotherapy. Flexion-based exercises (Williams flexion), core strengthening, aerobic conditioning, postural training and manual therapy. Aquatic therapy is excellent.
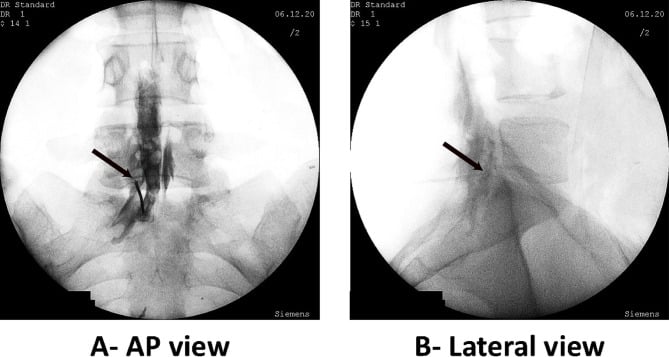
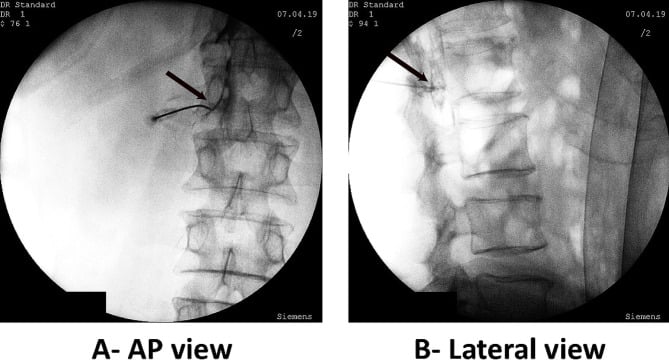
Epidural steroid injection. By an interlaminar or transforaminal approach. The benefit is short-term, weeks to months; it may delay surgery in some patients and has diagnostic value for surgical planning. Read that alongside the Friedly trial in the evidence section: adding glucocorticoid to epidural lidocaine offered minimal or no short-term benefit at 6 weeks, and because both arms were injected, the trial does not show that an epidural injection is no better than no injection.
Complications
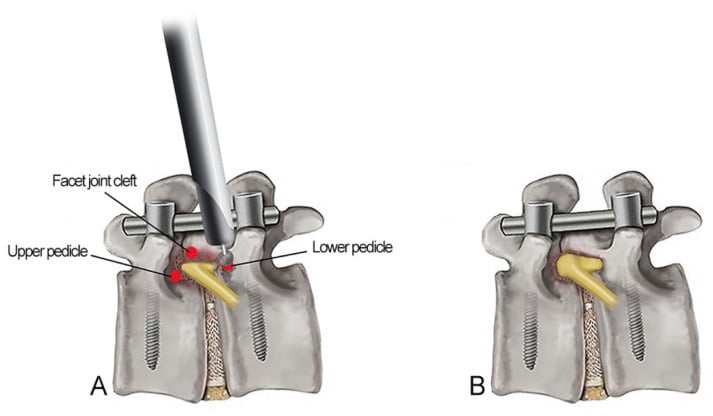
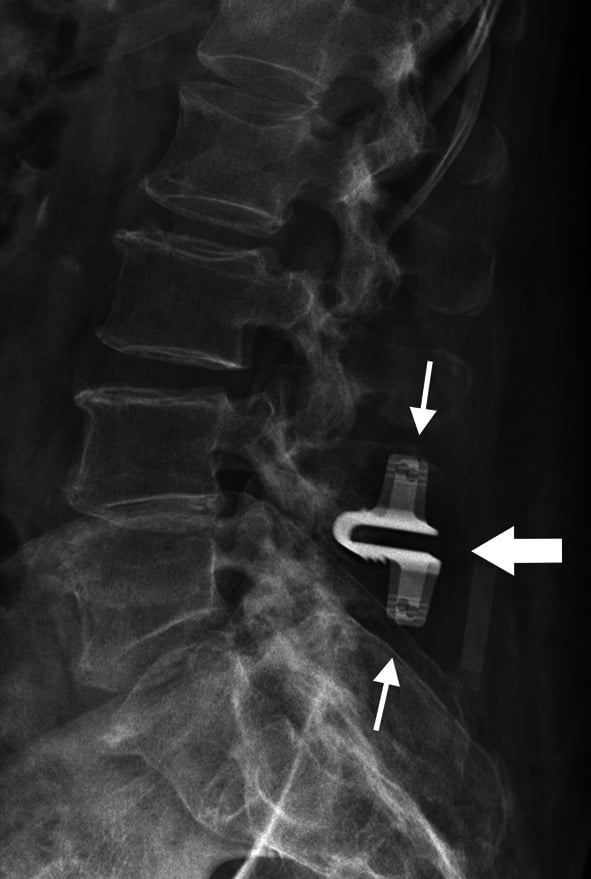
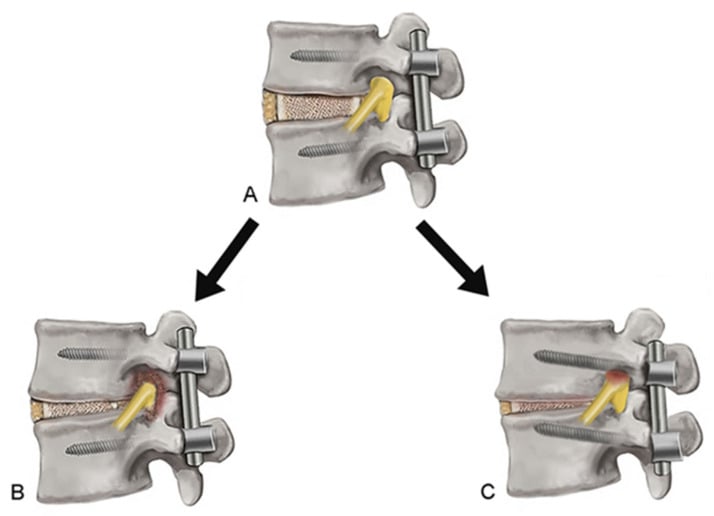
Dural tear is the most common intraoperative complication. Late, the problems are instability if too much facet was removed, recurrent stenosis at the same or an adjacent level, and epidural fibrosis (adhesions) causing symptoms.
- Rate
- 5-10%
- Management
- Primary repair, fibrin glue
- Rate
- 2-5%
- Management
- Bed rest, blood patch if needed
- Rate
- 1-3%
- Management
- Antibiotics, debridement if deep
- Rate
- 0.5-1%
- Management
- Prevent with careful technique
- Rate
- 5-10% (late)
- Management
- Fusion if symptomatic
- Rate
- 10-15% at 10 years
- Management
- Revision surgery
- Rate
- 2-3% per year (if fused)
- Management
- Surveillance, may need extension
Guidelines, Registries & Global Practice
Global Epidemiology
- Radiographic stenosis is present in 20-30% of people over 60; only 5-10% are symptomatic
- Lumbar decompression is among the most common spine operations in adults over 65 worldwide
- L4-5 is the most frequently operated level across populations
Side-by-Side Society Guidance
- Position
- Evidence-based guideline supports decompression for symptomatic stenosis after failed non-operative care; routine fusion not recommended for stenosis without instability
- Position
- Conservative care first (exercise, analgesia); image only when surgery is being considered; decompression for refractory neurogenic claudication
- Position
- Stepwise conservative trial then decompression; epidural steroid for short-term relief with limited durable benefit
- Position
- Decompression remains gold standard; add fusion selectively for instability or deformity
Decompression Alone vs Decompression Plus Fusion
The SLIP (Ghogawala, NEJM 2016) and Swedish Spinal Stenosis Study (Forsth, NEJM 2016) trials addressed whether stenosis with degenerative spondylolisthesis needs added fusion. They reached differing conclusions, so practice varies: many surgeons add fusion for clear dynamic instability or significant slip, while decompression alone is increasingly accepted for stable Grade 1 slips. Registry data (e.g. national spine registries) show rising fusion rates without proportionate outcome gains, prompting more selective use.
High- vs Limited-Resource Variation
- High-resource settings: ready MRI access, microscope or tubular (minimally invasive) decompression, instrumented fusion, and Enhanced Recovery After Surgery (ERAS) pathways with early mobilisation
- Limited-resource settings: greater reliance on clinical diagnosis and plain films/CT, open laminectomy as the default decompression, and longer conservative trials where surgical capacity is constrained
Medication Principles (non-billing)
- First-line analgesia: paracetamol and a short course of NSAIDs with gastroprotection
- Neuropathic agents (gabapentin/pregabalin) have limited evidence in stenosis and should be reserved for a clear neuropathic component
- Avoid prolonged opioids
MCQ Practice Points
Q: What are the key distinguishing features between neurogenic and vascular claudication? A: Neurogenic claudication (lumbar stenosis): relieved by sitting or bending forward (shopping cart sign), proximal-to-distal spread, variable walking distance, pulses present, and the bicycle (flexed) test is tolerated. Vascular claudication (PVD): relieved by standing still, distal-to-proximal spread, fixed walking distance, and diminished or absent pulses. Always check pulses to avoid missing PVD.
Q: What defines absolute lumbar spinal stenosis on imaging? A: Absolute stenosis: AP canal diameter under approximately 10-11mm OR dural sac cross-sectional area under 100mm². Relative stenosis: AP diameter 10-13mm. Lateral recess under 3mm and foraminal height under 15mm are additional thresholds. MRI is the gold standard; the Schizas morphological grade adds prognostic value beyond raw area.
Q: What did the SPORT stenosis trial show and what are the surgical indications? A: SPORT showed decompression was superior to nonoperative care in the as-treated analysis, with benefit sustained to 4 years; the intention-to-treat result was diluted by high crossover. Surgery is indicated for failed 6-12 weeks of conservative care, progressive neurological deficit, cauda equina syndrome (emergency), and intractable symptoms limiting function.
Q: What are the surgical options and when is fusion added? A: Decompression alone (laminectomy/laminotomy, preserving over 50% of each facet) for a stable spine. Add fusion for spondylolisthesis, segmental instability on flexion-extension films, more than 50% facetectomy, or recurrent stenosis. The most common intraoperative complication is dural tear (5-10%).
Common Examination Pitfalls
- Confusing neurogenic and vascular claudication (always check pulses)
- Missing spondylolisthesis on imaging (look for it specifically)
- Forgetting to assess stability with flexion-extension views
- Not correlating imaging stenosis with clinical symptoms
- Overlooking cauda equina red flags
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“What is your diagnosis and management approach?”
“How does spondylolisthesis affect your surgical planning?”
“What are the surgical considerations for multilevel stenosis in this high-risk patient?”
Key Definitions
- Canal narrowing causing neural compression and neurogenic claudication
- Absolute stenosis: Under 11mm AP diameter or under 100mm2 cross-sectional area
- Types: Central, lateral recess, foraminal, or combined stenosis
- Etiology: Degenerative (most common), congenital, post-traumatic, iatrogenic
Clinical Features
- Most common level: L4-5 (80%), then L3-4
- Cardinal symptom: Neurogenic claudication - leg symptoms with walking, relieved by flexion
- Key sign: Shopping cart sign - prefers flexion (opens canal)
- Extension worsens symptoms - ligamentum flavum buckles, foramina narrow
Neurogenic vs Vascular Claudication
- Neurogenic: flexion relief, better uphill, can cycle, normal pulses
- Vascular: standing still relief, calf pain, worse uphill, diminished pulses
- Neurogenic relief timing: Variable (minutes); Vascular: rapid (1-2 min)
- Both: Progressive reduction in walking distance
Imaging
- First-line: MRI - shows canal dimensions, soft tissue, neural compression
- Flexion-extension films: Assess for instability (over 3-4mm translation)
- Schizas grading: A (mild) to D (severe) based on CSF and root visibility
- CT myelogram: Alternative if MRI contraindicated, excellent bony detail
Management
- Conservative Rx: Flexion exercises, NSAIDs, physio, epidurals; trial 6-12 weeks
- Surgery indication: Failed conservative Rx, functional limitation, progressive deficit
- Standard surgery: Laminectomy (preserve over 50% facet to avoid instability)
- Add fusion if: Spondylolisthesis, instability, over 50% facetectomy
Evidence and Complications
- SPORT trial: Surgery superior in as-treated analysis; 80% improved at 2-4 years
- Dural tear: Most common intraop complication (5-10%); primary repair with fibrin glue
- Recurrent stenosis: 10-15% at 10 years may need revision
- Adjacent segment disease: 2-3% per year if fused
Evidence Base
Natural History
- Progressive decline in walking distance
- Neurological deterioration in minority
- Some patients stable for years
- Rarely causes complete paralysis
Evidence Base
SPORT Trial - Spinal Stenosis (without spondylolisthesis)
- Randomized (n=289) plus observational (n=365) cohorts at 13 US spine centers; stenosis without spondylolisthesis
- High crossover: by 2 years 67% of surgery-assigned had surgery, 43% of nonsurgical-assigned had surgery
- Intention-to-treat favored surgery on SF-36 bodily pain (mean difference 7.8, 95% CI 1.5-14.1) but not physical function or Oswestry
- As-treated (combined cohorts, adjusted): significant surgical advantage on all primary outcomes by 3 months, sustained at 2 years
SPORT Stenosis - 4-Year Results
- 4-year outcomes of the SPORT stenosis cohort (RC n=289, OC n=365)
- As-treated treatment effects favoring surgery: bodily pain 12.6 (95% CI 8.5-16.7), physical function 8.6 (95% CI 4.6-12.6)
- Oswestry Disability Index treatment effect -9.4 (95% CI -12.6 to -6.2)
- Early surgical advantages in satisfaction and self-rated progress maintained through 4 years
Verbiest - Developmental Lumbar Canal Stenosis
- First description of the radicular syndrome from developmental (congenital) narrowing of the lumbar vertebral canal
- Established the concept of absolute versus relative bony canal stenosis
- Foundational paper defining lumbar spinal stenosis as a distinct clinical entity
Schizas Morphological Grading of Stenosis Severity
- 7-grade classification (A1-A4, B, C, D) of dural sac morphology on axial T2 MRI based on the rootlet/CSF ratio
- Grades A and B retain visible CSF; grades C and D show no CSF around the rootlets
- Morphological grade identifies different patients than cross-sectional area alone; CSA over- or under-diagnosed stenosis in many cases
- Grades C and D were more likely to fail conservative treatment
Interspinous Process Device vs Conventional Decompression
- Double-blind RCT (n=159) of interspinous process device versus standard bony decompression for neurogenic claudication
- Device not superior at 8 weeks: Zurich Claudication Questionnaire success 63% (device) vs 72% (decompression)
- No difference in disability or other outcomes through 1 year
- Substantially higher early reoperation after the device (29% vs 8%, P less than 0.001)
Epidural Glucocorticoid Injections for Lumbar Stenosis
- Double-blind RCT (n=400) of epidural glucocorticoid plus lidocaine versus lidocaine alone for central LSS
- No significant difference in Roland-Morris disability at 6 weeks (adjusted difference -1.0, 95% CI -2.1 to 0.1)
- No significant difference in leg pain intensity (adjusted difference -0.2, 95% CI -0.8 to 0.4)
- Result held for both interlaminar and transforaminal approaches
References
- Weinstein JN, Tosteson TD, Lurie JD, et al. Surgical versus nonsurgical therapy for lumbar spinal stenosis. N Engl J Med. 2008;358(8):794-810. (PMID 18287602)
- Weinstein JN, Tosteson TD, Lurie JD, et al. Surgical versus nonoperative treatment for lumbar spinal stenosis four-year results of the Spine Patient Outcomes Research Trial. Spine (Phila Pa 1976). 2010;35(14):1329-38. (PMID 20453723)
- Phan K, Mobbs RJ. Minimally invasive versus open laminectomy for lumbar stenosis: a systematic review and meta-analysis. Spine (Phila Pa 1976). 2016;41(2):E91-E100. (PMID 26555839)
- Moojen WA, Arts MP, Jacobs WCH, et al. Interspinous process device versus standard conventional surgical decompression for lumbar spinal stenosis: randomized controlled trial. BMJ. 2013;347:f6415. (PMID 24231273)
- Verbiest H. A radicular syndrome from developmental narrowing of the lumbar vertebral canal. J Bone Joint Surg Br. 1954;36-B(2):230-7. (PMID 13163105 - no abstract indexed)
- Amundsen T, Weber H, Nordal HJ, Magnaes B, Abdelnoor M, Lilleas F. Lumbar spinal stenosis: conservative or surgical management? A prospective 10-year study. Spine (Phila Pa 1976). 2000;25(11):1424-35. (PMID 10828926)
- Malmivaara A, Slatis P, Heliovaara M, et al. Surgical or nonoperative treatment for lumbar spinal stenosis? A randomized controlled trial. Spine (Phila Pa 1976). 2007;32(1):1-8. (PMID 17202885)
- Kreiner DS, Shaffer WO, Baisden JL, et al; North American Spine Society. An evidence-based clinical guideline for the diagnosis and treatment of degenerative lumbar spinal STENOSIS (update). Spine J. 2013;13(7):734-43. (PMID 23830297)
- Schizas C, Theumann N, Burn A, et al. Qualitative grading of severity of lumbar spinal stenosis based on the morphology of the dural sac on magnetic resonance images. Spine (Phila Pa 1976). 2010;35(21):1919-24. (PMID 20671589)
- Friedly JL, Comstock BA, Turner JA, et al. A randomized trial of epidural glucocorticoid injections for spinal stenosis. N Engl J Med. 2014;371(1):11-21. (PMID 24988555)