Zone I Extensor Tendon Injury
- Conservative management (Splinting) is effective for MOST cases, including Bony Mallet.
- Surgery is reserved for volar subluxation or large fragments (over one-third of the articular surface) - though even there a clear advantage over splinting is not proven (Lamaris)
- Splinting must be CONTINUOUS. If the finger flexes once, the clock resets.
- Swan Neck Deformity develops due to proximal retraction of the central slip (Fowler's mechanism).
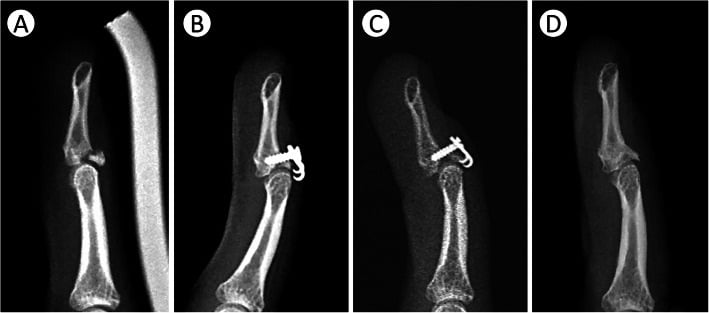
- Ishiguro Extension Block Pinning is the standard minimal invasive technique for bony mallet.
- “A lag of less than 10 degrees is functionally acceptable.
- “Dorsal skin necrosis is the most common complication of splinting (check the fit!).
- “Antibiotics are required for open injuries (Type II/III).
Overview
Mallet finger is disruption of the terminal extensor tendon at its insertion into the base of the distal phalanx, zone I of the extensor system. The patient cannot actively extend the DIPJ, an extensor lag, while passive extension remains intact.
Mechanism. A "jamming" injury, for example a basketball hitting the tip of the extended finger. The blow force-flexes the DIPJ against extensor resistance and either snaps the tendon or avulses its bony insertion. Whether the tendon or the bone gave way is the distinction that underlies the Doyle classification and the splint-versus-surgery decision.
Anatomy and Pathophysiology
The extensor apparatus. Extensor digitorum divides into a central slip, which inserts into the middle phalanx, and paired lateral bands, which reunite as the terminal tendon and insert into the dorsal lip of the distal phalanx. The terminal tendon is wide and wafer thin, less than 1mm. The triangular ligament prevents the lateral bands from subluxing volarly, and the oblique retinacular ligament (ORL) links PIPJ extension to DIPJ extension. A zone I disruption removes the distal anchor of this linked system while leaving the proximal apparatus intact.
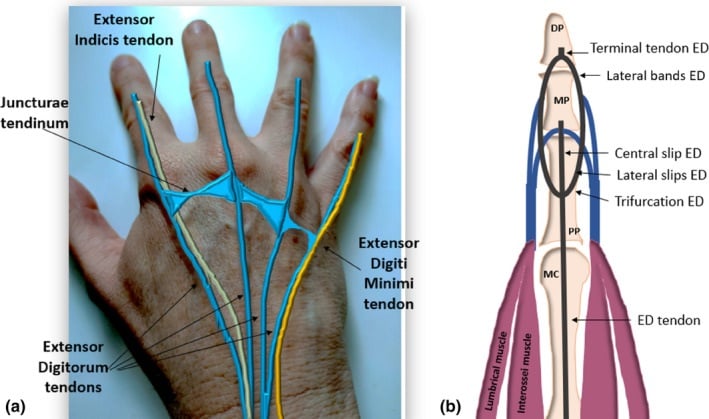
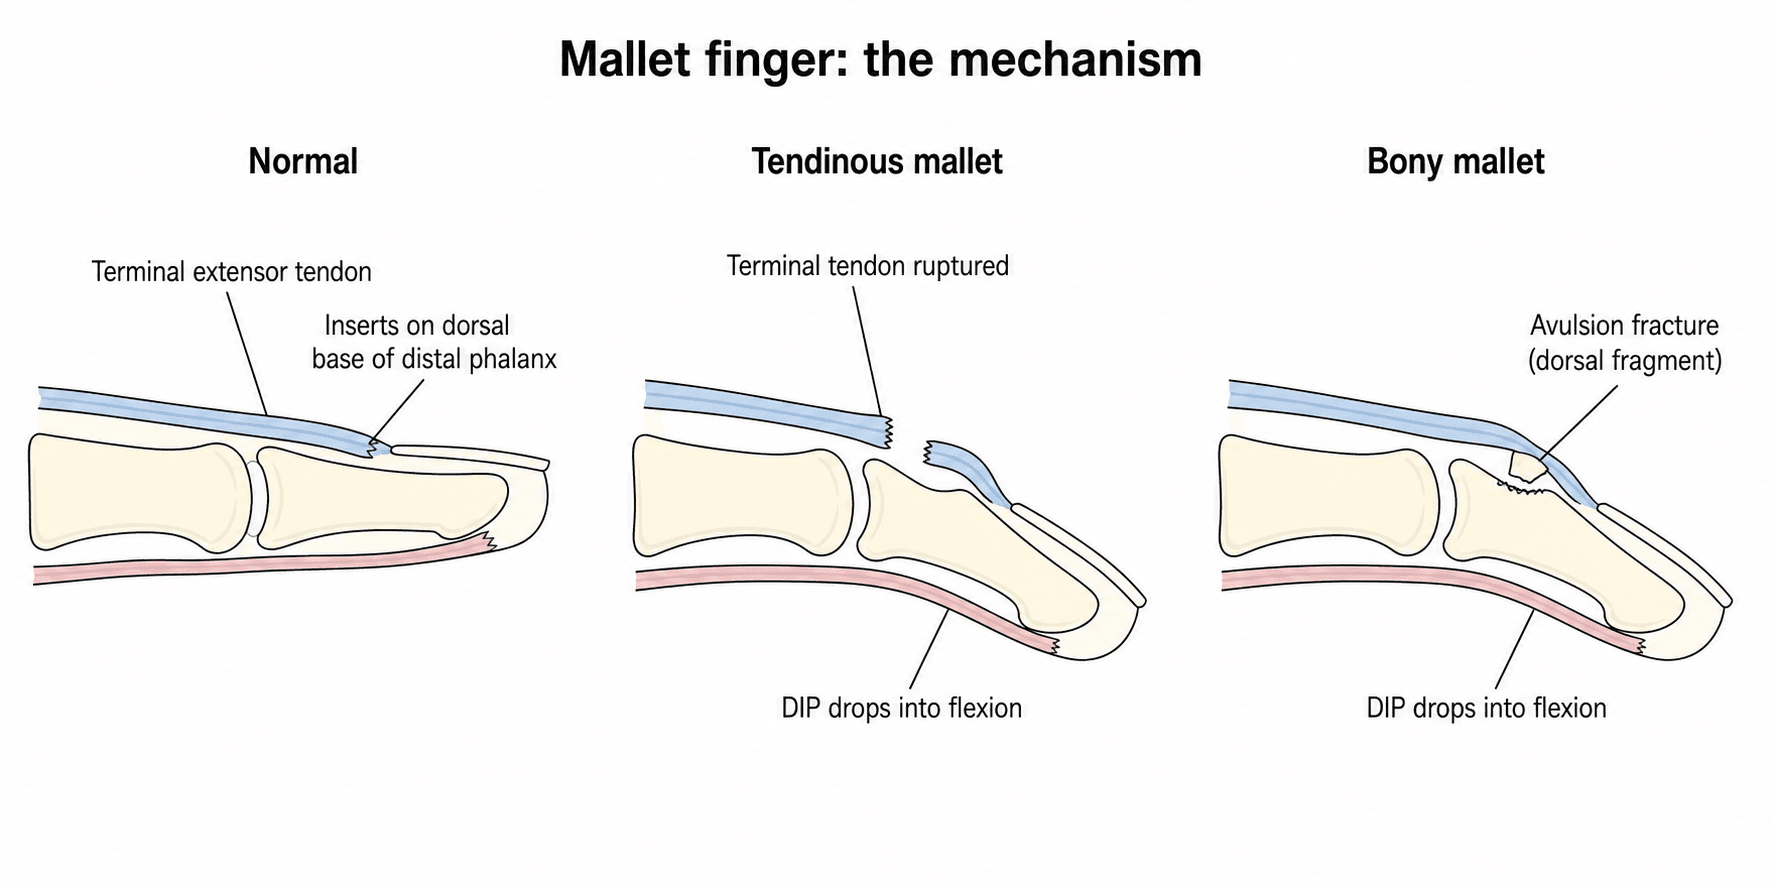
The swan neck. Once the distal anchor is lost the extensor force retracts proximally, which increases tension on the central slip and hyperextends the PIPJ. If the volar plate at the PIPJ is lax the PIPJ hyperextends, the lateral bands subluxate dorsally and lock the PIPJ in extension. The result is PIPJ hyperextension with DIPJ flexion, and it must be treated by correcting the DIPJ lag.
The skin and the nail. The dorsal skin of the DIPJ is supplied by tiny vascular branches and is very susceptible to pressure necrosis from splints. The germinal matrix lies immediately deep to the extensor tendon insertion, so nails are often damaged in Type IV injuries and a K-wire must be placed with care to avoid it.
Classification Systems
Doyle. The working classification, separating the closed tendon injury from the open injuries and the fractures:
- Type I - closed tendinous injury, the most common
- Type II - open injury (laceration)
- Type III - open injury with loss of skin or tendon substance
- Type IV - mallet fracture
- IVa - paediatric, a Salter-Harris physeal injury
- IVb - adult, less than 30% of the articular surface
- IVc - adult, greater than 30% of the articular surface, or subluxed
Type IVc is the most debated category regarding surgical management.
Wehbe and Schneider. Grades the bony mallet by the size of the fragment and the degree of subluxation. It is rarely used clinically, because the decision is binary, stable or unstable, and subluxation is the key determinant of instability.
Clinical Presentation and Assessment
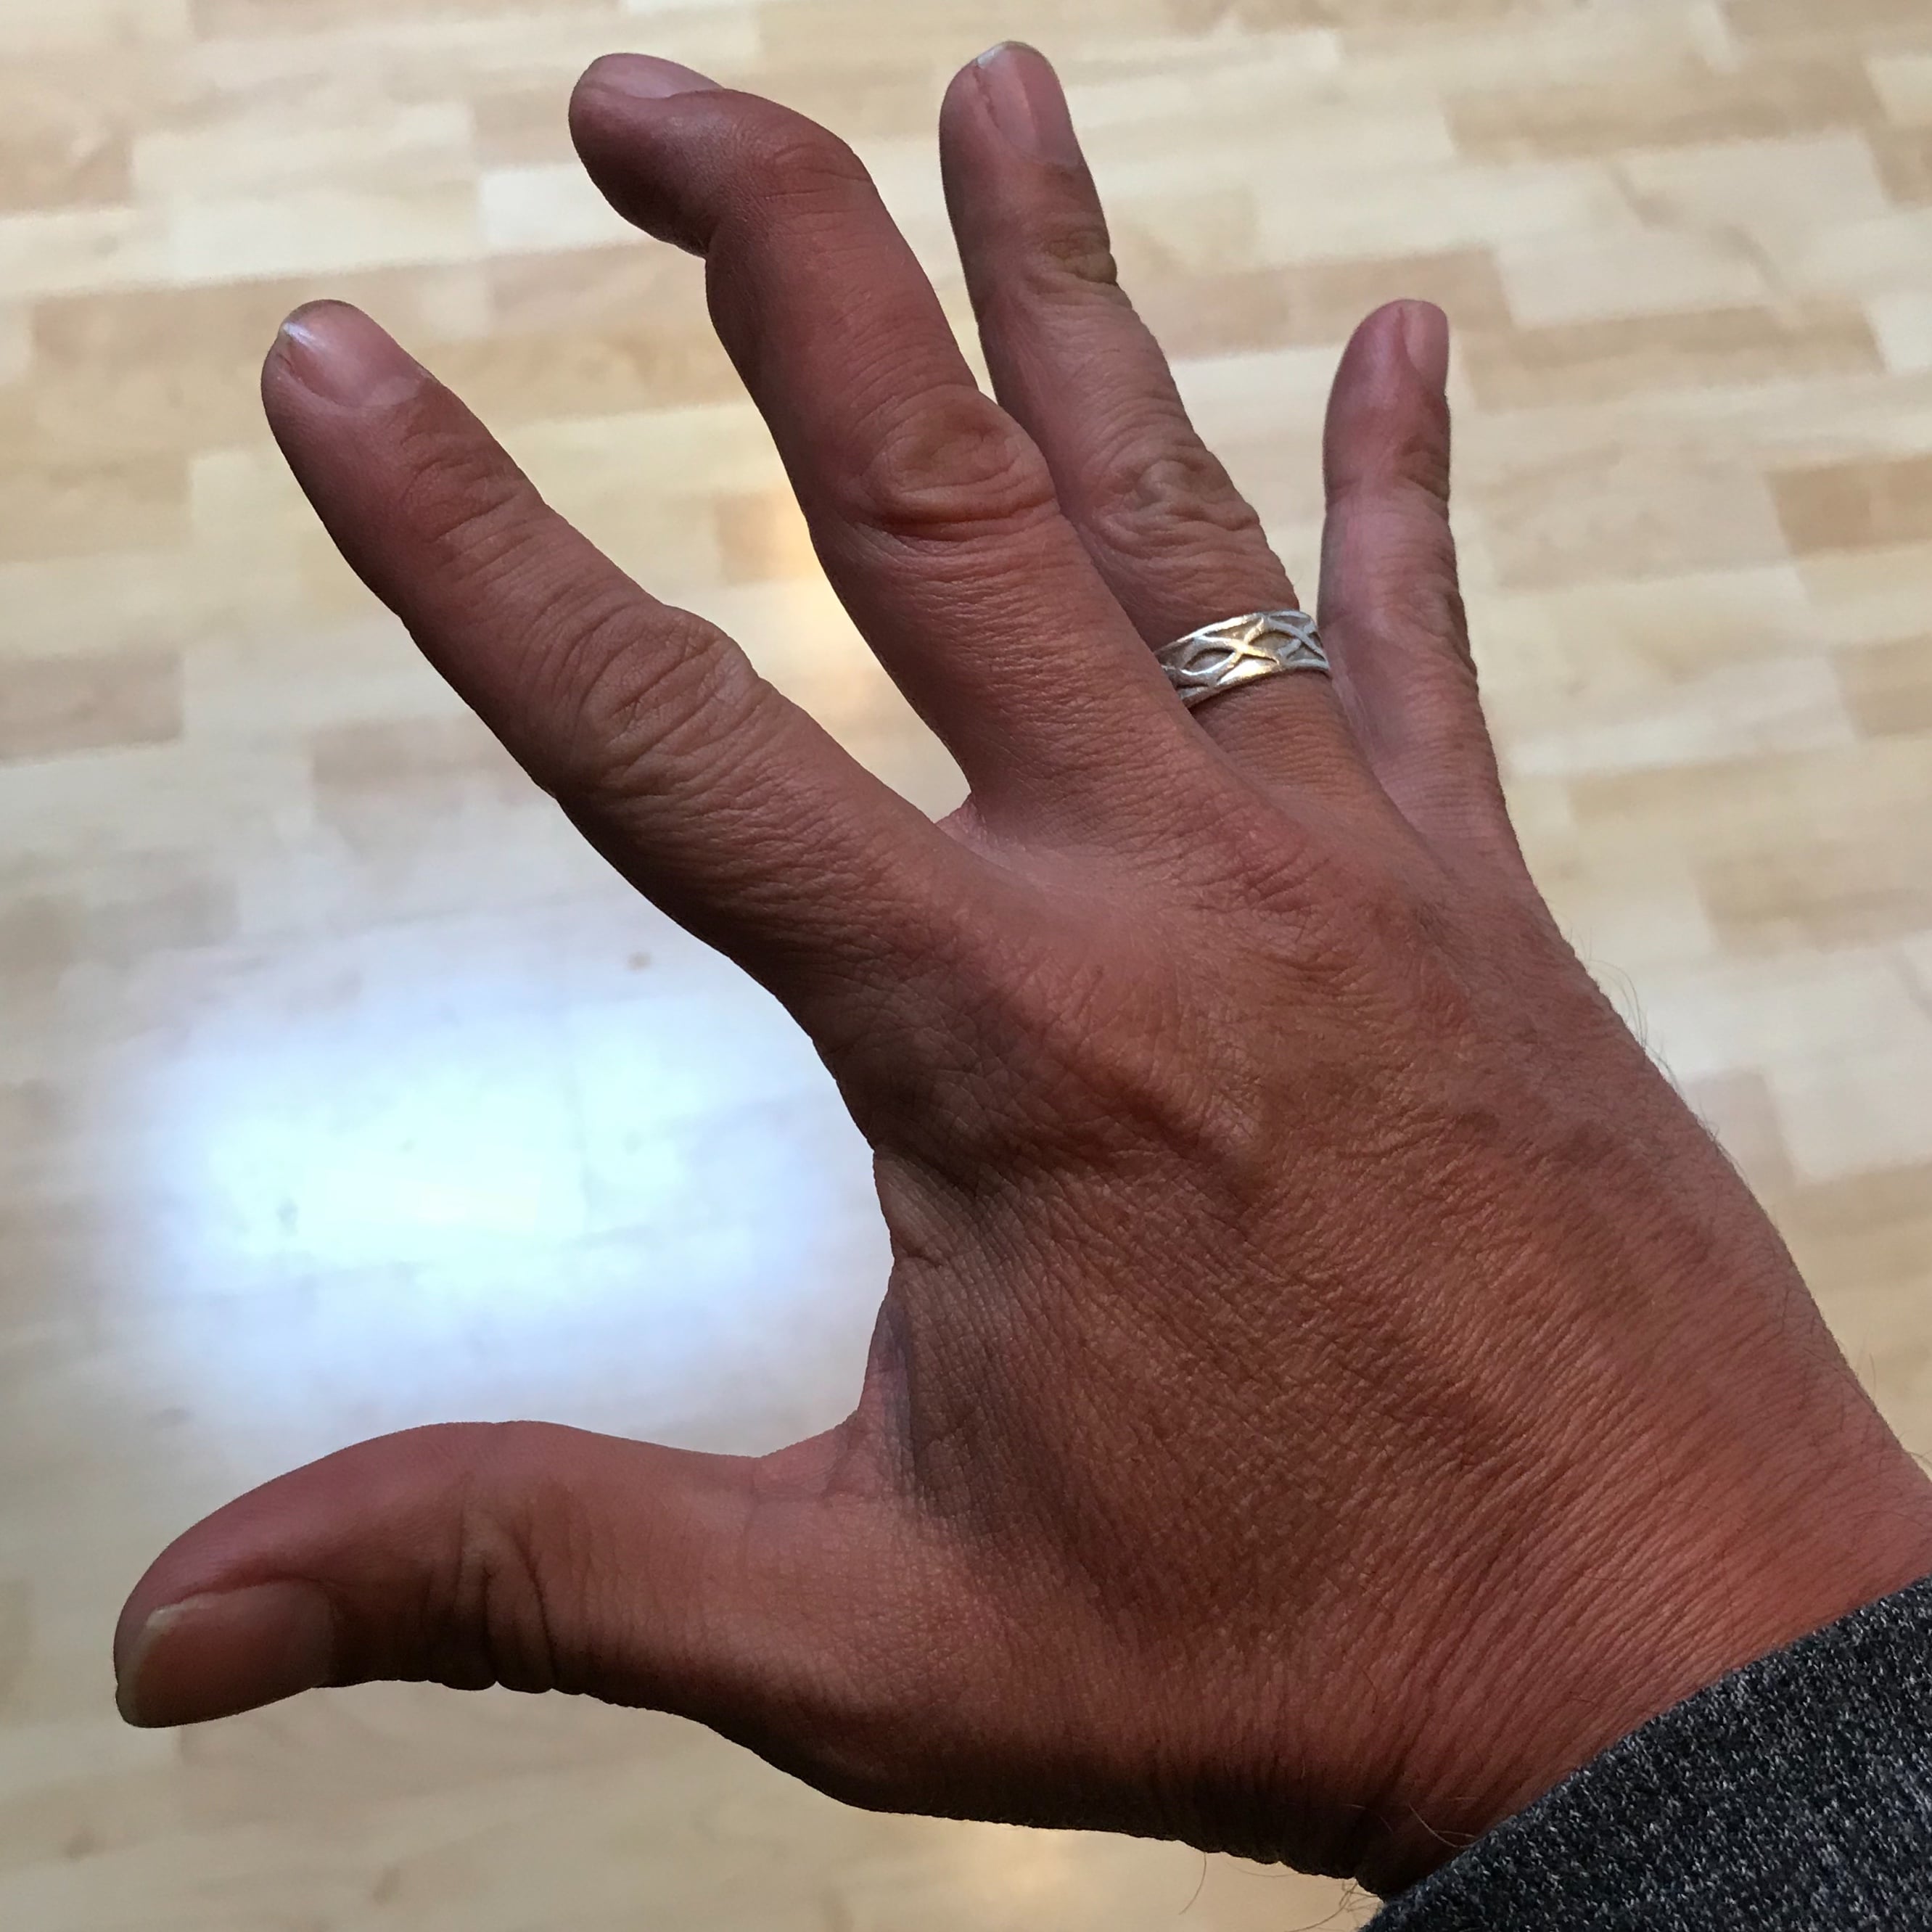
The classic presentation is a patient who jammed the tip of an extended finger and now cannot straighten the last joint. The fingertip droops into flexion and will not actively lift, although it can be passively pushed straight. The typical patient is a young athlete after a ball-sport injury, or an older adult after a trivial knock such as tucking in a bedsheet.
History. Three answers shape the plan: the mechanism, jamming or laceration; the timing, acute at less than 4 weeks or chronic beyond it; and the occupation, since a surgeon or musician needs a perfect glide while a labourer needs a stable union. Late presentation beyond 4 weeks can still be treated with splinting.
Examination. Look for the drooping DIPJ, with erythema, dorsal swelling, tenderness and bruising over the joint in the acute injury, and in a bony mallet a palpable step or fragment. Active extension is lost, the lag; passive extension is full, which rules out a locked joint or a fracture block. Check the PIPJ for hyperextension, the beginning of a swan neck, and look for any laceration so that a Type II is not missed. Always document the rotational alignment of the finger.
Red flags. Any skin breach, which makes this an open Type II or III injury; a flexed, bleeding fingertip in a child, which is a Seymour fracture; and a developing swan-neck posture at the PIPJ.
Investigations
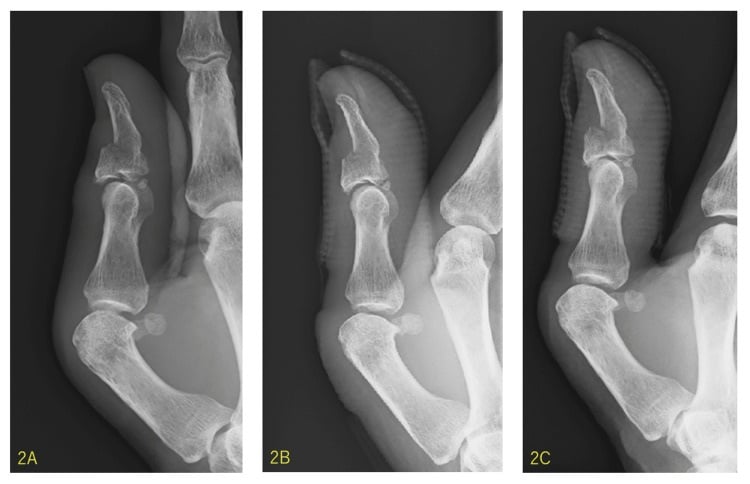
Radiographs. A PA and a true lateral of the finger. The true lateral is essential for assessing joint congruency. Three findings to report:
- Avulsion - a triangular fragment from the dorsal base of P3
- Subluxation - volar subluxation of P3 relative to the P2 head, which is a surgical indication
- Apposition - the gap between the fragment and the bone
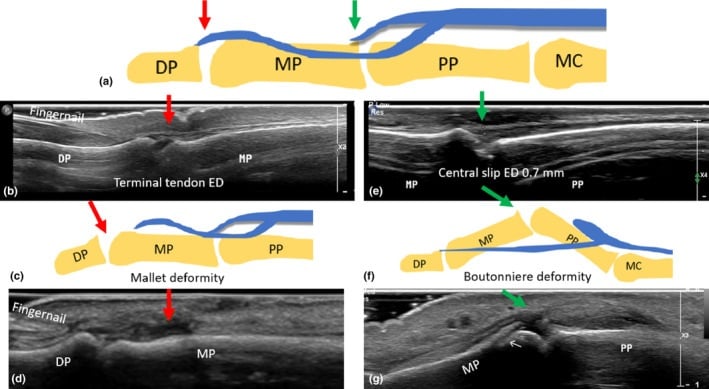
Ultrasound. Long-axis ultrasound can show the terminal tendon insertion and distinguish an intact tendon from a retracted or wavy terminal slip in mallet deformity.
Mallet Thumb
The thumb has its own, much rarer, version of the injury, mallet thumb, which examiners like to contrast with the finger lesion.
The tendon is different. Extension of the thumb IP joint is driven by the terminal insertion of extensor pollicis longus (EPL). A mallet thumb is therefore an EPL terminal disruption, a closed avulsion, a laceration or a bony avulsion of the dorsal distal phalanx, producing an IP-joint extension lag.
Splinting is less reliable. Unlike the finger's thin terminal slip, EPL has a strong, more proximal muscle belly with greater excursion that tends to retract a ruptured tendon. Closed extension splinting is therefore less reliable and there is a lower threshold for primary repair, particularly for open injuries and displaced bony fragments.
Otherwise the principles are the same. A true lateral radiograph, attention to joint congruency and subluxation, and IP extension immobilisation for stable closed or undisplaced bony injuries.
Differential Diagnosis
The "drooped fingertip" is not always a terminal extensor injury. Distinguishing these saves a patient from being splinted for a problem a splint cannot fix.
- Key distinguishing feature
- Extension lag, jamming mechanism
- Passive DIPJ extension
- Full
- Pitfall
- Missing an associated open laceration (Type II)
- Key distinguishing feature
- Avulsion fragment or physeal widening on X-ray
- Passive DIPJ extension
- Full unless blocked
- Pitfall
- Treating a Seymour fracture as a simple closed mallet
- Key distinguishing feature
- Extensor tendon subluxes off MCPJ; lag at MCPJ not DIPJ
- Passive DIPJ extension
- N/A (MCPJ problem)
- Pitfall
- Confusing extensor lag location
- Key distinguishing feature
- Loss of active DIPJ flexion, not extension
- Passive DIPJ extension
- Full
- Pitfall
- Mixing up the flexed-droop with a flexion-loss injury
- Key distinguishing feature
- Pain and mechanical block on passive extension
- Passive DIPJ extension
- Restricted / blocked
- Pitfall
- Forcing a splint onto a joint that cannot passively extend
- Key distinguishing feature
- Palpable cord, no acute injury
- Passive DIPJ extension
- Restricted
- Pitfall
- Attributing chronic contracture to a recent jam
Management
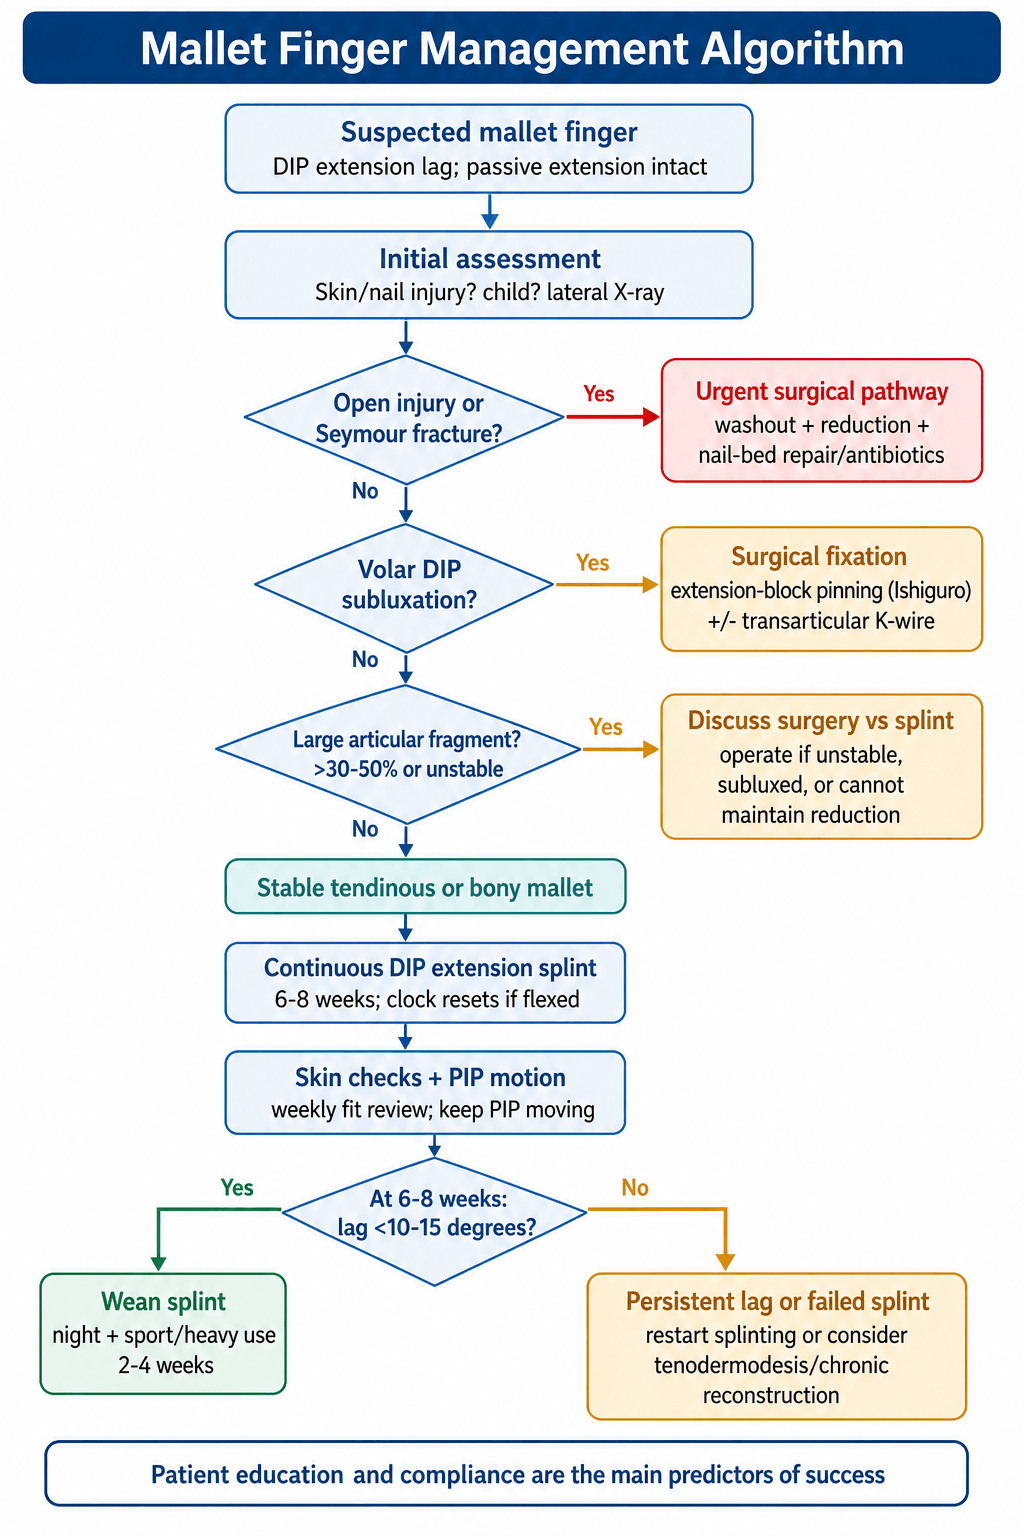
The decision. Almost every mallet finger, tendinous or bony, is treated in a splint; the indications for surgery are few and are listed under Surgery. Congruency of the joint, rather than the size of the fragment alone, drives the decision.
- Pathology
- Tendon Rupture
- Treatment
- Splint 6-8w
- Prognosis
- Good
- Pathology
- Avulsion #
- Treatment
- Splint 6w (Bony union fast)
- Prognosis
- Good (Remodels)
- Pathology
- Volar Subluxation
- Treatment
- Surgery (Ishiguro)
- Prognosis
- Variable (OA risk)
- Pathology
- Scarred/Long
- Treatment
- Re-splint or Tenotomy
- Prognosis
- Fair
Who. Type I, II, III and stable Type IVb injuries.
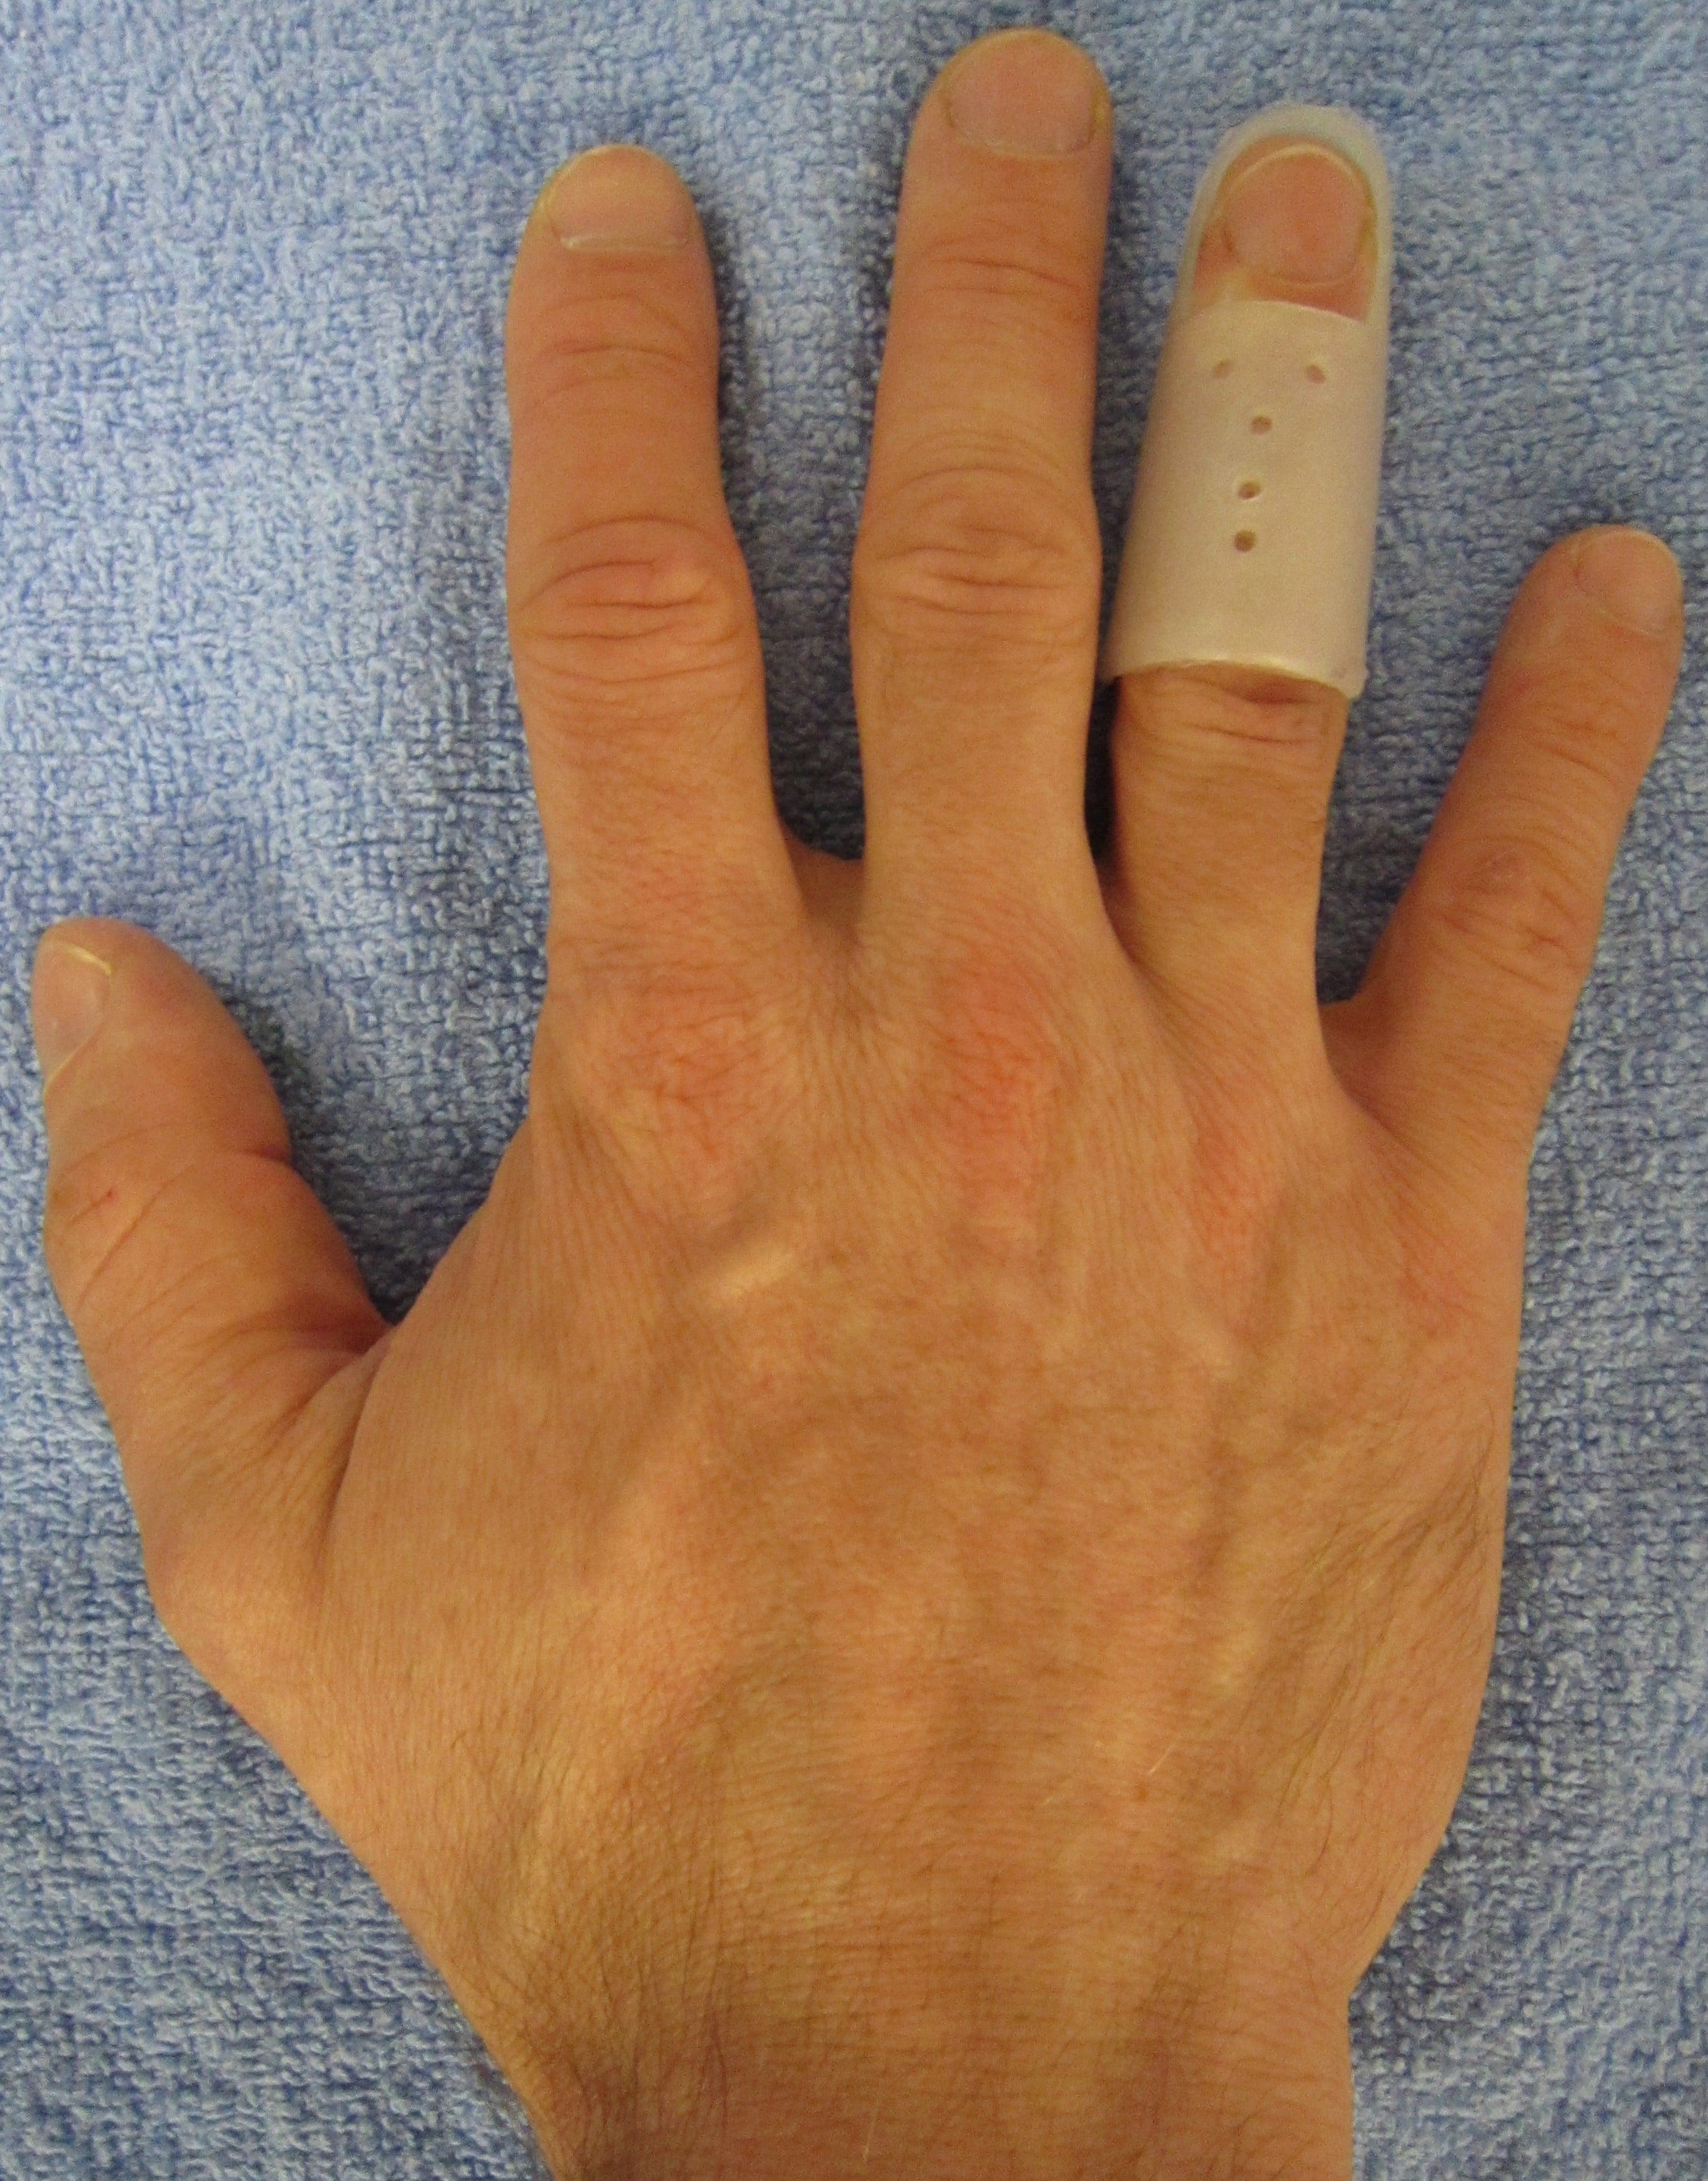
The protocol. The DIPJ is held in continuous extension for 6-8 weeks; if the joint flexes once, the clock resets. Weaning then takes 2-4 weeks, with the splint worn at night and for sport and heavy use. The splint is an off-the-shelf Stack splint or a custom thermoplastic one; the crucial requirement is uninterrupted approximation of the terminal tendon without excessive dorsal pressure or forced hyperextension, with the PIPJ left free.
The skin. The dorsal skin over the DIPJ is extremely thin, and a tight splint, especially a dorsal splint or a taped Stack, can cause pressure necrosis that turns a closed, simple injury into a complex soft-tissue defect. Instruct the patient to clean the finger daily while it is supported in extension, check the splint for blanching points, and use a slightly looser splint with perforations for aeration.
Outcome. 80-90% succeed. A lag of 5-10 degrees is common afterwards and is functional. Patient education is the single most important factor in success.
Surgical Technique
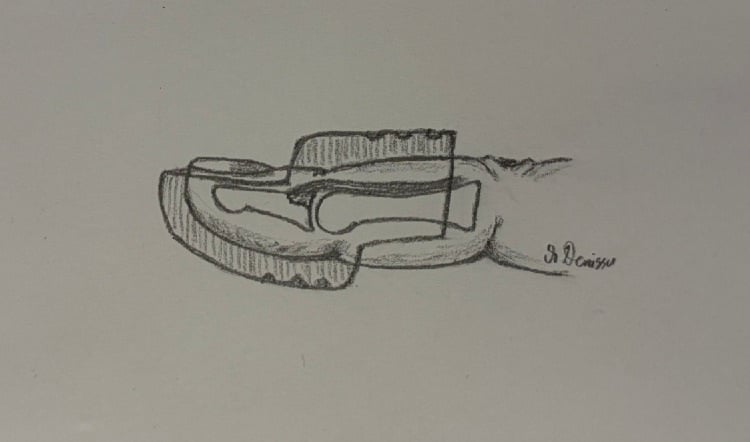
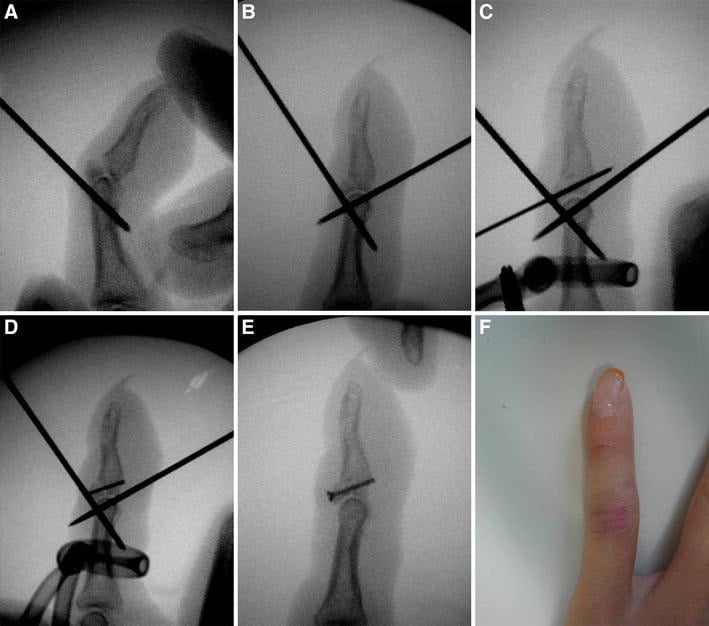
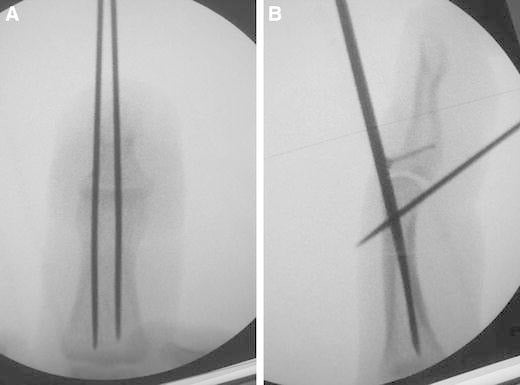
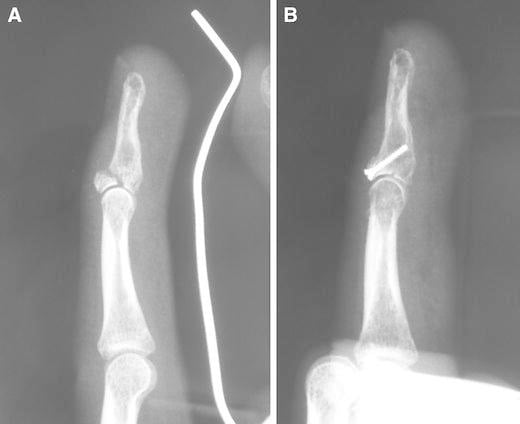
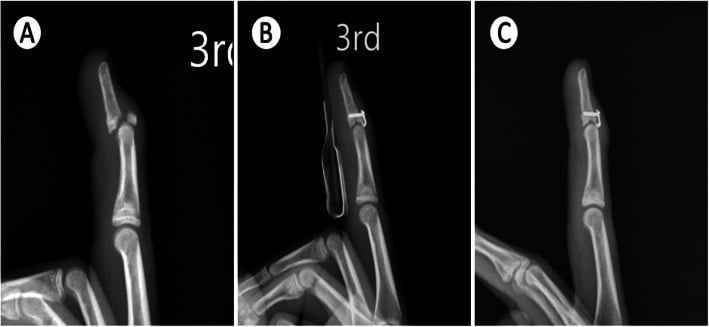
Extension block pinning. The P2 head is used as a backstop:
- Flex the DIPJ and insert a 1.0mm K-wire into the distal P2 head, aimed dorsally
- Extend the DIPJ; the fragment hits the wire and is reduced onto the P3 base
- Insert a second longitudinal K-wire across the DIPJ to lock the joint
The blocking wire must be placed dorsal to the fracture fragment. The technique is percutaneous with no dissection; its costs are pin track infection and wire migration.
Chronic Mallet: Beyond Tenodermodesis
Tenodermodesis is one option for the chronic symptomatic mallet, but examiners expect two further named procedures, especially once a swan-neck deformity has developed.
Fowler central slip tenotomy. The simpler operation, for the chronic mallet that has produced, or threatens, a swan-neck deformity with a supple PIP joint. The central slip is divided over the proximal part of the middle phalanx, releasing the proximal extensor tether so that more extensor force is transmitted distally to the terminal tendon; the DIP lag improves while the hyperextended PIP drops back. A small residual PIP extensor lag of around 10-15 degrees is accepted; a true boutonniere is the feared over-correction.
Oblique retinacular ligament (Spinner-Choi) reconstruction. A tendon graft, a lateral band or a free graft, is routed from the volar proximal phalanx, volar to the PIP axis, to the dorsal distal phalanx. Acting as a dynamic tenodesis it simultaneously extends the DIP and restrains PIP hyperextension, so a single operation addresses both components of the mallet-driven swan neck.
Joint-level salvage. A painful, arthritic or grossly unstable chronic DIP is often best treated by DIP arthrodesis rather than soft-tissue reconstruction.
Complications
Skin necrosis from a tight splint is the most common complication. Nail deformity is ridging from injury to the germinal matrix by the splint or the fracture. Recurrence occurs if the splint is removed too early.
Stiffness is loss of flexion, and it is often worse than the original 10-degree lag: most patients adapt well to a minor lag, but cannot adapt to a stiff, painful joint. Septic arthritis can follow a pin track infection. Hypersensitivity at the fingertip is common and needs desensitisation therapy.
Rehabilitation
- Splint in strict extension (0 degrees), in contact with the dorsal DIPJ 24 hours a day
- Clean the finger with it supported in extension, using a supporting finger or the splint
- Active PIPJ flexion and extension, which prevents stiffness and swan neck progression
- Check the splint fit weekly for blanching and pressure marks
- Explain that one flex episode resets the clock
- Measure active extension; if the lag is under 10 degrees, proceed
- Start gentle active flexion, 20-30 degrees at first, increasing by 10 degrees a week
- Continue the splint at night and for heavy tasks and sport
- Expect full DIPJ flexion by 10-12 weeks
- Putty exercises and grip strengthening
- Unrestricted activity by 12-16 weeks
- A slight recurrence of lag is common and acceptable; if it exceeds 15 degrees, restart a 2-week splint protocol
- Scar massage, and desensitisation if the tip is hypersensitive
Prognosis
After splinting. Satisfaction is high, especially in compliant patients, and 85% return to their pre-injury occupation. Compliance is the single most important predictor of outcome; late presentation still responds to splinting; younger patients heal faster while the elderly have thinner skin, a necrosis risk; diabetes and smoking impair tendon healing.
After surgery. Success runs at 70-80%, because the higher complication rate offsets the benefits: nail deformity in 15%, infection in 5-10%, stiffness in 20%. Surgery is reserved for subluxed joints or failed splinting.
- Good Prognosis
- Type I (Tendinous)
- Poor Prognosis
- Type III (Skin loss)
- Good Prognosis
- Small (under 30%)
- Poor Prognosis
- Large (over 50%) + Subluxed
- Good Prognosis
- Excellent
- Poor Prognosis
- Poor (repeated flexion)
- Good Prognosis
- Acute (under 4 weeks)
- Poor Prognosis
- Chronic (over 12 weeks)
- Good Prognosis
- Congruent
- Poor Prognosis
- Subluxed (volar)
Three principles. A bony mallet heals better than a tendinous one, bone-to-bone rather than tendon-to-bone. A persistent radiographic gap does not correlate with function: treat the patient, not the X-ray. A swan neck corrects when the mallet is treated early.
At five years. 90% have full function in grip, pinch and dexterity. Pain is rare; if present, suspect OA or a swan neck. Re-injury risk is low once healed, though a protective splint may be needed for contact sports.
Return to activity.
- Desk work - 1-2 weeks, in the splint
- Manual work - 8-12 weeks
- Non-contact sport - 10-12 weeks
- Contact sport - 12-16 weeks, with protective splinting recommended initially
Refer back for a progressive lag despite compliance, a developing swan neck, persistent pain at 8-12 weeks, or significant functional limitation. Most patients return to full function with minimal residual lag.
Guidelines, Registries & Global Practice
Global Epidemiology
- Mallet finger is among the most common closed tendon injuries of the hand, with a recognised peak in young men (sport-related forced flexion) and a second peak in older women (low-energy domestic injury, often involving thin dorsal skin).
- Typical mechanisms worldwide: ball-sports (basketball, volleyball, cricket, baseball, netball), bedmaking/tucking sheets, and catching a digit on clothing.
- The long, middle and ring fingers of the dominant hand are most often affected; bony mallet fractures account for a substantial minority of cases.
Side-by-Side Guideline Comparison
- First-line
- Continuous DIPJ extension splint 6-8w
- Surgical threshold
- Open injury, volar subluxation, large displaced fragment
- Notable emphasis
- Hand-therapy-led pathways, patient education
- First-line
- Extension splinting for most closed injuries
- Surgical threshold
- Subluxation or large articular fragment
- Notable emphasis
- Acceptance of small residual lag; shared decision-making
- First-line
- Splint for stable injuries
- Surgical threshold
- Unstable/subluxed fractures - extension block pinning or ORIF
- Notable emphasis
- Closed extension block (Ishiguro) as workhorse technique
- First-line
- Splint-first universally
- Surgical threshold
- Subluxation, open, failed conservative care
- Notable emphasis
- Adapting splint type to local resources
The striking feature is convergence: every major society recommends splint-first management and reserves surgery for volar subluxation, open injury, or selected large fragments. The genuine area of disagreement is the exact articular-percentage threshold (one-third versus one-half).
Registry and Outcome Notes
- There is no dedicated arthroplasty/implant registry for mallet finger, as the injury is rarely implant-based. Outcome evidence derives from RCTs, cohort series and the Cochrane review rather than national registries.
- Reported splinting success rates cluster around 80-90% acceptable outcome, with a residual extension lag of roughly 5-10 degrees that is usually functionally and cosmetically well tolerated.
High- vs Limited-Resource Practice
- Well-resourced settings: custom thermoplastic or perforated splints fabricated by hand therapists, structured education, and ready access to percutaneous pinning for subluxed fractures.
- Limited-resource or remote settings: off-the-shelf Stack splints, aluminium-foam splints, or simple thermoplastic; telehealth-supervised splinting protocols have been shown to be safe and effective where in-person therapy is scarce.
- Antibiotics for open injuries: open mallet injuries and Seymour fractures are treated as open fractures - urgent debridement plus a first-generation cephalosporin (e.g. cephalexin) with anti-staphylococcal cover, a recommendation consistent across guidelines and supported by the Seymour fracture literature.
Controversies and Areas of Uncertainty
Mallet finger looks simple, but several common viva questions sit on genuinely unsettled ground, and knowing what is not proven is as important as knowing the protocol.
The articular-percentage threshold. The "one-third rule" for surgery is a teaching convention, not a validated cut-off. Reviews note that size alone has never reliably predicted who benefits from surgery; congruency, the absence of volar subluxation, is the more defensible determinant.
Surgery versus splinting for the displaced bony mallet. The Cochrane review found no high-quality evidence that surgery outperforms splinting, even for larger fragments, while surgery adds infection and nail-deformity risk. Many surgeons still operate on subluxed joints, but the benefit is assumed rather than proven.
Splint type and duration. No splint design has been shown clearly superior; 6 versus 8 weeks and the weaning schedule rest on tradition and small trials, not robust RCTs.
The persistent radiographic gap. A residual fracture gap or incomplete reduction frequently coexists with excellent function, a strong argument for treating the patient, not the X-ray.
Patient selection for extension block pinning. Long dorsal-cortex fragments and older patients do worse after extension block pinning, which suggests morphology-based selection rather than one technique for all.
MCQ Practice Points
Q: What structure balances the lateral bands and prevents volar subluxation? A: The Triangular Ligament.
Q: What is the primary cause of Swan Neck deformity in chronic mallet finger? A: Proximal retraction of the extensor apparatus causing increased tension on the central slip.
Q: What is the most common complication of surgical treatment for mallet finger? A: Nail deformity (ridging) and infection.
Q: A patient wearing a stack splint complains of dorsal pain and white skin. What is the action? A: Adjust/Replace splint immediately (Risk of necrosis).
Q: What percentage of articular surface involvement indicates surgery for bony mallet? A: Greater than 30-50% WITH volar subluxation. Size alone is NOT an indication - congruency is key.
Q: How long should a mallet finger be splinted? A: 6-8 weeks continuous extension, then 2-4 weeks weaning. Clock resets if finger flexes.
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 30-year-old presents 4 months after a mallet injury. He ignored it. Now has a 40 degree lag and finds it catchy. Examination shows a Swan Neck deformity. Management?”
“X-ray shows a mallet fracture with a fragment involving 40% of the articular surface. The joint is congruent (no subluxation). What do you do?”
“A 7-year-old crushes his finger. The nail plate is avulsed proximally (lying on top of the fold). The tip is flexed. X-ray shows a physeal widening.”
“A 65-year-old diabetic presents 3 weeks into splint treatment for a mallet finger. She has a 1cm area of full thickness skin necrosis over the dorsal DIPJ. The underlying tendon is exposed. What is your management?”
Classification
- Type I: Tendon (Splint)
- Type II: Laceration (Wash/Repair)
- Type III: Coverage loss (Flap)
- Type IV: Bony (Splint unless subluxed)
Management
- Splint: 6-8 weeks straight
- Surgery: If Subluxed or greater than 50%
- Tech: Ishiguro Pinning
- Chronic: Tenodermodesis
Complications
- Skin Necrosis (Splint)
- Nail Ridge (Surgery)
- Stiffness
- Recurrence
Evidence Base
Cochrane Review: Interventions for Treating Mallet Finger
- Four randomised/quasi-randomised trials, 278 participants with 283 mallet injuries
- Three trials compared different finger splints versus a standard Stack splint
- One RCT found no significant difference between Kirschner-wire fixation and a Pryor-and-Howard splint, with similar complication rates
- All trials were methodologically flawed; insufficient evidence to define when surgery is indicated
Diagnosis and Management of Mallet Finger Injuries
- Narrative review of epidemiology, diagnosis and management focused on surgical indications
- Non-operative management is advocated for almost all mallet injuries
- Surgery is generally reserved for fractures involving more than one-third of the articular surface and for volar subluxation of the distal phalanx
- A clear advantage of surgery even in these complex cases has not been proven