The Labourer's Nerve (Coarse Power and Sensation)
- Formed by Lateral (C5-7) and Medial (C8-T1) Cords
- Runs MEDIAL to Brachial Artery in Cubital Fossa (TAN: Tendon, Artery, Nerve)
- Supplies Flexor Compartment of Forearm (Except FCU + Ulnar 1/2 FDP)
- Supplies LOAF muscles in hand (Lumb 1/2, Opponens, APB, FPB-sup)
- Sensation to Radial 3.5 digits (Palmar)
- “Hand of Benediction (High Median) is an ACTIVE sign (trying to fist)
- “Ulnar Claw (Low Ulnar) is a PASSIVE sign (at rest)
- “Palmar Cutaneous Branch is SPARED in Carpal Tunnel (arises proximal)
- “AIN is purely MOTOR (No sensory loss, just 'OK' sign fail)
Overview
The median nerve is the "eye of the hand", because it carries sensation from the thumb and index finger, and the "labourer's nerve", because it drives power grip through FDS, FDP and the thenar muscles. Its compression at the wrist, carpal tunnel syndrome, is the most common entrapment neuropathy; the two proximal syndromes, pronator syndrome and anterior interosseous nerve palsy, are recognised by what they take away.
Anatomy and Course
Formation and the arm. The nerve is formed by the fusion of the lateral cord (C5-7) and the medial cord (C8-T1) and gives no branches in the arm. It runs with the brachial artery, lateral to it at first and then crossing to lie medial to it. Because nothing leaves it above the elbow, a high lesion spares nothing below.
The ligament of Struthers. In the 1% of the population with a supracondylar spur on the humerus, visible on plain radiographs, a ligament runs from the spur to the medial epicondyle and the median nerve passes under it, where it can be compressed. Do not confuse it with the arcade of Struthers, which belongs to the ulnar nerve.
The cubital fossa. From lateral to medial the fossa holds the biceps tendon, the brachial artery and the median nerve, so the nerve lies medial to the brachial artery. It passes under the bicipital aponeurosis (lacertus fibrosus), which arises from the biceps tendon, inserts into the ulna and covers both the nerve and the artery; in bodybuilders or labourers a thickened lacertus can compress the nerve and mimic pronator syndrome, which is lacertus syndrome. The nerve then enters the forearm between the two heads of pronator teres, the site of pronator syndrome. It is vulnerable at each of these fibrous arches.
TANCubital Fossa Contents
Hook:TAN your arm from Lateral to Medial.
The forearm. The nerve supplies the flexor compartment of the forearm except FCU and the ulnar half of FDP. Motor branches go to pronator teres, FCR, palmaris longus and FDS, and the main trunk continues deep to FDS. The anterior interosseous nerve (AIN) leaves 5-8 cm distal to the lateral epicondyle, runs on the interosseous membrane and is purely motor, carrying only joint proprioception and no cutaneous sensation; it supplies FPL, FDP to the index and middle fingers and pronator quadratus. The palmar cutaneous branch arises about 5 cm proximal to the wrist crease and runs superficial to the flexor retinaculum to supply the thenar eminence and proximal palm.
The branches, in order from the elbow to the palm:
- Level
- Arm
- Function
- None
- Clinical Relevance
- High palsy spares nothing below
- Level
- Elbow
- Function
- Pronation
- Clinical Relevance
- First motor branch
- Level
- Proximal Forearm
- Function
- Wrist Flexion
- Clinical Relevance
- Tendon transfer donor
- Level
- Proximal Forearm
- Function
- Fascia tensor
- Clinical Relevance
- Graft harvest
- Level
- Mid Forearm
- Function
- PIP Flexion
- Clinical Relevance
- Independent function
- Level
- Mid Forearm
- Function
- DIP/IP Flexion
- Clinical Relevance
- OK Sign / Pinch
- Level
- Distal Forearm
- Function
- Palm Sensation
- Clinical Relevance
- Spared in CTS
- Level
- Hand (Tunnel)
- Function
- Thenar Motor
- Clinical Relevance
- Million Dollar Nerve
- Level
- Hand
- Function
- Sensation 3.5
- Clinical Relevance
- Numbness in CTS
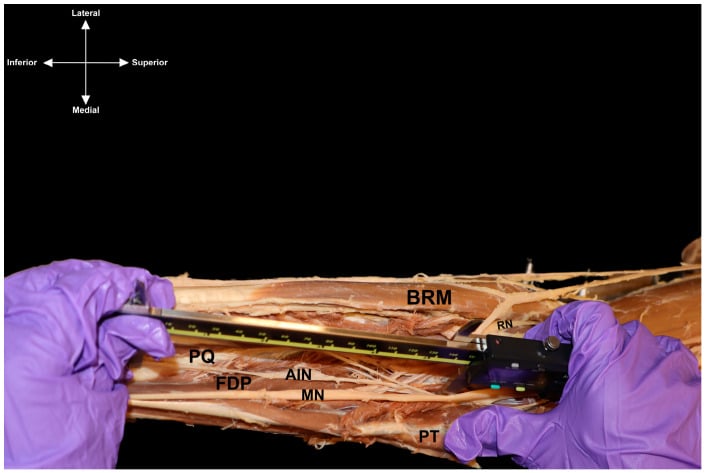
The carpal tunnel. An osseofibrous canal, and the examiner expects its walls, not just its contents:
- Roof: the flexor retinaculum (transverse carpal ligament), spanning the carpal arch
- Floor and sides: the concave arch of the carpal bones
- Radial attachments of the retinaculum: the tubercle of the scaphoid and the ridge of the trapezium
- Ulnar attachments: the pisiform and the hook of the hamate
It transmits 10 structures: the median nerve, deep to the retinaculum, and 9 flexor tendons (4 FDS, 4 FDP, 1 FPL). Guyon's canal lies superficial and ulnar to the retinaculum and is a separate compartment, so the ulnar nerve is not in the carpal tunnel. Because the canal is a rigid box, anything that raises its volume (tenosynovitis, a mass, fluid in pregnancy) or reduces its capacity (a distal radius malunion) raises the pressure on the nerve.
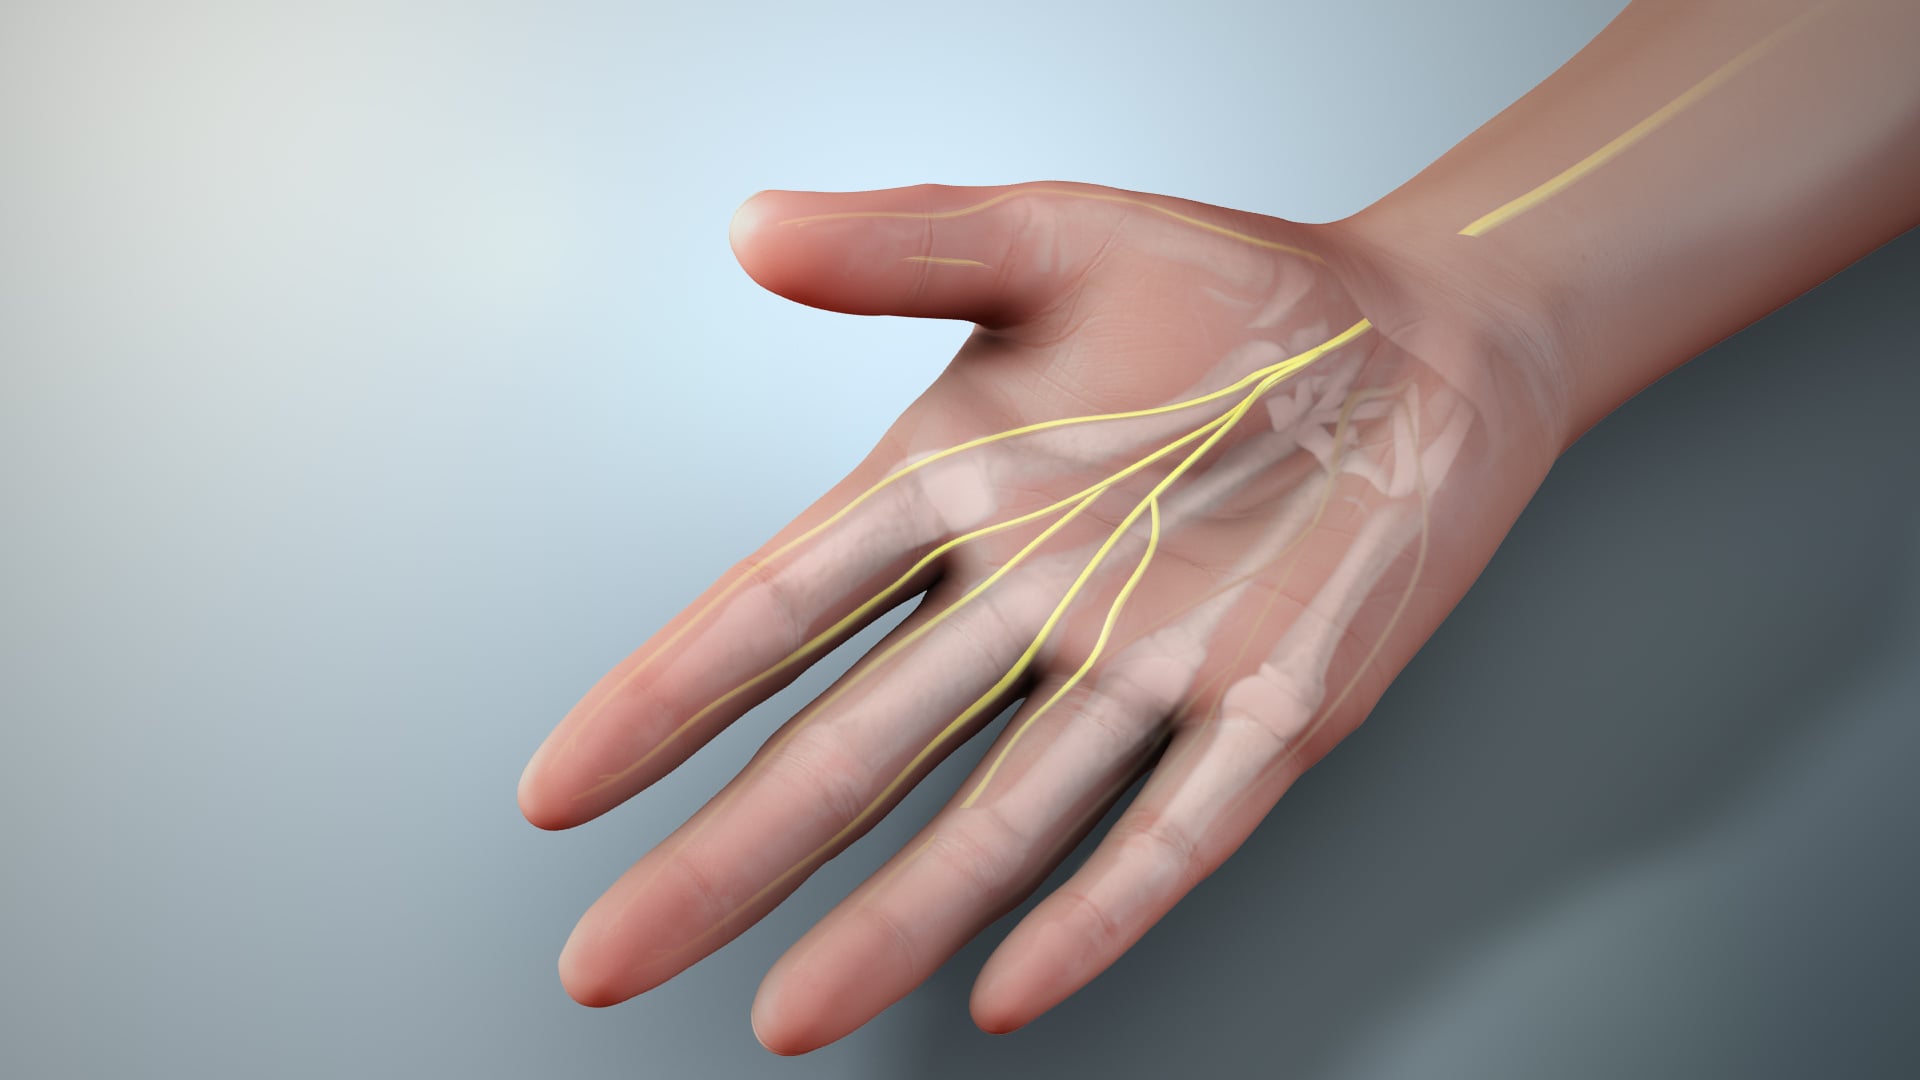
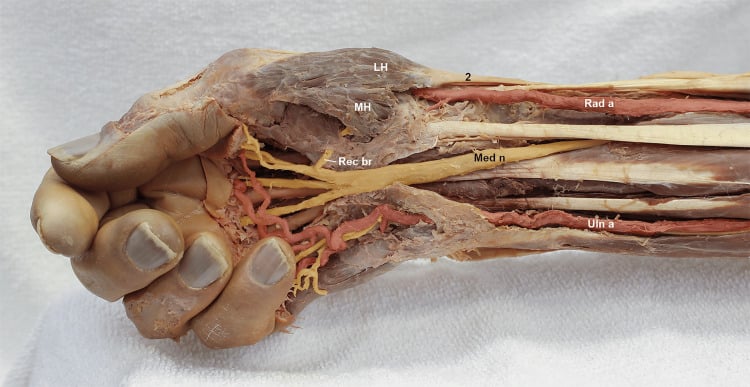
The hand. The recurrent motor branch, the "million dollar nerve", curves back from the tunnel to supply the thenar muscles: opponens pollicis, abductor pollicis brevis and the superficial head of flexor pollicis brevis. Its relation to the transverse carpal ligament varies, and it can pass through the ligament itself, which is why it demands caution in surgery. The digital nerves carry sensation from the thumb, index, middle and radial half of the ring finger and motor fibres to the first and second lumbricals; they are at risk during endoscopic release and trigger finger release.
LOAFThenar Muscles (LOAF)
Hook:The loaf of bread in your hand.
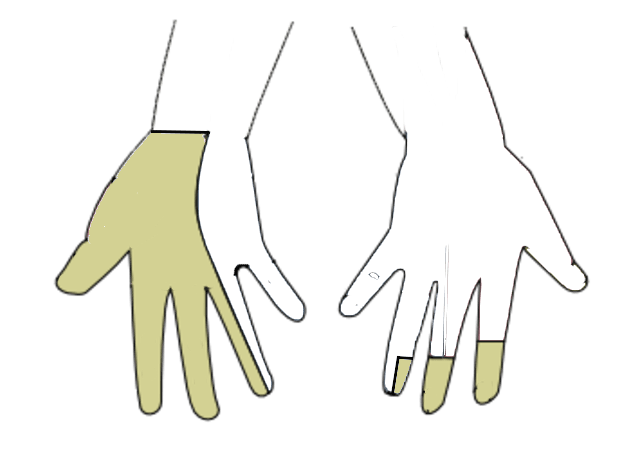
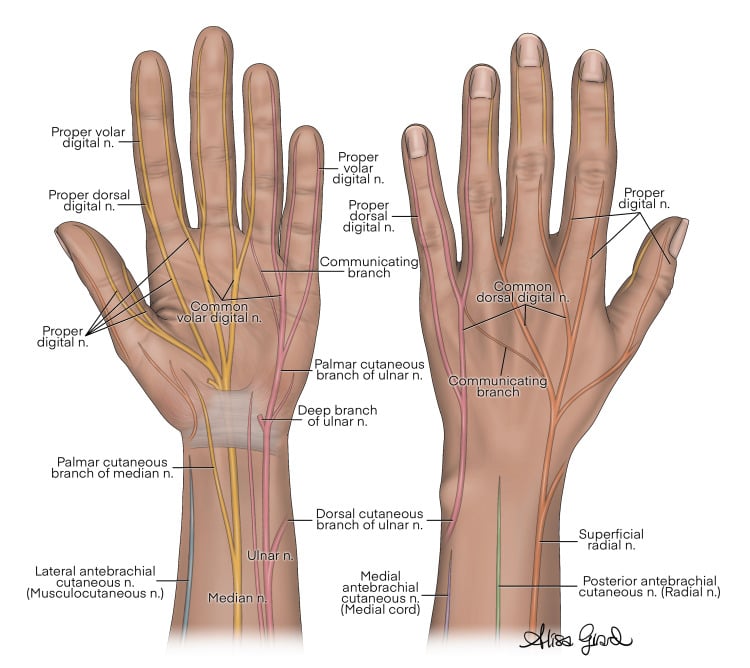
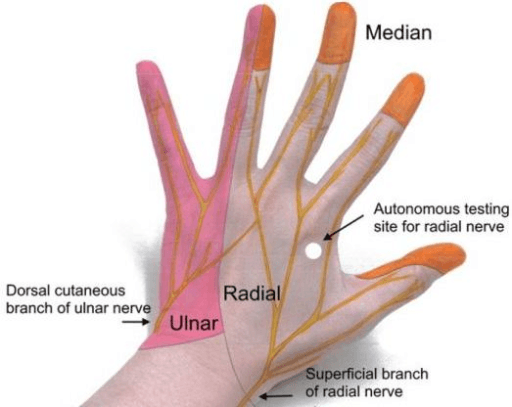
Sensory territory. The palmar surface of the thumb, index, middle and radial half of the ring finger, the dorsal aspects of their fingertips, and the thenar palm through the palmar cutaneous branch. The little finger is ulnar.
Classification Systems
Carpal tunnel syndrome is graded by neurophysiology. The sensory response goes first, the motor response follows, and denervation on EMG marks the severe grade:
- Sensory (SNAP)
- Slowed / Reduced Amp
- Motor (CMAP)
- Normal
- EMG
- Normal
- Sensory (SNAP)
- Absent / Severe Slowing
- Motor (CMAP)
- Delayed Latency
- EMG
- Normal / Mild changes
- Sensory (SNAP)
- Absent
- Motor (CMAP)
- Reduced Amp / Absent
- EMG
- Denervation (Fibs/Pos waves)
Clinical Assessment
Where is the lesion. Carpal tunnel syndrome wakes the patient at night with paraesthesia in the radial three and a half digits, and Phalen's test is positive. Pronator syndrome gives pain and paraesthesia that are activity related rather than nocturnal, with Tinel's sign in the proximal forearm; numbness that includes the palm points to a lesion proximal to the tunnel, because the palmar cutaneous branch is spared in carpal tunnel syndrome. Anterior interosseous nerve syndrome is a deep forearm ache with weakness and no sensory loss at all.
- Night Pain
- Yes (Classic)
- Sensory Loss
- Digits 1-3.5
- Motor Weakness
- APB (Thenar)
- Night Pain
- Rare (Activity related)
- Sensory Loss
- Palm + Digits
- Motor Weakness
- FPL/FDP/APB
- Night Pain
- Deep forearm ache
- Sensory Loss
- None
- Motor Weakness
- FPL/FDP (OK sign)
- Night Pain
- Neck pain
- Sensory Loss
- Thumb/Index (Dermatome)
- Motor Weakness
- Biceps/Wrist Ext
Hand of benediction, high median palsy. The sign appears when the patient tries to make a fist. FDS and the FDP to the index and middle fingers are paralysed, so those fingers cannot flex; the FDP to the ring and little fingers is ulnar and still works, so those fingers flex. The index and middle stay straight while the others curl. It is an active sign.
Ulnar claw, low ulnar palsy. The sign is there at rest. The intrinsics (third and fourth lumbricals, interossei) are paralysed, so EDC hyperextends the MCP joints and FDP flexes the IP joints of the ring and little fingers. It is a passive sign.
Provocative tests. Phalen's test holds the wrist flexed for 60 seconds and is positive when paraesthesia is reproduced in the digits; reverse Phalen's holds the wrist extended, which raises the pressure even more. Tinel's sign is percussion over the nerve: at the wrist it points to carpal tunnel syndrome, at the proximal forearm or elbow to pronator syndrome. Durkan's test is direct compression over the tunnel for 30 seconds and is the most sensitive test for carpal tunnel syndrome.
- Sensitivity
- 89%
- Specificity
- 90%
- Notes
- Most accurate manual test
- Sensitivity
- 68%
- Specificity
- 73%
- Notes
- Less specific in elderly
- Sensitivity
- 50%
- Specificity
- 77%
- Notes
- Great for tracking axon regeneration
Motor testing. Each muscle has its own test, and the examiner wants the instruction you give the patient:
- OK sign (Kiloh-Nevin), for the AIN: ask for an 'O' between thumb and index. Normal is a tip-to-tip pinch with FPL and FDP active; in AIN palsy FPL and FDP have failed, adductor and FDS compensate, and the pinch becomes pulp-to-pulp, the "tear drop" or posterior pinch
- Abduction, for APB: "touch the ceiling"; palpate the muscle belly to exclude a trick movement from PL or EPL
- Opposition, for opponens: "touch the pin to your thumb"
- FDS: hold the other fingers in extension
- FDP: hold the PIP joint in extension
Sensory testing. The autonomous zone is the tip of the index finger. Sensation splits along the ring finger, the radial half being median. Numbness of the palm proximal to the wrist crease is palmar cutaneous branch territory.
Investigations
Nerve conduction studies. The gold standard for grading severity. They are indicated for:
- Atypical symptoms
- Atrophy
- Revision surgery
- Workers' compensation claims
The findings are an increased distal motor latency (greater than 4.2 ms) and a decreased sensory conduction velocity. Compare with the ulnar and radial nerves, using the double innervation of the ring finger, to rule out a polyneuropathy.
Ultrasound. A cross-sectional area greater than 10-12 mm² at the inlet is diagnostic. Ultrasound is becoming the first-line imaging modality because of its cost and its dynamic capability.
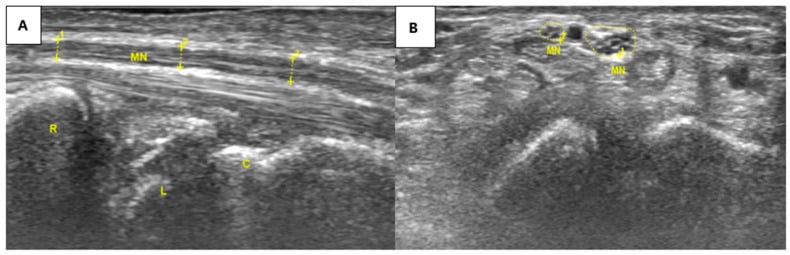
MRI and radiographs. MRI is for space-occupying lesions such as a lipoma or ganglion. Plain radiographs show previous fractures, a distal radius malunion in particular, and arthritis.
Management Strategy
Carpal tunnel syndrome. Conservative treatment is a night splint in neutral, a steroid injection, which is both diagnostic and therapeutic, and ergonomics. Surgery is indicated for:
- Failure of conservative treatment
- Constant numbness
- Thenar wasting
The procedure is carpal tunnel release, open or endoscopic, and it is highly effective for night symptoms.
- First Line
- Splint / NSAIDs
- Second Line
- Steroid Injection
- Surgery Indication
- Failed conservative over 3m
- First Line
- Injection + Splint
- Second Line
- Consider early surgery
- Surgery Indication
- Patient preference / Failure
- First Line
- Surgery (Release)
- Second Line
- None
- Surgery Indication
- Relative Emergency (prevent permanent loss)
- First Line
- Reduction of fracture
- Second Line
- Release if persistent
- Surgery Indication
- Compartment Syndrome equivalent
Pronator syndrome. Usually conservative, with physiotherapy and rest. Release is for the case resistant beyond 6 months, and it divides the ligament of Struthers, the lacertus, pronator teres and the FDS arch.
Anterior interosseous nerve syndrome. Observation. Many are a viral neuritis, a Parsonage-Turner variant, and spontaneous recovery is common. Surgery is for no recovery beyond 12 months.
Surgical Technique
Procedure Steps
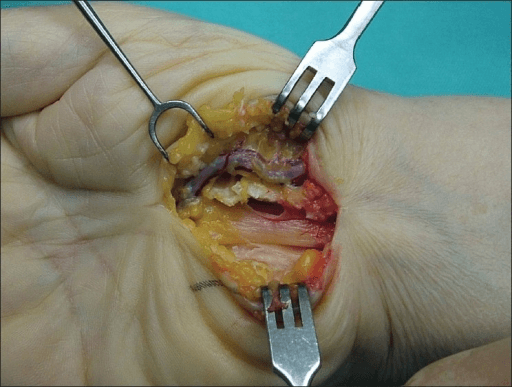
The incision lies in line with the ring finger axis, distal to Kaplan's cardinal line, and ulnar to the palmaris longus tendon so that the palmar cutaneous branch is avoided.
Incise the palmar fascia and identify the distal edge of the transverse carpal ligament.
Divide the ligament on its ulnar side, away from the recurrent branch on the radial side. Distally, the fat pad marks the superficial palmar arch. Release proximally into the forearm fascia.
The recurrent motor branch is extraligamentous in 50%, subligamentous in about 30% and transligamentous in about 20%, passing through the ligament itself. Always cut the ligament on the ULNAR side.
Meticulous haemostasis is required to prevent haematoma and scarring.
Complications
- Cause
- Loss of arch support/ligament healing
- Management
- Time, padding (Resolves by 6m)
- Cause
- Flexor retinaculum intact proximally
- Management
- Revision
- Cause
- Radial side incision
- Management
- Repair / Tendon Transfer
- Cause
- Nerve injury / idiopathic
- Management
- Multimodal therapy
Rehabilitation and Outcomes
After release. A splint is generally not required after a simple carpal tunnel release, and finger and wrist motion begins immediately; early mobilisation reduces the risk of complex regional pain syndrome. Grip strengthening begins at 4-6 weeks, with work hardening from 6 weeks; return to sport is the precaution of that phase.
- 0-2 weeks: wound healing and oedema management, avoiding heavy grip
- 2-6 weeks: tendon gliding, scar massage and desensitisation
- From 6 weeks: work hardening and grip strength
Return to work. Desk work at 1-2 weeks, light manual work at 4 weeks, heavy work at 6-8 weeks.
Exercises. Median nerve flossing runs through five positions: fist, then extend the fingers, then extend the wrist, then supinate, then stretch the thumb. Tendon gliding is the hook fist, the straight fist and the full fist.
Outcomes. Release gives 90% good or excellent results. Night pain resolves almost immediately ("the best sleep in years"); numbness recovers variably and is permanent if long-standing. Recurrence is rare, less than 5%, and when it happens look for scarring, a missed diagnosis or a double crush.
Guidelines, Registries & Global Practice
Global Epidemiology
- Carpal tunnel syndrome is the most common compressive neuropathy worldwide; population-based data (Atroshi et al., JAMA 1999) show clinically and electrophysiologically confirmed prevalence of about 2.7%, with median-distribution hand symptoms in roughly 14% of adults.
- Female predominance (approx 3:1 to 4:1), peak incidence in the 4th to 6th decades, and rising prevalence with obesity, diabetes, pregnancy, hypothyroidism and rheumatoid disease.
- Anterior interosseous nerve and pronator syndromes are rare by comparison and are frequently inflammatory (neuralgic amyotrophy) rather than purely compressive.
Side-by-Side Guideline Comparison
- Diagnosis
- Clinical criteria + provocative tests
- Electrodiagnostics
- Recommended before surgery if diagnosis uncertain
- Surgery
- Complete division of transverse carpal ligament; open or endoscopic equivalent
- Diagnosis
- Clinical, supported by validated questionnaires (e.g. CTS-6, Boston)
- Electrodiagnostics
- Not mandatory in classic cases; used when atypical or for medicolegal/work claims
- Surgery
- Decompression after failed/declined conservative care
- Diagnosis
- Clinical diagnosis; ultrasound increasingly used
- Electrodiagnostics
- Selective use
- Surgery
- Steroid injection then surgery; avoids routine NCS
- Diagnosis
- Clinical-first; imaging adjunctive
- Electrodiagnostics
- Confirmatory, not universally required
- Surgery
- Standardised release with recurrent-branch protection
Registry and Outcome Data
- Large administrative cohorts and hand-surgery registries consistently report carpal tunnel release as one of the highest-volume, highest-satisfaction elective hand procedures, with revision rates under 5%.
- There is no implant, so arthroplasty registries (NJR, AJRR, AOANJRR) do not apply; outcome surveillance relies on PROMs such as the Boston Carpal Tunnel Questionnaire and QuickDASH.
High- vs Limited-Resource Practice Variation
- Well-resourced settings: Liberal access to nerve conduction studies and high-resolution ultrasound; endoscopic release and wide-awake local-anaesthetic no-tourniquet (WALANT) open release are both common.
- Limited-resource settings: Diagnosis is predominantly clinical; open release under WALANT in an outpatient/minor-procedure room is the dominant cost-effective approach, reserving electrodiagnostics for atypical or revision cases.
Special Scenarios
Martin-Gruber anastomosis. A median-to-ulnar connection in the forearm, present in 15%. Muscles that are normally ulnar can be spared in a high ulnar lesion because they are being supplied by the median nerve. The reverse connection, ulnar to median in the hand from the deep branch to the recurrent branch, can spare the thenar muscles in carpal tunnel syndrome. Both anomalies can confuse nerve conduction findings.
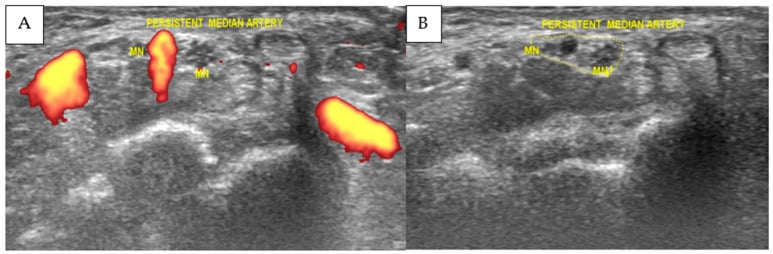
Bifid median nerve. The nerve divides into two or more fascicular bundles within or proximal to the tunnel, in roughly 2 to 3% of wrists and more on ultrasound series. The larger combined cross-sectional area predisposes to carpal tunnel syndrome, and at release both limbs must be decompressed and protected; a missed second limb is a cause of incomplete release.
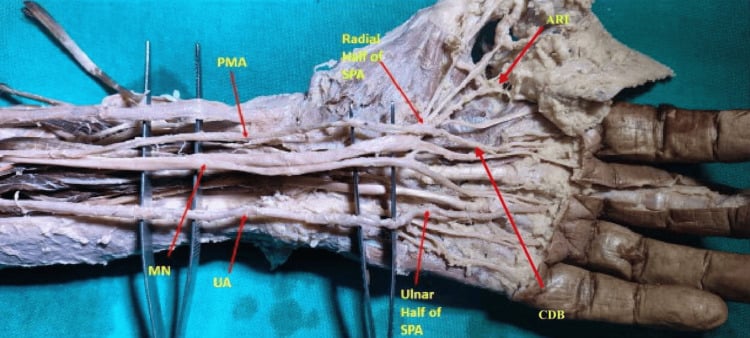
Persistent median artery. An embryological remnant that usually regresses but persists in a minority, frequently accompanying a bifid nerve and running with it into the palm. It can itself crowd the tunnel, may thrombose and cause acute carpal tunnel syndrome, and is a bleeding and injury hazard, especially during endoscopic or ultrasound-guided release, where it must be identified before the retinaculum is divided. Pre-operative ultrasound readily shows both variants; their presence argues for caution, or for open release, and for protecting the radial and ulnar limbs of the nerve.
Controversies & Areas of Uncertainty
Routine electrodiagnostics. Whether nerve conduction studies are mandatory before carpal tunnel release in classic cases is debated. UK and European practice increasingly accepts a clinical diagnosis, with validated questionnaires, for typical presentations, whereas many US centres still obtain confirmatory studies, partly for medicolegal and work-related reasons.
Endoscopic versus open release. Endoscopic release returns the patient to work faster, but there is no long-term advantage in symptom relief and a transiently higher rate of usually reversible nerve problems, so the choice remains surgeon- and patient-dependent rather than evidence-mandated.
Does pronator syndrome exist. Some authors question pronator syndrome as a discrete compressive entity, noting its overlap with proximal median irritation, lacertus syndrome and neuralgic amyotrophy, and the historically inconsistent surgical results.
The cause of AIN palsy. The pendulum has shifted from mechanical compression towards neuralgic amyotrophy with hourglass fascicular constrictions. That affects the timing of surgery and the role of high-resolution ultrasound or MRI in selecting the patients who will not recover spontaneously.
Ultrasound as a stand-alone test. Cross-sectional area thresholds vary between studies and operators, so ultrasound is best viewed as complementary to electrodiagnosis, not a replacement for it.
MCQ Practice Points
Q: Which fibers cross in Martin-Gruber anastomosis? A: Motor fibers from Median to Ulnar. Usually AIN branch fibers crossing to Ulnar nerve in the forearm to supply intrinsics (First Dorsal Interosseous).
Q: Which lumbricals are Median innervated? A: 1 and 2 (Index and Middle). They are unipennate. 3 and 4 are Ulnar and bipennate.
Q: Which structure is most superficial in the Carpal Tunnel? A: FDS to Middle/Ring. The FDS tendons are stacked 2 over 2 (3/4 over 2/5). The FPL is radial/deep. The Nerve is superficial to the tendons.
Q: The Median nerve passes between which two heads? A: The superficial (humeral) and deep (ulnar) heads of Pronator Teres. The ulnar artery passes deep to the deep head (separating artery and nerve).
Q: Where does the Palmar Cutaneous Branch arise? A: ~5cm proximal to the wrist crease. It travels superficial to the Transverse Carpal Ligament. This is why it is spared in Carpal Tunnel Syndrome (compression is deep to ligament) but can be injured in the surgical incision if placed too radially.
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 65-year-old lady presents with severe thenar wasting but no pain. She says her hands just feel 'clumsy'. Diagnosis?”
“A patient returns 3 months after Open CTR with WORSE pain and pillar tenderness. What is your differential?”
“A novice gymnast presents with inability to flex the IPJ of the thumb and DIPJ of the index finger. There is no sensory loss. What is the pathology?”
Anatomy High Yield
- Roots: C5-T1
- Cords: Medial + Lateral
- Tunel: 9 Tendons + 1 Nerve
- LOAF: Lumbricals 1/2, Opponens, APB, FPB
Clinical Signs
- Benediction: High Palsy (Active)
- OK Sign: AIN (Motor)
- Phalen's: CTS (Sensory)
- Durkan's: CTS (Compression)
Key Numbers
- 6mm: Normal 2-point discrimination
- Greater than 10mm²: US diagnosis of CTS
- Greater than 4.2ms: Motor Latency (abnormal)
- 5cm: PCB branching proximal to wrist
Surgical Steps
- Incision: Ring finger axis
- Kaplan's Line: Distal extent
- TCL: Cut on Ulnar side
- Protect: Recurrent Branch
Evidence Base
Splinting vs Surgery for CTS (Landmark RCT)
- 176 patients, open release vs nocturnal wrist splint, 18-month follow-up
- Success at 3 months: 80% surgery vs 54% splint (difference 26%)
- Success at 18 months: 90% surgery vs 75% splint (difference 15%)
- 41% of the splint group ultimately crossed over to surgery
Endoscopic vs Open CTR (Cochrane Review)
- 28 studies, 2586 hands; ECTR vs OCTR
- No difference in symptom relief or functional status at long-term follow-up
- Return to work ~8 days earlier with endoscopic release
- ECTR: more transient nerve problems but fewer wound complications
Corticosteroid Injection Efficacy (Cochrane Review)
- 12 studies, 671 participants
- Clinical improvement at 1 month vs placebo (RR 2.58)
- Benefit beyond 1 month not demonstrated vs placebo
- Local injection superior to oral corticosteroid up to 3 months
Ultrasound vs Electrodiagnosis for CTS
- Meta-analysis, 19 studies, 3131 wrists
- Ultrasound pooled sensitivity 77.6%, specificity 86.8%
- Wide variation across studies limits firm conclusions
Prevalence of CTS in a General Population
- Population survey of 2466 responders in southern Sweden
- Median-distribution symptoms in 14.4%
- Clinically certain CTS 3.8%; clinically AND electrophysiologically confirmed 2.7%
- Roughly 1 in 5 symptomatic subjects had confirmed CTS
AIN/PIN Palsy in Neuralgic Amyotrophy
- 51 cases of AIN/PIN involvement in neuralgic amyotrophy
- Pain was the presenting symptom in 52.9%, usually distal to the shoulder
- Neurolysis significantly improved Hand20 scores; conservative treatment did not
- Hourglass fascicular constrictions may explain failure to recover spontaneously