Nursemaid's Elbow (Pulled Elbow / Radial Head Subluxation)
Overview & Epidemiology
Nursemaid's (pulled) elbow is one of the commonest musculoskeletal injuries of early childhood and a frequent paediatric emergency-department presentation. It clusters between about 1 and 4 years (occasionally up to 5-6, and reported even in infants), is slightly more common in girls and on the left side, and becomes rare once the radial head enlarges and the annular ligament tightens with growth, so it is essentially not seen in adults.
The half without a story. Roughly half of cases present without a clear "pull" history, or with an unwitnessed or atypical mechanism, and that is exactly the group in which a fracture must be actively excluded. The recurring exam theme is a benign, clinical diagnosis with a simple and highly effective bedside cure; the skill is recognising it, distinguishing it from a fracture, and reducing it correctly first time.
Pathophysiology & Mechanism
The annular ligament. It encircles the head and neck of the radius, securing it against the radial notch of the ulna at the proximal radio-ulnar joint while allowing rotation (pronation and supination). In a young child the radial head is relatively small and incompletely ossified and the ligament is lax, so a sudden axial pull on an extended, pronated forearm can let the radial head slip partially out from under it, and the ligament becomes interposed: a subluxation, not a true dislocation. That mechanism is why the typical cause is a child lifted or swung by the hand (a practice to discourage).
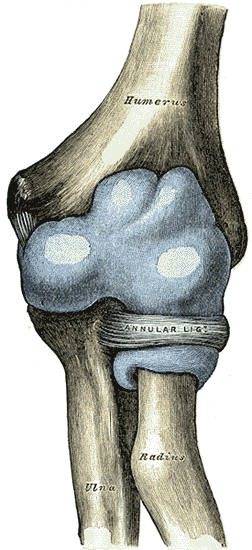
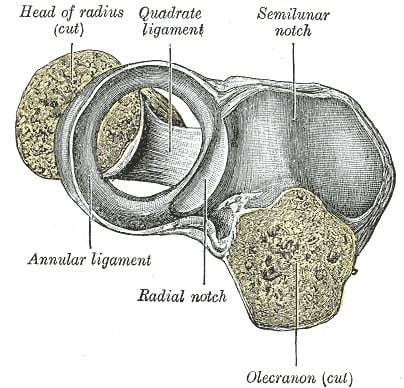
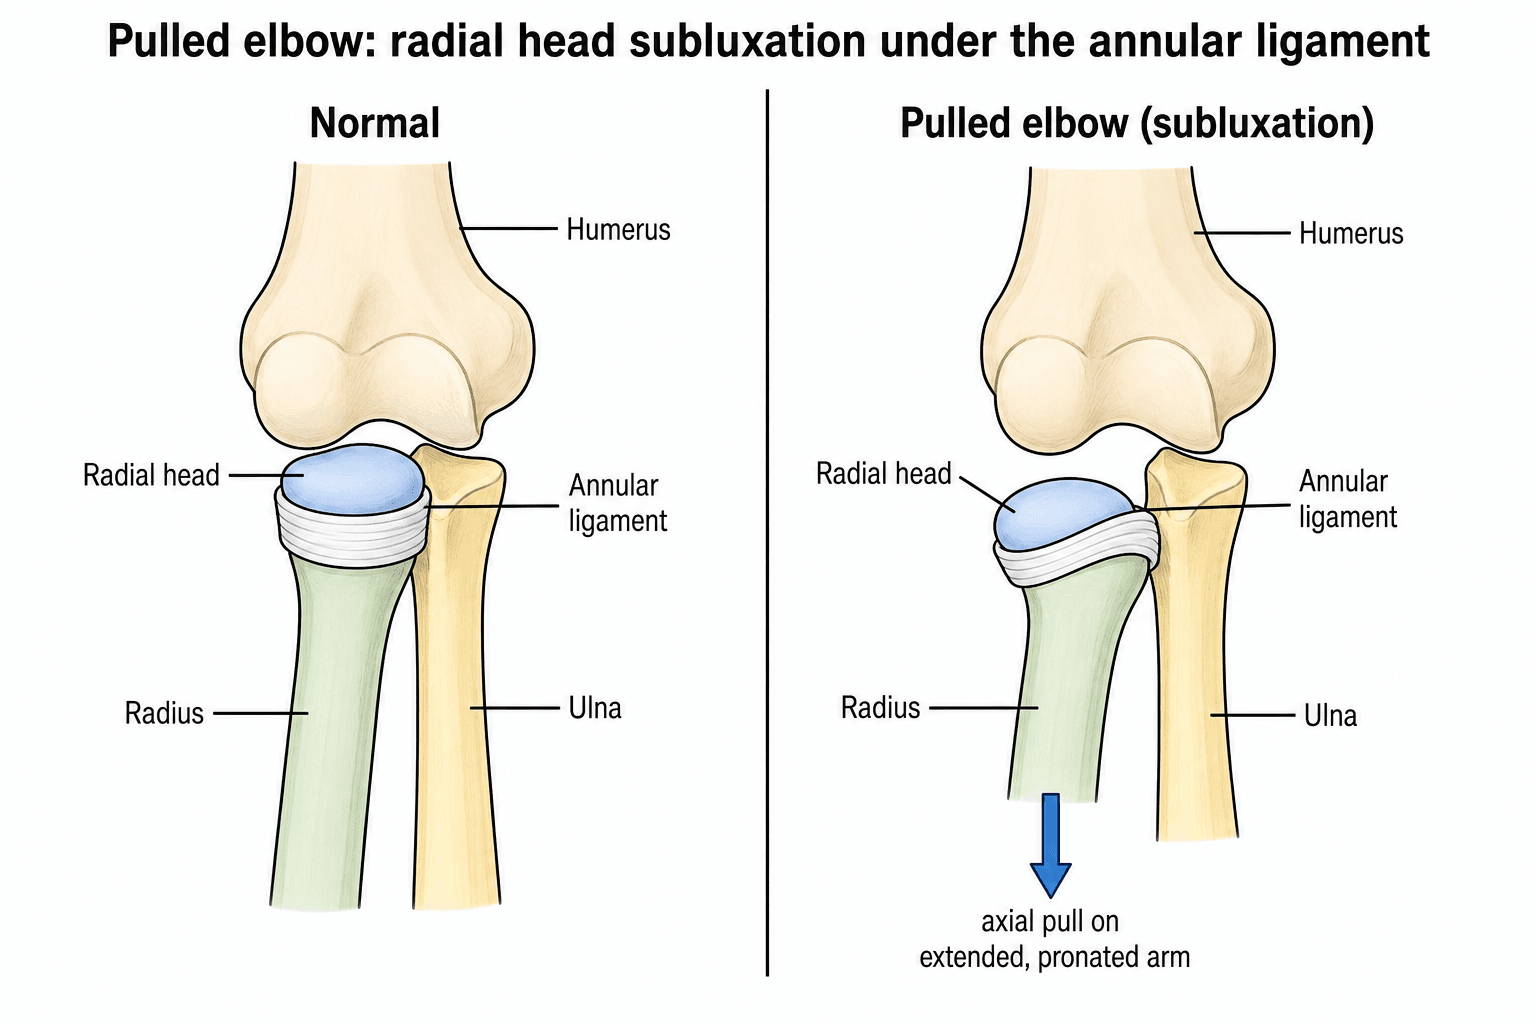
The supinator. Ultrasonographic work has refined the model: it is not only the annular ligament but also the supinator muscle (and its aponeurotic edge) that becomes interposed in the radiohumeral joint (Kimura). That explains two things examiners like. The injury occurs with the forearm pronated because the supinator is stretched, and both reduction manoeuvres work because hyperpronation unwinds the trapped tissue while supination-flexion relaxes the supinator and lets it slip back out.
Clinical Presentation & Diagnosis
The child. A young child, commonly 1-4 years, who suddenly stops using one arm after a pull. The arm is held close to the body, slightly flexed and pronated, with little or no pain at rest and no swelling or deformity, and the child resists supination and overhead use of the arm.
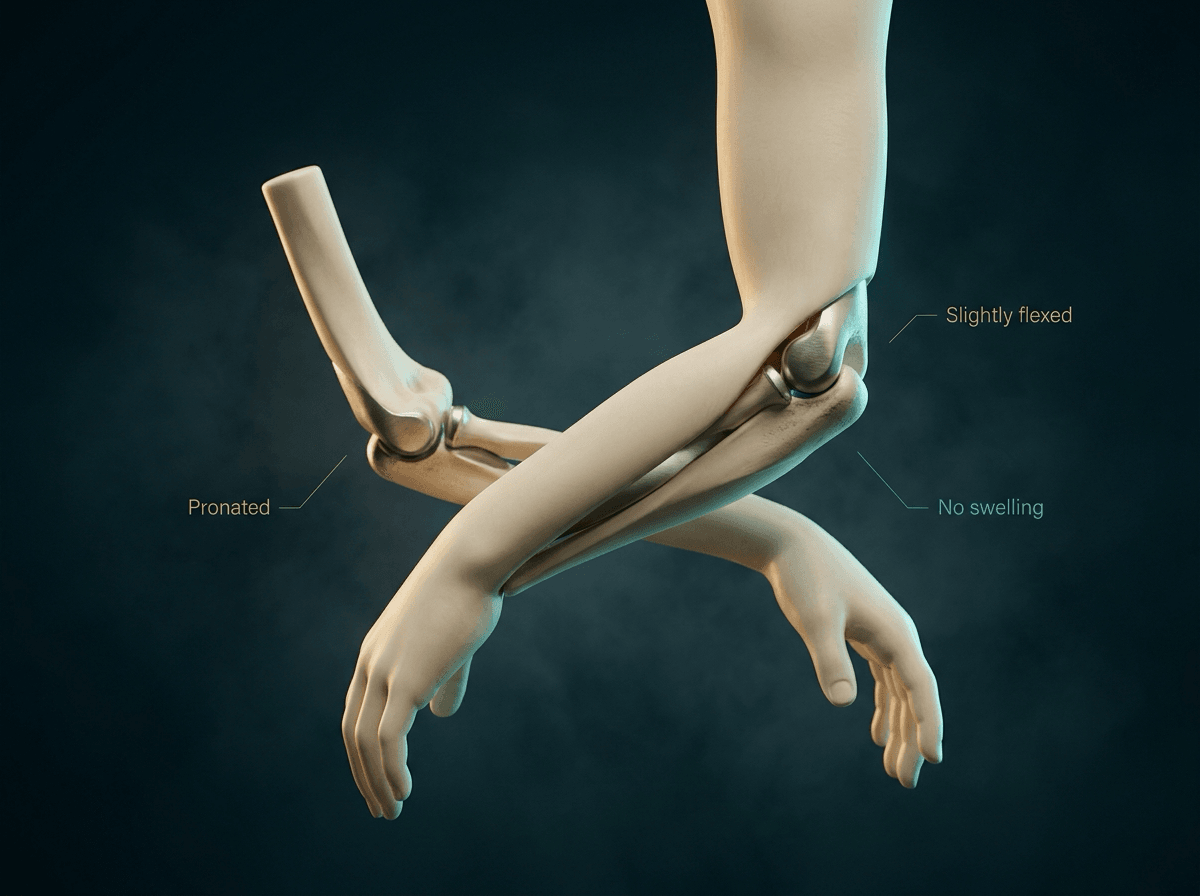
The diagnosis is clinical. The classic history plus this presentation is diagnostic. Radiographs are not routine and are usually normal; the only reason to take one is to exclude a fracture, and the red flags that call for it are listed under Investigations.
The differential. A pulled elbow is the commonest cause, but "pseudoparalysis" of an arm in a young child has a differential that must be actively excluded before manipulating:
- Occult fracture, supracondylar, lateral humeral condyle, radial neck, or a toddler's fracture pattern: suggested by swelling, deformity, focal bony tenderness or a fall or direct-trauma mechanism.
- Septic arthritis or osteomyelitis of the elbow or forearm: the child is systemically unwell and febrile, with warmth, swelling and pain on any passive movement (true pseudoparalysis); check inflammatory markers and do not "reduce".
- Clavicle fracture or shoulder pathology: referred reluctance to use the whole limb, so examine the whole arm, not just the elbow.
- Non-accidental injury: an inconsistent, changing or implausible history, or injuries of differing ages, is a safeguarding red flag.
- Brachial plexus or neurological causes: rare, but a flaccid arm without a clear pull warrants neurological examination.
If any of these is suspected, image and investigate before attempting reduction.
Investigations
Nothing routine. A typical pulled elbow is diagnosed and treated clinically, and imaging is targeted.
Radiographs. They are obtained only to exclude a fracture, before any manipulation, when one of the red flags below is present, and they are usually normal in a true pulled elbow. Note that the inadvertent supination involved in positioning for an AP film sometimes reduces the subluxation incidentally.
SWIFT red flagsWhen it is NOT a simple pulled elbow (X-ray / refer)
Hook:Any SWIFT red flag (Swelling, Wrong history, Inability to use post-reduction, focal Tenderness, Two failed attempts) means radiograph and refer — exclude a fracture.
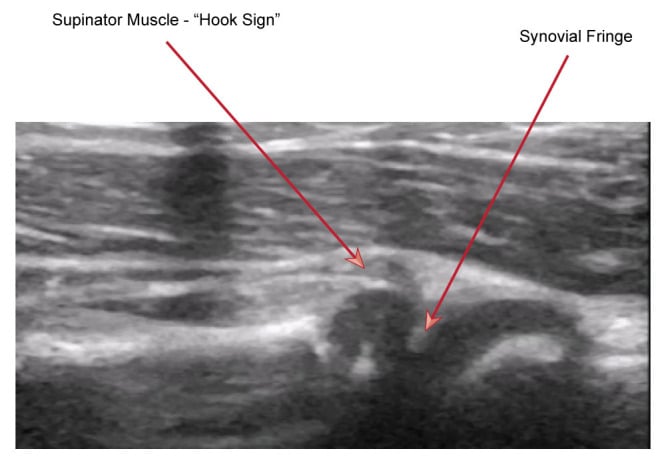
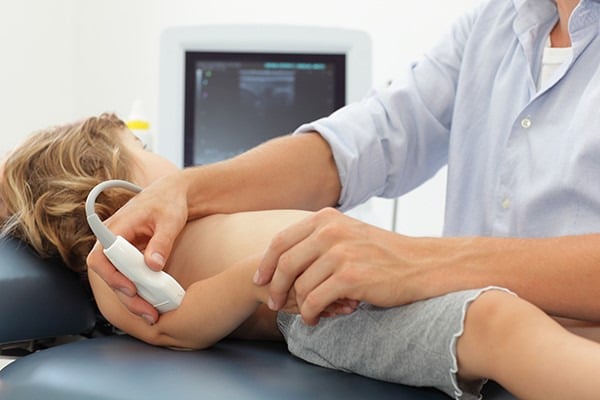
Point-of-care ultrasound. POCUS is an emerging, radiation-free aid in the atypical case: it can confirm a pulled elbow (the "hook sign" of the displaced annular ligament/supinator) and screen for a fracture before reduction. In a single-centre series (McCreary) it identified pulled elbow with high sensitivity and specificity and reduced unnecessary radiographs, which is useful precisely for the ~50% with an unclear history. The view is obtained with a high-frequency linear probe on the lateral elbow, marker toward the hand, covering the radiocapitellar joint.
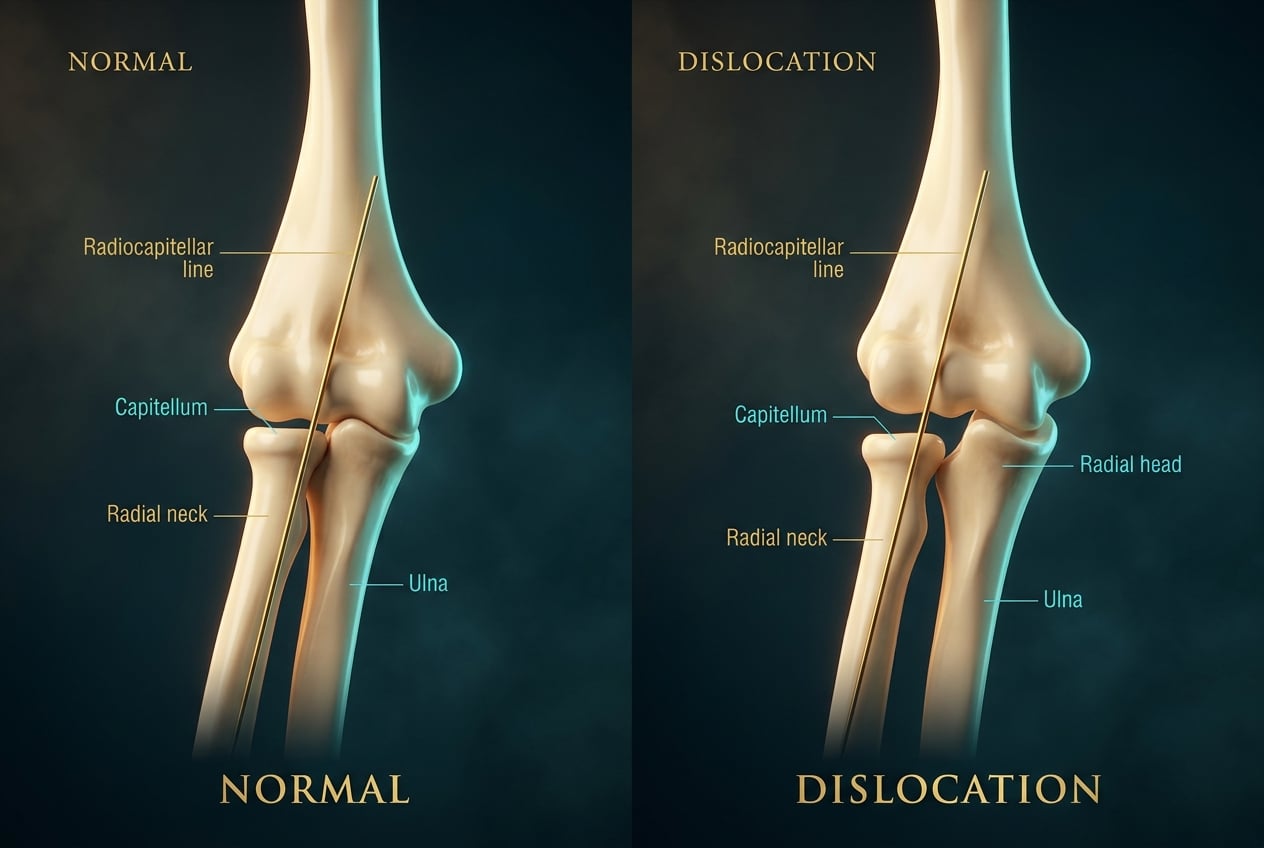
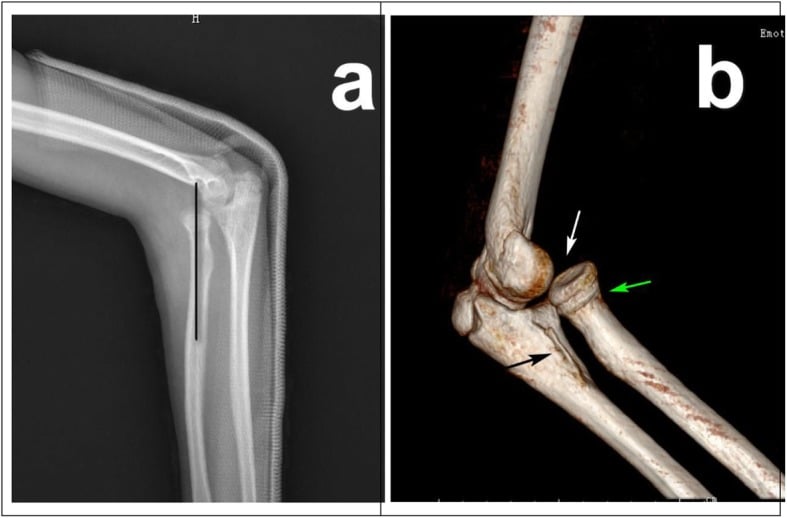
A pulled elbow is a self-reducing subluxation. When a film is taken, for an atypical or traumatic history or a failed reduction, the can't-miss alternative is a true radial head dislocation, and the way to catch it is the radiocapitellar line: a line drawn along the long axis of the radial neck or shaft must pass through the centre of the capitellum on every view. If it does not, the radial head is dislocated, and that is not a pulled elbow.
A dislocated radial head with a fractured or plastically bowed ulna is a Monteggia lesion; in children the ulna often bows rather than breaks, so look hard. It is treated by reducing or stabilising the ulna to relocate the radial head, never by repeated "pulled-elbow" manipulation, and a missed Monteggia (chronic radial head dislocation) is a classic, function-limiting pitfall. The other mimic is a congenital radial head dislocation, often posterior, with a domed or hypoplastic radial head and a convex capitellum: a bilateral or painless dislocation that was never a pulled elbow.
So in the atypical case, draw the radiocapitellar line and inspect the whole ulna before ever calling it a simple pulled elbow.
Management
The manoeuvre. Reduction is a simple bedside manoeuvre with the elbow at about 90 degrees, and there are two recognised techniques:
- Hyperpronation: firmly pronate the forearm and wrist, sometimes with slight elbow flexion
- Supination-flexion: supinate the forearm, then flex the elbow fully
Hyperpronation first. On Cochrane evidence the hyperpronation manoeuvre has fewer first-attempt failures than supination-flexion (failure about 9% versus 26%, risk ratio about 0.35, NNT about 6), so it should be tried first. A successful reduction often produces a palpable or audible click over the radial head, and the child typically resumes using the arm within minutes, which is the most reassuring sign.
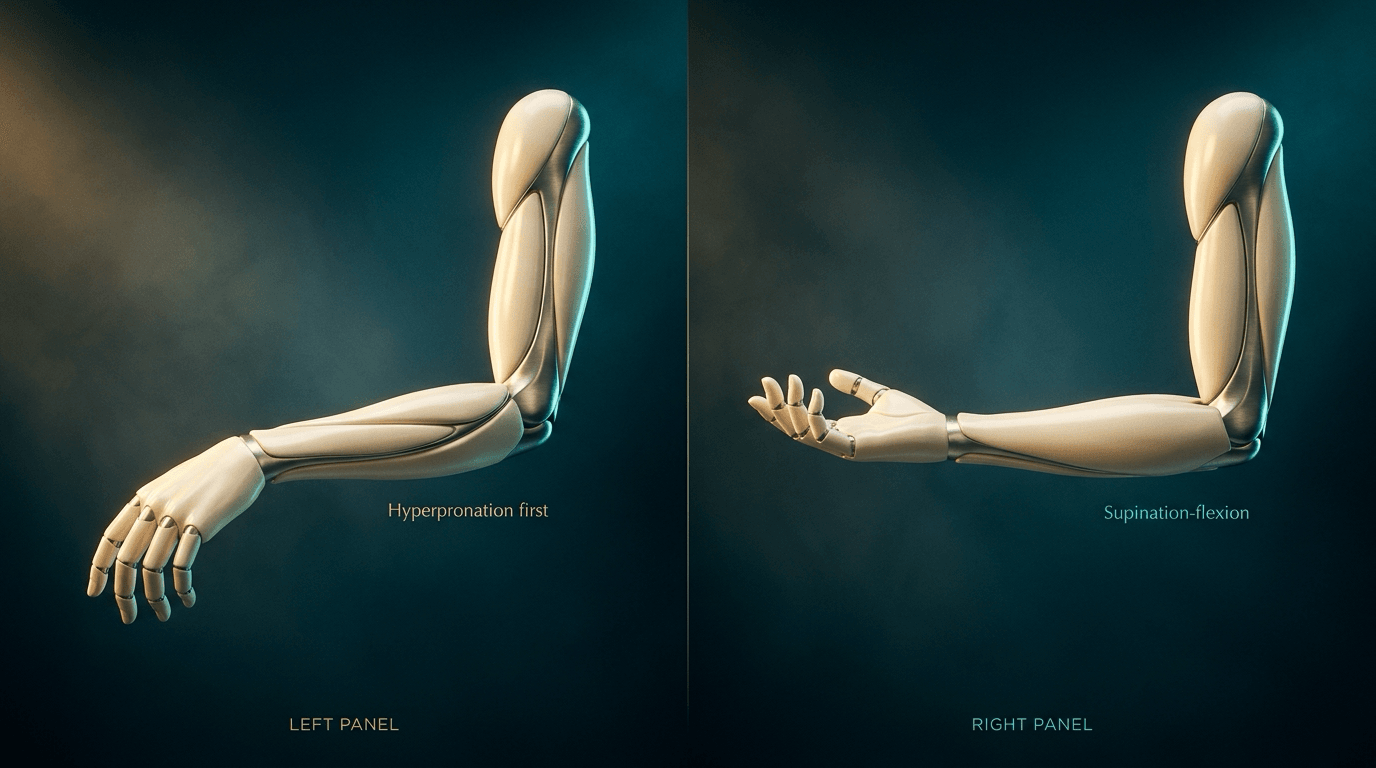
Two cautions on the numbers. The frequently quoted "about 80% office success" comes from a narrative review and is lower than this page's own Cochrane figures imply: a 9% first-attempt failure is a 91% first-attempt success, and Cochrane's ultimate failure ranged from none to 4.1%, so with a second attempt almost every child is reduced. The accompanying phrase "with no significant complications" overstates what is known, because the review records that adverse effects were not reported by the trials at all. Serious harm does appear to be rare in practice, but that is clinical experience, not a measured rate.
Step by step. This is how the hyperpronation manoeuvre is done.
- Position the child comfortably on the carer's lap; reassure and minimise distress.
- Support the elbow at about 90 degrees of flexion with one hand, the thumb resting gently over the radial head to feel for the click.
- With the other hand holding the distal forearm and wrist, firmly pronate (turn the palm down); some add slight further flexion at the end.
- Feel or hear the click over the radial head as the subluxation reduces.
- Watch for spontaneous use of the arm over the next few minutes (offer a toy or sticker to the affected hand); this, not the click alone, confirms success.
- If it fails, a second attempt is reasonable: repeating pronation, which the Cochrane review suggests may be more effective than repeating supination-flexion, or switching to supination-flexion. After two failed attempts, splint, image and refer.
Complications
Pulled elbow is benign with an excellent prognosis. A correctly reduced subluxation leaves no growth disturbance, instability or lasting loss of function, and because the tendency to recur resolves spontaneously once the radial head enlarges and the annular ligament tightens, no long-term treatment or activity restriction is required. A few problems are nonetheless examinable:
- Note
- The commonest issue; re-reduce and reinforce the carer advice against pulling or swinging by the hand
- Note
- The important pitfall: a supracondylar, lateral condyle or other elbow fracture mistaken for a pulled elbow and inappropriately manipulated; image when the picture is atypical
- Note
- Failure of two reduction attempts, or persistent non-use, mandates splinting, radiographs and referral; a small number need a period of rest before later successful reduction
- Note
- An atypical or inconsistent history is a safeguarding red flag, not just a fracture flag
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 2-year-old is brought in refusing to use the right arm after the parent lifted her by the hand. There is no swelling or deformity and she holds the arm pronated. What is the diagnosis, how do you confirm it, and how do you treat it?”
“The reduction fails after two attempts and the child still will not use the arm. What now, and why does pulled elbow happen in young children but not adults?”
What & why
- Radial head subluxation under the annular ligament (not a dislocation)
- Axial traction on an extended, pronated arm (lifting/swinging by the hand)
- Ages ~1-4; rare after ~5 (radial head enlarges)
Presentation
- Won't use the arm; held close, slightly flexed and pronated
- No swelling, deformity or focal bony tenderness; little pain at rest
- Resists supination/overhead use
Diagnosis
- Clinical - no routine radiographs (usually normal)
- X-ray only to exclude a fracture (atypical/traumatic, swelling, tenderness, failed reduction)
- Consider NAI if the history does not fit
Treatment
- Hyperpronation first (Cochrane: failure ~9% vs ~26%, RR 0.35, NNT ~6)
- Then supination-flexion if needed; success = click + arm use within minutes (~80%)
- If two attempts fail: splint, X-ray, refer; advise against pulling by the hand (recurrence common)
Evidence & Key Studies
The practice-defining study is the Krul Cochrane review (9 trials, 906 children): hyperpronation has fewer first-attempt failures than supination-flexion (9.2% vs 26.4%, RR 0.35, NNT 6) — though the authors stress the evidence is low-quality and a definitive RCT is still needed, so quote it as "probably superior at first attempt." Note two things the review does not say: it found the pain comparison too uncertain to call either way, and it records that adverse effects and recurrence were not reported at all. Yamanaka (clinical review) gives the bedside picture and is the origin of the widely quoted "~80% office success with no complications" — a narrative figure, not a pooled one, and lower than Cochrane's own numbers imply. Kimura adds the pathophysiology (ultrasound shows the supinator, not just the annular ligament, is interposed). McCreary illustrates the modern diagnostic adjunct (POCUS for the atypical case). The exam essentials — the mechanism, the clinical diagnosis, and hyperpronation-first — rest on this base.
Manipulative interventions for reducing pulled elbow in young children
- Across 9 trials (906 children), hyperpronation had fewer first-attempt failures than supination-flexion: 9.2% versus 26.4% (RR 0.35, 95% CI 0.25-0.50).
- Estimated number needed to treat of 6 (95% CI 5-8) to avoid one additional first-attempt failure using hyperpronation.
- Evidence is low-quality and a high-quality RCT is still needed, but pronation appears more effective at first attempt.
- PAIN - THE FINDING MOST OFTEN MISQUOTED: from 4 studies the evidence was VERY low quality and the review states it is uncertain whether there is or is not a difference in pain between the two methods. Cochrane does NOT establish that hyperpronation hurts less.
- After a failed first attempt, repeat pronation may be more effective than repeat supination-flexion (6 studies, very low-quality evidence)
- Ultimate failure - after whatever rescue each protocol allowed - ranged from none in two studies to 6 episodes (4.1% of 148) in one, so nearly every child is reduced eventually by one route or another
Pulled elbow in children
- Pulled elbow is a radial head subluxation from axial traction or a sudden pull of the extended, pronated arm; the practice of swinging children by the hands should be abandoned.
- The child holds the affected arm close to the body without considerable pain, swelling or deformity; once a fracture is excluded it is a clinical diagnosis.
- States office reduction has ~80% success 'with no complications' - this is the origin of a figure widely repeated elsewhere, and both halves of it need care (see limitation)
- Endorses hyperpronation over supination-flexion as the first manoeuvre, consistent with the Cochrane review
Role of the supinator muscle in the pathophysiological mechanism of a pulled elbow
- Reviews ultrasonographic evidence that BOTH the annular ligament and the supinator muscle become interposed in the radiohumeral joint in a pulled elbow
- Explains why the injury occurs with the forearm pronated (the supinator is stretched)
- Provides a mechanistic basis for why both hyperpronation and supination-flexion can reduce the subluxation
What is the utility of point-of-care ultrasound for suspected pulled elbow? A single-centre case series
- Retrospective series of 37 children (0-5 years) with suspected pulled elbow assessed with point-of-care ultrasound (POCUS)
- All 29 with a typical history had a positive POCUS; POCUS correctly identified pulled elbow with 100% sensitivity and specificity in this small series
- POCUS clarified the ~50% with an atypical/unwitnessed history and reduced unnecessary radiographs
- Proposed as an extension of clinical examination to confirm pulled elbow and lower radiation exposure