Ectopic Spinal Ligament Ossification | Cervical Myelopathy | East Asian Prevalence
- OPLL is ectopic ossification of the PLL causing cervical canal stenosis and compressive myelopathy
- East Asian prevalence is 10-20 times higher than Western populations; strong genetic association (COL6A1, rs6919606)
- CT is the gold standard for diagnosis and classification (sagittal reformats show ossification morphology)
- K-line on lateral cervical radiograph predicts outcome of posterior decompression: K-line positive = good result, K-line negative = consider anterior approach
- Dural ossification (double-layer sign or single-layer sign on CT) predicts intraoperative CSF leak and dural defect
- “OPLL is the most common cause of cervical myelopathy in Japan
- “Four types: continuous, segmental, mixed, localised (know CT appearances)
- “K-line positive = ossification does not cross the line joining the midpoints of the SPINAL CANAL at C2 and C7 (canal midpoint, not vertebral body midpoint)
- “Anterior approach directly removes OPLL but risks dural injury; posterior decompresses indirectly via posterior shift of the cord
- “Ossification of the ligamentum flavum (OLF) can coexist, especially in the thoracic spine
Overview and Epidemiology
What it is. The posterior longitudinal ligament undergoes progressive ectopic endochondral ossification, producing a mass that encroaches on the spinal canal, narrows it and compresses the cord. OPLL is the most common cause of cervical compressive myelopathy in East Asian populations and is increasingly recognised worldwide as imaging advances. Most of it is asymptomatic and discovered incidentally; once symptomatic myelopathy develops, timely surgical decompression is essential to prevent irreversible cord damage.
Who. Prevalence in Japanese adults on CT or radiograph screening is 1.9-4.3 percent, with comparable figures in Korea and China; Caucasian populations sit at 0.1-0.3 percent, 10-20 times lower. Men are affected about 2:1, onset is typically at 40-60 years, and the course is slowly progressive. Symptomatic myelopathy develops in 5-15 percent of those with OPLL.
Where. The C3-C5 levels are most commonly affected, but the ossification can extend from C2 into the thoracic spine. Ossification of the ligamentum flavum (OLF) or yellow ligament (OYL) coexists in 5-10 percent.
Natural history. The ossification grows slowly over years, and cervical myelopathy is the most common symptomatic presentation. Minor trauma can precipitate acute myelopathy on a canal that pre-existing OPLL has already narrowed, a scenario dealt with under Clinical Assessment.
Pathophysiology
The ligament. The PLL runs along the posterior surface of the vertebral bodies from C2 to the sacrum and forms the anterior boundary of the spinal canal. In OPLL it is progressively replaced by mature lamellar bone through endochondral ossification, mediated by osteogenic differentiation of ligamentous mesenchymal stem cells; the staged sequence from ligament hypertrophy through chondroid metaplasia to ossification is set out below. The mass grows anterior to the dura and can eventually incorporate or replace the ventral dural layer, which is the origin of the surgical problem of dural ossification.
- Histology
- Fibrocartilaginous proliferation within PLL
- Imaging Correlate
- Thickened PLL on MRI, no ossification on CT
- Clinical Significance
- Pre-clinical, not detectable on radiographs
- Histology
- Cartilaginous foci within the ligament substance
- Imaging Correlate
- Early punctate calcification on CT
- Clinical Significance
- Progressive but may remain asymptomatic
- Histology
- Mature lamellar bone replacing cartilage
- Imaging Correlate
- Clear ossification on CT, hyperdense on sagittal reformats
- Clinical Significance
- Canal encroachment begins; myelopathy possible
- Histology
- Ossification incorporates ventral dura
- Imaging Correlate
- Double-layer sign or single-layer sign on CT
- Clinical Significance
- CSF leak risk at surgery; dural defect anticipated
Molecular drivers. The key drivers are the bone morphogenetic proteins BMP-2, BMP-4 and BMP-7, osteocalcin, Runx2 (osteoblast differentiation) and Sox9 (chondrogenesis), with TGF-beta as a profibrotic signal. The strongest genetic association is a polymorphism of COL6A1 (collagen type VI alpha 1, rs6919606); R-Spondin 2 in the Wnt pathway and N-cadherin are also implicated. OPLL shares pathogenic pathways with diffuse idiopathic skeletal hyperostosis (DISH) and ossification of the ligamentum flavum (OLF).
Risk factors and associations. Beyond East Asian heritage (Japanese, Korean, Chinese), the associations are genetic, metabolic, endocrine, skeletal, dietary and mechanical:
- A family history of OPLL increases the risk 5-10 times
- Diabetes mellitus, impaired glucose tolerance, hyperinsulinaemia and the metabolic syndrome
- Hypoparathyroidism, the classical endocrine association
- DISH (Forestier disease), which coexists in 25-40 percent of OPLL patients
- A high-salt, low-animal-protein diet, proposed on epidemiological correlation
- Repeated micro-trauma to the PLL, cervical repetitive stress and occupational neck loading, which may trigger an osteogenic response
Classification and Types
The CT classification. The Japanese Investigation Committee classification (1994) is the standard system, defining four types by the morphological pattern of ossification on sagittal CT reformats. The type carries a surgical implication, tabulated alongside its morphology and frequency.
- Morphology on Sagittal CT
- Ossification extends across vertebral bodies and disc spaces as a single uninterrupted band
- Frequency
- Approximately 27-30 percent
- Surgical Implication
- Often requires multi-level anterior corpectomy or skip corpectomy
- Morphology on Sagittal CT
- Ossification present behind vertebral bodies only, with sparing at disc levels
- Frequency
- Approximately 39-43 percent (most common)
- Surgical Implication
- Posterior laminoplasty effective if K-line positive
- Morphology on Sagittal CT
- Combination of continuous and segmental patterns
- Frequency
- Approximately 26-30 percent
- Surgical Implication
- Approach determined by K-line and number of levels
- Morphology on Sagittal CT
- Ossification confined to the disc level only
- Frequency
- Approximately 2-5 percent (rarest)
- Surgical Implication
- Anterior discectomy or single-level corpectomy
The canal occupancy ratio. OPLL thickness divided by the anteroposterior canal diameter on axial CT quantifies severity: less than 30 percent is mild, 30-60 percent moderate, and greater than 60 percent severe. Surgical decompression is generally recommended when the ratio exceeds 60 percent or progressive myelopathy is present.
- Severity
- Mild
- Typical mJOA
- 15-17 (mild or normal)
- Management
- Observation if no myelopathy; serial imaging
- Severity
- Moderate
- Typical mJOA
- 12-14 (moderate)
- Management
- Surgical decompression if progressive myelopathy
- Severity
- Severe
- Typical mJOA
- Less than 12 (severe)
- Management
- Urgent surgical decompression recommended
The K-line (kyphosis line). Fujiyoshi et al. proposed the K-line as a practical radiographic tool for selecting the approach. On a lateral cervical radiograph, or a sagittal CT, draw a straight line joining the midpoints of the spinal canal at C2 and C7, that is, the midpoint of the canal's anteroposterior diameter at each level. The OPLL is K-line positive when the mass does not cross or extend posterior to the line, and K-line negative when it does.
The line runs through the canal, not through the vertebral bodies. The canal midpoint lies posterior to the body midpoint, so a line drawn through the bodies sits too far forward and will wrongly call some K-line positive patients negative, pushing them towards an unnecessary anterior procedure. It is a common and consequential error.
Why it predicts the outcome. Posterior decompression works by allowing the cord to drift posteriorly, away from the ossified mass. In a K-line positive patient the cord can shift back behind the OPLL, posterior laminoplasty is appropriate, and good neurological recovery is expected. If the mass is so large, or the alignment so kyphotic, that the OPLL crosses the line, the cord cannot shift past it; posterior decompression alone is insufficient and an anterior or combined approach is needed.
The dynamic K-line. Fujiyoshi's original description is a static measurement on a neutral lateral, and that is its main practical weakness: cervical alignment changes with posture, so a patient who is K-line positive in neutral can become K-line negative in flexion, and the cord is compressed in the position the neck actually adopts rather than the one the radiographer asked for. Later work therefore groups patients by whether the line stays positive across neutral and flexion films, and a patient who converts is a poor candidate for laminoplasty alone despite a reassuring neutral film. Obtain neutral and flexion laterals before committing to a posterior-only decompression; see cervical myelopathy for the dynamic K-line groups illustrated on paired films.
Dural ossification. Where the ossified ligament has incorporated or replaced the ventral dura, resecting the OPLL leaves a dural defect. It is present in approximately 5.7 percent of surgical cases, becomes more probable when the canal occupancy ratio is greater than 60 percent, and predicts intraoperative CSF leak. The axial CT is read for two signs before any anterior resection:
- Axial CT Appearance
- Two distinct hyperdense layers separated by a hypodense band
- Dural Status
- Dura ossified between the two layers
- Surgical Risk
- High risk of dural defect with anterior OPLL resection
- Axial CT Appearance
- Single homogeneous ossified mass with no visible dura between mass and thecal sac
- Dural Status
- Dura likely incorporated into OPLL mass
- Surgical Risk
- Very high risk; dural defect expected if OPLL removed
- Axial CT Appearance
- Hypodense band clearly visible between OPLL and thecal sac
- Dural Status
- Dura separate from OPLL
- Surgical Risk
- Lower risk of dural injury during anterior surgery
When either sign is present, anterior OPLL resection will almost certainly create a dural defect. The surgeon either plans for CSF management or chooses the floating method, in which the OPLL is thinned and allowed to float anteriorly without complete resection; both are set out under Management.
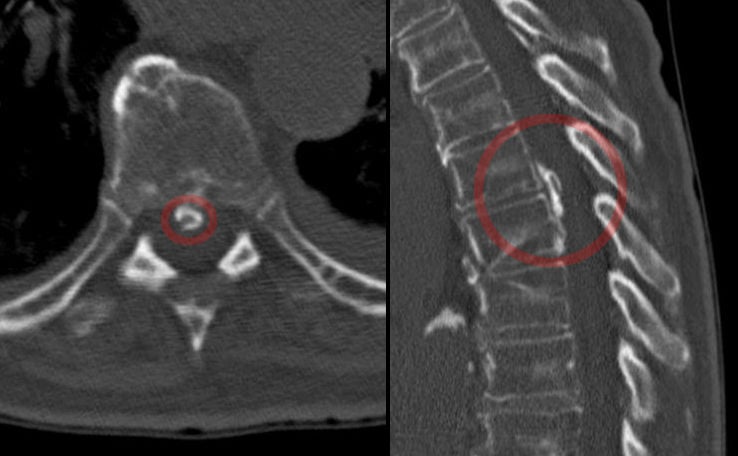
Thoracic OPLL. Rarer than cervical disease and more dangerous. The thoracic spine is kyphotic, so the cord already lies draped against the anterior ossified mass and posterior decompression alone allows little posterior cord drift; the K-line logic that works in the lordotic cervical spine often fails here, decompression may be inadequate and the cord can even be injured. The thoracic cord has a watershed blood supply, especially in the mid-thoracic region, so it is vulnerable to ischaemic injury during decompression and manipulation. T-OPLL is often of the continuous type, the thoracic canal is narrow, and it frequently coexists with ossification of the ligamentum flavum posteriorly, producing front-and-back ("pincer") compression that a single-sided decompression cannot relieve.
Thoracic strategy. The options are posterior decompression with instrumented fusion, often with some kyphosis correction (dekyphosis); posterolateral or anterior transthoracic decompression for a focal anterior beak; or a circumferential procedure for combined OPLL and OLF. Intra-operative neuromonitoring with MEP and SSEP is essential given the high cord-injury risk, and patients must be counselled that transient or permanent neurological worsening is more common than after cervical surgery.
Clinical Assessment
History. Onset is insidious: slowly progressive clumsiness of the hands and gait disturbance over months to years. Loss of hand dexterity (difficulty with buttons, chopsticks, writing) is an early sign; the gait becomes stiff-legged and spastic with frequent falls; urinary hesitancy, urgency and incontinence appear in advanced cases. Neck pain may be present but is often minimal relative to the degree of myelopathy. A history of minor trauma (whiplash, a fall) matters, because it can precipitate acute deterioration.
Examination. The signs to elicit:
- Motor: upper limb weakness, particularly of the intrinsic hand muscles, and spastic lower limb weakness
- Reflexes: hyperreflexia, a positive Hoffmann sign, a positive Babinski sign
- Sensory: variable sensory loss below the level of compression
- Gait: spastic, broad-based, with decreased proprioception
- Neck range of motion may be limited; examine cautiously to avoid precipitating myelopathy
- Lhermitte sign, an electric-shock sensation on neck flexion, is non-specific
Grading. The modified Japanese Orthopaedic Association (mJOA) score, 0-18, is the standard clinical tool for severity, and the mJOA recovery rate is used to quantify post-operative improvement:
- Mild, mJOA 15-17: subtle hand dysfunction, no gait disturbance
- Moderate, mJOA 12-14: obvious hand dysfunction, mild gait disturbance
- Severe, mJOA less than 12: marked gait disturbance, possible bowel and bladder dysfunction
Surgical decompression is generally recommended for moderate and severe myelopathy (mJOA less than 15) and for progressive mild myelopathy.
- Key Discriminator
- East Asian ethnicity, ossified PLL on CT
- Imaging Finding
- Hyperdense band posterior to vertebral body on CT
- Management Difference
- Ossification-specific surgical planning required
- Key Discriminator
- Disc-osteophyte complexes, no ossification
- Imaging Finding
- Disc protrusion and osteophytes on MRI/CT, no OPLL
- Management Difference
- Standard anterior or posterior decompression
- Key Discriminator
- Acute onset, often radicular component
- Imaging Finding
- Focal disc extrusion on MRI
- Management Difference
- Anterior discectomy and fusion
- Key Discriminator
- Posterior compression, thoracic more common
- Imaging Finding
- Hyperdense mass in ligamentum flavum on CT
- Management Difference
- Laminectomy for posterior decompression
- Key Discriminator
- Progressive myelopathy with vascular congestion
- Imaging Finding
- Flow voids on MRI, dilated perimedullary veins
- Management Difference
- Endovascular or surgical fistula obliteration
- Key Discriminator
- Upper and lower motor neuron signs, no sensory loss
- Imaging Finding
- No structural compression on imaging
- Management Difference
- Medical management, not surgical
OPLL or spondylotic myelopathy. The distinction matters because OPLL carries additional surgical risks, dural ossification and CSF leak among them, and may require different operative strategies. OPLL is confirmed by demonstrating ossification of the PLL on CT, not just disc protrusion or osteophytes, so always obtain CT in addition to MRI when OPLL is suspected: MRI may not clearly distinguish OPLL from disc material and osteophytes, although the signal characteristics described under Investigations help.
Minor trauma on an OPLL canal. A canal already narrowed by OPLL has no reserve space for the cord. A relatively trivial hyperextension injury (a fall onto the face, a low-speed motor vehicle collision, even a fall from standing in an older patient) momentarily buckles the ligamentum flavum and pinches the cord between it and the anterior OPLL, often producing a spinal cord injury without any fracture or dislocation, the SCIWORA-type pattern in adults with stenosis. The classic syndrome is acute central cord syndrome, the most common incomplete cord injury: upper-limb weakness disproportionately worse than the legs, hands worst, variable bladder dysfunction and sacral sparing, reflecting the central (medial) location of the cervical hand fibres.
Managing the acute injury. Urgent MRI defines cord compression and signal change. Maintain spinal cord perfusion by supporting mean arterial pressure, often to a MAP target of around 85 to 90 mmHg, and avoid hypotension and hyperextension; high-dose steroids are not routinely recommended. For a patient with ongoing cord compression, early surgical decompression, increasingly favoured and often within about 24 hours, gives better neurological recovery than delayed surgery, though a purely central cord injury with minimal residual compression may initially be managed expectantly. This is exactly why an asymptomatic OPLL patient must be counselled about trauma risk, and why a pre-existing stenotic OPLL lowers the threshold for considering decompression.
Investigations
Radiographs. The first-line films are AP, lateral and flexion-extension views of the cervical spine. Look for a radiodense band posterior to the vertebral bodies, the cervical alignment (lordosis or kyphosis) and the flowing anterior osteophytes of DISH. Radiographs may miss early or small OPLL, CT is more sensitive, and the lateral view serves the K-line but is not sufficient for diagnosis.
Dynamic views. Flexion-extension films assess cervical instability or a mobile OPLL. Segmental mobility matters if posterior surgery is planned, because instability may necessitate fusion; perform them cautiously in a myelopathic patient to avoid cord injury.
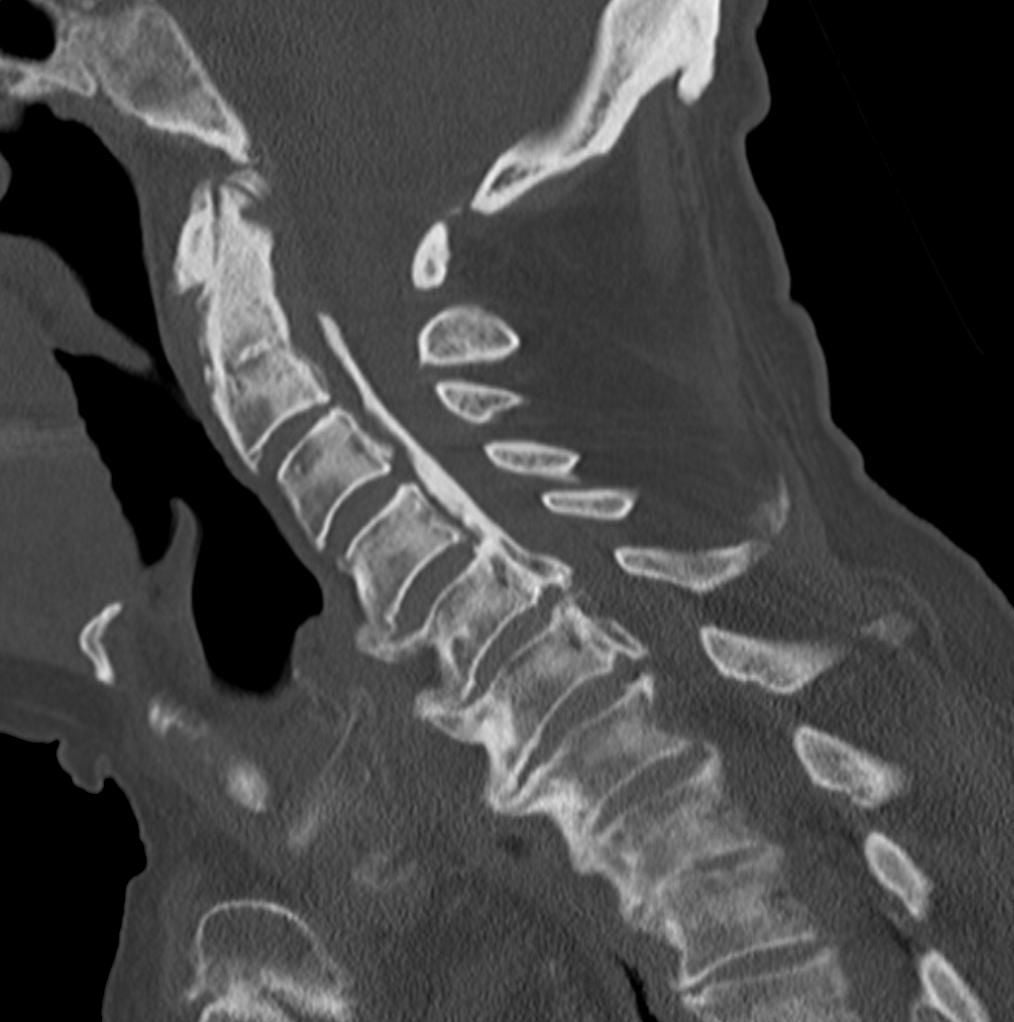
CT with sagittal reformats. The gold standard for diagnosis and classification. On sagittal reformats the ossification appears as a hyperdense strip along the posterior vertebral body margin, distinct from the vertebral cortex, and this is the view on which the type is assigned. Axial cuts give the canal occupancy ratio (OPLL thickness divided by the sagittal canal diameter) and the double-layer and single-layer signs of dural ossification.
MRI. The ossified mass is low signal on both T1 and T2, whereas disc material is typically T2 hyperintense, which is what lets MRI help separate OPLL from disc. T2 sagittal and axial sequences show the cord compression at the OPLL levels, and T2 hyperintensity within the cord indicates myelomalacia. That signal change carries prognostic weight: pre-operative T2 cord signal correlates with post-operative recovery, and multi-level high signal predicts a poorer outcome.
CT myelography. For the patient in whom MRI is contraindicated (pacemaker, cochlear implant). Contrast outlines the thecal sac and shows the relationship between the OPLL mass and the cord, and it can confirm dural ossification when the CT signs are equivocal.
The minimum workup for suspected OPLL myelopathy is CT plus MRI: CT classifies the OPLL and evaluates dural ossification, MRI assesses cord compression and signal change. Report the OPLL type, the canal occupancy ratio, the K-line status and the presence or absence of dural ossification signs.
Management Algorithm
The decision. Most OPLL is asymptomatic and does not require surgery; the operation is for myelopathy. Once decompression is indicated, the choice between anterior and posterior surgery rests on the OPLL type, the canal occupancy ratio, the K-line status, the number of levels involved, the cervical alignment and the presence of dural ossification. Anterior surgery removes the mass directly at the price of a high dural injury risk; posterior surgery decompresses indirectly through posterior cord shift. Mixed and continuous types often require multi-level surgery.
- Diagnosis
- CT confirms type, MRI no cord signal change
- Treatment
- Observation with serial follow-up
- Key Pearl
- Most OPLL is asymptomatic; treat only when myelopathy develops
- Diagnosis
- MRI: cord compression with T2 signal change; CT: OPLL classification
- Treatment
- Posterior laminoplasty
- Key Pearl
- K-line positive predicts good outcome with posterior decompression
- Diagnosis
- Anterior OPLL displacing cord, kyphotic alignment
- Treatment
- Anterior corpectomy with OPLL resection or floating method
- Key Pearl
- Posterior decompression alone insufficient when OPLL crosses K-line
- Diagnosis
- Double-layer sign on CT; anterior OPLL with canal occupancy greater than 60 percent
- Treatment
- Anterior approach with dural repair planning or posterior decompression
- Key Pearl
- Pre-operative recognition of dural ossification allows CSF leak prevention planning
Who. Asymptomatic and mild OPLL. The goal is to monitor for progression and prevent myelopathy developing, and the risk of progression to myelopathy is approximately 1-3 percent per year.
Baseline. CT to classify the type and measure canal occupancy, MRI for cord compression and signal change, and a clinical baseline of mJOA score, hand function and gait. Educate the patient about the myelopathy symptoms to watch for, and advise them to seek urgent review if these develop.
Follow-up. Serial CT or MRI at 6-12 month intervals for 2-3 years, with a clinical review of the mJOA score and any new hand clumsiness or gait change at each visit. Any neurological deterioration prompts a surgical discussion. Advise the patient to avoid high-impact activities, contact sports and extreme neck positions.
Medical treatment. There is no proven disease-modifying therapy for OPLL progression. Bisphosphonates, vitamin K2 (menatetrenone) and etidronate have been studied with limited evidence for slowing ossification. Neck pain is managed with simple analgesics, avoiding opioids in myelopathic patients, and physiotherapy is limited to gentle range-of-motion exercises without aggressive cervical manipulation.
ACAF, anterior controllable antedisplacement and fusion. The most important recent addition to OPLL surgery, designed to solve the exact problem that makes anterior corpectomy dangerous: peeling a dura-adherent ossified mass off the cord. A conventional corpectomy removes the vertebral bodies and then tries to resect the OPLL, risking a massive and unrepairable dural tear. ACAF instead moves the whole vertebral-body-plus-OPLL complex forward as a single unit and never removes the ossified mass at all:
- The anterior plate and screws are positioned first, with screws set to the intended new, more anterior position
- The vertebral bodies bearing the OPLL are isolated by bilateral longitudinal osteotomies at the body-pedicle junction, with the discs above and below released, freeing a "bone-OPLL complex"
- That freed complex is lifted anteriorly (ante-displaced) and held forward by tightening it onto the pre-contoured plate
Why it matters. Because the OPLL is never separated from the dura, the cord being decompressed by translating the whole anterior wall forward, the dreaded step of stripping ossified dura is avoided. That is the rationale for ACAF's lower CSF-leak profile in difficult, dura-adherent disease, precisely the population in which the double-layer sign and a high canal occupancy ratio make corpectomy most hazardous.
Complications
- Incidence
- 5-32 percent with anterior approach (higher with dural ossification)
- Risk Factors
- Dural ossification, continuous type, anterior approach
- Management
- Intra-operative repair, lumbar drain 3-5 days, fascial graft, tissue sealant
- Incidence
- 5-15 percent after posterior decompression
- Risk Factors
- Posterior cord shift, foraminal stenosis at C4-C5
- Management
- Observation (most recover 6-12 months), targeted therapy, consider prophylactic foraminotomy
- Incidence
- 10-30 percent show progression at 5 years post-operatively
- Risk Factors
- Young age, continuous type, metabolic syndrome
- Management
- Serial imaging, no proven pharmacological prevention
- Incidence
- 10-20 percent partial closure over time
- Risk Factors
- Hinge fracture, inadequate spacer, poor bone quality
- Management
- May require revision with laminectomy and fusion
- Incidence
- 5-15 percent at 5 years (higher with fusion than laminoplasty)
- Risk Factors
- Fusion constructs, long-segment fixation
- Management
- Conservative initially; revision extension of fusion if symptomatic
- Incidence
- 5-10 percent after corpectomy
- Risk Factors
- Multi-level corpectomy, osteoporosis, poor endplate preparation
- Management
- Revision fixation; consider posterior augmentation
- Incidence
- 1-3 percent
- Risk Factors
- Antiplatelet therapy, extensive decompression, inadequate drainage
- Management
- Emergency wound exploration and evacuation if cord compression
CSF leak, the signature complication. It is the most feared and characteristic complication of anterior OPLL surgery, and it tracks dural ossification: the incidence runs from 5 percent when no dural signs are present to over 30 percent when the double-layer or single-layer sign is identified on pre-operative CT. Prevention rests on identifying those signs before the operation, using the floating method instead of OPLL resection, and having dural repair materials available. When a leak occurs, it is managed with the repair, lumbar drainage and monitoring set out under Anterior Decompression.
C5 palsy. Weakness of deltoid and biceps is the most common neurological complication after posterior cervical decompression for OPLL. It typically manifests 1-7 days post-operatively and is thought to result from traction on the C5 nerve root during posterior cord shift; most recover, but the weakness can be distressing for patients. The risk may be reduced by a foraminotomy at C4-C5 at the time of laminoplasty.
Outcomes and Prognosis
- Indication
- Segmental OPLL, lordosis, multi-level
- Expected Neurological Recovery
- mJOA improvement 3-5 points; 60-80 percent recovery rate
- Key Complications
- C5 palsy, laminoplasty closure, axial neck pain
- Indication
- Localised or segmental OPLL, kyphosis
- Expected Neurological Recovery
- mJOA improvement 4-6 points; 70-85 percent recovery rate
- Key Complications
- CSF leak, graft complications, dysphagia
- Indication
- Severe multi-level OPLL, K-line negative, kyphosis
- Expected Neurological Recovery
- mJOA improvement 3-5 points; variable recovery rate
- Key Complications
- High morbidity, blood loss, infection, prolonged recovery
What predicts a good result. Segmental type, K-line positive status, an mJOA greater than 12, myelopathy of less than 12 months' duration, no T2 cord signal change on MRI, and age less than 65 years.
What predicts a poor one. Continuous or mixed type, K-line negative status, an mJOA less than 10, long-standing myelopathy of greater than 2 years, multi-level T2 cord hyperintensity, and age greater than 70 years.
The modifiable factor. Duration of myelopathy is the most important prognostic factor the surgeon can influence: earlier decompression yields better outcomes, so do not delay surgery in progressive myelopathy.
Guidelines, Registries & Global Practice
- East Asia: Highest prevalence worldwide (Japan 1.9-4.3 percent, Korea and China comparable)
- North America and Europe: 0.1-0.3 percent prevalence; increasing recognition with widespread CT usage
- Male predominance: 2:1 ratio globally
- Age distribution: Onset typically 40-60 years across all ethnicities
- Rising diagnosis: Global increase in OPLL detection paralleling increased CT utilisation, suggesting true prevalence in non-Asian populations may be higher than historical estimates
- Japan and Korea: Extensive surgical experience with laminoplasty; OPLL-specific instrumentation and techniques widely available
- North America: OPLL less commonly encountered; anterior approaches more familiar to spine surgeons; laminoplasty expertise concentrated in specialist centres
- Europe: Mixed practice; increasing adoption of laminoplasty for multi-level OPLL; anterior approaches preferred for focal disease
- Resource-limited settings: CT availability is the primary diagnostic barrier; laminectomy (without instrumentation) may be the only available surgical option
- Universal principle: Regardless of region, CT + MRI assessment, K-line analysis, and dural ossification screening should guide surgical planning
- Diagnosis Emphasis
- CT classification mandatory; mJOA scoring for all patients
- Surgical Approach
- Laminoplasty for K-line positive multi-level disease; anterior for K-line negative or focal OPLL
- Special Considerations
- Developed the K-line concept; extensive laminoplasty experience
- Diagnosis Emphasis
- CT and MRI essential; systematic classification of OPLL type
- Surgical Approach
- Approach based on K-line, alignment, number of levels, and dural status
- Special Considerations
- Prospective multicentre data on laminoplasty outcomes supports posterior approach for suitable candidates
- Diagnosis Emphasis
- MRI for myelopathy assessment; CT if OPLL suspected
- Surgical Approach
- Specialist spinal centre management; approach individualised
- Special Considerations
- Posterior decompression preferred for multi-level disease; anterior for focal disease with kyphosis
- Diagnosis Emphasis
- CT and MRI recommended; OPLL classification when identified
- Surgical Approach
- Surgeon experience and OPLL-specific factors guide approach
- Special Considerations
- Higher proportion of anterior surgery in US practice; increasing laminoplasty adoption
There is no dedicated international OPLL registry comparable to arthroplasty registries. The largest datasets come from the Japanese Investigation Committee on OPLL (nationwide surveys of over 10,000 cases), the AOSpine International study (prospective multicentre), and individual high-volume centre series from Japan and Korea. The Japanese nationwide surveys provide the most comprehensive natural history data and form the basis of current classification and management recommendations.
Record in every OPLL surgical planning case:
- OPLL type on CT (continuous, segmental, mixed, localised)
- Canal occupancy ratio (percentage)
- K-line status (positive or negative)
- Dural ossification signs on axial CT (double-layer, single-layer, or absent)
- Cervical alignment (lordotic, straight, or kyphotic)
- mJOA score
- Number of levels involved
- Presence or absence of coexisting OLF or DISH
These factors collectively determine the surgical approach and must be documented before the operative plan is finalised.
Controversies & Areas of Uncertainty
While K-line negative status suggests posterior decompression alone is insufficient, the optimal alternative (anterior corpectomy vs combined approach vs posterior decompression with fusion) remains debated. Some surgeons advocate a trial of posterior decompression with instrumented fusion for K-line negative patients to achieve indirect decompression via cervical alignment correction, avoiding anterior dural ossification risk entirely.
The floating method avoids dural injury but leaves residual OPLL anterior to the cord, and the time course of anterior migration (weeks to months) means decompression is not immediate. Direct OPLL resection achieves immediate decompression but carries high CSF leak risk when dural ossification is present. No randomised trial has compared these techniques head-to-head.
Bisphosphonates, vitamin K2 (menatetrenone), etidronate, and other agents have shown limited and conflicting evidence for slowing OPLL progression. No pharmacological therapy is currently recommended in any major guideline. Research into BMP pathway inhibitors and anti-osteogenic agents is ongoing but not yet clinically available.
Laminoplasty preserves motion but risks closure over time and does not address kyphotic alignment. Laminectomy with fusion corrects alignment but sacrifices motion segments and increases adjacent segment disease risk. The choice remains surgeon-dependent as no large RCT has definitively favoured one over the other for OPLL specifically.
MCQ Practice Points
Q: What is the prevalence of OPLL in the Japanese adult population? A: 1.9 to 4.3 percent based on population CT screening studies. This is approximately 10-20 times higher than in Caucasian populations. The condition is also common in Korean and Chinese populations, suggesting a shared genetic predisposition.
Q: What are the four CT types of OPLL according to the Japanese Investigation Committee classification? A: Continuous, segmental, mixed, and localised (circumscribed). Segmental type is the most common (approximately 40 percent), followed by continuous (approximately 28 percent), mixed (approximately 28 percent), and localised (approximately 2-5 percent). The classification is based on sagittal CT reformats.
Q: What is the K-line and how does it guide surgical approach selection in OPLL? A: The K-line is a straight line connecting the midpoints of the SPINAL CANAL at C2 and C7 on the lateral cervical radiograph - the canal midpoint, not the vertebral body midpoint. K-line positive (OPLL does not cross the line) means the cord has room to drift backwards, so posterior laminoplasty is appropriate. K-line negative (OPLL crosses the line) means it cannot, and posterior decompression alone will fail - Fujiyoshi reported a mean JOA recovery rate of only 13.9 per cent in K-line negative patients against 66.0 per cent in K-line positive patients, with intraoperative ultrasound confirming insufficient posterior cord shift. A K-line negative patient needs an anterior or combined approach.
Q: What CT signs predict dural ossification in OPLL and what is their surgical significance? A: The double-layer sign (two hyperdense layers with intervening hypodense band on axial CT) and the single-layer sign (homogeneous ossified mass without visible dura) both predict dural ossification. When present, direct OPLL resection will almost certainly create a dural defect and CSF leak. The floating method (thinning the OPLL without resection) is the preferred surgical technique when these signs are identified.
Q: When is anterior surgery preferred over posterior surgery for OPLL myelopathy? A: Anterior surgery is preferred when: K-line negative (OPLL crosses K-line), cervical kyphosis, localised OPLL (1-2 levels), high canal occupancy (greater than 60 percent) with focal compression, and failed posterior decompression. Posterior surgery is preferred when: K-line positive, multi-level involvement (3 or more levels), preserved cervical lordosis, and segmental type OPLL.
Q: What is the pathogenesis of OPLL and which genetic locus is most strongly associated? A: OPLL develops through endochondral ossification of the PLL, driven by osteogenic differentiation of ligamentous mesenchymal cells under the influence of BMP-2, BMP-4, BMP-7, Runx2, and Sox9. The strongest genetic association is with the COL6A1 gene (collagen type VI alpha 1) polymorphism. OPLL shares pathogenic pathways with DISH and OLF.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 52-year-old Japanese man presents with progressive hand clumsiness and gait disturbance over 8 months. Examination reveals hyperreflexia in all four limbs, positive Hoffmann sign bilaterally, and a spastic gait. mJOA score is 11. MRI shows cervical cord compression from C3 to C5 with T2 signal change in the cord. CT demonstrates a continuous type OPLL with canal occupancy of 55 percent. The OPLL mass does not cross the K-line on lateral radiograph. No dural ossification signs are seen on axial CT. What is your diagnosis and management plan?”
“A 48-year-old Korean woman with known OPLL presents with rapidly progressive cervical myelopathy over 3 months. MRI shows severe cord compression at C4-C5 with multi-level T2 signal change. CT demonstrates mixed type OPLL with 70 percent canal occupancy at C4-C5, and the OPLL mass crosses the K-line. Axial CT at C4 shows a double-layer sign. mJOA is 8. What is your surgical plan and how do you manage the dural ossification risk?”
Epidemiology and Pathogenesis
- Japanese prevalence 1.9-4.3 percent; East Asian populations affected 10-20 times more than Caucasians
- Endochondral ossification of PLL driven by BMP signalling; COL6A1 gene strongest genetic association
- Male-to-female ratio 2:1; onset age 40-60 years; C3-C5 most commonly affected levels
- Associated conditions: DISH (25-40 percent), diabetes mellitus, metabolic syndrome, hypoparathyroidism
CT Classification (Japanese Investigation Committee)
- Segmental (most common, approximately 40 percent): ossification behind vertebral bodies only
- Continuous (approximately 28 percent): ossification spans bodies and discs
- Mixed (approximately 28 percent): combination of continuous and segmental
- Localised (approximately 2-5 percent): ossification at disc level only, rarest type
K-line and Surgical Planning
- K-line: straight line joining the midpoints of the SPINAL CANAL (not the vertebral bodies) at C2 and C7 on lateral radiograph
- K-line positive (OPLL anterior to line): posterior laminoplasty is appropriate
- K-line negative (OPLL crosses line): anterior or combined approach required
- K-line predicts whether posterior cord shift can achieve decompression
Dural Ossification
- Double-layer sign: two ossified layers with hypodense band on axial CT = dural ossification
- Single-layer sign: homogeneous ossified mass without visible dura = high dural risk
- CSF leak rate 5-32 percent with anterior approach; floating method reduces risk
- Pre-operative recognition essential: plan dural repair, lumbar drain, or floating method
Surgical Approaches
- Posterior laminoplasty: K-line positive, multi-level, lordosis preserved; C5 palsy risk 5-15 percent
- Anterior corpectomy: K-line negative, focal disease, kyphosis; CSF leak and graft complications
- Floating method: thin OPLL with diamond burr, allow anterior migration; for dural ossification cases
- Combined approach: severe multi-level OPLL with kyphosis or failed prior surgery
Prognosis and Outcomes
- Best outcomes: K-line positive, mJOA greater than 12, myelopathy duration less than 12 months, no T2 signal
- Poor outcomes: K-line negative, mJOA less than 10, long-standing myelopathy, multi-level T2 signal change
- Duration of myelopathy is the most important modifiable prognostic factor
- OPLL progression rate 10-30 percent at 5 years post-operatively; no proven pharmacological prevention
Evidence Base and Key Trials
Ossification of the posterior longitudinal ligament of the cervical spine: etiology and natural history
- Comprehensive review of OPLL pathogenesis highlighting endochondral ossification driven by BMP signalling
- Japanese prevalence of 1.9 to 4.3 percent confirmed on population CT screening studies
- COL6A1 gene polymorphism identified as the strongest genetic association with OPLL
- Natural history: 1-3 percent annual risk of progression to symptomatic myelopathy in asymptomatic individuals
A new concept for making decisions regarding the surgical approach for cervical ossification of the posterior longitudinal ligament: the K-line
- K-line positive patients achieved significantly better neurological recovery after laminoplasty than K-line negative patients
- THE ACTUAL FIGURES: mean JOA recovery rate was 13.9 per cent in the K-line negative group versus 66.0 per cent in the K-line positive group (P less than 0.01) - a gap of 52 percentage points, not a modest difference
- K-line provides a simple pre-operative radiographic tool for surgical approach selection, and its elegance is that it collapses TWO known predictors of failure - cervical kyphosis and a large OPLL mass - into a single line
- Insufficient posterior shift of the spinal cord in the K-line negative group was demonstrated by INTRAOPERATIVE ULTRASONOGRAPHY, which is the mechanism: if the cord cannot drift back behind the K-line, decompressing from behind achieves nothing
- 27 patients in total - 19 K-line positive and only 8 K-line negative
Anterior cervical corpectomy and fusion versus posterior laminoplasty for the treatment of oppressive myelopathy owing to cervical ossification of posterior longitudinal ligament: a meta-analysis
- Anterior corpectomy and fusion provided significantly greater Japanese Orthopaedic Association (JOA) improvement than posterior laminoplasty for OPLL myelopathy
- Anterior approach had higher complication rates, particularly CSF leak and dysphagia, compared to posterior laminoplasty
- Posterior laminoplasty had shorter operative time, lower blood loss, and fewer overall complications
- No significant difference in fusion rate or long-term neurological recovery between approaches
Significance of the double-layer and single-layer signs in the ossification of the posterior longitudinal ligament of the cervical spine
- 197 patients undergoing anterior decompression and fusion for cervical OPLL - a substantial series for this question, not a small one
- Signs of dural penetration were present in 30.5 per cent overall, and were MUCH MORE PREVALENT IN NONSEGMENTAL OPLL
- THE NUMBERS THAT MATTER FOR CONSENT: an actual dural defect was found in 20 of 38 patients with a double-layer sign (52.6 per cent) but only 3 of 22 with a single-layer sign (13.6 per cent)
- The sign is GRADABLE, not binary - among double-layer cases, the mean diameter of the central hypodense mass was thicker in those who turned out to have a dural defect
- This was a replication of Hida's original description and found a WEAKER association than originally reported, though still a significant one