Age-based treatment selection, non-accidental injury screen and alignment follow-up
- Age and weight guide treatment more than the fracture label alone.
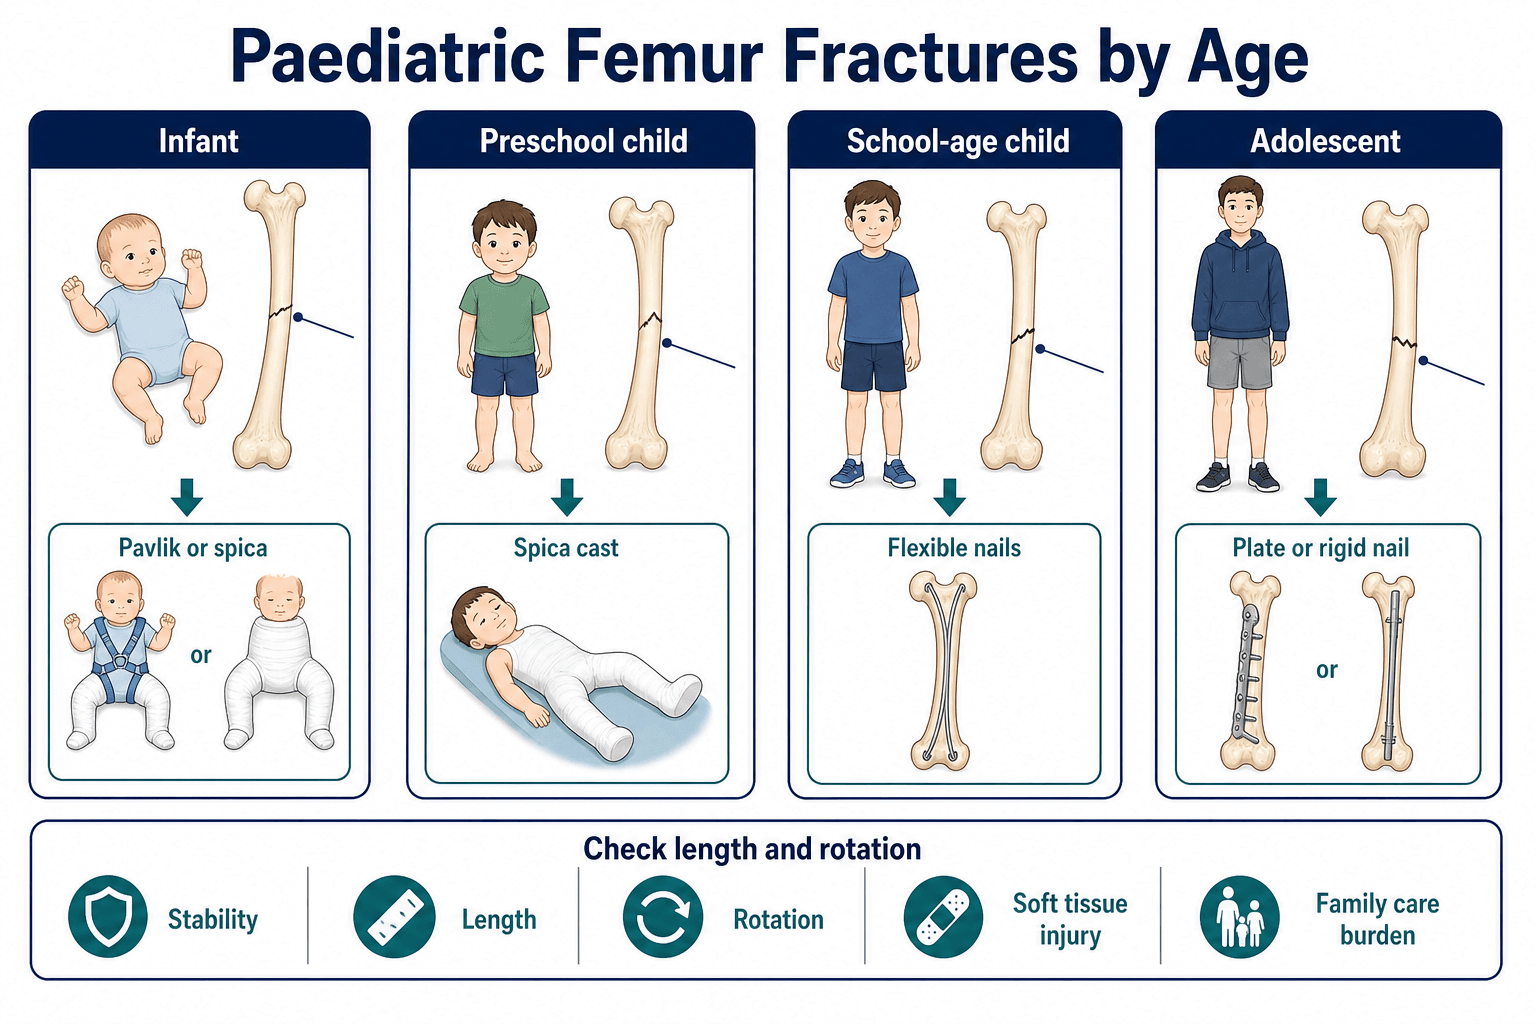
- Infants may be treated with Pavlik harness or spica depending on age and pattern.
- Young children commonly do well with early spica when alignment is acceptable.
- School-age children often need flexible nails or plating depending on length stability.
- Adolescents may need submuscular plating or rigid trochanteric-entry nails when appropriate.
- “Measure rotation clinically, not only on AP and lateral X-rays.
- “Length-unstable fractures are poor candidates for flexible nails alone.
- “High-energy femur fracture means look for chest, abdomen, head and other limb injuries.
- “Pain, anxiety and increasing analgesia can be compartment warning signs in children.
Overview and Epidemiology
Treatment of a paediatric femoral shaft fracture is organised by age, but age is only the start. The final plan depends on age, weight, skeletal maturity, fracture pattern, length stability, soft tissues, associated injuries, mechanism, safeguarding concerns and the family's ability to manage immobilisation and follow-up. The wrong operation for the wrong age or fracture pattern creates malunion, malrotation, skin problems or avoidable reoperation.
How the child changes with age. Younger children heal quickly and remodel well, but the mechanism must be checked against what they can developmentally do. School-age children sit in the transition zone, where a spica may be burdensome and operative stabilisation is often attractive. Adolescents behave more like adults mechanically, yet many still have open physes, so the implant entry point and growth safety remain important.
Pathophysiology
The biology explains why children can often be treated differently from adults, and it also explains the complications.
Healing and remodelling. Vascular bone and an active periosteum produce reliable callus. That is why younger children can often be treated with a harness or spica if alignment is acceptable.
Overgrowth. The femur can overgrow after a shaft fracture, especially in younger children. Some shortening may therefore be accepted, but the acceptance should be deliberate and followed.
Rotation. Rotational deformity remodels poorly, and malrotation is poorly seen on plain films. Rotation is therefore assessed clinically after reduction or fixation, not only on AP and lateral radiographs.
Length stability. Some patterns can shorten under load (they are listed under Classification). For these, flexible nails alone may be insufficient: the fracture is more likely to shorten and may need submuscular plating, external fixation or another stability strategy.
Implants. Flexible nails are load-sharing, submuscular plates provide relative stability, and rigid nails require safe entry points. The construct is matched to age, weight, fracture pattern and the open physes.
Soft tissues. Open fractures, severe swelling and polytrauma change priorities. Open-fracture care, external fixation or damage-control stabilisation may come before definitive fixation.
Pathological bone. Cysts, tumour, metabolic bone disease and osteogenesis imperfecta change healing and fixation. Treat the lesion and the bone-health diagnosis, not just the shaft fracture.
Classification
The practical classification sorts the fracture by its pattern and then by the context around the child. The age bands carry their treatment with them and are set out under Management.
Fracture pattern. Length stability is the major pattern distinction.
- Length stable: transverse and short oblique
- Length unstable, and prone to shortening: long oblique, spiral, comminuted and segmental
- Open: urgent antibiotics, debridement and stabilisation
- Pathological: a fracture through a lesion or abnormal bone, where the lesion is treated with the fracture
Context modifiers. Four features of the context can change the plan.
- Polytrauma may favour operative stabilisation
- Concern about non-accidental injury changes the pathway
- Obesity can make a spica or flexible nails less reliable
- Family and transport factors matter for safe discharge
Clinical Presentation
History
The history places the fracture in the context of the whole child.
Mechanism. Establish whether it was a fall, a twisting injury, road trauma, sport, a high-energy crush or a low-energy event. High-energy trauma triggers whole-child assessment; a low-energy fracture raises questions of pathology or safeguarding.
Developmental fit. Ask whether the child walks and whether the mechanism matches their age and ability. A femur fracture in a non-walking child needs safeguarding and bone-fragility review, with the thresholds set out below.
Associated injuries. Ask about head, chest, abdominal, pelvic, hip, knee or other limb pain. A femur fracture can coexist with a femoral neck fracture, a floating knee, or a pelvic or visceral injury.
Bone health. Ask about previous fractures, bone pain, a known cyst, metabolic bone disease, malignancy or features of osteogenesis imperfecta. Pathological fractures need diagnosis-specific treatment.
Pre-hospital care. Traction, splinting, analgesia, time since injury and the transfer details define pain control, skin risk and urgency.
Family practicality. Ask about spica care, transport, toileting, skin checks, sleep, stairs and car seats. A spica is safe only if the family can manage the child at home.
Examination
Perform a paediatric trauma assessment before discussing implant choice.
The whole child. Airway, breathing, circulation, head, chest, abdomen, pelvis and the other limbs. A femur fracture may be one marker of major trauma.
Thigh and skin. Look for swelling, deformity, shortening, external rotation, an open wound, the bruising pattern and threatened skin. These change the urgency, the open-fracture pathway and the choice of fixation.
Neurovascular status. Record distal perfusion and sciatic, peroneal and tibial nerve function where testable. This documents a baseline and detects a vascular or nerve injury.
Associated joints. Examine the hip, knee, tibia and pelvis so that a femoral neck fracture, distal physeal injury, floating knee or pelvic injury is not missed.
Compartments. Children may not describe classic compartment symptoms. Watch pain behaviour, anxiety, increasing analgesia, swelling, and pain with passive stretch when it can be assessed.
Rotation. After reduction or fixation, compare foot progression, the thigh-foot profile and hip rotation with the other side.
FEMURInitial Assessment
Hook:FEMUR runs the assessment: trauma survey, skin and nerves, mechanism, pattern, then rotation.
The safeguarding assessment, with its actual thresholds
"Consider safeguarding" is an instruction everyone accepts and few can operationalise. Two thresholds make it actionable.
The trigger. The AAOS guideline sets a formal one: every child under 36 months with a femoral shaft fracture should be evaluated for child abuse. That means evaluated, rather than screened informally or merely considered. Three years is deliberately wider than the intuitive cut-off, because the point is to catch the child whose walking is delayed or whose history is plausible on first telling.
Where the risk concentrates. The recognised risk factors for abuse are:
- Age under 12 months
- Non-ambulatory status
- Delayed presentation
- A history inconsistent with the injury or with the child's developmental ability
- Other injuries
A femoral shaft fracture in a child who has never walked is the single strongest of these: the force required has no innocent mechanism available to a child who cannot yet generate it. A spiral femur fracture is not automatically abuse, but the mechanism must fit.
A femur fracture in a non-walking child is a safeguarding diagnosis until the history, developmental stage and injury pattern are reconciled. Do not focus only on implant choice.
Scale. In a two-year audit of one UK city's emergency department, fractures of any kind occurred in the order of 53 per 10,000 children under two years. This is not a rare scenario an orthopaedic trainee will avoid.
The documentation failure you control. In the same audit the interval between injury and presentation was unrecorded in 34% of cases, though it is central to the abuse assessment and free to capture. Record when the injury happened, who was present, when the child was last seen to move the leg normally, and who brought them in. A note that omits the timeline weakens every later assessment, including your own.
Investigations
Radiographs. AP and lateral views of the femur, always including the hip and knee, define the level, pattern, shortening and any associated joint injury. In high-energy trauma, look specifically for a distal femoral physeal injury and a femoral neck injury.
Trauma imaging. After high-energy injury, imaging as indicated by the paediatric trauma team finds head, chest, abdominal, pelvic or other limb injuries.
Pathological concern. Full-length radiographs and lesion-specific MRI or laboratory tests identify a cyst, tumour or bone fragility.
Rotation. The clinical profile comes first. CT is used only when necessary, to quantify malrotation when clinical assessment is unreliable.
After treatment. Post-treatment radiographs confirm length, angulation and implant position. Serial films then check union, maintenance of alignment and complications.
Differential Diagnosis
- Clue
- High-energy injury, hip/knee pain or fracture line near joint.
- Why it matters
- Needs different reduction accuracy, fixation and complication follow-up.
- Clue
- Cyst, lytic lesion, previous pain, low-energy mechanism or abnormal bone quality.
- Why it matters
- Treat the lesion and fracture together.
- Clue
- Non-ambulant child, inconsistent story, delay or other injuries.
- Why it matters
- Activate safeguarding pathway while treating pain and fracture.
- Clue
- Osteogenesis imperfecta, metabolic bone disease or recurrent fractures.
- Why it matters
- Changes fixation, follow-up and family counselling.
- Clue
- Young child localises poorly and may appear to have thigh pain.
- Why it matters
- Prevents over-investigation or missing tibial tenderness.
- Clue
- Road trauma, fall from height or crush injury.
- Why it matters
- Look for head, chest, abdomen, pelvis and floating knee injuries.
Management
Treatment is a ladder. Start with analgesia, temporary splintage or traction, skin and neurovascular care, and whole-child assessment. Then choose definitive treatment by age, size, pattern and context.
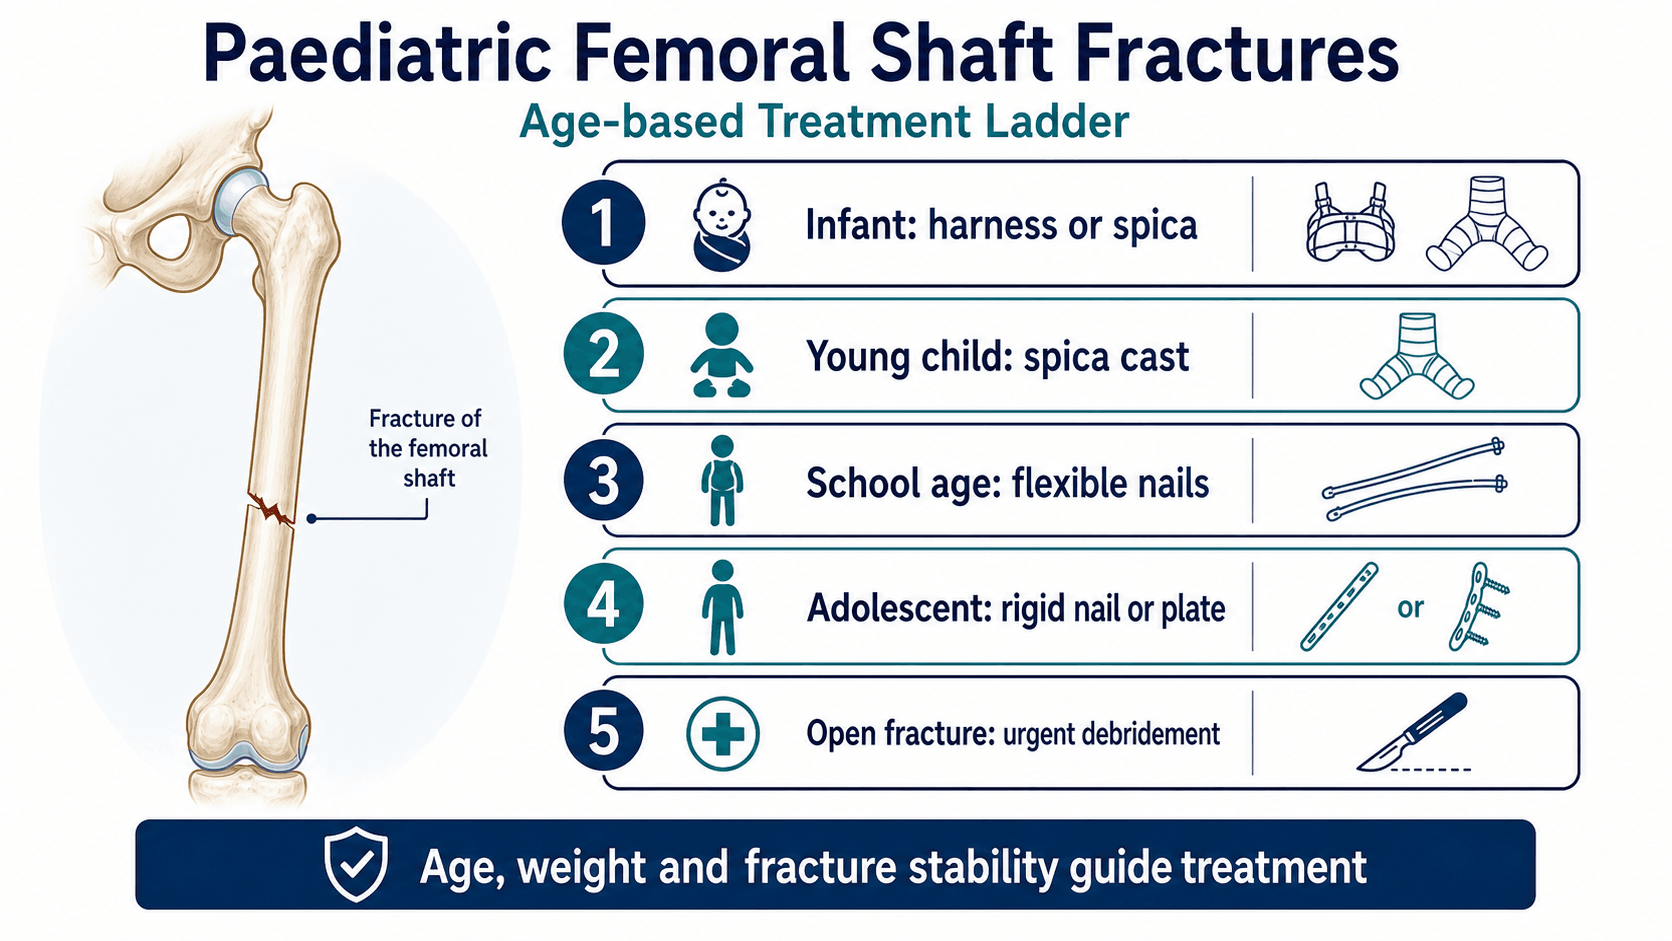
- Usual direction
- Pavlik harness or spica for selected closed injuries.
- When to change course
- Safeguarding, pathological fracture, polytrauma or unacceptable alignment changes the pathway.
- Usual direction
- Early spica is common when reduction is acceptable and family care is practical; otherwise selective surgery.
- When to change course
- Obesity, polytrauma, open injury, unacceptable shortening or family constraints may favour operative treatment.
- Usual direction
- Flexible intramedullary nails in suitable size/weight.
- When to change course
- Avoid flexible nails alone once the pattern is length unstable.
- Usual direction
- Submuscular plate or other stable construct.
- When to change course
- Flexible nails risk shortening, malalignment and reoperation.
- Usual direction
- Submuscular plate or lateral trochanteric-entry rigid nail, depending on anatomy and the physis.
- When to change course
- Avoid piriformis entry in skeletally immature children because of femoral head blood supply risk.
- Usual direction
- Antibiotics, tetanus, debridement and damage-control or definitive stabilisation as appropriate.
- When to change course
- Soft tissues, contamination and physiology decide timing more than age alone.
The spica. The hip spica is the workhorse non-operative treatment for femoral shaft fractures in infants and young children. It encases the trunk and the affected leg or legs to hold length and alignment. The practical questions from the history are confirmed before discharge, and the family is taught skin care, hygiene, transport and return precautions; discharging a child in a cast the family cannot safely manage is the failure.
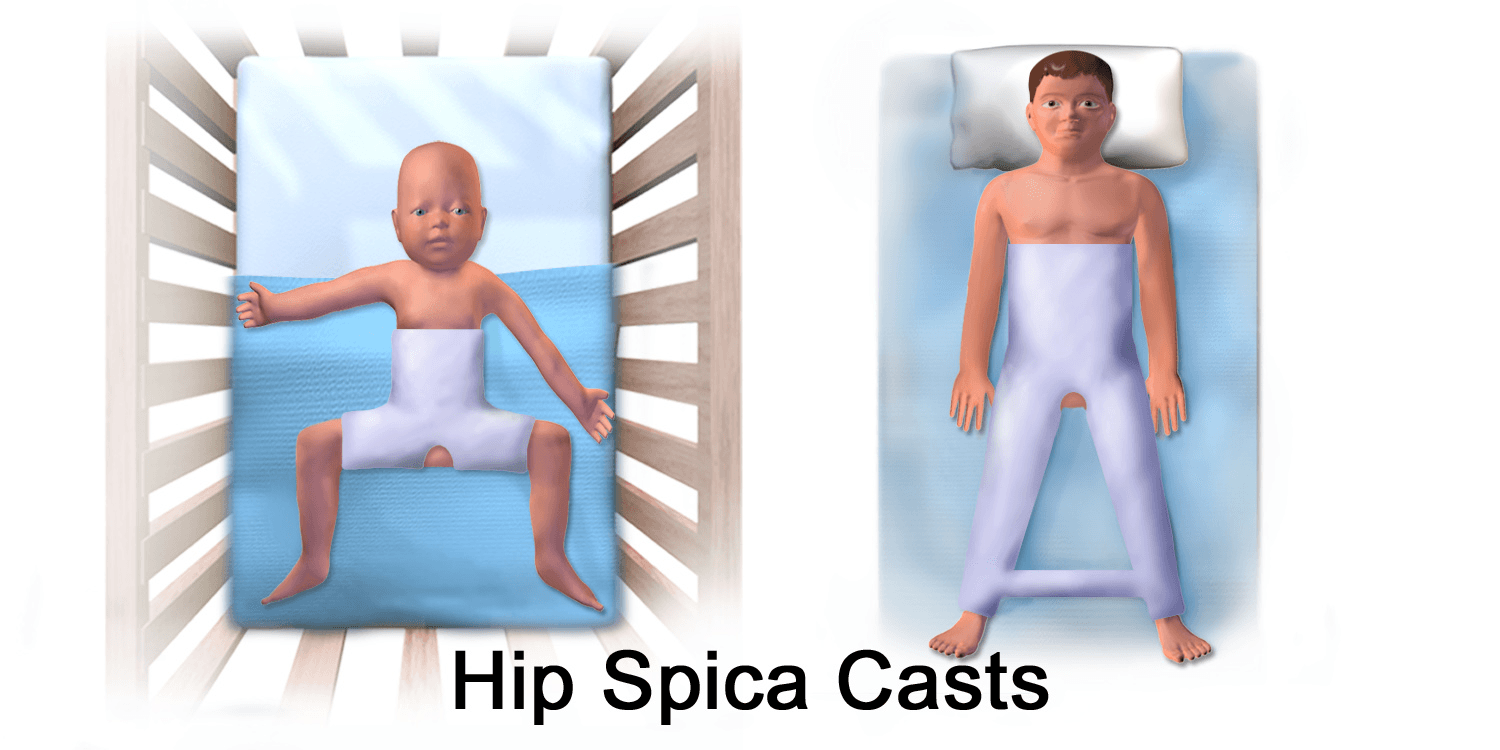
Applying an early hip spica with excessive traction and the knee/hip in marked (90-90) flexion — particularly using a leg-holder and traction during casting — can cause leg (calf) compartment syndrome of the casted limb, a recognised and limb-threatening complication. The modern trend is less flexion, no excessive traction, and a single-leg ("walking") spica for isolated low-energy femoral fractures, with vigilant neurovascular and skin checks after casting.
Choosing the construct. Match the fixation to length stability, weight and comminution; the common failure is flexible nails in a fracture that predictably shortens. A rigid trochanteric-entry nail is used only when maturity and anatomy are appropriate. External fixation is for an open fracture, severe soft-tissue injury or damage control.
Checking rotation. Check rotation clinically after reduction or fixation. The common failure is accepting AP and lateral alignment while missing malrotation.
Acceptable deformity by age
Remodelling potential falls with age, so the tolerated deformity narrows as the child gets older. Acceptable angulation depends on its plane as well as the age, and acceptable apposition also changes with age. Younger children also overgrow, so bayonet shortening of up to ~1.5–2 cm is deliberately accepted in the under-10s. Rotation has no place in the table: it remodels poorly at every age, is not accepted, and must be corrected.
- Varus/valgus
- 30°
- Anterior/posterior angulation
- 30°
- Shortening
- 15 mm
- Varus/valgus
- 15°
- Anterior/posterior angulation
- 20°
- Shortening
- 20 mm
- Varus/valgus
- 10°
- Anterior/posterior angulation
- 15°
- Shortening
- 15 mm
- Varus/valgus
- 5°
- Anterior/posterior angulation
- 10°
- Shortening
- 10 mm
Complications
Early
- Compartment syndrome
- Skin breakdown or cast problems
- Loss of reduction or shortening
- Open-fracture infection
- Associated injuries missed in polytrauma
Late
- Malrotation
- Limb length discrepancy from overgrowth or shortening
- Knee stiffness after flexible nailing or immobilisation
- Refracture after early implant removal
- AVN risk with inappropriate rigid nail entry
Follow-up
What a good result means. Outcome is more than radiographic union. A good result includes acceptable length, rotation and angulation, hip and knee motion, skin integrity, family functioning, a safe return to activity, and no missed safeguarding or polytrauma issue. Stopping follow-up at union is the failure.
What each review checks.
- Skin, pain, and cast or wound problems, early
- Alignment and shortening, until callus is reliable
- Knee and hip motion, after immobilisation or fixation
- Limb length and rotation, measured clinically
- Implant removal, planned only when indicated and timed safely
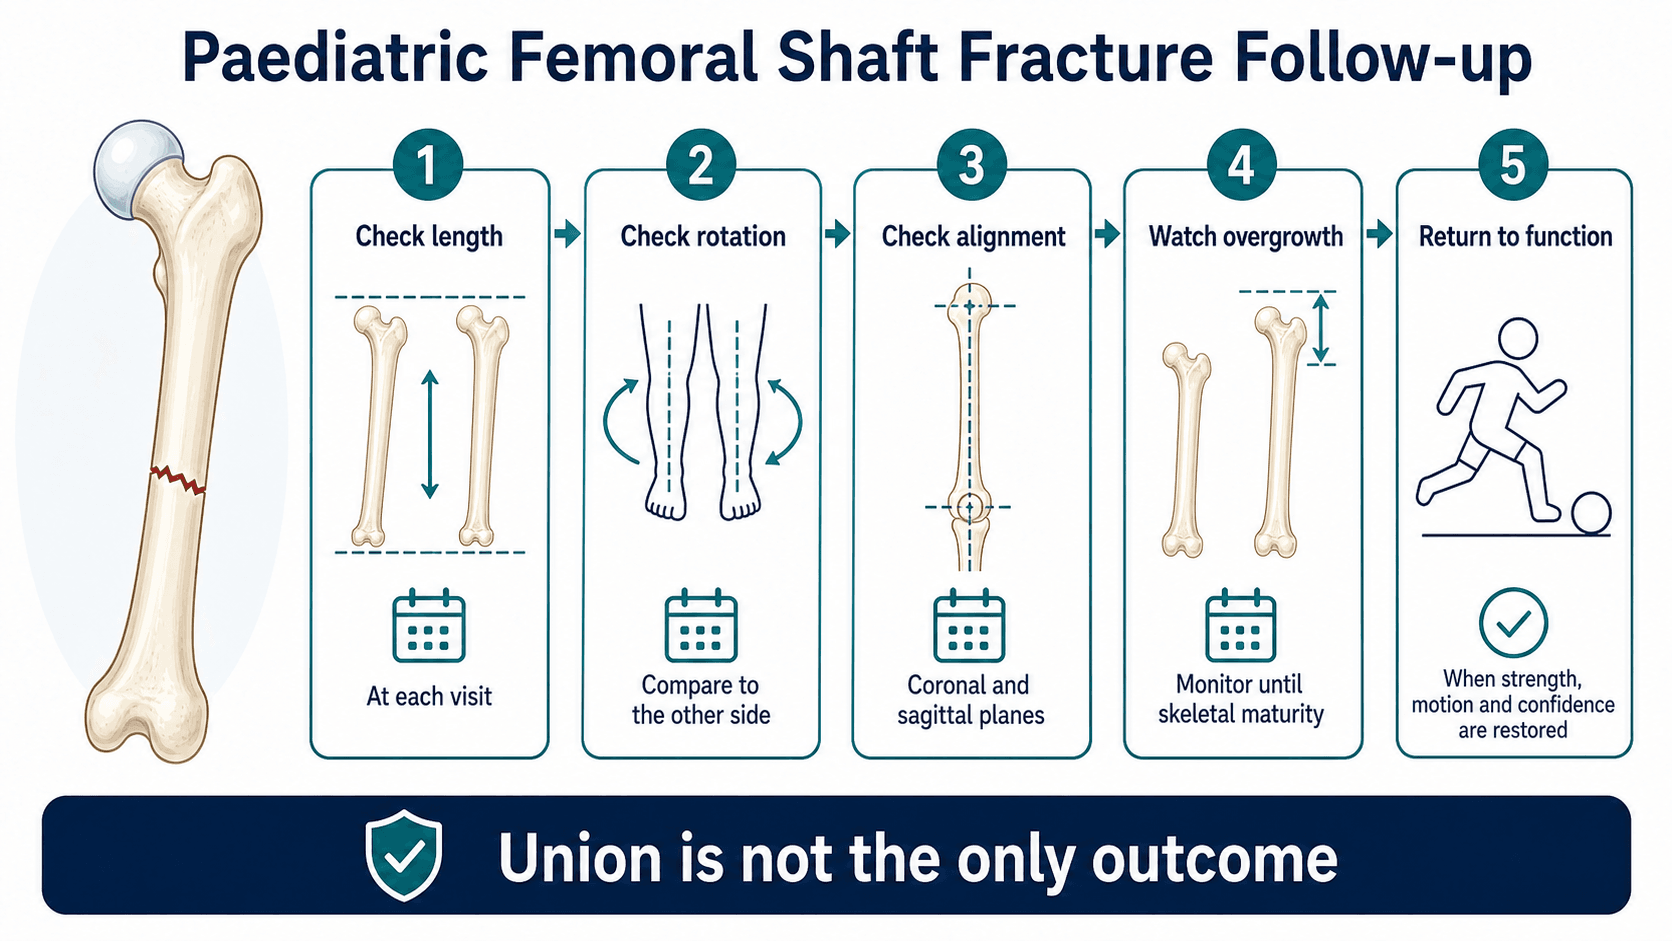
The X-ray heals faster than the child returns to normal life. Rotation, limb length, gait and family burden all need review.
Guidelines, Registries & Global Practice
Paediatric femoral shaft fractures are common worldwide, but implants, resources and pathways differ. The principles below let you defend a plan in any examination system.
Global epidemiology
- Femoral shaft fractures account for roughly 1.5 to 2% of all paediatric fractures, with a bimodal age distribution: a peak in toddlers (often low-energy or non-accidental) and a second peak in adolescents (high-energy).
- There is a consistent male predominance and a strong association of the youngest fractures with non-accidental injury (see Clarke et al, Injury 2012).
- In a non-ambulant infant, abuse rather than implant choice is the dominant clinical question.
Side-by-side guidance
- Emphasis
- Age-banded clinical practice guideline; mandatory abuse evaluation under 36 months; flexible nailing as an option ages 5 to 11.
- Practical signal
- Best-known structured age framework, though several recommendations are weak/inconclusive.
- Emphasis
- Open-fracture and major-trauma standards stress early senior review, analgesia, neurovascular documentation and safeguarding.
- Practical signal
- Process and safeguarding standards rather than implant prescription.
- Emphasis
- Construct-stability principles: relative versus absolute stability, canal fill, submuscular plating technique and safe nail entry.
- Practical signal
- Strong technical guidance for length-unstable and complex fractures.
- Emphasis
- Reinforces age-based selection with growing role of operative fixation in school-age children.
- Practical signal
- Broadly convergent with AAOS, with regional implant preferences.
Registry and outcome notes
- Paediatric femoral shaft fractures are not tracked in arthroplasty registries (NJR, AJRR, AOANJRR), so evidence comes from institutional series and meta-analyses rather than implant-survival registries.
- The most robust comparative evidence is from systematic reviews of flexible nailing versus submuscular plating (Hu et al 2023; Liu et al 2024), which show comparable union and complication trade-offs rather than a single superior implant.
High-resource versus limited-resource practice
- Typical pathway
- Early spica, flexible nails, submuscular plates and image intensifier readily available.
- Reason
- Shorter admissions and early mobilisation are prioritised.
- Typical pathway
- Greater reliance on traction (gallows for infants, skin/skeletal traction for older children) and delayed spica.
- Reason
- Fewer theatre slots, implants and intensifier access make non-operative care safer and more practical.
- Typical pathway
- Safeguarding screening for non-ambulant children and whole-child trauma assessment are non-negotiable.
- Reason
- Child safety and missed polytrauma do not depend on resources.
Controversies and Areas of Uncertainty
The age-based framework hides several genuinely contested decisions. These are the points examiners use to separate a safe trainee from a thinking one.
- Arguments on each side
- Classic teaching warns against flexible nails over about 49 kg; newer series (Atassi) report good results in lighter unstable fractures with full canal fill.
- Pragmatic position
- Weight is a relative, not absolute, contraindication; combine weight, pattern and canal fill rather than a single cut-off.
- Arguments on each side
- Two meta-analyses put numbers on it. Against submuscular plating, elastic nailing carried higher implant irritation (odds ratio 6.49; relative risk 3.36 in the second review), more malalignment (OR 2.60) and more overall complications (OR 4.14) - while nails give shorter operating time, less blood loss and no second incision. The trade-off is real in both directions, but 'roughly equivalent' understates a fourfold difference in overall complications.
- Pragmatic position
- Default to plating for comminuted/heavier patterns; reserve nails for length-stable or lighter children, locking the nails if unstable.
- Arguments on each side
- Immediate spica shortens admission; some advocate short traction first to limit unacceptable shortening.
- Pragmatic position
- Immediate spica is reasonable when shortening is under 2 cm and the family can manage care.
- Arguments on each side
- Some accept up to 2 cm shortening anticipating overgrowth; others find overgrowth unpredictable.
- Pragmatic position
- Accept small shortening deliberately and follow limb length; do not rely on overgrowth to rescue a poor reduction.
- Arguments on each side
- Trochanteric/lateral entry reduces but does not abolish AVN and abductor risk; piriformis entry is unsafe in the immature femur.
- Pragmatic position
- Use lateral trochanteric entry only near skeletal maturity; never piriformis entry with an open physis.
Viva Approach and Common Pitfalls
- Practical meaning
- Use age and size to narrow the safe options.
- Pitfall
- Choosing your favourite implant before assessing the child.
- Practical meaning
- Look for head, chest, abdomen, pelvis, femoral neck and knee injuries.
- Pitfall
- Treating the femur while missing polytrauma.
- Practical meaning
- Skin, toileting, transport, sleep and seating must be safe.
- Pitfall
- Calling spica non-operative but ignoring family burden.
- Practical meaning
- Use them where the fracture can resist shortening.
- Pitfall
- Using nails for unstable comminution without a plan for length.
- Practical meaning
- Compare clinical rotation, not only radiographs.
- Pitfall
- Missing malrotation until gait review.
- Practical meaning
- Review gait, limb length, rotation, stiffness, implant irritation and return to activity.
- Pitfall
- Assuming callus equals recovery.
Common pitfalls
- Choosing treatment from age alone.
- Missing non-accidental injury.
- Ignoring femoral neck or knee associated injury.
- Using flexible nails for an unstable comminuted fracture without plan for shortening.
- Not checking rotation.
- Discharging a spica family without practical education.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“How do you choose treatment for paediatric femoral shaft fracture?”
“A nine-month-old has a femur fracture after a vague fall story. What do you do?”
“A 10-year-old weighing 45 kg has a comminuted, length-unstable mid-shaft femoral fracture. How would you fix it and why?”
Age Ladder
- Infant harness/spica
- Toddler spica
- School-age flexible nails or plate
- Adolescent plate or rigid nail selected
Assess
- Trauma survey
- Skin
- Nerves and vessels
- Mechanism fit
- Pattern stability
Complications
- Malrotation
- LLD
- Cast sores
- Knee stiffness
- Infection
Do Not Miss
- NAI
- Open fracture
- Femoral neck injury
- Floating knee
- Pathological fracture
Evidence Base: Guidelines and Comparative Trials
AAOS clinical practice guideline anchors age-based care
- Children younger than 36 months with a femoral shaft fracture should be evaluated for child abuse.
- Early spica casting or traction with delayed spica is an option for children aged 6 months to 5 years with shortening less than 2 cm.
- Flexible intramedullary nailing is recommended as a treatment option for children aged 5 to 11 years.
- Pre-operative and post-operative documentation should screen for neurovascular injury and leg-length discrepancy.
AAOS guideline adherence is high but did not change outcomes
- Retrospective review of 361 paediatric diaphyseal femur fractures across 2007 to 2012.
- Publication of the 2009 AAOS guideline produced little overall change in treatment selection.
- The only significant shift was a decrease in flexible nailing in children aged 5 to 11 years, contrary to that specific recommendation.
Flexible nails perform well even in length-unstable patterns
- 101 paediatric femoral shaft fractures (mean age 7 years, mean weight 29 kg) treated with flexible elastic nailing.
- 51 of 101 (50%) were length-unstable patterns; all fractures united.
- No revision for malunion: 3 had malrotation greater than 15 degrees, none had leg-length inequality over 1 cm.
- No patient, fracture or treatment characteristic (including instability) predicted complications.
Locking flexible nails controls shortening in unstable fractures
- 107 length-unstable femoral shaft fractures fixed with Enders rods; 37 (35%) locked with a distal cortical screw.
- Locked rods migrated only 1.3 to 1.9 mm versus 12.1 mm for unlocked rods (p less than 0.05).
- Non-locked cases had significantly more limp, clinical shortening and painful palpable rods at follow-up.
- Locking added no extra operative time, blood loss or complications.
Submuscular bridge plating is reliable for complex fractures
- 51 patients (mean age 10 years); 67% high-energy and 55% unstable patterns.
- All fractures united with maintenance of length and alignment, allowing early functional treatment without casting.
- Only 2 significant complications (4%): one plate fracture and one refracture of a pathological fracture after early removal.
- Leg-length discrepancy ranged from 23 mm short to 10 mm long in 4 patients (8%).
ESIN versus submuscular plate: meta-analysis of school-age fractures
- 8 studies, 561 patients comparing elastic stable intramedullary nailing (ESIN) with submuscular plate (SMP).
- ESIN had shorter operative time and less blood loss.
- ESIN had higher implant irritation (OR 6.49), more malalignment (OR 2.60) and more overall complications (OR 4.14).
- No significant difference in limb-length discrepancy, infection, delayed union or unplanned revision.
A femur fracture in a non-ambulant infant is a red flag for abuse
- Incidence of 53 fractures per 10,000 children under 2 years over a 2-year period.
- Femur and skull fractures in the youngest children were most strongly associated with child-protection referral.
- Risk factors for abuse: age under 12 months, non-ambulatory status, delayed presentation, inconsistent history and other injuries.
- Time interval between injury and presentation was unrecorded in 34% of cases, a key documentation failure.
Evidence Base: Implant Choice and Outcomes
ESIN versus plate: complication trade-offs
- 10 studies, 775 paediatric diaphyseal femur fractures (428 ESIN, 347 plate).
- ESIN had shorter surgery, less blood loss, but longer fracture healing time.
- Prominent/irritating implants were markedly more common with ESIN (RR 3.36).
- Infection and angulation deformity rates were similar between constructs.
Stainless-steel flexible nails for unstable fractures need cortical abutment
- 41 stable versus 40 unstable femoral shaft fractures fixed with single-lateral Ender nails.
- All fractures healed at a mean of 1.4 months with no infections or refractures.
- Only minor angular deformities, with no clinically detectable malalignment in either group.
- One Winquist grade IV comminuted fracture developed a 3 cm leg-length difference.
AAOS guideline checklist adherence in practice
- 313 children reviewed after embedding AAOS-based checklists into the EMR order set.
- 89.9% received age-appropriate treatment consistent with the AAOS guideline after implementation.
- Complication rates were identical (12%) before and after checklist implementation.
- Standardised checklists improved process documentation but not outcomes.
Paediatric biology principle: remodelling, overgrowth and rotation
- Coronal and sagittal angulation remodel with growth, especially near the physis and in younger children.
- Rotational deformity does NOT remodel and must be corrected at treatment.
- Femoral overgrowth after shaft fracture in young children averages roughly 1 cm (reported means about 0.9 to 1.2 cm, occasionally up to 2 cm), which supports accepting a small deliberate shortening (under 2 cm) in some spica-treated cases.