Anabolic Steroids, Stimulants & 'Doping'
- Doping means performance- and appearance-enhancing substances, principally anabolic-androgenic steroids and stimulants
- Anabolic steroids build muscle and strength but cause serious, sometimes permanent, cardiovascular, hepatic, renal, endocrine and psychiatric harm
- An unexpected or bilateral tendon rupture in a muscular athlete should raise the possibility of anabolic steroid use
- The tendon-rupture association is firm; the mechanism is a hypothesis, and the most-cited series proposes a behavioural one
- In the six-patient bodybuilder series, repair did well despite continued steroid use, and one patient died of a myocardial infarction within a year
- The response is recognition, honest counselling and treatment, anti-doping (WADA) compliance and education/prevention
- “Hepatic harm (cholestasis, tumours) is linked especially to oral 17-alpha-alkylated agents
- “Stimulants: cardiovascular (palpitations, hypertension, arrhythmia) and heat-illness risk
- “WADA lists a substance that meets at least two of three criteria: performance enhancement, health risk, spirit of sport
Overview
Doping is the use of performance- and appearance-enhancing drugs and substances. The principal agents are anabolic-androgenic steroids (AAS) and stimulants, with growth hormone, diuretics (for weight or masking), erythropoietin and blood doping, and various supplements alongside them. The drug classes are WADA-prohibited, and doping is an ethical issue in sport as well as a health one.
Why the orthopaedic surgeon meets it. Performance-enhancing drug use often becomes relevant to the orthopaedic surgeon through its musculoskeletal consequence, and a tendon rupture may be the presenting sign of doping. Recognising the drug use matters beyond the injury, because doping can cause severe and sometimes permanent organ damage, including liver, kidney and heart disease. Recognition is what lets athletes, adolescents included, receive the care, treatment and education needed to reduce those risks.
Anabolic-Androgenic Steroids
AAS increase muscle mass and strength. The price is a wide range of serious, sometimes permanent, adverse effects:
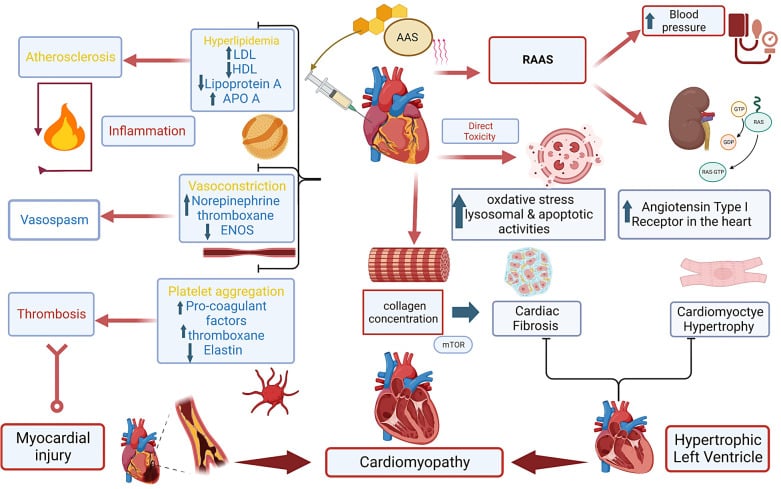
- Cardiovascular: cardiomyopathy, hypertension, dyslipidaemia and thrombosis
- Hepatic: cholestasis and hepatic tumours, especially with oral 17-alpha-alkylated agents
- Renal: renal disease
- Endocrine: testicular atrophy and hypogonadism, gynaecomastia, and virilisation in women
- Psychiatric: aggression ('roid rage'), mood disturbance and dependence
- Acne
- In adolescents: premature physeal closure and stunted growth
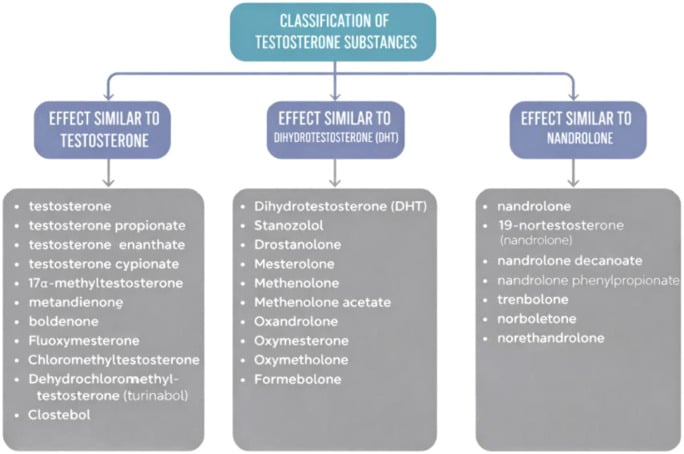
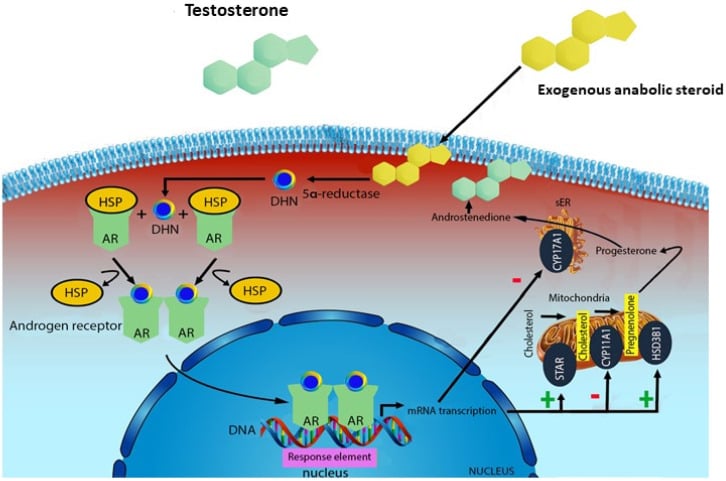
The first two figures show how the preparations are grouped and how an exogenous steroid acts on the cell.
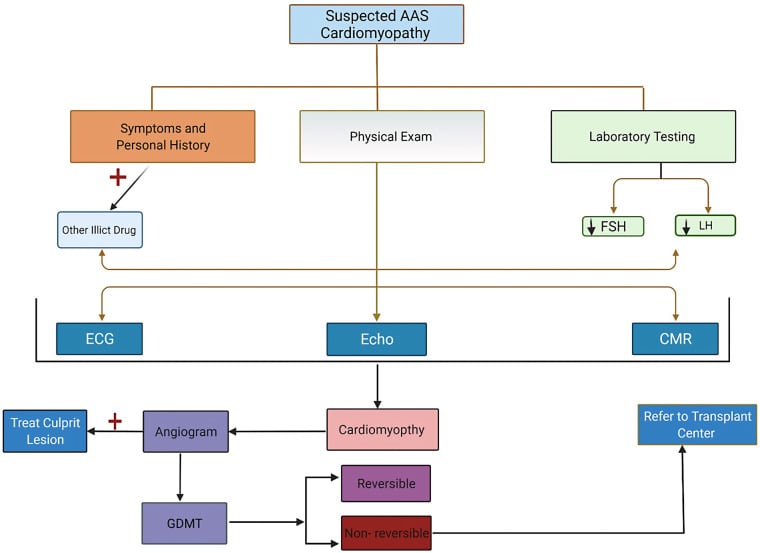
The two cardiac figures set out the pathways from AAS to cardiomyopathy and a work-up for the patient in whom it is suspected.
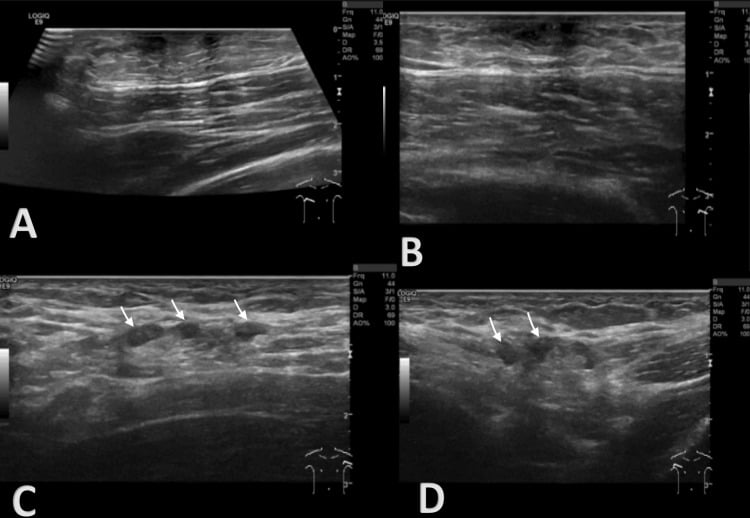
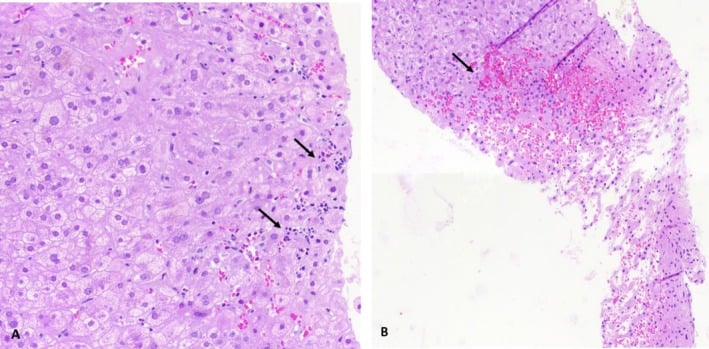
Two case figures show the endocrine and hepatic harms in individual patients.
Tendon Rupture: The Orthopaedic Clue
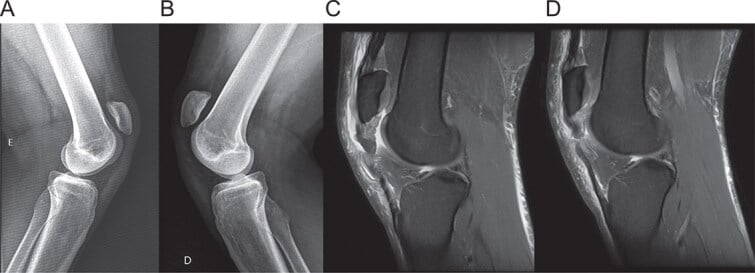
The association. AAS use is associated with tendon rupture, the key orthopaedic adverse effect. Classically it is the pectoralis major, but the Achilles, quadriceps/patellar and biceps tendons also rupture. An unexpected, spontaneous or bilateral tendon rupture in a notably muscular athlete should therefore prompt consideration of anabolic steroid use.
The mechanism is debated. The familiar explanation is that steroids strengthen muscle disproportionately to tendon, so the tendon fails. The series most often cited for the association proposes a behavioural route instead: steroid use contributes through an excessive upward adjustment of the athlete's lifting goals, so the athlete simply loads more, rather than through any demonstrated change in tendon material properties.
What to say. Both explanations remain hypotheses, and the mechanism is asserted more often than demonstrated. Present the association confidently and the mechanism tentatively.
What the Bodybuilder Series Actually Found
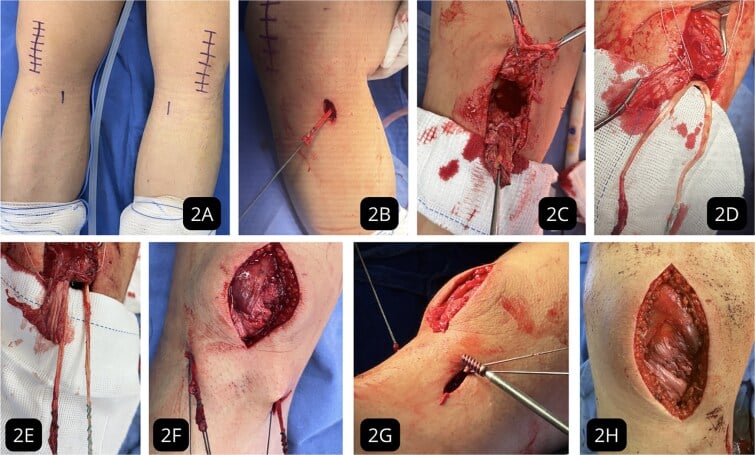
The series. Stefanou and colleagues reported six male bodybuilders who ruptured the pectoralis major during weightlifting, followed for a mean of 16 months. Besides the behavioural mechanism above, they observed that the injury was probably not related to limb dominance.
Continued use did not spoil the repair. All six were treated surgically and had excellent results by Bak criteria, returning to full activity at a mean of 5.4 months (5 to 7). There were no postoperative complications despite continued anabolic steroid use, and suture-anchor fixation succeeded regardless of the chronicity of the repair.
What that does and does not show. The result cuts against the assumption that ongoing use ruins tendon healing, and against any reflex urgency about operating early. Six patients at 16 months' mean follow-up settle neither question.
One of the six died. Within a year of surgery, one patient died of a myocardial infarction. One death in six is not an incidence, but it is the proportion worth carrying: the tendon is the visible problem and the cardiovascular disease is the one that kills. A pectoralis rupture in a heavily muscled lifter is a reason to ask about cardiovascular symptoms and arrange assessment, not simply to book the repair; that risk belongs with sudden cardiac death in athletes.
Stimulants and the Other Doping Classes
Stimulants. Amphetamines and certain pre-workout agents enhance alertness and performance. They carry cardiovascular risks, namely palpitations, hypertension, arrhythmia and a contribution to sudden cardiac events, and increase the risk of heat illness and dehydration.
Erythropoietin and blood doping. EPO, blood transfusion or hypoxia-mimetics raise the red-cell mass and haematocrit, and with it oxygen-carrying capacity and endurance. The harm is hyperviscosity, leading to thrombosis (DVT/PE, stroke, myocardial infarction) that has been implicated in athlete deaths, plus hypertension.
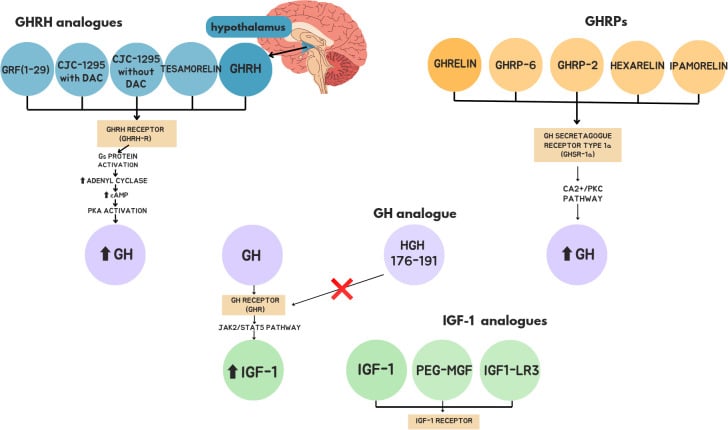
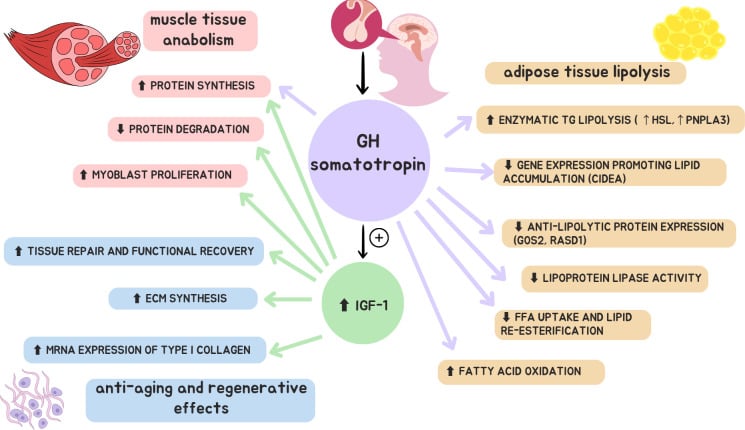
Growth hormone. GH is taken for a claimed anabolic and recovery benefit, although the ergogenic evidence is weak. Its harms, several of them orthopaedically relevant, are acromegalic soft-tissue and bony overgrowth (coarse features, enlarged jaw, hands and feet), carpal tunnel syndrome, arthralgia with joint swelling and fluid retention, and insulin resistance and diabetes.
Beta-blockers. They reduce heart rate and tremor, so they are banned specifically in precision and aiming sports such as archery and shooting, where a steady hand matters. They are not ergogenic in endurance or power sport.
Diuretics. Diuretics are used to make weight through rapid fluid loss, and as masking agents that dilute the urine to hide other prohibited drugs. Their harms are dehydration, electrolyte disturbance and cramps.
The WADA Anti-Doping Framework
The Prohibited List. The World Anti-Doping Agency (WADA) publishes an annual Prohibited List of banned substances and methods, some prohibited at all times and others in-competition only. A substance is included if it meets at least two of three criteria: performance enhancement, health risk, or violation of the spirit of sport.
Strict liability. The athlete is responsible for any prohibited substance found in their sample, regardless of intent or how it got there. A violation therefore needs no proof of fault, which is why contaminated supplements are a real hazard.
Therapeutic Use Exemption (TUE). A TUE allows an athlete to use an otherwise-prohibited substance for a legitimate medical condition, insulin for diabetes for example, if the criteria are met and it is approved in advance.
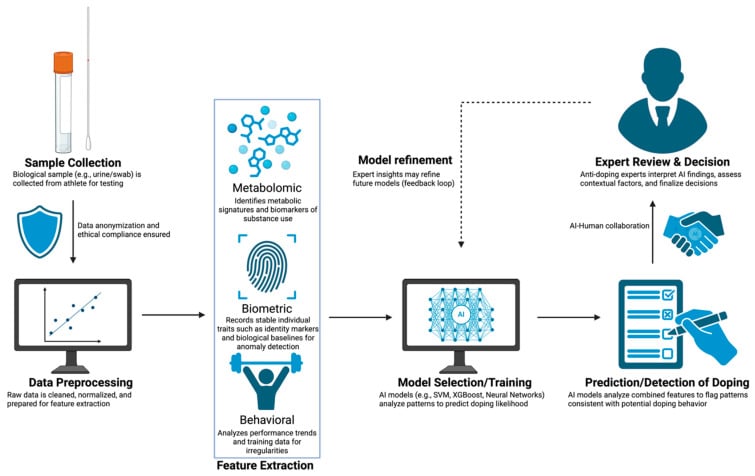
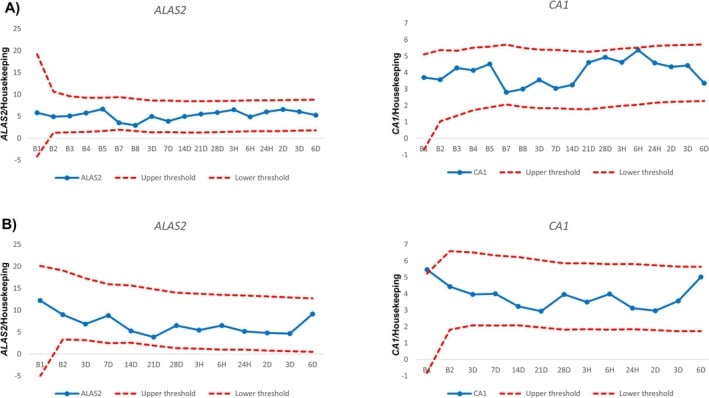
Athlete Biological Passport (ABP). The passport monitors the athlete's own biological markers over time and detects doping indirectly, through deviations from that athlete's baseline, rather than detecting the drug itself. Testing is both in- and out-of-competition. The passport has a haematological module (haemoglobin and reticulocytes) for blood doping and EPO, and a steroidal module (the urinary steroid profile).
Recognition and Response
Recognising the doping athlete. Apart from the tendon rupture, the signs of doping can mimic other health concerns: palpitations, acne, mood change, headaches and cramps.
The response. Management is recognition, honest counselling, and treatment of the health consequences, with compliance with the anti-doping (WADA) framework. Education and prevention foster an anti-doping culture among athletes, coaches and clinicians. For the orthopaedic surgeon, this means recognising the doping athlete behind a tendon rupture and addressing the underlying issue, rather than treating the tendon rupture in isolation.
Mnemonics & Memory Aids
STEROIDS
Hook:STEROIDS: Stimulants/Steroids, Tendon rupture, Endocrine effects, 'Roid rage, Organ damage, Identify the athlete, Doping (WADA)/education, Stimulant CV/heat risk.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A very muscular gym athlete sustains a pectoralis major rupture with little provocation. What should you suspect, and what are the wider concerns?”
The substances
- Anabolic-androgenic steroids; stimulants
- Growth hormone; diuretics (weight/masking); erythropoietin/blood doping; supplements
- WADA-prohibited; an ethical and health issue in sport
Anabolic-steroid harms
- Cardiovascular: cardiomyopathy, hypertension, dyslipidaemia, thrombosis
- Hepatic (cholestasis/tumours - oral 17-alkylated); renal disease
- Endocrine (hypogonadism/gynaecomastia/virilisation); psychiatric ('roid rage'/dependence); adolescent physeal closure
Orthopaedic relevance
- TENDON RUPTURE (pectoralis major, Achilles, quadriceps/patellar, biceps) - association firm, mechanism debated
- Suspect AAS in an unexpected/bilateral rupture in a muscular athlete; repair did well despite continued use (6 cases)
- One of those six died of a myocardial infarction within a year - assess the cardiovascular risk too
- Stimulants: cardiovascular (palpitations/arrhythmia) + heat-illness risk
Response
- Recognition (signs can mimic other conditions)
- Treat injury + health consequences; honest counselling
- Anti-doping (WADA) framework + education/prevention (anti-doping culture)
Evidence & Key Studies
Appearance- and performance-enhancing drugs and substances - recognition and prevention
- Commonly used appearance/performance-enhancing substances ('doping') include anabolic-androgenic steroids, stimulants, diuretics, growth hormone and supplements.
- Signs and symptoms can mimic other health concerns (palpitations, stunted growth, acne, severe headaches, muscle cramps, dizziness, dehydration), and some effects are severe and long-term.
- Doping can lead to severe and sometimes permanent organ damage, including liver, kidney and heart disease; recognition, treatment and education/prevention (fostering an anti-doping culture) are important.
Pectoralis major rupture in body builders: a case series including anabolic steroid use
- Six male bodybuilding athletes who sustained a pectoralis major rupture during weightlifting, with the location and type of injury, the history and type of anabolic steroid use, the method of repair and the outcome recorded. Mean follow-up was 16 months (12 to 24).
- All patients treated surgically had excellent results by Bak criteria and returned to full activity at a mean of 5.4 months (5 to 7). No postoperative complications occurred despite continued anabolic steroid use, and suture-anchor fixation gave excellent results regardless of the chronicity of the repair. One patient died of a myocardial infarction within a year of surgery.
- The authors suggest anabolic steroid use may contribute to the injury through an excessive upward adjustment of the athlete's lifting goals rather than a demonstrated change in tendon properties, and that the rupture is probably not related to limb dominance. With six patients this is a case series, so it establishes what can happen rather than how often, and cannot support a rupture risk estimate.
The common performance/appearance-enhancing substances (anabolic-androgenic steroids, stimulants, diuretics, growth hormone, supplements), the fact that their signs can mimic other conditions, and that doping can cause severe and sometimes permanent organ damage (liver, kidney, heart) with recognition, treatment and education/prevention being important, come from the cited Siegmund review. The specific adverse- effect profile of anabolic-androgenic steroids (cardiovascular/hepatic/endocrine/psychiatric, adolescent physeal closure), the key orthopaedic association with TENDON RUPTURE (pectoralis major, Achilles, quadriceps), the cardiovascular/heat risks of stimulants, and the anti-doping (WADA) framework are standard, well-established teaching. The surgical outcomes, the finding that continued steroid use did not compromise repair, the death from myocardial infarction and the proposed behavioural mechanism come from the Stefanou series of six patients, which is too small to give any rate. The Siegmund citation is a nursing review rather than a study. No cohort quantifies the tendon-rupture risk attributable to anabolic steroids, no controlled study demonstrates altered human tendon material properties from them, and no evidence establishes whether stopping steroids before or after tendon repair changes the outcome - so none of those figures is quoted here.