The Physis (Growth Plate)
Overview & development
Development. The physis develops from cartilage-committed mesenchymal cells expressing the SOX family of genes. It is the site of endochondral ossification, the orderly conversion of a cartilage template into bone that drives longitudinal growth, and its multilayered structure is built by chondrocyte proliferation and hypertrophy. Disturbances of physeal development and physiology produce the skeletal dysplasias.
How much each physis grows. The physes do not contribute equally, which is why some fractures remodel well and why epiphysiodesis timing matters. In the lower limb growth is "around the knee"; in the upper limb it is "away from the elbow":
- Distal femur, the fastest: about 9 to 10 mm per year, roughly 70% of femoral and about 38% of lower-limb growth
- Proximal tibia, next: about 6 mm per year, roughly 55 to 60% of tibial and about 27% of lower-limb growth
- Together the knee physes give about 65% of lower-limb length
- Proximal humerus: roughly 80% of humeral growth
- Distal radius and ulna: about 80% of forearm growth
The elbow. The elbow physes therefore contribute little, which is why elbow fractures remodel poorly and need accurate reduction.
Maturity and remaining growth. Physes close at roughly age 14 in girls and 16 in boys, better judged by bone age (Greulich-Pyle / Sanders). Remaining growth for epiphysiodesis timing is estimated with:
- the Menelaus rule of thumb: about 10 mm a year from the distal femur and 6 mm from the proximal tibia, with girls growing to 14 and boys to 16
- the Green-Anderson growth-remaining charts
- the Moseley straight-line graph
- the Paley multiplier
Concepts: histology & the four zones
The physis is read from the epiphyseal side to the metaphyseal side, and the four zones follow in that order.
- Cells / activity
- Stem-like chondrocytes; matrix synthesis/storage
- Key features
- Low oxygen, scattered cells; the germinal source
- Clinical link
- Source layer; damage here harms future growth
- Cells / activity
- Rapidly dividing flattened cells in columns
- Key features
- Highest oxygen/glycogen; site of LONGITUDINAL growth
- Clinical link
- Fed by epiphyseal vessels; arrest if supply lost
- Cells / activity
- Enlarging cells → apoptosis (maturation/degeneration/provisional calcification)
- Key features
- Most cell volume, least matrix; mineralisation begins
- Clinical link
- WEAKEST zone — Salter-Harris fracture plane
- Cells / activity
- Matrix mineralises; vessels invade; osteoblasts form bone
- Key features
- Primary spongiosa; metaphyseal ingrowth vessels
- Clinical link
- Site of new bone; rickets widens this region
Where growth happens. Longitudinal growth happens mainly in the proliferative zone, through cell division and column formation. The hypertrophic zone adds height as its cells enlarge.
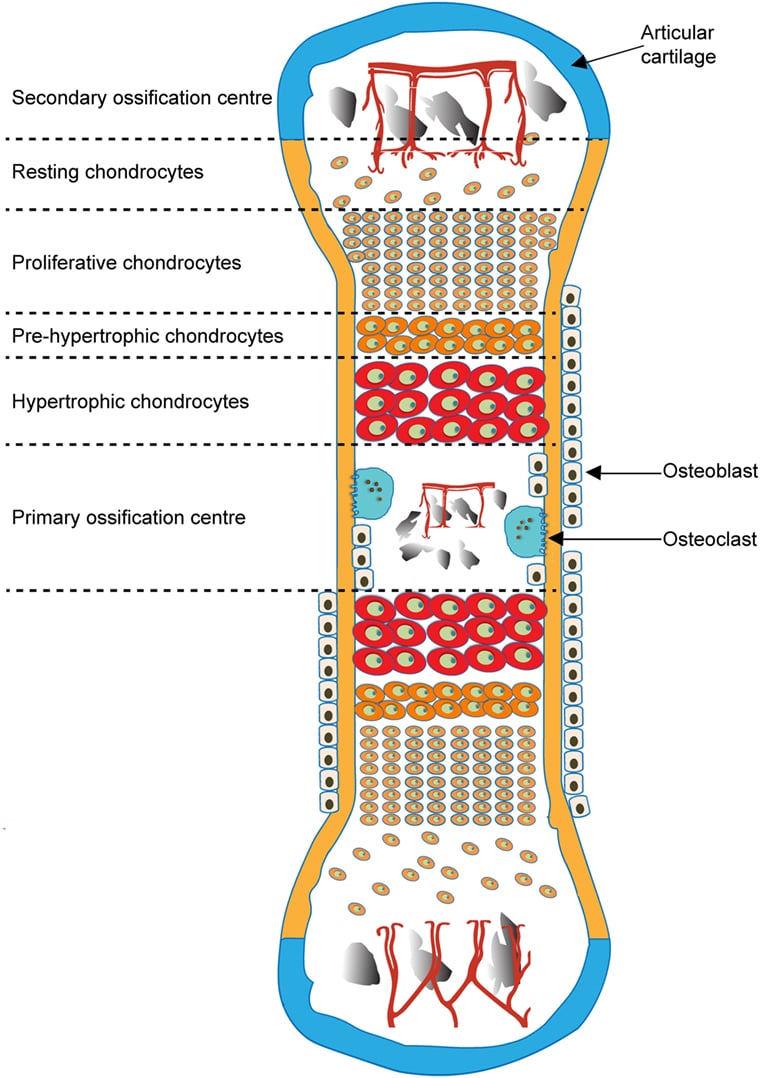
Matrix and mineralisation. The matrix is rich in collagens (mainly types II, IX, X and XI) and proteoglycans (aggrecan, decorin). The resting and proliferative zones lay down a type II / IX / XI collagen and aggrecan-rich matrix. In the hypertrophic zone, terminally differentiated chondrocytes switch to type X collagen and release alkaline phosphatase, calcium and matrix vesicles.
Provisional calcification. The matrix then mineralises before the hypertrophic cells undergo apoptosis. Metaphyseal vessels bring in osteoblasts, which form the primary spongiosa.
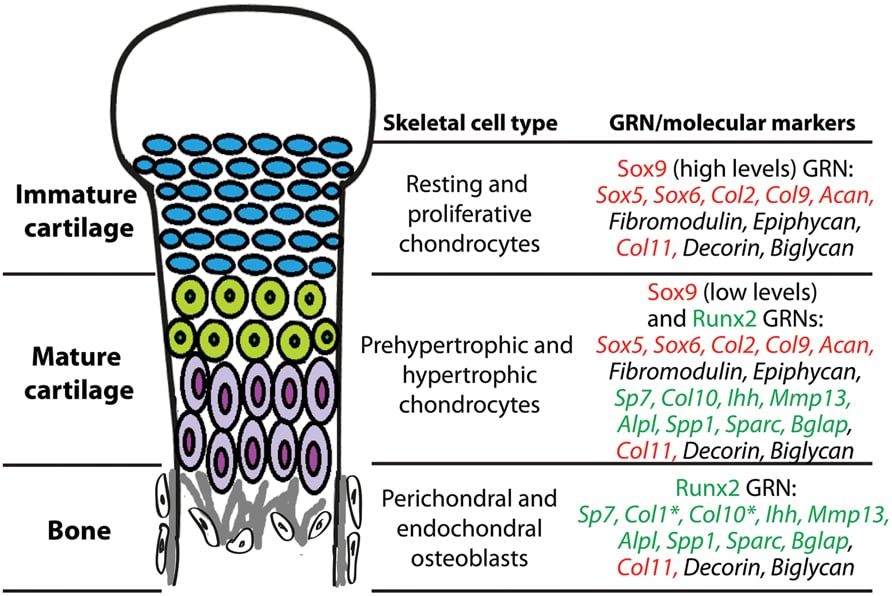
Why the hypertrophic zone fails. It has the largest cells, the least extracellular matrix per unit volume and a partially mineralised, transitional structure, which makes it mechanically the weakest layer. Shear and avulsion forces propagate through it, and it is the plane of the Salter-Harris fracture.
Why that usually spares growth. The germinal reserve and proliferative zones lie on the epiphyseal side of that plane and keep their epiphyseal blood supply, so most physeal fractures heal without growth disturbance. Growth arrest follows only when the germinal layers or their blood supply are damaged (crush / SH-V, or a bony bar across the plate).
RPHCThe four zones, in order
Hook:'Real Patients Have Cartilage' — Reserve, Proliferative, Hypertrophic, Calcification, top (epiphysis) to bottom (metaphysis).
Blood supply & surrounding structures
Epiphyseal vessels supply the reserve and proliferative zones. Their disruption is catastrophic for growth, because it starves the dividing cells and the plate arrests.
Metaphyseal vessels supply the zone of provisional calcification, the ossification front, and remove debris. Their loss impairs ossification, but the germinal cells survive.
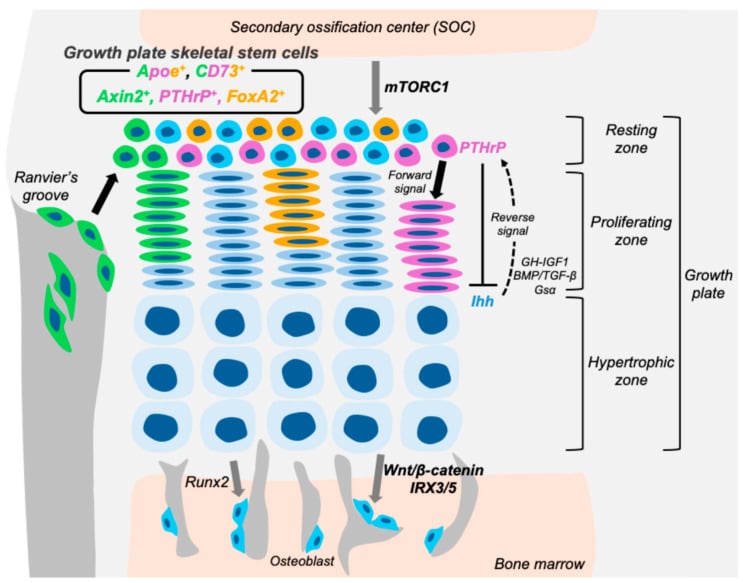
The periphery. Two rim structures sit around the plate, and they are easily swapped. The groove of Ranvier is a wedge of cells at the periphery that adds chondrocytes there, driving latitudinal (appositional, width) growth. The perichondral ring of LaCroix is a fibrous collar around the physis that gives mechanical support and limits shear.
Two directions of growth. Examiners like the pairing: proliferative zone = length, groove of Ranvier = width, ring of LaCroix = support.
Molecular & endocrine regulation
The PTHrP-Ihh loop. The pace of chondrocyte maturation is set by a negative-feedback loop. As proliferating chondrocytes begin to mature, they secrete Indian hedgehog (Ihh), which (directly and via the perichondrium) stimulates production of parathyroid hormone-related protein (PTHrP) near the ends of the bone. PTHrP acts on its receptor to keep chondrocytes proliferating and delay their hypertrophic differentiation.
Closing the loop. As cells move away from the PTHrP source they escape its influence, hypertrophy and release more Ihh. The axis therefore tightly controls the proportion of proliferating to hypertrophic cells, and with it the rate of growth.
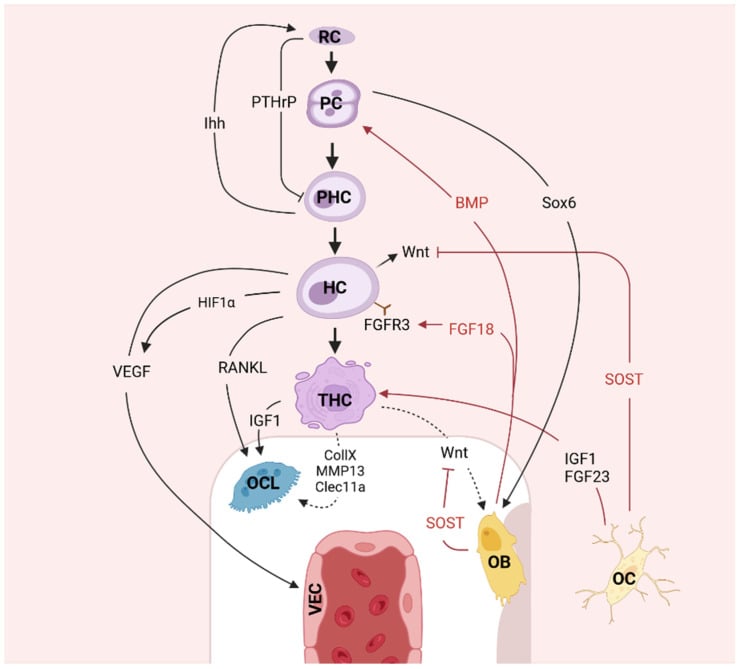
Systemic hormones and other local factors act on the same zones:
- Effect on the growth plate
- Keeps chondrocytes proliferating; delays hypertrophy (with Ihh, the master local loop)
- Effect on the growth plate
- From prehypertrophic cells; stimulates PTHrP and proliferation; couples to osteoblast formation
- Effect on the growth plate
- Stimulates proliferative-zone chondrocytes (GH acts partly directly, partly via IGF-1)
- Effect on the growth plate
- Drives chondrocyte hypertrophy and ossification; deficiency delays bone age
- Effect on the growth plate
- Accelerate maturation and ultimately cause physeal CLOSURE (oestrogen is the key closer in both sexes)
- Effect on the growth plate
- Regulate chondrocyte differentiation and the cartilage-to-bone transition
- Effect on the growth plate
- Vitamin D needed for mineralisation; glucocorticoids suppress growth
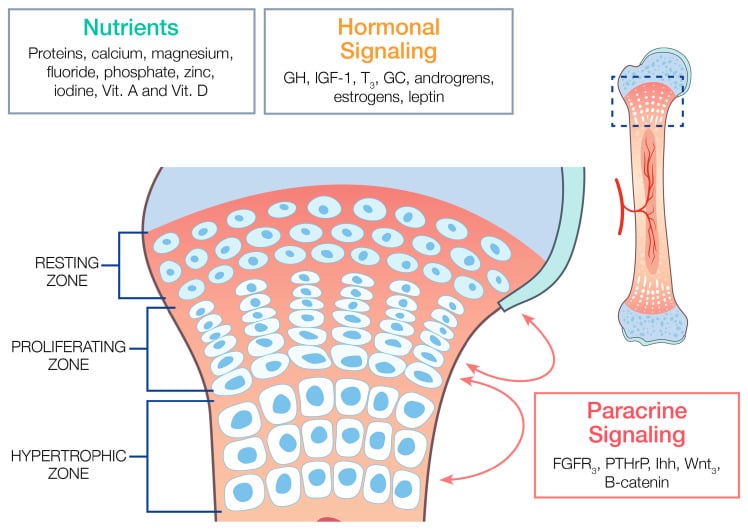
Clinical correlations. Because these pathways converge on the physis, their disturbance produces recognisable disease:
- Rickets (defective mineralisation) widens the hypertrophic and provisional calcification zones and frays the metaphysis
- Achondroplasia results from an activating FGFR3 mutation that inhibits proliferation
- Oestrogen, not testosterone, drives physeal closure in both sexes: precocious puberty brings early closure and short stature, and oestrogen deficiency tall stature
- Growth hormone excess or deficiency alters longitudinal growth
Clinical significance
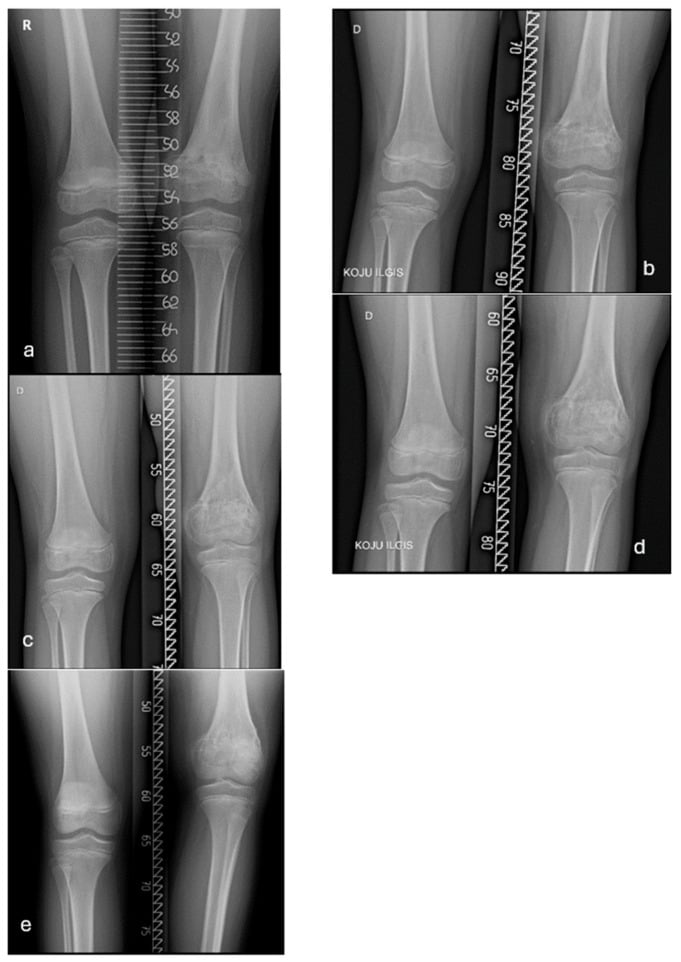
Fractures and growth arrest. When a physeal fracture injures the germinal zones, or a physeal bar forms, the result is growth arrest, angular deformity or limb-length discrepancy. Arrest may become evident only after the fracture has united, so comparison of serial radiographs over time is essential.
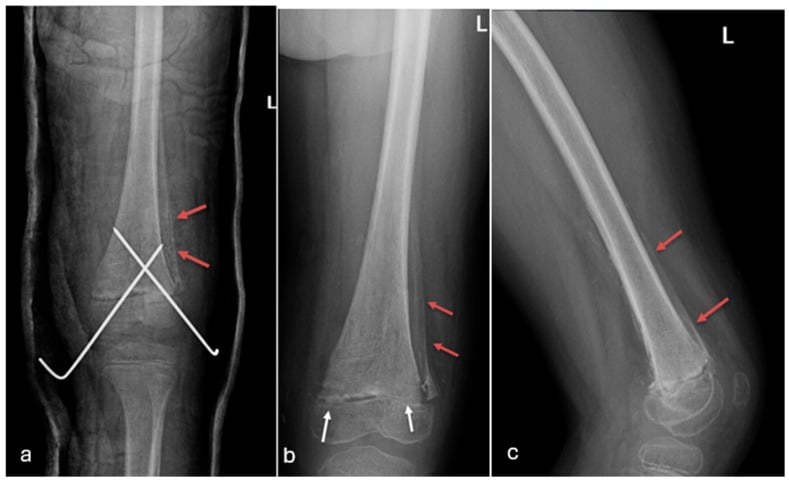
Limb-length discrepancy. Serial calibrated standing radiographs document a changing discrepancy during growth. The trend, skeletal maturity and remaining growth determine whether observation, epiphysiodesis, lengthening or deformity correction is appropriate.
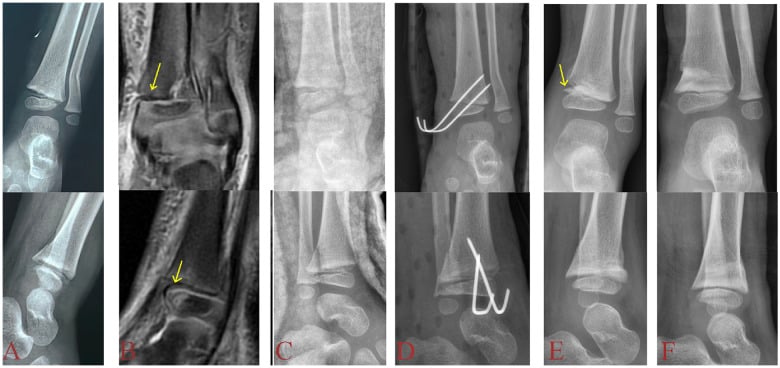
Persistent widening after reduction. Physeal widening that persists after reduction is a warning sign. In the case below, MRI identified periosteum trapped in the anteromedial distal tibial physis, and repeat radiographs remained abnormal until the interposed tissue was addressed: imaging that changed management rather than merely confirming the fracture.
Infection and surgery. The physis is the route of haematogenous osteomyelitis, through sluggish metaphyseal flow. It is also the target of guided-growth surgery (tension-band plating, for example, or epiphysiodesis) that deliberately modulates the plate to correct deformity or length.
The Hueter-Volkmann law. The physis is mechanosensitive. Increased compression across the plate slows longitudinal growth, while reduced compression (or tension/distraction) accelerates it, and this is the mechanics that makes guided growth work.
Guided growth. A tension-band plate or staple that tethers one side of the physis (a hemiepiphysiodesis) slows that side while the other keeps growing, gradually correcting an angular deformity (e.g. genu valgum/varum). It is reversible: remove the implant and growth resumes. A complete epiphysiodesis is permanent and is used to equalise limb length.
The same law explains deformity. Pathological compression of part of the plate, as at the medial proximal tibia in Blount disease (tibia vara), or an asymmetric physeal bar tethering one region produces progressive angular deformity.
Viva practice
Exam viva
Practise clinical reasoning and management decisions out loud
“Describe the histological zones of the growth plate from the epiphysis to the metaphysis, and tell me which zone fails in a physeal fracture and why.”
“How is chondrocyte proliferation and maturation regulated at the growth plate, and how does the periphery of the physis grow?”
Exam cheat sheet
Zones (epiphysis → metaphysis)
- Reserve (resting): germinal, matrix storage, low O2
- Proliferative: dividing columns = LONGITUDINAL growth; high O2/glycogen
- Hypertrophic: cells enlarge/mineralise/apoptose; WEAKEST = Salter-Harris plane
- Provisional calcification / chondro-osseous junction: vessel invasion, primary spongiosa
Blood supply & periphery
- Epiphyseal vessels → reserve/proliferative (loss = growth arrest)
- Metaphyseal vessels → ossification front
- Groove of Ranvier = width (latitudinal) growth; Ring of LaCroix = mechanical support
Regulation
- PTHrP-Ihh feedback loop = master local control (PTHrP delays hypertrophy)
- GH/IGF-1 (proliferation), thyroid (hypertrophy), oestrogen (closes the plate in both sexes)
- BMP/TGF-beta, Wnt/beta-catenin, vitamin D modulate differentiation/mineralisation
Clinical links
- Physeal fractures through the hypertrophic zone; growth arrest if germinal zones/bar
- Rickets widens the hypertrophic/calcification zone; achondroplasia = FGFR3
- Guided growth (tension-band plate / epiphysiodesis) modulates the plate
Evidence Base
Developmental regulation of the growth plate
- Landmark review of endochondral bone formation - the single process generating almost the entire skeleton - and the signalling pathways and transcription factors that control it.
- Synthesises the PTHrP-Indian hedgehog feedback loop, FGF (FGFR3), BMP and Wnt signalling and the master transcription factors (e.g. Sox9, Runx2) governing chondrocyte proliferation and hypertrophy.
- Frames how disturbance of these pathways produces the skeletal dysplasias (e.g. FGFR3 in achondroplasia).
Morphology and physiology of the epiphyseal growth plate
- Describes the multilayer growth plate: resting (protein synthesis/germinal), proliferative (rapid duplication), transformation/hypertrophic and degenerative zones with intensive mineralisation and chondrocyte apoptosis.
- Matrix is composed of collagens (mainly II, IX, X, XI) and proteoglycans (aggrecan, decorin); regulation involves growth/thyroid/sex hormones, beta-catenin, BMPs, IGF, TGF-beta and vitamin D.
- Identifies PTHrP (from the perichondrium) as the most significant factor, stimulating proliferation and delaying hypertrophy, with an Indian hedgehog (Ihh) feedback loop; disturbances cause skeletal dysplasia.
Imaging findings of metabolic bone disease
- Impaired chondrocyte development and failure to mineralise growth-plate cartilage in rickets lead to WIDENED growth plates and frayed metaphyses at sites of greatest growth.
- Thyroid hormone regulates endochondral bone formation; untreated congenital hypothyroidism delays bone age and produces irregular/fragmented epiphyses.
- Illustrates how systemic metabolic derangements manifest specifically at the physis and metaphysis.
The developmental signalling framework (PTHrP-Ihh, FGFR3, BMP/Wnt, Sox9/Runx2) is the classic synthesis of Kronenberg 2003 (DOI); the zonal structure, matrix composition and the PTHrP-Ihh regulatory loop are detailed by Burdan et al. 2009 (DOI); and the physeal manifestations of metabolic bone disease (rickets, hypothyroidism) by Chang et al. 2016 (DOI). The classic descriptions of the perichondral ring of LaCroix, the groove of Ranvier and the dual epiphyseal/metaphyseal blood supply are standard physeal anatomy used in these and related works.