Young Athlete Calf Claudication | Anomalous Gastrocnemius | Love-Whelan Types | Surgical Release
- Think PAES in any young athlete with calf claudication and normal resting pulses
- Functional entrapment (Type VI) = normal anatomy, hypertrophied gastrocnemius compresses artery during plantarflexion
- Provocative manoeuvres (active plantarflexion, passive dorsiflexion) abolish or diminish pedal pulses
- CT or MR angiography with provocative positioning is the diagnostic gold standard
- Surgical myotomy of the offending muscle head with arterial reconstruction if the vessel is diseased
- “PAES vs CECS: PAES = vascular symptoms (claudication, pallor); CECS = myofascial pain and paraesthesiae with normal pulses
- “Bilateral imaging mandatory even if unilateral symptoms
- “Popliteus muscle or fibrous bands can also entrap (Love-Whelan Type IV)
- “Chronic entrapment may cause popliteal artery thrombosis or aneurysm formation
Overview and Epidemiology
Popliteal artery entrapment syndrome (PAES) is the most common cause of non-atherosclerotic claudication in young athletes. It is frequently missed, and left untreated, chronic PAES may progress to popliteal artery thrombosis, aneurysm formation, or even acute limb ischaemia requiring emergency revascularisation. Acute ischaemia is rare, but it is reported in late presentations with thrombosis.
Who. Patients are aged 15 to 40 years, peaking at 20 to 30, and the male-to-female ratio is approximately 2:1, although PAES is increasingly recognised in female athletes. Athletes are over-represented because of muscle hypertrophy. The typical patient is an athlete or military recruit with no diabetes, smoking or hyperlipidaemia.
How common. Anatomical variants are present in approximately 3 to 5 percent of cadaveric specimens. Imaging shows bilateral abnormality in 60 to 70 percent of patients, and the contralateral leg may be asymptomatic.
Why it is missed. Over 50 percent of patients are initially misdiagnosed, frequently as shin splints, CECS or lumbar radiculopathy, and the average delay from symptom onset to diagnosis is 12 to 24 months. A high index of suspicion and simple bedside provocative pulse testing can clinch the diagnosis.
Anatomy and Pathophysiology
The entrapment. The popliteal artery normally passes through the popliteal fossa without any musculotendinous compression. In PAES an anomalous relationship between the artery and gastrocnemius (most commonly the medial head), popliteus or fibrous bands leads to repeated arterial compression during plantarflexion and dorsiflexion. Functional PAES is the exception to the anomaly: a normal but hypertrophied gastrocnemius compresses a normally positioned artery during vigorous exercise.
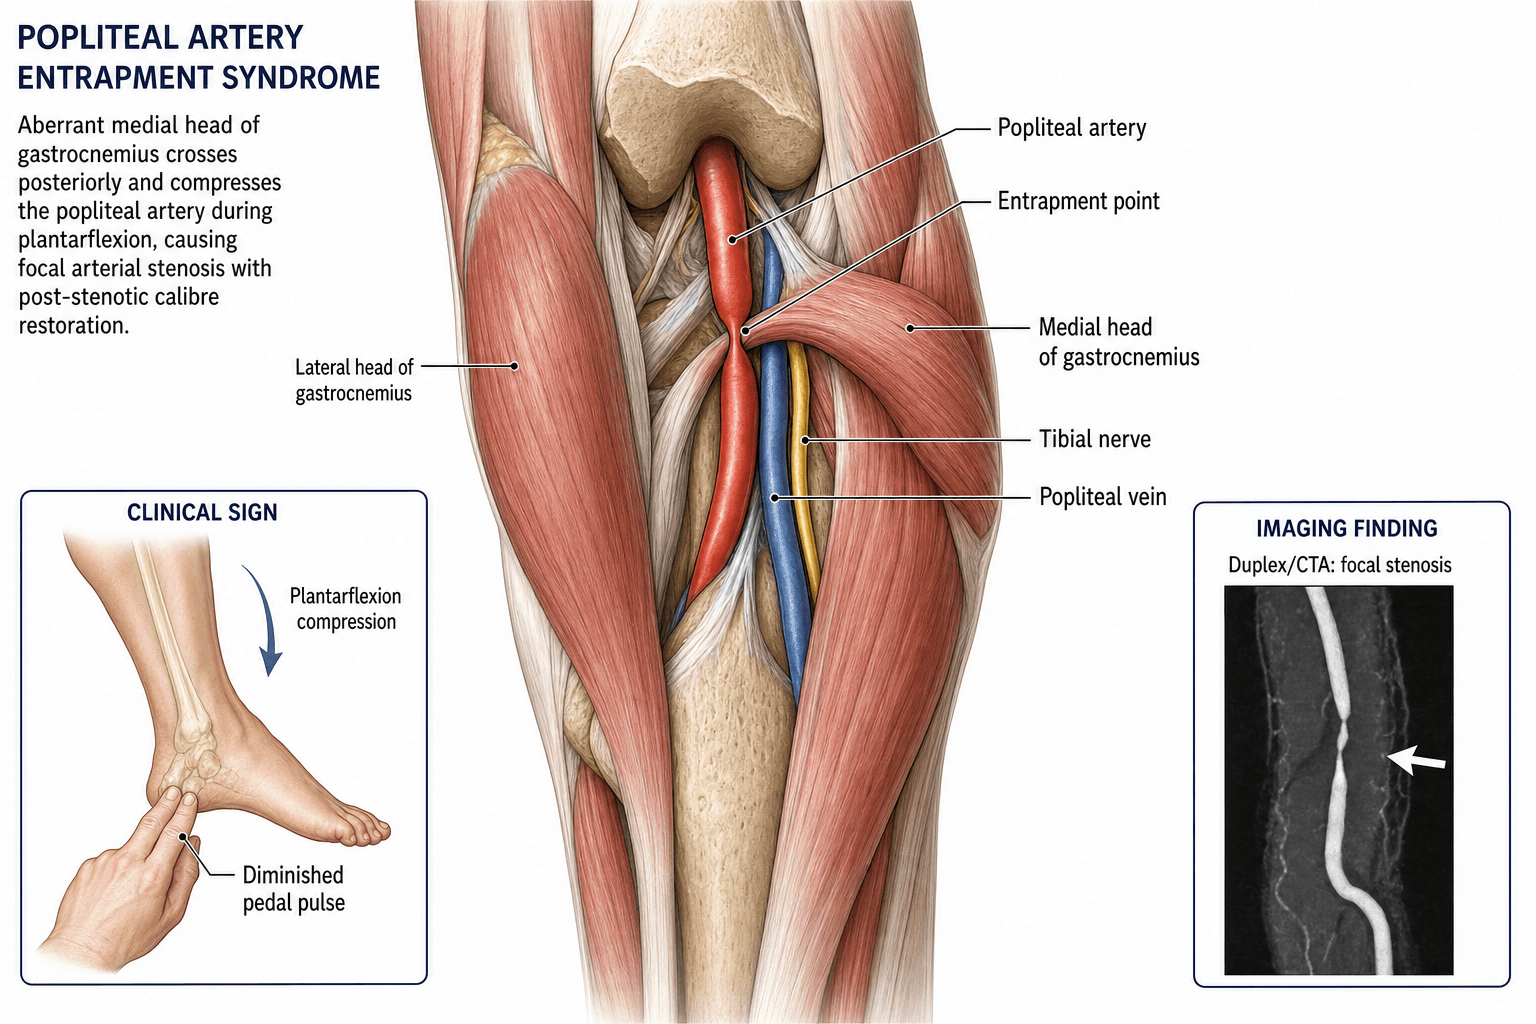
- Normal Position
- Between medial and lateral gastrocnemius heads
- Entrapment Variant
- Medial to medial head or deep to popliteus
- Clinical Consequence
- Compression with ankle movement
- Normal Position
- Originates from medial femoral condyle posteriorly
- Entrapment Variant
- Aberrant origin lateral or deep to artery
- Clinical Consequence
- Direct arterial compression
- Normal Position
- Deep to neurovascular bundle in popliteal fossa
- Entrapment Variant
- Hypertrophied or anomalous fibres crossing artery
- Clinical Consequence
- Type IV entrapment
- Normal Position
- Variable, thin tendon
- Entrapment Variant
- Anomalous slip crossing neurovascular bundle
- Clinical Consequence
- Rare entrapment variant
From compression to occlusion. Repeated compression damages the artery in a predictable sequence, and the end result is acute or chronic limb ischaemia:
- External compression during exercise (functional)
- Intimal irritation and fibrosis from repeated compression
- Fibrous narrowing and post-stenotic dilatation
- Thrombosis, aneurysm or complete occlusion
Why athletes. Progressive gastrocnemius hypertrophy narrows the popliteal space, and running, cycling and rowing put the artery through thousands of compression cycles. Higher training loads correlate with worse compression.
Classification and Types
The Love-Whelan classification guides surgical planning. The anatomical types require resection of the anomalous structure, while functional entrapment responds to myotomy of the medial head of gastrocnemius.
- Anatomical Relationship
- Medial gastrocnemius normal, artery runs medial to it
- Mechanism
- Artery deviates medially around normal muscle course
- Frequency
- Approximately 10 to 15 percent
- Anatomical Relationship
- Aberrant medial gastrocnemius head, artery in normal position
- Mechanism
- Abnormal muscle head crosses and compresses the artery
- Frequency
- Approximately 15 to 20 percent
- Anatomical Relationship
- Anomalous accessory slip of gastrocnemius
- Mechanism
- Muscle slip wraps around artery, compressing it
- Frequency
- Approximately 10 to 15 percent
- Anatomical Relationship
- Popliteus muscle or fibrous band compresses deep artery
- Mechanism
- Artery entrapped deep to popliteus or by congenital fibrous band
- Frequency
- Approximately 5 to 10 percent
- Anatomical Relationship
- Any of Types I-IV with venous entrapment as well
- Mechanism
- Both popliteal artery and vein compressed by anomalous structures
- Frequency
- Approximately 5 percent
- Anatomical Relationship
- Normal anatomy, hypertrophied muscle
- Mechanism
- Muscle hypertrophy compresses artery during exercise only
- Frequency
- Most common form in athletes
Clinical Assessment
History. The complaint is claudication: reproducible pain in the calf or foot on exertion, relieved promptly by rest. The foot may become numb, pale or cold during exercise, and calf pain on running, walking or dorsiflexion limits sport. Up to 30 percent report bilateral symptoms.
Examination at rest. The resting examination is often completely normal, with palpable pedal pulses. After exertion, look for pallor, delayed capillary refill or dependent rubor. Examine both legs even when the symptoms are unilateral, and feel the pulses in both the resting and the provoked positions.
Provocative pulse testing. This is the bedside hallmark. With the patient supine, palpate the dorsalis pedis and posterior tibial pulses before, during and after the manoeuvre: active plantarflexion against resistance, the examiner pushing against the forefoot, or passive dorsiflexion of the ankle to maximum. The test is positive when the pedal pulses diminish or disappear during the manoeuvre and return when the ankle comes back to neutral.
- Technique
- Patient pushes foot down against examiner resistance
- Positive Finding
- Pulse diminution or loss
- Notes
- Most sensitive bedside test
- Technique
- Examiner forces ankle into maximal dorsiflexion
- Positive Finding
- Pulse diminution or loss
- Notes
- Stretches gastrocnemius, compresses artery
- Technique
- Patient actively dorsiflexes against resistance
- Positive Finding
- Less reliable than plantarflexion
- Notes
- May help identify popliteus-related entrapment
Reading the result. A positive provocative test in a young athlete with exertional calf pain is highly suggestive of PAES and mandates imaging. A negative test does not exclude the diagnosis, because sensitivity is imperfect, especially in functional PAES, where compression occurs only at higher forces.
A positive test is not the diagnosis. In Turnipseed's series, stress plethysmography was positive in 18 per cent of asymptomatic operated patients. Functional entrapment is therefore a diagnosis of symptoms plus a positive test plus normal compartment pressures, never of the test alone.
PAES or CECS. PAES is a vascular problem: claudication with pallor, a cold foot and diminished pulses on provocation, and the pain is ischaemic. Chronic exertional compartment syndrome is myofascial: burning, tight, bursting pain with normal pulses, no skin changes and a tense compartment after exertion, the pain coming from raised compartment pressure. Paraesthesiae and foot drop may occur in CECS from nerve compression within the compartment.
The two conditions can coexist and must be investigated independently. Measure compartment pressures and perform dynamic vascular imaging if either diagnosis is suspected.
- Pulses
- Diminish with provocation
- Key Discriminator
- Exertional pallor + pulse loss, no atherosclerosis
- Definitive Test
- Dynamic MR/CT angio with provocative positioning
- Pulses
- Normal
- Key Discriminator
- Burning tight pain, raised compartment pressure post-exertion
- Definitive Test
- Compartment pressure measurement pre/post-exercise
- Pulses
- May be diminished
- Key Discriminator
- Cyst in arterial wall, not muscle entrapment
- Definitive Test
- MRI showing cystic lesion in popliteal artery wall
- Pulses
- Absent or reduced
- Key Discriminator
- Atherosclerotic risk factors present, older patient
- Definitive Test
- CT angio showing atheromatous disease
- Pulses
- Normal
- Key Discriminator
- Radiating pain, neurological signs, back pain
- Definitive Test
- MRI lumbar spine
- Pulses
- Normal
- Key Discriminator
- Diffuse posteromedial tibial tenderness, no vascular symptoms
- Definitive Test
- Clinical diagnosis; bone scan if stress fracture suspected
Investigations
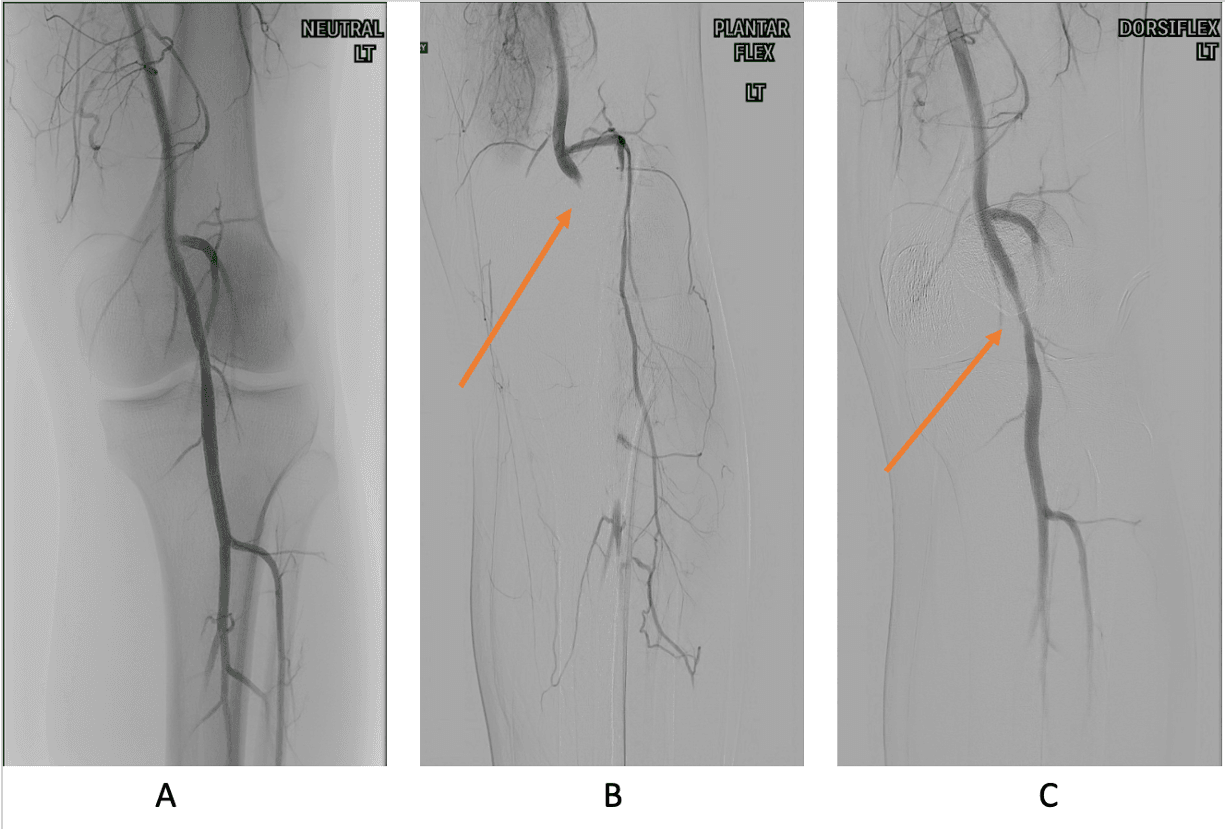
The critical step is dynamic imaging with provocative positioning. A resting MRI or CTA alone may be completely normal in functional PAES, so the artery must be imaged during plantarflexion or dorsiflexion. Always specify this in the imaging request, or the study will be non-diagnostic, and always image both legs.
Duplex ultrasound first. Duplex is non-invasive, dynamic, done at the bedside and free of radiation. The resting scan assesses popliteal artery calibre, flow velocities and any aneurysmal change, and the scan is then repeated with active plantarflexion and passive dorsiflexion. A velocity increase of greater than 50 percent, or complete cessation of flow, with the provocative manoeuvres is the positive finding.
MR angiography is the gold standard. The popliteal fossa is imaged in the neutral position, then with the foot in active plantarflexion or passive dorsiflexion. It shows compression or occlusion of the artery, the anomalous musculotendinous structures and arterial wall changes such as thickening or aneurysm. There is no radiation, the soft-tissue characterisation is excellent, and muscle anatomy and arterial lumen are shown in one study.
CT angiography is the alternative when MRI is contraindicated (pacemaker, claustrophobia) or rapid assessment is needed in an acute presentation. It is performed in neutral and in plantarflexion. It is faster than MRI, gives excellent arterial detail and can assess calcification, at the cost of ionising radiation and less soft-tissue detail.
Conventional angiography is indicated if imaging suggests complete popliteal occlusion, or if endovascular intervention is being considered. It shows segmental occlusion, collateral formation and "spindle-shaped" post-stenotic dilatation, and it has a therapeutic role in catheter-directed thrombolysis for acute thrombosis.
Management Algorithm
The principle. Surgical decompression is definitive for both functional and anatomical PAES. Release the offending structure, and reconstruct the artery only if it is diseased: a diseased segment needs an interposition vein graft or bypass. Plan bilateral surgery if the imaging abnormalities are bilateral.
The aim is to eliminate arterial compression by releasing the medial head of gastrocnemius.
Before surgery. Confirm the compression on bilateral MR angiography with provocative positioning and check the arterial wall. In functional PAES the wall is normal and no graft is needed.
The operation. Explore the popliteal fossa posteriorly through an S-shaped or zig-zag incision and identify the medial head of gastrocnemius, the popliteal artery and vein, and the tibial nerve. Divide the medial head at its musculotendinous junction, ensuring full decompression of the artery through the full range of ankle motion. Verify with intra-operative duplex, or palpable distal pulses, through full ankle range.
For functional PAES, myotomy alone is curative in 85 to 95 percent of cases because the artery itself is normal. Failure to divide the muscle completely is the most common cause of recurrent symptoms.
Turnipseed's counterpoint. In Turnipseed's 43 functional entrapments, MRA/MRI showed normal musculotendinous anatomy with lateral neurovascular compression on plantarflexion. The structure excised was the soleal band rather than the medial gastrocnemius head, and 19 of the 43 also needed compartment releases.
After surgery.
- Weight-bearing as tolerated from post-operative day 1
- Ankle neutral splint for 24 to 48 hours, for wound healing
- Monitor distal pulses, wound healing and calf swelling
- Anticoagulation not routinely required unless arterial repair was performed
- Graduated running programme from 4 weeks; full sport usually cleared at 6 to 8 weeks
- Duplex ultrasound at 6 weeks and 12 months to confirm decompression and arterial patency
Complications
Natural history. Untreated PAES follows the predictable course set out under pathophysiology, from compression to thrombosis or aneurysm. Young patients with anatomical PAES should be offered surgical decompression even if asymptomatic, because the natural history is one of progressive arterial damage. Functional PAES may be observed if symptoms are mild, but surgery is indicated for competitive athletes and for those with documented arterial wall changes.
- Incidence
- 10 to 20 percent of untreated anatomical PAES
- Risk Factors
- Delayed diagnosis, Type I-III entrapment
- Management
- Urgent revascularisation + entrapment release
- Incidence
- 5 to 10 percent of chronic PAES
- Risk Factors
- Long-standing entrapment, post-stenotic dilatation
- Management
- Aneurysm repair + entrapment release
- Incidence
- 5 to 15 percent
- Risk Factors
- Incomplete myotomy, arterial wall damage not addressed
- Management
- Repeat imaging; consider completion myotomy or bypass
- Incidence
- 15 to 30 percent at 5 years (70 to 85 percent patency)
- Risk Factors
- Poor vein quality, technical error, ongoing compression
- Management
- Revision bypass or endovascular salvage
- Incidence
- 5 to 10 percent
- Risk Factors
- Posterior incision, re-operation, obesity
- Management
- Wound care, antibiotics, delayed mobilisation
- Incidence
- Less than 5 percent
- Risk Factors
- Incomplete muscle division, scar tissue
- Management
- Revision surgery with wider decompression
Outcomes and Prognosis
- Treatment
- Myotomy alone
- Expected Outcome
- 85 to 95 percent symptom resolution
- Long-term Function
- Full return to sport at 6 to 8 weeks
- Treatment
- Muscle resection + decompression
- Expected Outcome
- 80 to 90 percent symptom resolution
- Long-term Function
- Full return to sport at 8 to 12 weeks
- Treatment
- Resection + vein bypass graft
- Expected Outcome
- 70 to 85 percent graft patency at 5 years
- Long-term Function
- Return to sport at 3 to 6 months, may have activity limits
- Treatment
- Emergency revascularisation + release
- Expected Outcome
- 60 to 80 percent limb salvage
- Long-term Function
- Variable; depends on ischaemia time and muscle damage
Prognosis. The best prognosis belongs to functional PAES treated by myotomy alone, with a normal artery and a simple decompression. Anatomical PAES diagnosed early, before the arterial wall is damaged, does well; late presentation with thrombosis or aneurysm requiring bypass carries a guarded prognosis.
Warning signs. The poor prognostic indicators are delayed diagnosis over 12 months, acute limb ischaemia at presentation, and popliteal occlusion with poor run-off.
Symptom duration. Delayed diagnosis sits on that list, yet Sinha's systematic review found no relationship between duration of symptoms and the presence of irreversible arterial injury. Symptom duration alone should therefore not decide urgency.
Reconstruction fails often. The same review found a median failure rate of 27.5 per cent for arterial reconstruction, which is the argument for operating before the artery is damaged rather than after.
Guidelines, Registries & Global Practice
- PAES prevalence: Anatomical variants found in approximately 3 to 5 percent of cadaveric specimens globally
- Athlete predominance: Reported worldwide in runners, cyclists, rowers, footballers, and military recruits
- Functional PAES: Most common form in athletes; incidence increasing with recognition and dynamic imaging
- Late presentation: Average diagnostic delay of 12 to 24 months reported across centres in Europe, North America, and Australasia
- High-resource: MR angiography with provocative positioning as first-line dynamic imaging; posterior surgical approach with intra-operative duplex
- Limited-resource: Dynamic duplex ultrasound with provocative manoeuvres is a low-cost, high-yield alternative; open myotomy with clinical verification of decompression
- Universal principle: The diagnosis is clinical (young athlete + provocative pulse loss); imaging confirms and classifies
- Surgery: Posterior popliteal approach is the global standard; arterial reconstruction techniques vary by surgeon training
- Diagnosis Emphasis
- Provocative pulse testing in all young claudicants
- Imaging
- Dynamic duplex first-line; MR/CT angio for surgical planning
- Surgery
- Myotomy for functional; resection + bypass if artery diseased
- Diagnosis Emphasis
- High index of suspicion in athletes; check bilateral pulses
- Imaging
- CTA or MRA with provocative positioning; duplex screening
- Surgery
- Surgical decompression; endovascular has limited role (external compression)
- Diagnosis Emphasis
- Differentiate from CECS with pulse examination
- Imaging
- Bilateral imaging mandatory; dynamic protocol essential
- Surgery
- Early referral to vascular surgery; myotomy curative for functional PAES
There is no dedicated international registry for PAES due to its rarity. The evidence base comprises case series, systematic reviews of pooled series, and expert consensus. ESVS guidelines recommend dynamic imaging and early surgical decompression. The key message for exams: PAES is rare but important as a cause of young-person claudication, and the diagnosis is often delayed. A simple provocative pulse test can be diagnostic.
Record in any young patient with exertional calf pain:
- Provocative pulse testing performed and result (positive or negative)
- Bilateral pulse assessment in resting and provoked positions
- Differential diagnosis considered (PAES, CECS, cystic adventitial disease, radiculopathy)
- Imaging requested with dynamic provocative protocol specified
- If PAES confirmed, bilateral imaging and early vascular surgical referral
Missed PAES leading to popliteal artery thrombosis is a preventable cause of acute limb ischaemia in young patients. Always perform provocative pulse testing in any young person with exertional calf symptoms.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 24-year-old competitive rower presents with a 6-month history of reproducible left calf pain and foot numbness during training. The pain resolves within 2 minutes of rest. He has no medical history and does not smoke. Resting examination reveals normal palpable pedal pulses bilaterally. When you ask him to actively plantarflex against resistance, the left dorsalis pedis pulse disappears. What is your diagnosis, investigation, and management?”
“A 32-year-old military recruit presents to the emergency department with a 4-hour history of sudden onset severe left calf pain, foot pallor, and numbness. He reports a 2-year history of intermittent calf pain during training that was attributed to shin splints. Examination reveals an absent left dorsalis pedis pulse, cold pale foot with reduced sensation, and intact motor function. CT angiography shows a short segment popliteal artery occlusion with an anomalous medial gastrocnemius head compressing the vessel. How would you manage this?”
Key Anatomy
- Popliteal artery passes between medial and lateral gastrocnemius heads through the popliteal fossa
- Anomalous medial gastrocnemius head is the most common compressive structure
- Popliteus muscle and fibrous bands can also entrap (Type IV)
- Bilateral anatomical variants present in 60 to 70 percent of cases on imaging
Diagnosis
- Young athlete (under 40) with calf claudication and no atherosclerotic risk factors
- Provocative pulse testing: active plantarflexion or passive dorsiflexion abolishes pedal pulses
- Dynamic MR or CT angiography with provocative positioning is the gold standard
- Always image both legs and order dynamic (not resting-only) imaging
Classification (Love-Whelan)
- Types I-III: Anatomical variants of gastrocnemius-artery relationship
- Type IV: Popliteus or fibrous band compression
- Type V: Any anatomical type with coexisting venous entrapment
- Type VI (Functional): Normal anatomy, hypertrophied muscle compresses artery on exercise
Treatment Algorithm
- Functional PAES (Type VI): Myotomy of medial gastrocnemius head alone (85 to 95 percent cure)
- Anatomical PAES with normal artery: Resection of anomalous tissue + decompression
- Anatomical PAES with diseased artery: Resection + interposition saphenous vein graft
- Acute thrombosis: Urgent thrombectomy + bypass + entrapment release + consider fasciotomy
PAES vs CECS Differential
- PAES: vascular symptoms (pallor, cold foot, pulse loss) with normal compartment pressures
- CECS: myofascial burning pain with raised compartment pressures and normal pulses
- Both can coexist and must be investigated independently
- Dynamic duplex and compartment pressure studies are complementary investigations
Evidence Base and Key Trials
Popliteal artery entrapment syndrome
- Original description of the anatomical classification of popliteal artery entrapment
- Identified the medial head of gastrocnemius as the primary compressive structure
- Established the concept of anomalous musculo-arterial relationships causing claudication in young patients
- Recommended surgical exploration and division of the anomalous muscle fibres
Functional popliteal artery entrapment syndrome: A poorly understood and often missed diagnosis that is frequently mistreated
- 854 patients operated between 1987 and 2007 for chronic recurrent exertional compartment syndrome (CRECS), functional popliteal artery entrapment (FPAES) or both - the two are routinely confused
- 757 (95 per cent) had raised compartment pressures and underwent fasciectomy for CRECS
- Stress plethysmography was POSITIVE IN 139 PATIENTS (18 PER CENT) WHO WERE ASYMPTOMATIC - a positive provocative test alone does not make the diagnosis
- Only 43 patients had positive stress plethysmography WITH appropriate symptoms AND normal compartment pressures; MRA/MRI in all 43 showed NORMAL musculotendinous anatomy with lateral neurovascular compression on plantarflexion
- All 43 had excision of the SOLEAL BAND under general anaesthesia, with relief of symptoms; 19 of the 43 (44 per cent) also required CRECS releases
Popliteal entrapment syndrome
- PRISMA systematic review of the English-language literature from 1947 to December 2010: 291 articles identified, 44 included, of which 30 studies concerned popliteal artery entrapment specifically
- NO relationship was found between duration of symptoms and the presence of irreversible arterial injury
- Diagnosis used a median of three tests per study (range 1 to 6); arteriography was used in 28 of the 30 studies, with an estimated mean sensitivity of 97 per cent (range 85 to 100)
- Arterial reconstruction was described in 23 studies with a MEDIAN FAILURE RATE OF 27.5 PER CENT (range 0 to 83) - the reconstructions fail often
- The proportion of patients asymptomatic after surgery was reported in only 12 of the 30 studies, median 77 per cent (range 70 to 100)
Long-term outcomes after revascularization for advanced popliteal artery entrapment syndrome with segmental arterial occlusion
- 22 limbs in 18 consecutive patients with ADVANCED PAES and segmental arterial occlusion, treated over 16 years; mean age 31 years and 94 per cent male
- Presentation was claudication in 18 limbs, ischaemic rest pain in three and toe necrosis in one - this is the disease left too long
- Fourteen limbs had musculotendinous section with a popliteo-popliteal interposition graft; the remainder had femoropopliteal or distal bypasses. ALL reconstructions used reversed saphenous vein
- Overall primary graft patency was 80.9 per cent at one year and 74.6 per cent at both three and five years
Popliteal artery entrapment syndrome
- Comprehensive review of PAES classification, diagnostic modalities, and management strategies
- Dynamic duplex ultrasound with provocative manoeuvres is the recommended first-line non-invasive investigation
- Greater than 50 percent velocity increase or complete flow cessation during plantarflexion is diagnostic
- Resting ultrasound alone misses functional PAES; dynamic imaging protocol is essential
- MR or CT angiography with provocative positioning is the gold standard for surgical planning