Chordoma | Chondrosarcoma | Osteosarcoma | Ewing Sarcoma
- Chordoma - most common primary malignant spine tumour, arises from notochord remnants, sacrum 50%, skull base 35%
- Chondrosarcoma - second most common, arises from cartilage, ring-and-arc calcifications on CT
- En bloc resection is goal for chordoma/chondrosarcoma (chemotherapy and radiation resistant)
- Ewing sarcoma - paediatric/young adult, highly chemo/radiosensitive, permeative bone destruction
- Osteosarcoma - rare in spine, requires neoadjuvant chemo, osteoid matrix on imaging
- “Chordoma - T2 hyperintense, physaliferous cells (vacuolated), brachyury positive
- “Chondrosarcoma - ring-and-arc calcifications, arises from posterior elements
- “Marginal excision = 50-70% local recurrence vs 20-30% with wide margins
- “Ewing and osteosarcoma require chemotherapy unlike chordoma/chondrosarcoma
Overview and Epidemiology
Primary malignant bone tumours of the spine are rare, only 5% of all spinal tumours, and they need management quite distinct from that of metastases. The most common are chordoma, chondrosarcoma, osteosarcoma and Ewing sarcoma.
Who gets which. Chordoma and chondrosarcoma are tumours of adulthood, while Ewing sarcoma and osteosarcoma mainly affect children and young adults. Age at presentation helps narrow the differential diagnosis, and so does location.
- Share of primary spine tumours
- 40%
- Typical age
- 40-70 years
- Sex
- M more than F (2:1)
- Characteristic site
- Midline: sacrum, clivus, vertebral body
- Share of primary spine tumours
- 20%
- Typical age
- 30-70 years
- Sex
- M=F
- Characteristic site
- Posterior elements
- Share of primary spine tumours
- 10%
- Typical age
- 10-30 years
- Sex
- M more than F
- Characteristic site
- Vertebral body or posterior elements
- Share of primary spine tumours
- 5%
- Typical age
- 10-25 years
- Sex
- M more than F
- Characteristic site
- Any location
- Share of primary spine tumours
- 25%
- Typical age
- Variable
- Sex
- Variable
- Characteristic site
- -
Where chordoma arises. Chordoma, the most common primary malignant tumour of the spine, arises from notochord remnants along the neuraxis. The figures examiners expect are sacrococcygeal 50%, skull base (clivus) 35%, mobile spine 15%, and within the mobile spine the cervical region is more commonly affected than the thoracic or lumbar. Learn them, but know where they come from.
What the population data show. That split derives from surgical case series, and the population-based data disagree: the SEER analysis of 400 microscopically confirmed chordomas found 29.2% sacral, 32.8% mobile spine and 32% cranial (McMaster, PMID 11227920), roughly equal thirds. The classic ratio over-weights the sacrum because sacral chordomas grow silently until large and are referred to surgical centres, while skull-base disease presents to neurosurgery and small mobile-spine tumours are found incidentally. Quote 50/35/15 in an exam; do not use it to argue a lesion is unlikely to be chordoma because of its level.
Pathophysiology
Notochordal origin. Chordoma arises from remnants of the embryonic notochord, the primordial axial skeleton that guides vertebral development.
Histology. The pathognomonic cell is the physaliferous cell, vacuolated and containing mucin. The tumour has a lobulated architecture with fibrous septae and an abundant myxoid matrix.
Immunohistochemistry. Brachyury is the highly specific diagnostic marker. The tumour is also cytokeratin positive (EMA, CK8/18) and S-100 positive.
Subtypes. Conventional chordoma is the most common and chondroid chordoma has a better prognosis. Dedifferentiated chordoma, with its high-grade sarcomatous component, has the worst.
Classification and Staging
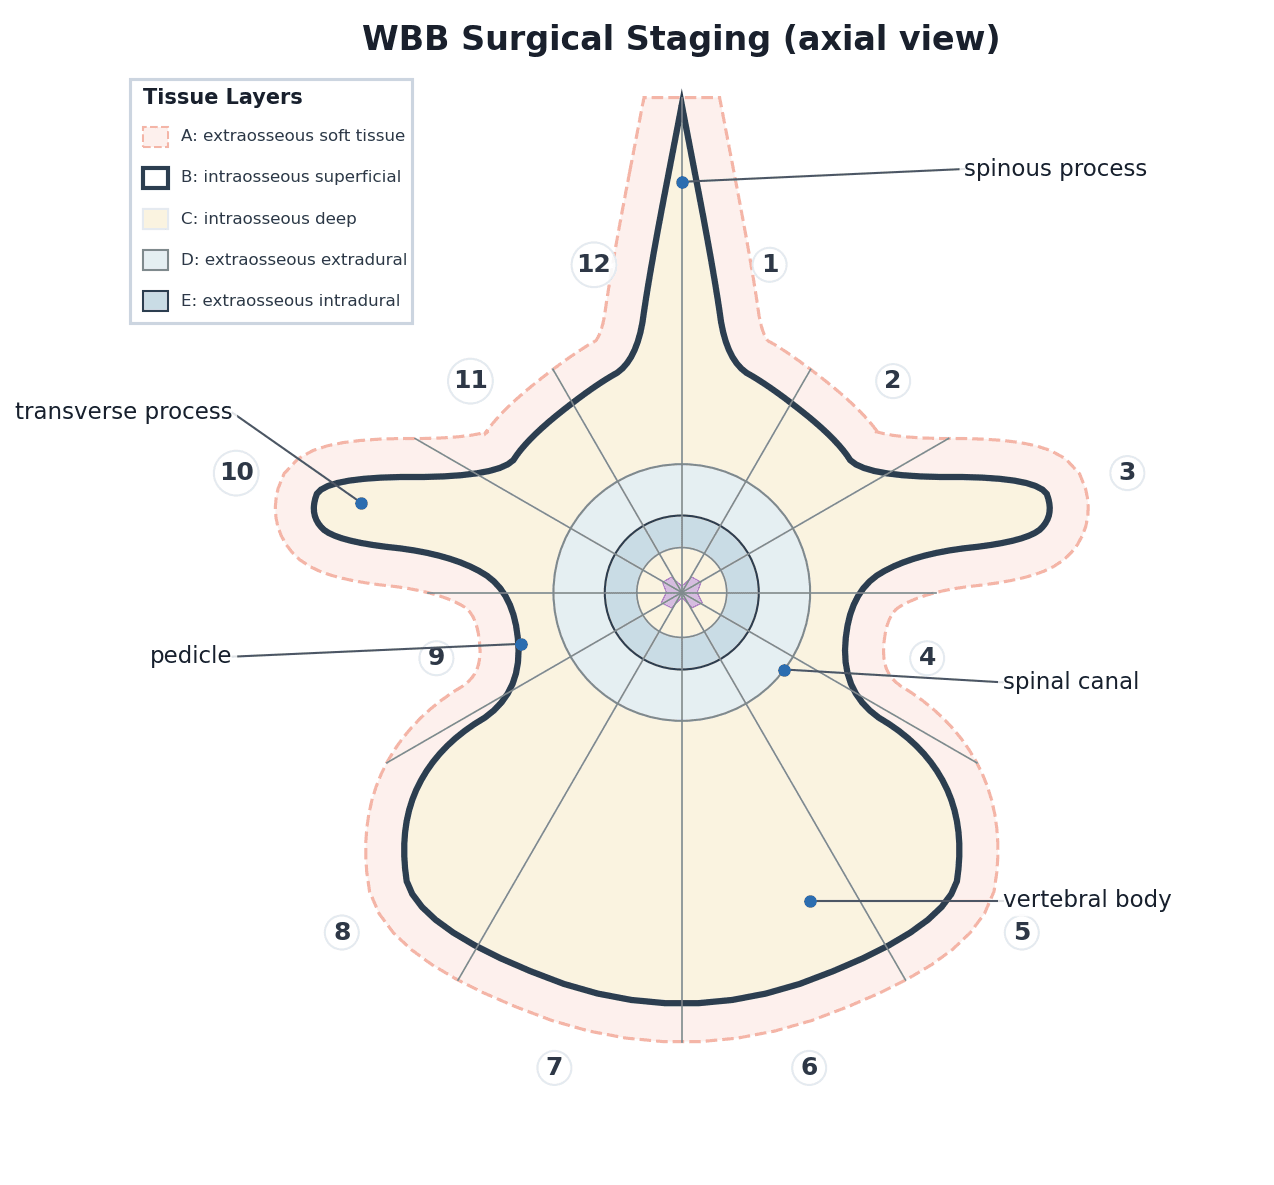
Enneking's system is the standard staging for musculoskeletal tumours. The Weinstein-Boriani-Biagini (WBB) system is an anatomical staging specific to the spine and guides the planning of en bloc resection. No specific staging system exists for chordoma, which is staged with Enneking combined with its anatomical location.
- Grade
- Low (G1)
- Compartment
- Intracompartmental
- Metastases
- M0
- Grade
- Low (G1)
- Compartment
- Extracompartmental
- Metastases
- M0
- Grade
- High (G2)
- Compartment
- Intracompartmental
- Metastases
- M0
- Grade
- High (G2)
- Compartment
- Extracompartmental
- Metastases
- M0
- Grade
- Any
- Compartment
- Any
- Metastases
- M1
Stage III covers any grade with regional or distant metastases. Most spine tumours at presentation are Stage IIB (extracompartmental) because of the anatomical complexity of the spine.
Clinical Presentation
Pain. Pain is the most common presentation: localised back pain, often insidious in onset and typically progressive over months. It may be mechanical or constant, and night pain and rest pain are common.
Neurology. Nerve root compression produces radiculopathy, cord compression produces myelopathy, and sacral tumours can cause cauda equina syndrome. Bowel and bladder dysfunction comes late.
Chordoma. A sacral chordoma gives low back pain, sciatica, constipation and urinary symptoms, and may present as a palpable presacral mass on rectal examination. At the skull base it causes cranial nerve palsies and headache.
Ewing sarcoma. It often presents with systemic symptoms (fever, weight loss, raised inflammatory markers) and may mimic infection.
Osteosarcoma. Pain and swelling, a possible pathological fracture, and a raised alkaline phosphatase.
Red flags.
- Pain worse at night or at rest
- Progressive neurological deficit
- Weight loss, fever
- Palpable mass
- Pathological fracture
Site and age first. This page covers the primary malignant tumours, but the first sieve for any primary spinal bone tumour is where in the vertebra it sits and the patient's age, which also flags the common benign primaries.
- Posterior elements: osteoid osteoma, osteoblastoma, aneurysmal bone cyst, chondrosarcoma
- Vertebral body: haemangioma, giant cell tumour, chordoma, eosinophilic granuloma (Langerhans cell histiocytosis, classically causing vertebra plana in a child), metastasis, myeloma
- Under about 30 and benign-looking: osteoid osteoma, osteoblastoma, ABC or eosinophilic granuloma
- Under about 30 and aggressive: Ewing sarcoma or osteosarcoma
A painful scoliosis with night pain relieved by NSAIDs in a teenager is the classic osteoid osteoma or osteoblastoma story. Place the lesion in this location-plus-age grid before committing to a diagnosis.
The adult over 40. A destructive vertebral lesion in any adult over 40 is statistically far more likely to be a metastasis or myeloma than a primary sarcoma, with chordoma and chondrosarcoma the leading primary malignant possibilities. The management of a primary tumour (en bloc resection, excision of the biopsy tract) is so different that it must be actively excluded before any intervention.
- Typical age
- Bimodal
- Key discriminators
- Midline + T2 bright (chordoma); ring-arc Ca (chondrosarcoma); osteoid/sunburst (osteo); permeative + systemic features (Ewing)
- Why it matters
- Needs planned biopsy and en bloc resection - do not curette
- Typical age
- Over 50
- Key discriminators
- Known primary; multiple levels; pedicle erosion; usually spares disc
- Why it matters
- Most common malignant spine lesion - tissue/staging before assuming primary
- Typical age
- 50-70
- Key discriminators
- Diffuse osteopenia; punched-out lytic lesions; paraprotein on electrophoresis
- Why it matters
- Systemic disease - radiosensitive, rarely needs en bloc
- Typical age
- 20-40
- Key discriminators
- Expansile lytic lesion, often sacrum/vertebral body; locally aggressive, benign
- Why it matters
- Denosumab and curettage/resection - different algorithm
- Typical age
- Under 20
- Key discriminators
- Expansile, fluid-fluid levels on MRI, posterior elements
- Why it matters
- Benign - curettage/embolisation, not en bloc
- Typical age
- Any
- Key discriminators
- Disc + adjacent endplate destruction; fever; raised CRP/ESR; mimics Ewing
- Why it matters
- Antimicrobial therapy, not surgery - culture before treating
Investigations
Radiographs. Often the first imaging, but their sensitivity is limited and they may be normal in early disease, so advanced imaging is always required. Look for a lytic or sclerotic pattern, bone destruction, matrix mineralisation and a soft-tissue mass.
CT. The best study of bone architecture. It characterises the matrix (calcification, osteoid), assesses fracture and is essential for surgical planning and biopsy guidance. CT angiography is useful for vascular mapping before surgery.
MRI. The gold standard, essential for every primary spine tumour. Image the whole spine to assess skip metastases.
- T1: anatomical detail, marrow replacement
- T2/STIR: tumour extent, oedema
- Post-contrast: enhancement pattern, vascularity
- DWI: cellularity
Nuclear medicine. A bone scan has limited sensitivity for primary tumours, and chordoma may be cold, but it is useful for screening for skeletal metastases. PET-CT is increasingly used for staging metastatic disease and assessing treatment response: FDG uptake correlates with grade and SUV with prognosis. Low-grade tumours may be FDG-negative, and post-treatment change confounds interpretation.
Tumour-specific appearances.
- Radiograph
- Midline lytic destruction, soft-tissue mass
- CT
- Midline lytic destruction, soft-tissue mass
- MRI
- Very high T2 signal (mucin), lobulated, enhances
- Radiograph
- Stippled or ring-and-arc calcifications
- CT
- Ring-and-arc calcifications
- MRI
- High T2 signal, ring-and-arc pattern
- Radiograph
- Dense sclerosis, sunburst periosteal reaction
- CT
- Dense osteoid matrix, sunburst pattern
- MRI
- Variable signal, heterogeneous enhancement
- Radiograph
- Permeative or moth-eaten destruction, soft-tissue mass
- CT
- Permeative destruction, cortical breakthrough
- MRI
- T2 hyperintense, permeative, marked enhancement
Reading the calcification. Ring-and-arc calcification is pathognomonic of a chondroid matrix, not of malignancy: enchondroma, osteochondroma and chondroblastoma produce the identical pattern. What makes a lesion chondrosarcoma is the company the matrix keeps, a destructive soft-tissue mass, not the arcs themselves.
Biopsy. CT-guided biopsy is preferred in the spine, through a tract that avoids contaminating multiple compartments.
A poorly planned biopsy can compromise the subsequent en bloc resection. The biopsy tract must be excisable with the definitive surgery, so discuss the approach and coordinate with the surgeon who will perform it BEFORE the biopsy.
Management
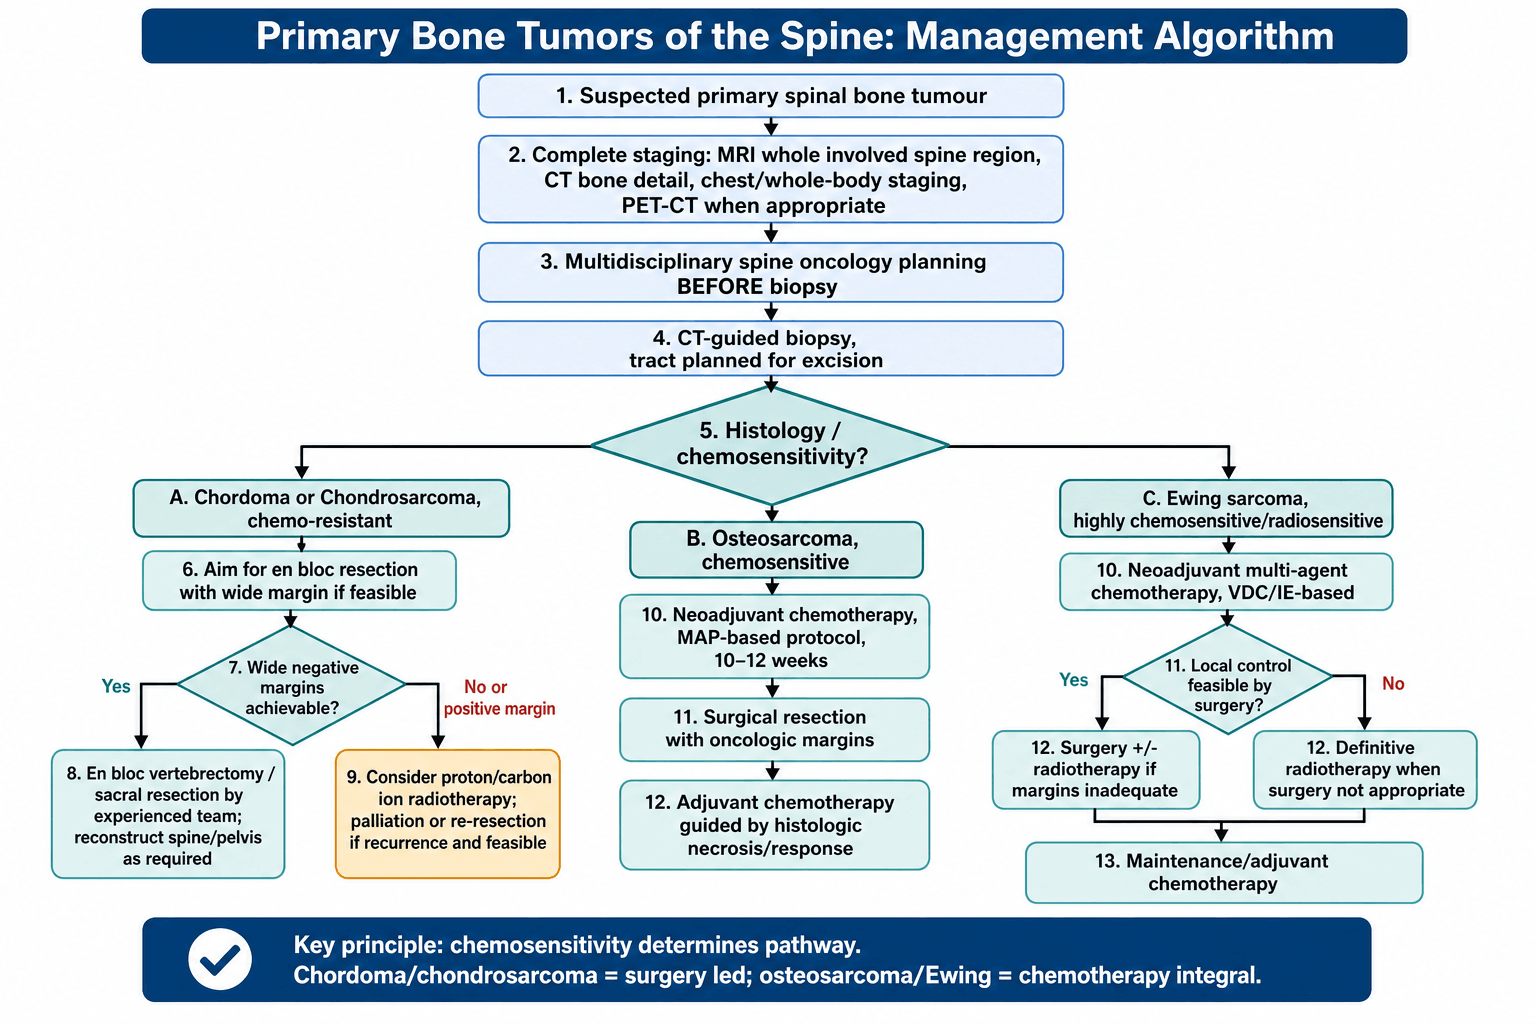
Chemosensitivity decides the pathway. Chordoma and chondrosarcoma are not chemosensitive and are resistant to conventional radiation, so surgery is the primary treatment and wide en bloc resection is the only curative option. Ewing sarcoma and osteosarcoma are chemosensitive, and chemotherapy is integral to their treatment; Ewing sarcoma is highly radiosensitive as well.
Margins. The goal of en bloc resection is a negative margin without violating the tumour capsule. Enneking's margin types carry very different local recurrence rates:
- Intralesional: through the tumour, contaminating the field; recurrence approaching 100%
- Marginal: through the reactive zone; 50-70%
- Wide: through normal tissue, with a cuff around the tumour; 20-30%
- Radical: the entire compartment, rarely achievable in the spine
En bloc vertebrectomy is technically demanding and requires an experienced spine oncology team.
Sacral tumours. Sacral chordoma is resected through a combined anterior-posterior approach, and the level of resection determines function (the roots are set out under Complications). Preoperative embolisation reduces blood loss, rectal involvement may require a colostomy, and the complication rate is high (wound, infection, neurological). Reconstruction uses spinopelvic instrumentation, bone graft or a cage, and a soft-tissue flap for wound coverage.
Mobile spine. En bloc spondylectomy is a total vertebrectomy including the posterior elements, often staged, with circumferential reconstruction. It achieves the best margins but carries the highest morbidity. The WBB zones involved determine the approach, together with whether one or several levels are involved and whether there is epidural (layer D) involvement. The spinal cord cannot be sacrificed, and involvement of an adjacent level increases the difficulty.
Chordoma and chondrosarcoma. Chemotherapy is not effective. Proton or carbon-ion therapy may improve local control, and targeted therapy (imatinib, EGFR inhibitors) is under investigation.
- Staging (MRI, CT, PET)
- Biopsy, coordinated with the surgeon
- En bloc resection with wide margins
- Consider proton therapy if margins are positive
Osteosarcoma. Neoadjuvant chemotherapy is mandatory, on the MAP protocol, and surgery follows it. Histological response predicts prognosis.
- Staging
- Neoadjuvant chemotherapy (10-12 weeks)
- Surgical resection
- Adjuvant chemotherapy based on necrosis
Ewing sarcoma. Chemotherapy is given before and after surgery, VDC/IE is the standard protocol, and radiation is added if margins are inadequate.
- Staging, including whole-body PET
- Neoadjuvant chemotherapy
- Surgery or radiation (or both)
- Maintenance chemotherapy
Complications
Early. Wound complications are the most common, especially after sacral resection. The others are cerebrospinal fluid leak, neurological deficit and massive blood loss, on average 2-5 L for sacral tumours.
Late. Hardware failure, pseudarthrosis, adjacent level disease and chronic pain.
Sacral resection: count the roots preserved. The severity runs from the top down: losing S2 costs more than losing S3, because every root below the cut goes with it. The reference figures are Todd's 53-patient Mayo series (PMID 11953593):
- Normal bowel
- 87%
- Normal bladder
- 89%
- Normal bowel
- 100%
- Normal bladder
- 69%
- Normal bowel
- 67%
- Normal bladder
- 60%
- Normal bowel
- 40%
- Normal bladder
- 25%
- Normal bowel
- 0%
- Normal bladder
- 0%
The rules. Bilateral preservation of S2 and at least one S3 is generally needed to retain useful bladder, bowel and sexual function, and losing both S3 roots (a bilateral cut at or above S3) typically produces neurogenic bladder and bowel and sexual dysfunction. Unilateral sacrifice of even all the sacral roots on one side is usually tolerated with preserved continence, provided the contralateral S2-S4 are intact. Resection below S3 bilaterally usually preserves continence, with some saddle numbness.
Bladder is the weaker organ at every level. Even with both S3 roots preserved only about two-thirds keep normal bladder function, against near-universal bowel continence, so consent for bladder dysfunction must be more pessimistic than for bowel. These are retrospective, single-centre, surgeon-graded outcomes over ten years with no urodynamics: read them as counselling anchors, not guarantees.
Stability is a separate question. S1 sacrifice adds plantarflexion weakness, and bilateral S1 loss also threatens spinopelvic continuity. A cut through or above S1 divides the weight-bearing ala and disrupts the pelvic ring, mandating lumbopelvic (spinopelvic) reconstruction, whereas low sacrectomies below S1 usually do not.
Counsel and plan on two axes: the roots kept (continence) and the level relative to S1 (stability).
Mobile spine. Nerve roots may have to be sacrificed for clear margins, and en bloc techniques carry a risk of spinal cord injury.
Local recurrence. The risk factors are intralesional rather than en bloc surgery, positive surgical margins, tumour grade and dedifferentiated histology. Recurrence is managed by re-resection if feasible, radiation therapy (proton or carbon ion), or palliative care if unresectable.
Postoperative Care
En Bloc Spine Tumour Resection Protocol
Postoperative Rehabilitation Timeline
- Intensive care monitoring for first 24-72 hours
- Haemodynamic monitoring
- Drain management and output monitoring
- Pain management (multimodal, patient-controlled analgesia)
- DVT prophylaxis (mechanical initially, chemical once haemostasis assured)
- Wound assessment for flap viability if soft tissue reconstruction
- Mobilisation with physiotherapy (weight-bearing status per surgeon)
- Wound care and drain removal when output minimal
- Bladder/bowel function monitoring (especially sacral resections)
- Nutritional support for wound healing
- Begin rehabilitation for neurological deficits
- Outpatient wound checks every 1-2 weeks
- Progressive mobilisation and physiotherapy
- Brace if spinal instability concern
- Imaging at 6 weeks to assess instrumentation
- Referral for radiation oncology if margins positive (proton therapy)
- Surveillance imaging every 3-6 months (MRI for local, CT chest for metastases)
- Functional rehabilitation for neurological deficits
- Oncology follow-up for adjuvant therapy if indicated
- Psychological support for adaptation to functional deficits
Outcomes
- 5-Year Survival (Wide Excision)
- 65-70%
- 5-Year Survival (Marginal/Intralesional)
- 35-40%
- Key Prognostic Factor
- Surgical margin status
- 5-Year Survival (Wide Excision)
- 90%
- 5-Year Survival (Marginal/Intralesional)
- 70%
- Key Prognostic Factor
- Tumour grade
- 5-Year Survival (Wide Excision)
- 30%
- 5-Year Survival (Marginal/Intralesional)
- 10-15%
- Key Prognostic Factor
- Tumour grade
- 5-Year Survival (Wide Excision)
- 60-70%
- 5-Year Survival (Marginal/Intralesional)
- Similar (chemo-dependent)
- Key Prognostic Factor
- Response to chemotherapy
- 5-Year Survival (Wide Excision)
- 40-50%
- 5-Year Survival (Marginal/Intralesional)
- 20-30%
- Key Prognostic Factor
- Necrosis rate post-chemo
Margin status comes first. For chordoma and chondrosarcoma, surgical margin status is the most important prognostic factor, and proton beam therapy can help salvage a positive margin. The other prognostic factors in chordoma are histological subtype, tumour size and location, the skull base having the worst access.
Guidelines, Registries & Global Practice
Global epidemiology
Primary malignant bone tumours of the spine are rare, accounting for only a small fraction of spinal tumours; the spine is far more commonly affected by metastatic disease. Chordoma is the most frequent primary malignant tumour of the mobile spine and is itself uncommon. The age distribution is bimodal across the group: chordoma and chondrosarcoma predominate in adults (typically 40-70 and 30-70 years respectively), whereas Ewing sarcoma and osteosarcoma cluster in children and young adults. Across reported series there is a modest male predominance for chordoma. The largest contemporary outcome data come from multicentre registries rather than single-country health systems.
Major guidelines, side by side
- Core recommendation for primary malignant spine tumour
- Enneking-appropriate en bloc resection with wide/marginal margins for chordoma, chondrosarcoma, osteosarcoma and (where feasible) Ewing sarcoma; refer to a tumour-board centre before biopsy
- Strength / level
- Multicentre cohort evidence (Level III)
- Core recommendation for primary malignant spine tumour
- Centralise chordoma care; en bloc resection as first-line; high-dose particle (proton/carbon-ion) radiotherapy for residual, recurrent or unresectable disease; systemic options limited
- Strength / level
- Expert consensus position paper
- Core recommendation for primary malignant spine tumour
- All suspected bone sarcomas referred to a specialist sarcoma multidisciplinary team; diagnostic biopsy performed at (or directed by) the treating centre
- Strength / level
- Service-standard guidance
- Core recommendation for primary malignant spine tumour
- Histology-specific algorithms: wide excision for chordoma/chondrosarcoma; neoadjuvant chemotherapy + surgery for osteosarcoma; multiagent chemotherapy ± local therapy for Ewing sarcoma
- Strength / level
- Category 2A consensus
- Core recommendation for primary malignant spine tumour
- Defines diagnostic entities and grading (e.g. brachyury-defined chordoma, fusion-defined Ewing sarcoma, chondrosarcoma grade) that drive treatment
- Strength / level
- Reference standard
A consistent thread across all bodies is that biopsy must be planned by the treating sarcoma team, because a poorly placed tract can render a curative en bloc resection impossible.
Registry and multicentre evidence
Because each centre sees few cases, the strongest evidence is pooled. The AOSpine Knowledge Forum Tumour databases have quantified that Enneking-appropriate en bloc surgery improves survival and local control in spinal Ewing sarcoma and osteosarcoma. For radiotherapy, the Proton Collaborative Group prospective registry and large single-institution proton cohorts demonstrate high local control with low high-grade toxicity. These collaborations function as the de-facto registries for these rare tumours.
Global practice variation
The principal variation worldwide is access to particle therapy. Proton and carbon-ion facilities are concentrated in a limited number of centres in North America, Europe and Asia; carbon-ion therapy in particular is largely confined to dedicated centres (notably in Japan and Europe). In settings without particle therapy, management relies more heavily on achieving a wide en bloc margin and on high-dose photon techniques. Centralisation of these rare tumours to high-volume sarcoma units is recommended in every health system, as surgeon and centre experience correlate with margin achievement and outcome.
Given the rarity and complexity of these tumours, referral to a specialist sarcoma service is strongly recommended for all patients with a suspected primary malignant spine tumour before any biopsy is performed.
MCQ Practice Points
Q: What is the most common primary malignant bone tumor of the spine? A: Chordoma. It arises from notochordal remnants and occurs predominantly in the sacrum (50%), skull base (35%), and mobile spine (15%). It is a slow-growing, locally aggressive tumor with high recurrence rates.
Q: What histological finding is pathognomonic for chordoma? A: Physaliphorous cells (bubbly vacuolated cells) arranged in lobules within a myxoid matrix. These cells are positive for brachyury immunostaining, which is the most specific marker for chordoma.
Q: What is the Enneking staging system for spinal tumors and how does it guide surgery? A: The WBB (Weinstein-Boriani-Biagini) system adapted for spine divides the vertebra into 12 sectors and 5 layers (A-E). It determines surgical margin possibilities - wide excision (en bloc) is possible when tumor is contained within sectors/layers that can be resected together.
Q: What radiation modality is preferred for chordoma and chondrosarcoma of the spine? A: Proton beam therapy or carbon ion therapy. These tumors are relatively radioresistant to conventional photon therapy but respond to particle therapy which delivers higher doses with sharp dose fall-off protecting the spinal cord.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 55-year-old man presents with 12 months of progressive low back and buttock pain. MRI shows a large destructive sacral mass that is very bright on T2-weighted imaging. The mass extends presacrally.”
“A 45-year-old woman presents with thoracic back pain. CT shows a mass arising from the posterior elements of T7 with characteristic ring-and-arc calcifications. There is extension into the spinal canal.”
“A 14-year-old boy presents with 6 weeks of back pain, fever, and weight loss. MRI shows a destructive lumbar vertebral body lesion with large paraspinal soft tissue mass. WCC and ESR are elevated.”
“A 60-year-old man who had sacral chordoma resection 3 years ago presents with increasing sacral pain. MRI shows a 4cm presacral mass consistent with local recurrence. There is no distant disease on PET-CT.”
Tumor Types
- Chordoma: Notochord origin, sacrum 50%, T2 bright, brachyury+
- Chondrosarcoma: Cartilage origin, posterior elements, ring-arc calcifications
- Osteosarcoma: Bone-forming, osteoid matrix, sunburst pattern
- Ewing: Neural crest, pediatric, t(11;22), permeative lytic
Treatment Differences
- Chordoma/Chondrosarcoma: En bloc resection (chemo/RT resistant)
- Osteosarcoma: Neoadjuvant chemo + surgery + adjuvant chemo
- Ewing: Chemo + surgery or radiation + chemo
- Margin status is critical for chordoma/chondrosarcoma
Enneking Staging
- Stage I: Low grade (G1), A=intra, B=extra compartmental
- Stage II: High grade (G2), A=intra, B=extra compartmental
- Stage III: Any grade with metastases
- Most spine tumors present as Stage IIB
Surgical Margins
- Intralesional: Through tumor = approaching 100% recurrence
- Marginal: Through reactive zone = 50-70% recurrence
- Wide: Cuff of normal tissue = 20-30% recurrence
- Radical: Entire compartment (rarely achievable in spine)
Sacral Chordoma
- Combined anterior-posterior approach
- Level of resection determines function
- Above S2-S3: Bladder/bowel dysfunction
- Preoperative embolization essential
- Proton therapy if margins positive
Exam Pearls
- Ring-arc calcification = chondrosarcoma
- T2 hyperintense sacral mass = chordoma until proven otherwise
- Pediatric + systemic symptoms + spine mass = Ewing
- Biopsy tract must be excisable - coordinate with surgeon
Evidence Base
Chordoma of the Mobile Spine: Margin-Free En Bloc Resection
- Consecutive series of 52 chordomas of the mobile spine over 50 years
- Intralesional extracapsular excision plus radiotherapy: recurrence in 12 of 16 (mean 30 months)
- En bloc resection: 12 of 18 continuously disease-free at mean 8 years follow-up
- All recurrences after en bloc occurred where margins were contaminated or the tumour had been previously treated
Operative Management of Sacral Chordoma: Margin Predicts Survival
- 52 sacrococcygeal chordomas treated surgically (Mayo Clinic, 1980-2001)
- Overall local recurrence 44%; recurrence-free survival 59% at 5 years and 46% at 10 years
- Overall survival 74%, 52% and 47% at 5, 10 and 15 years
- A wide margin was the single most important predictor of survival - all wide-margin patients survived (p = 0.0001); a combined anteroposterior approach made a wide margin more likely (81% of wide-margin cases)
Ewing Sarcoma of the Mobile Spine
- 13 patients with non-metastatic mobile-spine Ewing sarcoma treated with multiagent chemotherapy plus radiotherapy for local control
- Disease-free survival 49% at 5 years and 36% at 10 years; local recurrence in 3 (23%)
- Pain control improved in 92% and motor function maintained or improved in most
- Post-laminectomy progressive kyphosis in 4 of 10 (40%), underscoring the need for reconstruction
WBB Surgical Staging of Primary Spine Tumours
- Defining paper introducing the Weinstein-Boriani-Biagini (WBB) surgical staging system
- Vertebra divided into 12 radiating zones (clock-face) and 5 tissue layers (A-E)
- Applies Enneking oncological principles to the unique anatomy of the spine
- Standardises terminology for tumour extent and surgical margins to enable planning and comparison across centres
AOSpine: En Bloc Resection in Spinal Ewing Sarcoma
- Multicentre AOSpine Knowledge Forum Tumour series of 58 surgically treated primary spinal Ewing sarcomas
- Enneking-appropriate (en bloc, wide/marginal) surgery was associated with significantly better survival (p = 0.034)
- Neoadjuvant plus postoperative chemotherapy significantly improved survival (p = 0.008)
- Intralesional margins and previous spine tumour surgery were associated with increased local recurrence
AOSpine: Prognostic Factors in Primary Spinal Osteosarcoma
- Multicentre AOSpine ambispective series of 58 primary spinal osteosarcomas (1987-2012)
- Enneking-appropriate (en bloc) resection gave longer median survival than Enneking-inappropriate surgery (6.8 vs 3.7 years, p = 0.048)
- Enneking-inappropriate surgery carried a significantly higher local recurrence rate (p = 0.001)
- 30% suffered local recurrence and 59% of those died; most patients die despite aggressive surgery
Adjuvant High-Dose Proton-Based Radiotherapy for Spinal Chordoma
- 76 primary spinal/sacral chordomas with en bloc resection and minimum 5-year follow-up (median 9.3 years)
- Completing the goal 70 Gy proton-based dose (C70) gave better 5-year overall survival than incomplete dosing (82% vs 63%, p = .001)
- 5-year local-recurrence-free interval was higher with complete dosing (93% vs 78%, p = .017)
- Local control rates fall with longer follow-up, so mid-term figures may overstate durability
Proton Therapy for Chordoma: Multicentre Prospective Registry
- 100 chordoma patients on the Proton Collaborative Group prospective registry (61% skull base, 23% spine, 16% sacrum)
- 85% had surgical resection; median proton dose 74 Gy (RBE)
- 2-/3-year local control 97%/94%, overall survival 89%/83%
- Very low high-grade toxicity - no grade 4 acute and no grade 3 or higher late toxicity; CNS necrosis under 1%
References
- Boriani S, Bandiera S, Biagini R, et al. Chordoma of the mobile spine: fifty years of experience. Spine (Phila Pa 1976). 2006;31(4):493-503. PMID: 16481964.
- Fuchs B, Dickey ID, Yaszemski MJ, et al. Operative management of sacral chordoma. J Bone Joint Surg Am. 2005;87(10):2211-6. PMID: 16203885.
- Boriani S, Weinstein JN, Biagini R. Primary bone tumors of the spine. Terminology and surgical staging. Spine (Phila Pa 1976). 1997;22(9):1036-44. PMID: 9152458.
- Marco RA, Gentry JB, Rhines LD, et al. Ewing's sarcoma of the mobile spine. Spine (Phila Pa 1976). 2005;30(7):769-73. PMID: 15803079.
- Stacchiotti S, Sommer J; Chordoma Global Consensus Group. Building a global consensus approach to chordoma: a position paper from the medical and patient community. Lancet Oncol. 2015;16(2):e71-83. PMID: 25638683.
- Charest-Morin R, Dirks MS, Patel S, et al. Ewing sarcoma of the spine: prognostic variables for survival and local control in surgically treated patients. Spine (Phila Pa 1976). 2018;43(9):622-629. PMID: 28837533.
- Dekutoski MB, Clarke MJ, Rose P, et al. Osteosarcoma of the spine: prognostic variables for local recurrence and overall survival, a multicenter ambispective study. J Neurosurg Spine. 2016;25(1):59-68. PMID: 26943248.
- Tobert DG, Kelly SP, Xiong GX, et al. The impact of radiotherapy on survival after surgical resection of chordoma with minimum five-year follow-up. Spine J. 2023;23(1):34-41. PMID: 35470086.
- Chhabra AM, Rice SR, Holtzman A, et al. Clinical outcomes and toxicities of 100 patients treated with proton therapy for chordoma on the proton collaborative group prospective registry. Radiother Oncol. 2023;183:109551. PMID: 36813169.
- Beddok A, Saint-Martin C, Mammar H, et al. High-dose proton therapy and tomotherapy for the treatment of sacral chordoma: a retrospective monocentric study. Acta Oncol. 2021;60(2):245-251. PMID: 33095672.