Motion-Preserving Wrist Salvage | Capitate Into Lunate Fossa | SLAC/SNAC Wrist | Kienbock Disease | Dorsal Approach | PIN Neurectomy
- PRC is a motion-preserving salvage procedure for scapholunate advanced collapse (SLAC) and scaphoid nonunion advanced collapse (SNAC) wrist, and for Kienbock disease - it is NOT a primary arthroplasty
- The critical prerequisite is intact articular cartilage on both the capitate head and the lunate fossa of the radius - if either surface is degenerate, PRC will fail and four-corner fusion or total wrist fusion should be performed instead
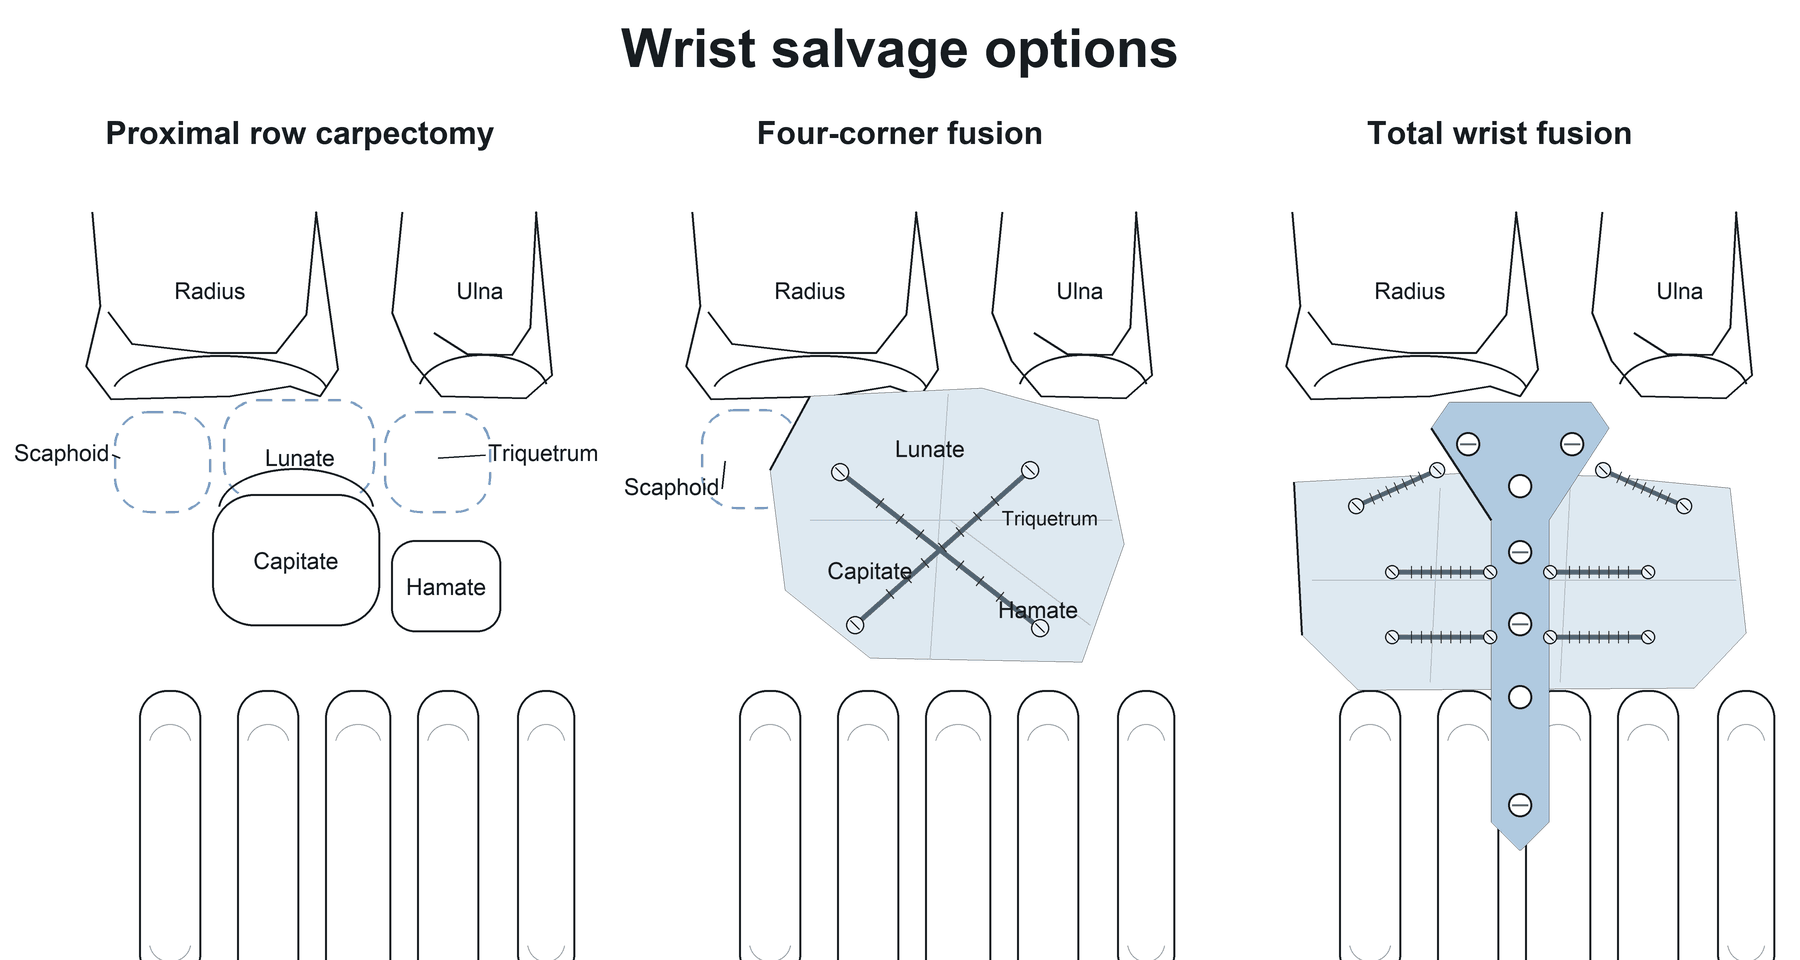
- PRC removes the scaphoid, lunate, and triquetrum and allows the capitate to migrate proximally and seat into the lunate fossa, creating a new simplified radiocarpal articulation
- Post-operative wrist flexion-extension arc is approximately 60-65% of the contralateral side, and grip strength is approximately 50-60% - patients must understand these expectations pre-operatively
- Dorsal approach with posterior interosseous nerve (PIN) neurectomy is the standard technique; PIN neurectomy provides partial denervation of the wrist joint and augments pain relief
- “Always begin a viva answer by confirming the lunate fossa and capitate head cartilage are intact - if not, PRC is contraindicated
- “SLAC wrist pattern: arthritis begins at the radioscaphoid joint and progresses to the capitolunate joint, but the radiolunate joint is preserved until late - this is why PRC works
- “SNAC wrist: arthritis pattern is similar but the scaphoid nonunion site determines the distribution; the proximal pole fragment articulates with the radius
- “The key advantage of PRC over four-corner fusion is simplicity: no hardware, no nonunion risk, shorter immobilisation, and faster rehabilitation
Proximal Row Carpectomy
Overview and Indications
The proximal row carpectomy (PRC) excises the scaphoid, lunate and triquetrum and lets the capitate migrate proximally to articulate directly with the lunate fossa of the radius. First described by Stamm in 1946, it has become a well-established treatment for selected patients with SLAC and SNAC wrist arthritis and with Kienbock disease.
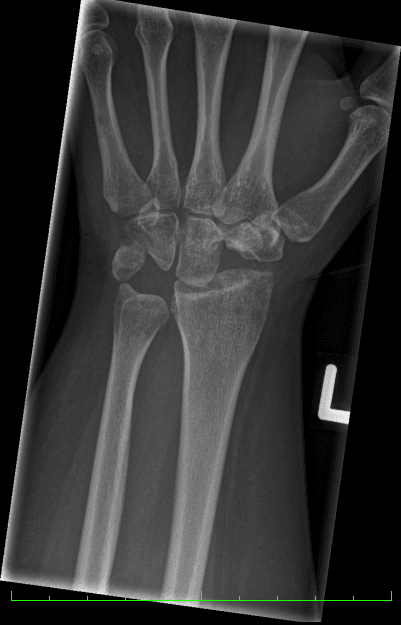
The principle. Removing the arthritic proximal row leaves a simplified radiocarpal joint, capitate head in lunate fossa, which relieves pain while keeping a functional arc of flexion and extension.
Indications. Each assumes an intact lunate fossa and capitate head.
- SLAC wrist (Watson and Ballet classification), stages I and II
- SNAC wrist, analogous stages
- Kienbock disease, Lichtman stage IIIA or early IIIB
- Chronic carpal instability with secondary arthritis limited to the radioscaphoid and midcarpal joints
- Failed prior procedures, such as radial shortening or capitate-shortening osteotomy for Kienbock disease
Relative indications.
- Elderly or low-demand patients who prioritise pain relief over maximum grip strength, in whom PRC is simpler than four-corner fusion
- Manual labourers who understand the functional trade-offs
- Patients who cannot comply with the prolonged immobilisation that four-corner fusion requires
Contraindications. Examiners test your ability to exclude the unsuitable patient.
- Capitate head cartilage degeneration
- Lunate fossa arthritis (radiolunate involvement)
- Inflammatory arthritis (rheumatoid, psoriatic)
- SLAC/SNAC stage IV (pancarpal)
- Active wrist infection
- Severe osteoporosis, which gives poor bone quality for the new articulation
- Pre-operative flexion-extension arc less than 30 degrees, which indicates severe capsular contracture that will not improve with PRC
PRC fails when the capitate head cartilage or the lunate fossa of the radius is damaged. Once the capitate head has degenerated, as in SLAC/SNAC stage III (capitolunate arthritis with capitate head degeneration), or in stage IV (pancarpal arthritis), PRC is contraindicated. Examiners want to see you inspect both articular surfaces intra-operatively before excising the proximal row. If either surface is worn, convert to four-corner fusion or total wrist fusion.
PRCPatient Selection for PRC - SLIC It Right
Hook:SLIC the wrist correctly - if the lunate fossa or capitate head is degenerate, PRC will fail
Choosing between the three salvages. Four-corner fusion excises the scaphoid and fuses the lunate, triquetrum, capitate and hamate, so the native radiolunate articulation is preserved and grip strength is better; a degenerate capitate head is irrelevant because the midcarpal joint is fused. PRC's advantage is simplicity: no hardware, no nonunion risk, shorter immobilisation and faster rehabilitation. Total wrist fusion is the salvage when both radiocarpal and midcarpal joints are destroyed or a motion-preserving operation has failed, trading all wrist motion for reliable pain relief.
- Best option
- Proximal row carpectomy (PRC)
- Reasoning
- Simpler surgery, no hardware, retains functional wrist motion, faster recovery; contraindicated if capitate head or lunate fossa cartilage is damaged
- Best option
- Four-corner fusion (4CF) with scaphoidectomy
- Reasoning
- Preserves the radiolunate articulation; capitate degeneration is irrelevant because midcarpal joint is fused; better grip strength than PRC
- Best option
- Total wrist fusion (TWF)
- Reasoning
- Reliable pain relief; sacrifices all wrist motion; best salvage option when both radiocarpal and midcarpal joints are destroyed
- Best option
- Proximal row carpectomy (PRC)
- Reasoning
- Removes the fragmented lunate and creates a stable articulation between capitate and lunate fossa; effective in stages where lunate is beyond salvage
What to promise. Counsel for a flexion-extension arc of approximately 60-65% and grip strength of approximately 50-60% of the contralateral side; the patient must understand both before surgery.
Relevant Anatomy and Biomechanical Principles
The proximal row. The scaphoid, lunate and triquetrum form an intercalated segment between the radius and ulna and the distal carpal row. Removing it converts a complex two-row system into a simplified hinge and fundamentally alters wrist kinematics.
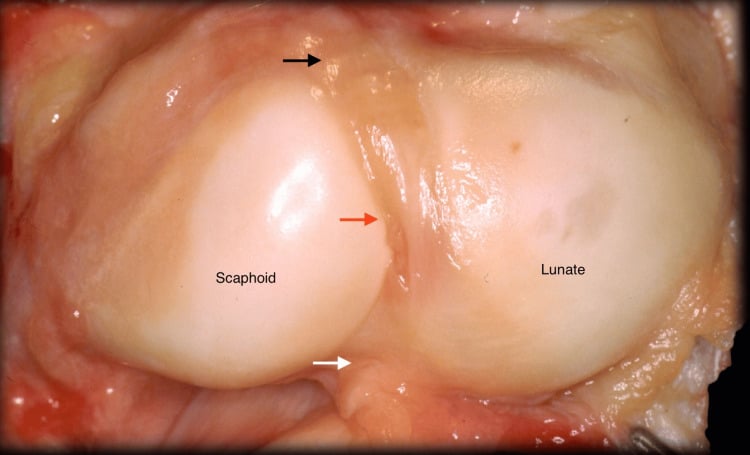
The new bearing surfaces. The lunate fossa is the concave articular surface of the distal radius that normally carries the lunate. The capitate head is the convex proximal surface of the capitate, normally articulating with the scaphoid and lunate at the midcarpal joint. Its radius of curvature is slightly smaller than the fossa's, so after PRC the contact area is reduced and contact pressures are higher than in the native joint; this size mismatch is the theoretical basis for the long-term concern about degeneration at the new articulation.
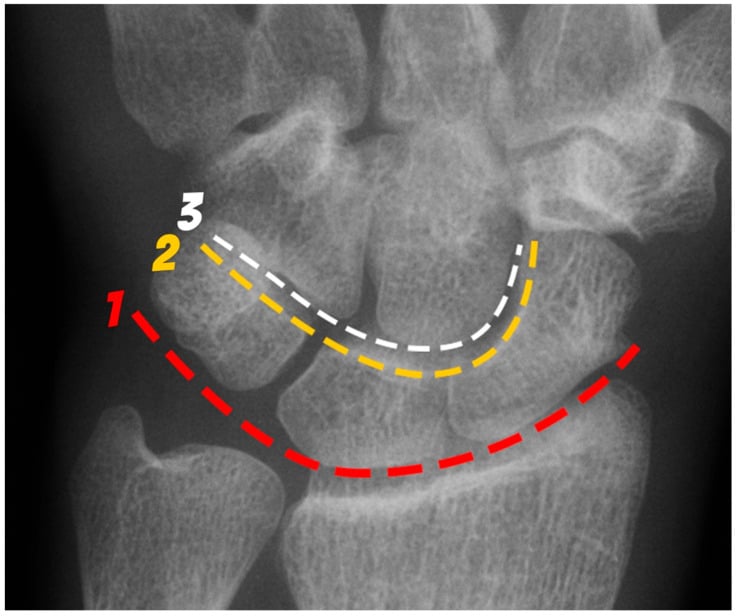
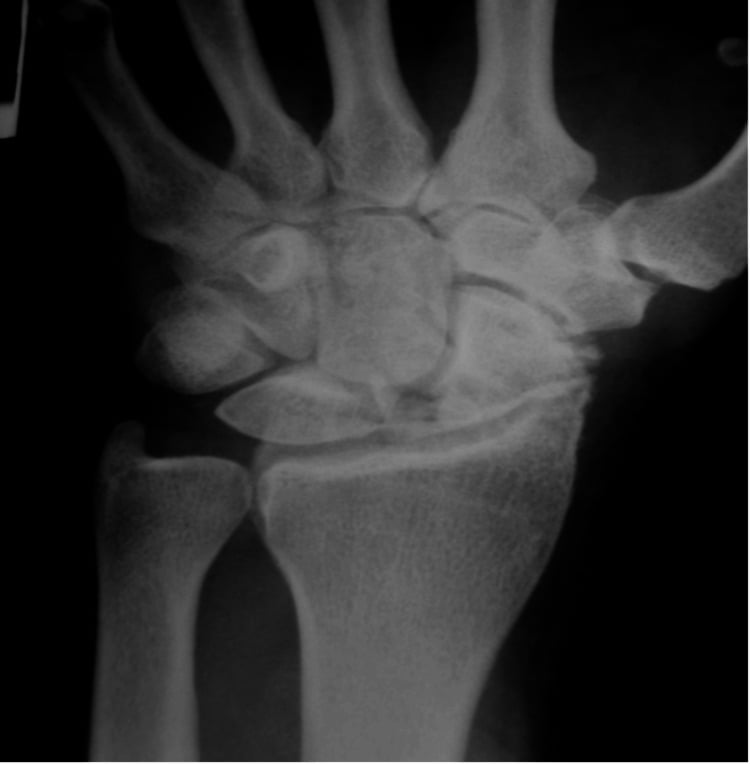
SLAC wrist. Watson and Ballet described the sequence. Disruption of the scapholunate ligament lets the scaphoid flex (rotatory subluxation) and the lunate extend (dorsal intercalated segment instability, DISI). The flexed scaphoid concentrates load on the radioscaphoid joint, which wears first, while the extended, dorsally rotated lunate unloads the radiolunate joint and its cartilage is preserved until late. That preserved lunate fossa is why PRC works.
SNAC wrist. The initiating event is a scaphoid nonunion rather than a ligament rupture. The distal pole stays connected to the distal row and keeps some motion; the proximal pole may behave like a free fragment. Arthritis develops at the radioscaphoid joint and at the fracture site, and the radiolunate joint is again preserved until late.
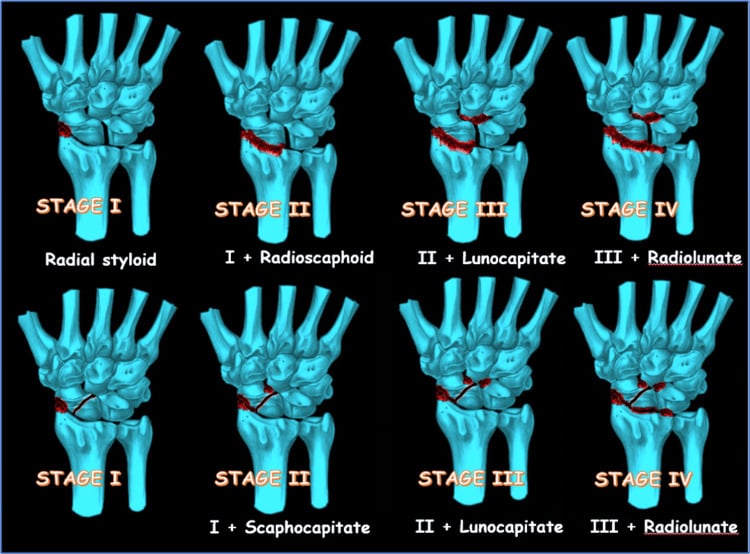
The stages. SLAC and SNAC have their own sequences but share the feature that matters: the radiolunate joint is spared until late, at stage IV. PRC therefore remains viable through the earlier stages provided the capitate head is also intact, and the stage II pattern is the key PRC window.
- SLAC
- Radial styloid
- SNAC
- Distal scaphoid fragment and radial styloid (styloid-scaphoid)
- SLAC
- + Radioscaphoid
- SNAC
- + Scaphocapitate
- SLAC
- + Capitolunate, with capitate head degeneration
- SNAC
- + Capitolunate (periscaphoid/midcarpal)
- SLAC
- Pancarpal, including radiolunate
- SNAC
- Pancarpal, including radiolunate
In SLAC stage II the scaphocapitate joint may also be involved, but the capitate head must be intact for PRC.
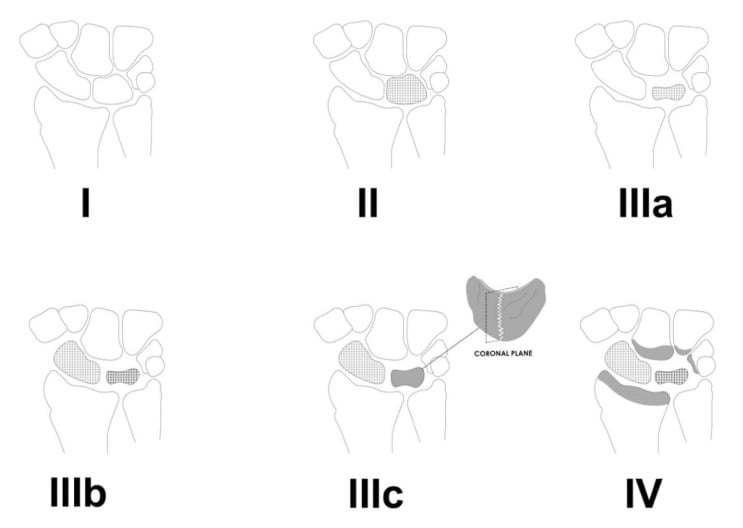
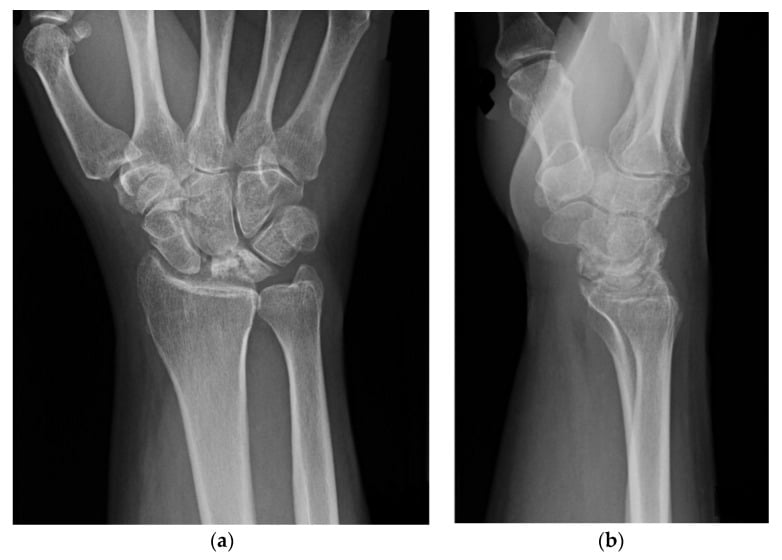
Kienbock disease. In Lichtman stage IIIA (lunate collapse without fixed scaphoid rotation) and early IIIB (lunate collapse with fixed scaphoid rotation) the lunate is fragmented and avascular beyond salvage. PRC removes it and creates a stable capitate-lunate fossa articulation, provided both surfaces are intact. It is an alternative to radial shortening osteotomy (for stage II-IIIA with ulnar-neutral or ulnar-positive variance) or lunate replacement or revascularisation procedures.
Internervous Plane and Surgical Interval
No internervous plane. The extensor tendons are all innervated by the posterior interosseous nerve (PIN), so there is no true internervous plane at the wrist. The dorsal approach, standard for PRC, is developed through the third extensor compartment (EPL), between EDC and EPL, or between EDC and ECRB, the interval most commonly used.
The layers. A radial-based or ulnar-based retinacular flap is raised to expose the extensor tendons and the dorsal wrist capsule. The capsule is opened longitudinally or in an H shape for wide exposure of the carpus, and its flaps are preserved for repair.
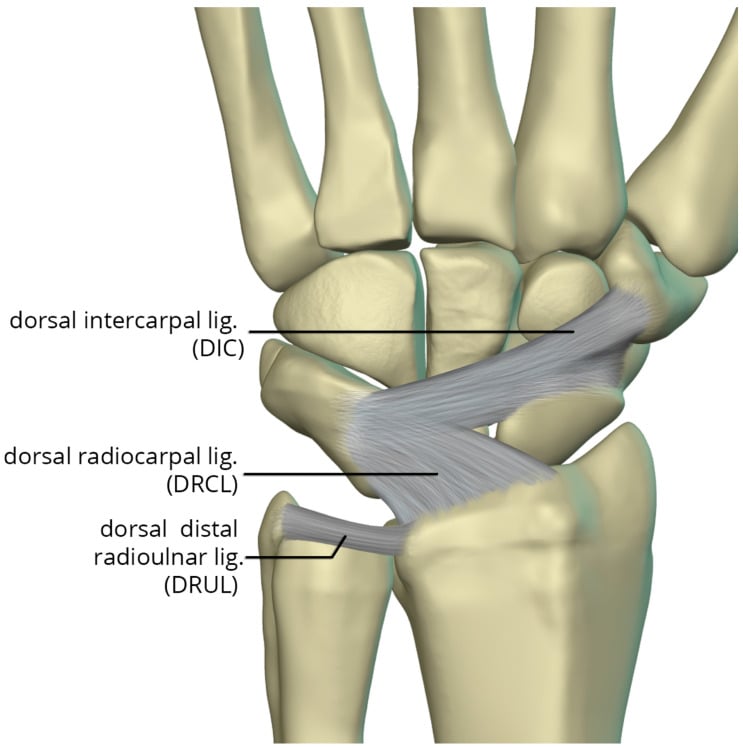
Structures encountered.
- EPL (third compartment) - mobilised and protected, usually transposed subcutaneously
- EDC (fourth compartment) - retracted ulnarly
- ECRB and ECRL (second compartment) - retracted radially
- Superficial radial (radial sensory) nerve branches - cross the radial aspect of the wrist in the subcutaneous tissue and must be protected during superficial dissection
- Dorsal radiocarpal and dorsal intercarpal ligaments - divided to reach the carpus, with repair attempted at closure
The posterior interosseous nerve (PIN) provides sensation to the dorsal wrist capsule. Dividing it (PIN neurectomy) denervates the dorsal capsule and contributes to pain relief after PRC. It is found on the floor of the fourth extensor compartment, lying on the interosseous membrane deep to the EDC tendons, just proximal to the radiocarpal joint. It is not the same as the motor PIN (which innervates the extensor muscles more proximally in the forearm) - the terminal sensory branch is what is divided here.
Patient Positioning and Setup
Position. Supine with the arm extended on a hand table (arm board), the shoulder abducted approximately 60-80 degrees and the elbow flexed. A padded bolster or rolled towel under the wrist facilitates dorsiflexion and exposure.
Anaesthesia. General or regional, the latter a brachial plexus block (supraclavicular, infraclavicular or axillary). Regional anaesthesia provides excellent post-operative analgesia and is commonly used.
Tourniquet. A pneumatic tourniquet on the upper arm at 250 mmHg (or 100 mmHg above systolic pressure), inflated after exsanguination with an Esmarch bandage. Keep tourniquet time under 120 minutes.
Fluoroscopy. The image intensifier, brought in from the head or foot of the table, confirms complete excision of the proximal row, proper seating of the capitate in the lunate fossa and the absence of retained bone fragments.
Instruments. Standard hand instruments, osteotomes, rongeurs, a Freer elevator, small Hohmann retractors and a power burr for smoothing irregular bone surfaces; K-wires may be used for temporary fixation if needed. Loupe magnification (2.5x-4.5x) is recommended for precise dissection and protection of the volar ligamentous structures.
Surgical Technique
Exposure. A longitudinal dorsal incision of approximately 6-8 cm (a transverse incision is an alternative) is centred over Lister tubercle, running from the distal radius to the mid-metacarpal level. Dissect the subcutaneous tissue carefully to protect the superficial radial nerve branches, then open the third compartment, transpose the EPL radially and raise a radially based retinacular flap from the fourth compartment to expose the EDC.
The decision point. Open the dorsal capsule and examine the capitate head and the lunate fossa. If both show intact cartilage, proceed with PRC; if either is significantly degenerate, abandon PRC and convert to four-corner fusion or total wrist fusion.
Scaphoid. Excise it first, piecemeal with rongeur and osteotome, or en bloc by dividing the scapholunate and scaphotrapezial ligaments and the volar capsular attachments. The scaphoid is often fragmented or sclerotic in SLAC and SNAC wrists, which makes piecemeal removal practical.
Lunate. Divide the scapholunate and lunotriquetral ligaments, grasp the lunate with a towel clip or bone clamp and mobilise it by releasing its volar capsular attachments, preserving the volar capsuloligamentous structures (see the alert below).
Triquetrum. Its removal completes the excision; being the most ulnar and accessible, it is the easiest of the three.
Seating the capitate. Manual traction and ulnar deviation help the capitate head migrate proximally into the lunate fossa, and fluoroscopy confirms concentric seating and adequate reduction. Smooth any osteophytes or irregular surfaces on the capitate head or radial fossa with a rongeur or power burr.
PIN neurectomy. Identify the terminal PIN (see the pearl on the surgical interval) and excise a 1-2 cm segment, submitting it for histological confirmation if desired.
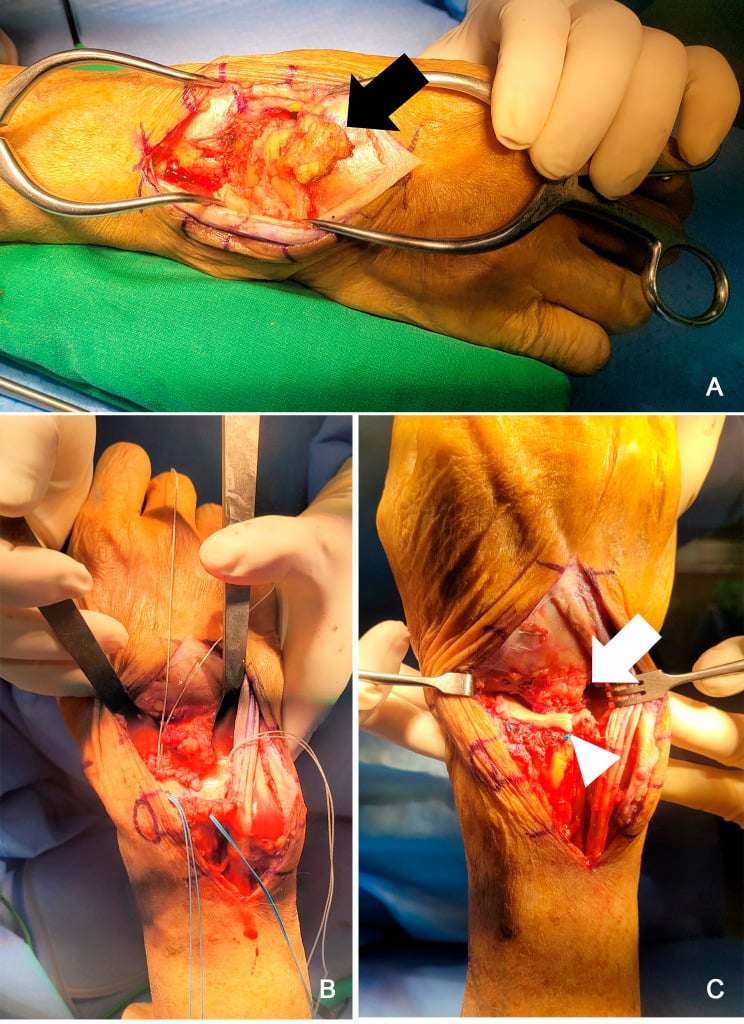
During removal of the scaphoid and lunate, aggressive dissection volarly can damage the radioscaphocapitate (RSC) ligament, the long radiolunate (LRL) ligament, and the volar wrist capsule. These structures provide secondary stability to the capitate-lunate fossa articulation after PRC. If they are disrupted, the capitate may subluxate volarly. Dissect immediately against bone, staying subperiosteal, and avoid plunging through the volar capsule.
Structures at Risk and Complications
PRC has a favourable complication profile compared with four-corner fusion, but its specific complications must be understood.
Capitate-lunate fossa degeneration. The most significant long-term concern; the size mismatch described under anatomy is its theoretical basis. Over 10-20 years, degenerative change may develop at the new articulation, bringing recurrent pain and the need for total wrist fusion; this is the principal argument against PRC in very young patients (under 40-45).
Over 15-20 years, many patients develop degenerative changes at the capitate-lunate fossa interface. This is why PRC is generally recommended for patients aged 50-60 years or older in some practices, while younger patients may be steered toward four-corner fusion (which preserves the native radiolunate joint). However, this age threshold is debated, and many surgeons offer PRC to younger patients who understand the potential need for future fusion.
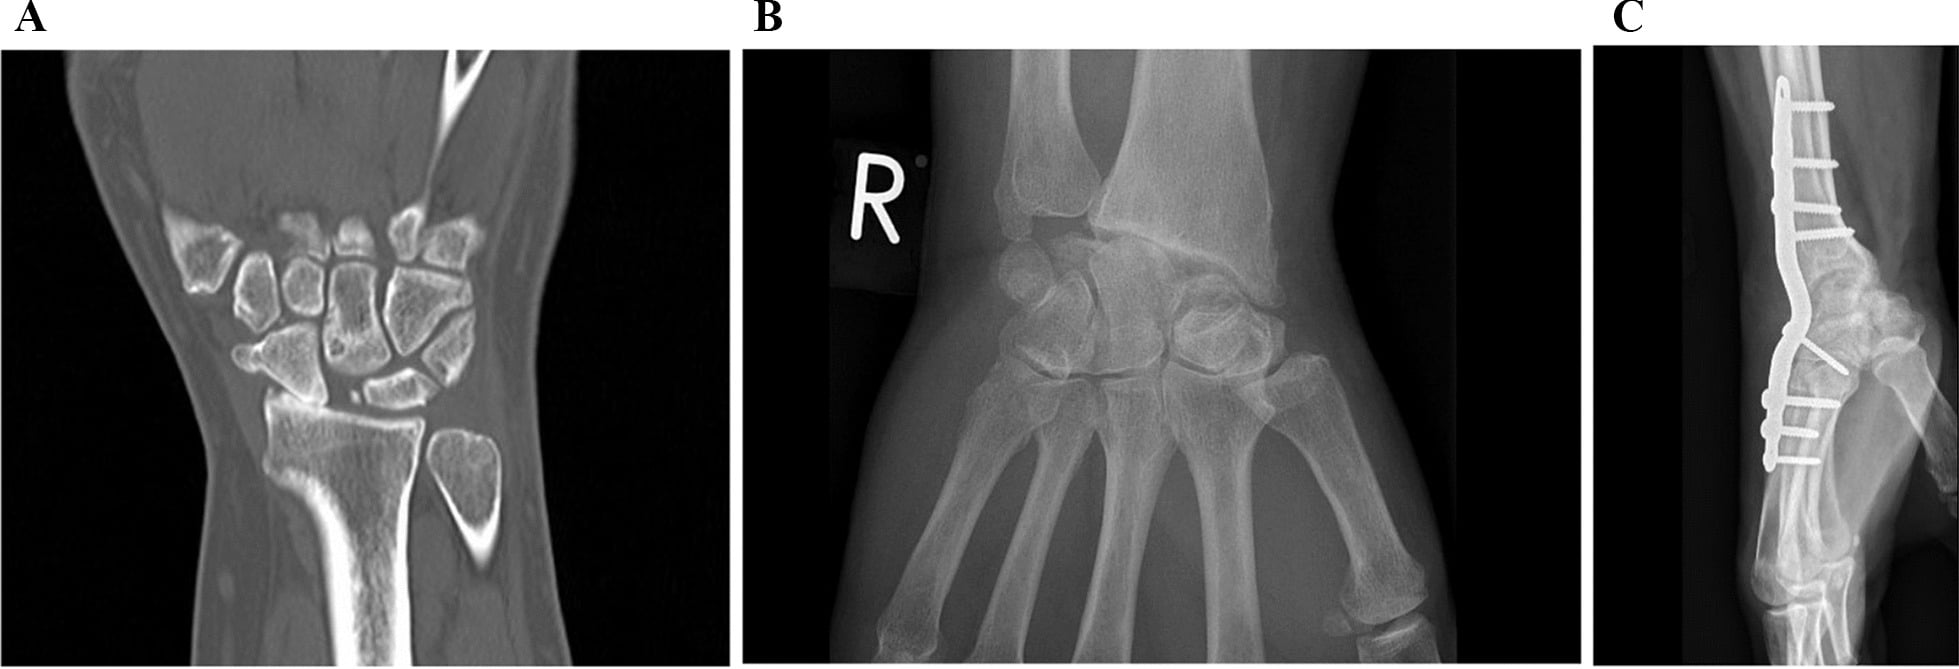
Volar subluxation of the capitate. Follows damage to the volar ligaments during excision (see the alert above) and presents with pain, weakness and a palpable volar prominence. Treatment is capsular reconstruction or conversion to total wrist fusion.
Radial sensory nerve injury. Branches of the superficial radial nerve crossing the dorsal wrist are at risk during superficial dissection, and a neuroma causes dorsal wrist and thumb dysaesthesia. Meticulous handling and retraction of these branches is essential.
Extensor tendon irritation or rupture. Chronic tenosynovitis or attrition over prominent bone edges, especially a retained scaphoid ridge, may irritate or rupture the EPL, EDC or EIP. Smooth every bone edge and repair the retinaculum to provide a gliding surface.
Persistent pain. Some patients have residual pain despite a technically successful PRC, particularly with heavy loading or at end-range motion. PIN neurectomy reduces this risk but does not eliminate it, and smokers and heavy manual labourers are at higher risk.
Stiffness. Some loss of motion is inherent, because the new articulation is less mobile than the native two-row system. Stiffness beyond that may come from capsular contracture, prolonged immobilisation or arthrofibrosis; early protected mobilisation after 3-4 weeks reduces the risk.
Carpal tunnel syndrome. Oedema or haematoma in the carpal tunnel after surgery may compress the median nerve, so pre-operative carpal tunnel symptoms should be addressed with a concurrent release.
Reflex sympathetic dystrophy / complex regional pain syndrome (CRPS). Reported in approximately 2-5% of wrist surgery cases; early recognition and multidisciplinary management are essential.
Guidelines, Registries and Global Practice
There is no single universal guideline specifically for PRC; clinical practice follows evidence-based principles of carpal arthritis management and shared decision-making. Several international hand surgery societies have published consensus guidance:
- ASSH (American Society for Surgery of the Hand, US): PRC is recognised as a motion-preserving salvage option for SLAC/SNAC wrist and Kienbock disease when the lunate fossa and capitate head are preserved. The choice between PRC and four-corner fusion should be individualised based on patient age, demands, articular surface integrity, and surgeon experience.
- BSSH (British Society for Surgery of the Hand, UK): PRC is supported in national guidance as a treatment option for stage II and early stage III SLAC/SNAC wrist. The BSSH outcomes standards recognise both PRC and four-corner fusion as acceptable salvage procedures.
- FESSH (Federation of European Societies for Surgery of the Hand): European practice tends to favour four-corner fusion more than North American practice, though the gap has narrowed. FESSH position papers support both PRC and four-corner fusion as valid options, with the key discriminator being capitate head integrity.
- Large-scale national registries for wrist salvage procedures are less developed than arthroplasty registries. However, institutional series and systematic reviews consistently report approximately 80-90% patient satisfaction at 5-10 years and approximately 70-80% satisfaction at 15+ years after PRC.
- Conversion to total wrist fusion after failed PRC is reported in approximately 5-15% of patients at long-term follow-up, with higher conversion rates in younger patients and heavy manual labourers.
- European centres have historically favoured four-corner fusion over PRC, reflecting training traditions and concern about long-term capitate-lunate fossa degeneration. However, PRC adoption has increased as long-term data demonstrate acceptable durability.
- North American hand surgeons more commonly perform PRC, particularly in older or lower-demand patients, valuing its simplicity and lower complication rate.
- In Asia-Pacific practice, both procedures are widely used, with some centres reporting excellent results with PRC for Kienbock disease (reflecting the higher prevalence of Kienbock disease in this population).
- In low- and middle-income settings, PRC is valued for its simplicity (no expensive implants, no bone graft harvesting for fusion, shorter operative time) and predictable outcomes.
- Total wrist fusion after failed PRC is technically straightforward (no prior hardware to remove, no nonunion to address) and provides reliable pain relief.
- Patients should be counselled pre-operatively about the possibility of future fusion, particularly if they are young or perform heavy manual work.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A 55-year-old office worker presents with progressive right wrist pain and stiffness. She had a scapholunate ligament injury 8 years ago that was not treated. Radiographs show scapholunate dissociation with radioscaphoid arthritis and scaphocapitate joint narrowing. The radiolunate joint appears preserved. She wants to retain as much wrist motion as possible. Discuss your management.”
“A 40-year-old right-hand-dominant carpenter presents with progressive left wrist pain and stiffness. MRI shows Lichtman stage IIIB Kienbock disease with lunate collapse and early scaphoid flexion. The lunate is fragmented and avascular. He wants to continue working as a carpenter. Discuss the surgical options and justify your recommendation.”
One-liner
- Motion-preserving salvage: excision of scaphoid, lunate, and triquetrum with capitate seating into the lunate fossa
- Described by Stamm (1946); principle is to remove the arthritic proximal row and create a simplified radiocarpal joint
Indications
- SLAC wrist stage I-II (and early III if capitate head preserved)
- SNAC wrist analogous stages
- Kienbock disease Lichtman IIIA / early IIIB
- Chronic carpal instability with secondary arthritis
- Elderly or low-demand patients prioritising pain relief with motion
Absolute prerequisites (SLIC)
- Intact lunate fossa articular cartilage on the radius
- Intact capitate head cartilage
- No inflammatory arthritis, no pancarpal disease
- Both surfaces must be inspected intra-operatively before committing
Contraindications
- Capitate head degeneration (SLAC stage III)
- Radiolunate arthritis (SLAC stage IV, rheumatoid)
- Inflammatory arthritis involving the wrist
- Active infection, severe osteoporosis
- Pre-operative wrist motion less than 30 degrees flexion-extension
Surgical technique
- Dorsal approach through third or fourth extensor compartment
- Inspect capitate head and lunate fossa first - critical decision point
- Excise scaphoid (piecemeal), lunate, then triquetrum
- Protect volar capsuloligamentous structures (RSC, LRL ligaments)
- PIN neurectomy on floor of fourth compartment
- Confirm concentric capitate seating with fluoroscopy
- Immobilise 3-4 weeks then progressive mobilisation
PRC vs Four-Corner Fusion
- PRC: simpler, no hardware, no nonunion risk, shorter recovery, slightly less grip strength
- 4CF: better grip strength, preserves radiolunate joint, but has hardware issues and nonunion risk
- Both provide comparable pain relief and patient satisfaction
- Choice depends on age, demands, articular integrity, and surgeon/patient preference
Outcomes
- Flexion-extension arc: approximately 60-65% of contralateral
- Grip strength: approximately 50-60% of contralateral
- Patient satisfaction: approximately 80-90% at 5-10 years
- Conversion to TWF: approximately 5-15% at long-term follow-up
- Long-term radiographic degeneration common but often asymptomatic
Complications
- Capitate-lunate fossa degeneration (long-term, 10-20 years)
- Volar subluxation of capitate if volar ligaments damaged
- Radial sensory nerve neuroma
- Extensor tendon irritation or rupture
- CRPS (approximately 2-5%)
- Persistent pain despite technically successful procedure
Evidence Base
Cohen and Kozin - Degenerative Arthritis of the Wrist: Proximal Row Carpectomy Versus Four-Corner Arthrodesis
- Two cohorts of 19 patients from separate institutions, each performing exclusively one procedure for scapholunate advanced collapse, matched preoperatively for age, gender, dominance, stage and pain/function. Follow-up averaged 19 months after PRC and 28 months after four-corner arthrodesis. The flexion-extension arc was effectively identical - 81 degrees after PRC and 80 degrees after arthrodesis, being 62 and 58 per cent of the opposite wrist - while the arthrodesis group kept more radial deviation and total radial-ulnar deviation. Grip strength averaged 71 per cent after PRC against 79 per cent after arthrodesis. Pain relief and satisfaction were equivalent; the only significant functional difference was a higher SF-36 mental health component score in the arthrodesis group, with no difference on the physical component or a wrist-specific outcome scale.
Wall et al - Proximal Row Carpectomy: Minimum 20-Year Follow-Up
- Seventeen wrists in 16 patients, including seven manual labourers, operated at an average age of 36 years and reviewed at a minimum of 20 years. Survival was 65 per cent, the flexion-extension arc 68 degrees and grip strength 72 per cent of the contralateral side, and every patient returned to their original employment. There was no correlation between radiographic degenerative change and satisfaction. The predicted probability of failure was higher the younger the patient at surgery, levelling off at age 40; the authors recommend a minimum age between 35 and 40 while explicitly declining to exclude younger patients, who instead need counselling about the increased failure risk.
Mulford, Ceulen, and Bosch - Proximal Row Carpectomy vs Four Corner Fusion: Systematic Review of Outcomes
- Fifty-two articles reporting PRC or four-corner fusion for SLAC or SNAC wrists were collated. Grip strength, pain relief and subjective outcomes were similar between the two procedures. PRC may give a better postoperative range of movement and avoids the complications specific to four-corner fusion - nonunion, hardware problems and dorsal impingement - but the risk of subsequent radiocarpal osteoarthritis is significantly higher after PRC, although the majority of those patients were asymptomatic at review.
Richou et al - Proximal Row Carpectomy: Long-Term Results
- Continuous single-centre series of 24 patients operated mainly for Kienbock disease, SLAC and SNAC wrists, assessed by an independent observer at a mean of 116 months. Pain improved in every case; 83 per cent were satisfied, with a mean visual analogue score of 1.2, subjective wrist value 76 per cent and DASH 31. The flexion-extension arc averaged 76 degrees and grip strength 78 per cent of the contralateral limb. Radiographic change appeared in 52 per cent with no clinical impact, and three patients required arthrodesis - all of whom had never been comfortable with their carpectomy.