The Great Extensor Nerve of the Upper Limb
- Originates from Posterior Cord (C5-T1)
- Passes through Triangular Interval to enter Spiral Groove
- Pierces Lateral Intermuscular Septum 10cm proximal to lateral epicondyle
- Divides into Superficial (Sensory) and Deep (PIN) at lateral epicondyle
- PIN enters Supinator via Arcade of Frohse
- “Triceps is usually SPARED in humeral shaft fractures (innervation is proximal)
- “ECRL is innervated by Radial Nerve proper (before division)
- “ECRB is often innervated by Radial Nerve proper or PIN
- “Mobile Wad = BR, ECRL, ECRB
Overview and Function
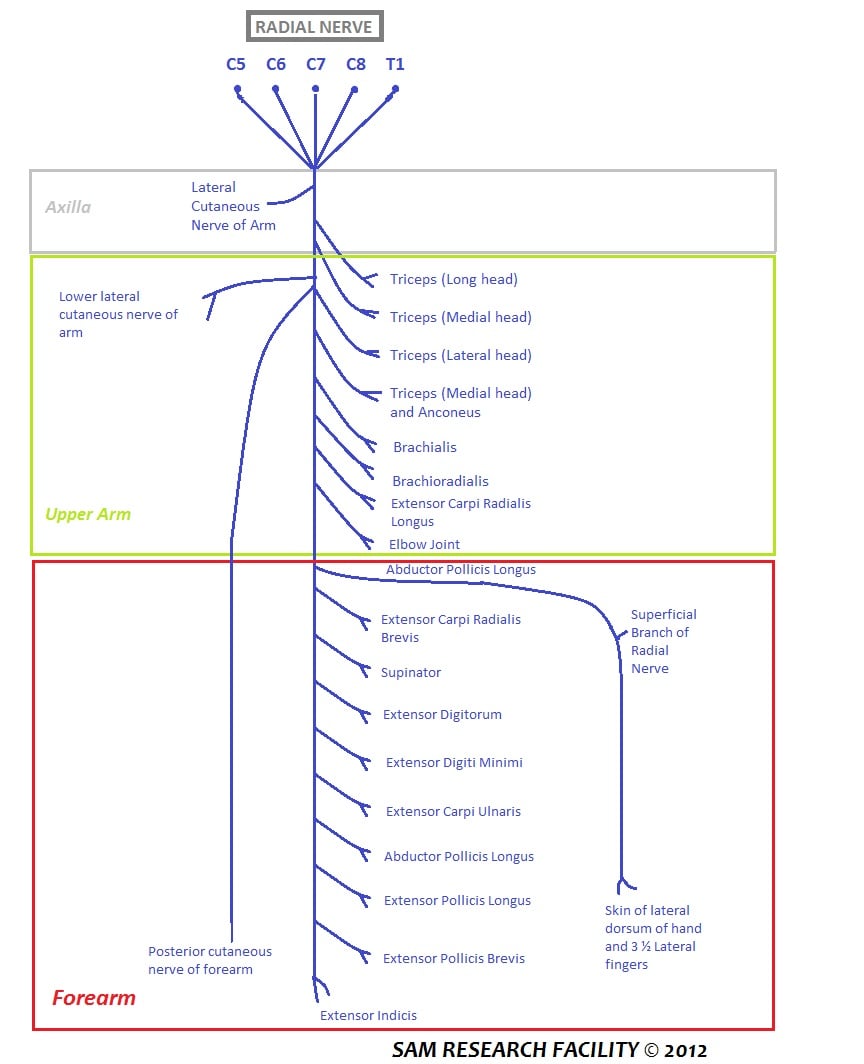
The radial nerve is the nerve of extension. It extends the elbow, the wrist and the fingers, and it supinates the forearm when the elbow is extended; lose it and the result is the classic wrist drop. What is lost depends on where along its course the nerve is injured, so the motor and sensory maps below are the tools for localising a lesion.
Motor supply. The muscle groups are listed from proximal to distal, which is also the order of motor recovery.
- Arm - triceps (long, lateral and medial heads) and anconeus
- Around the lateral epicondyle - brachioradialis, ECRL and, variably, ECRB
- Forearm, through the posterior interosseous nerve (PIN) - supinator, EDC, EDM, ECU, APL, EPB, EPL and EIP
Sensory supply. Four cutaneous nerves, three of them given off before the hand:
- Posterior cutaneous nerve of the arm, arising in the axilla - the posterior arm
- Lower lateral cutaneous nerve of the arm, arising in the spiral groove - the lateral aspect of the lower arm
- Posterior cutaneous nerve of the forearm, arising in the spiral groove - a strip down the middle of the posterior forearm
- Superficial radial nerve (SRN) - the dorsum of the thumb, index, middle and radial half of the ring finger, proximal to the PIP joints
The autonomous zone is the first dorsal web space, and that is where sensation is tested.
Course and Relations
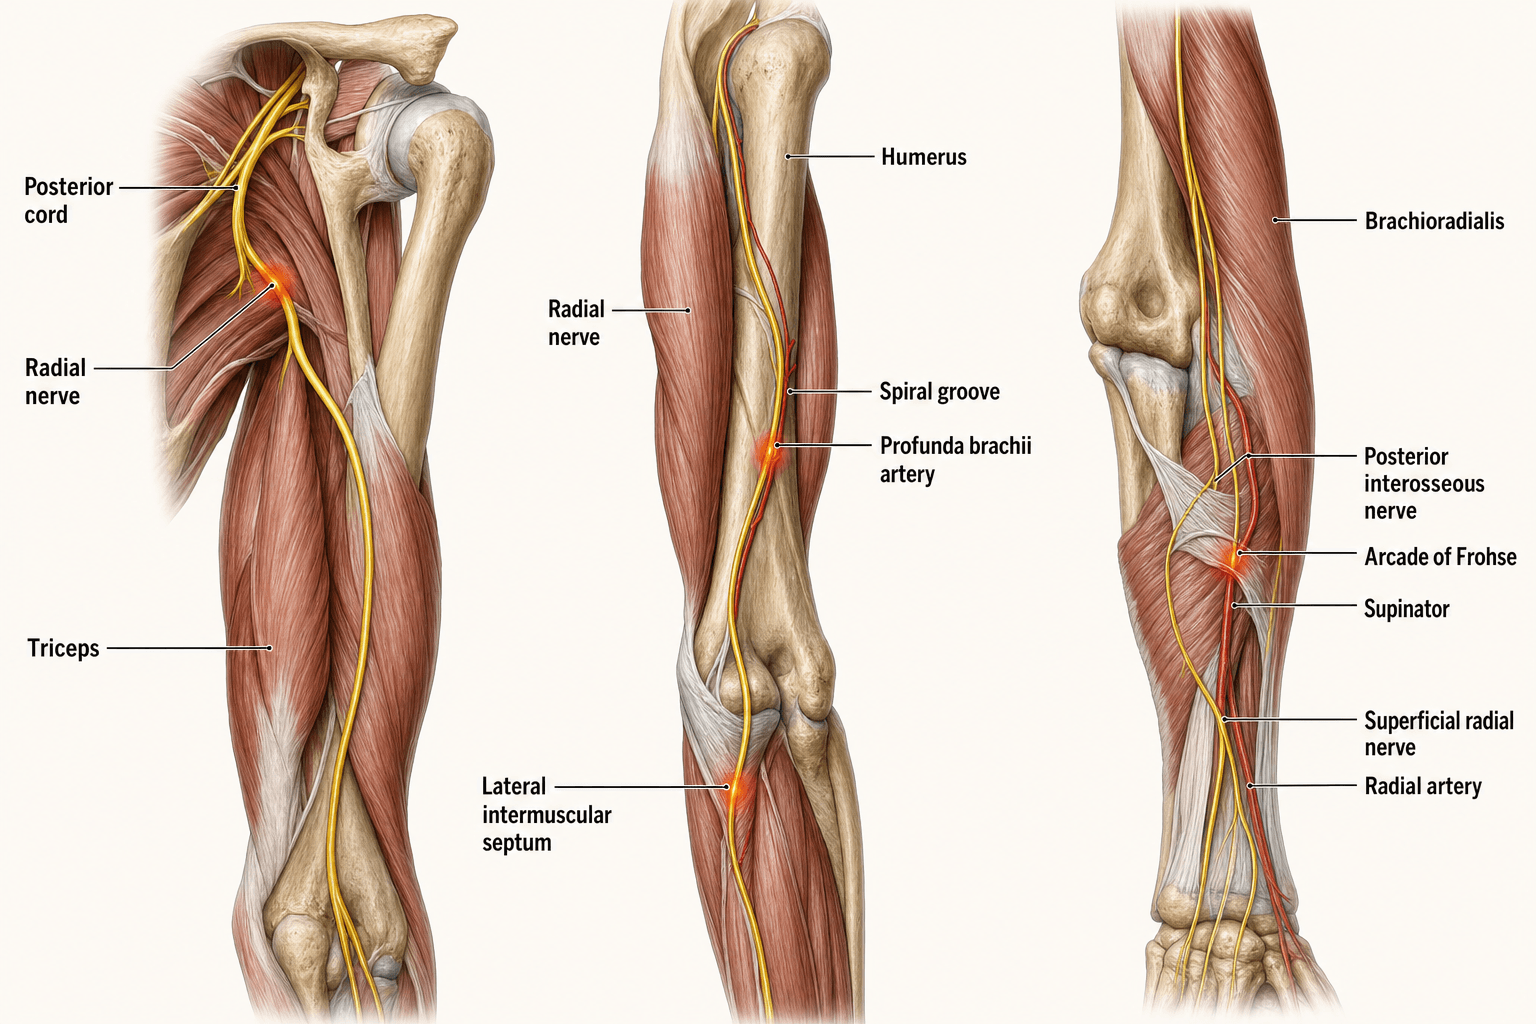
Origin. The radial nerve is the continuation of the posterior cord of the brachial plexus, with roots C5, C6, C7, C8 and (T1). In the axilla it lies posterior to the axillary artery, and shoulder dislocation can injure it. Branches to triceps leave both in the axilla and in the spiral groove.
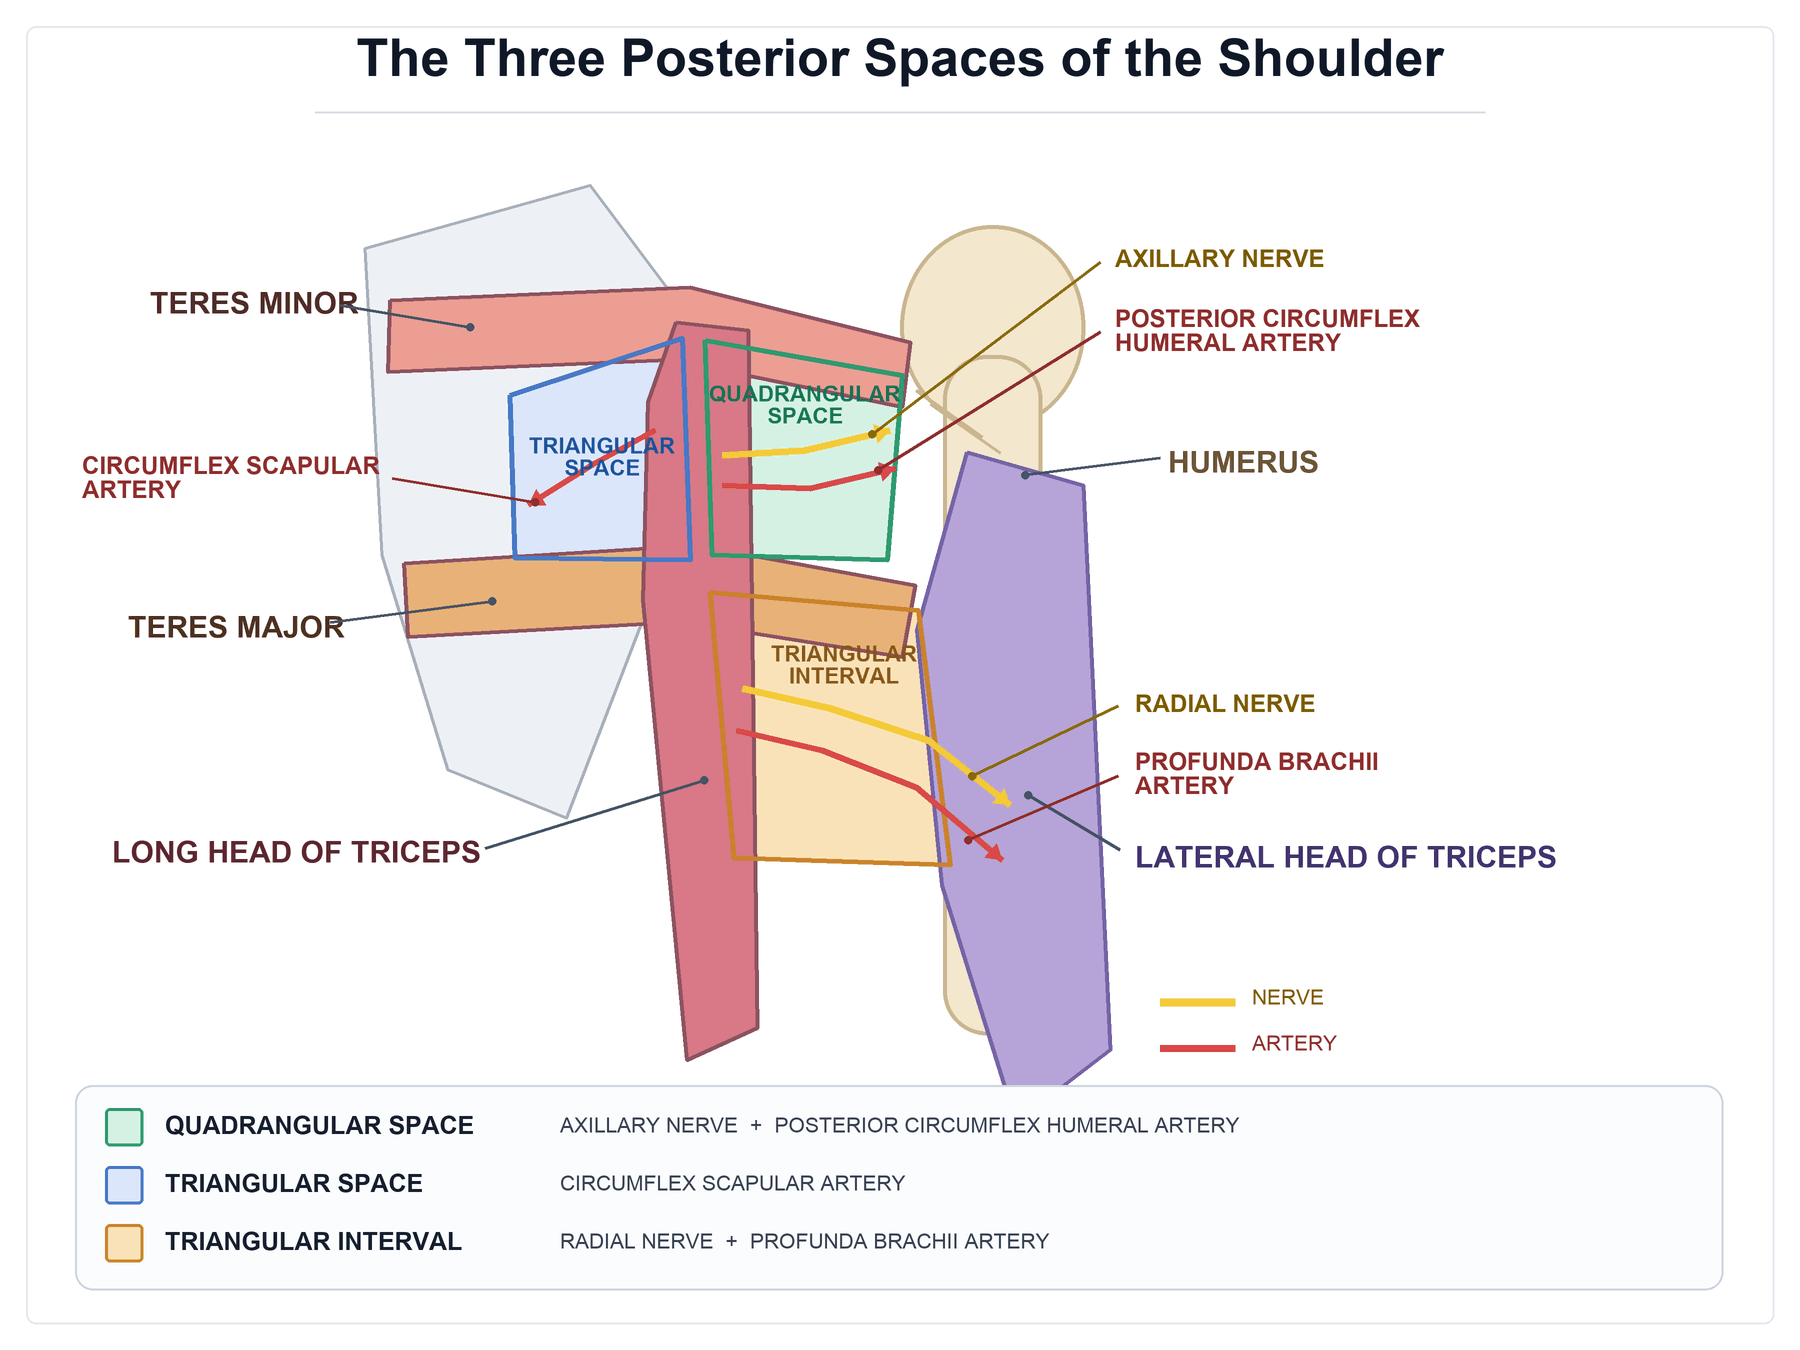
The triangular interval. The nerve leaves the axilla for the posterior compartment through the triangular interval, travelling with the profunda brachii artery. Examiners pair the interval with its two neighbours, and it is the lowest of the three, bounded above by teres major. The one not to confuse it with is the quadrangular space, which transmits the axillary nerve (at risk in shoulder dislocation and proximal humerus fracture) and the posterior circumflex humeral artery. The triangular space between them carries only the circumflex scapular vessels, and no nerve.
- Boundaries
- Teres minor (above), teres major (below), long head of triceps (medial), surgical neck of humerus (lateral)
- Contents
- AXILLARY nerve + posterior circumflex humeral artery
- Boundaries
- Teres minor (above), teres major (below), long head of triceps (lateral)
- Contents
- Circumflex scapular artery (branch of the subscapular artery)
- Boundaries
- Teres major (above), long head of triceps (medial), shaft/lateral head of humerus (lateral)
- Contents
- RADIAL nerve + profunda brachii (deep brachial) artery
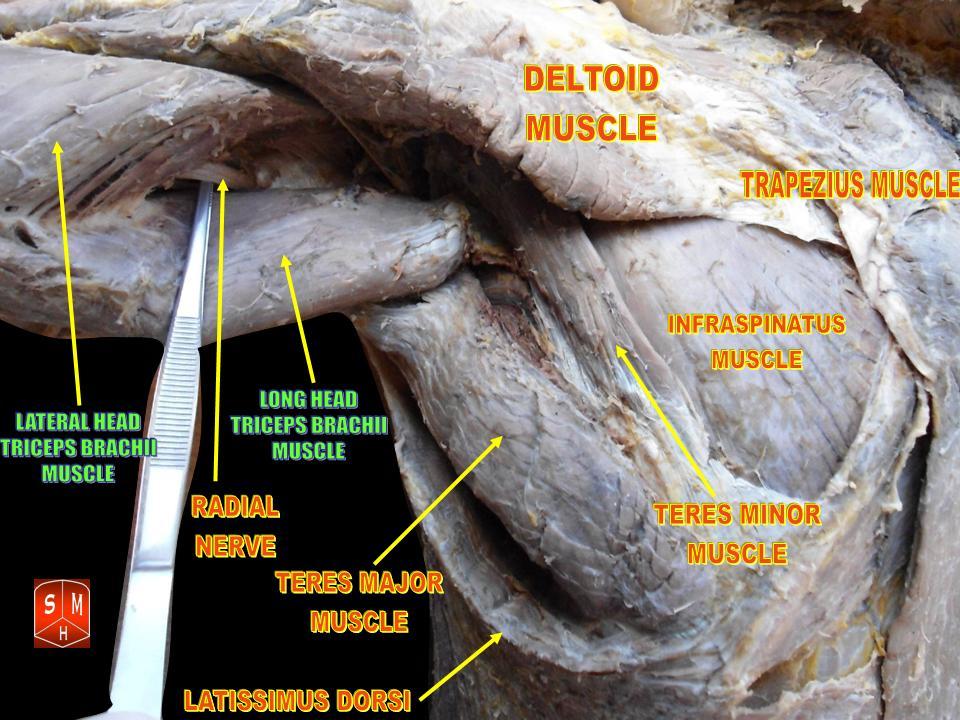
The spiral groove. The nerve winds around the humerus in the spiral (musculospiral) groove, from medial to lateral, between the lateral and medial heads of triceps. Here it supplies those two heads and anconeus, and gives off the lower lateral cutaneous nerve of the arm and the posterior cutaneous nerve of the forearm. This is the segment vulnerable in humeral shaft fractures and the classic site of Saturday night palsy.
The lateral intermuscular septum. About 10cm proximal to the lateral epicondyle the nerve pierces the lateral intermuscular septum and passes from the posterior to the anterior compartment, where it lies between brachialis medially and brachioradialis laterally. This is the danger zone in lateral approaches to the humerus. The same tether makes the Holstein-Lewis fracture, a spiral fracture of the distal third, dangerous: with the nerve held by the septum at that level, it is at high risk of entrapment or injury.
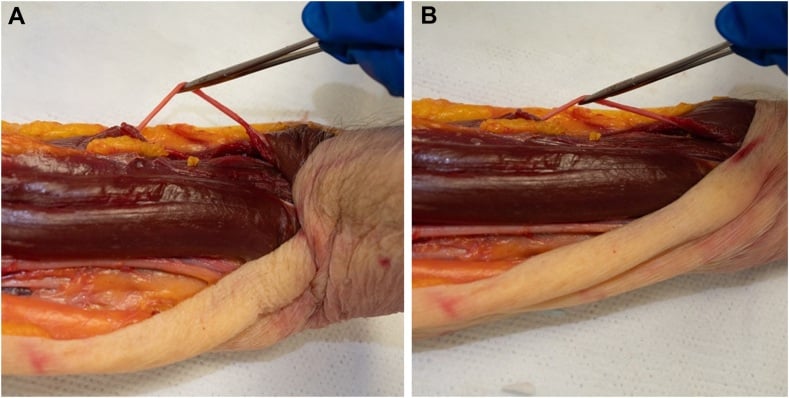
Branches above the elbow. In the anterior compartment the nerve supplies, in order, brachioradialis, ECRL and then ECRB, whose supply is variable: often from the radial nerve proper, or from the PIN. ECRL is supplied by the radial nerve proper, before the division. Brachioradialis, ECRL and ECRB together form the mobile wad of Henry.
The division. Anterior to the lateral epicondyle, at the level of the radiocapitellar joint, the nerve divides into the superficial radial nerve, which is purely sensory, and the posterior interosseous nerve, which is purely motor. The radial recurrent vessels, the leash of Henry, overlie the nerve at the level of the division.
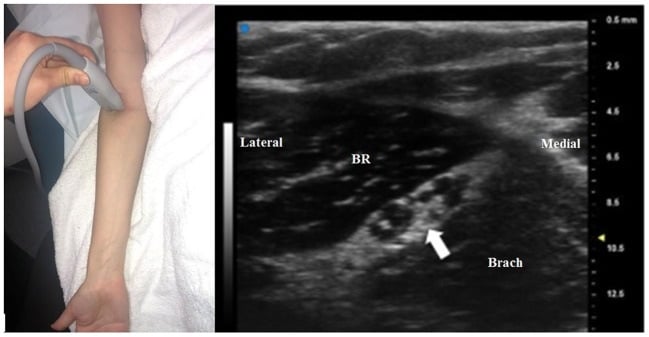
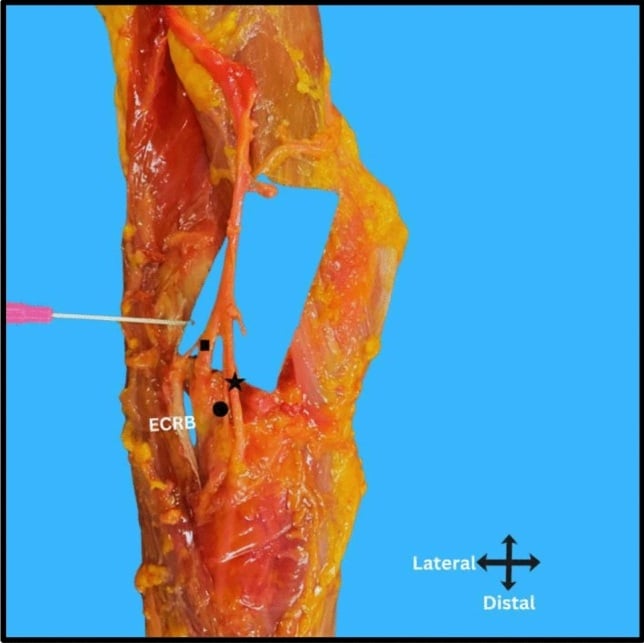
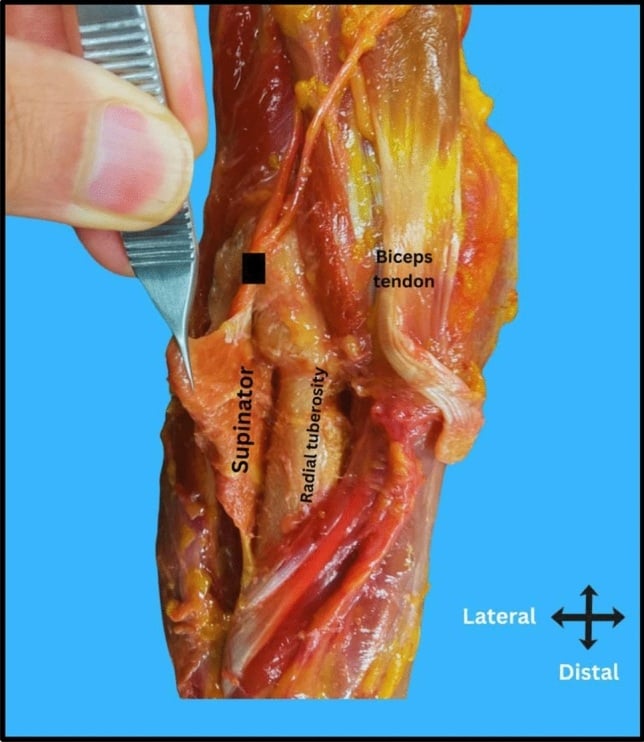
The posterior interosseous nerve. The PIN passes beneath the arcade of Frohse, the proximal edge of supinator (the supinator arch). It winds around the radial neck within the substance of supinator, between its superficial and deep heads, then emerges in the posterior compartment to supply the extensors and ends as a sensory twig to the wrist capsule.
The superficial radial nerve. The SRN runs deep to brachioradialis through the forearm. In the distal third it emerges posteriorly between the tendons of brachioradialis and ECRL, at Wartenberg's point, then becomes subcutaneous and divides into dorsal digital nerves. Injury here causes Wartenberg's syndrome, which is purely sensory.
Levels of Injury
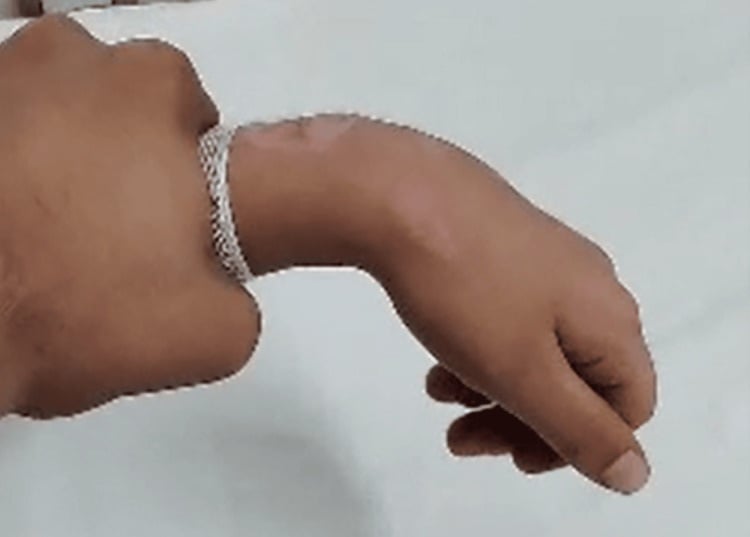
The level decides the deficit. A lesion in the axilla affects triceps as well as the wrist and finger extensors. A lesion in the spiral groove usually spares triceps, because its innervation is proximal, and this is what distinguishes crutch palsy from Saturday night palsy. A PIN lesion at the elbow is motor only: ECRL is preserved, so the wrist still extends, in radial deviation.
- Motor Loss
- Triceps, Wrist Ext, Finger Ext
- Sensory Loss
- Post Arm, Forearm, Dorsal Hand
- Eponym
- Crutch Palsy / Saturday Night (High)
- Motor Loss
- Wrist Ext (Weak), Finger Ext
- Sensory Loss
- Post Forearm, Dorsal Hand (Triceps Sparing)
- Eponym
- Saturday Night Palsy / Humeral #
- Motor Loss
- Finger Ext, Thumb Ext (ECRL preserved → radial deviation)
- Sensory Loss
- None (PIN is motor)
- Eponym
- PIN Syndrome
- Motor Loss
- None
- Sensory Loss
- Dorsal Webspace
- Eponym
- Wartenberg Syndrome
Clinical Assessment
Motor testing. Test each group on its own:
- Triceps - extend the elbow against resistance, with the shoulder abducted to eliminate gravity
- Brachioradialis - flex the elbow in neutral rotation
- ECRL and ECRB - extend the wrist, and check for radial deviation
- EDC - extend the MCP joints with wrist extension blocked
- EPL - retropulsion of the thumb, lifting it off the table with the palm down
Sensory testing. Test the autonomous zone. Any sensory loss more proximal than that suggests a higher lesion.
Tenodesis imitates extension in both directions. Finger flexion can make the wrist appear to extend, and wrist flexion can make the fingers appear to extend. Always isolate the joint being tested: test EDC with the MCP joints isolated.
Investigations
Imaging. Each modality answers a different question:
- Plain radiographs - a humeral shaft fracture (Holstein-Lewis) or a radial head fracture or dislocation
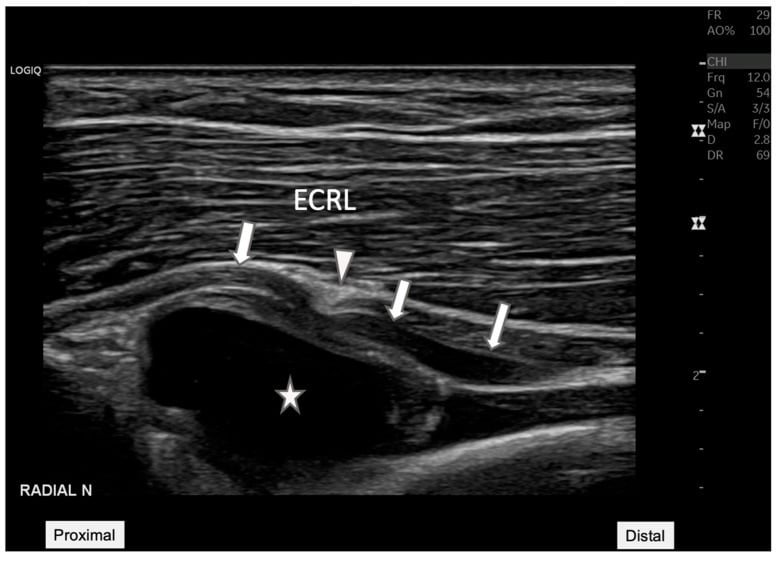
- Ultrasound - can visualise nerve continuity in a Holstein-Lewis fracture, and whether the nerve is entrapped in callus
- MRI - a soft-tissue mass, such as a lipoma or ganglion, compressing the PIN
Neurophysiology. EMG and nerve conduction studies are used to:
- Assess continuity in closed injuries
- Monitor recovery, looking for re-innervation potentials
- Distinguish PIN syndrome from radial tunnel syndrome
Timing. A baseline study immediately after injury is of limited value, because Wallerian changes take roughly 3-4 weeks to appear, and 3-4 weeks is regarded as optimal for the first assessment. The best timing of that first study, and whether ultrasound should pre-empt it, is still debated, with imaging increasingly used to triage early.
Differential Diagnosis of Wrist/Finger Drop
A "wrist drop" is not always a radial nerve lesion, and not every radial nerve lesion is at the same level. Localising the lesion is the high-yield exam skill.
- Triceps
- Weak/absent
- Wrist Extension
- Absent (true wrist drop)
- Finger (MCP) Extension
- Absent
- Sensory Loss
- Dorsal forearm + 1st webspace
- Discriminator
- Triceps involved = lesion above spiral groove
- Triceps
- Spared
- Wrist Extension
- Weak/absent
- Finger (MCP) Extension
- Absent
- Sensory Loss
- Dorsal forearm + 1st webspace
- Discriminator
- Triceps spared, sensory loss present
- Triceps
- Spared
- Wrist Extension
- Present (radial deviation)
- Finger (MCP) Extension
- Absent (finger drop)
- Sensory Loss
- None
- Discriminator
- No sensory loss, ECRL preserved
- Triceps
- Spared
- Wrist Extension
- Present
- Finger (MCP) Extension
- Present
- Sensory Loss
- None
- Discriminator
- Pain only, no motor deficit
- Triceps
- Weak
- Wrist Extension
- Weak
- Finger (MCP) Extension
- Weak
- Sensory Loss
- Dermatomal (middle finger)
- Discriminator
- Neck pain, reflex changes, multi-nerve pattern
- Triceps
- Variable
- Wrist Extension
- Weak
- Finger (MCP) Extension
- Weak
- Sensory Loss
- Cortical pattern
- Discriminator
- Increased tone, brisk reflexes, no autonomous-zone map
- Triceps
- Variable
- Wrist Extension
- Weak (often bilateral)
- Finger (MCP) Extension
- Weak
- Sensory Loss
- Variable
- Discriminator
- Systemic features, often bilateral / multifocal
Answer three questions in order: (1) Is the triceps working? (above vs below spiral groove). (2) Is there sensory loss? (radial nerve proper/SRN vs pure PIN). (3) Does the wrist extend with radial deviation? (ECRL preserved = PIN lesion).
Management of Palsy
Closed palsy is observed. Palsy complicates 11.8% of humeral shaft fractures in Shao's systematic review, and most are neurapraxias, with 85-90% recovering. Spontaneous recovery without exploration runs at around 71%, and the dominant evidence (Shao 2005; Bishop and Ring 2009) supports observation for closed palsy, with decision analysis favouring waiting.
Where the debate lies. The case for exploring earlier is made for high-energy mechanisms and for secondary palsy, which develops after fracture manipulation; some argue the threshold for exploration should be lower there. With an open fracture, many authors recommend inspecting the nerve at debridement or fixation, since a lacerated or interposed nerve is more likely, while others argue that a clean, low-energy open wound does not in itself mandate routine exploration. No high-level trial settles this.
Holstein-Lewis and postoperative palsy. A palsy with a Holstein-Lewis fracture has a high rate of recovery, but some advocate early exploration when the spiral distal fracture is the cause, because the nerve may be encased. After surgery, a nerve that was seen intact is observed; if its integrity is unknown, consider exploration.
Management Algorithm for Humeral Shaft Palsy
Closed injury or open? Check nerve function.
If no clinical recovery. Look for fibrillation potentials (denervation).
If no recovery by 3-4 months (and no advancing Tinel's), consider exploration + nerve graft OR tendon transfers.
Jones transfer, below.
While waiting. A dynamic extension splint (outrigger) prevents flexor contractures and assists function while the nerve recovers. Physiotherapy maintains passive range of motion in every joint to prevent stiffness, and strengthens the substitute muscles.
Tendon transfers. Transfers reconstruct a palsy that has failed to recover. The decision is weighed from 3-4 months, as above; the standard texts frame transfers for palsy that has not recovered by 3-6 months, or for confirmed neurotmesis.
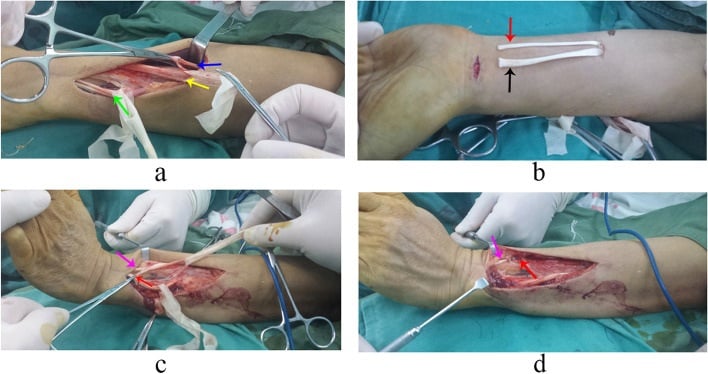
The classic Jones Transfer for radial nerve palsy:
- Pronator Teres → ECRB (Restore Wrist Ext)
- FCU (or FCR) → EDC (Restore Finger Ext)
- Palmaris Longus → EPL (Restore Thumb Ext)
Compression Syndromes
The radial tunnel runs from the radiocapitellar joint to the distal edge of supinator. The PIN can be compressed at five classic points along it, a favourite enumeration in vivas:
- Fibrous bands at the front of the radiocapitellar joint, tethering the nerve to the capsule
- The leash of Henry, the radial recurrent vessels crossing the nerve
- The medial (tendinous) edge of ECRB
- The arcade of Frohse, the thickened proximal edge of the superficial head of supinator - the commonest site
- The distal edge of supinator
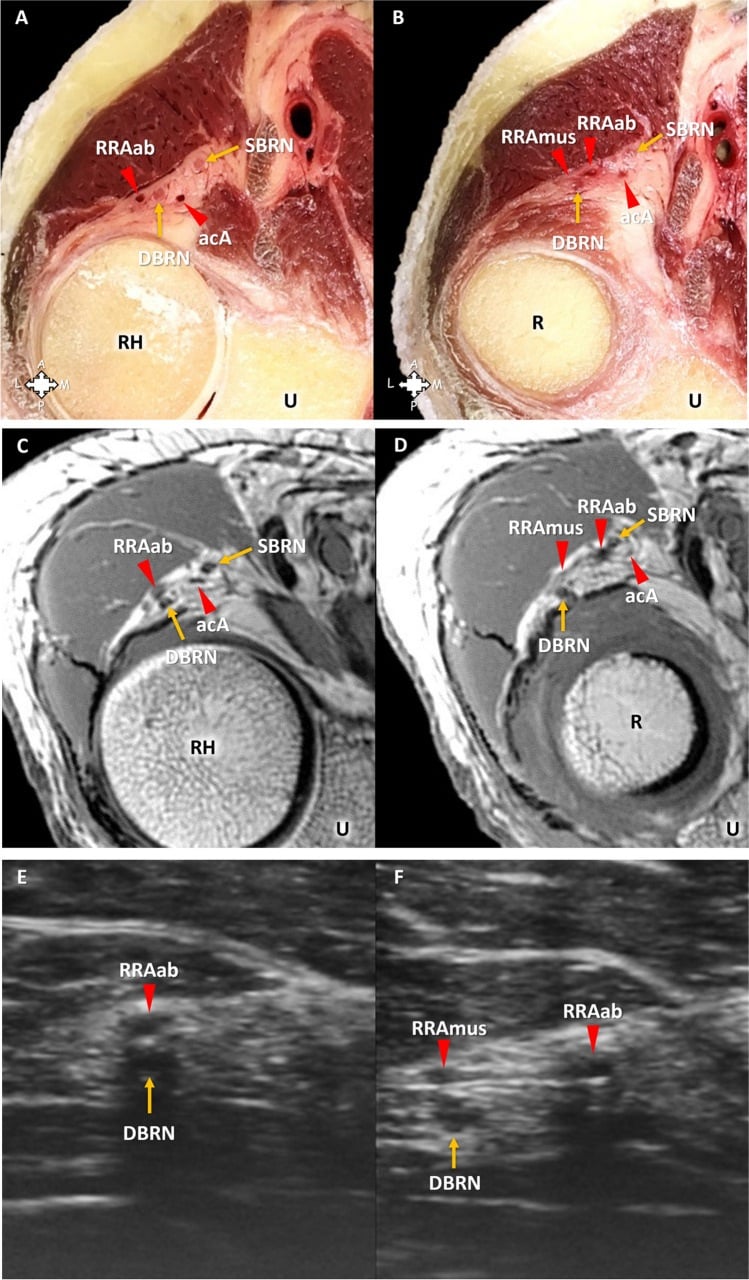
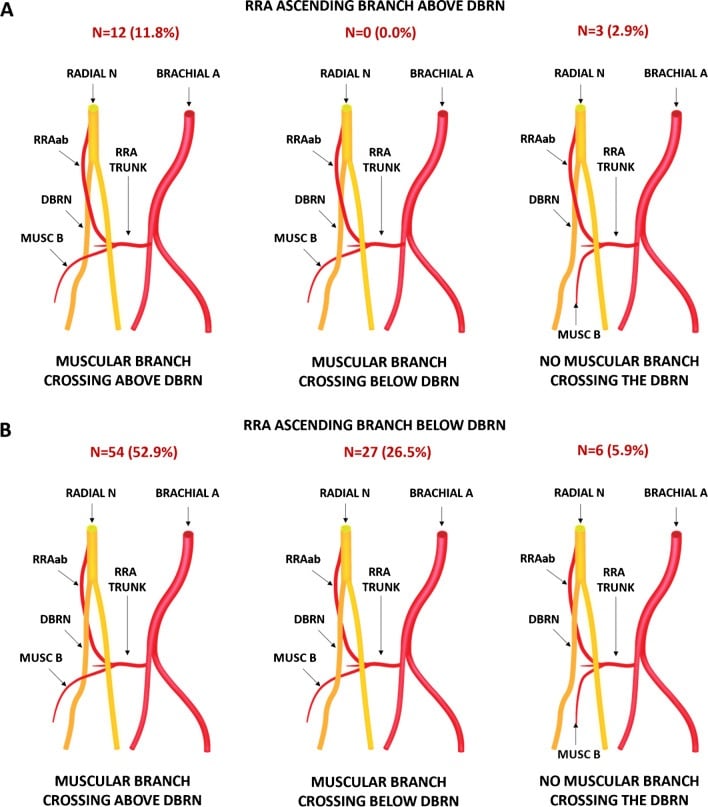
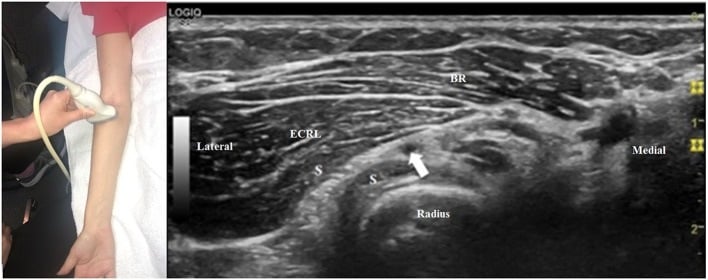
Same tunnel, two syndromes. PIN syndrome is a painless motor palsy: finger drop, with the wrist extending in radial deviation. Radial tunnel syndrome is pain in the proximal forearm with no motor weakness; it resembles tennis elbow, but the pain is 4cm distal to the epicondyle. The arcade of Frohse is the commonest culprit in both.
Radial tunnel syndrome is contested. It is a pain syndrome with no objective motor or sensory deficit and no reliable electrodiagnostic confirmation, and its overlap with lateral epicondylitis and inconsistent surgical results fuel scepticism. Conservative management is the mainstay, and decompression outcomes are variable.
Decompression. No single surgical window exposes all five sites, so the approach is matched to the suspected level, and complete release may need more than one window.
Wartenberg's syndrome. The SRN is compressed between the tendons of brachioradialis and ECRL, which scissor it during pronation. It causes pain and paraesthesia over the dorsal thumb and web space, with a positive Tinel's sign. The differential is de Quervain's tenosynovitis, which Finkelstein's test distinguishes. Surgical release is rarely needed but effective.
Surgical Approaches
Posterior approach to the humerus. Used for distal-third fractures and for exploration of the radial nerve. Through a midline posterior incision:
- Develop the interval between the long and lateral heads of triceps proximally, or split triceps in the midline distally
- Identify the nerve in the spiral groove with the profunda brachii artery
- Trace it distally through the lateral intermuscular septum
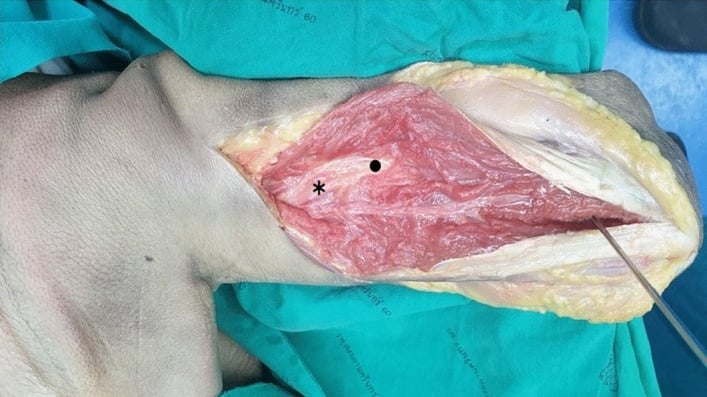
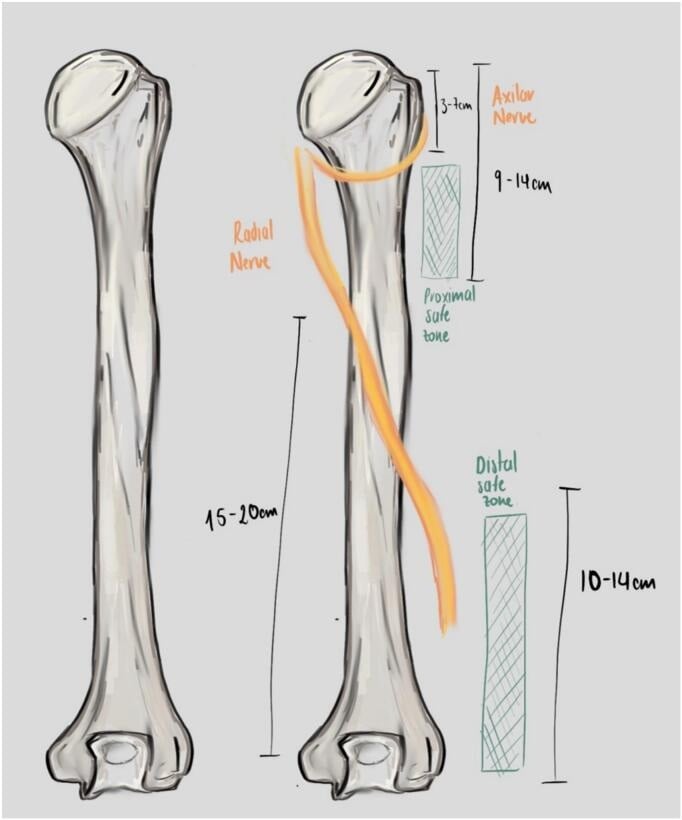
Anterolateral approach. Used for the mid and proximal shaft and for PIN decompression. The interval is brachioradialis (radial nerve) and brachialis (musculocutaneous nerve), and the nerve is identified between them. Proximally on the lateral side, where the nerve crosses the septum, do not strip too vigorously.
Henry approach (volar). Used for PIN decompression and fixation of the radius, and gives excellent exposure of the radius:
- Open the interval between brachioradialis (radial nerve) and FCR (median nerve)
- Identify the SRN under brachioradialis and follow it proximally to the bifurcation
- Ligate the leash of Henry
- Identify the PIN entering supinator
- Supinate the forearm to move the PIN away from the incision
Complications
- Cause
- Injury to SRN
- Prevention
- Protect Wartenberg's point
- Management
- Bury nerve end
- Cause
- Plate fixation (humerus/radius)
- Prevention
- Identify and protect
- Management
- Explore/Repair
- Cause
- Neurotmesis
- Prevention
- Early exploration if open
- Management
- Tendon transfers
- Cause
- Dynamic compression
- Prevention
- Release arcade
- Management
- Decompression
Guidelines, Registries & Global Practice
Global Epidemiology
- Humeral shaft fractures: incidence approximately 14.5 per 100,000 per year in a European population, rising to nearly 60 per 100,000 per year in the ninth decade, with a bimodal pattern (young men, high energy; older women, low-energy falls) (Ekholm 2006).
- Radial nerve palsy complicates roughly 8-12% of humeral shaft fractures overall, highest in middle/distal-third transverse and spiral patterns (Shao 2005; Ekholm 2006).
- Holstein-Lewis (distal-third spiral) fractures account for around 7.5% of shaft fractures but carry approximately 22% palsy risk (Ekholm 2008).
- Spontaneous recovery of closed traumatic palsy is around 71% with observation and approximately 88% overall including those explored (Shao 2005).
Side-by-Side Guidance
- Position on closed radial nerve palsy
- Observation first-line; surgery for low-recovery scenarios or patient preference
- Emphasis
- Decision-analysis and systematic-review driven (Bishop & Ring; Shao)
- Position on closed radial nerve palsy
- Expectant management for closed palsy; document neurovascular status, image to plan
- Emphasis
- Early neurovascular documentation, structured follow-up
- Position on closed radial nerve palsy
- Inspect/protect the nerve during any planned humeral fixation; explore in open injuries
- Emphasis
- Surgical technique, iatrogenic-injury avoidance, fixation planning
- Position on closed radial nerve palsy
- Aligns with conservative-first approach; ultrasound increasingly used to triage
- Emphasis
- Imaging-led triage, nerve continuity assessment
Ready access to high-resolution ultrasound and electrodiagnostics allows early triage of nerve continuity, MRI for compressive masses around the PIN, and microsurgical repair/grafting or tendon transfer when recovery fails.
Where nerve imaging and electrophysiology are scarce, management leans on serial clinical examination (advancing Tinel's sign), dynamic extension splinting to prevent contracture, and tendon transfers - which are reliable, equipment-light and durable.
Radial nerve injury during humeral or radial plating is a recognised complication worldwide - document pre-operative nerve status, identify and protect the nerve, and beware the segment 10cm proximal to the lateral epicondyle. The nerve is also vulnerable to prolonged tourniquet or arm-board pressure (Saturday-night-type compression).
MCQ Practice Points
Q: What is the primary root value of the Radial Nerve? A: C5-T1. It is the largest branch of the brachial plexus and receives fibers from all roots (continuation of posterior cord).
Q: Where does the radial nerve pierce the lateral intermuscular septum? A: 10cm proximal to the lateral epicondyle. This is a critical landmark for the anterolateral approach.
Q: Which muscle is used to restore wrist extension in a radial nerve palsy? A: Pronator Teres. It is transferred to the ECRB tendon (PT → ECRB).
Q: What anatomical structure forms the Arcade of Frohse? A: The proximal fibrotendinous edge of the Supinator muscle.
Q: Which three muscles make up the Mobile Wad of Henry? A: Brachioradialis, ECRL, and ECRB.
Anatomy Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A patient presents with a mid-shaft humeral fracture and a wrist drop. Describe the anatomy of the radial nerve relevant to this injury.”
“Describe the course of the Posterior Interosseous Nerve and the potential sites of compression.”
“A patient has paresthesia over the dorsal thumb and index finger. Differentiate Wartenberg's Syndrome from De Quervain's Tenosynovitis.”
Key Anatomy
- Posterior Cord (C5-T1)
- Triangular Interval (with Profunda Brachii)
- Lateral Intermuscular Septum (pierces 10cm proximal to elbow)
- Arcade of Frohse (Supinator edge) - PIN compression site
- Wartenberg's Point (Distal radius) - SRN emergence
- Lister's Tubercle - EPL turns around it (supplied by PIN)
Branches (Motor)
- Axilla: Long/Medial Triceps
- Spiral Groove: Lateral/Medial Triceps, Anconeus
- Elbow: Brachioradialis, ECRL, ECRB
- PIN: Supinator, EDC, EDM, ECU, APL, EPB, EPL, EIP
Clinical Signs
- Wrist Drop (High lesion)
- Finger Drop + Radial Deviation (PIN lesion)
- Triceps Sparing (Spiral Groove lesion)
- First Dorsal Webspace Numbness (Radial Nerve proper/SRN)
- Tinel's at Wartenberg's point (Wartenberg Syndrome)
Surgical Pearls
- Find nerve in interval between Brachialis and Brachioradialis (Anterior)
- Ligate 'Leash of Henry' (Radial Recurrent vessels)
- Supinate forearm to move PIN away from incision (Henry approach)
- Beware nerve 10cm proximal to lateral epicondyle in lateral plating
Evidence Base
Radial Nerve Palsy in Humeral Shaft Fractures - Landmark Systematic Review
- 35 studies, 1045 patients with radial nerve palsy after humeral shaft fracture
- Overall prevalence of palsy 11.8% (532 palsies in 4517 fractures)
- Overall recovery 88.1%; spontaneous recovery 70.7% in conservatively treated patients
- No significant difference in final result between expectant management and early exploration
- Middle and middle-distal shaft, transverse and spiral patterns carried highest risk
The Holstein-Lewis Fracture and Radial Nerve Risk
- Holstein-Lewis fractures were 7.5% of all humeral shaft fractures (27 of 361)
- Associated with significantly higher acute radial nerve palsy than other patterns: 22% vs 8% (statistically significant)
- All 6 radial nerve palsies recovered regardless of operative or non-operative treatment
- Functional outcome (SMFA) good and similar between treatment groups
Ultrasound Evaluation of the Radial Nerve in Humeral Fractures
- Prospective study of 11 patients with sensorimotor radial deficit after humeral fracture
- In all 5 operated patients, US findings of a severely damaged nerve were confirmed at surgery (entrapment, dissection, laceration, riding on a fragment, buried in callus)
- In the 6 patients treated conservatively, US demonstrated nerve continuity
- US can distinguish a nerve in continuity from an interrupted or entrapped nerve
Observation vs Early Surgery - Decision Analysis
- Expected-value decision analysis using literature-derived probabilities and patient utilities (82 subjects)
- Observation (value 8.4) outperformed early surgery (value 6.7) as the optimal strategy
- Early surgery becomes preferred only if expected spontaneous recovery falls below 40%
- Early surgery also favoured when an informed patient places very high utility on a successful early result
Fingerbreadth Safe-Zone Rule for the Radial Nerve and PIN
- Anatomic study of 10 fresh-frozen cadaveric elbows
- Four fingerbreadths defines a safe zone between the lateral epicondyle and the radial nerve proximally
- Two fingerbreadths defines a safe zone for the PIN from the radiocapitellar joint - only with the forearm pronated
- Radial head diameter and capitellar width correlated with PIN distance
Surgical Approaches to the Radial Tunnel - Anatomic Comparison
- 30 fresh-frozen cadaveric specimens, 10 each of anterior, anterolateral and posterior approaches
- Anterior and anterolateral approaches best visualised the radial head bands, leash of Henry, ECRB origin and arcade of Frohse
- The posterior approach best exposed the distal border of supinator
- No single approach adequately visualised all five compression sites
Tendon Transfers for Irrecoverable Radial Nerve Palsy
- Pronator teres to ECRB restores wrist extension
- FCU (or FCR) to EDC restores finger MCP extension
- Palmaris longus to EPL restores independent thumb extension
- FCR-based (Boyes) variants preserve wrist flexion-extension balance