Failure of Digital Separation
- Simple: Skin only connection between digits.
- Complex: Bone, joint, or nail involvement.
- Complete: Web extends to fingertip.
- Incomplete: Partial webbing (proximal only).
- Border Digits (thumb-index, ring-small): Operate earlier (6-12 months) due to length inequality causing angular deformity.
- “3rd web space most commonly affected
- “Border digits need EARLIER surgery (6-12mo)
- “NEVER release both sides of digit at once
- “Full-thickness skin graft (usually groin)
- “Web creep is most common complication
Overview and Epidemiology
Syndactyly is failure of digital separation during embryological development, and is one of the two commonest congenital hand anomalies, alongside polydactyly. Be careful with the flat claim that it is the commonest. The ranking is population-dependent: polydactyly is markedly more frequent in populations of African descent, and the Italian multicentre series cited below found radial polydactyly first, with simple syndactyly close behind. "One of the two commonest, and the commonest in most European series" is the defensible form.
Who and where. The incidence is about 1 in 2,000 live births, with a 2:1 male predominance, and 50% of cases are bilateral. The third web space, between the long and ring fingers, is the one most often affected; the embryology below explains why.
Associated syndromes. Syndactyly is part of several syndromes, and the hand pattern sits alongside features elsewhere in the body:
- Syndactyly Pattern
- Complex, complete - 'mitten hand'
- Other Key Features
- Craniosynostosis, midface hypoplasia
- Syndactyly Pattern
- Simple, often symbrachydactyly
- Other Key Features
- Absent pec major, chest wall anomaly
- Syndactyly Pattern
- Variable syndactyly
- Other Key Features
- Craniosynostosis, polydactyly
- Syndactyly Pattern
- Hands and feet
- Other Key Features
- Craniosynostosis, broad thumbs/toes
Neurovascular Anatomy and Its Surgical Limits
The single most important point of operative anatomy, and a stock viva follow-up, is that the neurovascular bifurcation in a syndactylised web sits more distally than normal. It dictates how deep a commissure can safely be created.
The artery. The common digital artery divides into the two proper digital arteries more distally than normal, sometimes distal to the level of the desired web commissure. The web may then not be deepened to the normal level without dividing one proper digital artery. If so, ligate one branch, since the digit survives on its other proper artery, or stage the release.
The nerve. The digital nerve also divides distally, usually a little distal to the artery, but it can be split more proximally by interfascicular microdissection. The nerve is therefore rarely the limiting structure; the artery is.
The rule that follows. Each separated digit ends up perfused by a single proper digital artery on its newly raw side. That is the anatomical reason both borders of one digit are never released in the same stage.
In theatre. In complete syndactyly always assume the supply is aberrant. Identify the bifurcation early, and if it is too distal, choose between accepting a slightly shallower commissure, ligating one branch, or staging. Never dissect blindly proximally through the artery.
Pathophysiology
Normal separation. The limb buds appear as paddle-shaped structures at 4-5 weeks of gestation, and the digital rays become visible within the hand plate at week 6. Between weeks 6 and 8 the interdigital mesenchyme is removed by programmed cell death (apoptosis), and by week 8 the digits are fully separated with distinct web spaces. Syndactyly is the failure of that apoptosis.
The signals. Three pathways govern patterning and interdigital cell death:
- Sonic Hedgehog (SHH) - regulates anterior-posterior patterning
- WNT signalling - controls apoptosis of the interdigital tissue
- Bone morphogenetic proteins (BMPs) - trigger interdigital cell death
Simple and complex. In simple syndactyly only the soft-tissue apoptosis fails, so skin and subcutaneous tissue stay connected over a normally developed skeleton. Complex syndactyly reflects a more severe embryological disruption, with abnormal skeletal patterning in addition to the soft tissue, and may involve delta phalanges and shared joints.
Genetics. Syndactyly can be sporadic or autosomal dominant. Isolated syndactyly is often autosomal dominant with variable penetrance, and the simple type is often familial. Syndromic syndactyly is linked to specific genes: FGFR2 in Apert and in syndromic complex syndactyly, TWIST1 in Saethre-Chotzen. Environmental factors are rarely implicated.
Why the third web. The long and ring rays, the third and fourth, separate last, in weeks 7-8, which leaves a longer window for developmental disruption. The first web, between thumb and index, separates earliest and is the least commonly affected.
Classification
Every syndactyly is described on two axes: the tissue that joins the digits, and how far the web extends. The descriptions combine, so a web is, for example, simple and complete.
By tissue.
- Simple - skin and subcutaneous tissue only, with no bony involvement, separate nail folds and normal skeletal anatomy on X-ray. The most common type, at 70-80%. Surgery is straightforward and function excellent.
- Complex - a bony connection between the digits, with shared joints or abnormal skeletal elements, and the nails may be shared or abnormal. Separation requires osteotomy, and function is good but may need revision.
- Complicated - complex features plus accessory phalanges and multiple deformities, often with a syndromic association. The most challenging surgical reconstruction.
By extent. A complete web reaches the fingertip at nail level and involves the entire length of the digit, so it requires nail fold reconstruction and more skin graft. An incomplete web is partial and proximal only, with the distal digits separate, and is easier to reconstruct with less graft.
The combinations. A simple complete web is a full skin web with no bone involvement. A complex incomplete web is a partial web with bone fusion, and a complex complete web is a full web with shared bones and nails.

Clinical Assessment
History. The questions that matter:
- Family history - autosomal dominant inheritance in some forms
- Pregnancy - teratogen exposure, maternal diabetes
- Syndromic features - head shape, chest wall, other anomalies
- Function - grip and fine motor development
Examination. Inspect the web, then the digits, then function, and look beyond the hand:
- Complete or incomplete - does the web reach the fingertip, and which web spaces are affected?
- Simple or complex - palpate for a bony connection; a shared nail suggests the complex type
- The digits - length discrepancy, rotation, and angular deformity, especially where border digits are involved
- Function - active movement, independent flexion and extension, grip patterns, and opposition if the thumb is involved
- Skin quality and scars
- Other anomalies - in the hand (polydactyly, camptodactyly) and syndromic features of the head, chest and feet
Investigations
Radiographs are essential for surgical planning. They show the bony anatomy, identify shared or fused bones, define the joints and detect accessory phalanges. The appearance by type:
- X-ray Appearance
- Normal bony anatomy
- X-ray Appearance
- Shared phalanges, delta phalanx
- X-ray Appearance
- Accessory bones, abnormal joints
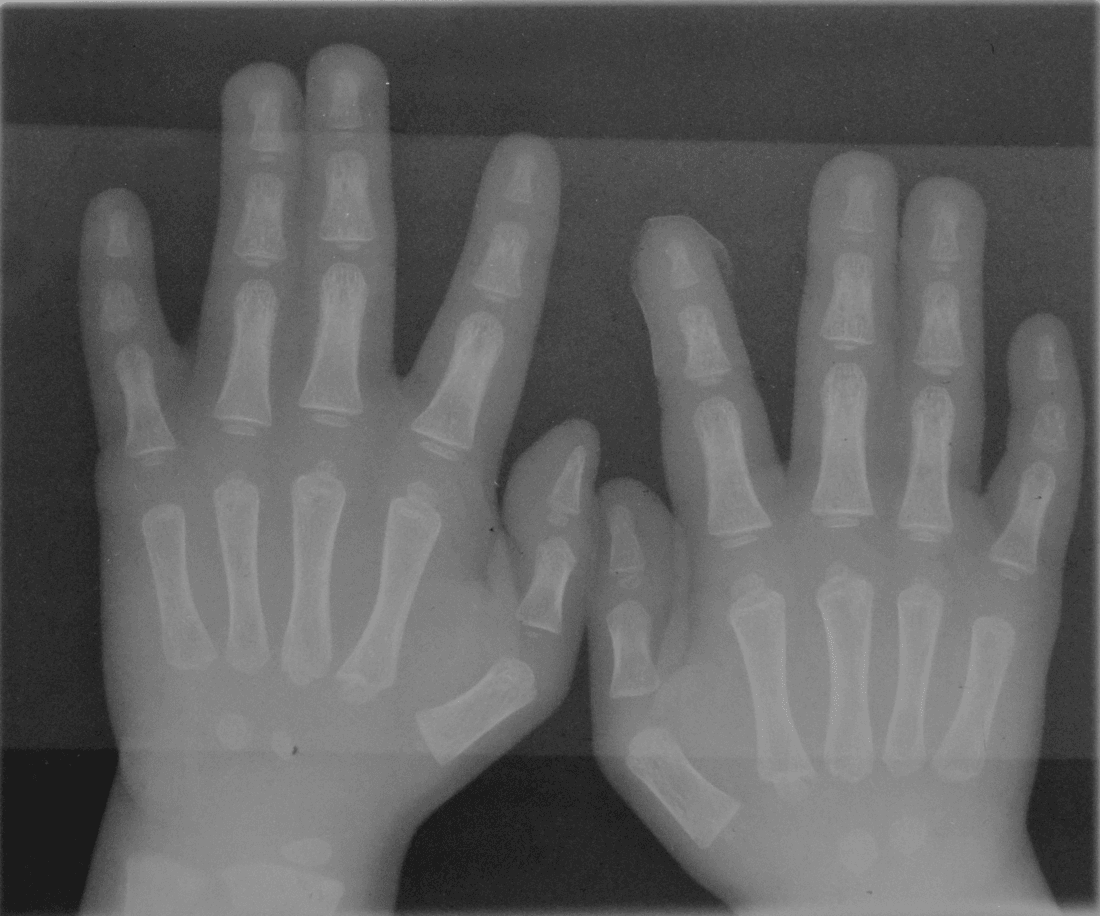
Further investigation is for selected children:
- Genetic testing - if there are syndromic features (Apert, Poland)
- Cardiac echo - for the cardiac anomalies associated with syndromes
- CT or MRI - rarely needed, complex cases only
Differential diagnosis. Not every pair of digits held together is true syndactyly. Distinguish these on examination and radiograph.
- Key Distinguishing Feature
- Failure of separation, digits otherwise formed
- Web / Skeletal Pattern
- Soft-tissue or bony web; digits of near-normal length
- Key Distinguishing Feature
- Short, hypoplastic or absent digits with nail nubbins
- Web / Skeletal Pattern
- Webbing PLUS deficiency; often unilateral, Poland-associated
- Key Distinguishing Feature
- Syndactyly WITH an extra (often central) digit
- Web / Skeletal Pattern
- Web plus duplicated ray, 3rd/4th web region
- Key Distinguishing Feature
- Distal fusion with proximal sinus/fenestration, amniotic bands
- Web / Skeletal Pattern
- Fenestrated web, near-normal proximal commissure, tip fusion
- Key Distinguishing Feature
- Central ray deficiency creating a cleft
- Web / Skeletal Pattern
- Transverse web of border digits flanking a central defect
- Key Distinguishing Feature
- Fixed PIP flexion of a SINGLE digit, no fusion
- Web / Skeletal Pattern
- No web abnormality
Management
Border digits: 6-12 months. Where the thumb and index or the ring and small fingers are joined, release comes earlier, at 6-12 months. The two digits differ in length, so the shorter is tethered by the longer and bends towards it, and delayed surgery leaves a permanent angular deformity. The first web is also critical for thumb function.
Central digits: 12-18 months. Index-long and long-ring webs are released at the standard 12-18 months. The digits are of similar length, so the deformity risk is lower, the larger digits are easier to operate on, and the release still precedes the critical period of fine motor development. Whether central webs should go earlier is discussed under Controversies.
When releasing syndactyly in multiple adjacent web spaces, never release both sides of a digit at the same time. This compromises blood supply and can cause digital necrosis. Stage the surgery 3-6 months apart.
Complex and syndromic hands. These may need earlier intervention, and are often reconstructed in multiple staged procedures.
Apert syndrome has complex, complete syndactyly, often described as a "mitten hand" or "spade hand". Surgery is challenging because of the shared bony structures and the number of digits involved. It requires staged procedures, often 4-5 operations, although the Salazard series below averaged six per child. Coordinate with the craniofacial team for concurrent craniosynostosis management.
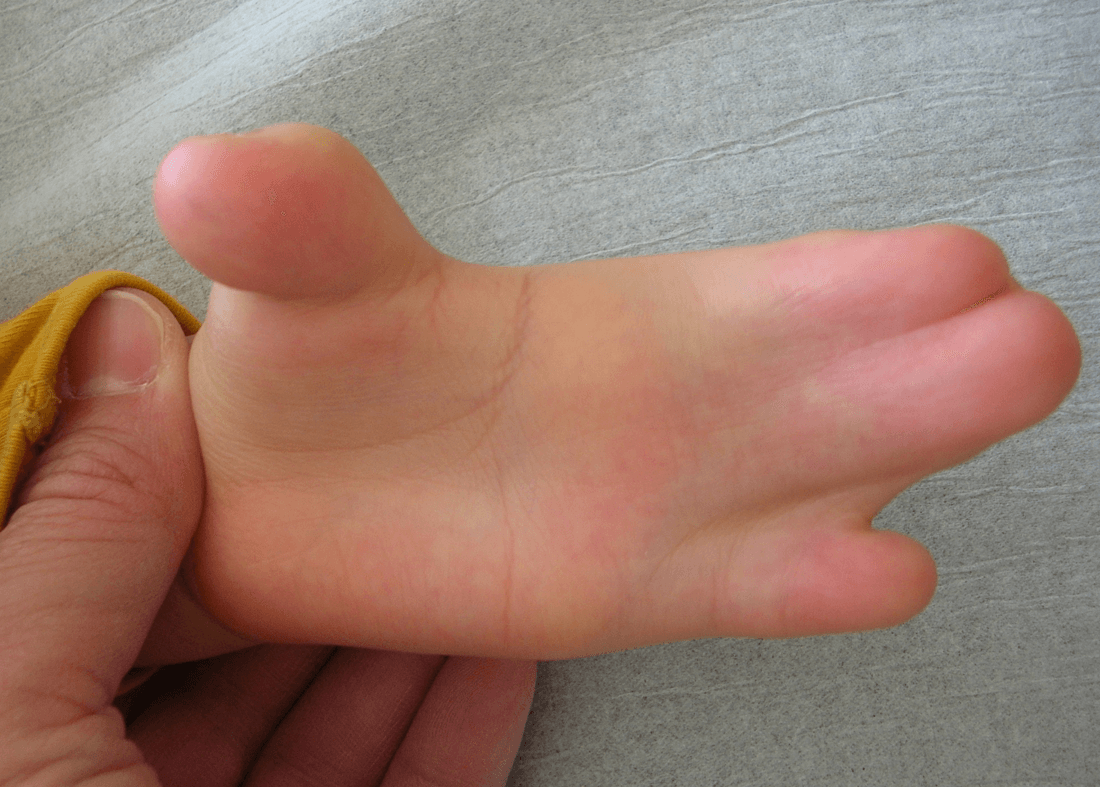
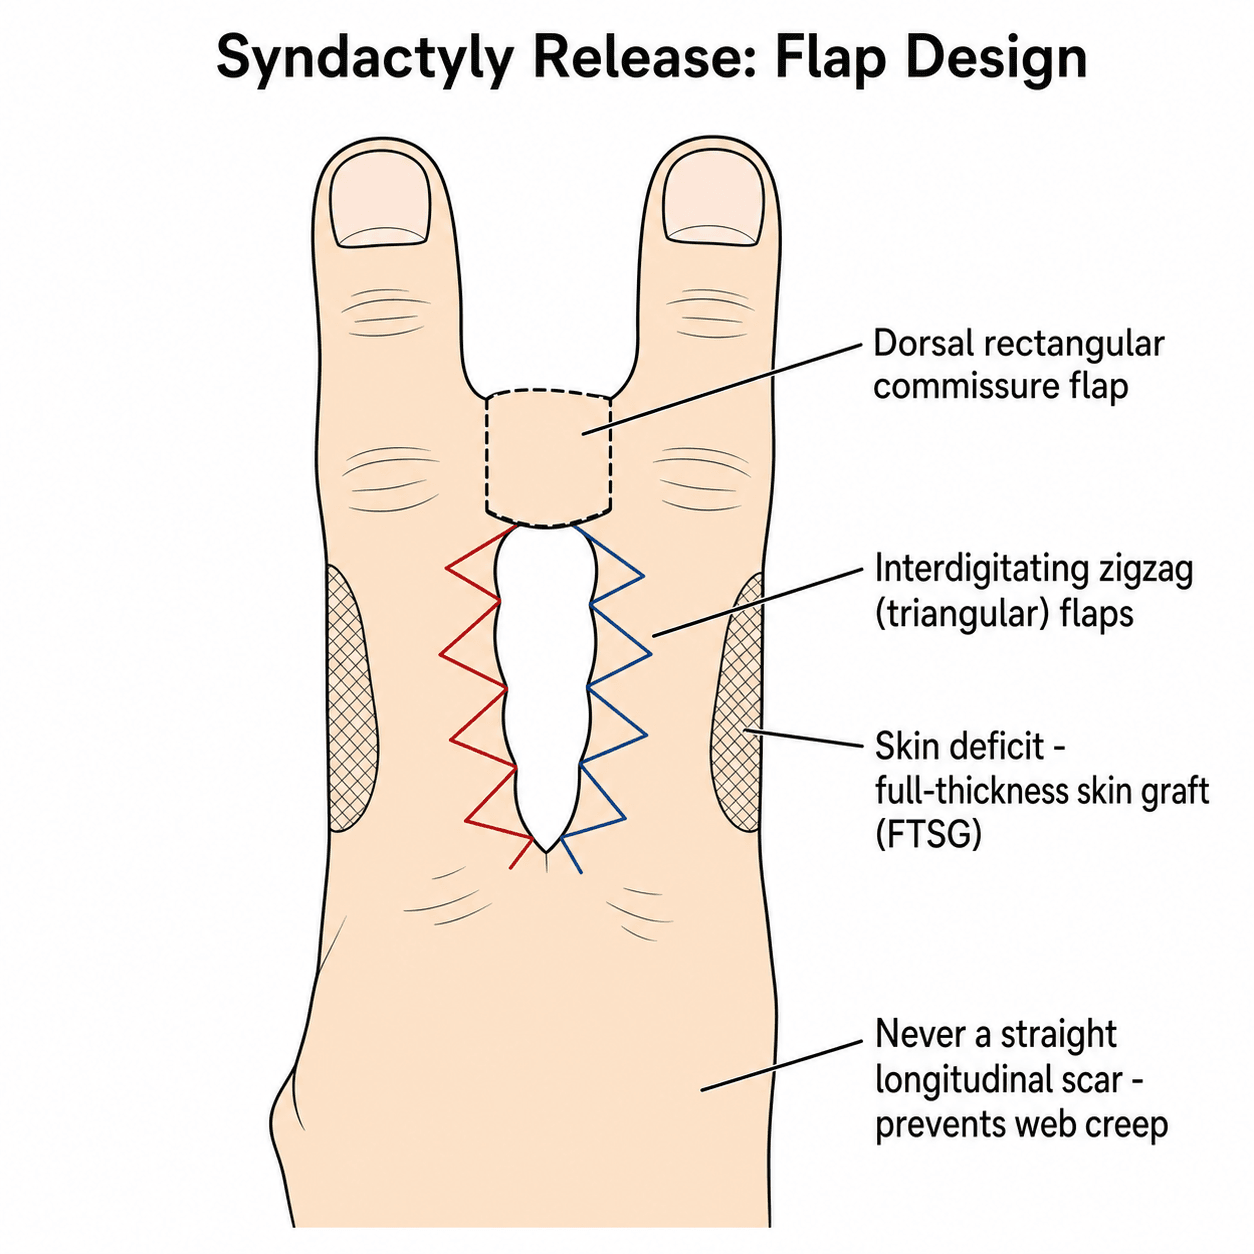
The incisions. The digits are separated along zigzag interdigitating flaps, which prevent the linear scar contracture that a straight incision would produce. Preserve the digital neurovascular bundles throughout, remembering that the arteries may be aberrant.
The commissure. A wide-based dorsal rectangular advancement flap recreates the commissure at the correct level. It avoids web creep, the distal migration of the web.
The graft. Full-thickness skin graft (FTSG) covers what the flaps cannot, and is required for most complete syndactyly. The usual donor site is the groin crease, which gives the best colour match and a hidden scar; the hypothenar eminence and antecubital fossa are alternatives. Why a graft is needed at all is set out in the next section.
Complex syndactyly adds osteotomy for bony separation and nail fold reconstruction, and may need bone graft.
Technical points. Design the flaps adequately and close without excessive tension, with adequate graft, since tension-free coverage limits web creep. Meticulous technique prevents web creep and graft loss.
Postoperative care. Protection first, then scar management, then surveillance through growth:
- Bulky dressing with the digits separated
- Forearm-to-fingertip splint
- Elevation for 48-72 hours
- Monitor perfusion
- Dressing change at 7-10 days, with a graft check
- Splint continued for 3-4 weeks
- Hand therapy for scar management, with silicone or pressure garments
- Web spacers at night for 6-12 months
- Regular review until skeletal maturity, watching for web creep
- Growth may require revision
The Skin Deficit: Why a Graft Is Needed
A favourite "explain the principle" question: why can a conjoined web almost never simply be sewn back as two digits?
The geometry. Two separated digits present a far greater combined skin circumference than the flat, fused mass they came from. Separating them therefore creates an obligatory skin shortfall: there is not enough skin to wrap both digits and line the new commissure.
What the flaps do. The dorsal commissure flap, rectangular or hourglass, resurfaces the new web at the correct level. The interdigitating zigzag flaps resurface part of each digit while breaking up the scar line. The residual raw areas, typically on the mid-lateral sides of the digits, are covered with full-thickness skin graft.
Why extent matters. A narrow incomplete web has a small deficit that local and dorsal flaps can cover alone. A complete, and especially a complex, web has a large deficit that still generally needs FTSG for tension-free closure, so graft-free, flap-only closure is realistic only for simple incomplete webs.
Complications
Early. The early problems and their causes:
- Vascular compromise - from releasing both sides of a digit
- Flap necrosis - tension, poor design
- Graft failure - infection, haematoma, a poor bed
- Infection - the standard surgical risk
Web creep is the most common complication, at 10-20%. The commissure migrates distally, developing over months to years as a result of an inadequate flap or graft, and may need revision surgery.
Scar contracture is what linear scars do, and the zigzag design prevents it. It may need Z-plasty revision, and hand therapy is important.
Angular deformity follows delayed surgery on border digits. Early surgery prevents it; once established it may need corrective osteotomy.
Revision surgery is indicated for:
- Significant web creep
- Scar contracture limiting function
- Angular deformity
- Nail deformity
- Growth-related changes
Guidelines, Registries & Global Practice
Global Epidemiology
- Syndactyly is among the most common congenital hand anomalies worldwide, with widely quoted figures around 1 in 2,000-3,000 live births (population estimates vary with ascertainment).
- Registry data place overall congenital hand/upper-limb malformation incidence at roughly 1-3 per 10,000 live births, with simple syndactyly consistently among the top anomalies after radial polydactyly.
- Male predominance and a slight right-side preponderance are reported across populations.
- Around 10-20% of hand-anomaly cohorts carry a syndromic association, so every case warrants a screen for dysmorphic, craniofacial, chest-wall and lower-limb features.
Society Guidance Compared
Syndactyly is managed by surgical principle rather than by a single binding national guideline; the table below summarises how the major bodies frame care.
- Emphasis
- Function-led timing and staged release
- Practical Position
- Border digits earlier; never release both sides of one digit in a single stage
- Emphasis
- Paediatric hand MDT pathways
- Practical Position
- Referral to specialist paediatric hand units; FTSG remains standard for complete webs
- Emphasis
- Technique variation and graft-sparing flaps
- Practical Position
- Increasing use of dorsal commissure flaps to reduce or avoid grafting in simple cases
- Emphasis
- Standardised nomenclature
- Practical Position
- Oberg-Manske-Tonkin (OMT) classification adopted to harmonise reporting of malformations
Registry & Classification Notes
- Modern reporting uses the IFSSH-endorsed Oberg-Manske-Tonkin (OMT) classification, which frames syndactyly within malformations of hand-plate formation/differentiation, replacing purely descriptive systems for research and audit.
- The Withey score is the most widely used outcome instrument for grading post-release web creep, scar and digital deformity, allowing cross-centre comparison.
- No implant is involved, so there is no arthroplasty-style registry; epidemiology relies on birth-defect surveillance programmes (e.g. EUROCAT in Europe) and national hand-surgery audits.
High- vs Limited-Resource Practice Variation
- High-resource settings: elective staged release at specialist paediatric hand units, full-thickness grafting or graft-sparing dorsal flaps, formal hand therapy, silicone and night web-spacers, and longitudinal follow-up to skeletal maturity.
- Limited-resource settings: later presentation is common, raising rates of fixed angular deformity in border digits and reducing the window for graft-free techniques; single-stage, graft-minimising approaches and visiting/charitable surgical teams play a larger role.
- Universal principles (resource-independent): zigzag interdigitating incisions, a dorsal flap to recreate the commissure at the correct level, never releasing both borders of one digit simultaneously, and tension-free coverage to limit web creep.
Controversies & Areas of Uncertainty
The traditional teaching is well established, but several points remain genuinely debated and are favourite viva discriminators.
How early is too early? Tradition releases central digits at 12-18 months, and some advocate earlier release for psychosocial or parental reasons. Comparative data suggest that releasing central webs under 1 year may worsen cosmetic (Withey) scores. The consensus is border digits early, central digits not rushed below 12 months.
Is a graft always needed? Dorsal commissure or V-Y flaps can avoid grafting in simple incomplete webs, sparing donor-site morbidity and graft-related creep, while complete and complex webs still generally need it. Skin substitutes such as dermal matrices are an evolving option, not standard.
Toes: operate at all? Webbing of the second and third toes is very common, usually simple and incomplete, and often a familial trait considered a normal variant in many families. It causes no functional impairment, and "webbed toes" are generally accepted. Surgery is rarely required, and the indication is cosmetic. Release carries a high recurrence, up to about 28%, which rises if surgery is after age 2, and satisfaction is modest. Many units counsel against routine surgery, and surgery is only for the patient who strongly desires it.
Self-Assessment Quiz
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“6-month-old infant presents with complete simple syndactyly between thumb and index finger. What is your management?”
“10-month-old with complete simple syndactyly involving 2nd, 3rd, and 4th web spaces bilaterally. Parents want all corrected. How do you approach this?”
“Infant with Apert syndrome presents with complex complete syndactyly of all digits ('mitten hand'). Parents ask about treatment options and prognosis. How do you counsel them?”
CLASSIFICATION
- Simple: Skin only connection
- Complex: Bone/joint/nail involved
- Complete: Web to fingertip
- Incomplete: Partial proximal web
- 3rd web space most common
TIMING
- BORDER (thumb-index, ring-small): 6-12 months
- CENTRAL (index-long, long-ring): 12-18 months
- NEVER release both sides of digit at once
- Stage multiple webs 3-6 months apart
SURGICAL TECHNIQUE
- Zigzag interdigitating incisions
- Dorsal rectangular flap for commissure
- Full-thickness skin graft (groin)
- Complex: osteotomy + nail reconstruction
COMPLICATIONS
- WEB CREEP: Most common (10-20%)
- Scar contracture
- Vascular compromise (both sides released)
- Angular deformity (delayed border surgery)
- Nail deformity (complex type)
ASSOCIATED SYNDROMES
- APERT: Mitten hand + craniosynostosis
- POLAND: Symbrachydactyly + absent pec major
- CARPENTER: Craniosynostosis + polydactyly
- PFEIFFER: Broad thumbs/toes + craniosynostosis
Evidence Base
Kurebayashi L et al
- 34 patients (51 commissures) graded blindly by 3 surgeons using the Withey score
- Children operated under 1 year had a WORSE mean Withey score (5.83) than those over 1 year (3.94), p=0.011
- Higher Withey score reflects more web creep and scar/rotational deformity
- Suggests very early release (under 12 months) of central webs may not improve cosmesis
Grahn PM et al
- 26 consecutive children, 39 web reconstructions at a median age of 20 months (11-43), using a hexagonal dorsal skin flap with straight midline incisions closed at the mid-lateral lines
- The case mix matters: 30 simple, 4 complex and 5 complicated syndactylies, and 18 of the simple ones were INCOMPLETE - so the graftless result rests substantially on the easier end of the spectrum
- Inguinal skin grafts were needed in only 2 children, both with complex or complicated syndactyly
- One child had a SELF-INDUCED bilateral postoperative infection that led to web creep; two developed hypertrophic scars that responded to silicone
- Mean parental cosmetic VAS 87 (45-100) and functional VAS 92 (63-100) at mean follow-up 1.3 years (0.5-3.7)
Hsu VM et al
- 28 syndactylies (25 simple incomplete, 3 simple complete) released with a modified V-Y dorsal metacarpal flap WITHOUT skin graft
- Mean follow-up 4.2 years; only 2 patients (7.1%) had complications, both corrected by revision
- Eliminates donor-site morbidity and graft-related web creep in selected cases
- Authors restrict the graftless technique primarily to simple incomplete syndactyly
- Mean operative time 68 minutes; all cases performed by a single senior surgeon between 1998 and 2007
Langlais T et al
- 68 toe syndactylies in 38 patients, operated 2008-2017, mean follow-up 6.9 years (2.8-11.2); mean age at first surgery was 3.9 years (0.8-16.7) - this is a LATE-OPERATED cohort
- Recurrence in 18 syndactylies (28.1 per cent) affecting 14 patients; surgery after age 2 was the only independent risk factor on both univariate and multivariate analysis (p=0.02)
- Complications in 7 syndactylies (11.7 per cent): six keloids (9.4 per cent) and one scar retraction, each requiring a further procedure; African ethnicity was a risk factor for keloid (4 of 15, p=0.02)
- Mean Withey score 4.9 (1-11) and mean OxAFQ-C 52 of 60; overall 67 per cent would repeat the surgery and 69 per cent were satisfied
- COUNTERINTUITIVELY, patients with SIMPLE syndactyly were LESS satisfied than those with complex or complicated disease (p=0.02) - only about half of the simple group would repeat it
Senes FM et al
- A RETROSPECTIVE pooling of reports from eight Italian paediatric hand-surgery centres for 2010-2015 - not a population registry: 765 children with hand and upper-limb malformations among 3,100,421 live births
- Overall malformation incidence 2.5 per 10,000 live births, with male and right-side predominance
- Radial polydactyly was the commonest anomaly, closely followed by simple syndactyly, symbrachydactyly and complex syndactyly
- Inheritance or familial predisposition in 25 cases; 84 children had syndromes related to the hand anomaly
- THE AUTHORS THEMSELVES CONCLUDE that the Italian incidence is LOWER than that registered in other countries, and attribute this to the retrospective design and to defects that never reach a hand surgeon
Salazard B & Casanova D
- 16 Apert hands treated with early staged surgery (mean 6 operations per child)
- First-web opening, digital separation, thumb realignment and clinodactyly correction performed
- Upton classification used to select first-web technique (dorsal hand flap in severe stages)
- Nine hands had four fingers and seven had five; there was ALWAYS bilateral opposition and symphalangism, sparing only the fifth finger
- Web revision required in 16 per cent; all children achieved a rudimentary but functional pinch grip
- The authors close on the ceiling, not the success: THE FUNCTIONAL PROGNOSIS IS DARKENED BY SYMPHALANGISM - the stiff interphalangeal joints are not correctable by soft-tissue surgery and set the limit on what any reconstruction can achieve
Upton J
- Defined the widely used Upton classification of Apert hand anomalies (types I-III)
- Detailed pathologic anatomy of upper-limb anomalies in Apert syndrome
- Links severity of complex syndactyly to thumb and metacarpal involvement
- Guides the sequence and technique of staged reconstruction
Flatt AE
- Classic reference text on congenital hand surgery
- Codified simple/complex and complete/incomplete descriptive terminology
- Established core surgical principles: zigzag flaps, dorsal commissure flap, FTSG
- Foundation for the modern staged approach to syndactyly