Rare | T8-T12 Common | Cord at Risk | Anterior Approach Preferred
- Rare pathology - only 0.25-0.75% of all symptomatic disc herniations
- Lower thoracic predominance - 75% occur at T8-T12 where relatively more motion
- Myelopathy is primary concern - narrow canal, cord cannot be retracted
- Posterior laminectomy CONTRAINDICATED for central discs - high paraplegia risk
- Anterior/anterolateral approaches for central discs - transthoracic or thoracoscopic; costotransversectomy is a posterolateral route
- Artery of Adamkiewicz at T9-L2 (usually left) - major blood supply to cord
- “40-70% of thoracic discs are calcified (complicates surgical removal)
- “Central disc from posterior = catastrophic cord injury
- “Many thoracic discs asymptomatic (incidental MRI findings)
- “Transthoracic approach provides best visualisation but requires thoracotomy
Overview and Epidemiology
Thoracic disc herniation is rare, accounting for only 0.25-0.75% of all symptomatic disc herniations (Arce and Dohrmann 1985, PMID 3975822). The rib cage makes the thoracic spine inherently stable and protects its discs from the degenerative change common in the cervical and lumbar regions. When a thoracic disc does herniate, the narrow canal and the closeness of the spinal cord make both diagnosis and treatment difficult.
History. Mixter and Barr described the first surgical treatment in 1934. Early posterior decompressive laminectomy gave poor results, only 57% success against over 80% for the posterolateral, lateral and transthoracic approaches (Arce and Dohrmann 1985, PMID 3975822). The anterior and anterolateral approaches pioneered in the 1960s to 1980s define the modern era, and outcomes have improved significantly with proper approach selection.
Who and where. Symptomatic herniations requiring surgery are estimated at about 1 per 1,000,000 population a year (Stillerman et al 1998, PMID 9525706). Presentation peaks in the fourth to sixth decades, with a slight male predominance of about 1.5:1. 75% occur at T8-T12 in the lower thoracic spine and 25% at T1-T7.
Why the lower thoracic spine. The lower thoracic spine moves relatively more than the upper. Its anatomy is transitional as it approaches the thoracolumbar junction, the rib cage constrains it less, mechanical stress concentrates at the change from kyphosis to lordosis, and it carries greater axial load than the upper thoracic spine.
In the landmark MRI study of asymptomatic individuals by Wood and colleagues, 73% had at least one positive anatomical finding, including disc herniation in 37%, disc bulge in 53% and cord deformation in 29% (Wood et al 1995, PMID 7593072). These are radiological abnormalities. Not every thoracic disc herniation is symptomatic or needs treatment, and clinical correlation is essential.
Associated conditions. Four conditions are associated with thoracic disc disease:
- Scheuermann's disease may predispose to thoracic disc degeneration
- Ankylosing spondylitis brings an increased fracture risk but also disc disease
- Degenerative scoliosis produces asymmetric loading
- Trauma can cause an acute herniation, which is rare but possible with a high-energy mechanism
Anatomy and Biomechanics
The canal. The thoracic canal is the narrowest region of the vertebral column, 12-14mm in diameter at its narrowest point, T5-T8, around a cord of 8-10mm. The cord fills 40-50% of the canal, against 25% in the cervical spine; the lumbar canal holds the cauda equina. The CSF space dorsally is limited, so the cord lies close to the posterior elements.
In the cervical spine ample CSF allows safe posterior retraction of the cord. In the thoracic spine there is minimal CSF dorsally, and attempting to retract the cord causes direct mechanical injury and vascular compromise, leading to irreversible paraplegia. This is the fundamental reason posterior laminectomy is contraindicated for central thoracic discs, and the most important exam point in the topic.
The artery of Adamkiewicz. The arteria radicularis magna is the largest anterior segmental medullary artery, supplying the lower two-thirds of the spinal cord through the anterior spinal artery (standard anatomical teaching). Damaging it causes an anterior spinal artery syndrome with paraplegia, so segmental vessels at these levels are ligated with care. Some surgeons obtain preoperative CT angiography to identify it, though this is not routine.
- Details
- T9-L2 in 80% of population (range T5-L4)
- Details
- Left side in 75-80% of cases
- Details
- T9-T11
- Details
- Lower thoracic and lumbosacral cord segments
- Details
- Injury causes anterior spinal artery syndrome (paraplegia, loss of pain/temperature, preserved proprioception)
The disc. Thoracic discs are thinner than lumbar discs, 5-7mm high against 10-12mm, less mobile because of the rib cage, and have a smaller nucleus pulposus relative to the annulus. They are more prone to calcification with age: 65% of surgical cases were calcified in Stillerman's series (Stillerman et al 1998, PMID 9525706).
Biomechanics. The thoracic spine is stabilised by:
- The rib cage articulations, costovertebral and costotransverse
- Longer spinous processes in a shingled arrangement
- Coronal facets, which limit rotation and allow lateral flexion
- The kyphosis, which loads the anterior column
Motion is relatively limited in the upper and mid thoracic spine, 2-4 degrees per level, and increases towards the thoracolumbar junction to 6-8 degrees at T11-T12.
Pathophysiology
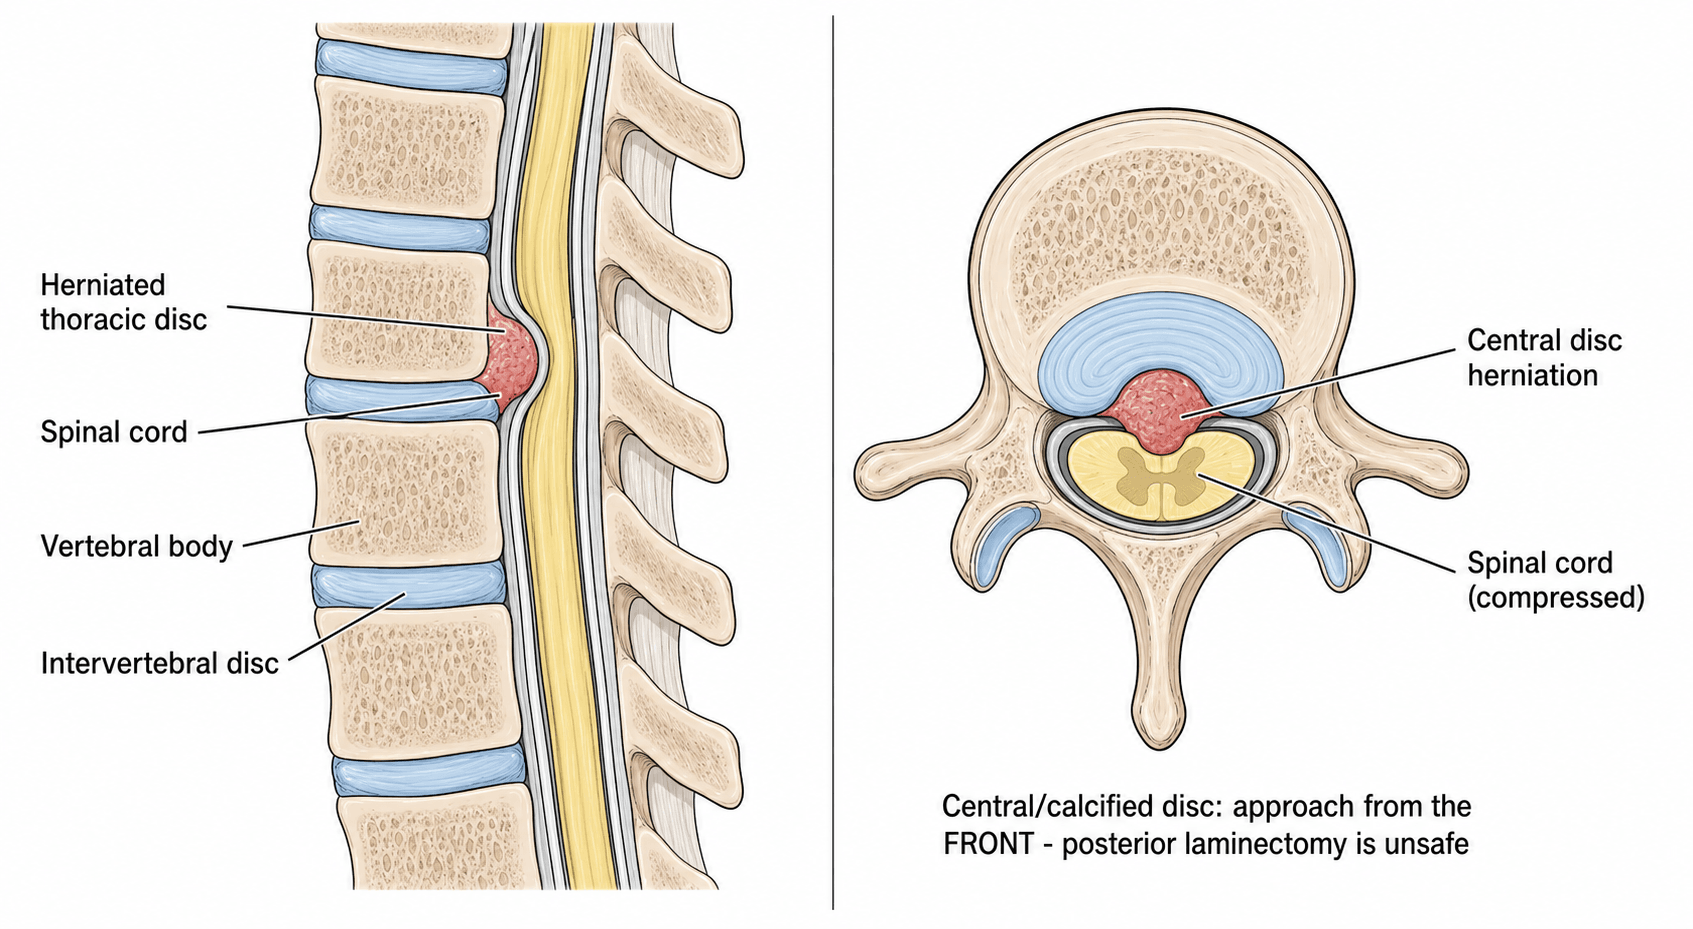
Where the disc goes. A thoracic disc herniates centrally, centrolaterally or laterally into the foramen, and the location decides both the syndrome and the approach (see Classification). A giant herniation is a rare variant with extensive canal compromise.
Calcification. Thoracic disc pathology differs from the lumbar disc, where extrusion through the posterior annulus is common. Thoracic discs undergo dystrophic calcification more often than cervical or lumbar discs; lower metabolic activity and vascularity, chronic mechanical stress with minimal motion (repetitive microtrauma), age-related degeneration with calcium deposited in the nucleus and annulus, and the association with Scheuermann's disease, whose endplate irregularities promote degeneration, are the reasons given.
Why calcification matters. A calcified disc behaves like bone at surgery and cannot be removed with rongeurs or curettes, so it needs a high-speed burr (see Surgical Approaches), and its removal carries an increased risk of dural tear and cord injury. With high-energy trauma a calcified disc may act as a missile and cause an acute traumatic herniation.
How the cord is injured. The disc flattens the cord against the posterior canal by direct mechanical compression, and compresses the anterior spinal or radicular arteries. Cord oedema is reversible in its early stages; chronic compression leads to myelomalacia, necrosis of the cord, which is irreversible.
Compared with the cervical and lumbar spine. The thoracic cord is a tight fit with no CSF buffer, so it tolerates compression worst of the three, and the thoracic disc calcifies most often.
- Cervical
- Cord with space
- Thoracic
- Cord (tight fit)
- Lumbar
- Cauda equina (nerve roots)
- Cervical
- Moderate (CSF buffer)
- Thoracic
- Poor (no buffer)
- Lumbar
- Good (roots mobile)
- Cervical
- Often safe
- Thoracic
- CONTRAINDICATED
- Lumbar
- Standard approach
- Cervical
- 10-20%
- Thoracic
- 40-70%
- Lumbar
- 5-10%
A giant thoracic disc occupies more than roughly 40 percent of the canal and is usually heavily calcified. A chronic calcified disc can erode through the ventral dura into the subarachnoid space, a transdural (intradural) herniation, reported in around 5-10 percent of operative series and much more common with giant calcified discs.
On CT or CT-myelography look for intradural gas and the "comet-tail" sign with discontinuity of the ventral dura. MRI shows the herniation tracking intradurally, with loss of the dural plane against the disc.
The dural defect is already present, so anticipate and plan for a durotomy and dural reconstruction: primary repair, patch or graft, dural sealant, often a lumbar CSF drain. CSF-leak rates are high, and an unrecognised defect leads to a persistent fistula or pseudomeningocele.
Manage these anteriorly with planned dural repair and never blunt-avulse an adherent calcified disc off the cord, which tears cord and dura. Burr the eggshell, and if a thin shell remains densely adherent to the dura, leaving it is acceptable provided the cord is decompressed.
Classification Systems
Location is the most clinically relevant classification. It determines the surgical approach and predicts outcome.
- Definition
- Midline, posterior central canal
- Frequency
- 20-30%
- Clinical Features
- Myelopathy, bilateral findings, no radiculopathy
- Preferred Approach
- Anterior only (transthoracic, thoracoscopic)
- Definition
- Paracentral, eccentric
- Frequency
- 60-70%
- Clinical Features
- Myelopathy plus radiculopathy, most common
- Preferred Approach
- Anterior or posterolateral
- Definition
- Far lateral, in or beyond foramen
- Frequency
- 10-15%
- Clinical Features
- Radiculopathy only, no myelopathy
- Preferred Approach
- Posterolateral safe (transpedicular, lateral extracavitary)
Clinical Presentation
Thoracic disc herniation presents as one of three syndromes: myelopathy, radiculopathy, or axial pain alone.
Myelopathy (50-70% of symptomatic cases). Progressive cord compression produces an upper motor neuron pattern:
- Lower limb weakness with spasticity
- A spastic, wide-based, scissoring gait
- A sensory level at or below the level of the herniation
- Hyperreflexia below the level of the lesion and a positive Babinski sign
- Loss of the abdominal reflexes at the level of compression
- Bowel and bladder dysfunction (urgency, frequency, retention), a late finding
An eccentric disc that compresses one side of the cord may cause a Brown-Séquard (hemicord) syndrome. Motor weakness (corticospinal tract) and loss of proprioception and vibration (dorsal columns) are ipsilateral; loss of pain and temperature is contralateral, because the spinothalamic tract crosses. This is classic exam material for thoracic spine pathology.
Radiculopathy (25-40%). Thoracic radicular pain is band-like, running around the chest or abdomen in the distribution of the intercostal nerve, and worse with coughing, sneezing and Valsalva, which raise intraspinal pressure. It mimics visceral pathology, cardiac chest pain or abdominal conditions such as pancreatitis and cholecystitis. Thoracic dermatomes are less distinct than limb dermatomes, so there is no classic dermatomal pattern, though there may be hypoaesthesia or hyperaesthesia in the thoracic dermatome.
Axial pain alone (10-20%). Chronic midline thoracic back pain with a mechanical pattern, worse with activity and better with rest. It may be the only symptom for years and often delays the diagnosis.
Natural history. Without treatment, a substantial proportion of established myelopathic cases progress to more severe deficit. Worsening is gradual, over months to years, and acute deterioration is rare but possible, especially with a traumatic herniation. Once myelopathy develops, spontaneous improvement is uncommon.
Examination. The neurological examination finds the level and the tracts involved, the functional assessment sets the baseline against which surgery is judged, and the red flags decide the urgency.
- Motor - lower limb strength (hip flexion, knee extension, ankle dorsiflexion and plantarflexion), spasticity (increased tone, clonus) and gait (spastic or ataxic patterns)
- Sensory - pinprick and light touch to find the sensory level; proprioception and vibration for dorsal column function; temperature, often lost with pain in spinothalamic dysfunction
- Reflexes - lower limb hyperreflexia below the lesion; pathological reflexes (Babinski, and Hoffmann's if there is cervical involvement); abdominal reflexes (T8-T12), which may be absent at the level of the lesion
Investigations
MRI is the diagnostic modality of choice. It shows the herniation, whether protrusion or extrusion; the cord compression, as flattening or displacement of the cord; any cord signal change; whether the disc is central, centrolateral or lateral; and whether one level or several are involved.
- Purpose
- Assess cord signal, CSF, disc
- Key Findings
- Disc appears dark, cord compression visible, T2 hyperintensity in cord indicates oedema/myelomalacia
- Purpose
- Determine herniation location
- Key Findings
- Central vs centrolateral vs lateral classification
- Purpose
- Anatomical detail
- Key Findings
- Disc-cord relationship, vertebral body marrow
- Purpose
- Rule out tumour, infection
- Key Findings
- Enhancement suggests neoplasm or infection vs bland disc
Cord signal change on T2-weighted MRI has prognostic significance, and helps counsel patients on expected recovery and surgical urgency.
- No signal change - better surgical outcomes, more reversible compression
- Faint or mild hyperintensity - cord oedema, still potentially reversible
- Intense hyperintensity - myelomalacia (cord necrosis), poor prognosis, likely permanent deficit
CT is essential for surgical planning. It is indicated in all operative candidates to assess calcification, when MRI is contraindicated (pacemaker, claustrophobia), and as CT myelography with water-soluble contrast via lumbar puncture if MRI is not available. It shows calcification as high-density material and its extent, which decides burr against rongeur; pedicle size for a transpedicular approach; and whether ossification is OPLL or calcified disc.
Plain radiographs have limited value and are not diagnostic, but may raise suspicion in the appropriate clinical context. They may show disc space narrowing, a calcified disc on the lateral view (pathognomonic when present), Scheuermann's changes (irregular endplates, Schmorl's nodes) and the overall alignment, kyphosis or scoliosis.
Electrodiagnostics. Somatosensory evoked potentials establish a preoperative baseline of cord function; their use in theatre, with motor evoked potentials, is covered under Surgical Approaches. EMG and nerve conduction studies have a limited role in thoracic radiculopathy, because the intercostal muscles are difficult to study, but may help exclude a peripheral nerve lesion.
Other causes of thoracic myelopathy and pain. Tumour, infection, demyelination and dural arteriovenous fistula are separated by the investigations in the table. For a metabolic cause, check B12, copper and vitamin E levels.
- Distinguishing Features
- Insidious myelopathy or band-like radicular pain; often calcified
- Key Investigation
- MRI (cord compression) + CT (calcification)
- Distinguishing Features
- Known malignancy, constitutional symptoms, rapid progression, night pain
- Key Investigation
- Whole-spine MRI with contrast, staging
- Distinguishing Features
- Fever, raised CRP/ESR, immunosuppression, IVDU
- Key Investigation
- MRI with contrast, CRP/ESR, blood cultures
- Distinguishing Features
- Myelopathy, dense ossification, no disc extrusion
- Key Investigation
- CT (ossification) + MRI
- Distinguishing Features
- Younger, relapsing course, longitudinally extensive cord signal
- Key Investigation
- Brain + cord MRI, CSF oligoclonal bands
- Distinguishing Features
- Stepwise myelopathy, lower-limb claudication, flow voids on MRI
- Key Investigation
- Spinal MRI/MRA, spinal angiography
- Distinguishing Features
- Band-like chest/abdominal pain without neurology; pain pattern atypical for spine
- Key Investigation
- ECG/troponin, abdominal imaging as indicated
Management
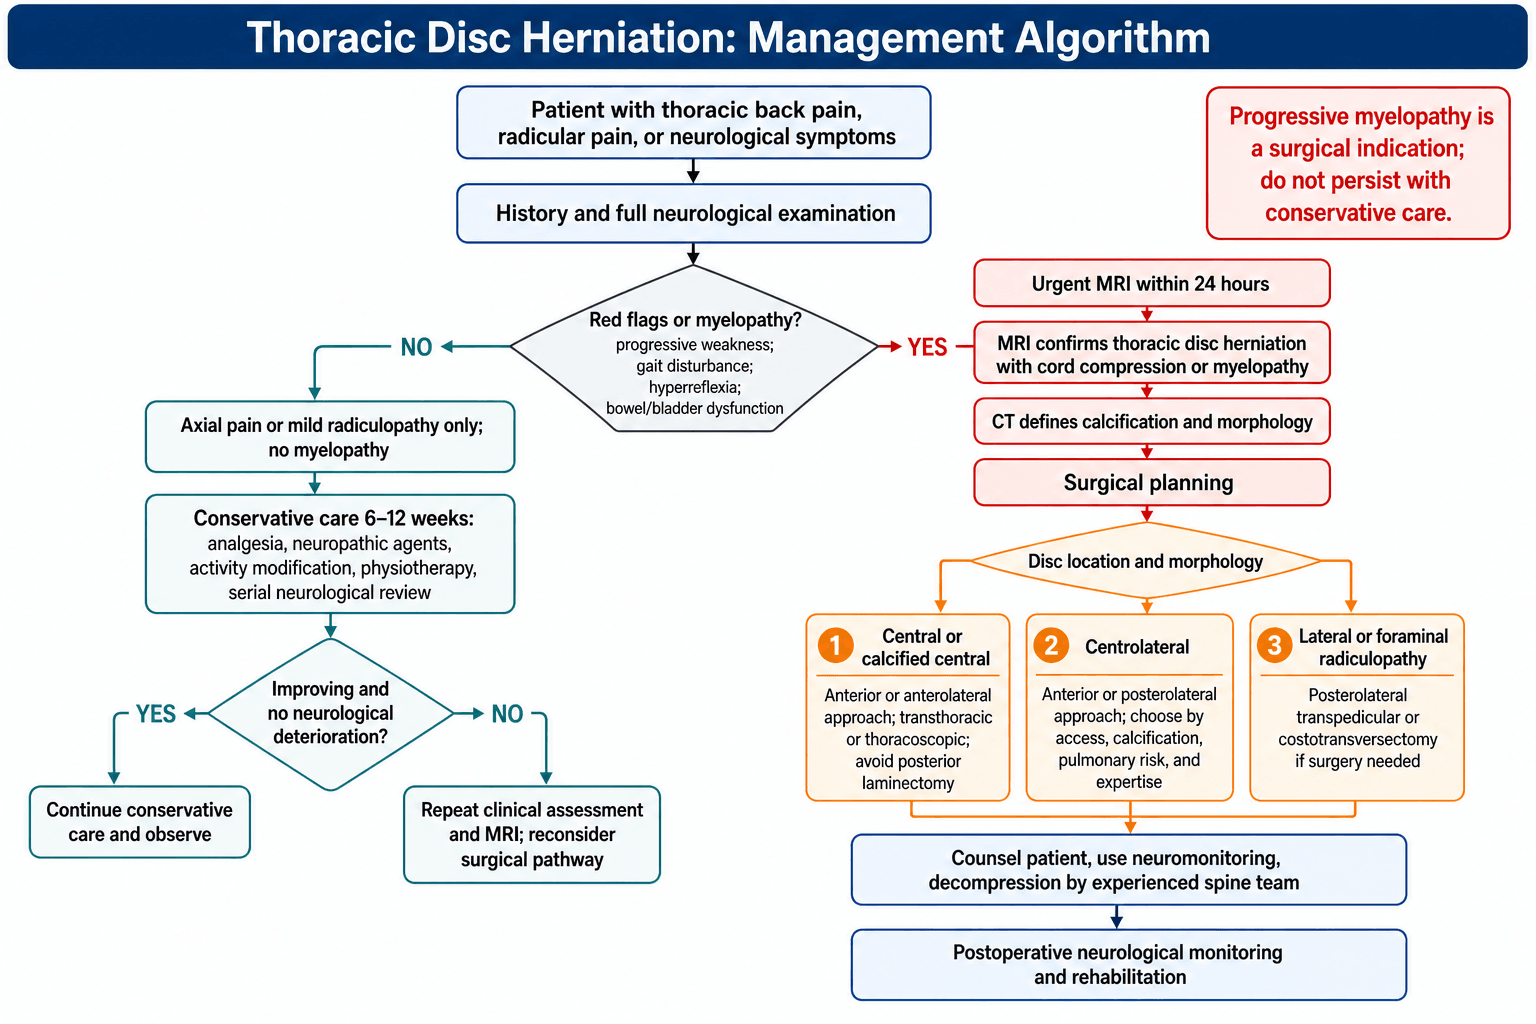
The decision. Management turns on whether the cord is threatened. Red flags (progressive weakness, myelopathy, bowel or bladder dysfunction) call for an urgent MRI; when it confirms a herniation with myelopathy, a CT for calcification follows, and the approach is chosen by disc location. Radiculopathy or axial pain alone gets a conservative trial of 6-12 weeks, and worsening or developing myelopathy during it means a repeat MRI and reconsideration of surgery.
Conservative management is indicated for:
- Mild radiculopathy without motor weakness
- Axial pain only, with no neurological deficit
- An asymptomatic incidental finding
- Medical comorbidities that preclude surgery
- Patient preference after informed discussion
The protocol:
- Analgesia - NSAIDs, paracetamol, neuropathic agents (gabapentin, pregabalin)
- Activity modification - avoid provocative activities, ergonomic adjustments
- Physiotherapy - core strengthening, posture training, with a limited role in thoracic disc
- Monitoring - serial neurological examinations, MRI if worsening
Many patients with mild radiculopathy or axial pain and no myelopathy improve with conservative care. It is abandoned for:
- Development of myelopathy
- Progressive motor weakness
- Bowel or bladder dysfunction
- Intractable pain despite optimal management
Progressive myelopathy from thoracic disc herniation is a surgical indication. Some mild cervical myelopathy may stabilise, but the thoracic canal is narrow with less compensatory capacity, and delaying surgery risks irreversible cord damage. Do not attempt prolonged conservative management in the presence of myelopathy.
Surgical Approaches
The gold standard for calcified central discs, indicated for central and centrolateral herniations because it gives the best view of the disc-cord interface.
- Lateral decubitus, affected side up
- Posterolateral thoracotomy at the rib corresponding to the disc (for example the 9th rib for a T8-T9 disc)
- Single lung ventilation, deflating the ipsilateral lung for exposure
- Resect the rib and divide the intercostal muscles
- Enter the pleural cavity and pack the lung anteriorly
- Identify the level by counting ribs and confirm it with an intraoperative radiograph
- Dissect the parietal pleura to expose the vertebral bodies and identify the disc space
- Ligate the segmental vessels at the disc level, beware the artery of Adamkiewicz
- Remove the disc and the posterior longitudinal ligament, and all herniated material until the cord is decompressed
- Consider corpectomy and a cage if the removal is extensive (optional fusion)
- Close in layers over a chest tube
It gives excellent visualisation and direct access to the disc without cord manipulation, and a calcified disc can be removed safely. The price is a thoracotomy, with post-thoracotomy pain, the pulmonary complications of single lung ventilation, a possible need for cardiothoracic assistance, and a longer hospital stay.
- Use a high-speed diamond burr, which produces less heat than a cutting burr
- Thin the posterior shell of the calcified disc first, like an eggshell
- Remove the fragments through the thinned shell with micro-rongeurs
- Avoid levering against the cord, which causes direct injury
- Irrigate copiously while burring to reduce heat
- Monitor SSEPs and MEPs throughout to detect early cord ischaemia
Intraoperative neuromonitoring. Every thoracic disc operation should have SSEPs, as a baseline and continuously, to detect cord ischaemia, and MEPs, which are more sensitive than SSEPs to motor pathway injury and guide safe decompression. The alarm criteria are a 50% fall in amplitude or a 10% rise in latency. The response is to stop manipulation, increase the MAP and consider aborting.
Operating on the wrong level is the classic, catastrophic medicolegal pitfall unique to the thoracic spine. It is the commonest region for wrong-level spine surgery, and counting ribs alone is not enough.
The thoracic spine is a long, featureless segment with no reliable intra-operative landmark, and the cord-compressing disc is often not palpable. Anatomical variants defeat simple counting: a transitional thoracolumbar vertebra or a cervical or lumbar rib changes the number of rib-bearing vertebrae and throws off any rib count.
- Before surgery, count levels on a whole-spine or long-cassette MRI from a fixed reliable landmark, both down from C2 and up from the sacrum/L5, reconcile the two counts, and document any anomalous ribs or transitional vertebra
- In theatre, rib counting under fluoroscopy is unreliable in isolation; use a true AP and lateral fluoroscopic count referenced to a fixed landmark with a radio-opaque marker
- For a difficult level the most reliable safeguard is a CT-guided percutaneous marker placed the day of or before surgery: methylene blue, a fiducial or coil, a marker screw, or a small dab of vertebroplasty cement at the target pedicle
- Document the imaging-confirmed level in the notes, and hold a surgical time-out before incision and again before the discectomy
Complications
The rates differ by approach, and the table sets them side by side.
- Transthoracic
- 5-10%
- Thoracoscopic
- 5-8%
- Costotransversectomy
- 10-15%
- Transthoracic
- 15-20%
- Thoracoscopic
- 10-15%
- Costotransversectomy
- Less than 5%
- Transthoracic
- 5-10%
- Thoracoscopic
- 5-8%
- Costotransversectomy
- Less than 5%
- Transthoracic
- 2-5%
- Thoracoscopic
- 2-4%
- Costotransversectomy
- Less than 2%
- Transthoracic
- 20-30%
- Thoracoscopic
- 10-15%
- Costotransversectomy
- 5-10%
Neurological deterioration (5-15%). Paraplegia is the most feared complication, and myelopathy may worsen through cord manipulation or ischaemia. The mechanisms are direct cord injury, vascular injury to the artery of Adamkiewicz and spinal cord ischaemia. Prevention means avoiding cord retraction, neuromonitoring, gentle technique and an anterior approach for a central disc; high-dose steroids are controversial, and management is supportive care and rehabilitation.
Pulmonary complications (10-20% across the open and thoracoscopic transthoracic approaches). Pneumothorax from inadequate chest tube drainage, pleural effusion from post-thoracotomy inflammation, pneumonia from single lung ventilation and atelectasis, and a prolonged air leak from pleural space problems. Chest physiotherapy, incentive spirometry and adequate chest tube management are the prevention; treatment is chest tube management, antibiotics for pneumonia and supportive care.
CSF leak and dural tear (5-10%). Incidental durotomy happens especially during calcified disc removal and can lead to a CSF fistula, a persistent leak through the wound, or a pseudomeningocele. Careful dural dissection and burring away from the dura are the prevention. Repair primarily if identified, oversewing with 6-0 Prolene; consider a lumbar drain if the leak persists, and revision surgery if a pseudomeningocele is symptomatic.
Vascular injury (2-5%). Injury to the artery of Adamkiewicz causes an anterior spinal artery syndrome with paraplegia; segmental artery injury causes bleeding and cord ischaemia; aortic injury is rare but catastrophic in anterior approaches. Preoperative identification of the artery by CT angiography, careful vessel ligation and maintaining MAP during surgery are the prevention. Control the bleeding, consult vascular surgery for a major vessel, and give supportive care for cord ischaemia.
Chronic post-thoracotomy pain affects 20-30% of patients after an open transthoracic approach. It is intercostal neuralgia from rib retraction and nerve injury, and it can be severe and persistent enough to affect quality of life. Counsel patients preoperatively and consider a thoracoscopic approach to reduce the risk. Manage it with neuropathic pain medication, nerve blocks, and pain clinic referral if severe.
Minor complications include:
- Wound infection (2-5%), superficial or deep - antibiotics or debridement
- Seroma - a fluid collection, usually self-limiting
- Intercostal neuralgia - rib retraction injury, chronic pain
- Horner's syndrome - sympathetic chain injury in the upper thoracic spine, with ptosis, miosis and anhidrosis
- Chylothorax - thoracic duct injury in left-sided approaches above T6, with milky chest tube output; conservative management or ligation
Complications of not operating. Non-operative management has its own list:
- Progressive myelopathy (25-50%), and delayed surgery may have worse outcomes
- Irreversible cord damage - myelomalacia from prolonged compression
- Chronic pain - persistent radiculopathy or axial pain
- Functional decline - loss of ambulation, wheelchair dependence
Postoperative Care and Outcomes
Rehabilitation. Three phases carry the patient from mobility to full activity:
- Weeks 0-6 - pain control, wound healing and basic mobility through walking, gentle range of motion and respiratory exercises; no lifting over 5kg, no twisting, no strenuous activity
- Weeks 6-12 - restore function and strength with progressive resistance training, core strengthening and balance; lifting increases gradually and high-impact activities are avoided
- Weeks 12 onwards - return to full activities, work and sport with sport-specific training, unrestricted activities as tolerated, and monitoring by serial neurological examination and functional outcome measures
- Description
- Japanese Orthopaedic Association thoracic myelopathy score (0-11)
- Use
- Myelopathy severity and improvement
- Description
- 0-5 scale of myelopathy
- Use
- Simple grading system
- Description
- Visual Analogue Scale for pain (0-10)
- Use
- Pain assessment
- Description
- Oswestry Disability Index
- Use
- Functional limitation
- Description
- Quality of life measure
- Use
- General health status
Results. In systematic reviews and case series (see Evidence Base: Stillerman et al 1998, Quint et al 2011, Brotis et al 2019, Hamid et al 2023), 60-80% improve or stabilise after surgery, 15-20% are unchanged and 5-10% worsen.
Prognostic factors. Each factor has a better and a worse end:
- Symptom duration - under 12 months does better than over 24 months, and long-standing myelopathy over 24 months does worse
- Cord signal - no preoperative T2 signal change does better; myelomalacia on MRI predicts poor recovery
- Age - under 60 years does better, over 70 years worse
- Disc - a soft disc does better; calcified discs are more difficult, with a higher complication rate
- Location - lateral does better; central discs are more challenging, with worse outcomes
- Severity and health - severe preoperative deficit (non-ambulatory, Nurick grade 4-5) and multiple medical comorbidities do worse
- Immediately, decompression relieves the mechanical pressure
- Over weeks to months, cord oedema resolves and early motor return begins
- At 6-12 months, improvement continues (cord remyelination)
- At 12-18 months, recovery plateaus
Counsel patients that maximum recovery takes 12-18 months. Early postoperative neurological status may not reflect the final outcome, and therapy and rehabilitation continue throughout.
Return to activities. Typical milestones:
- Desk work at 6-8 weeks, sooner after a minimally invasive approach
- Manual labour at 12-16 weeks
- Contact sport at 6 months, after full recovery and rehabilitation
- Driving at 4-6 weeks, when off opioids and able to perform an emergency stop
Guidelines, Registries & Global Practice
Global Epidemiology
- Figure
- 0.25-0.75%
- Source
- Arce & Dohrmann, Surg Neurol 1985 (PMID 3975822)
- Figure
- Approximately 1 per 1,000,000 per year
- Source
- Stillerman et al, J Neurosurg 1998 (PMID 9525706)
- Figure
- 4th decade
- Source
- Arce & Dohrmann 1985 (PMID 3975822)
- Figure
- 75% below T8
- Source
- Arce & Dohrmann 1985 (PMID 3975822)
- Figure
- Approximately 65%
- Source
- Stillerman et al 1998 (PMID 9525706)
- Figure
- 37%
- Source
- Wood et al, JBJS Am 1995 (PMID 7593072)
Guidance and Consensus, Side by Side
There is no high-level randomised guideline for this rare condition; practice is driven by case series, meta-analyses, and society/spine-unit consensus. The points where bodies genuinely converge or differ:
- Position
- Posterior decompressive laminectomy is contraindicated for central/calcified discs; favour anterior or posterolateral routes
- Evidence base
- Level IV series; laminectomy 57% vs over 80% success (PMID 3975822)
- Position
- All approaches acceptable; posterolateral carries lower medical/surgical morbidity than anterior/lateral
- Evidence base
- Level III, 1036 patients (PMID 31493617)
- Position
- Thoracoscopic microdiscectomy is a safe alternative to open thoracotomy for soft centrolateral discs in experienced units
- Evidence base
- Level IV, 167 cases (PMID 22160099)
- Position
- Lower-morbidity posterolateral option for centrolateral discs
- Evidence base
- Level III, 328 patients (PMID 37475044)
- Position
- Progressive thoracic myelopathy warrants urgent specialist referral and decompression; observation reserved for radiculopathy/axial pain without cord compromise
- Evidence base
- Consensus / Level IV
Registry Evidence
National joint registries (NJR, AJRR, AOANJRR, SHAR) do not capture thoracic discectomy, and no dedicated thoracic disc registry exists, reflecting the rarity of the condition. The best pooled evidence is therefore from systematic reviews and network meta-analyses rather than registry data: surgery carries minimal mortality but overall morbidity up to 29%, with approach-specific differences (PMID 31493617).
Global Practice Variation
- High-resource settings: Care concentrated in tertiary/quaternary spine units with intraoperative neuromonitoring (SSEPs/MEPs); growing use of thoracoscopic and tubular minimally invasive approaches; cardiothoracic collaboration for transthoracic exposure.
- Limited-resource settings: Open transthoracic or costotransversectomy predominate where thoracoscopic equipment and neuromonitoring are unavailable; later presentation with established myelopathy is more common, worsening prognosis.
- Regional preference: Endoscopic spine techniques have been adopted earliest and most widely in parts of Asia, while open and tubular posterolateral approaches remain standard in many Western units.
- Perioperative care (universal principles): Single-shot antibiotic prophylaxis at induction (e.g. cefazolin), mechanical and chemical VTE prophylaxis, neuropathic agents (gabapentin/pregabalin) for radicular pain, and structured rehabilitation for myelopathic patients. Outcomes converge internationally at 60-80% neurological improvement.
MCQ Practice Points
Q: Why is posterior laminectomy contraindicated for central thoracic disc herniation?
A: The thoracic spinal cord cannot be safely retracted. The thoracic canal is narrow (12-14mm diameter) with the cord occupying 40-50% of the space. There is minimal CSF dorsally. Attempting to access a central disc from behind requires retracting the cord posteriorly, which causes direct mechanical injury and vascular compromise resulting in irreversible paraplegia. In contrast, the cervical canal has more space (cord occupies only 25%) allowing safer posterior retraction. The lumbar spine has nerve roots (cauda equina) which can be retracted. This is the single most important concept in thoracic disc surgery.
Q: What is the artery of Adamkiewicz and why is it clinically important?
A: The arteria radicularis magna (artery of Adamkiewicz) is the largest anterior segmental medullary artery supplying the lower two-thirds of the spinal cord via the anterior spinal artery. It is located at T9-L2 in 80% of individuals, most commonly at T9-T11, and enters from the left side in 75-80%. Clinically, it's important because injury during thoracic surgery (especially when ligating segmental vessels during transthoracic approach or anterior spinal procedures) can cause anterior spinal artery syndrome with paraplegia, loss of pain and temperature sensation below the lesion, but preservation of proprioception (dorsal columns spared). Some surgeons obtain preoperative CT angiography to identify its location, though this is not routine.
Q: What imaging modality best assesses calcification in thoracic disc herniation and why is this important?
A: CT scan is the best modality for assessing disc calcification. 40-70% of symptomatic thoracic disc herniations are calcified, and this is critical surgical information because calcified discs behave like bone - they cannot be removed with standard rongeurs or curettes. The surgeon must use a high-speed diamond burr to carefully thin the posterior shell of the calcified disc (like an eggshell) and then remove fragments. This increases operative time, difficulty, and risk of dural tear and cord injury. Preoperative knowledge of calcification allows proper surgical planning and patient counseling about increased risks.
Q: What is the prognostic significance of T2 hyperintensity in the spinal cord on MRI?
A: T2 hyperintensity (increased signal) in the spinal cord indicates cord edema or myelomalacia:
- Mild/faint hyperintensity suggests cord edema which is potentially reversible with decompression
- Intense hyperintensity suggests myelomalacia (cord necrosis) which is irreversible
- Patients with no T2 signal change have better surgical outcomes
- Patients with myelomalacia have poor recovery potential - many deficits will be permanent despite adequate surgical decompression
This information helps counsel patients about realistic expectations. A patient with severe myelomalacia should understand that surgery prevents further deterioration but may not restore lost function.
Q: How do you select surgical approach for thoracic disc herniation?
- Central disc → Anterior approach mandatory (transthoracic, thoracoscopic) - posterior contraindicated
- Centrolateral disc → Anterior or posterolateral (transthoracic, costotransversectomy) - surgeon preference and patient factors
- Lateral/foraminal disc → Posterolateral acceptable (transpedicular, lateral extracavitary) - no need for thoracotomy
- Calcified disc → Anterior approach preferred (better visualization for burr work)
- COPD/pulmonary disease → Favor costotransversectomy or VATS over open thoracotomy
- Surgeon expertise → Thoracoscopic requires specialized training
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 55-year-old male presents with 6-month history of progressive lower limb weakness and gait dysfunction. MRI shows a central T10-T11 disc herniation with cord compression and T2 signal change. CT confirms the disc is heavily calcified. How would you manage this patient?”
“A 45-year-old female presents with 3-month history of band-like chest pain around the left T8 dermatome. No lower limb weakness. MRI shows a lateral T7-T8 disc herniation in the left foramen. How would you manage this?”
“A 60-year-old patient with significant COPD and FEV1 of 45% predicted has thoracic myelopathy from a centrolateral T9-T10 disc herniation. How do you approach surgical decision-making?”
Key Epidemiology
- 0.25-0.75% of all disc herniations (RARE)
- 75% occur at T8-T12 (lower thoracic)
- Peak age 4th-6th decades
- 40-70% are calcified (complicates surgery)
Critical Anatomy
- Narrow thoracic canal (12-14mm diameter)
- Cord occupies 40-50% of canal (vs 25% cervical)
- Limited CSF space dorsally
- Artery of Adamkiewicz at T9-L2 (usually LEFT)
Why Posterior is Contraindicated
- Cord CANNOT be safely retracted in thoracic spine
- Historical posterior laminectomy: only 57% success vs over 80% other approaches
- Central disc from posterior = PARAPLEGIA
- Must use anterior or anterolateral approach
Clinical Presentation
- Myelopathy 50-70%: weakness, spasticity, gait dysfunction
- Radiculopathy 25-40%: band-like chest/abdominal pain
- Axial pain 10-20%: chronic thoracic back pain
- T2 hyperintensity = myelomalacia (poor prognosis)
Investigations
- MRI: Diagnostic modality of choice
- CT: Essential for calcification assessment
- T2 signal change: Edema vs myelomalacia (prognosis)
- Neuromonitoring: SSEPs and MEPs intraoperatively
Approach Selection
- CENTRAL: Anterior only (transthoracic, VATS)
- CENTROLATERAL: Anterior or posterolateral (costotransversectomy)
- LATERAL: Posterolateral OK (transpedicular)
- Calcified disc: Anterior preferred (better visualization)
Transthoracic Approach
- Lateral decubitus, single lung ventilation
- Rib resection, enter pleural cavity
- Ligate segmental vessels (beware Adamkiewicz)
- Direct anterior disc access, burr for calcified disc
Calcified Disc Technique
- High-speed DIAMOND burr (reduces heat)
- Thin posterior shell like eggshell
- Remove fragments through thin shell
- Copious irrigation, NO levering against cord
Complications
- Neurological deterioration 5-15% (paraplegia worst)
- Pulmonary 10-20% (pneumothorax, effusion, pneumonia)
- CSF leak/dural tear 5-10%
- Chronic post-thoracotomy pain 20-30%
Outcomes
- 60-80% improve or stabilize
- Recovery takes 12-18 months (counsel patient)
- Better if: short duration, no T2 change, younger, soft disc
- Worse if: long-standing, myelomalacia, older, calcified
Viva Killer Points
- Posterior laminectomy for central disc = CONTRAINDICATED
- Why: Cord cannot be retracted (narrow canal)
- Adamkiewicz: T9-L2, LEFT side, anterior spinal artery supply
- Calcified disc (40-70%): CT essential, requires burr
Evidence Base
Arce and Dohrmann (1985)
- Review of 280 reported thoracic disc herniations with CT-improved diagnosis
- Peak incidence in the fourth decade; 75% of protruded discs occurred below T8
- Surgical success ranged from 57% for decompressive laminectomy to over 80% for posterolateral, lateral, and transthoracic approaches
- Favourable prognostic group: history of trauma, symptoms less than one month, soft disc
Stillerman et al (1998)
- Single-surgeon series of 82 herniated thoracic discs in 71 patients (1971-1995)
- Calcification present in 65%; intradural extension in 7%; multiple herniations in 14%
- Four approaches used: transthoracic (60%), transfacet pedicle-sparing (28%), lateral extracavitary (10%), transpedicular (2%)
- Postoperative improvement: pain 87%, spasticity 95%, sensory 84%, bladder 76%, motor 58%; overall complication rate 14.6%
Quint et al (2011)
- Prospective cohort of 167 consecutive single-level thoracoscopic microdiscectomies
- Mean VAS pain reduced by 4.4 points; ASIA motor score improved by mean 4.6 points
- At 2 years, 79% reported excellent/good pain outcome and 80% excellent/good motor outcome
- Overall complication rate 15.6%
Brotis et al (2019)
- Systematic review and network meta-analysis of 15 studies, 1036 patients
- Surgery carried minimal mortality (3 deaths) but overall morbidity as high as 29%
- Complications: medical 21%, surgical-site 11%, CSF-related 8%, neurological 5%
- Anterior and lateral approaches carried higher medical and surgical complication risk than the posterolateral approach
Hamid et al (2023)
- Systematic review and meta-analysis of the transfacet pedicle-sparing approach, 328 patients across 11 studies
- Significant improvement in VAS pain and Nurick myelopathy scores after surgery
- Pooled overall complication rate 12.4% with 3.5% neurological worsening
- Lower complication rates and shorter hospital stay than alternative approaches in selected patients
Wood et al (1995)
- MRI of 90 asymptomatic individuals to define the prevalence of incidental thoracic findings
- 73% had at least one positive anatomical finding
- Disc herniation in 37%, disc bulge in 53%, annular tear in 58%, cord deformation in 29%
- Findings represent radiological abnormalities only and require clinical correlation
- Some advocate leaving small calcified fragments vs complete removal
- Risk of incomplete decompression vs risk of cord injury during aggressive removal
- No high-quality comparative data
- Some surgeons perform fusion after extensive discectomy or corpectomy
- Others perform discectomy alone without fusion
- Thoracic spine stability from rib cage may allow discectomy without fusion
- No RCT data comparing outcomes
- Incidental thoracic disc herniations common on MRI
- No clear consensus on surveillance vs prophylactic surgery
- Generally observe unless developing symptoms