Coracoid Transfer | Anterior Instability | Glenoid Bone Loss
- Coracoid transfer creates a triple blocking effect: bone block, sling effect, and capsular repair
- Indicated when glenoid bone loss is greater than 25 percent (inverted pear) or off-track Hill-Sachs
- Latarjet uses two screws to fix the coracoid flush with the anteroinferior glenoid rim, not medial on the neck
- Complications: nerve injury (axillary, musculocutaneous), hardware issues, graft nonunion, recurrent instability
- Bristow-Latarjet is the gold standard for recurrent anterior instability with significant bone loss
- “Inverted pear glenoid = greater than 25 percent bone loss = operative (Latarjet)
- “Triple effect: bone block + conjoint tendon sling + inferior capsular shift
- “Musculocutaneous nerve lies 5-8 cm distal to coracoid tip — blunt dissection only
- “Recurrent dislocation after soft tissue repair alone + bone loss = Latarjet indication
Overview and Epidemiology
Coracoid transfer is the answer to a specific question, and the question is asked elsewhere. The condition is anterior shoulder instability; the lesion this operation does NOT address on its own is the Bankart, which is why a soft-tissue repair is the alternative when bone stock is adequate; and the measurement that decides between them is on glenoid bone loss in instability, read together with the humeral side - the Hill-Sachs lesion and its own operation, remplissage, since bipolar bone loss is assessed on the glenoid track rather than either defect alone. The nerve that makes the coracoid osteotomy consequential is the musculocutaneous, which enters coracobrachialis a few centimetres distal to the tip.
The burden. Anterior shoulder dislocation is the most common large joint dislocation, and recurrent instability develops in 50-90% of young athletes after a first dislocation. Glenoid bone loss is present in up to 70% of recurrent dislocators, and in approximately 20% of them the loss exceeds a quarter of the glenoid - the inverted pear glenoid, which is the group this operation is for.
What is asked. Examiners want the difference between the Bristow and the Latarjet, the indication for coracoid transfer rather than arthroscopic soft-tissue repair, and the procedure's specific complications.
Pathophysiology
Why a soft-tissue repair fails once the rim has gone. Anterior glenoid bone loss is a bony deficiency and cannot be overcome by soft-tissue repair alone. A deficient anteroinferior rim leaves the labrum and capsule with no stable anchor point, and the humeral head translates over the deficient rim even after a Bankart repair.
The critical threshold is loss of greater than 25% of the glenoid diameter, the inverted pear glenoid. Below it, arthroscopic Bankart repair has acceptable results; above it, coracoid transfer is indicated. An off-track Hill-Sachs lesion, an engaging lesion that crosses the glenoid track, is an additional indication even with lesser degrees of glenoid bone loss.
The inverted pear. A normal glenoid is wider inferiorly than superiorly, the shape of a pear. Once enough anteroinferior bone has gone the superior width equals or exceeds the inferior width and the pear inverts. The sign is a reliable indicator on imaging that arthroscopic Bankart repair alone will have unacceptably high failure rates.
The glenoid track. The track is the contact area of the humeral head on the glenoid through the arc of motion, and its width is approximately 84% of the glenoid width. A Hill-Sachs lesion that stays inside the track is on-track and does not engage; one whose width plus the bone defect exceeds the track is off-track, engages and dislocates.
The triple blocking effect. Patte's rationale for the operation, and the three mechanisms that explain why a coracoid transfer succeeds where a Bankart repair fails in bone loss:
- Bone block - the coracoid graft replaces the missing anterior-inferior glenoid bone
- Sling effect - the conjoint tendon crosses the anteroinferior glenoid as a dynamic sling when the arm is abducted and externally rotated
- Soft tissue repair - capsulolabral reattachment to the CA ligament remnant restores the labral bumper
- Normal
- Intact labral bumper, deep concavity
- With Bone Loss
- Flattened, deficient anteroinferior rim
- After Latarjet
- Restored by coracoid graft
- Normal
- Centred within glenoid fossa
- With Bone Loss
- Translates anteriorly over deficient rim
- After Latarjet
- Graft blocks translation, sling reinforces
- Normal
- Negative intra-articular pressure maintained
- With Bone Loss
- Lost with rim fracture/attrition
- After Latarjet
- Restored via capsular repair to CA ligament
- Normal
- Balanced rotator cuff and capsuloligamentous structures
- With Bone Loss
- Deficient AIGHL and labrum
- After Latarjet
- Conjoint tendon sling provides dynamic restraint in abduction-external rotation
Classification and Types
Three things get classified here: how much glenoid bone has gone, whether the Hill-Sachs lesion engages, and which version of the coracoid transfer is being described.
Bone loss is expressed as a percentage of the glenoid diameter, and the percentage carries the operation with it.
- Glenoid Morphology
- Normal pear shape
- Recommended Treatment
- Arthroscopic Bankart repair
- Rationale
- Soft tissue repair sufficient, low recurrence
- Glenoid Morphology
- Borderline — still pear-shaped
- Recommended Treatment
- Bankart + remplissage or Latarjet (debated)
- Rationale
- Consider patient factors: sport, contact, Hill-Sachs
- Glenoid Morphology
- Inverted pear
- Recommended Treatment
- Latarjet (gold standard)
- Rationale
- Bony reconstruction required; Bankart failure rate exceeds 30 percent
- Glenoid Morphology
- Severe deficiency
- Recommended Treatment
- Iliac crest bone graft (Eden-Hybinette) or distal tibial allograft
- Rationale
- Coracoid graft may be insufficient for massive defects
The 25 percent threshold is the most commonly cited critical value, though some authors argue for earlier intervention at 15-20 percent in high-risk patients.
Clinical Assessment
History. Establish the pattern of instability, what has already been done to the shoulder, and what the patient needs the arm to do. The answers that change management:
- Number of instability episodes, the mechanism, and whether this is a first dislocation or a recurrence
- Any previous Bankart repair or stabilisation, and what was done
- Functional demands: contact sport, overhead athlete, manual labourer
- Numbness or weakness after dislocation episodes
Examination. Confirm that the instability is anterior, then look for the findings that change the plan rather than confirm the diagnosis.
- Apprehension test - positive in anterior instability in abduction-external rotation
- Relocation test - apprehension relieved by a posteriorly directed force
- Load and shift - anterior and posterior translation, graded 0-3
- Beighton score - generalised ligamentous laxity; the hypermobile patient needs a different approach
- Rotator cuff assessment, to exclude concomitant cuff pathology
- Glenoid bone loss quantified as a percentage of the glenoid diameter on CT
- The Hill-Sachs lesion characterised: size, depth and location on MRI or CT, and whether it is on-track or off-track
- Coracoid size and bone quality assessed, which matters most in the older osteopenic patient, because a small or osteoporotic coracoid may not provide an adequate graft
- Axillary and musculocutaneous nerve function documented, establishing the baseline for any post-operative comparison
Choosing between a Bankart repair and a coracoid transfer. Recurrence is the arithmetic behind the threshold: arthroscopic Bankart repair is quoted at 5-15% in the shoulders selected for it, but once bone loss passes a quarter of the glenoid its failure rate exceeds 30%, against 1-5% after Latarjet. The lower edge of the borderline band is quoted variously as 13% and as 15%, and inside that band the decision turns on the patient rather than the percentage: contact or collision sport, an engaging Hill-Sachs lesion, and whether a soft-tissue repair has already failed.
- Arthroscopic Bankart
- Less than 15 percent (no inverted pear)
- Latarjet (Coracoid Transfer)
- Greater than 25 percent (inverted pear)
- Arthroscopic Bankart
- Non-engaging or small
- Latarjet (Coracoid Transfer)
- Off-track / engaging with bone loss
- Arthroscopic Bankart
- Primary repair
- Latarjet (Coracoid Transfer)
- Revision after failed Bankart
- Arthroscopic Bankart
- Low-demand, non-contact
- Latarjet (Coracoid Transfer)
- Contact/collision athlete, high demand
- Arthroscopic Bankart
- 5-15 percent
- Latarjet (Coracoid Transfer)
- 1-5 percent
- Voluntary dislocators
- Active infection
- Severe glenohumeral arthritis
- Inadequate coracoid bone stock, typically the elderly osteopenic patient
- Uncontrolled seizure disorder
Investigations
Radiographs first, and expect them to understate the problem. A true AP, an axillary, a Stryker notch and, where available, a Bernageau view. The Stryker notch shows the Hill-Sachs lesion, the axillary shows glenoid rim fracture or erosion, and hardware from prior surgery is looked for. Plain films underestimate glenoid bone loss compared with CT.
CT is mandatory for any patient being considered for a Latarjet. Thin-slice acquisition with three-dimensional reconstruction and an en-face (sagittal oblique) glenoid view. Measurement is by the best-fit circle method: a circle is fitted to the inferior glenoid rim, which is typically intact in anterior bone loss, and the missing anterior bone is expressed as a percentage of the circle diameter. An inverted pear, superior width greater than or equal to inferior width, confirms loss of greater than 25 percent.
Where the inverted pear can be looked for. Three-dimensional CT with a Bernageau view, the best-circle fit method on an AP or axillary radiograph, or MRI with sagittal oblique reconstructions.
MRI for what the CT does not show. Labrum, capsule, rotator cuff and articular cartilage: the Bankart lesion, labral tears, a HAGL, capsular volume and the dimensions of the Hill-Sachs. It is the study that finds the concomitant pathology to be planned for, and it is read alongside the CT rather than instead of it.
Management and Surgical Technique
What is being moved. The coracoid process gives attachment to the conjoint tendon (short head of biceps and coracobrachialis), to pectoralis minor and to the coracoacromial ligament. The transfer keeps the conjoint tendon attached to the graft, which is what makes the dynamic sling across the anteroinferior glenoid possible, and releases the other two.
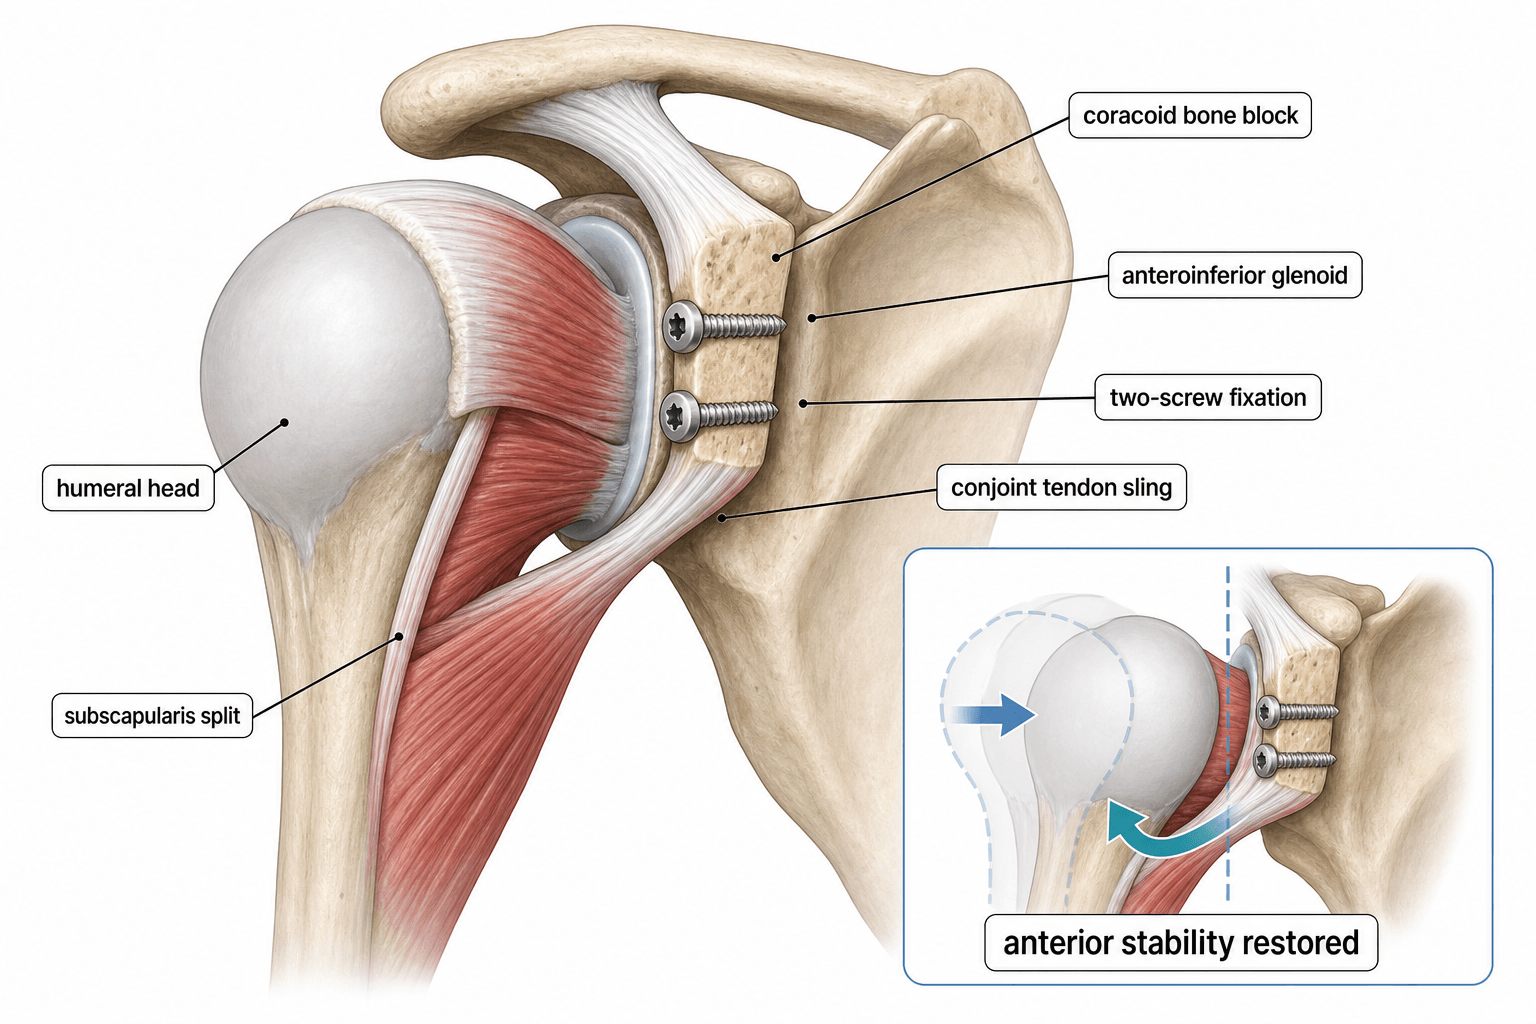
Positioning. Beach chair or lateral decubitus, with the arm free-draped so that range of motion can be assessed.
Surgical Steps
A standard deltopectoral interval, the cephalic vein retracted laterally with the deltoid, and the coracoid exposed from tip to base. Identify the coracoclavicular ligaments, trapezoid and conoid, because the osteotomy must be distal to them. Identify the axillary nerve inferiorly and the musculocutaneous nerve medially.
Release pectoralis minor sharply from the medial coracoid and the CA ligament sharply from the lateral coracoid, leaving a stump of CA ligament for the later capsular repair and preserving the conjoint tendon attachment laterally. Osteotomise the coracoid at its base with an oscillating saw or osteotome, just distal to the coracoclavicular ligaments; the graft is approximately 2.5-3 cm long. Decorticate the medial (deep) surface to expose cancellous bone and drill two parallel holes for the screws.
Retract the subscapularis, by split or tenotomy according to surgeon preference, and identify the glenoid rim and neck. Freshen the anterior glenoid neck to bleeding cancellous bone with a burr or curette. The graft should sit flush with the anteroinferior glenoid rim, extending from approximately the 2 to 5 o'clock position in a right shoulder, and must not overhang into the joint.
Two parallel cortical screws, typically 3.5 or 4.0 mm malleolar screws, aimed posteriorly and slightly superiorly. Bicortical fixation is ideal, and reduces the risk of the graft fracturing through the screw holes; palpate the posterior glenoid neck to confirm the screws have penetrated it without leaving prominent tips, and use intra-operative fluoroscopy to confirm graft position, screw length and the absence of a step-off. Then suture the capsule and the remaining CA ligament to the lateral aspect of the graft, recreating the labral bumper.
Repair the subscapularis: the upper and lower portions if a split was used, or with strong sutures through bone tunnels or anchors after a tenotomy. Close the deltopectoral interval loosely to prevent adhesions, and immobilise in a sling in internal rotation for 4-6 weeks.
Split or tenotomy. The modern standard is a horizontal split between the upper two-thirds and lower one-third of the subscapularis tendon, at the relatively avascular junction, with the coracoid graft passed through the split. It preserves the subscapularis attachment and function, and it carries the conjoint tendon through the lower subscapularis so that the sling acts precisely at the position of apprehension, abduction with external rotation.
What a tenotomy costs. An L-shaped or complete tenotomy gives wider exposure of the glenoid, but it has to be repaired and it risks subscapularis insufficiency, fatty infiltration and weakness: a positive belly-press or lift-off test afterwards, and potential loss of internal-rotation power.
Medial placement of the graft on the glenoid neck is the most common technical error. It does not restore the articular arc and may leave the shoulder unstable. A graft set too laterally, overhanging into the joint, causes early osteoarthritis.
Complications
The price of the operation. The overall complication rate is approximately 15-30%, and most of what goes wrong involves the graft or the metal holding it.
- Incidence
- 5-15 percent
- Risk Factors
- Poor fixation, medial placement, smoking, osteopenia
- Management
- Most asymptomatic; revise if unstable
- Incidence
- Up to 30 percent partial at 1 year
- Risk Factors
- Screw prominence, biological factors
- Management
- Monitor with CT; revise if instability recurs
- Incidence
- 2-10 percent
- Risk Factors
- Small graft, screw holes weakening, early mobilisation
- Management
- Hardware removal if symptomatic; revision graft if unstable
- Incidence
- 1-5 percent
- Risk Factors
- Medial graft placement, resorption, off-track Hill-Sachs
- Management
- CT to assess graft; revision with iliac crest graft if needed
- Incidence
- 1-8 percent (mostly neuropraxia)
- Risk Factors
- Retraction, drilling, screw placement
- Management
- Most resolve within 3-6 months; EMG if persistent
- Incidence
- 5-15 percent
- Risk Factors
- Prominent screw heads, thin soft tissue coverage
- Management
- Remove screws after graft union (typically 6 months)
- Incidence
- 5-10 percent
- Risk Factors
- Prolonged immobilisation, subscapularis over-tightening
- Management
- Physiotherapy; manipulation under anaesthesia if persistent beyond 6 months
- Incidence
- 20-30 percent at long-term follow-up
- Risk Factors
- Graft overhang, malrotation, residual instability
- Management
- Treat OA according to severity; may need arthroplasty
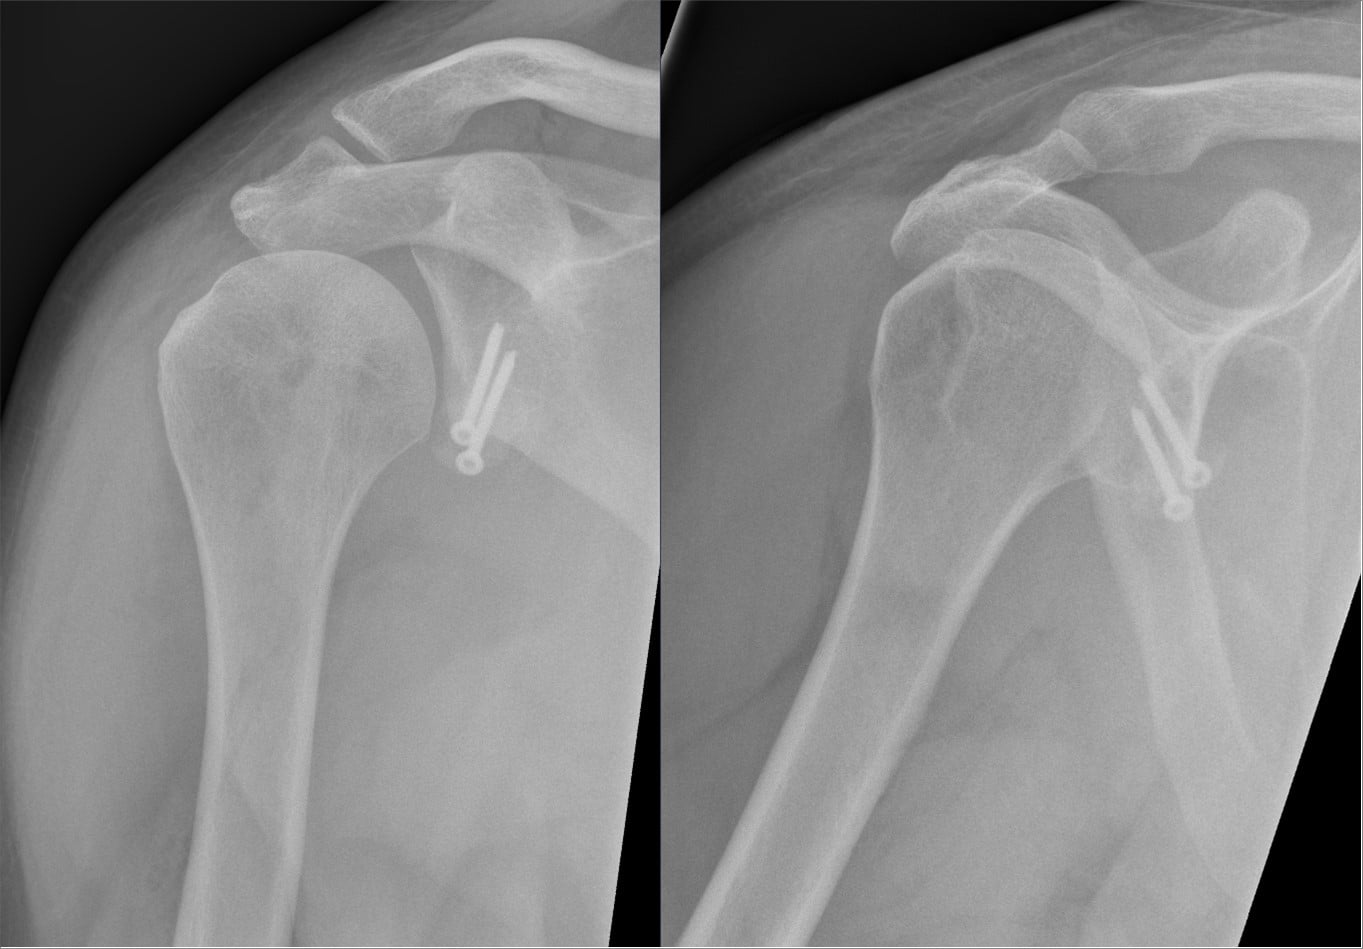
The axillary nerve is injured during retraction of the inferior capsule, or by a drill or screw penetrating the posterior glenoid neck. The musculocutaneous nerve is injured during medial retraction of the conjoint tendon or coracobrachialis; it enters coracobrachialis 5-8 cm distal to the coracoid tip. Both injuries are usually neuropraxias that resolve, but a permanent injury is catastrophic. Stay lateral to the conjoint tendon during dissection and use blunt retraction only.
Outcomes and Prognosis
- Short-term (Under 2 years)
- 1-3 percent
- Mid-term (2-5 years)
- 2-5 percent
- Long-term (Over 10 years)
- 5-8 percent
- Short-term (Under 2 years)
- 80-90 percent
- Mid-term (2-5 years)
- 75-85 percent
- Long-term (Over 10 years)
- Contact sport return approximately 70-80 percent
- Short-term (Under 2 years)
- 85-95 percent
- Mid-term (2-5 years)
- Stable after union
- Long-term (Over 10 years)
- Late resorption possible in some
- Short-term (Under 2 years)
- Significant improvement
- Mid-term (2-5 years)
- Maintained improvement
- Long-term (Over 10 years)
- Slight decline with OA changes
- Short-term (Under 2 years)
- Minimal new changes
- Mid-term (2-5 years)
- Mild changes in 10-20 percent
- Long-term (Over 10 years)
- Moderate-severe in 20-30 percent
Reading the figures. The 1-5% recurrence usually quoted for the Latarjet is a short- to mid-term number; beyond ten years it is 5-8%, and return to sport and patient-reported scores drift down over the same period as radiographic arthritis appears.
Who does well. A young patient having a primary bony procedure rather than a revision, with good bone quality and a graft positioned flush with the rim, and a contact athlete motivated for rehabilitation.
Who does badly. Revision surgery after several previous procedures, poor bone quality in an osteopenic coracoid, a medially malpositioned graft, post-operative stiffness, and the voluntary dislocator.
The trade-off. The Latarjet achieves the lowest recurrence rate of any instability procedure in the setting of bone loss, and pays for it with a higher complication rate than arthroscopic soft-tissue repair.
Guidelines, Registries and Global Practice
- Anterior shoulder dislocation is the commonest joint dislocation, with incidence peaking in males aged 20-30 years
- Recurrent instability rates vary: up to 90 percent in young male contact athletes, less than 20 percent in older low-demand patients
- Glenoid bone loss is present in the majority of recurrent dislocators undergoing surgical stabilisation
- Latarjet is the most performed bony procedure worldwide for instability with bone loss
- High-resource settings: CT-based 3D planning, patient-specific instrumentation, arthroscopic Latarjet in specialist centres
- Limited-resource settings: Open Latarjet with intra-operative fluoroscopy remains the standard; CT may not be available for pre-operative planning
- Universal principle: Graft position (flush with rim) and adequate fixation (two bicortical screws) are non-negotiable regardless of setting
- Rehabilitation protocols vary globally but the principle of protected immobilisation followed by progressive ROM is universal
- Indications Emphasis
- Greater than 25 percent bone loss or off-track Hill-Sachs; failed Bankart
- Technique Preference
- Open or arthroscopic Latarjet at surgeon discretion
- Key Recommendation
- CT mandatory before any bony procedure; report bone loss as percentage
- Indications Emphasis
- Bone loss assessment essential; Latarjet for inverted pear
- Technique Preference
- Open Latarjet preferred; arthroscopic in experienced centres
- Key Recommendation
- Multi-disciplinary discussion for borderline cases; shared decision-making
- Indications Emphasis
- Risk stratification based on bone loss, sport, and prior surgery
- Technique Preference
- Both open and arthroscopic Latarjet acceptable; remplissage considered for moderate bone loss
- Key Recommendation
- Discussion of OA risk and return-to-sport timeline essential for informed consent
- Indications Emphasis
- Principles of graft fixation: compression, stability, congruent position
- Technique Preference
- Technique focuses on precise graft positioning and bicortical fixation
- Key Recommendation
- Emphasise anatomical reduction of the graft flush with glenoid rim
There is no dedicated global registry specifically tracking Latarjet outcomes, though some national shoulder registries (Danish, Norwegian) capture instability procedures. The evidence base includes one landmark randomised trial (Bessiere et al.) plus multiple large case series and meta-analyses. The Walch-Lyon school in France holds the largest single-surgeon series with long-term follow-up. Current guidelines are consensus-based, drawing from Level 2-4 evidence.
Record in every Latarjet:
- Pre-operative bone loss measurement (percentage on CT) and Hill-Sachs classification (on-track vs off-track)
- Graft size and fixation method (screw diameter, bicortical confirmation)
- Intra-operative fluoroscopy confirming graft position flush with rim
- Any concern for nerve irritation or injury during the case
- Post-operative rehabilitation plan and return-to-sport timeline
A poorly positioned graft that requires revision is a major source of medicolegal claims. Document graft position with intra-operative imaging and clearly communicate rehabilitation restrictions.
Controversies and Areas of Uncertainty
No high-quality randomised trial has definitively shown superiority of one approach over the other. Arthroscopic Latarjet offers better visualisation and cosmesis but has a steep learning curve. Open Latarjet has longer track record and more outcome data. Current consensus: either approach is acceptable if performed by an experienced surgeon.
The management of borderline bone loss remains debated. Some advocate Latarjet for all contact athletes regardless of bone loss percentage, while others reserve it for confirmed inverted pear glenoids. The SMOOTH trial and similar studies are attempting to clarify this grey zone.
Arthroscopic remplissage (posterior capsulotenodesis to the Hill-Sachs defect) combined with Bankart repair may be an alternative to Latarjet in moderate bone loss. However, it does not address glenoid deficiency and may cause loss of external rotation. Its role is best defined for on-track Hill-Sachs with minimal glenoid bone loss.
Partial graft resorption is common on CT but its clinical significance is debated. Some studies show no correlation between partial resorption and instability recurrence, while others suggest it predisposes to failure. Complete resorption is rare but catastrophic.
The classic Latarjet fixes the coracoid with two cortical screws, but a modern alternative is cortical suture-button (EndoButton-type) fixation - worth knowing as it directly targets the screw-related complications:
- The screw construct: two parallel bicortical screws give strong compression and is the long-track-record standard, but screws cause many of the procedure's specific complications - graft fracture through the screw holes, hardware irritation/prominence, intra-articular or posterior screw penetration, and nerve injury from the drill/screw trajectory near the suprascapular/axillary nerves.
- The suture-button (Boileau guided-Latarjet) construct: the graft is held against the glenoid by a double cortical-button/suture loop passed through bone tunnels (no metal across the graft). It avoids screw-related graft fracture and hardware prominence and is favoured in the arthroscopic guided Latarjet.
- The trade-offs: button fixation provides less rigid compression at the graft-glenoid interface (relying more on the suture-loop and bone apposition), so concerns include graft positioning/healing and a different complication profile; comparative data show broadly similar union/recurrence with fewer hardware complications.
- The constant: whatever the fixation, the graft must sit flush with the rim and the construct must be stable enough for early protected motion.
Exam point: screws (two bicortical) are the standard but cause graft-fracture/hardware/nerve complications; suture-button fixation (the guided arthroscopic Latarjet) avoids metal across the graft at the cost of less rigid compression - both depend on a flush, well-positioned graft.
MCQ Practice Points
Q: What is the critical threshold of glenoid bone loss above which arthroscopic Bankart repair alone is contraindicated? A: Greater than 25 percent of the glenoid diameter (inverted pear glenoid). Below this, arthroscopic soft tissue repair has acceptable recurrence rates. Above this, bony augmentation (Latarjet) is the gold standard because the labrum and capsule have no stable rim to anchor to.
Q: What is the triple blocking effect of the Latarjet procedure? A: Bone block (coracoid graft replaces the deficient anteroinferior glenoid rim), sling effect (the conjoint tendon creates a dynamic sling that reinforces the anteroinferior capsule in abduction-external rotation), and capsular repair (the CA ligament remnant is used to reattach the capsule, restoring the labral bumper). This triple mechanism explains why Latarjet succeeds where Bankart fails in bone loss.
Q: Which nerve is at greatest risk during the Latarjet procedure and how do you protect it? A: The musculocutaneous nerve is at greatest risk. It enters the coracobrachialis muscle 5-8 cm distal to the coracoid tip. Protection requires: staying lateral to the conjoint tendon during dissection, using blunt retraction only (no sharp retractors medially), and avoiding excessive medial retraction of the coracobrachialis. The axillary nerve is also at risk during inferior capsular exposure and drill/screw penetration through the posterior glenoid neck.
Q: What is the most common technical error during the Latarjet procedure? A: Medial placement of the coracoid graft. The graft should be positioned flush with the glenoid rim (not medial on the glenoid neck). A medially placed graft does not restore the articular arc and fails to prevent anterior humeral head translation. Overly lateral placement (overhanging into the joint) causes early osteoarthritis.
Q: What is the incidence and significance of graft osteolysis after Latarjet? A: Partial graft resorption is common (up to 30 percent at 1 year on CT) but its clinical significance is debated. Most partial resorption does not cause recurrent instability. Complete graft resorption is rare but catastrophic, requiring revision with an alternative graft source (iliac crest bone graft or distal tibial allograft).
Q: When is an Eden-Hybinette iliac crest bone graft preferred over a Latarjet? A: When glenoid bone loss exceeds 35-40 percent, when the coracoid is insufficient (small, osteoporotic, or previously harvested), or in revision after a failed Latarjet with complete graft resorption. The iliac crest provides a larger bone block but does not include the dynamic sling effect of the conjoint tendon.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 24-year-old rugby player has sustained 5 anterior dislocations of his dominant right shoulder over 3 years. He had an arthroscopic Bankart repair 2 years ago but redislocated 6 months post-operatively during a tackle. A CT scan shows 30 percent anteroinferior glenoid bone loss with an inverted pear glenoid. There is an engaging Hill-Sachs lesion. What is your management?”
“A 30-year-old contact athlete underwent an open Latarjet procedure 8 weeks ago for recurrent anterior instability with 28 percent glenoid bone loss. At routine follow-up, he reports persistent tingling over the lateral forearm and weakness of elbow flexion. A CT scan shows the coracoid graft is positioned 5 mm medial to the glenoid rim with early signs of resorption at the superior screw. How do you manage this?”
Indications
- Glenoid bone loss greater than 25 percent (inverted pear on CT)
- Off-track (engaging) Hill-Sachs lesion
- Failed arthroscopic Bankart repair with bone loss
- Contact or collision athletes with recurrent instability and bone deficiency
- Revision anterior stabilisation surgery
Triple Blocking Effect
- Bone block: coracoid graft replaces deficient anteroinferior glenoid rim
- Sling effect: conjoint tendon creates dynamic reinforcement in ABER position
- Soft tissue repair: capsular reattachment to CA ligament remnant restores bumper
Key Surgical Steps
- Deltopectoral approach, identify and protect cephalic vein
- Osteotomise coracoid at base distal to coracoclavicular ligaments
- Preserve conjoint tendon attachment, release pectoralis minor medially
- Decorticate anterior glenoid neck, position graft flush with rim
- Fix with two parallel bicortical screws, confirm position with fluoroscopy
Complications
- Graft nonunion (5-15 percent), resorption (up to 30 percent partial), fracture (2-10 percent)
- Recurrence (1-5 percent) — usually from medial graft or resorption
- Musculocutaneous nerve (5-8 cm from coracoid tip) and axillary nerve at risk
- Hardware irritation (5-15 percent), late OA (20-30 percent at 10+ years)
Bristow vs Latarjet
- Bristow: coracoid tip with CA ligament, single screw — largely historical
- Latarjet: full coracoid flat on glenoid, two screws — current gold standard
- Congruent arc: coracoid rotated 90 degrees for better articular congruence
- Both create triple blocking effect but Latarjet provides larger bone block
Evidence Base and Key Trials
The open Latarjet procedure is more reliable in terms of shoulder stability than arthroscopic Bankart repair
- Prospective comparative study of arthroscopic Bankart versus open Latarjet in patients with recurrent anterior instability
- Open Latarjet group had significantly lower recurrence rate compared with arthroscopic Bankart group
- Better outcomes in Latarjet group for sport participation and patient-reported scores
- Higher complication rate in Latarjet group but most were minor and self-limiting
Long-Term Restoration of Anterior Shoulder Stability: A Retrospective Analysis of Arthroscopic Bankart Repair Versus Open Latarjet Procedure
- Retrospective comparison of arthroscopic Bankart repair versus open Latarjet at long-term follow-up
- Latarjet group had significantly lower recurrence rate compared with Bankart group
- Progression of osteoarthritis seen in a significant proportion at long-term follow-up
- Patient satisfaction remained high despite radiographic arthritis changes
A systematic review and meta-analysis of clinical and patient-reported outcomes following two procedures for recurrent traumatic anterior instability of the shoulder: Latarjet procedure vs. Bankart repair
- Systematic review and meta-analysis comparing Latarjet versus Bankart repair for recurrent anterior instability
- Pooled recurrence rate was significantly lower after Latarjet compared with Bankart repair
- Graft nonunion and hardware complications were the most common surgical complications of Latarjet
- Neurological injury was uncommon and typically transient
Complications and re-operations after Bristow-Latarjet shoulder stabilization: a systematic review
- Systematic review of 45 studies reporting complications after Bristow-Latarjet shoulder stabilization
- Overall complication rate was approximately 15-30 percent across all reported series
- Nerve injury (mostly neuropraxia) occurred in 1-8 percent of cases, with axillary and musculocutaneous nerves most commonly affected
- Hardware-related complications and graft nonunion were the most frequent indications for re-operation
Results of modified Latarjet reconstruction in patients with anteroinferior instability and significant bone loss
- Case series of modified Latarjet reconstruction in patients with anteroinferior instability and significant glenoid bone loss
- Excellent results with very low recurrence rate in patients with inverted pear glenoids
- Demonstrated that coracoid transfer effectively addresses instability in the setting of bone deficiency where soft tissue repair alone would fail
- Established the rationale for the congruent arc modification of the Latarjet technique