The Boxer's Muscle and the Scapula's Gliding Base
- The long thoracic nerve (C5, C6, C7 - Bell's nerve) is the sole motor supply; the C5 and C6 contributions pierce the middle scalene and the C7 contribution passes in front of it.
- The nerve runs 22 to 24 cm superficially on the OUTER surface of serratus anterior in the mid-axillary line, deep only to the deep fascia - the longest motor nerve in the upper limb relative to its calibre, and the most exposed.
- Serratus palsy causes MEDIAL winging: the whole medial border and the inferior angle lift and move medially, worst on forward flexion and the wall-push test, with the shoulder height normal or elevated.
- The inferior digitations from ribs 5 to 9 converging on the inferior angle are the powerful upward rotator - they give serratus the longest upward-rotation moment arm of any scapular muscle.
- Chronic irreparable palsy is treated by split pectoralis major (sternal head) transfer to the inferior angle, extended with a fascia lata or tendon graft.
- “The wall-push test loads FORWARD FLEXION, which is why it reveals serratus and not trapezius palsy - resisted coronal abduction is the trapezius test. Do both.
- “The long thoracic nerve is the classic casualty of axillary node dissection, first rib resection, chest drain insertion, and thoracoscopic port placement in the mid-axillary line.
- “Neuralgic amyotrophy (Parsonage-Turner) causes severe shoulder pain followed by painless winging days later; observe for 12 to 24 months before reconstructing - but 'it recovers on its own' overstates it. In 246 patients, two-thirds still had pain or paresis beyond three years.
- “In a serratus flap only the lower three or four digitations are taken, and the branches of the long thoracic nerve to the upper digitations are preserved - otherwise the donor wings.
Overview
Serratus anterior is a broad, fan-shaped muscle that wraps around the lateral chest wall from the upper eight or nine ribs to the whole costal surface of the medial border of the scapula. Its serrated origin gives it its name. Sandwiched between the ribs and the subscapularis, it is the gliding element of the scapulothoracic articulation.
Two jobs. It holds the scapula against the chest wall, which turns the scapulothoracic interface into a functional joint. It also protracts and upwardly rotates the scapula, delivering the reach of a punch (hence "the boxer's muscle") and roughly half of the total upward rotation needed for overhead elevation.
One anatomical fact explains the clinical problems. The motor nerve to serratus is the longest in the upper limb relative to its calibre, and the most superficially placed. The long thoracic nerve runs 22 to 24 cm down the lateral chest wall on the outer surface of the very muscle it supplies, protected by nothing but deep fascia. That course is why long thoracic palsy is by far the commonest cause of scapular winging, why it is a recognised complication of half a dozen unrelated operations, and why an examiner will always ask for the nerve's relationship to the middle scalene.
Attachments, Innervation and Relations
Origin. Fleshy digitations arise from the outer surfaces of the upper eight or nine ribs (ribs 1 to 8, commonly extending to rib 9) and the intervening intercostal fascia. The first digitation arises from both the first and second ribs and the fascia between them, so there are typically eight or nine digitations from nine or ten rib attachments. The lower four interdigitate with the origin of external oblique, a constant and much-loved detail that also marks the plane at which the lower digitations are separated during flap harvest.
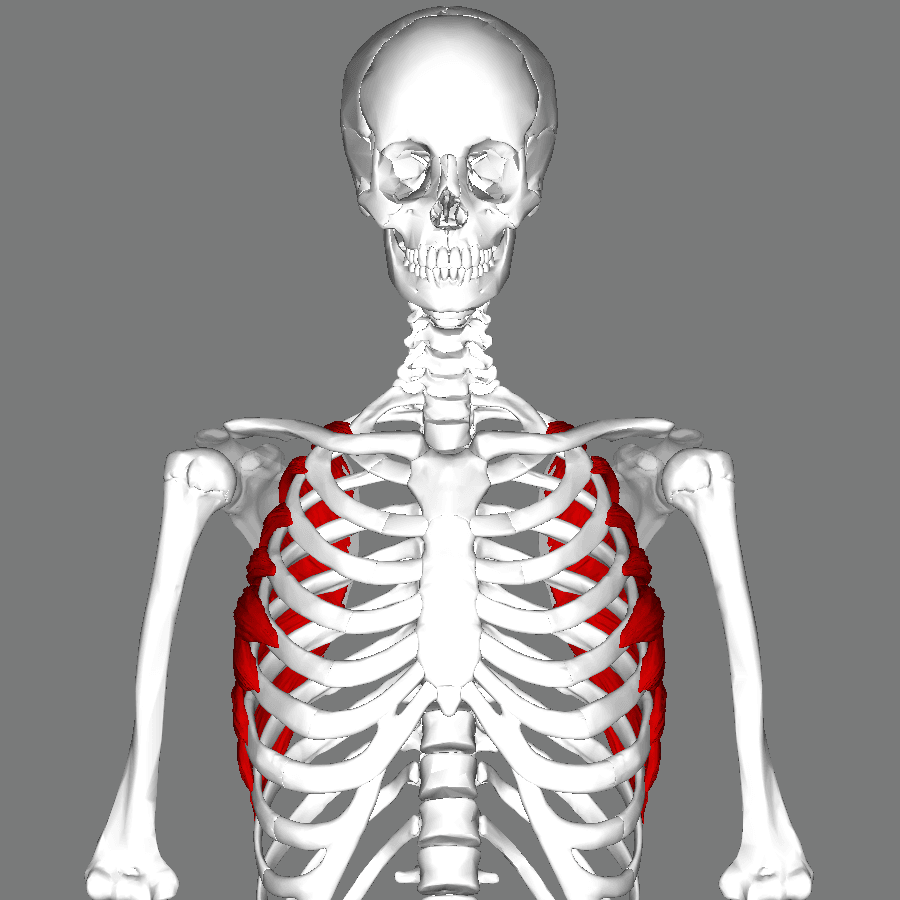
Insertion. Every part inserts on the costal (deep) surface of the medial border, but the three parts differ in size and role:
- Superior part - ribs 1 and 2 to a triangular impression on the costal surface of the superior angle
- Intermediate part - ribs 2 to 4, a thin sheet along the costal surface of the medial border
- Inferior part - ribs 5 to 9, converging as a thick, powerful fan onto the costal surface of the inferior angle. It carries most of the muscle mass and generates most of the rotation
Why the costal insertion matters. Because the whole insertion is on the rib-facing surface of the scapula, serratus pulls the medial border toward the chest wall as well as forward around it. That is why its failure produces a wing rather than merely weakness: nothing else holds the vertebral border down.
Fibre orientation. The fibres run posteriorly and medially around the chest wall, the upper fibres almost horizontally, the lower obliquely upward and backward to the inferior angle.
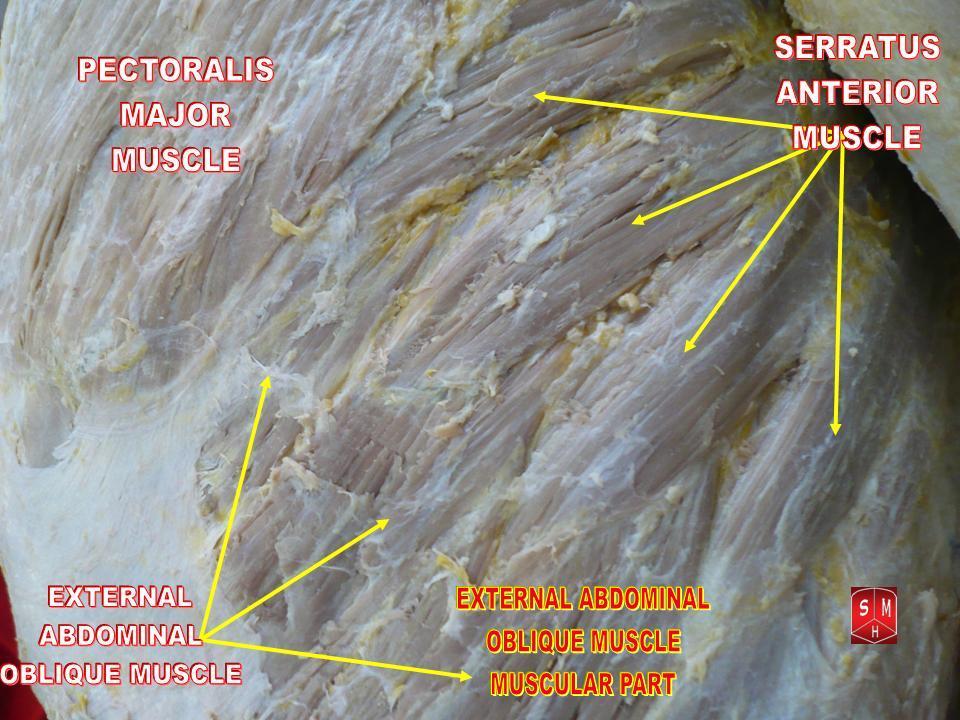
The long thoracic nerve descends on the outer surface of serratus anterior along the mid-axillary line, deep only to the deep fascia, from the second rib to the level of the ninth. Anything that cuts, cauterises, retracts or stretches in that line risks it; the operations and the manoeuvre that protects the nerve in each are set out under Surgical Relevance. Whenever the operation is in the axilla, name the nerve in the consent and identify it before you divide anything.
Action and Biomechanics
Scapulohumeral rhythm. Full arm elevation of about 180 degrees is produced by roughly 120 degrees of glenohumeral motion and 60 degrees of scapular upward rotation, the classical 2:1 rhythm. It is nearer 1:1 in the mid-range, with more glenohumeral motion early and late.
Where serratus fits. Its upward rotation comes from the inferior digitations, ribs 5 to 9, converging on the inferior angle. The inferior angle is the point furthest from the scapular rotation axis, so that insertion gives serratus the longest upward-rotation moment arm of any scapular muscle. The moment arm increases with elevation, making serratus a late-range rotator like the lower trapezius.
- Part Responsible
- Whole muscle, especially upper and intermediate
- Mechanism
- Draws the medial border forward around the chest wall
- Loss Produces
- Weak punching and pushing; loss of reach
- Part Responsible
- Inferior digitations to the inferior angle
- Mechanism
- Longest upward-rotation moment arm of any scapular muscle
- Loss Produces
- Loss of the last 50-70 degrees of elevation
- Part Responsible
- Inferior digitations
- Mechanism
- Pulls the inferior angle forward, tipping the acromion back
- Loss Produces
- Anterior acromial tilt and secondary subacromial impingement
- Part Responsible
- Whole muscle
- Mechanism
- Rotates the glenoid outward around a vertical axis
- Loss Produces
- Loss of glenoid orientation for the elevated arm
- Part Responsible
- Whole muscle, costal-surface insertion
- Mechanism
- Compressive vector toward the ribs
- Loss Produces
- MEDIAL winging - the hallmark sign
- Part Responsible
- Inferior digitations with the scapula fixed
- Mechanism
- Elevates the ribs
- Loss Produces
- Minor; not clinically significant in isolation
Tilt and external rotation. Serratus also tilts the scapula posteriorly and rotates it externally, both of which lift the anterior acromion away from the cuff. Without posterior tilt the acromion stays anteriorly tipped.
Excursion. Serratus is a long-excursion muscle: the scapula translates several centimetres around the curved chest wall. A transfer intended to substitute for it (pectoralis major to the inferior angle) therefore almost always needs a graft extension to reach with adequate excursion.
Force couples. Upper and lower trapezius are its synergists in upward rotation, pectoralis minor and major in protraction. The rhomboids and middle trapezius oppose it in retraction, and levator scapulae, the rhomboids, pectoralis minor and latissimus dorsi in downward rotation. The serratus-trapezius pair is the upward-rotation force couple and the serratus-rhomboid pair the protraction-retraction couple; serratus is the only muscle in both.
Rehabilitation follows the moment arm. Serratus activation exercises, protraction with the arm elevated (push-up plus, wall slides, serratus punch), target the inferior digitations specifically, because that is where the upward-rotation moment lives.
When it fails. Complete long thoracic palsy produces a characteristic sequence:
- Medial winging. With the medial border unanchored, it and the inferior angle lift off the chest wall and move medially, exaggerated by forward flexion or a wall push.
- A lost overhead arc. The scapula cannot upwardly rotate, so forward elevation is limited to about 90 to 120 degrees, and what remains is effortful because the deltoid has lost its stable base.
- Ache. The shoulder aches from the loss of a stable base, with a dragging pain at the medial border and at the trapezius as it over-works.
- Secondary problems. Subacromial impingement from the loss of posterior tilt, adhesive capsulitis in the neglected case, and traction brachial plexopathy in a minority.
- Cosmetic distress, often the loudest complaint: the scapula visibly stands off the chest wall under a shirt.
Surface Anatomy and Examination
Surface anatomy. With the arm forward-flexed to 90 degrees and pushed against resistance, the digitations become visible as an oblique series of finger-like ridges on the lateral chest wall below the axilla, interdigitating with external oblique: the classic sight in a lean athlete. The inferior angle and medial border are palpated from behind, and in serratus palsy they are lifted and can be hooked with the fingers.
Examine every winging pattern. The commonest diagnostic error is examining only one. A patient sent with "winging" needs the wall push (serratus), resisted abduction with the shrug (trapezius) and eccentric lowering (rhomboid), plus an assessment for a fixed bony wing.
The wall-push test is the definitive serratus test. The patient faces a wall at arm's length and pushes with both hands flat, elbows extended, at shoulder height, while the examiner stands behind and watches both medial borders and inferior angles. In serratus palsy the whole medial border and the inferior angle lift away from the chest wall and displace medially toward the spine. The test loads forward flexion, not abduction, which is why it finds serratus and not trapezius.
Resisted forward flexion is the alternative when no wall is available. The patient forward-flexes to 90 degrees and the examiner resists at the wrist while watching the scapula; medial winging appears and increases with load, and elevation fails beyond 90 to 120 degrees. It means the same as a positive wall push. Grade the winging by the gap between the inferior angle and the chest wall.
Resisted abduction is the control that identifies the other winging pattern. The patient abducts against resistance in the coronal plane and the shrug is tested as well. An inferior angle that rotates laterally, with a drooped shoulder and a weak shrug, is trapezius palsy: a completely different nerve (spinal accessory) and a completely different reconstruction.
Eccentric lowering finds the subtle third pattern. The patient lowers both arms slowly from full forward flexion while the examiner watches from behind. A subtle medial border lift with lateral scapular drift on the descent, with a normal shrug and a normal wall push, is rhomboid insufficiency from a dorsal scapular nerve lesion.
Grading and documentation. Record the maximum active forward flexion in degrees, the distance in centimetres between the inferior angle and the chest wall at maximum wing, and whether the winging is present at rest or only on loading. Photograph or video the resting posture and the wall push: serial images are the only reliable way to demonstrate the slow recovery of a neurapraxic long thoracic palsy.
Pitfalls. Not every wing is a serratus palsy, and not every serratus palsy is alone:
- Pain-inhibited pseudo-winging after any painful shoulder condition; re-examine after an interscalene or subacromial block if pain is limiting
- Voluntary winging in the hypermobile adolescent - reproducible, painless, and abolished by distraction
- Bony pseudo-winging from a scapular osteochondroma or exostosis, a malunited scapular or rib fracture, or an elastofibroma - the wing is fixed rather than dynamic
- Missing the second palsy. Neuralgic amyotrophy is patchy; always test the trapezius, the rhomboids, supraspinatus and infraspinatus, and the anterior interosseous nerve as well
- Serratus (long thoracic)
- Medially
- Trapezius (spinal accessory)
- Laterally
- Rhomboid (dorsal scapular)
- Slightly laterally
- Serratus (long thoracic)
- Forward flexion / wall push
- Trapezius (spinal accessory)
- Resisted coronal abduction
- Rhomboid (dorsal scapular)
- Slow eccentric lowering
- Serratus (long thoracic)
- Normal or elevated
- Trapezius (spinal accessory)
- Drooped
- Rhomboid (dorsal scapular)
- Normal
- Serratus (long thoracic)
- Normal
- Trapezius (spinal accessory)
- Weak, flat trapezial ridge
- Rhomboid (dorsal scapular)
- Normal
- Serratus (long thoracic)
- Gross and obvious
- Trapezius (spinal accessory)
- Moderate
- Rhomboid (dorsal scapular)
- Subtle
- Serratus (long thoracic)
- Neuralgic amyotrophy, axillary surgery, chest drain, backpack, traction
- Trapezius (spinal accessory)
- Posterior triangle node biopsy, neck dissection
- Rhomboid (dorsal scapular)
- Middle scalene entrapment, C5 lesion, interscalene block
- Serratus (long thoracic)
- Split pectoralis major to the inferior angle with a graft
- Trapezius (spinal accessory)
- Eden-Lange transfer
- Rhomboid (dorsal scapular)
- Rarely reconstructed; treat the cause
Complications
Iatrogenic long thoracic nerve injury. Transection, diathermy, traction or compression along the mid-axillary line, or needle injury in the middle scalene, produces medial winging with loss of overhead elevation, secondary impingement and, in the neglected case, adhesive capsulitis. It is avoided by identifying and preserving the nerve at axillary dissection, siting chest ports away from the mid-axillary line, using an adequate axillary roll, and using ultrasound guidance for blocks without injecting into the substance of the middle scalene.
Complications of pectoralis major transfer. Recurrent winging is the recognised failure; the full list:
- Recurrent winging - reported after non-compliance with the postoperative regimen and associated with inadequate tensioning of the graft-tendon construct
- Fixation failure at the inferior angle, particularly in osteopenic bone; use multiple drill holes and a robust suture
- Loss of adduction and internal rotation power from the sternal head harvest - relevant to a manual worker or a climber, and a consent point
- Chest wall haematoma and seroma in the tunnel
- Pneumothorax if the tunnel or the inferior angle drill holes are made carelessly
- Persistent pain where the original problem included cuff disease or a cervical driver that was never treated
The complications of scapulothoracic fusion and of serratus flap harvest are set out with those operations above.
Clinical Relevance
Neuralgic amyotrophy (Parsonage-Turner syndrome) is the commonest single cause. Severe continuous pain, lasting around four weeks on average, is followed by painless weakness as the pain settles. It is frequently patchy and multifocal: long thoracic and/or suprascapular involvement in the upper and middle trunk distribution is the commonest pattern, at 71 per cent, and it often follows a viral illness, immunisation or surgery.
Other non-traumatic causes. Neuralgic amyotrophy aside, consider:
- Viral illness without frank neuralgic amyotrophy
- Repetitive activity - overhead sport, tennis, weightlifting and occupational overhead work
- Idiopathic, a genuine category after careful evaluation
Traumatic and positional. Ask about injury and posture:
- Traction injury - forced depression of the shoulder with the head bent to the opposite side; falls; road traffic collisions
- Heavy backpack or shoulder strap compression at the second rib
- Prolonged general anaesthesia in the lateral decubitus position with an inadequate axillary roll
Iatrogenic. Axillary lymph node dissection and mastectomy are the classic surgical cause. The rest of the list:
- First rib resection and scalenectomy for thoracic outlet syndrome
- Chest drain insertion and thoracoscopic port placement in the mid-axillary line
- Thoracotomy, latissimus dorsi flap harvest and transaxillary approaches
- Interscalene and supraclavicular block - the C5 and C6 contributions run in the middle scalene, so needle injury there is possible
Winging that is not a palsy must be excluded. Bony pseudo-wings and pain-inhibited winging are covered under the examination pitfalls; glenohumeral instability and painful cuff disease also produce a dyskinetic pseudo-winging. Facioscapulohumeral muscular dystrophy is bilateral, with facial and humeral involvement, and the trapezius and rhomboids are affected as well.
Surgical Relevance
Protecting the nerve
- Where the Nerve Lies
- On the chest wall in the mid-axillary line, deep to the axillary fascia, over ribs 2 to 5
- Protective Manoeuvre
- Identify the nerve on the serratus surface at the start; keep the dissection lateral to it and preserve it with its fascial covering
- Where the Nerve Lies
- Passing over the outer border of the first rib to reach serratus
- Protective Manoeuvre
- Retract gently; avoid diathermy on the medial chest wall; identify the nerve before rib division
- Where the Nerve Lies
- Mid-axillary line from the second rib downward
- Protective Manoeuvre
- Site ports anterior or posterior to the mid-axillary line where the operation allows; use blunt entry
- Where the Nerve Lies
- Directly beneath the insertion site in the mid-axillary line
- Protective Manoeuvre
- Blunt dissection, finger sweep, no sharp instrument beyond the pleura
- Where the Nerve Lies
- Immediately posterior to the serratus branch of the thoracodorsal artery
- Protective Manoeuvre
- Separate the serratus branch from the nerve under magnification; preserve the nerve
- Where the Nerve Lies
- Compressed against the chest wall by body weight
- Protective Manoeuvre
- Adequate axillary roll placed caudal to the axilla; regular position checks in long cases
- Where the Nerve Lies
- C5-C6 contributions within the middle scalene
- Protective Manoeuvre
- Ultrasound guidance; avoid injecting into the substance of the middle scalene
Nerve surgery
Neurolysis is described for a nerve found tethered at the middle scalene or beneath a fascial band at the second rib, in a patient whose recovery has reached a plateau on serial EMG.
Nerve transfer is an option for a documented complete lesion with no reinnervation at 6 to 12 months, before muscle degeneration is irreversible. Thoracodorsal to long thoracic transfer is the best described; medial pectoral nerve transfer and intercostal nerve transfer have also been used. Transfer is only worthwhile while serratus remains reinnervable, and that window closes at about 12 to 18 months. Beyond it, the operation is a tendon transfer, not a nerve operation.
Pectoralis major transfer for chronic irreparable palsy
Indications. The case for transfer:
- Symptomatic winging with functional limitation, persisting beyond 12 to 24 months with no reinnervation on serial EMG
- Preserved passive scapular and glenohumeral motion - a stiff shoulder must be mobilised first
- An intact, innervated pectoralis major (medial and lateral pectoral nerves; confirm on examination)
- A patient who understands that this is a stabilisation, not a restoration of normal serratus function
Why pectoralis major. The sternal head has a line of pull that runs anteriorly and medially across the chest wall to the inferior angle, closely approximating the vector of the inferior serratus digitations. It has sufficient power, and it is expendable in the sense that the clavicular head is retained. Split transfer with the clavicular head retained is the standard; taking the entire muscle is unnecessary and costs adduction power.
The serratus anterior flap
What is taken. Only the lower three or four digitations (from ribs 5 to 8 or 9), based on the serratus branch of the thoracodorsal artery from the subscapular system. These digitations are thin, pliable and well vascularised, ideal for contouring over irregular surfaces.
The critical technical point. The serratus branch runs parallel to and immediately anterior to the long thoracic nerve on the surface of the muscle, so harvest requires the two to be separated under magnification, and the nerve branches to the upper digitations must be preserved. Taking the upper digitations, or dividing the nerve above the level of the harvest, produces a donor-site winging scapula: a complication that is entirely avoidable and entirely the surgeon's fault.
Approach. A lateral chest wall incision along the anterior border of latissimus dorsi, with the arm abducted. Latissimus is retracted posteriorly, the thoracodorsal pedicle identified in the axilla, and the serratus branch traced distally onto the muscle. The chosen digitations are detached from the ribs, taking care of the intercostal perforators and of the pleura immediately deep to the rib origins.
Applications. The flap's uses:
- Free flap for coverage of the foot, hand and scalp, where a thin, pliable, well-contoured muscle flap is needed
- Pedicled flap for the chest wall, axilla and shoulder
- Chimeric flap with latissimus dorsi, scapular or parascapular skin, and rib, all on a single subscapular pedicle - the workhorse of complex composite reconstruction
- Functional muscle transfer, transplanted with its nerve branch and neurotised, for facial reanimation and for restoring elbow or finger flexion
- Serratus fascia flap - the fascia alone, for very thin coverage such as the dorsum of the hand
Guidelines, Registries & Global Practice
Anatomical variation
- The nerve most often has three root contributions (C5, C6, C7), but a C8 contribution is described in a minority, and the C7 contribution is occasionally absent.
- The relationship to the middle scalene varies: the C5 and C6 contributions usually pierce the muscle, but either may pass anterior or posterior to it, which affects both entrapment and the safety of a needle placed in the muscle substance.
- The number of digitations varies between eight and ten, and the extent of interdigitation with external oblique varies.
- The thoracodorsal-to-serratus branching point varies over several centimetres, which matters for pedicle length in flap planning and is worth confirming with pre-operative imaging or Doppler in a complex case.
Practice framing across bodies
- Position Relevant to Serratus Anterior and the Long Thoracic Nerve
- Prolonged non-operative management with serial electrodiagnostics before considering transfer; pectoralis major transfer is the accepted reconstruction for chronic irreparable palsy.
- Position Relevant to Serratus Anterior and the Long Thoracic Nerve
- Recommend early recognition and referral of scapular winging, with maintenance of passive range as the priority during observation.
- Position Relevant to Serratus Anterior and the Long Thoracic Nerve
- Identification and preservation of the long thoracic nerve is a standard step of axillary lymph node dissection and is documented in the operative record.
- Position Relevant to Serratus Anterior and the Long Thoracic Nerve
- Chest drains and thoracoscopic ports should be placed with awareness of the mid-axillary course of the nerve; blunt entry technique is standard.
- Position Relevant to Serratus Anterior and the Long Thoracic Nerve
- Serratus flap harvest is limited to the lower digitations with preservation of the long thoracic nerve branches to the upper digitations.
Resource-dependent practice
- Well-resourced settings: serial quantitative EMG, MR neurography, nerve transfer within the reinnervation window, and Achilles allograft for the pectoralis major extension.
- Limited-resource settings: the diagnosis is entirely clinical if all three winging patterns are examined; autologous fascia lata is an excellent and freely available graft for the pectoralis major transfer; scapulothoracic fusion requires only cerclage wire and a plate. The determinant of outcome is patient selection and construct tension, not the graft material.
Epidemiology and global framing
- Neuralgic amyotrophy is the commonest non-iatrogenic cause worldwide and is likely under-diagnosed; the characteristic history of severe pain preceding weakness is the diagnostic key.
- Iatrogenic injury after axillary surgery has fallen with the shift from routine axillary clearance to sentinel node biopsy in breast cancer, but remains the commonest surgical cause.
- There are no registries and no randomised trials in this field; recommendations rest on consistent case series and on anatomy. That consistency is itself the message: observe long, examine all three patterns, and if you reconstruct, tension the graft properly.
MCQ Practice Points
Q: What supplies serratus anterior, and from which roots? A: The long thoracic nerve (nerve of Bell), C5, C6 and C7, arising directly from the ventral rami in the neck.
Q: What is the relationship of the long thoracic nerve to the middle scalene? A: The C5 and C6 contributions pierce the middle scalene; the C7 contribution passes anterior to it.
Q: Where does the nerve run in the chest wall? A: On the OUTER (superficial) surface of serratus anterior in the mid-axillary line, deep only to the deep fascia, for approximately 22 to 24 cm.
Q: From which ribs does serratus anterior arise? A: The outer surfaces of the upper eight or nine ribs, the first digitation arising from both the first and second ribs.
Q: On which surface of the scapula does it insert? A: The COSTAL (deep) surface of the medial border, from the superior to the inferior angle - which is why its loss produces winging.
Q: Which way does the scapula wing in serratus palsy? A: Medially, with the inferior angle moving toward the spine, provoked by forward flexion and the wall-push test, with normal shoulder height.
Q: Which digitations produce most of the upward rotation? A: The inferior digitations from ribs 5 to 9 converging on the inferior angle - the longest upward-rotation moment arm of any scapular muscle.
Q: What is the pedicle of the serratus anterior flap? A: The serratus branch of the thoracodorsal artery, from the subscapular system. It runs parallel and immediately anterior to the long thoracic nerve.
Q: What is the reconstruction for chronic irreparable serratus palsy? A: Split pectoralis major (sternal head) transfer to the inferior angle, extended with a fascia lata, hamstring or Achilles allograft.
Q: How long do you observe a long thoracic palsy before reconstructing? A: 12 to 24 months with serial EMG, unless the nerve is known to have been divided. Nerve transfer, if considered, must be done within about 12 to 18 months.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 32-year-old man had two weeks of severe left shoulder and neck pain that woke him at night. The pain has settled but now his shoulder blade sticks out and he cannot lift his arm above shoulder height. How do you assess and manage him?”
“The same patient returns two years later. There is still gross medial winging, forward flexion is limited to 100 degrees, EMG shows no reinnervation and the muscle is fatty on MRI. Passive movement is full. What do you offer?”
“You are asked to raise a free serratus anterior flap for coverage of a degloved dorsum of the foot. Describe the anatomy you rely on and how you avoid a winging donor.”
Anatomy
- Origin: outer surfaces of the upper 8-9 ribs, first digitation from ribs 1 and 2
- Insertion: costal surface of the medial border, superior to inferior angle
- Nerve: long thoracic (Bell's), C5-C6-C7
- Blood: lateral thoracic artery (upper), serratus branch of thoracodorsal (lower)
Nerve Course
- C5 and C6 pierce middle scalene; C7 passes anterior to it
- Crosses the first or second rib into the axilla
- Descends 22-24 cm on the OUTER surface of serratus in the mid-axillary line
- Deep only to deep fascia - the most exposed motor nerve in the limb
Clinical
- Medial winging - inferior angle moves toward the spine
- Wall-push test; forward flexion limited to 90-120 degrees
- Causes: neuralgic amyotrophy, axillary surgery, chest drain, traction, backpack
- Observe 12-24 months, keep passive range - but two-thirds have residual pain or paresis at 3 years
Surgical
- Nerve transfer (thoracodorsal to long thoracic) within about 12-18 months
- Chronic: split pectoralis major sternal head to inferior angle with a graft
- Salvage: scapulothoracic fusion, losing terminal elevation
- Flap: lower 3-4 digitations on the serratus branch; preserve the nerve to the upper digitations
Evidence Base
Split Pectoralis Major Transfer for Serratus Anterior Palsy
- Eleven consecutive patients, mean age 34 years, with symptomatic winging from serratus anterior palsy and preoperative symptoms of 12 to 60 months
- Ten had electromyograms documenting a long thoracic nerve injury
- Through an inferior axillary incision the sternal head of pectoralis major was mobilised and transferred to the inferior angle of the scapula, reinforced with autogenous fascia lata
- A scapulothoracic orthosis was worn for 6 weeks and vigorous activity restricted for 6 months
- At a mean of 41 months, 10 of 11 (91 per cent) had satisfactory results; the single failure was a full recurrence of winging attributed to non-compliance with rehabilitation
Results of Pectoralis Major Transfer with Fascia Lata Autograft Augmentation for Scapular Winging
- 15 patients, mean age 32.8 years, reviewed at a mean of 64 months after pectoralis major transfer with fascia lata autograft for scapular winging
- Pain decreased in 11 patients and function improved in 10; 12 said they would undergo the procedure again
- By the Rowe score results were excellent in 2, good in 5, fair in 4 and poor in 4
- The four scores the paper actually reports sit close together and all in the middling band: mean Rowe 66 (41-92), Constant-Murley 74 (32-95), Simple Shoulder Test 8 of 12 positive responses and ASES 63 (10-87)
- Better results occurred in patients achieving at least 60 degrees of postoperative external rotation
- Complete relief of pain and full function were not always achieved, though most returned to their preoperative activity level with minor adaptations
The Clinical Spectrum of Neuralgic Amyotrophy in 246 Cases
- 246 patients studied, 199 with idiopathic and 47 with hereditary neuralgic amyotrophy
- Pain runs in three consecutive phases, beginning with severe continuous pain lasting about 4 weeks on average; sensory involvement was present in 78.4 per cent
- The disorder is typically patchy; upper and middle trunk involvement affecting the long thoracic and/or suprascapular nerve was commonest, at 71.1 per cent
- Recurrent attacks occurred in 26.1 per cent of idiopathic cases over a mean 6-year follow-up
- Overall recovery was LESS favourable than usually assumed, with persisting pain and paresis in approximately two-thirds of patients followed for 3 years or more
Long Thoracic Nerve - Anatomy and Functional Assessment
- Fifteen fresh cadavers dissected, with intra-operative electrical stimulation in six patients undergoing brachial plexus surgery
- The long thoracic nerve was formed by branches from the C5, C6 and C7 roots
- The C5 and C6 branches joined BENEATH the scalenus medius to form an upper division lying 1 cm posterior and superior to the origin of the upper trunk; union with the C7 branch occurred caudally in the axillary region
- Two branches from the upper division to the upper serratus anterior were consistently identified, and stimulating them produced shoulder protraction
- In the supraclavicular region the nerve runs parallel to the brachial plexus, contrary to most textbook schematics
The Serratus Anterior Free-Muscle Flap - Experience with 100 Consecutive Cases
- 100 consecutive free serratus transplantations, 10 combined with latissimus dorsi and 2 with rib
- Overall success was 99 per cent with a single flap failure and four partial losses
- Significant complications occurred at 18 per cent of recipient sites and 12 per cent of donor sites, with eight seromas or haematomas
- NO scapular winging occurred and all patients retained full shoulder range of movement
- The flap has a consistently long pedicle and multipennate, malleable anatomy, and underlying rib can be included as a myo-osseous flap
Scapulothoracic Fusion for Facioscapulohumeral Muscular Dystrophy
- Eleven scapulothoracic fusions in eight patients with infantile and adolescent facioscapulohumeral muscular dystrophy, mean age 17 years
- The scapula was fused in 25 degrees of abduction using 16-gauge wires with a plate or washers to prevent wire pull-out, plus iliac crest autograft
- Winging, shoulder fatigue and pain were eliminated in every case; abduction improved from a mean of 75 to 145 degrees and flexion to 144 degrees
- At a mean of 6.3 years seven shoulders held a mean of 139 degrees abduction and 134 degrees flexion, but in the remaining four both had fallen to a mean of 48 degrees because of progressive loss of deltoid strength
- The only complication was prominent subcutaneous wires requiring trimming in two cases